
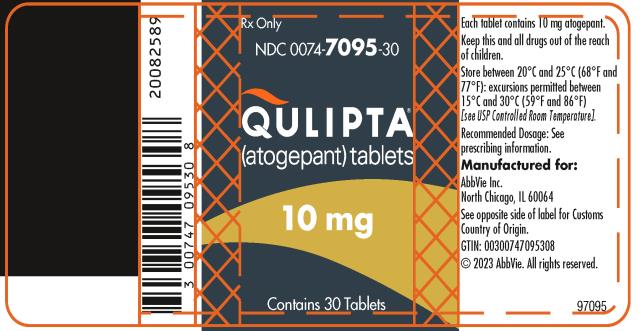
Qulipta Atogepant 10 mg Tablet, 30-count — NDC 0074-7095-30 (Billing 00074-7095-30)
This is a package of 30 tablets of Qulipta Atogepant 10 mg Tablet from AbbVie Inc., marketed since Sep 2021 and currently FDA-listed; retail pharmacies pay about $38.36 per tablet (NADAC). It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 0074-7095-30 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0074 labeler · 7095 product · 30 package
- Package marketed since
- Sep 30, 2021
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Billing quantity
- 30 EA per package
- Barcode (UPC)
- 0300747096305, 0300747094301
- Medicaid fills, this package
- 4,764 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 082700
- GCN: 51231
- GPI-14 (Medi-Span): 67701010000310
- HICL (First Databank): 047599
- AHFS class code: 28:32.12.00
- RxCUI (RxNorm): 2571836
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Calcitonin Gene-related Peptide Receptor Antagonist class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Atogepant is used to prevent migraine headaches (severe, throbbing headaches that sometimes are accompanied by nausea and sensitivity to sound or light). Atogepant is in a class of medications called calcitonin gene-related peptide receptor antagonists. It works by blocking the action of a certain natural substance in the body that causes migraine headaches.
Read the full MedlinePlus article ↗- It helps prevent migraine in adults. You take it regularly, including for episodic or chronic migraine, rather than using it once a migraine has started.
- Qulipta is a tablet you take by mouth once a day. You can take it with or without food. Your prescriber will set the right amount for you, so follow their directions.
- The most common are nausea, constipation, and feeling tired or sleepy. Tell your pharmacist or doctor if they bother you or don't ease up.
- Get emergency help for trouble breathing, facial swelling, hives, or a serious rash, since these can be allergic reactions. Call your doctor if you notice higher blood pressure or...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Atogepant — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $38.358 | $1,150.75 / 30 tablets |
| Medicaid paysCMS SDUD · 12 mo | $37.38 | $1,121.42 / 30 tablets |
| Medicare drug plans payPart D · Q2 2026 | $38.69 | $1,160.81 / 30 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Oct 7, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00074-7095-30 You're viewing this Main listing | 30 TABLET in 1 BOTTLE | 2021-09-30 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Qulipta 10 mgthis 00074-7095-30 | AbbVie | 30 tablets | $38.358 | — | Availability likely | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Oct 7, 2026
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 12383545 ↗ | Method of use | U-3534 | Jun 6, 2039 |
| US 12090148 ↗ | Method of use | U-3534 | Jul 29, 2041 |
| US 12090148 ↗ | Method of use | U-3534 | Jul 29, 2041 |
| US 12350259 ↗ | Method of use | U-4234 | Feb 27, 2043 |
| US 12383545 ↗ | Method of use | U-3534 | Jun 6, 2039 |
| US 12383545 ↗ | Method of use | U-3534 | Jun 6, 2039 |
| US 12465598 ↗ | Method of use | U-4355 | Sep 27, 2042 |
| US 9499545 ↗ | Drug substance | U-3534 | Nov 10, 2031 |
| US 9499545 ↗ | Drug substance | U-3534 | Nov 10, 2031 |
| US 9499545 ↗ | Drug substance | U-3534 | Nov 10, 2031 |
| US 8754096 ↗ | Drug substance | U-3534 | Sep 28, 2035 |
| US 8754096 ↗ | Drug substance | U-3534 | Sep 28, 2035 |
| US 8754096 ↗ | Drug substance | U-3534 | Sep 28, 2035 |
| US 12090148 ↗ | Method of use | U-3534 | Jul 29, 2041 |
| US 12622897 ↗ | Method of use | U-4536 | Sep 27, 2042 |
| US 12622897 ↗ | Method of use | U-4536 | Sep 27, 2042 |
| US 9850246 ↗ | Drug substance | — | Mar 13, 2033 |
| US 9850246 ↗ | Drug substance | — | Mar 13, 2033 |
| US 9850246 ↗ | Drug substance | — | Mar 13, 2033 |
| US 10117836 ↗ | Drug product | — | Jan 30, 2035 |
| US 10117836 ↗ | Drug product | — | Jan 30, 2035 |
| US 10117836 ↗ | Drug product | — | Jan 30, 2035 |
| Code | What it grants | Expires |
|---|---|---|
| I-909 | New indication (3-year) | Apr 17, 2026 |
| NCE | New Chemical Entity (5-year) | Sep 28, 2026 |
| I-909 | New indication (3-year) | Apr 17, 2026 |
| NCE | New Chemical Entity (5-year) | Sep 28, 2026 |
| I-909 | New indication (3-year) | Apr 17, 2026 |
| NCE | New Chemical Entity (5-year) | Sep 28, 2026 |
Is there a generic version of QULIPTA 10 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Atogepant inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII D9C330MD8B
Copovidone is a synthetic polymer made by combining two types of plastic-like molecules. It acts as a binder and film-former to help hold tablet ingredients together and improve how the medicine dissolves in your body.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
UNII 7CV7WJK4UI
Sodium stearyl fumarate is a synthetic compound made from stearyl alcohol and fumaric acid. It acts as a lubricant and glidant in tablets and capsules, helping ingredients flow smoothly during manufacturing and preventing sticking.
-
UNII O03S90U1F2
A synthetic compound combining vitamin E with polyethylene glycol and succinic acid. It acts as a solubilizer and antioxidant in medicines, helping dissolve poorly water-soluble drugs and prevent degradation of active ingredients.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 8, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from AbbVie Inc. labeler code 00074
- Synthroid Levothyroxine Sodium 150 ug Tablet NDC 0074-7069-11
- Synthroid Levothyroxine Sodium 175 ug Tablet NDC 0074-7070-19
- atogepant 10 mg Tablet NDC 0074-7091-00
- atogepant 30 mg Tablet NDC 0074-7092-00
- atogepant 60 mg Tablet NDC 0074-7093-00
- Qulipta Atogepant 60 mg Tablet NDC 0074-7094-04
- Qulipta Atogepant 30 mg Tablet NDC 0074-7096-04
- VUITY Pilocarpine Hydrochloride 12.5 mg/mL Solution/ Drops NDC 0074-7098-01
- Synthroid Levothyroxine Sodium 200 ug Tablet NDC 0074-7148-11
- Synthroid Levothyroxine Sodium 300 ug Tablet NDC 0074-7149-19
- Depakote Divalproex Sodium 125 mg Tablet, Delayed Release NDC 0074-7325-13
- Depakote Divalproex Sodium 250 mg Tablet, Delayed Release NDC 0074-7326-13
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE QULIPTA is indicated for the preventive treatment of migraine in adults. QULIPTA is a calcitonin gene-related peptide receptor antagonist indicated for the preventive treatment of migraine in adults. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION QULIPTA is taken orally with or without food. ( 2.1 ) For episodic migraine, the recommended dosage is 10 mg, 30 mg, or 60 mg taken once daily. ( 2.1 ) For chronic migraine, the recommended dosage is 60 mg taken once daily. ( 2.1 ) Severe Renal Impairment or End-Stage Renal Disease ( 2.2 , 8.6 ): Episodic migraine: 10 mg once daily. Chronic migraine: Not recommended.
2.1Recommended Dosage QULIPTA is taken orally with or without food. Episodic Migraine The recommended dosage of QULIPTA for episodic migraine is 10 mg, 30 mg, or 60 mg taken once daily. Chronic Migraine The recommended dosage of QULIPTA for chronic migraine is 60 mg taken once daily.
2.2Dosage Modification s Dosage modifications and usage recommendations for episodic and chronic migraine with concomitant use of specific drugs and for patients with renal impairment are provided in Table 1. Table 1 : Dos age Modifications for Drug Interactions and for Specific Populations Dosage Modifications Recommended Once Daily Dosage for Episodic Migraine Usage and Recommended Once Daily Dosage for Chronic Migraine Concomitant Drug [see Drug Interactions ( 7 )] Strong CYP3A4 Inhibitors ( 7.1 ) 10 mg 10 mg Strong CYP3A4 Inducers ( 7.2 ) 60 mg a Not recommended Moderate CYP3A4 Inducers ( 7.2 ) 60 mg Not recommended Weak CYP3A4 Inducers ( 7.2 ) 30 mg or 60 mg 60 mg a OATP Inhibitors ( 7.3 ) 10 mg or 30 mg 30 mg Renal Impairment [see Use in Specific Populations ( 8 )] Severe Renal Impairment and End-Stage Renal Disease (CLcr <30 mL/min) ( 8.6 ) 10 mg Not recommended a Coadministration decreases atogepant exposure.
Monitor for reduced efficacy.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS QULIPTA 10 mg is supplied as white to off-white, round biconvex tablets debossed with “A” and “10” on one side. QULIPTA 30 mg is supplied as white to off-white, oval biconvex tablets debossed with “A30” on one side. QULIPTA 60 mg is supplied as white to off-white, oval biconvex tablets debossed with “A60” on one side. Tablets: 10 mg, 30 mg, and 60 mg. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS QULIPTA is contraindicated in patients with a history of hypersensitivity to atogepant or any of the components of QULIPTA. Reactions have included anaphylaxis and dyspnea [see Warnings and Precautions ( 5.1 )] . Patients with a history of hypersensitivity to atogepant or to any of the components of QULIPTA. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hypersensitivity Reactions: If a hypersensitivity reaction occurs, discontinue QULIPTA and initiate appropriate therapy. Severe hypersensitivity reactions have included anaphylaxis and dyspnea. These reactions can occur days after administration.
( 5.1 ) Hypertension: New-onset or worsening of pre-existing hypertension may occur. ( 5.2 ) Raynaud’s phenomenon: New-onset or worsening of pre-existing Raynaud’s phenomenon may occur. ( 5.3 )
5.1Hypersensitivity Reactions Hypersensitivity reactions, including anaphylaxis, dyspnea, rash, pruritus, urticaria, and facial edema, have been reported with use of QULIPTA [see Adverse Reactions ( 6.2 )] . Hypersensitivity reactions can occur days after administration. If a hypersensitivity reaction occurs, discontinue QULIPTA and institute appropriate therapy [see Contraindications ( 4 )] .
5. 2 Hyper tension Development of hypertension and worsening of pre-existing hypertension have been reported following the use of CGRP antagonists, including QULIPTA, in the postmarketing setting. Some of the patients who developed new-onset hypertension had risk factors for hypertension.
There were cases requiring initiation of pharmacological treatment for hypertension and, in some cases, hospitalization. Hypertension may occur at any time during treatment, but was most frequently reported within 7 days of therapy initiation. QULIPTA was discontinued in many of the reported cases.
Monitor patients treated with QULIPTA for new-onset hypertension, or worsening of pre-existing hypertension, and consider whether discontinuation of QULIPTA is warranted if evaluation fails to establish an alternative etiology or blood pressure is inadequately controlled. 5. 3 Raynaud’s Phenomenon Development of Raynaud’s phenomenon and recurrence or worsening of pre-existing Raynaud’s phenomenon have been reported in the postmarketing setting following the use of CGRP antagonists, including QULIPTA.
In reported cases with small molecule CGRP antagonists, symptom onset occurred a median of 1.5 days following dosing. Many of the cases reported serious outcomes, including hospitalizations and disability, generally related to debilitating pain. In most reported cases, discontinuation of the CGRP antagonist resulted in resolution of symptoms.
QULIPTA should be discontinued if signs or symptoms of Raynaud’s phenomenon develop, and patients should be evaluated by a healthcare provider if symptoms do not resolve. Patients with a history of Raynaud’s phenomenon should be monitored for, and informed about the possibility of, worsening or recurrence of signs and symptoms.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: Hypersensitivity Reactions [see Warnings and Precautions ( 5.1 )] Hypertension [see Warnings and Precautions ( 5.2 )] Raynaud’s Phenomenon [see Warnings and Precautions ( 5.3 )] The most common adverse reactions (at least 4% and greater than placebo) are nausea, constipation, and fatigue/somnolence. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact AbbVie at 1-800-678-1605 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The safety of QULIPTA was evaluated in 2657 patients with migraine who received at least one dose of QULIPTA. Of these, 1225 patients were exposed to QULIPTA for at least 6 months, and 826 patients were exposed for 12 months.
In the 12-week, placebo-controlled clinical studies (Studies 1, 2, and 3), 314 patients received at least one dose of QULIPTA 10 mg once daily, 411 patients received at least one dose of QULIPTA 30 mg once daily, 678 patients received at least one dose of QULIPTA 60 mg once daily, and 663 patients received placebo [see Clinical Studies ( 14 ) ] . Approximately 88% were female, 75% were White, 13% were Black, 10% were Asian, and 10% were of Hispanic or Latino ethnicity. The mean age at study entry was 41 years (range 18 to 74 years).
The most common adverse reactions (incidence at least 4% and greater than placebo) are nausea, constipation, and fatigue/somnolence. Table 2 summarizes the adverse reactions that occurred during Studies 1, 2, and 3. Table 2: Adverse Reactions Occurring with an Incidence of At Least 2% for QULIPTA and Greater than Placebo in Studies 1, 2, and 3 * Placebo (N= 663 ) % QULIPTA 10 mg (N=314) % QULIPTA 30 mg (N=411) % QULIPTA 60 mg (N= 678 ) % Nausea 3 5 6 9 Constipation 2 6 6 8 Fatigue/Somnolence 4 4 4 5 Decreased Appetite <1 2 1 3 Dizziness 2 2 2 3 * 10 mg and 30 mg incidence from Studies 1 and 2; 60 mg pooled incidence from Studies 1, 2, and 3.
The adverse reactions that most commonly led to discontinuation of QULIPTA in these studies were nausea (0.6%), constipation (0.5%), and fatigue/somnolence (0.2%). Liver Enzyme Elevations In Study 1, Study 2, and Study 3, the rate of transaminase elevations over 3 times the upper limit of normal was similar between patients treated with QULIPTA (0.9%) and those treated with placebo (1.2%). However, there were cases with transaminase elevations over 3 times the upper limit of normal that were temporally associated with QULIPTA treatment; these were asymptomatic and resolved within 8 weeks of discontinuation.
There were no cases of severe liver injury or jaundice. Decreases in Body Weight In Study 1, Study 2, and Study 3, the proportion of patients with a weight decrease of at least 7% at any point was 2.5% for placebo, 3.8% for QULIPTA 10 mg, 3.2% for QULIPTA 30 mg, and 5.3% for QULIPTA 60 mg.
6.2Postmarketing Experience The following adverse reactions have been identified during post approval use of QULIPTA. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to estimate their frequency or establish a causal relationship to drug exposure. Immune System Disorders : Hypersensitivity (e.g., anaphylaxis, dyspnea, rash, pruritus, urticaria, facial edema) [see Contraindications ( 4 ) and Warnings and Precautions ( 5.1 )] Vascular Disorders: Hypertension [see Warnings and Precautions ( 5.2 )] , Raynaud’s phenomenon [see Warnings and Precautions ( 5.3 )]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Recommended dosage modifications: Strong CYP3A4 Inhibitors ( 2.2 , 7.1 ): Episodic or chronic migraine: 10 mg once daily Strong CYP3A4 Inducers ( 2.2 , 7.2 ): Episodic migraine: 60 mg once daily (monitor for reduced efficacy). Chronic migraine: Not recommended. Moderate CYP3A4 Inducers ( 2.2 , 7.2 ): Episodic migraine: 60 mg once daily.
Chronic migraine: Not recommended. Weak CYP3A4 Inducers ( 2.2 , 7.2 ): Episodic migraine: 30 mg or 60 mg once daily. Chronic migraine: 60 mg once daily.
OATP Inhibitors ( 2.2 , 7.3 ): Episodic migraine: 10 mg or 30 mg once daily. Chronic migraine: 30 mg once daily.
7.1CYP3A4 Inhibitors Coadministration of QULIPTA with itraconazole, a strong CYP3A4 inhibitor, resulted in a significant increase in exposure of atogepant in healthy subjects [see Clinical Pharmacology ( 12.3 )] . The recommended dosage of QULIPTA with concomitant use of strong CYP3A4 inhibitors is 10 mg once daily [see Dosage and Administration ( 2.2 ) ] . No dosage adjustment of QULIPTA is needed with concomitant use of moderate or weak CYP3A4 inhibitors.
7.2CYP3A4 Inducers Coadministration of QULIPTA with steady-state rifampin, a strong CYP3A4 inducer and OATP1B1 and OATP1B3 inhibitor, resulted in a significant decrease in exposure of atogepant in healthy subjects [see Clinical Pharmacology ( 12.3 )] . Concomitant administration of QULIPTA with moderate inducers of CYP3A4 can also result in decreased exposure of atogepant. Coadministration of QULIPTA with steady-state topiramate, a weak CYP3A4 inducer, resulted in decreased exposure of atogepant in healthy subjects [see Clinical Phar macology ( 12.3 )] .
For episodic migraine, the recommended dosage of QULIPTA with concomitant use of strong or moderate CYP3A4 inducers is 60 mg once daily. During concomitant use of QULIPTA with strong CYP3A4 inducers, monitor monthly for signs of reduced efficacy, and consider alternative therapies if a reduction in efficacy is observed. The recommended dosage of QULIPTA with concomitant use of weak CYP3A4 inducers is 30 mg or 60 mg once daily [see Dosage and Administration ( 2.2 ) ] .
For chronic migraine, concomitant use of strong or moderate CYP3A4 inducers with QULIPTA is not recommended. The recommended dosage of QULIPTA with concomitant use of weak CYP3A4 inducers is 60 mg once daily. Monitor monthly for signs of reduced efficacy, and consider alternative therapies if a reduction in efficacy is observed [see Dosage and Administration ( 2.2 ) ] .
7 .3 OATP Inhibitors Coadministration of QULIPTA with single dose rifampin, an OATP inhibitor, resulted in a significant increase in exposure of atogepant in healthy subjects [see Clinical Pharmacology ( 12.3 )] . For episodic migraine, the recommended dosage of QULIPTA with concomitant use of OATP inhibitors is 10 mg or 30 mg once daily. For chronic migraine, the recommended dosage of QULIPTA with concomitant use of OATP inhibitors is 30 mg once daily [see Dosage and Administration ( 2.2 ) ] .
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Based on animal data, may cause fetal harm. ( 8.1 ) Avoid use in patients with severe hepatic impairment. ( 8.7 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors outcomes in women who become pregnant while taking QULIPTA. Patients should be encouraged to enroll by calling 1-833-277-0206 or visiting http://empresspregnancyregistry.com . Risk Summary There are no adequate data on the developmental risk associated with the use of QULIPTA in pregnant women.
In animal studies, oral administration of atogepant during the period of organogenesis (rats and rabbits) or throughout pregnancy and lactation (rats) resulted in adverse developmental effects (decreased fetal and offspring body weight in rats; increased incidence of fetal structural variations in rabbits) at exposures greater than those used clinically [see Data ] . In the U.S. general population, the estimated background risk of major birth defects and miscarriages in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
The estimated rate of major birth defects (2.2%-2.9%) and miscarriage (17%) among deliveries to women with migraine are similar to rates reported in women without migraine. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk Published data have suggested that women with migraine may be at increased risk of preeclampsia and gestational hypertension during pregnancy. Data Animal Data Oral administration of atogepant (0, 5, 15, 125, or 750 mg/kg/day) to pregnant rats during the period of organogenesis resulted in decreases in fetal body weight and in skeletal ossification at the two highest doses tested (125 and 750 mg/kg), which were not associated with maternal toxicity.
At the no-effect dose (15 mg/kg/day) for adverse effects on embryofetal development, plasma exposure (AUC) was approximately 4 times that in humans at the maximum recommended human dose (MRHD) of 60 mg/day. Oral administration of atogepant (0, 30, 90, or 130 mg/kg/day) to pregnant rabbits during the period of organogenesis resulted in an increase in fetal visceral and skeletal variations at the highest dose tested (130 mg/kg/day), which was associated with minimal maternal toxicity. At the no-effect dose (90 mg/kg/day) for adverse effects on embryofetal development, plasma exposure (AUC) was approximately 3 times that in humans at the MRHD.
Oral administration of atogepant (0, 15, 45, or 125 mg/kg/day) to rats throughout gestation and lactation resulted in decreased pup body weight at the highest dose tested (125 mg/kg/day), which persisted into adulthood. At the no-effect dose (45 mg/kg/day) for adverse effects on pre- and postnatal development, plasma exposure (AUC) was approximately 5 times that in humans at the MRHD.
8.2Lactation Risk Summary Data from a lactation study in twelve healthy adult females indicate that atogepant is excreted in breast milk in low amounts. The estimated relative infant dose is approximately 0.19% of the maternal weight-adjusted dose, and the milk-to-plasma ratio is 0.08 (see Data ). There are no data on the effects of atogepant on the breastfed infant or the effects on milk production.
The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for QULIPTA and any potential adverse effects on the breastfed infant from QULIPTA or from the underlying maternal condition. Data A study was conducted in twelve healthy adult lactating females who were between 23 and 34 years of age and between 1 month and 6 months postpartum. Each subject was administered a single oral dose of atogepant 60 mg.
Maternal plasma and breast milk were collected for 24 hours after dosing. Using a 150 mL/kg/day estimated infant milk intake, the mean estimated relative infant dose was approximately 0.19% of the maternal weight-adjusted dose. The mean milk-to-plasma ratio was 0.08.
All subjects had detectable levels… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors outcomes in women who become pregnant while taking QULIPTA. Patients should be encouraged to enroll by calling 1-833-277-0206 or visiting http://empresspregnancyregistry.com . Risk Summary There are no adequate data on the developmental risk associated with the use of QULIPTA in pregnant women.
In animal studies, oral administration of atogepant during the period of organogenesis (rats and rabbits) or throughout pregnancy and lactation (rats) resulted in adverse developmental effects (decreased fetal and offspring body weight in rats; increased incidence of fetal structural variations in rabbits) at exposures greater than those used clinically [see Data ] . In the U.S. general population, the estimated background risk of major birth defects and miscarriages in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
The estimated rate of major birth defects (2.2%-2.9%) and miscarriage (17%) among deliveries to women with migraine are similar to rates reported in women without migraine. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk Published data have suggested that women with migraine may be at increased risk of preeclampsia and gestational hypertension during pregnancy. Data Animal Data Oral administration of atogepant (0, 5, 15, 125, or 750 mg/kg/day) to pregnant rats during the period of organogenesis resulted in decreases in fetal body weight and in skeletal ossification at the two highest doses tested (125 and 750 mg/kg), which were not associated with maternal toxicity.
At the no-effect dose (15 mg/kg/day) for adverse effects on embryofetal development, plasma exposure (AUC) was approximately 4 times that in humans at the maximum recommended human dose (MRHD) of 60 mg/day. Oral administration of atogepant (0, 30, 90, or 130 mg/kg/day) to pregnant rabbits during the period of organogenesis resulted in an increase in fetal visceral and skeletal variations at the highest dose tested (130 mg/kg/day), which was associated with minimal maternal toxicity. At the no-effect dose (90 mg/kg/day) for adverse effects on embryofetal development, plasma exposure (AUC) was approximately 3 times that in humans at the MRHD.
Oral administration of atogepant (0, 15, 45, or 125 mg/kg/day) to rats throughout gestation and lactation resulted in decreased pup body weight at the highest dose tested (125 mg/kg/day), which persisted into adulthood. At the no-effect dose (45 mg/kg/day) for adverse effects on pre- and postnatal development, plasma exposure (AUC) was approximately 5 times that in humans at the MRHD.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Population pharmacokinetic modeling suggests no clinically significant pharmacokinetic differences between elderly and younger subjects. Clinical studies of QULIPTA did not include sufficient numbers of patients aged 65 years and over to determine whether they respond differently from younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Atogepant is a calcitonin gene-related peptide (CGRP) receptor antagonist.
12.2Pharmacodynamics Cardiac Electrophysiology At a dose 5 times the maximum recommended daily dose, QULIPTA does not prolong the QT interval to any clinically relevant extent.
12.3Pharmacokinetics Absorption Following oral administration of QULIPTA, atogepant is absorbed with peak plasma concentrations at approximately 1 to 2 hours. Atogepant displays dose-proportional pharmacokinetics up to 170 mg per day (approximately 3 times the highest recommended dosage), with no accumulation. Effect of Food When QULIPTA was administered with a high-fat meal, the food effect was not significant (AUC and C max were reduced by approximately 18% and 22%, respectively, with no effect on median time to maximum atogepant plasma concentration).
QULIPTA was administered without regard to food in clinical efficacy studies. Distribution Plasma protein binding of atogepant was not concentration-dependent in the range of 0.1 to 10 µM; the unbound fraction of atogepant was approximately 4.7% in human plasma. The mean apparent volume of distribution of atogepant (Vz/F) after oral administration is approximately 292 L .
Elimination Metabolism Atogepant is eliminated mainly through metabolism, primarily by CYP3A4. The parent compound (atogepant), and a glucuronide conjugate metabolite (M23) were the most prevalent circulating components in human plasma. Excretion The elimination half-life of atogepant is approximately 11 hours.
The mean apparent oral clearance (CL/F) of atogepant is approximately 19 L/hr. Following single oral dose of 50 mg 14 C-atogepant to healthy male subjects, 42% and 5% of the dose was recovered as unchanged atogepant in feces and urine, respectively. Specific Populations Patients with Renal Impairment The renal route of elimination plays a minor role in the clearance of atogepant.
Based on a population pharmacokinetic analysis, there is no significant difference in the pharmacokinetics of atogepant in patients with mild or moderate renal impairment (CLcr 30-89 mL/min) relative to those with normal renal function (CLcr >90 mL/min). Patients with severe renal impairment or end-stage renal disease (ESRD; CLcr <30 mL/min) have not been studied [see Dosage and Administration ( 2.2 ) and Use in Specific Populations ( 8.6 ) ] . Patients with Hepatic Impairment In patients with pre-existing mild (Child-Pugh Class A), moderate (Child-Pugh Class B), or severe (Child-Pugh Class C) hepatic impairment, the total atogepant exposure was increased by 24%, 15%, and 38%, respectively.
Due to a potential for liver injury in patients with severe hepatic impairment, avoid use of QULIPTA in patients with severe hepatic impairment [see Use in Specific Populations ( 8.7 )] . Other Specific Populations Based on a population pharmacokinetic analysis, age, sex, race, and body weight did not have a significant effect on the pharmacokinetics (C max and AUC) of atogepant. Therefore, no dose adjustments are warranted based on these factors.
Drug Interactions In Vitro Studies Enzymes In vitro, atogepant is not an inhibitor for CYPs 3A4, 1A2, 2B6, 2C8, 2C9, 2C19, or 2D6 at clinically relevant concentrations. Atogepant does not inhibit MAO-A or UGT1A1 at clinically relevant concentrations. Atogepant is not anticipated to be a clinically significant perpetrator of drug-drug interactions through CYP450s, MAO-A, or UGT1A1 inhibition.
Atogepant is not an inducer of CYP1A2, CYP2B6, or CYP3A4 at clinically relevant concentrations. Transporters Atogepant is a substrate of P-gp, BCRP, OATP1B1, OATP1B3, and OAT1. Dose adjustment for concomitant use of QULIPTA with inhibitors of OATP is recommended based on a clinical interaction study with a OATP inhibitor [see Dosage and Administration ( 2.2 )] .
Coadministration of atogepant with BCRP and/or P-gp inhibitors is not expected to increase the exposure of atogepant. Atogepant is not a substrate of OA… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Atogepant is a calcitonin gene-related peptide (CGRP) receptor antagonist.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied QULIPTA 10 mg is supplied as white to off-white, round biconvex tablets debossed with “A” and “10” on one side in the following packaging presentations: Bottle of 30, NDC: 0074-7095-30 QULIPTA 30 mg is supplied as white to off-white, oval biconvex tablets debossed with “A30” on one side in the following packaging presentations: Bottle of 30, NDC: 0074-7096-30 QULIPTA 60 mg is supplied as white to off-white, oval biconvex tablets debossed with “A60” on one side in the following packaging presentations: Bottle of 30, NDC: 0074-7094-30
16.2Storage and Handling Store between 20°C and 25°C (68°F and 77°F): excursions permitted between 15°C and 30°C (59°F and 86°F) [ see USP Controlled Room Temperature ] .
16.1How Supplied QULIPTA 10 mg is supplied as white to off-white, round biconvex tablets debossed with “A” and “10” on one side in the following packaging presentations: Bottle of 30, NDC: 0074-7095-30 QULIPTA 30 mg is supplied as white to off-white, oval biconvex tablets debossed with “A30” on one side in the following packaging presentations: Bottle of 30, NDC: 0074-7096-30 QULIPTA 60 mg is supplied as white to off-white, oval biconvex tablets debossed with “A60” on one side in the following packaging presentations: Bottle of 30, NDC: 0074-7094-30
📦 Storage and Handling ▾
16.2Storage and Handling Store between 20°C and 25°C (68°F and 77°F): excursions permitted between 15°C and 30°C (59°F and 86°F) [ see USP Controlled Room Temperature ] .
📋 Description ▾
11 DESCRIPTION The active ingredient of QULIPTA is atogepant, a calcitonin gene-related peptide (CGRP) receptor antagonist. The chemical name of atogepant is (3’ S )- N -[(3 S ,5 S ,6 R )-6-methyl-2-oxo-1-(2,2,2-trifluoroethyl)-5-(2,3,6-trifluorophenyl)piperidin-3-yl]-2’-oxo-1’,2’,5,7-tetrahydrospiro[cyclopenta[ b ]pyridine-6,3’-pyrrolo[2,3- b ]pyridine]-3-carboxamide, and it has the following structural formula: The molecular formula is C 29 H 2 3 F 6 N 5 O 3 and molecular weight is 603.5. Atogepant is a white to off-white powder.
It is freely soluble in ethanol, soluble in methanol, sparingly soluble in acetone, slightly soluble in acetonitrile, and practically insoluble in water. QULIPTA is available as tablets for oral administration containing 10 mg, 30 mg, or 60 mg atogepant. The inactive ingredients include colloidal silicon dioxide, croscarmellose sodium, mannitol, microcrystalline cellulose, polyvinylpyrrolidone vinyl acetate copolymer, sodium chloride, sodium stearyl fumarate, and vitamin E polyethylene glycol succinate.
The active ingredient of TRADENAME is atogepant, a calcitonin gene-related peptide (CGRP) receptor antagonist. The chemical name of atogepant is (S)-N-((3S,5S,6R)-6-methyl-2-oxo-1-(2,2,2-trifluoroethyl)-5-(2,3,6-trifluorophenyl)piperidin-3-yl)-2'-oxo-1',2',5,7-tetrahydrospiro[cyclopenta[b]pyridine-6,3'-pyrrolo[2,3-b]pyridine]-3-carboxamide and has the following structural formula:
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Patient Information ). Hypersensitivity Reactions Inform patients about the signs and symptoms of hypersensitivity reactions and that these reactions can occur with QULIPTA. Advise patients to discontinue QULIPTA and seek immediate medical attention if they experience any symptoms of a hypersensitivity reaction [see Warnings and Precautions ( 5.1 )] .
Hypertension Inform patients that hypertension can develop or pre-existing hypertension can worsen with QULIPTA, and that they should contact their healthcare providers if they experience elevation in their blood pressure [see Warnings and Precautions ( 5.2 )] . Raynaud’s Phenomenon Inform patients that Raynaud’s phenomenon can develop or worsen with QULIPTA. Advise patients to discontinue QULIPTA and contact their healthcare provider if they experience signs or symptoms of Raynaud’s phenomenon [see Warnings and Precautions ( 5.3 )] .
Drug Interactions Inform patients that QULIPTA may interact with certain other drugs, and that dosage modifications of QULIPTA may be recommended when used with some other drugs. Advise patients to report to their healthcare provider the use of any other prescription medications, over-the-counter medications, herbal products, or grapefruit juice [ see Dosage and Administration ( 2.2 ) and Drug Interactions ( 7.1 , 7.2 , 7.3 )] . Pregnancy Advise patients to notify their healthcare provider if they become pregnant during treatment or plan to become pregnant .
Encourage pregnant patients to enroll in the registry that monitors pregnancy outcomes in women exposed to QULIPTA during pregnancy [see Use in Specific Populations ( 8.1 )] . Lactation Inform patients to notify their healthcare provider if they are breastfeeding or plan to breastfeed [see Use in Specific Populations ( 8.2 )] . Manufactured for: AbbVie Inc.
North Chicago, IL 60064 © 2025 AbbVie. All rights reserved. QULIPTA and its design are trademarks of Allergan Pharmaceuticals International Limited, an AbbVie company.
20096809 September 2025
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption Following oral administration of QULIPTA, atogepant is absorbed with peak plasma concentrations at approximately 1 to 2 hours. Atogepant displays dose-proportional pharmacokinetics up to 170 mg per day (approximately 3 times the highest recommended dosage), with no accumulation. Effect of Food When QULIPTA was administered with a high-fat meal, the food effect was not significant (AUC and C max were reduced by approximately 18% and 22%, respectively, with no effect on median time to maximum atogepant plasma concentration).
QULIPTA was administered without regard to food in clinical efficacy studies. Distribution Plasma protein binding of atogepant was not concentration-dependent in the range of 0.1 to 10 µM; the unbound fraction of atogepant was approximately 4.7% in human plasma. The mean apparent volume of distribution of atogepant (Vz/F) after oral administration is approximately 292 L .
Elimination Metabolism Atogepant is eliminated mainly through metabolism, primarily by CYP3A4. The parent compound (atogepant), and a glucuronide conjugate metabolite (M23) were the most prevalent circulating components in human plasma. Excretion The elimination half-life of atogepant is approximately 11 hours.
The mean apparent oral clearance (CL/F) of atogepant is approximately 19 L/hr. Following single oral dose of 50 mg 14 C-atogepant to healthy male subjects, 42% and 5% of the dose was recovered as unchanged atogepant in feces and urine, respectively. Specific Populations Patients with Renal Impairment The renal route of elimination plays a minor role in the clearance of atogepant.
Based on a population pharmacokinetic analysis, there is no significant difference in the pharmacokinetics of atogepant in patients with mild or moderate renal impairment (CLcr 30-89 mL/min) relative to those with normal renal function (CLcr >90 mL/min). Patients with severe renal impairment or end-stage renal disease (ESRD; CLcr <30 mL/min) have not been studied [see Dosage and Administration ( 2.2 ) and Use in Specific Populations ( 8.6 ) ] . Patients with Hepatic Impairment In patients with pre-existing mild (Child-Pugh Class A), moderate (Child-Pugh Class B), or severe (Child-Pugh Class C) hepatic impairment, the total atogepant exposure was increased by 24%, 15%, and 38%, respectively.
Due to a potential for liver injury in patients with severe hepatic impairment, avoid use of QULIPTA in patients with severe hepatic impairment [see Use in Specific Populations ( 8.7 )] . Other Specific Populations Based on a population pharmacokinetic analysis, age, sex, race, and body weight did not have a significant effect on the pharmacokinetics (C max and AUC) of atogepant. Therefore, no dose adjustments are warranted based on these factors.
Drug Interactions In Vitro Studies Enzymes In vitro, atogepant is not an inhibitor for CYPs 3A4, 1A2, 2B6, 2C8, 2C9, 2C19, or 2D6 at clinically relevant concentrations. Atogepant does not inhibit MAO-A or UGT1A1 at clinically relevant concentrations. Atogepant is not anticipated to be a clinically significant perpetrator of drug-drug interactions through CYP450s, MAO-A, or UGT1A1 inhibition.
Atogepant is not an inducer of CYP1A2, CYP2B6, or CYP3A4 at clinically relevant concentrations. Transporters Atogepant is a substrate of P-gp, BCRP, OATP1B1, OATP1B3, and OAT1. Dose adjustment for concomitant use of QULIPTA with inhibitors of OATP is recommended based on a clinical interaction study with a OATP inhibitor [see Dosage and Administration ( 2.2 )] .
Coadministration of atogepant with BCRP and/or P-gp inhibitors is not expected to increase the exposure of atogepant. Atogepant is not a substrate of OAT3, OCT2, or MATE1. Atogepant is not an inhibitor of P-gp, BCRP, OAT1, OAT3, NTCP, BSEP, MRP3, or MRP4 at clinically relevant concentrations.
Atogepant is a weak inhibitor of OATP1B1, OATP1B3, OCT1, and MATE1. No clinical drug interactions are expected for atogepant as a perpetrator with these transpor… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Cardiac Electrophysiology At a dose 5 times the maximum recommended daily dose, QULIPTA does not prolong the QT interval to any clinically relevant extent.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES Figure 1: Change from Baseline in Monthly Migraine Days in Study 1 Figure 2: Distribution of Change from Baseline in Mean Monthly Migraine Days by Treatment Group in Study 1 Diagram Description automatically generated Chart, bar chart Description automatically generated Figure 5: Change from Baseline in Monthly Migraine Days in Study 3 Figure 6: Distribution of Change from Baseline in Mean Monthly Migraine Days by Treatment Group in Study 3
14.1Episodic Migraine The efficacy of QULIPTA for the preventive treatment of episodic migraine in adults was demonstrated in two randomized, multicenter, double-blind, placebo-controlled studies (Study 1 and Study 2). The studies enrolled patients with at least a 1-year history of migraine with or without aura, according to the International Classification of Headache Disorders (ICHD-3) diagnostic criteria. In Study 1 (NCT03777059), 910 patients were randomized 1:1:1:1 to receive QULIPTA 10 mg (N = 222), QULIPTA 30 mg (N = 230), QULIPTA 60 mg (N = 235), or placebo (N = 223), once daily for 12 weeks.
In Study 2 (NCT02848326), 652 patients were randomized 1:2:2:2 to receive QULIPTA 10 mg (N = 94), QULIPTA 30 mg (N = 185), QULIPTA 60 mg (N = 187), or placebo (N = 186), once daily for 12 weeks. In both studies, patients were allowed to use acute headache treatments (i.e., triptans, ergotamine derivatives, NSAIDs, acetaminophen, and opioids) as needed. The use of a concomitant medication that acts on the CGRP pathway was not permitted for either acute or preventive treatment of migraine.
The studies excluded patients with myocardial infarction, stroke, or transient ischemic attacks within six months prior to screening. Study 1 The primary efficacy endpoint was the change from baseline in mean monthly migraine days (MMD) across the 12-week treatment period. Secondary endpoints included the change from baseline in mean monthly headache days, the change from baseline in mean monthly acute medication use days, the proportion of patients achieving at least a 50% reduction from baseline in mean MMD (3-month average), the change from baseline in mean monthly Activity Impairment in Migraine-Diary (AIM-D) Performance of Daily Activities (PDA) domain scores, the change from baseline in mean monthly AIM-D Physical Impairment (PI) domain scores, across the 12-week treatment period, and the change from baseline at Week 12 for Migraine Specific Quality of Life Questionnaire version 2.1 (MSQ v2.1) Role Function-Restrictive (RFR) domain scores.
The AIM-D evaluates difficulty with performance of daily activities (PDA domain) and physical impairment (PI domain) due to migraine, with scores ranging from 0 to 100. Higher scores indicate greater impact of migraine, and reductions from baseline indicate improvement. The MSQ v2.1 Role Function-Restrictive (RFR) domain score assesses how often migraine impacts function related to daily social and work-related activities over the past 4 weeks, with scores ranging from 0 to 100.
Higher scores indicate lesser impact of migraine on daily activities, and increases from baseline indicate improvement. Patients had a mean age of 42 years (range 18 to 73 years), 89% were female, 83% were White, 14% were Black, and 9% were of Hispanic or Latino ethnicity. The mean migraine frequency at baseline was approximately 8 migraine days per month and was similar across treatment groups.
A total of 805 (88%) patients completed the 12-week double-blind study period. Key efficacy results of Study 1 are summarized in Table 3. Table 3: Efficacy Endpoints in Study 1 QULIPTA 10 mg N= 214 QULIPTA 30 mg N= 223 QULIPTA 60 mg N= 222 Placebo N= 214 Monthly Migraine Days (MMD) across 12 weeks Baseline 7.5 7.9 7.8
7.5Mean change from baseline -3.7 -3.9 -4.2 -2.5 Difference from placebo -1.2 -1.4 -1.7 p -value <0.001 <0.001 <0.001 Monthly Headache Days across 12 weeks Baseline 8.4 8.8 9.0
8.4Mean change from baseline -3.9 -4.0 -4.2 -2.5 Difference from placebo -1.4 -1.5 -1.7 p -… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity Atogepant was administered orally to mice (0, 5, 20, or 75 mg/kg/day in males; 0, 5, 30, 160 mg/kg/day in females) and rats (0, 10, 20, or 100 mg/kg in males; 0, 25, 65, or 200 mg/kg in females) for up to 2 years. There was no evidence of drug-related tumors in either species. Plasma exposures at the highest doses tested in mice and rats were approximately 8 and 20-35 times, respectively, that in humans at the maximum recommended human dose (MRHD) of 60 mg/day.
Mutagenicity Atogepant was negative in in vitro (Ames, chromosomal aberration test in Chinese Hamster Ovary cells) and in vivo (rat bone marrow micronucleus) assays. Impairment of Fertility Oral administration of atogepant (0, 5, 20, or 125 mg/kg/day) to male and female rats prior to and during mating and continuing in females to Gestation Day 7 resulted in no adverse effects on fertility or reproductive performance. Plasma exposures (AUC) at the highest dose tested are approximately 15 times that in humans at the MRHD.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity Atogepant was administered orally to mice (0, 5, 20, or 75 mg/kg/day in males; 0, 5, 30, 160 mg/kg/day in females) and rats (0, 10, 20, or 100 mg/kg in males; 0, 25, 65, or 200 mg/kg in females) for up to 2 years. There was no evidence of drug-related tumors in either species. Plasma exposures at the highest doses tested in mice and rats were approximately 8 and 20-35 times, respectively, that in humans at the maximum recommended human dose (MRHD) of 60 mg/day.
Mutagenicity Atogepant was negative in in vitro (Ames, chromosomal aberration test in Chinese Hamster Ovary cells) and in vivo (rat bone marrow micronucleus) assays. Impairment of Fertility Oral administration of atogepant (0, 5, 20, or 125 mg/kg/day) to male and female rats prior to and during mating and continuing in females to Gestation Day 7 resulted in no adverse effects on fertility or reproductive performance. Plasma exposures (AUC) at the highest dose tested are approximately 15 times that in humans at the MRHD.
📄 Patient Package Insert ▾
PATIENT INFORMATION QULIPTA ® ( kew-LIP-tah ) (atogepant) tablets, for oral use What is QULIPTA ? QULIPTA is a prescription medicine used for the preventive treatment of migraine in adults. It is not known if QULIPTA is safe and effective in children.
Do not take QULIPTA if you: have had an allergic reaction to atogepant or any ingredients in QULIPTA. See the end of this Patient Information leaflet for a complete list of ingredients in QULIPTA. Before you take QULIPTA tell your healthcare provider about all of your medical conditions, including if you: have high blood pressure. have circulation problems in your fingers and toes. have kidney problems or are on dialysis. have liver problems. are pregnant or plan to become pregnant.
It is not known if QULIPTA will harm your unborn baby. Pregnancy Registry: There is a pregnancy registry for women who take QULIPTA. The purpose of this registry is to collect information about the health of you and your baby.
Talk to your healthcare provider or call 1-833-277-0206 to enroll in this registry. You can also visit http://empresspregnancyregistry.com . are breastfeeding or plan to breastfeed. Very small amounts of QULIPTA pass into breast milk.
Talk to your healthcare provider if you plan to breastfeed. Tell your healthcare provider about all the medicines you take, including prescription and over-the-counter medicines, vitamins, and herbal supplements. QULIPTA may affect the way other medicines work, and other medicines may affect how QULIPTA works.
Your healthcare provider may need to change the dose of QULIPTA when taken with certain other medicines. Keep a list of medicines you take to show to your healthcare provider or pharmacist when you get a new medicine. How should I take QULIPTA ?
Take QULIPTA by mouth with or without food. Take QULIPTA exactly as your healthcare provider tells you to take it. What are the possible side effects of QULIPTA ?
QULIPTA can cause serious side effects, including: Allergic (hypersensitivity) reactions, including anaphylaxis: Serious allergic reactions can happen when you take QULIPTA or days after. Stop taking QULIPTA and get emergency medical help right away if you get any of the following symptoms, which may be part of a serious allergic reaction: • swelling of the face, lips, or tongue • trouble breathing • rash itching hives High blood pressure: High blood pressure or worsening of high blood pressure can happen when you take QULIPTA.
Contact your healthcare provider if you have an increase in blood pressure. Raynaud’s phenomenon: A type of circulation problem can worsen or happen when you take QULIPTA. Raynaud’s phenomenon can lead to your fingers or toes feeling numb, cool, or painful, or changing color from pale, to blue, to red.
Contact your healthcare provider if these symptoms occur. The most common side effects of QULIPTA include : nausea, constipation, and fatigue/sleepiness. These are not all of the possible side effects of QULIPTA.
Call your doctor for medical advice about side effects. You may report side effects to FDA at 1-800-FDA-1088. How should I store QULIPTA ?
Store QULIPTA at room temperature between 68ºF to 77ºF (20ºC to 25ºC). Keep QULIPTA and all medicines out of the reach of children. General information about the safe and effective use of QULIPTA .
Medicines are sometimes prescribed for purposes other than those listed in a Patient Information leaflet. Do not use QULIPTA for a condition for which it was not prescribed. Do not give QULIPTA to other people, even if they have the same symptoms you have.
It may harm them. You can ask your pharmacist or healthcare provider for information about QULIPTA that is written for health professionals. What are the ingredients in QULIPTA ?
Active ingredient: atogepant Inactive ingredients: colloidal silicon dioxide, croscarmellose sodium, mannitol, microcrystalline cellulose, polyvinylpyrrolidone vinyl acetate copolymer, sodium chloride, sodium stearyl fumarate, and vitamin E polyethylene… [Excerpted — this section continues on DailyMed.]
📄 Recent Major Changes ▾
Dosage and Administration ( 2.2 ) 9/2025 Warnings and Precautions ( 5.2 , 5.3 ) 3/2025
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL NDC 0074- 7095 -30 Rx Only QULIPTA ® (atogepant) tablets 10 mg Contains 30 Tablets PRINCIPAL DISPLAY PANEL NDC 0074-7095-30 Rx Only QULIPTA® (atogepant) tablets 10 mg Contains 30 Tablets
PRINCIPAL DISPLAY PANEL NDC 0074- 7096 -30 Rx Only QULIPTA ® (atogepant) tablets 30 mg Contains 30 Tablets PRINCIPAL DISPLAY PANEL NDC 0074-7096-30 Rx Only QULIPTA® (atogepant) tablets 30 mg Contains 30 Tablets
PRINCIPAL DISPLAY PANEL NDC 0074- 7094 -30 Rx Only QULIPTA ® (atogepant) tablets 60 mg Contains 30 Tablets PRINCIPAL DISPLAY PANEL NDC 0074-7094-30 Rx Only QULIPTA® (atogepant) tablets 60 mg Contains 30 Tablets