
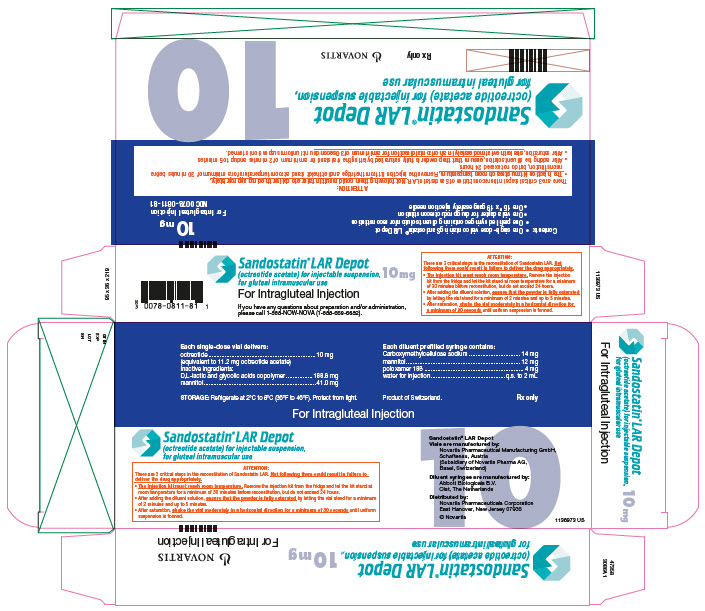
Sandostatin LAR Depot octreotide acetate Kit — NDC 0078-0811-81 (Billing 00078-0811-81)
This is a package of Sandostatin LAR Depot octreotide acetate Kit from Novartis Pharmaceuticals Corporation, marketed since Jul 2016 and currently FDA-listed; retail pharmacies pay about $3,523.03 per unit (NADAC). It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 0078-0811-81 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0078 labeler · 0811 product · 81 package
- Package marketed since
- Jul 22, 2016
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC-A, from the NDC)
- 3 0078081181 1
- Medicaid fills, this package
- 14 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Other active recalls for Octreotide Acetate (different manufacturers) — 4 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 041347
- GCN: 21307
- GPI-14 (Medi-Span): 30170070106410
- HICL (First Databank): 019000
- AHFS class code: 68:29.04.00
- RxCUI (RxNorm): 898589
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 8, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Somatostatin Analog class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 8, 2026
Clinical
- It treats acromegaly, which is too much growth hormone. It also treats the severe diarrhea and flushing from metastatic carcinoid tumors, and the watery diarrhea from VIPomas. Myca...
- It depends on your product. Injections go under the skin or into a vein, while the long-acting kit is given by a provider in the buttock about every 4 weeks. Mycapssa capsules are...
- Stomach issues are the most common, like diarrhea, belly pain, gas and nausea. Injection-site pain and headache can also happen. These often ease after the first month.
- Call for severe upper belly pain, fever, yellowing of the skin or eyes, a very slow or irregular heartbeat, or signs of high or low blood sugar. Get help right away for trouble bre...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Octreotide Acetate — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $3,523.030 | — |
| Medicaid paysCMS SDUD · 12 mo | $2,798.16 | — |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J2353 | $208.095 / J2353 unit | — |
Where does this data come from?
- CMS NADAC weekly file · file of Oct 7, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Oct 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00078-0811-81 You're viewing this Main listing | 1 KIT in 1 KIT * 6 mL in 1 VIAL * 2 mL in 1 SYRINGE | 2016-07-22 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Sandostatin LAR Depotthis 00078-0811-81 | Novartis | 1 kit | $3,523.030 | AB | Availability likely | — |
| Sandostatin LAR Depot 00078-0818-81 | Novartis | 1 kit | $4,588.550 | AB | Availability likely | +30% |
| Sandostatin LAR Depot 00078-0825-81 | Novartis | 1 kit | $6,948.080 | AB | Availability likely | +97% |
| Octreotide Acetate 00480-9257-08 | Teva | 1 kit | — | AB | FDA listed | — |
| Octreotide Acetate 67457-0756-10 | Mylan | 1 kit | — | AB | FDA listed | — |
| Octreotide Acetate 67457-0759-20 | Mylan | 1 kit | — | AB | FDA listed | — |
| Octreotide Acetate 67457-0762-30 | Mylan | 1 kit | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Oct 7, 2026
Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Octreotide inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 8, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Novartis Pharmaceuticals Corporation labeler code 00078
- Jadenu deferasirox 90 mg Granule NDC 0078-0727-15
- Betoptic S betaxolol hydrochloride 2.8 mg/mL Suspension/ Drops NDC 0078-0729-10
- Ilaris canakinumab 150 mg/mL Injection, Solution NDC 0078-0734-61
- ILEVRO nepafenac 3 mg/mL Suspension/ Drops NDC 0078-0743-03
- MAXITROL neomycin sulfate, polymyxin b sulfate and dexamethasone 3.5 mg/g; 10000 [USP'U]/g; 1 mg/g Ointment NDC 0078-0771-01
- ENTRESTO Sacubitril and Valsartan 49 mg; 51 mg Tablet, Film Coated NDC 0078-0777-20
- Tobrex tobramycin 3 mg/g Ointment NDC 0078-0813-01
- Sandostatin LAR Depot octreotide acetate Kit NDC 0078-0818-81
- Sandostatin LAR Depot octreotide acetate Kit NDC 0078-0825-81
- BEOVU brolucizumab 6 mg/.05mL Injection, Solution NDC 0078-0827-60
- Kymriah tisagenlecleucel 2000000 1/1 Injection, Suspension NDC 0078-0846-19
- Kisqali ribociclib 200 mg Tablet, Film Coated NDC 0078-0860-01
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE SANDOSTATIN LAR DEPOT 10 mg, 20 mg, and 30 mg is indicated in patients in whom initial treatment with Sandostatin Injection has been shown to be effective and tolerated. SANDOSTATIN LAR DEPOT is a somatostatin analogue indicated for: Treatment in patients who have responded to and tolerated Sandostatin Injection subcutaneous injection for: Acromegaly ( 1.1 ) Severe diarrhea/flushing episodes associated with metastatic carcinoid tumors ( 1.2 ) Profuse watery diarrhea associated with Vasoactive Intestinal Peptide (VIP) secreting tumors ( 1.3 )
1.1Acromegaly Long-term maintenance therapy in acromegalic patients who have had an inadequate response to surgery and/or radiotherapy, or for whom surgery and/or radiotherapy, is not an option. The goal of treatment in acromegaly is to reduce GH and IGF-1 levels to normal [see Clinical Studies (14), Dosage and Administration (2)] .
1.2Carcinoid Tumors Long-term treatment of the severe diarrhea and flushing episodes associated with metastatic carcinoid tumors.
1.3Vasoactive Intestinal Peptide Tumors (VIPomas) Long-term treatment of the profuse watery diarrhea associated with VIP-secreting tumors.
1.4Important Limitations of Use In patients with carcinoid syndrome and VIPomas, the effect of Sandostatin Injection and SANDOSTATIN LAR DEPOT on tumor size, rate of growth and development of metastases, has not been determined.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION SANDOSTATIN LAR DEPOT should be administered by a trained healthcare provider. It is important to closely follow the mixing instructions included in the packaging. SANDOSTATIN LAR DEPOT must be administered immediately after mixing.
Do not directly inject diluent without preparing suspension. The recommended needle size for administration of SANDOSTATIN LAR DEPOT is the 1½” 19 gauge safety injection needle (supplied in the drug product kit). For patients with a greater skin to muscle depth, a size 2” 19 gauge needle (not supplied) may be used.
SANDOSTATIN LAR DEPOT should be administered intramuscularly (IM) in the gluteal region at 4-week intervals. Administration of SANDOSTATIN LAR DEPOT at intervals greater than 4 weeks is not recommended. Injection sites should be rotated in a systematic manner to avoid irritation.
Deltoid injections should be avoided due to significant discomfort at the injection site when given in that area. SANDOSTATIN LAR DEPOT should never be administered intravenously or subcutaneously. The following dosage regimens are recommended.
Patients Not Currently Receiving Sandostatin Injection Subcutaneously: Acromegaly: 50 mcg three times daily Sandostatin Injection subcutaneously for 2 weeks followed by SANDOSTATIN LAR DEPOT 20 mg intragluteally every 4 weeks for 3 months ( 2.1 ) Carcinoid Tumors and VIPomas: Sandostatin Injection subcutaneously 100 to 600 mcg/day in 2-4 divided doses for 2 weeks followed by SANDOSTATIN LAR DEPOT 20 mg every 4 weeks for 2 months ( 2.2 ) Patients Currently Receiving Sandostatin Injection Subcutaneously: Acromegaly: 20 mg every 4 weeks for 3 months ( 2.1 ) Carcinoid Tumors and VIPomas: 20 mg every 4 weeks for 2 months ( 2.2 ) Renal Impairment, Patients on Dialysis: 10 mg every 4 weeks ( 2.3 ) Hepatic Impairment, Patients With Cirrhosis: 10 mg every 4 weeks ( 2.4 )
2.1Acromegaly Patients Not Currently Receiving Octreotide Acetate Patients not currently receiving octreotide acetate should begin therapy with Sandostatin Injection given subcutaneously in an initial dose of 50 mcg three times daily which may be titrated. Most patients require doses of 100 mcg to 200 mcg three times daily for maximum effect but some patients require up to 500 mcg three times daily. Patients should be maintained on Sandostatin Injection subcutaneous for at least 2 weeks to determine tolerance to octreotide acetate.
Patients who are considered to be “responders” to the drug, based on GH and IGF-1 levels and who tolerate the drug, can then be switched to SANDOSTATIN LAR DEPOT in the dosage scheme described below (Patients Currently Receiving Sandostatin Injection). Patients Currently Receiving Sandostatin Injection Patients currently receiving Sandostatin Injection can be switched directly to SANDOSTATIN LAR DEPOT in a dose of 20 mg given IM intragluteally at 4-week intervals for 3 months. After 3 months, dosage may be adjusted as follows: GH ≤ 2.5 ng/mL, IGF-1 normal, and clinical symptoms controlled: maintain SANDOSTATIN LAR DEPOT dosage at 20 mg every 4 weeks GH > 2.5 ng/mL, IGF-1 elevated, and/or clinical symptoms uncontrolled, increase SANDOSTATIN LAR DEPOT dosage to 30 mg every 4 weeks GH ≤ 1 ng/mL, IGF-1 normal, and clinical symptoms controlled, reduce SANDOSTATIN LAR DEPOT dosage to 10 mg every 4 weeks If GH, IGF-1, or symptoms are not adequately controlled at a dose of 30 mg, the dose may be increased to 40 mg every 4 weeks.
Doses higher than 40 mg are not recommended. In patients who have received pituitary irradiation, SANDOSTATIN LAR DEPOT should be withdrawn yearly for approximately 8 weeks to assess disease activity. If GH or IGF-1 levels increase and signs and symptoms recur, SANDOSTATIN LAR DEPOT therapy may be resumed.
2.2Carcinoid Tumors and VIPomas Patients Not Currently Receiving Octreotide Acetate Patients not currently receiving octreotide acetate should begin therapy with Sandostatin Injection given subcutaneously. The suggested daily dosage for c… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS SANDOSTATIN LAR DEPOT is available in single-dose kits for injectable suspension containing a 6-mL single-dose vial of 10 mg, 20 mg, or 30 mg strength, a prefilled syringe containing 2 mL of diluent, one vial adapter, and one sterile 1½” 19 gauge safety injection needle. An instruction booklet for the preparation of drug suspension for injection is also included with each kit. For injectable suspension: strengths 10 mg per 6 mL, 20 mg per 6 mL, or 30 mg per 6 mL single-dose vials ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Cholelithiasis and Complications of Cholelithiasis: Monitor periodically. Discontinue if complications of cholelithiasis are suspected ( 5.1 ) Glucose Metabolism: Hypoglycemia or hyperglycemia may occur. Glucose monitoring is recommended and anti-diabetic treatment may need adjustment ( 5.2 ) Thyroid Function: Hypothyroidism may occur.
Monitor thyroid levels periodically ( 5.3 ) Cardiac Function: Bradycardia, arrhythmia, or conduction abnormalities may occur. Use with caution in at-risk patients ( 5.4 ) Steatorrhea and Malabsorption of Dietary Fats: New onset steatorrhea, stool discoloration, loose stools, abdominal bloating, and weight loss may occur. If new occurrence or worsening of these symptoms are reported, evaluate for potential pancreatic exocrine insufficiency ( 5.5 )
5.1Cholelithiasis and Complications of Cholelithiasis SANDOSTATIN LAR DEPOT may inhibit gallbladder contractility and decrease bile secretion, which may lead to gallbladder abnormalities or sludge. There have been postmarketing reports of cholelithiasis (gallstones) resulting in complications, including cholecystitis, cholangitis, pancreatitis and requiring cholecystectomy in patients taking SANDOSTATIN LAR DEPOT [see Adverse Reactions (6)] . Patients should be monitored periodically.
If complications of cholelithiasis are suspected, discontinue SANDOSTATIN LAR DEPOT and treat appropriately.
5.2Hyperglycemia and Hypoglycemia Octreotide alters the balance between the counter-regulatory hormones, insulin, glucagon, and growth hormone (GH), which may result in hypoglycemia or hyperglycemia. Blood glucose levels should be monitored when SANDOSTATIN LAR DEPOT treatment is initiated, or when the dose is altered. Anti-diabetic treatment should be adjusted accordingly [see Adverse Reactions (6)] .
5.3Thyroid Function Abnormalities Octreotide suppresses the secretion of thyroid-stimulating hormone (TSH), which may result in hypothyroidism. Baseline and periodic assessment of thyroid function (TSH, total and/or free T 4 ) is recommended during chronic octreotide therapy [see Adverse Reactions (6)] .
5.4Cardiac Function Abnormalities In both acromegalic and carcinoid syndrome patients, bradycardia, arrhythmias and conduction abnormalities have been reported during octreotide therapy. Other electrocardiogram (ECG) changes were observed, such as QT prolongation, axis shifts, early repolarization, low voltage, R/S transition, early R wave progression, and nonspecific ST-T wave changes. The relationship of these events to octreotide acetate is not established because many of these patients have underlying cardiac disease.
Dose adjustments in drugs, such as beta-blockers that have bradycardic effects may be necessary. In one acromegalic patient with severe congestive heart failure (CHF), initiation of Sandostatin Injection-therapy resulted in worsening of CHF with improvement when drug was discontinued. Confirmation of a drug effect was obtained with a positive rechallenge [see Adverse Reactions (6)] .
5.5Steatorrhea and Malabsorption of Dietary Fats New onset steatorrhea, stool discoloration and loose stool have been reported in patients receiving somatostatin analogs, including SANDOSTATIN LAR DEPOT. Somatostatin analogs reversibly inhibit secretion of pancreatic enzymes and bile acids, which may result in malabsorption of dietary fats and subsequent symptoms of steatorrhea, loose stools, abdominal bloating, and weight loss. If new occurrence or worsening of these symptoms are reported in patients receiving SANDOSTATIN LAR DEPOT, evaluate patients for potential pancreatic exocrine insufficiency and manage accordingly.
5.6Changes in Vitamin B12 Levels Depressed vitamin B 12 levels and abnormal Schilling tests have been observed in some patients receiving octreotide therapy, and monitoring of vitamin B 12 levels is recommended during therapy with SANDOSTATIN LAR DEPOT.
5.7Changes in Zinc Levels Octreotide has been investigated for the… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: Cholelithiasis and Complications of Cholelithiasis [see Warnings and Precautions (5.1)] Hyperglycemia and Hypoglycemia [see Warnings and Precautions (5.2)] Thyroid Function Abnormalities [see Warnings and Precautions (5.3)] Cardiac Function Abnormalities [see Warnings and Precautions (5.4)] Steatorrhea and Malabsorption of Dietary Fats [see Warnings and Precautions (5.5)] Changes in Vitamin B12 Levels [see Warnings and Precautions (5.6)] Changes in Zinc Levels [see Warnings and Precautions (5.7)] Monitoring: Laboratory Tests [see Warnings and Precautions (5.8)] Drug Interactions [see Warnings and Precautions (5.9)] The most common adverse reactions, occurring in ≥ 20% of patients are: Acromegaly: diarrhea, cholelithiasis, abdominal pain, flatulence ( 6.1 ) Carcinoid Syndrome: back pain, fatigue, headache, abdominal pain, nausea, dizziness ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Novartis Pharmaceuticals Corporation at 1-888-669-6682 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trial of another drug and may not reflect the rates observed in practice. Acromegaly The safety of SANDOSTATIN LAR DEPOT in the treatment of acromegaly has been evaluated in three Phase 3 studies in 261 patients, including 209 exposed for 48 weeks and 96 exposed for greater than 108 weeks. SANDOSTATIN LAR DEPOT was studied primarily in a double-blind, cross-over manner.
Patients on subcutaneous Sandostatin Injection were switched to the LAR formulation followed by an open-label extension. The population age range was 14 to 81 years old and 53% were female. Approximately 35% of these acromegaly patients had not been treated with surgery and/or radiation.
Most patients received a starting dose of 20 mg every 4 weeks intramuscularly. Dose was up or down titrated based on efficacy and tolerability to a final dose between 10 mg to 60 mg every 4 weeks. Table 1 below reflects adverse events from these studies regardless of presumed causality to study drug.
Table 1. Adverse Events Occurring in ≥ 10% of Acromegalic Patients in the Phase 3 Studies Abbreviation: AEs, adverse events. WHO Preferred Term Phase 3 Studies (Pooled) Number (%) of Subjects with AEs 10 mg/20 mg/30 mg (n = 261) n (%) Diarrhea 93 (35.6) Abdominal Pain 75 (28.7) Flatulence 66 (25.3) Influenza-Like Symptoms 52 (19.9) Constipation 46 (17.6) Headache 40 (15.3) Anemia 40 (15.3) Injection-Site Pain 36 (13.8) Cholelithiasis 35 (13.4) Hypertension 33 (12.6) Dizziness 30 (11.5) Fatigue 29 (11.1) The safety of SANDOSTATIN LAR DEPOT in the treatment of acromegaly was also evaluated in a postmarketing randomized Phase 4 study.
One-hundred four (104) patients were randomized to either pituitary surgery or 20 mg of SANDOSTATIN LAR DEPOT. All the patients were treatment naïve ( ‘de novo’ ). Crossover was allowed according to treatment response and a total of 76 patients were exposed to Sandostatin LAR.
Approximately half of the patients initially randomized to SANDOSTATIN LAR DEPOT were exposed to SANDOSTATIN LAR DEPOT up to 1 year. The population age range was between 20 to 76 years old, 45% were female, 93% were Caucasian, and 1% Black. The majority of these patients were exposed to 30 mg every 4 weeks.
Table 2 below reflects the adverse events occurring in this study regardless of presumed causality to study drug. Table 2. Adverse Events Occurring in ≥ 10% of Acromegalic Patients in Phase 4 Study WHO Preferred Term Phase 4 Study SANDOSTATIN LAR DEPOT N = 76 n (%) Phase 4 Study Surgery N = 64 n (%) Diarrhea 36 (47.4) 2 (3.1) Cholelithiasis 29 (38.2) 3 (4.7) Abdominal Pain 19 (25.0) 2 (3.1) Nausea 12 (15.8) 5 (7.8) Alopecia 10 (13.2) 5 (7.8) Injection-Site… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
5.9Drug Interactions Octreotide has been associated with alterations in nutrient absorption, so it may have an effect on absorption of orally administered drugs. Concomitant administration of octreotide injection with cyclosporine may decrease blood levels of cyclosporine [see Drug Interactions (7.1)] .
7 DRUG INTERACTIONS The following drugs require monitoring and possible dose adjustment when used with SANDOSTATIN LAR DEPOT: Cyclosporine, insulin, oral hypoglycemic agents, beta-blockers, and bromocriptine ( 7 ) Lutetium Lu 177 Dotatate Injection: Discontinue SANDOSTATIN LAR DEPOT at least 4 weeks prior to each lutetium Lu 177 dotatate dose ( 7.6 )
7.1Cyclosporine Concomitant administration of octreotide injection with cyclosporine may decrease blood levels of cyclosporine and result in transplant rejection.
7.2Insulin and Oral Hypoglycemic Drugs Octreotide inhibits the secretion of insulin and glucagon. Therefore, blood glucose levels should be monitored when SANDOSTATIN LAR DEPOT treatment is initiated and when the dose is altered and anti-diabetic treatment should be adjusted accordingly.
7.3Bromocriptine Concomitant administration of octreotide and bromocriptine increases the availability of bromocriptine.
7.4Other Concomitant Drug Therapy Concomitant administration of bradycardia-inducing drugs (e.g., beta-blockers) may have an additive effect on the reduction of heart rate associated with octreotide. Dose adjustments of concomitant medication may be necessary. Octreotide has been associated with alterations in nutrient absorption, so it may have an effect on absorption of orally administered drugs.
7.5Drug Metabolism Interactions Limited published data indicate that somatostatin analogs may decrease the metabolic clearance of compounds known to be metabolized by cytochrome P450 enzymes, which may be due to the suppression of growth hormone. Since it cannot be excluded that octreotide may have this effect, other drugs mainly metabolized by CYP3A4 and which have a low therapeutic index (e.g., quinidine, terfenadine) should therefore be used with caution.
7.6Lutetium Lu 177 Dotatate Injection Octreotide competitively binds to somatostatin receptors and may interfere with the efficacy of lutetium Lu 177 dotatate. Discontinue SANDOSTATIN LAR DEPOT at least 4 weeks prior to each lutetium Lu 177 dotatate dose.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Females and Males of Reproductive Potential: Advise premenopausal females of the potential for an unintended pregnancy ( 8.3 )
8.1Pregnancy Risk Summary The limited data with SANDOSTATIN LAR DEPOT in pregnant women are insufficient to inform a drug-associated risk for major birth defects and miscarriage. In animal reproduction studies, no adverse developmental effects were observed with intravenous administration of octreotide to pregnant rats and rabbits during organogenesis at doses 7- and 13-times, respectively the maximum recommended human dose (MRHD) of 1.5 mg/day based on body surface area (BSA). Transient growth retardation, with no impact on postnatal development, was observed in rat offspring from a pre- and post-natal study of octreotide at intravenous doses below the MRHD based on BSA ( see Data ).
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data In embryo-fetal development studies in rats and rabbits, pregnant animals received intravenous doses of octreotide up to 1 mg/kg/day during the period of organogenesis.
A slight reduction in body weight gain was noted in pregnant rats at 0.1 and 1 mg/kg/day. There were no maternal effects in rabbits or embryo-fetal effects in either species up to the maximum dose tested. At 1 mg/kg/day in rats and rabbits, the dose multiple was approximately 7- and 13-times, respectively, at the highest recommended human dose of 1.5 mg/day based on BSA.
In a pre- and post-natal development rat study at intravenous doses of 0.02-1 mg/kg/day, a transient growth retardation of the offspring was observed at all doses which was possibly a consequence of growth hormone inhibition by octreotide. The doses attributed to the delayed growth are below the human dose of 1.5 mg/day, based on BSA.
8.2Lactation Risk Summary There is no information available on the presence of SANDOSTATIN LAR DEPOT in human milk, the effects of the drug on the breastfed infant, or the effects of the drug on milk production. Studies show that octreotide administered subcutaneously passes into the milk of lactating rats; however, due to species-specific differences in lactation physiology, animal data may not reliably predict drug levels in human milk ( see Data ). The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for SANDOSTATIN LAR DEPOT, and any potential adverse effects on the breastfed child from SANDOSTATIN LAR DEPOT or from the underlying maternal condition.
Data Following a subcutaneous dose (1 mg/kg) of octreotide to lactating rats, transfer of octreotide into milk was observed at a low concentration compared to plasma (milk/plasma ratio of 0.009).
8.3Females and Males of Reproductive Potential Discuss the potential for unintended pregnancy with premenopausal women as the therapeutic benefits of a reduction in GH levels and normalization of insulin-like growth factor 1 (IGF-1) concentration in acromegalic females treated with octreotide may lead to improved fertility.
8.4Pediatric Use Safety and efficacy of SANDOSTATIN LAR DEPOT in the pediatric population have not been demonstrated. No formal controlled clinical trials have been performed to evaluate the safety and effectiveness of SANDOSTATIN LAR DEPOT in pediatric patients under 6 years of age. In postmarketing reports, serious adverse events, including hypoxia, necrotizing enterocolitis, and death, have been reported with Sandostatin use in children, most notably in children under 2 years of age.
The relationship of these events to octreotide acetate has not been established as the majority of these pediatric patients had serious underlying comorbid conditions. The efficacy and safety of SANDOSTATIN LAR DEPOT was… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary The limited data with SANDOSTATIN LAR DEPOT in pregnant women are insufficient to inform a drug-associated risk for major birth defects and miscarriage. In animal reproduction studies, no adverse developmental effects were observed with intravenous administration of octreotide to pregnant rats and rabbits during organogenesis at doses 7- and 13-times, respectively the maximum recommended human dose (MRHD) of 1.5 mg/day based on body surface area (BSA). Transient growth retardation, with no impact on postnatal development, was observed in rat offspring from a pre- and post-natal study of octreotide at intravenous doses below the MRHD based on BSA ( see Data ).
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data In embryo-fetal development studies in rats and rabbits, pregnant animals received intravenous doses of octreotide up to 1 mg/kg/day during the period of organogenesis.
A slight reduction in body weight gain was noted in pregnant rats at 0.1 and 1 mg/kg/day. There were no maternal effects in rabbits or embryo-fetal effects in either species up to the maximum dose tested. At 1 mg/kg/day in rats and rabbits, the dose multiple was approximately 7- and 13-times, respectively, at the highest recommended human dose of 1.5 mg/day based on BSA.
In a pre- and post-natal development rat study at intravenous doses of 0.02-1 mg/kg/day, a transient growth retardation of the offspring was observed at all doses which was possibly a consequence of growth hormone inhibition by octreotide. The doses attributed to the delayed growth are below the human dose of 1.5 mg/day, based on BSA.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and efficacy of SANDOSTATIN LAR DEPOT in the pediatric population have not been demonstrated. No formal controlled clinical trials have been performed to evaluate the safety and effectiveness of SANDOSTATIN LAR DEPOT in pediatric patients under 6 years of age. In postmarketing reports, serious adverse events, including hypoxia, necrotizing enterocolitis, and death, have been reported with Sandostatin use in children, most notably in children under 2 years of age.
The relationship of these events to octreotide acetate has not been established as the majority of these pediatric patients had serious underlying comorbid conditions. The efficacy and safety of SANDOSTATIN LAR DEPOT was examined in a single randomized, double-blind, placebo-controlled, 6-month pharmacokinetics study in 60 pediatric patients age 6 to 17 years with hypothalamic obesity resulting from cranial insult. The mean octreotide concentration after 6 doses of 40 mg SANDOSTATIN LAR DEPOT administered by IM injection every four weeks was approximately 3 ng/mL.
Steady-state concentrations were achieved after 3 injections of a 40-mg dose. Mean BMI increased 0.1 kg/m 2 in SANDOSTATIN LAR DEPOT-treated subjects compared to 0.0 kg/m 2 in saline control-treated subjects. Efficacy was not demonstrated.
Diarrhea occurred in 11 of 30 (37%) patients treated with SANDOSTATIN LAR DEPOT. No unexpected adverse events were observed. However, with SANDOSTATIN LAR DEPOT 40 mg once a month, the incidence of new cholelithiasis in this pediatric population (33%) was higher than that seen in other adult indications, such as acromegaly (22%) or malignant carcinoid syndrome (24%), where SANDOSTATIN LAR DEPOT was dosed at 10 mg to 30 mg once a month.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of Sandostatin did not include sufficient numbers of subjects age 65 years and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
10 OVERDOSAGE Doses of 2.5 mg (2500 mcg) of Sandostatin Injection subcutaneously have caused hypoglycemia, flushing, dizziness, and nausea. Contact Poison Control (1-800-222-1222) for latest recommendations.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY SANDOSTATIN LAR DEPOT is a long-acting dosage form consisting of microspheres of the biodegradable glucose star polymer, D,L-lactic and glycolic acids copolymer, containing octreotide acetate. It maintains all of the clinical and pharmacological characteristics of the immediate-release dosage form Sandostatin Injection with the added feature of slow release of octreotide acetate from the site of injection, reducing the need for frequent administration. This slow release occurs as the polymer biodegrades, primarily through hydrolysis.
SANDOSTATIN LAR DEPOT is designed to be injected intramuscularly (intragluteally) once every 4 weeks.
12.1Mechanism of Action Octreotide exerts pharmacologic actions similar to the natural hormone, somatostatin. It is an even more potent inhibitor of growth hormone, glucagon, and insulin than somatostatin. Like somatostatin, it also suppresses LH response to GnRH, decreases splanchnic blood flow, and inhibits release of serotonin, gastrin, vasoactive intestinal peptide, secretin, motilin, and pancreatic polypeptide.
By virtue of these pharmacological actions, octreotide has been used to treat the symptoms associated with metastatic carcinoid tumors (flushing and diarrhea), and VIP secreting adenomas (watery diarrhea).
12.2Pharmacodynamics Octreotide substantially reduces and in many cases can normalize growth hormone and/or IGF-1 (somatomedin C) levels in patients with acromegaly. Single doses of Sandostatin Injection given subcutaneously have been shown to inhibit gallbladder contractility and to decrease bile secretion in normal volunteers. In controlled clinical trials, the incidence of gallstone or biliary sludge formation was markedly increased [see Warnings and Precautions (5.1)] .
Octreotide may cause clinically significant suppression of TSH.
12.3Pharmacokinetics Sandostatin Injection According to data obtained with the immediate-release formulation, Sandostatin Injection solution, after subcutaneous injection, octreotide is absorbed rapidly and completely from the injection site. Peak concentrations of 5.2 ng/mL (100-mcg dose) were reached 0.4 hours after dosing. Using a specific radioimmunoassay, intravenous and subcutaneous doses were found to be bioequivalent.
Peak concentrations and area under the curve (AUC) values were dose proportional both after subcutaneous or intravenous single doses up to 400 mcg and with multiple doses of 200 mcg 3 times daily (600 mcg/day). Clearance was reduced by about 66% suggesting nonlinear kinetics of the drug at daily doses of 600 mcg/day compared to 150 mcg/day. The relative decrease in clearance with doses above 600 mcg/day is not defined.
In healthy volunteers, the distribution of octreotide from plasma was rapid (tα 1/2 = 0.2 h), the volume of distribution (Vdss) was estimated to be
13.6L and the total body clearance was 10 L/h. In blood, the distribution of octreotide into the erythrocytes was found to be negligible and about 65% was bound in the plasma in a concentration-independent manner. Binding was mainly to lipoprotein and, to a lesser extent, to albumin.
The elimination of octreotide from plasma had an apparent half-life of 1.7 hours, compared with the 1-3 minutes with the natural hormone, somatostatin. The duration of action of subcutaneously administered Sandostatin Injection solution is variable but extends up to 12 hours depending upon the type of tumor, necessitating multiple daily dosing with this immediate-release dosage form. About 32% of the dose is excreted unchanged into the urine.
In an elderly population, dose adjustments may be necessary due to a significant increase in the half-life (46%) and a significant decrease in the clearance (26%) of the drug. In patients with acromegaly, the pharmacokinetics differ somewhat from those in healthy volunteers. A mean peak concentration of 2.8 ng/mL (100-mcg dose) was reached in 0.7 hours after subcutaneous dosing.
The Vdss was estimated to be 21.6 ±
8.5L and… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Octreotide exerts pharmacologic actions similar to the natural hormone, somatostatin. It is an even more potent inhibitor of growth hormone, glucagon, and insulin than somatostatin. Like somatostatin, it also suppresses LH response to GnRH, decreases splanchnic blood flow, and inhibits release of serotonin, gastrin, vasoactive intestinal peptide, secretin, motilin, and pancreatic polypeptide.
By virtue of these pharmacological actions, octreotide has been used to treat the symptoms associated with metastatic carcinoid tumors (flushing and diarrhea), and VIP secreting adenomas (watery diarrhea).
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING SANDOSTATIN LAR DEPOT is available in single-dose kits containing a 6-mL single-dose vial of 10 mg, 20 mg or 30 mg strength, a prefilled syringe containing 2 mL of diluent, one vial adapter, and one sterile 1½” 19 gauge safety injection needle. An instruction booklet for the preparation of drug suspension for injection is also included with each kit. Drug Product Kits 10 mg kit NDC 0078-0811-81 20 mg kit NDC 0078-0818-81 30 mg kit NDC 0078-0825-81 Demonstration kit 0078-9825-81 For prolonged storage, SANDOSTATIN LAR DEPOT should be stored at refrigerated temperatures between 2°C to 8°C (36°F to 46°F) and protected from light until the time of use.
SANDOSTATIN LAR DEPOT drug product kit should remain at room temperature for 30 to 60 minutes prior to preparation of the drug suspension. However, after preparation the drug suspension must be administered immediately.
📋 Description ▾
11 DESCRIPTION Octreotide is the acetate salt of a cyclic octapeptide. It is a long-acting octapeptide with pharmacologic properties mimicking those of the natural hormone somatostatin. Octreotide is known chemically as L-Cysteinamide, D-phenylalanyl-L-cysteinyl-L-phenylalanyl-D-tryptophyl-L-lysyl-L-threonyl-N-[2-hydroxy-1-(hydroxy-methyl) propyl]-, cyclic (2→7)-disulfide; [R-(R*,R*)].
The molecular weight of octreotide is 1019.3 g/mol (free peptide, C 49 H 66 N 10 O 10 S 2 ) and its amino acid sequence is: SANDOSTATIN LAR DEPOT is available in a single-dose vial containing the sterile drug product, which when mixed with diluent, becomes a suspension that is given as a monthly intragluteal injection. The octreotide is uniformly distributed within the microspheres which are made of a biodegradable glucose star polymer, D,L-lactic and glycolic acids copolymer. Sterile mannitol is added to the microspheres to improve suspendability.
SANDOSTATIN LAR DEPOT is available as: sterile 6-mL single-dose vials in 3 strengths delivering 10 mg, 20 mg, or 30 mg octreotide-free peptide. Each single-dose vial of SANDOSTATIN LAR DEPOT delivers: *Equivalent to 10 mg, 20 mg, or 30 mg octreotide, respectively. Name of Ingredient 10 mg 20 mg 30 mg octreotide acetate 11.2 mg * 22.4 mg * 33.6 mg * D,L-lactic and glycolic acids copolymer 188.8 mg 377.6 mg 566.4 mg mannitol 41.0 mg 81.9 mg 122.9 mg Each prefilled syringe of diluent contains: carboxymethylcellulose sodium 14 mg mannitol 12 mg poloxamer 188 4 mg water for injection q.s. to 2 mL octreotide amino acid sequence
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Cholelithiasis and Complications of Cholelithiasis Advise patients to contact their healthcare provider if they experience signs or symptoms of gallstones (cholelithiasis) or complications of cholelithiasis (e.g., cholecystitis, cholangitis and pancreatitis) [see Warnings and Precautions (5.1)] . Carcinoid Tumors and VIPomas Patients with carcinoid tumors and VIPomas should be advised to adhere closely to their scheduled return visits for reinjection in order to minimize exacerbation of symptoms [see Dosage and Administration (2.2)] .
Acromegaly Patients with acromegaly should also be urged to adhere to their return visit schedule to help assure steady control of GH and IGF-1 levels [see Dosage and Administration (2.1)] . Steatorrhea and Malabsorption of Dietary Fats Advise patients to contact their healthcare provider if they experience new or worsening symptoms of steatorrhea, stool discoloration, loose stools, abdominal bloating, and weight loss [see Warnings and Precautions (5.5)] . Pregnancy Inform female patients that treatment with SANDOSTATIN LAR DEPOT may result in unintended pregnancy [see Use in Specific Populations (8.3)] .
Distributed by: Novartis Pharmaceuticals Corporation East Hanover, New Jersey 07936 © Novartis T2024-51
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Sandostatin Injection According to data obtained with the immediate-release formulation, Sandostatin Injection solution, after subcutaneous injection, octreotide is absorbed rapidly and completely from the injection site. Peak concentrations of 5.2 ng/mL (100-mcg dose) were reached 0.4 hours after dosing. Using a specific radioimmunoassay, intravenous and subcutaneous doses were found to be bioequivalent.
Peak concentrations and area under the curve (AUC) values were dose proportional both after subcutaneous or intravenous single doses up to 400 mcg and with multiple doses of 200 mcg 3 times daily (600 mcg/day). Clearance was reduced by about 66% suggesting nonlinear kinetics of the drug at daily doses of 600 mcg/day compared to 150 mcg/day. The relative decrease in clearance with doses above 600 mcg/day is not defined.
In healthy volunteers, the distribution of octreotide from plasma was rapid (tα 1/2 = 0.2 h), the volume of distribution (Vdss) was estimated to be
13.6L and the total body clearance was 10 L/h. In blood, the distribution of octreotide into the erythrocytes was found to be negligible and about 65% was bound in the plasma in a concentration-independent manner. Binding was mainly to lipoprotein and, to a lesser extent, to albumin.
The elimination of octreotide from plasma had an apparent half-life of 1.7 hours, compared with the 1-3 minutes with the natural hormone, somatostatin. The duration of action of subcutaneously administered Sandostatin Injection solution is variable but extends up to 12 hours depending upon the type of tumor, necessitating multiple daily dosing with this immediate-release dosage form. About 32% of the dose is excreted unchanged into the urine.
In an elderly population, dose adjustments may be necessary due to a significant increase in the half-life (46%) and a significant decrease in the clearance (26%) of the drug. In patients with acromegaly, the pharmacokinetics differ somewhat from those in healthy volunteers. A mean peak concentration of 2.8 ng/mL (100-mcg dose) was reached in 0.7 hours after subcutaneous dosing.
The Vdss was estimated to be 21.6 ±
8.5L and the total body clearance was increased to 18 L/h. The mean percent of the drug bound was 41.2%. The disposition and elimination half-lives were similar to normals. The half-life in renal-impaired patients was slightly longer than normal subjects (2.4-3.1 h versus 1.9 h). The clearance in renal-impaired patients was 7.3-8.8 L/h as compared to
8.3L/h in healthy subjects. In patients with severe renal failure requiring dialysis, clearance was reduced to about half that found in healthy subjects (from approximately 10 L/h to
4.5L/h). Patients with liver cirrhosis showed prolonged elimination of drug, with octreotide half-life increasing to 3.7 h and total body clearance decreasing to
5.9L/h, whereas patients with fatty liver disease showed half-life increasing to 3.4 h and total body clearance of
8.4L/h. In normal subjects, octreotide half-life is 1.9 h and the clearance is
8.3L/h which is comparable with the clearance in fatty-liver patients. SANDOSTATIN LAR DEPOT The magnitude and duration of octreotide serum concentrations after an intramuscular injection of the long-acting depot formulation SANDOSTATIN LAR DEPOT reflect the release of drug from the microsphere polymer matrix. Drug release is governed by the slow biodegradation of the microspheres in the muscle, but once present in the systemic circulation, octreotide distributes and is eliminated according to its known pharmacokinetic properties which are as follows.
After a single IM injection of the long-acting depot dosage form SANDOSTATIN LAR DEPOT in healthy volunteer subjects, the serum octreotide concentration reached a transient initial peak of about 0.03 ng/mL/mg within 1 hour after administration progressively declining over the following 3 to 5 days to a nadir of < 0.01 ng/mL/mg, then slowly increasing and reaching a plateau about 2 to 3 we… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Octreotide substantially reduces and in many cases can normalize growth hormone and/or IGF-1 (somatomedin C) levels in patients with acromegaly. Single doses of Sandostatin Injection given subcutaneously have been shown to inhibit gallbladder contractility and to decrease bile secretion in normal volunteers. In controlled clinical trials, the incidence of gallstone or biliary sludge formation was markedly increased [see Warnings and Precautions (5.1)] .
Octreotide may cause clinically significant suppression of TSH.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Acromegaly The clinical trials of SANDOSTATIN LAR DEPOT were performed in patients who had been receiving Sandostatin Injection for a period of weeks to as long as 10 years. The acromegaly studies with SANDOSTATIN LAR DEPOT described below were performed in patients who achieved GH levels of < 10 ng/mL (and, in most cases < 5 ng/mL) while on subcutaneous Sandostatin Injection. However, some patients enrolled were partial responders to subcutaneous Sandostatin Injection, i.e., GH levels were reduced by > 50% on subcutaneous Sandostatin Injection compared to the untreated state, although not suppressed to < 5 ng/mL.
SANDOSTATIN LAR DEPOT was evaluated in three clinical trials in acromegalic patients. In 2 of the clinical trials, a total of 101 patients were entered who had, in most cases, achieved a GH level < 5 ng/mL on Sandostatin Injection given in doses of 100 mcg or 200 mcg three times daily. Most patients were switched to 20 mg or 30 mg doses of SANDOSTATIN LAR DEPOT given once every 4 weeks for up to 27 to 28 injections.
A few patients received doses of 10 mg and a few required doses of 40 mg. Growth hormone and IGF-1 levels were at least as well controlled with SANDOSTATIN LAR DEPOT as they had been on Sandostatin Injection and this level of control remained for the entire duration of the trials. A third trial was a 12-month study that enrolled 151 patients who had a GH level < 10 ng/mL after treatment with Sandostatin Injection (most had levels < 5 ng/mL).
The starting dose of SANDOSTATIN LAR DEPOT was 20 mg every 4 weeks for 3 doses. Thereafter, patients received 10 mg, 20 mg, or 30 mg every 4 weeks, depending upon the degree of GH suppression [see Dosage and Administration (2)] . Growth hormone and IGF-1 were at least as well controlled on SANDOSTATIN LAR DEPOT as they had been on Sandostatin Injection.
Table 5 summarizes the data on hormonal control (GH and IGF-1) for those patients in the first two clinical trials who received all 27 to 28 injections of SANDOSTATIN LAR DEPOT. Table 5. Hormonal Response in Acromegalic Patients Receiving 27 to 28 Injections During 1 Treatment With SANDOSTATIN LAR DEPOT 1 Average of monthly levels of GH and IGF-1 over the course of the trials.
Mean Hormone Level Sandostatin Injection S.C. SANDOSTATIN LAR DEPOT n % n % GH < 5.0 ng/mL 69/88 78 73/88 83 < 2.5 ng/mL 44/88 50 41/88 47 < 1.0 ng/mL 6/88 7 10/88 11 IGF-1 normalized 36/88 41 45/88 51 GH < 5.0 ng/mL + IGF-1 normalized 36/88 41 45/88 51 < 2.5 ng/mL + IGF-1 normalized 30/88 34 37/88 42 < 1.0 ng/mL + IGF-1 normalized 5/88 6 10/88 11 For the 88 patients in Table 5, a mean GH level of < 2.5 ng/mL was observed in 47% receiving SANDOSTATIN LAR DEPOT. Over the course of the trials, 42% of patients maintained mean growth hormone levels of < 2.5 ng/mL and mean normal IGF-1 levels.
Table 6 summarizes the data on hormonal control (GH and IGF-1) for those patients in the third clinical trial who received all 12 injections of SANDOSTATIN LAR DEPOT. Table 6. Hormonal Response in Acromegalic Patients Receiving 12 Injections During 1 Treatment With SANDOSTATIN LAR DEPOT 1 Average of monthly levels of GH and IGF-1 over the course of the trial.
Mean Hormone Level Sandostatin Injection S.C. SANDOSTATIN LAR DEPOT n % n % GH < 5.0 ng/mL 116/122 95 118/122 97 < 2.5 ng/mL 84/122 69 80/122 66 < 1.0 ng/mL 25/122 21 28/122 23 IGF-1 normalized 82/122 67 82/122 67 GH < 5.0 ng/mL + IGF-1 normalized 80/122 66 82/122 67 < 2.5 ng/mL + IGF-1 normalized 65/122 53 70/122 57 < 1.0 ng/mL + IGF-1 normalized 23/122 19 27/122 22 For the 122 patients in Table 6, who received all 12 injections in the third trial, a mean GH level of < 2.5 ng/mL was observed in 66% receiving SANDOSTATIN LAR DEPOT.
Over the course of the trial, 57% of patients maintained mean growth hormone levels of < 2.5 ng/mL and mean normal IGF-1 levels. In comparing the hormonal response in these trials, note that a higher percentage of patients in the third trial suppressed th… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Studies in laboratory animals have demonstrated no mutagenic potential of Sandostatin. No mutagenic potential of the polymeric carrier in SANDOSTATIN LAR DEPOT, D,L-lactic and glycolic acids copolymer, was observed in the Ames mutagenicity test. No carcinogenic potential was demonstrated in mice treated subcutaneously with octreotide for 85-99 weeks at doses up to 2 mg/kg/day (8-times the human exposure based on BSA).
In a 116-week subcutaneous study in rats administered octreotide, a 27% and 12% incidence of injection-site sarcomas or squamous cell carcinomas was observed in males and females, respectively, at the highest dose level of 1.25 mg/kg/day (10-times the human exposure based on BSA) compared to an incidence of 8% to 10% in the vehicle-control groups. The increased incidence of injection-site tumors was most probably caused by irritation and the high sensitivity of the rat to repeated subcutaneous injections at the same site.
Rotating injection sites would prevent chronic irritation in humans. There have been no reports of injection-site tumors in patients treated with Sandostatin Injection for at least 5 years. There was also a 15% incidence of uterine adenocarcinomas in the 1.25 mg/kg/day females compared to 7% in the saline-control females and 0% in the vehicle-control females.
The presence of endometritis coupled with the absence of corpora lutea , the reduction in mammary fibroadenomas, and the presence of uterine dilatation suggest that the uterine tumors were associated with estrogen dominance in the aged female rats which does not occur in humans. Octreotide did not impair fertility in rats at doses up to 1 mg/kg/day, which represents 7-times the human exposure based on BSA.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Studies in laboratory animals have demonstrated no mutagenic potential of Sandostatin. No mutagenic potential of the polymeric carrier in SANDOSTATIN LAR DEPOT, D,L-lactic and glycolic acids copolymer, was observed in the Ames mutagenicity test. No carcinogenic potential was demonstrated in mice treated subcutaneously with octreotide for 85-99 weeks at doses up to 2 mg/kg/day (8-times the human exposure based on BSA).
In a 116-week subcutaneous study in rats administered octreotide, a 27% and 12% incidence of injection-site sarcomas or squamous cell carcinomas was observed in males and females, respectively, at the highest dose level of 1.25 mg/kg/day (10-times the human exposure based on BSA) compared to an incidence of 8% to 10% in the vehicle-control groups. The increased incidence of injection-site tumors was most probably caused by irritation and the high sensitivity of the rat to repeated subcutaneous injections at the same site.
Rotating injection sites would prevent chronic irritation in humans. There have been no reports of injection-site tumors in patients treated with Sandostatin Injection for at least 5 years. There was also a 15% incidence of uterine adenocarcinomas in the 1.25 mg/kg/day females compared to 7% in the saline-control females and 0% in the vehicle-control females.
The presence of endometritis coupled with the absence of corpora lutea , the reduction in mammary fibroadenomas, and the presence of uterine dilatation suggest that the uterine tumors were associated with estrogen dominance in the aged female rats which does not occur in humans. Octreotide did not impair fertility in rats at doses up to 1 mg/kg/day, which represents 7-times the human exposure based on BSA.
📄 Recent Major Changes ▾
Warnings and Precautions, Steatorrhea and Malabsorption of Dietary Fats ( 5.5 ) 7/2024
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL NDC 0078-0811-81 Sandostatin ® LAR Depot (octreotide acetate) for injectable suspension, for gluteal intramuscular use 10 mg For Intragluteal Injection Rx only NOVARTIS PRINCIPAL DISPLAY PANEL NDC 0078-0811-81 Sandostatin® LAR Depot (octreotide acetate) for injectable suspension, for gluteal intramuscular use 10 mg For Intragluteal Injection Rx only NOVARTIS
PRINCIPAL DISPLAY PANEL NDC 0078-0818-81 Sandostatin ® LAR Depot (octreotide acetate) for injectable suspension, for gluteal intramuscular use 20 mg For Intragluteal Injection Rx only NOVARTIS PRINCIPAL DISPLAY PANEL NDC 0078-0818-81 Sandostatin® LAR Depot (octreotide acetate) for injectable suspension, for gluteal intramuscular use 20 mg For Intragluteal Injection Rx only NOVARTIS
PRINCIPAL DISPLAY PANEL NDC 0078-0825-81 Sandostatin ® LAR Depot (octreotide acetate) for injectable suspension, for gluteal intramuscular use 30 mg For Intragluteal Injection Rx only NOVARTIS PRINCIPAL DISPLAY PANEL NDC 0078-0825-81 Sandostatin® LAR Depot (octreotide acetate) for injectable suspension, for gluteal intramuscular use 30 mg For Intragluteal Injection Rx only NOVARTIS
Medicaid utilization & spend
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | ✓ Available |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |