
Irbesartan and Hydrochlorothiazide 300 mg; 12.5 mg Tablet, Film Coated, 90-count — NDC 0093-8232-98 (Billing 00093-8232-98)
This is a package of 90 tablets of Irbesartan and Hydrochlorothiazide 300 mg; 12.5 mg Tablet, Film Coated from Teva Pharmaceuticals USA, Inc., marketed since Aug 2013 and currently FDA-listed; retail pharmacies pay about $0.1881 per tablet (NADAC).
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 041897
- GCN: 11295
- GPI-14 (Medi-Span): 36994002300340
- HICL (First Databank): 018963
- AHFS class code: 24:32.08.00
- RxCUI (RxNorm): 310792
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Thiazide Diuretic class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Hydrochlorothiazide is used alone or in combination with other medications to treat high blood pressure. Hydrochlorothiazide is used to treat edema (fluid retention; excess fluid held in body tissues) caused by various medical problems, including heart, kidney, and liver disease and to treat edema caused by using certain medications including estrogen and corticosteroids. Hydrochlorothiazide is in a class of medications called diuretics ('water pills'). It works by causing the kidneys to get rid of unneeded water and salt from the body into the urine. High blood pressure is a common condition...
Read the full MedlinePlus article ↗Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.188 | $16.93 / 90 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.4038 | $36.34 / 90 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.2914 | $26.23 / 90 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 00093-8232-56 0093-8232-56 Main listing | 30 TABLET, FILM COATED in 1 BOTTLE | $0.1881 / ea | $5.64 | 2013-08-27 | — | Active |
| 00093-8232-98 You're viewing this | 90 TABLET, FILM COATED in 1 BOTTLE | $0.1881 / ea | $16.93 | 2013-08-27 | — | Active |
You're viewing the largest of 2 pack sizes for this product.
This pack effectively ties for the lowest per-ea cost of the 2 priced pack sizes ($0.1881 NADAC).
This pack accounts for about 16% of this product's recent Medicaid fills; most go to the 30 tablets pack. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 00093-8232-56?
What NDC number is used to bill for this package of Irbesartan and Hydrochlorothiazide 300 mg; 12.5 mg Tablet, Film Coated?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Irbesartan and Hydrochlorothiazide 300 mg/1; 12.5 mgthis 00093-8232-98 | Teva | 90 tablets | $0.188 | AB | Availability likely | — |
| Irbesartan and Hydrochlorothiazide 300 mg/1; 12.5 mg 43547-0331-03 | Solco | 30 tablets | $0.188 | AB | Availability likely | — |
| Irbesartan and Hydrochlorothiazide 300 mg/1; 12.5 mg 00054-0255-13 | Hikma | 30 tablets | $0.219 | — | FDA listed | +16% |
| Avalide 300 mg/1; 12.5 mg 00024-5856-30 | Sanofi-Aventis | 30 tablets | — | AB | FDA listed | — |
| Irbesartan and Hydrochlorothiazide 300 mg/1; 12.5 mg 29300-0216-10 | Unichem | 1000 tablets | — | — | FDA listed | — |
| Irbesartan and Hydrochlorothiazide 300 mg/1; 12.5 mg 33342-0058-06 | Macleods | 10 tablets | — | AB | FDA listed | — |
| Irbesartan and Hydrochlorothiazide 300 mg/1; 12.5 mg 46708-0443-10 | Alembic | 10 tablets | — | AB | FDA listed | — |
| Irbesartan and Hydrochlorothiazide 300 mg/1; 12.5 mg 62332-0052-10 | Alembic | 10 tablets | — | AB | FDA listed | — |
| Irbesartan and Hydrochlorothiazide 300 mg/1; 12.5 mg 65862-0630-05 | Aurobindo | 500 tablets | — | — | FDA listed | — |
| Irbesartan and Hydrochlorothiazide 300 mg/1; 12.5 mg 70518-1550-00 | REMEDYREPACK | 90 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII R75537T0T4
Hypromellose 2910 is a plant-derived thickening agent made from cellulose. It serves as a binder that holds tablet ingredients together, a film-coating for pills, and a viscosity controller in liquids.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII LQA7B6G8JG
A synthetic polymer made by combining water-soluble compounds. It acts as a surfactant and solubilizer to help mix oil and water-based ingredients, improving the medicine's texture and how active ingredients dissolve.
-
UNII B697894SGQ
Polyethylene glycol 400 is a clear, thick liquid made from petroleum-derived polymers. It acts as a solvent and humectant in medicines, helping dissolve active ingredients and retain moisture in the formulation.
-
UNII 30IQX730WE
Polyethylene glycol 6000 is a synthetic polymer made from ethylene glycol units. It acts as a binder, filler, and solubilizer in medicines to help hold ingredients together, add bulk, and improve how well active drugs dissolve and absorb.
-
UNII U725QWY32X
Povidone K30 is a synthetic polymer made from petroleum. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in the stomach so the medicine can be absorbed.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
14 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: FETAL TOXICITY When pregnancy is detected, discontinue irbesartan and hydrochlorothiazide tablets as soon as possible [see Warnings and Precautions ( 5.1 ) and Use in Specific Populations ( 8.1 )]. Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus [see Warnings and Precautions ( 5.1 ) and Use in Specific Populations ( 8.1 )] . WARNING: FETAL TOXICITY See full prescribing information for complete boxed warning .
When pregnancy is detected, discontinue irbesartan and hydrochlorothiazide tablets as soon as possible. ( 5.1 , 8.1 ) Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus. ( 5.1 , 8.1 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Irbesartan and hydrochlorothiazide tablets are indicated for the treatment of hypertension. Irbesartan and hydrochlorothiazide tablets may be used in patients whose blood pressure is not adequately controlled on monotherapy. Irbesartan and hydrochlorothiazide tablets may also be used as initial therapy in patients who are likely to need multiple drugs to achieve their blood pressure goals.
The choice of irbesartan and hydrochlorothiazide tablets as initial therapy for hypertension should be based on an assessment of potential benefits and risks. Patients with stage 2 (moderate or severe) hypertension are at relatively high risk for cardiovascular events (such as strokes, heart attacks, and heart failure), kidney failure, and vision problems, so prompt treatment is clinically relevant. The decision to use a combination as initial therapy should be individualized and may be shaped by considerations such as the baseline blood pressure, the target goal, and the incremental likelihood of achieving goal with a combination compared with monotherapy.
Data from Studies V and VI [see Clinical Studies ( 14.2 )] provide estimates of the probability of reaching a blood pressure goal with irbesartan and hydrochlorothiazide tablets compared to irbesartan or hydrochlorothiazide (HCTZ) monotherapy. The relationship between baseline blood pressure and achievement of a SeSBP <140 or <130 mmHg or SeDBP <90 or <80 mmHg in patients treated with irbesartan and hydrochlorothiazide tablets compared to patients treated with irbesartan or HCTZ monotherapy are shown in Figures 1a through 2b.
Figure 1a: Probability of Achieving SBP <140 mmHg in Patients from Initial Therapy Studies V (Week 8) and VI (Week 7) * Figure 1b: Probability of Achieving SBP <130 mmHg in Patients from Initial Therapy Studies V (Week 8) and VI (Week 7) * Figure 2a: Probability of Achieving DBP <90 mmHg in Patients from Initial Therapy Studies V (Week 8) and VI (Week 7) * Figure 2b: Probability of Achieving DBP <80 mmHg in Patients from Initial Therapy Studies V (Week 8) and VI (Week 7) * * For all probability curves, patients without blood pressure measurements at Week 7 (Study VI) and Week 8 (Study V) were counted as not reaching goal (intent-to-treat analysis).
The above graphs provide a rough approximation of the likelihood of reaching a targeted blood pressure goal (e.g., Week 8 sitting systolic blood pressure ≤140 mmHg) for the treatment groups. The curve of each treatment group in each study was estimated by logistic regression modeling from all available data of that treatment group. The estimated likelihood at the right tail of each curve is less reliable due to small numbers of subjects with high baseline blood pressures.
For example, a patient with a blood pressure of 180/105 mmHg has about a 25% likelihood of achieving a goal of <140 mmHg (systolic) and 50% likelihood of achieving <90 mmHg (diastolic) on irbesartan alone (and lower still likelihoods on HCTZ alone). The likelihood of achieving these goals on irbesartan and hydrochlorothiazide tablets rises to about 40% (systolic) or 70% (diastolic). Irbesartan and hydrochlorothiazide tablets are a combination of irbesartan, an angiotensin II receptor antagonist, and hydrochlorothiazide, a thiazide diuretic, indicated for hypertension: In patients not adequately controlled with monotherapy.
( 1 ) As initial therapy in patients likely to need multiple drugs to achieve their blood pressure goals. ( 1 ) Figure 1a Figure 1b Figure 2a Figure 2b
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION General Considerations Maximum effects within 2 to 4 weeks after dose change. ( 2.1 ) Renal impairment: Not recommended for patients with severe renal impairment (creatinine clearance <30 mL/min). ( 2.1 , 5.8 ) Hypertension Initiate with 150/12.5 mg. Titrate to 300/12.5 mg then 300/25 mg if needed. ( 2.2 ) Replacement therapy: May be substituted for titrated components. ( 2.3 )
2.1General Considerations The side effects of irbesartan are generally rare and apparently independent of dose; those of hydrochlorothiazide are a mixture of dose-dependent (primarily hypokalemia) and dose-independent phenomena (e.g., pancreatitis), the former much more common than the latter [see Adverse Reactions ( 6 )] . Maximum antihypertensive effects are attained within 2 to 4 weeks after a change in dose. Irbesartan and hydrochlorothiazide tablets may be administered with or without food.
Irbesartan and hydrochlorothiazide tablets may be administered with other antihypertensive agents. Renal Impairment The usual regimens of therapy with irbesartan and hydrochlorothiazide tablets may be followed as long as the patient’s creatinine clearance is >30 mL/min. In patients with more severe renal impairment, loop diuretics are preferred to thiazides, so irbesartan and hydrochlorothiazide tablets are not recommended.
Hepatic Impairment No dosage adjustment is necessary in patients with hepatic impairment.
2.2Add-On Therapy In patients not controlled on monotherapy with irbesartan or hydrochlorothiazide, the recommended doses of irbesartan and hydrochlorothiazide tablets, in order of increasing mean effect, are (irbesartan and hydrochlorothiazide) 150/12.5 mg, 300/12.5 mg, and 300/25 mg. The largest incremental effect will likely be in the transition from monotherapy to 150/12.5 mg [see Clinical Studies ( 14.2 )] .
2.3Replacement Therapy Irbesartan and hydrochlorothiazide tablets may be substituted for the titrated components.
2.4Initial Therapy The usual starting dose is irbesartan and hydrochlorothiazide tablets 150/12.5 mg once daily. The dosage can be increased after 1 to 2 weeks of therapy to a maximum of 300/25 mg once daily as needed to control blood pressure [see Clinical Studies ( 14.2 )] . Irbesartan and hydrochlorothiazide tablets are not recommended as initial therapy in patients with intravascular volume depletion [see Warnings and Precautions ( 5.2 )] .
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Irbesartan and hydrochlorothiazide tablets USP, 150/12.5 mg are light pink to pink film-coated, capsule-shaped tablets, debossed with “TEVA” on one side of the tablet and “7238” on the other side. Irbesartan and hydrochlorothiazide tablets USP, 300/12.5 mg are light pink to pink film-coated, capsule-shaped tablets, debossed with “TEVA” on one side of the tablet and “7239” on the other side. 150 mg irbesartan/12.5 mg hydrochlorothiazide tablets ( 3 ) 300 mg irbesartan/12.5 mg hydrochlorothiazide tablets ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Irbesartan and hydrochlorothiazide tablets are contraindicated in patients who are hypersensitive to any component of this product. Because of the hydrochlorothiazide component, this product is contraindicated in patients with anuria or hypersensitivity to other sulfonamide-derived drugs. Do not coadminister aliskiren with irbesartan and hydrochlorothiazide tablets in patients with diabetes [see Drug Interactions ( 7 )].
Hypersensitivity to any component of this product. ( 4 ) Anuria. ( 4 ) Hypersensitivity to sulfonamide-derived drugs.
( 4 ) Do not coadminister aliskiren with irbesartan and hydrochlorothiazide tablets in patients with diabetes. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hypotension: Correct volume depletion prior to administration. ( 5.2 ) Impaired renal function. ( 5.7 ) Thiazide diuretics may cause an exacerbation or activation of systemic lupus erythematosus. ( 5.4 ) Acute angle-closure glaucoma, acute myopia, and choroidal effusion. ( 5.8 )
5.1Fetal Toxicity Irbesartan and hydrochlorothiazide can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Resulting oligohydramnios can be associated with fetal lung hypoplasia and skeletal deformations.
Potential neonatal adverse effects include skull hypoplasia, anuria, hypotension, renal failure, and death. When pregnancy is detected, discontinue irbesartan and hydrochlorothiazide as soon as possible [see Use in Specific Populations ( 8.1 )]. Thiazides cross the placenta and use of thiazides during pregnancy is associated with a risk of fetal or neonatal jaundice, thrombocytopenia, and possibly other adverse reactions that have occurred in adults.
5.2Hypotension in Volume or Salt-Depleted Patients Excessive reduction of blood pressure was rarely seen in patients with uncomplicated hypertension treated with irbesartan alone (<0.1%) or with irbesartan and hydrochlorothiazide (approximately 1%). Initiation of antihypertensive therapy may cause symptomatic hypotension in patients with intravascular volume or sodium depletion, e.g., in patients treated vigorously with diuretics or in patients on dialysis. Such volume depletion should be corrected prior to administration of antihypertensive therapy.
If hypotension occurs, the patient should be placed in the supine position and, if necessary, given an intravenous infusion of normal saline. A transient hypotensive response is not a contraindication to further treatment, which usually can be continued without difficulty once the blood pressure has stabilized.
5.3Hypersensitivity Reaction Hydrochlorothiazide Hypersensitivity reactions to hydrochlorothiazide may occur in patients with or without a history of allergy or bronchial asthma, but are more likely in patients with such a history.
5.4Systemic Lupus Erythematosus Hydrochlorothiazide Thiazide diuretics have been reported to cause exacerbation or activation of systemic lupus erythematosus.
5.5Electrolyte and Metabolic Imbalances Irbesartan and Hydrochlorothiazide In double-blind clinical trials of various doses of irbesartan and hydrochlorothiazide, the incidence of hypertensive patients who developed hypokalemia (serum potassium <3.5 mEq/L) was 7.5% versus 6.0% for placebo; the incidence of hyperkalemia (serum potassium >5.7 mEq/L) was <1.0% versus 1.7% for placebo. No patient discontinued due to increases or decreases in serum potassium. On average, the combination of irbesartan and hydrochlorothiazide had no effect on serum potassium.
Higher doses of irbesartan ameliorated the hypokalemic response to hydrochlorothiazide. Coadministration of irbesartan and hydrochlorothiazide tablets with potassium-sparing diuretics, potassium supplements, potassium-containing salt substitutes or other drugs that raise serum potassium levels may result in hyperkalemia, sometimes severe. Monitor serum potassium in such patients.
Hydrochlorothiazide Hydrochlorothiazide can cause hypokalemia and hyponatremia. Hypomagnesemia can result in hypokalemia which appears difficult to treat despite potassium repletion. Drugs that inhibit the renin-angiotensin system can cause hyperkalemia.
Monitor serum electrolytes periodically. Hyperuricemia may occur or frank gout may be precipitated in certain patients receiving thiazide therapy. Hydrochlorothiazide may alter glucose tolerance and raise serum levels of cholesterol and triglycerides.
The antihypertensive effects of the drug may be enhanced in the post-sympathectomy patient. Thiazides may decrease urinary… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Most common adverse events (≥5% on irbesartan and hydrochlorothiazide tablets and more often than on placebo) are dizziness, fatigue, and musculoskeletal pain. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Teva at 1-888-838-2872 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The adverse reaction information from clinical trials does, however, provide a basis for identifying the adverse events that appear to be related to drug use and for approximating rates. Irbesartan and Hydrochlorothiazide Irbesartan and hydrochlorothiazide tablets have been evaluated for safety in 1694 patients treated for essential hypertension in 6 clinical trials.
In Studies I through IV with irbesartan and hydrochlorothiazide, no adverse events peculiar to this combination drug product have been observed. Adverse events have been limited to those that were reported previously with irbesartan or hydrochlorothiazide (HCTZ). The overall incidence of adverse events was similar with the combination and placebo.
In general, treatment with irbesartan and hydrochlorothiazide was well tolerated. For the most part, adverse events have been mild and transient in nature and have not required discontinuation of therapy. In controlled clinical trials, discontinuation of irbesartan and hydrochlorothiazide therapy due to clinical adverse events was required in only 3.6%.
This incidence was significantly less (p=0.023) than the 6.8% of patients treated with placebo who discontinued therapy. In these double-blind controlled clinical trials, the following adverse events reported with irbesartan and hydrochlorothiazide occurred in ≥1% of patients, and more often on the irbesartan and hydrochlorothiazide combination than on placebo, regardless of drug relationship: Irbesartan/HCTZ Placebo Irbesartan HCTZ (n=898) (n=236) (n=400) (n=380) (%) (%) (%) (%) Body as a Whole Chest Pain 2 1 2 2 Fatigue 6 3 4 3 Influenza 3 1 2 2 Cardiovascular Edema 3 3 2 2 Tachycardia 1 0 1 1 Gastrointestinal Abdominal Pain 2 1 2 2 Dyspepsia/heartburn 2 1 0 2 Nausea/vomiting 3 0 2 2 Immunology Allergy 1 0 1 1 Musculoskeletal Musculoskeletal Pain 6 5 6 10 Nervous System Dizziness 8 4 6 5 Dizziness Orthostatic 1 0 1 1 Renal/Genitourinary Abnormality Urination 2 1 1 2 The following adverse events were also reported at a rate of 1% or greater, but were as, or more, common in the placebo group: headache, sinus abnormality, cough, URI, pharyngitis, diarrhea, rhinitis, urinary tract infection, rash, anxiety/nervousness, and muscle cramp.
Adverse events occurred at about the same rates in men and women, older and younger patients, and black and non-black patients. Adverse events in Studies V and VI were similar to those described above in Studies I through IV. Irbesartan Other adverse events that have been reported with irbesartan, without regard to causality, are listed below: Body as a Whole: fever, chills, orthostatic effects, facial edema, upper extremity edema Cardiovascular: flushing, hypertension, cardiac murmur, myocardial infarction, angina pectoris, hypotension, syncope, arrhythmic/conduction disorder, cardiorespiratory arrest, heart failure, hypertensive crisis Dermatologic: pruritus, dermatitis, ecchymosis, erythema face, urticaria Endocrine/Metabolic/Electrolyte Imbalances: sexual dysfunction, libido change, gout Gastrointestinal: diarrhea, constipation, gastroenteritis, flatulence, abdominal distention Musculoskeletal/Connective Tissue: musculoskeletal trauma, extremity swelling, muscle cramp, arthritis, muscle ache, musculoskeletal chest pain, joint stiffness, bursitis, muscle weakness Nervous System: anxiety/nervousness, sleep disturbance, numbness, somnolence, vertigo,… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS NSAIDs and selective COX-2 inhibitors: Can reduce diuretic, natriuretic of diuretic, may lead to increased risk of renal impairment and reduced antihypertensive effect. Monitor renal function periodically. ( 7 ) Dual blockade of the renin-angiotensin system: Increased risk of renal impairment, hypotension, and hyperkalemia.
( 7 ) Antidiabetic drugs: Dosage adjustment of antidiabetic may be required. ( 7 ) Cholestyramine and colestipol: Reduced absorption of thiazides. ( 7 ) Lithium: Increases in serum lithium concentrations and lithium toxicity.
( 7 ) Carbamazepine: Increased risk of hyponatremia. ( 7 )
7.1Nonsteroidal Anti-inflammatory Agents Including Selective Cyclooxygenase-2 Inhibitors (COX-2 Inhibitors) Irbesartan In patients who are elderly, volume depleted (including those on diuretic therapy), or with compromised renal function, coadministration of NSAIDs, including selective COX-2 inhibitors, with angiotensin II receptor antagonists, including irbesartan, may result in deterioration of renal function, including possible acute renal failure. These effects are usually reversible. Therefore, monitor renal function and blood pressure periodically in patients receiving irbesartan and NSAID therapy.
Hydrochlorothiazide Administration of a nonsteroidal anti-inflammatory agent, including a selective COX-2 inhibitor can reduce the diuretic, natriuretic, and antihypertensive effects of loop, potassium-sparing, and thiazide diuretics. Therefore, when irbesartan and hydrochlorothiazide tablets and nonsteroidal anti-inflammatory agents are used concomitantly, the patient should be observed closely to determine if the desired effect of the diuretic is obtained.
7.2Dual Blockade of the Renin-Angiotensin System (RAS) Dual blockade of the RAS with angiotensin-receptor blockers, ACE inhibitors, or aliskiren is associated with increased risks of hypotension, hyperkalemia, and changes in renal function (including acute renal failure) compared to monotherapy. Closely monitor blood pressure, renal function, and electrolytes in patients on irbesartan and hydrochlorothiazide and other agents that affect the RAS. In most patients no benefit has been associated with using two RAS inhibitors concomitantly.
In general, avoid combined use of RAS inhibitors. Do not coadminister aliskiren with irbesartan and hydrochlorothiazide tablets in patients with diabetes. Avoid use of aliskiren with irbesartan and hydrochlorothiazide tablets in patients with renal impairment (GFR <60 mL/min).
7.3Agents Increasing Serum Potassium Coadministration of irbesartan and hydrochlorothiazide tablets with other drugs that raise serum potassium levels may result in hyperkalemia, sometimes severe. Monitor serum potassium in such patients.
7.4Antidiabetic Drugs (oral agents and insulin) Dosage adjustment of the antidiabetic drug may be required when coadministered with hydrochlorothiazide.
7.5Cholestyramine and Colestipol Resins Absorption of hydrochlorothiazide is impaired in the presence of anionic exchange resins. Stagger the dosage of hydrochlorothiazide and the resin such that irbesartan and hydrochlorothiazide tablets are administered at least 4 hours before or 4 to 6 hours after the administration of the resin.
7.6Lithium Increases in serum lithium concentrations and lithium toxicity have been reported with concomitant use of irbesartan or thiazide diuretics. Monitor lithium levels in patients receiving irbesartan and hydrochlorothiazide tablets and lithium.
7.7Carbamazepine Concomitant use of carbamazepine and hydrochlorothiazide has been associated with the risk of symptomatic hyponatremia. Monitor electrolytes during concomitant use.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Potential for adverse effects in infant. ( 8.2 )
8.1Pregnancy Risk Summary Irbesartan and hydrochlorothiazide can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death [ see Clinical Considerations ] . Most epidemiologic studies examining fetal abnormalities after exposure to antihypertensive use in the first trimester have not distinguished drugs affecting the renin-angiotensin system from other antihypertensive agents.
When pregnancy is detected, discontinue irbesartan and hydrochlorothiazide as soon as possible. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes regardless of drug exposure. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo-fetal risk Hypertension in pregnancy increases the maternal risk for preeclampsia, gestational diabetes, premature delivery, and delivery complications (e.g., need for cesarean section and postpartum hemorrhage). Hypertension increases the fetal risk for intrauterine growth restriction and intrauterine death. Pregnant women with hypertension should be carefully monitored and managed accordingly.
Fetal/neonatal adverse reactions Oligohydramnios in pregnant women who use drugs affecting the renin-angiotensin system in the second and third trimesters of pregnancy can result in the following: reduced fetal renal function leading to anuria and renal failure, fetal lung hypoplasia, skeletal deformations, including skull hypoplasia, hypotension, and death. Perform serial ultrasound examinations to assess the intra-amniotic environment. Fetal testing may be appropriate, based on the week of pregnancy.
Patients and physicians should be aware, however, that oligohydramnios may not appear until after the fetus has sustained irreversible injury. Closely observe infants with histories of in utero exposure to irbesartan and hydrochlorothiazide for hypotension, oliguria, and hyperkalemia and other symptoms of renal impairment. In neonates with a history of in utero exposure to irbesartan and hydrochlorothiazide, if oliguria or hypotension occurs, direct attention toward support of blood pressure and renal perfusion.
Exchange transfusion or dialysis may be required as means of reversing hypotension and/or substituting for disordered renal function. Thiazides cross the placenta, and use of thiazides during pregnancy is associated with a risk of fetal or neonatal jaundice, thrombocytopenia, and possibly other adverse reactions that have occurred in adults [see Warnings and Precautions ( 5.1 )]. Data Animal data Irbesartan crosses the placenta in rats and rabbits.
In female rats given irbesartan prior to mating through gestation and lactation at oral doses of 50, 180, or 650 mg/kg/day (1.6 to 21.1 times the maximum recommended human dose (MRHD) based on body surface area), fetuses examined on Gestation Day 20 showed increased incidences of hydroureter and renal pelvic cavitation and/or absence of renal papilla in all irbesartan-treated groups. Subcutaneous edema also occurred in fetuses at maternal doses ≥180 mg/kg/day (5.8 times the MRHD). These anomalies occurred when female rats received irbesartan from prior to mating through Day 20 of gestation but were not observed in pups postnatally in the same study, or when irbesartan was given to pregnant rats only during organogenesis (Gestation Day 6 through Gestation Day 15) at oral doses from 50 to 450 mg/kg/day (up to 14.6 times the MRHD).
In addition, no adverse effects on kidney development were observed in pups from dams given irbesartan from Gestation Day 15 through Lactation Day 24 at doses of 50,… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Irbesartan and hydrochlorothiazide can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death [ see Clinical Considerations ] . Most epidemiologic studies examining fetal abnormalities after exposure to antihypertensive use in the first trimester have not distinguished drugs affecting the renin-angiotensin system from other antihypertensive agents.
When pregnancy is detected, discontinue irbesartan and hydrochlorothiazide as soon as possible. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes regardless of drug exposure. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo-fetal risk Hypertension in pregnancy increases the maternal risk for preeclampsia, gestational diabetes, premature delivery, and delivery complications (e.g., need for cesarean section and postpartum hemorrhage). Hypertension increases the fetal risk for intrauterine growth restriction and intrauterine death. Pregnant women with hypertension should be carefully monitored and managed accordingly.
Fetal/neonatal adverse reactions Oligohydramnios in pregnant women who use drugs affecting the renin-angiotensin system in the second and third trimesters of pregnancy can result in the following: reduced fetal renal function leading to anuria and renal failure, fetal lung hypoplasia, skeletal deformations, including skull hypoplasia, hypotension, and death. Perform serial ultrasound examinations to assess the intra-amniotic environment. Fetal testing may be appropriate, based on the week of pregnancy.
Patients and physicians should be aware, however, that oligohydramnios may not appear until after the fetus has sustained irreversible injury. Closely observe infants with histories of in utero exposure to irbesartan and hydrochlorothiazide for hypotension, oliguria, and hyperkalemia and other symptoms of renal impairment. In neonates with a history of in utero exposure to irbesartan and hydrochlorothiazide, if oliguria or hypotension occurs, direct attention toward support of blood pressure and renal perfusion.
Exchange transfusion or dialysis may be required as means of reversing hypotension and/or substituting for disordered renal function. Thiazides cross the placenta, and use of thiazides during pregnancy is associated with a risk of fetal or neonatal jaundice, thrombocytopenia, and possibly other adverse reactions that have occurred in adults [see Warnings and Precautions ( 5.1 )]. Data Animal data Irbesartan crosses the placenta in rats and rabbits.
In female rats given irbesartan prior to mating through gestation and lactation at oral doses of 50, 180, or 650 mg/kg/day (1.6 to 21.1 times the maximum recommended human dose (MRHD) based on body surface area), fetuses examined on Gestation Day 20 showed increased incidences of hydroureter and renal pelvic cavitation and/or absence of renal papilla in all irbesartan-treated groups. Subcutaneous edema also occurred in fetuses at maternal doses ≥180 mg/kg/day (5.8 times the MRHD). These anomalies occurred when female rats received irbesartan from prior to mating through Day 20 of gestation but were not observed in pups postnatally in the same study, or when irbesartan was given to pregnant rats only during organogenesis (Gestation Day 6 through Gestation Day 15) at oral doses from 50 to 450 mg/kg/day (up to 14.6 times the MRHD).
In addition, no adverse effects on kidney development were observed in pups from dams given irbesartan from Gestation Day 15 through Lactation Day 24 at doses of 50, 180, or 650 mg/kg/day (up to 21.1 times the MRHD). The observed effects are believed to b… [Excerpted — this section continues on DailyMed.]
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Of 1694 patients receiving irbesartan and hydrochlorothiazide in controlled clinical studies of hypertension, 264 (15.6%) were 65 years and over, while 45 (2.7%) were 75 years and over. No overall differences in safety or effectiveness were observed between these patients and younger patients, but greater sensitivity of some older individuals cannot be ruled out [see Clinical Pharmacology ( 12.3 ) and Clinical Studies ( 14 )].
🆘 Overdosage ▾
10 OVERDOSAGE Irbesartan No data are available in regard to overdosage in humans. However, daily doses of 900 mg for 8 weeks were well tolerated. The most likely manifestations of overdosage are expected to be hypotension and tachycardia; bradycardia might also occur from overdose.
Irbesartan is not removed by hemodialysis. To obtain up-to-date information about the treatment of overdosage, a good resource is a certified regional Poison Control Center. Telephone numbers of certified Poison Control Centers are listed in the Physicians’ Desk Reference (PDR).
In managing overdose, consider the possibilities of multiple-drug interactions, drug-drug interactions, and unusual drug kinetics in the patient. Laboratory determinations of serum levels of irbesartan are not widely available, and such determinations have, in any event, no established role in the management of irbesartan overdose. Acute oral toxicity studies with irbesartan in mice and rats indicated acute lethal doses were in excess of 2000 mg/kg, about 25-fold and 50-fold the MRHD (300 mg) based on body surface area.
Hydrochlorothiazide The most common signs and symptoms of overdose observed in humans are those caused by electrolyte depletion (hypokalemia, hypochloremia, hyponatremia) and dehydration resulting from excessive diuresis. If digitalis has also been administered, hypokalemia may accentuate cardiac arrhythmias. The degree to which hydrochlorothiazide is removed by hemodialysis has not been established.
The oral LD 50 of hydrochlorothiazide is greater than 10 g/kg in both mice and rats.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Irbesartan Angiotensin II is a potent vasoconstrictor formed from angiotensin I in a reaction catalyzed by angiotensin-converting enzyme (ACE, kininase II). Angiotensin II is the principal pressor agent of the RAS and also stimulates aldosterone synthesis and secretion by adrenal cortex, cardiac contraction, renal resorption of sodium, activity of the sympathetic nervous system, and smooth muscle cell growth. Irbesartan blocks the vasoconstrictor and aldosterone-secreting effects of angiotensin II by selectively binding to the AT 1 angiotensin II receptor.
There is also an AT 2 receptor in many tissues, but it is not involved in cardiovascular homeostasis. Irbesartan is a specific competitive antagonist of AT 1 receptors with a much greater affinity (more than 8500-fold) for the AT 1 receptor than for the AT 2 receptor, and no agonist activity. Blockade of the AT 1 receptor removes the negative feedback of angiotensin II on renin secretion, but the resulting increased plasma renin activity and circulating angiotensin II do not overcome the effects of irbesartan on blood pressure.
Irbesartan does not inhibit ACE or renin or affect other hormone receptors or ion channels known to be involved in the cardiovascular regulation of blood pressure and sodium homeostasis. Because irbesartan does not inhibit ACE, it does not affect the response to bradykinin; whether this has clinical relevance is not known. Hydrochlorothiazide Hydrochlorothiazide is a thiazide diuretic.
Thiazides affect the renal tubular mechanisms of electrolyte reabsorption, directly increasing excretion of sodium and chloride in approximately equivalent amounts. Indirectly, the diuretic action of hydrochlorothiazide reduces plasma volume, with consequent increases in plasma renin activity, increases in aldosterone secretion, increases in urinary potassium loss, and decreases in serum potassium. The renin-aldosterone link is mediated by angiotensin II, so coadministration of an angiotensin II receptor antagonist tends to reverse the potassium loss associated with these diuretics.
The mechanism of the antihypertensive effect of thiazides is not fully understood.
12.2Pharmacodynamics Irbesartan In healthy subjects, single oral irbesartan doses of up to 300 mg produced dose-dependent inhibition of the pressor effect of angiotensin II infusions. Inhibition was complete (100%) 4 hours following oral doses of 150 mg or 300 mg and partial inhibition was sustained for 24 hours (60% and 40% at 300 mg and 150 mg, respectively). In hypertensive patients, angiotensin II receptor inhibition following chronic administration of irbesartan causes a 1.5-fold to 2-fold rise in angiotensin II plasma concentration and a 2-fold to 3-fold increase in plasma renin levels.
Aldosterone plasma concentrations generally decline following irbesartan administration, but serum potassium levels are not significantly affected at recommended doses. In hypertensive patients, chronic oral doses of irbesartan (up to 300 mg) had no effect on glomerular filtration rate, renal plasma flow or filtration fraction. In multiple dose studies in hypertensive patients, there were no clinically important effects on fasting triglycerides, total cholesterol, HDL-cholesterol, or fasting glucose concentrations.
There was no effect on serum uric acid during chronic oral administration and no uricosuric effect. Hydrochlorothiazide After oral administration of hydrochlorothiazide, diuresis begins within 2 hours, peaks in about 4 hours and lasts about 6 to 12 hours. Drug Interactions Hydrochlorothiazide Alcohol, barbiturates, or narcotics: Potentiation of orthostatic hypotension may occur.
Skeletal muscle relaxants: Possible increased responsiveness to muscle relaxants such as curare derivatives. Corticosteroids, ACTH : Intensified electrolyte depletion, particularly hypokalemia. Pressor amines (e.g., norepinephrine): Possible decreased response to pressor amines but not… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Irbesartan Angiotensin II is a potent vasoconstrictor formed from angiotensin I in a reaction catalyzed by angiotensin-converting enzyme (ACE, kininase II). Angiotensin II is the principal pressor agent of the RAS and also stimulates aldosterone synthesis and secretion by adrenal cortex, cardiac contraction, renal resorption of sodium, activity of the sympathetic nervous system, and smooth muscle cell growth. Irbesartan blocks the vasoconstrictor and aldosterone-secreting effects of angiotensin II by selectively binding to the AT 1 angiotensin II receptor.
There is also an AT 2 receptor in many tissues, but it is not involved in cardiovascular homeostasis. Irbesartan is a specific competitive antagonist of AT 1 receptors with a much greater affinity (more than 8500-fold) for the AT 1 receptor than for the AT 2 receptor, and no agonist activity. Blockade of the AT 1 receptor removes the negative feedback of angiotensin II on renin secretion, but the resulting increased plasma renin activity and circulating angiotensin II do not overcome the effects of irbesartan on blood pressure.
Irbesartan does not inhibit ACE or renin or affect other hormone receptors or ion channels known to be involved in the cardiovascular regulation of blood pressure and sodium homeostasis. Because irbesartan does not inhibit ACE, it does not affect the response to bradykinin; whether this has clinical relevance is not known. Hydrochlorothiazide Hydrochlorothiazide is a thiazide diuretic.
Thiazides affect the renal tubular mechanisms of electrolyte reabsorption, directly increasing excretion of sodium and chloride in approximately equivalent amounts. Indirectly, the diuretic action of hydrochlorothiazide reduces plasma volume, with consequent increases in plasma renin activity, increases in aldosterone secretion, increases in urinary potassium loss, and decreases in serum potassium. The renin-aldosterone link is mediated by angiotensin II, so coadministration of an angiotensin II receptor antagonist tends to reverse the potassium loss associated with these diuretics.
The mechanism of the antihypertensive effect of thiazides is not fully understood.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
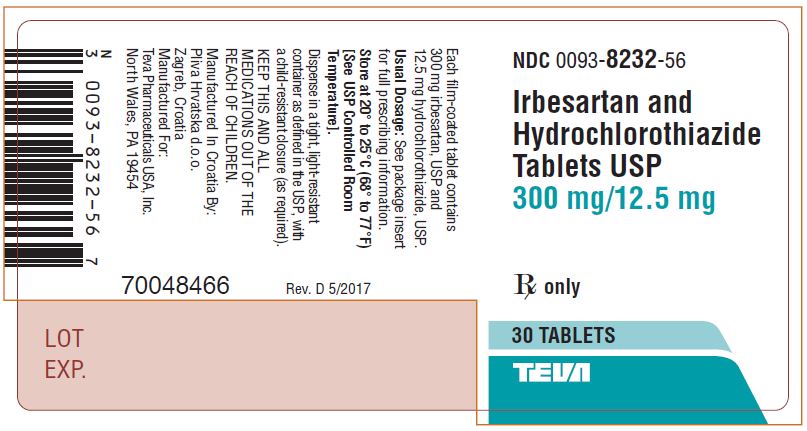
16.1How Supplied Irbesartan and hydrochlorothiazide tablets, USP are available as follows: 150 mg/12.5 mg: Light pink to pink, film-coated, capsule-shaped tablets, debossed with “TEVA” on one side of the tablet and “7238” on the other side and are available in bottles of 30 (NDC 0093-8238-56) and 90 (NDC 0093-8238-98). 300 mg/12.5 mg: Light pink to pink, film-coated, capsule-shaped tablets, debossed with “TEVA” on one side of the tablet and “7239” on the other side and are available in bottles of 30 (NDC 0093-8232-56) and 90 (NDC 0093-8232-98).
16.2Storage Store at 20° to 25°C (68° to 77°F) [See USP Controlled Room Temperature]. Dispense in a tight, light-resistant container as defined in the USP, with a child-resistant closure (as required).
📦 Storage and Handling ▾
16.2Storage Store at 20° to 25°C (68° to 77°F) [See USP Controlled Room Temperature]. Dispense in a tight, light-resistant container as defined in the USP, with a child-resistant closure (as required).
📋 Description ▾
11 DESCRIPTION Irbesartan and Hydrochlorothiazide Tablets USP are a combination of an angiotensin II receptor antagonist (AT 1 subtype), irbesartan, USP and a thiazide diuretic, hydrochlorothiazide (HCTZ), USP. Irbesartan, USP is a non-peptide compound, chemically described as a 2-Butyl-3-[ p -( o -1 H -tetrazol-5-ylphenyl)benzyl]-1,3-diazaspiro[4.4]non-1-en-4-one. Its structural formula is: C 25 H 28 N 6 O M.W.
428.5 Irbesartan, USP is a white to off-white crystalline powder. It is a nonpolar compound with a partition coefficient (octanol/water) of 10.1 at pH of 7.4. Irbesartan, USP is slightly soluble in alcohol and methylene chloride and practically insoluble in water.
Hydrochlorothiazide, USP is 6-Chloro-3,4-dihydro-2 H -1,2,4-benzothiadiazine-7-sulfonamide 1,1-dioxide. Its structural formula is: C 7 H 8 ClN 3 O 4 S 2 M.W. 297.7 Hydrochlorothiazide, USP is a white, or practically white, practically odorless, crystalline powder.
Hydrochlorothiazide, USP is very slightly soluble in water and freely soluble in sodium hydroxide solution. Irbesartan and Hydrochlorothiazide Tablets USP are available for oral administration in film-coated tablets containing either 150 mg or 300 mg of irbesartan, USP combined with 12.5 mg of hydrochlorothiazide, USP. Inactive ingredients include: colloidal silicon dioxide, croscarmellose sodium, hypromellose, iron oxide black, iron oxide red, iron oxide yellow, magnesium stearate, microcrystalline cellulose, poloxamer, polyethylene glycol, povidone, pregelatinized corn starch and titanium dioxide. image 1 image 2
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Pregnancy Tell female patients of childbearing age about the consequences of exposure to irbesartan and hydrochlorothiazide tablets during pregnancy. Discuss treatment options with women planning to become pregnant. Ask patients to report pregnancies to their physician as soon as possible.
Symptomatic Hypotension Tell patients using irbesartan and hydrochlorothiazide tablets that they may feel lightheaded, especially during the first days of use. Tell patients to inform their physician if they feel lightheaded or faint. Tell the patient, if fainting occurs, stop using irbesartan and hydrochlorothiazide tablets and contact the prescribing doctor.
Tell patients using irbesartan and hydrochlorothiazide tablets that getting dehydrated can lower their blood pressure too much and lead to lightheadedness and possible fainting. Dehydration may occur with excessive sweating, diarrhea, or vomiting and with not drinking enough liquids. Potassium Supplements Advise patients not to use potassium supplements or salt substitutes containing potassium without consulting their healthcare provider [see Drug Interactions ( 7.3 )] .
Acute Angle-Closure Glaucoma, Acute Myopia, and Choroidal Effusion Advise patients to discontinue irbesartan and hydrochlorothiazide tablets and seek immediate medical attention if they experience symptoms of acute angle-closure glaucoma, acute myopia, and choroidal effusion [see Warnings and Precautions ( 5.8 )] . Non-melanoma Skin Cancer Instruct patients taking hydrochlorothiazide to protect skin from the sun and undergo regular skin cancer screening. Manufactured In Croatia By: Pliva Hrvatska d.o.o.
Zagreb, Croatia Manufactured For: Teva Pharmaceuticals USA, Inc. North Wales, PA 19454 Rev. Q 12/2025
🍼 Nursing Mothers ▾
8.2Lactation There are no available data on the presence of irbesartan in human milk, effects on milk production, or the breastfed infant. Irbesartan or some metabolite of irbesartan is secreted in the milk of lactating rats. Thiazides appear in human milk [see Clinical Pharmacology ( 12.3 )]. Because of the potential for adverse effects on the nursing infant, the use of irbesartan and hydrochlorothiazide in breastfeeding women is not recommended.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Irbesartan Irbesartan is an orally active agent that does not require biotransformation into an active form. The oral absorption of irbesartan is rapid and complete with an average absolute bioavailability of 60% to 80%. Following oral administration of irbesartan, peak plasma concentrations of irbesartan are attained at 1.5 to 2 hours after dosing.
Food does not affect the bioavailability of irbesartan. Irbesartan exhibits linear pharmacokinetics over the therapeutic dose range. The terminal elimination half-life of irbesartan averaged 11 to 15 hours.
Steady-state concentrations are achieved within 3 days. Limited accumulation of irbesartan (<20%) is observed in plasma upon repeated once-daily dosing. Hydrochlorothiazide When plasma levels have been followed for at least 24 hours, the plasma half-life has been observed to vary between 5.6 and 14.8 hours.
Metabolism and Elimination Irbesartan Irbesartan is metabolized via glucuronide conjugation and oxidation. Following oral or intravenous administration of 14 C-labeled irbesartan, more than 80% of the circulating plasma radioactivity is attributable to unchanged irbesartan. The primary circulating metabolite is the inactive irbesartan glucuronide conjugate (approximately 6%).
The remaining oxidative metabolites do not add appreciably to irbesartan’s pharmacologic activity. Irbesartan and its metabolites are excreted by both biliary and renal routes. Following either oral or intravenous administration of 14 C-labeled irbesartan, about 20% of radioactivity is recovered in the urine and the remainder in the feces, as irbesartan or irbesartan glucuronide.
In vitro studies of irbesartan oxidation by cytochrome P450 isoenzymes indicated irbesartan was oxidized primarily by 2C9; metabolism by 3A4 was negligible. Irbesartan was neither metabolized by, nor did it substantially induce or inhibit, isoenzymes commonly associated with drug metabolism (1A1, 1A2, 2A6, 2B6, 2D6, 2E1). There was no induction or inhibition of 3A4.
Hydrochlorothiazide Hydrochlorothiazide is not metabolized but is eliminated rapidly by the kidney. At least 61% of the oral dose is eliminated unchanged within 24 hours. Distribution Irbesartan Irbesartan is 90% bound to serum proteins (primarily albumin and α 1 -acid glycoprotein) with negligible binding to cellular components of blood.
The average volume of distribution is 53 to 93 liters. Total plasma and renal clearances are in the range of 157 to 176 mL/min and 3.0 to 3.5 mL/min, respectively. With repetitive dosing, irbesartan accumulates to no clinically relevant extent.
Studies in animals indicate that radiolabeled irbesartan weakly crosses the blood-brain barrier and placenta. Irbesartan is excreted in the milk of lactating rats. Hydrochlorothiazide Hydrochlorothiazide crosses the placental but not the blood-brain barrier and is excreted in breast milk.
Specific Populations Pediatric Irbesartan and hydrochlorothiazide pharmacokinetics have not been investigated in patients <18 years of age. Gender No gender-related differences in pharmacokinetics were observed in healthy elderly (age 65 to 80 years) or in healthy young (age 18 to 40 years) subjects. In studies of hypertensive patients, there was no gender difference in half-life or accumulation, but somewhat higher plasma concentrations of irbesartan were observed in females (11% to 44%).
No gender-related dosage adjustment is necessary. Geriatric In elderly subjects (age 65 to 80 years), irbesartan elimination half-life was not significantly altered, but AUC and C max values were about 20% to 50% greater than those of young subjects (age 18 to 40 years). No dosage adjustment is necessary in the elderly.
Race In healthy black subjects, irbesartan AUC values were approximately 25% greater than whites; there were no differences in C max values. Renal insufficiency The pharmacokinetics of irbesartan were not altered in patients with renal impairment or in patients on hemodialysis. Irbesar… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Irbesartan In healthy subjects, single oral irbesartan doses of up to 300 mg produced dose-dependent inhibition of the pressor effect of angiotensin II infusions. Inhibition was complete (100%) 4 hours following oral doses of 150 mg or 300 mg and partial inhibition was sustained for 24 hours (60% and 40% at 300 mg and 150 mg, respectively). In hypertensive patients, angiotensin II receptor inhibition following chronic administration of irbesartan causes a 1.5-fold to 2-fold rise in angiotensin II plasma concentration and a 2-fold to 3-fold increase in plasma renin levels.
Aldosterone plasma concentrations generally decline following irbesartan administration, but serum potassium levels are not significantly affected at recommended doses. In hypertensive patients, chronic oral doses of irbesartan (up to 300 mg) had no effect on glomerular filtration rate, renal plasma flow or filtration fraction. In multiple dose studies in hypertensive patients, there were no clinically important effects on fasting triglycerides, total cholesterol, HDL-cholesterol, or fasting glucose concentrations.
There was no effect on serum uric acid during chronic oral administration and no uricosuric effect. Hydrochlorothiazide After oral administration of hydrochlorothiazide, diuresis begins within 2 hours, peaks in about 4 hours and lasts about 6 to 12 hours. Drug Interactions Hydrochlorothiazide Alcohol, barbiturates, or narcotics: Potentiation of orthostatic hypotension may occur.
Skeletal muscle relaxants: Possible increased responsiveness to muscle relaxants such as curare derivatives. Corticosteroids, ACTH : Intensified electrolyte depletion, particularly hypokalemia. Pressor amines (e.g., norepinephrine): Possible decreased response to pressor amines but not sufficient to preclude their use.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Irbesartan Monotherapy The antihypertensive effects of irbesartan were examined in 7 major placebo-controlled, 8 to 12-week trials in patients with baseline diastolic blood pressures of 95 to 110 mmHg. Doses of 1 to 900 mg were included in these trials in order to fully explore the dose-range of irbesartan. These studies allowed a comparison of once or twice-daily regimens at 150 mg/day, comparisons of peak and trough effects, and comparisons of response by gender, age, and race.
Two of the 7 placebo-controlled trials identified above and 2 additional placebo-controlled studies examined the antihypertensive effects of irbesartan and hydrochlorothiazide in combination. The 7 studies of irbesartan monotherapy included a total of 1915 patients randomized to irbesartan (1 to 900 mg) and 611 patients randomized to placebo. Once-daily doses of 150 to 300 mg provided statistically and clinically significant decreases in systolic and diastolic blood pressure with trough (24-hour post dose) effects after 6 to 12 weeks of treatment compared to placebo, of about 8 to 10/5 to 6 mmHg and 8 to 12/5 to 8 mmHg, respectively.
No further increase in effect was seen at dosages greater than 300 mg. The dose-response relationships for effects on systolic and diastolic pressure are shown in Figures 3 and 4. Figure 3.
Placebo-Subtracted Reduction in Trough SeSBP; Integrated Analysis Figure 4. Placebo-Subtracted Reduction in Trough SeDBP; Integrated Analysis Once-daily administration of therapeutic doses of irbesartan gave peak effects at around 3 to 6 hours and, in one continuous ambulatory blood pressure monitoring study, again around 14 hours. This was seen with both once-daily and twice-daily dosing.
Trough-to-peak ratios for systolic and diastolic response were generally between 60% and 70%. In a continuous ambulatory blood pressure monitoring study, once-daily dosing with 150 mg gave trough and mean 24-hour responses similar to those observed in patients receiving twice-daily dosing at the same total daily dose. Analysis of age, gender, and race subgroups of patients showed that men and women, and patients over and under 65 years of age, had generally similar responses.
Irbesartan was effective in reducing blood pressure regardless of race, although the effect was somewhat less in blacks (usually a low-renin population). Black patients typically show an improved response with the addition of a low dose diuretic (e.g., 12.5 mg hydrochlorothiazide). The effect of irbesartan is apparent after the first dose and is close to the full observed effect at 2 weeks.
At the end of the 8-week exposure, about 2/3 of the antihypertensive effect was still present 1 week after the last dose. Rebound hypertension was not observed. There was essentially no change in average heart rate in irbesartan-treated patients in controlled trials. figure03 figure04
14.2Irbesartan and Hydrochlorothiazide The antihypertensive effects of irbesartan and hydrochlorothiazide tablets were examined in 4 placebo-controlled studies in patients with mild-moderate hypertension (mean seated diastolic blood pressure [SeDBP] between 90 and 110 mmHg), one study in patients with moderate hypertension (mean seated systolic blood pressure [SeSBP] 160 to 179 mmHg or SeDBP 100 to 109 mmHg), and one study in patients with severe hypertension (mean SeDBP ≥110 mmHg) of 8 to 12 weeks. These trials included 3149 patients randomized to fixed doses of irbesartan (37.5 to 300 mg) and concomitant hydrochlorothiazide (6.25 to 25 mg).
Study I was a factorial study that compared all combinations of irbesartan (37.5 mg, 100 mg, and 300 mg or placebo) and hydrochlorothiazide (6.25 mg, 12.5 mg, and 25 mg or placebo). Study II compared the irbesartan and hydrochlorothiazide combinations of 75/12.5 mg and 150/12.5 mg to their individual components and placebo. Study III investigated the ambulatory blood pressure responses to irbesartan and hydrochlorothiazide (75/12.5 mg and 150/12.5… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Irbesartan and Hydrochlorothiazide No carcinogenicity studies have been conducted with the irbesartan and hydrochlorothiazide combination. Irbesartan and hydrochlorothiazide was not mutagenic in standard in vitro tests (Ames microbial test and Chinese hamster mammalian-cell forward gene-mutation assay). Irbesartan and hydrochlorothiazide was negative in tests for induction of chromosomal aberrations ( in vitro -human lymphocyte assay; in vivo -mouse micronucleus study).
The combination of irbesartan and hydrochlorothiazide has not been evaluated in definitive studies of fertility. Irbesartan No evidence of carcinogenicity was observed when irbesartan was administered at doses of up to 500/1000 mg/kg/day (males/females, respectively) in rats and 1000 mg/kg/day in mice for up to 2 years. For male and female rats, 500 mg/kg/day provided an average systemic exposure to irbesartan (AUC 0-24 hours , bound plus unbound) about 3 and 11 times, respectively, the average systemic exposure in humans receiving the maximum recommended human dose (MRHD) of 300 mg irbesartan/day, whereas 1000 mg/kg/day (administered to females only) provided an average systemic exposure about 21 times that reported for humans at the MRHD.
For male and female mice, 1000 mg/kg/day provided an exposure to irbesartan about 3 and 5 times, respectively, the human exposure at 300 mg/day. Irbesartan was not mutagenic in a battery of in vitro tests (Ames microbial test, rat hepatocyte DNA repair test, V79 mammalian-cell forward gene-mutation assay). Irbesartan was negative in several tests for induction of chromosomal aberrations ( in vitro -human lymphocyte assay; in vivo -mouse micronucleus study).
Irbesartan had no adverse effects on fertility or mating of male or female rats at oral doses ≤650 mg/kg/day, the highest dose providing a systemic exposure to irbesartan (AUC 0-24 hours , bound plus unbound) about 5 times that found in humans receiving the MRHD of 300 mg/day. Hydrochlorothiazide Two-year feeding studies in mice and rats conducted under the auspices of the National Toxicology Program (NTP) uncovered no evidence of a carcinogenic potential of hydrochlorothiazide in female mice (at doses of up to approximately 600 mg/kg/day) or in male and female rats (at doses of up to approximately 100 mg/kg/day).
The NTP, however, found equivocal evidence for hepatocarcinogenicity in male mice. Hydrochlorothiazide was not genotoxic in vitro in the Ames mutagenicity assay of Salmonella typhimurium strains TA 98, TA 100, TA 1535, TA 1537, and TA 1538 and in the Chinese Hamster Ovary (CHO) test for chromosomal aberrations, or in vivo in assays using mouse germinal cell chromosomes, Chinese hamster bone marrow chromosomes, and the Drosophila sex-linked recessive lethal trait gene. Positive test results were obtained only in the in vitro CHO Sister Chromatid Exchange (clastogenicity) and in the Mouse Lymphoma Cell (mutagenicity) assays, using concentrations of hydrochlorothiazide from 43 to 1300 mcg/mL, and in the Aspergillus nidulans non-disjunction assay at an unspecified concentration.
Hydrochlorothiazide had no adverse effects on the fertility of mice and rats of either sex in studies wherein these species were exposed, via their diet, to doses of up to 100 and 4 mg/kg, respectively, prior to mating and throughout gestation.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Irbesartan and Hydrochlorothiazide No carcinogenicity studies have been conducted with the irbesartan and hydrochlorothiazide combination. Irbesartan and hydrochlorothiazide was not mutagenic in standard in vitro tests (Ames microbial test and Chinese hamster mammalian-cell forward gene-mutation assay). Irbesartan and hydrochlorothiazide was negative in tests for induction of chromosomal aberrations ( in vitro -human lymphocyte assay; in vivo -mouse micronucleus study).
The combination of irbesartan and hydrochlorothiazide has not been evaluated in definitive studies of fertility. Irbesartan No evidence of carcinogenicity was observed when irbesartan was administered at doses of up to 500/1000 mg/kg/day (males/females, respectively) in rats and 1000 mg/kg/day in mice for up to 2 years. For male and female rats, 500 mg/kg/day provided an average systemic exposure to irbesartan (AUC 0-24 hours , bound plus unbound) about 3 and 11 times, respectively, the average systemic exposure in humans receiving the maximum recommended human dose (MRHD) of 300 mg irbesartan/day, whereas 1000 mg/kg/day (administered to females only) provided an average systemic exposure about 21 times that reported for humans at the MRHD.
For male and female mice, 1000 mg/kg/day provided an exposure to irbesartan about 3 and 5 times, respectively, the human exposure at 300 mg/day. Irbesartan was not mutagenic in a battery of in vitro tests (Ames microbial test, rat hepatocyte DNA repair test, V79 mammalian-cell forward gene-mutation assay). Irbesartan was negative in several tests for induction of chromosomal aberrations ( in vitro -human lymphocyte assay; in vivo -mouse micronucleus study).
Irbesartan had no adverse effects on fertility or mating of male or female rats at oral doses ≤650 mg/kg/day, the highest dose providing a systemic exposure to irbesartan (AUC 0-24 hours , bound plus unbound) about 5 times that found in humans receiving the MRHD of 300 mg/day. Hydrochlorothiazide Two-year feeding studies in mice and rats conducted under the auspices of the National Toxicology Program (NTP) uncovered no evidence of a carcinogenic potential of hydrochlorothiazide in female mice (at doses of up to approximately 600 mg/kg/day) or in male and female rats (at doses of up to approximately 100 mg/kg/day).
The NTP, however, found equivocal evidence for hepatocarcinogenicity in male mice. Hydrochlorothiazide was not genotoxic in vitro in the Ames mutagenicity assay of Salmonella typhimurium strains TA 98, TA 100, TA 1535, TA 1537, and TA 1538 and in the Chinese Hamster Ovary (CHO) test for chromosomal aberrations, or in vivo in assays using mouse germinal cell chromosomes, Chinese hamster bone marrow chromosomes, and the Drosophila sex-linked recessive lethal trait gene. Positive test results were obtained only in the in vitro CHO Sister Chromatid Exchange (clastogenicity) and in the Mouse Lymphoma Cell (mutagenicity) assays, using concentrations of hydrochlorothiazide from 43 to 1300 mcg/mL, and in the Aspergillus nidulans non-disjunction assay at an unspecified concentration.
Hydrochlorothiazide had no adverse effects on the fertility of mice and rats of either sex in studies wherein these species were exposed, via their diet, to doses of up to 100 and 4 mg/kg, respectively, prior to mating and throughout gestation.
📄 Package Label / Principal Display Panel ▾
Package/Label Display Panel NDC 0093-8238-56 Irbesartan and Hydrochlorothiazide Tablets USP 150 mg/12.5 mg Rx only 30 TABLETS 1
Package/Label Display Panel NDC 0093-8232-56 Irbesartan and Hydrochlorothiazide Tablets USP 300 mg/12.5 mg Rx only 30 TABLETS 2