
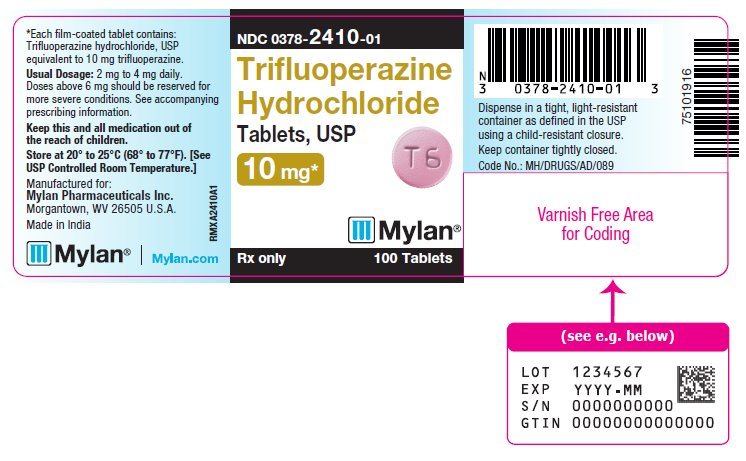
Trifluoperazine Hydrochloride 10 mg Tablet, Film Coated, 100-count — NDC 0378-2410-01 (Billing 00378-2410-01)
This is a package of 100 tablets of Trifluoperazine Hydrochloride 10 mg Tablet, Film Coated from Mylan Pharmaceuticals Inc., marketed since Aug 1997 and currently FDA-listed; retail pharmacies pay about $1.24 per tablet (NADAC). It is this product's only package size.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 003852
- GCN: 14831
- GPI-14 (Medi-Span): 59200085100320
- HICL (First Databank): 001630
- AHFS class code: 28:16.08.24
- RxCUI (RxNorm): 198322
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Phenothiazine class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Trifluoperazine is used to treat schizophrenia (a mental illness that affects how a person thinks, feels and behaves) and anxiety. Trifluoperazine is in a group of medications called antipsychotics. It works by decreasing abnormal excitement in the brain.
Read the full MedlinePlus article ↗- It is used to manage schizophrenia. It can also be used for short-term treatment of generalized non-psychotic anxiety, though it is usually not the first medicine tried for that.
- The label limits anxiety treatment to no more than 12 weeks and to a low daily dose ceiling. Longer or higher use can cause tardive dyskinesia that may be permanent. Your prescribe...
- Drowsiness, dizziness, dry mouth, blurred vision, fatigue and trouble sleeping are common. Be careful with driving early on. Rhythmic movements of the mouth or tongue, stiff muscle...
- It is best to avoid it. Alcohol, sedatives and narcotics can add to the drowsiness and depressant effects of this medicine.
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $1.243 | $124.32 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | $1.36 | $135.79 / 100 tablets |
| Medicare drug plans payPart D · Q2 2026 | $1.53 | $153.36 / 100 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00378-2410-01 You're viewing this Main listing | 100 TABLET, FILM COATED in 1 BOTTLE, PLASTIC | 1997-08-29 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Trifluoperazine Hydrochloride 10 mgthis 00378-2410-01 | Mylan | 100 tablets | $1.243 | AB | Availability likely | — |
| Trifluoperazine Hydrochloride 10 mg 00781-8036-01 | Sandoz | 100 tablets | $1.243 | AB | Availability likely | — |
| Trifluoperazine Hydrochloride 10 mg 51079-0575-20 | Mylan | 1 tablet | $1.243 | AB | Availability likely | — |
| Trifluoperazine Hydrochloride 10 mg 48433-0143-20 | Safecor | 1 tablet | — | AB | FDA listed | — |
| Trifluoperazine Hydrochloride 10 mg 72162-2205-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 2S42T2808B
A synthetic red dye used as a colorant to give the medicine its red color. It helps make pills or liquids visually distinct and easier to identify.
-
UNII L06K8R7DQK
A synthetic blue dye approved by the FDA for use in medications and foods. It serves as a colorant to make pills and liquids visually distinct and easier to identify.
-
UNII H77VEI93A8
A synthetic yellow dye used to color medications. It helps identify the drug and make it visually distinctive, with no effect on how the medicine works.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII VH2XOU12IE
Polydextrose is a synthetic polymer made from dextrose (sugar) that acts as a bulking agent and filler in medicines. It helps give tablets and capsules proper volume and texture while often adding slight sweetness.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII XHX3C3X673
Triacetin is a clear, oily liquid made from glycerin and acetic acid. It works as a plasticizer and solvent in medicines, helping soften coatings and improve how liquids mix together in formulations.
15 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING Increased Mortality in Elderly Patients with Dementia-Related Psychosis Elderly patients with dementia-related psychosis treated with antipsychotic drugs are at an increased risk of death. Analyses of seventeen placebo-controlled trials (modal duration of 10 weeks), largely in patients taking atypical antipsychotic drugs, revealed a risk of death in drug-treated patients of between 1.6 to 1.7 times the risk of death in placebo-treated patients. Over the course of a typical 10-week controlled trial, the rate of death in drug-treated patients was about 4.5%, compared to a rate of about 2.6% in the placebo group.
Although the causes of death were varied, most of the deaths appeared to be either cardiovascular (e.g., heart failure, sudden death) or infectious (e.g., pneumonia) in nature. Observational studies suggest that, similar to atypical antipsychotic drugs, treatment with conventional antipsychotic drugs may increase mortality. The extent to which the findings of increased mortality in observational studies may be attributed to the antipsychotic drug as opposed to some characteristic(s) of the patients is not clear.
Trifluoperazine hydrochloride is not approved for the treatment of patients with dementia-related psychosis (see WARNINGS ).
🎯 Indications and Usage ▾
INDICATIONS AND USAGE For the management of schizophrenia. Trifluoperazine hydrochloride tablets, USP are effective for the short-term treatment of generalized non-psychotic anxiety. However, trifluoperazine hydrochloride tablets are not the first drug to be used in therapy for most patients with non-psychotic anxiety because certain risks associated with its use are not shared by common alternative treatments (i.e., benzodiazepines).
When used in the treatment of non-psychotic anxiety, trifluoperazine hydrochloride tablets should not be administered at doses of more than 6 mg per day or for longer than 12 weeks because the use of trifluoperazine hydrochloride tablets at higher doses or for longer intervals may cause persistent tardive dyskinesia that may prove irreversible (see WARNINGS ). The effectiveness of trifluoperazine hydrochloride tablets as a treatment for non-psychotic anxiety was established in a 4-week clinical multicenter study of outpatients with generalized anxiety disorder (DSM-III).
This evidence does not predict that trifluoperazine hydrochloride tablets will be useful in patients with other non-psychotic conditions in which anxiety, or signs that mimic anxiety, are found (i.e., physical illness, organic mental conditions, agitated depression, character pathologies, etc.). Trifluoperazine hydrochloride tablets have not been shown effective in the management of behavioral complications in patients with mental retardation.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION-ADULTS Dosage should be adjusted to the needs of the individual. The lowest effective dosage should always be used. Dosage should be increased more gradually in debilitated or emaciated patients.
When maximum response is achieved, dosage may be reduced gradually to a maintenance level. Because of the inherent long action of the drug, patients may be controlled on convenient b.i.d. administration; some patients may be maintained on once a day administration. When trifluoperazine hydrochloride is administered by intramuscular injection, equivalent oral dosage may be substituted once symptoms have been controlled.
Note: Although there is little likelihood of contact dermatitis due to the drug, persons with known sensitivity to phenothiazine drugs should avoid direct contact. Elderly Patients In general, dosages in the lower range are sufficient for most elderly patients. Since they appear to be more susceptible to hypotension and neuromuscular reactions, such patients should be observed closely.
Dosage should be tailored to the individual, response carefully monitored, and dosage adjusted accordingly. Dosage should be increased more gradually in elderly patients. Non-Psychotic Anxiety Usual dosage is 1 mg or 2 mg twice daily.
Do not administer at doses of more than 6 mg per day or for longer than 12 weeks. Schizophrenia Oral Usual starting dosage is 2 mg to 5 mg b.i.d. (Small or emaciated patients should always be started on the lower dosage.) Most patients will show optimum response on 15 mg or 20 mg daily, although a few may require 40 mg a day or more.
Optimum therapeutic dosage levels should be reached within 2 or 3 weeks.
⛔ Contraindications ▾
CONTRAINDICATIONS A known hypersensitivity to phenothiazines, comatose or greatly depressed states due to central nervous system depressants and, in cases of existing blood dyscrasias, bone marrow depression and preexisting liver damage.
⚠️ Warnings ▾
WARNINGS Increased Mortality in Elderly Patients with Dementia-Related Psychosis Elderly patients with dementia-related psychosis treated with antipsychotic drugs are at an increased risk of death. Trifluoperazine hydrochloride is not approved for the treatment of patients with dementia-related psychosis (see BOXED WARNING ). Tardive Dyskinesia Tardive dyskinesia, a syndrome consisting of potentially irreversible, involuntary, dyskinetic movements, may develop in patients treated with antipsychotic drugs.
Although the prevalence of the syndrome appears to be highest among the elderly, especially elderly women, it is impossible to rely upon prevalence estimates to predict, at the inception of antipsychotic treatment, which patients are likely to develop the syndrome. Whether antipsychotic drug products differ in their potential to cause tardive dyskinesia is unknown. Both the risk of developing the syndrome and the likelihood that it will become irreversible are believed to increase as the duration of treatment and the total cumulative dose of antipsychotic drugs administered to the patient increase.
However, the syndrome can develop, although much less commonly, after relatively brief treatment periods at low doses. There is no known treatment for established cases of tardive dyskinesia, although the syndrome may remit, partially or completely, if antipsychotic treatment is withdrawn. Antipsychotic treatment itself, however, may suppress (or partially suppress) the signs and symptoms of the syndrome and thereby may possibly mask the underlying disease process.
The effect that symptomatic suppression has upon the long-term course of the syndrome is unknown. Given these considerations, antipsychotics should be prescribed in a manner that is most likely to minimize the occurrence of tardive dyskinesia. Chronic antipsychotic treatment should generally be reserved for patients who suffer from a chronic illness that 1) is known to respond to antipsychotic drugs, and, 2) for whom alternative, equally effective, but potentially less harmful treatments are not available or appropriate.
In patients who do require chronic treatment, the smallest dose and the shortest duration of treatment producing a satisfactory clinical response should be sought. The need for continued treatment should be reassessed periodically. If signs and symptoms of tardive dyskinesia appear in a patient on antipsychotics, drug discontinuation should be considered.
However, some patients may require treatment despite the presence of the syndrome. For further information about the description of tardive dyskinesia and its clinical detection, please refer to the sections on PRECAUTIONS and ADVERSE REACTIONS . Neuroleptic Malignant Syndrome (NMS) A potentially fatal symptom complex sometimes referred to as Neuroleptic Malignant Syndrome (NMS) has been reported in association with antipsychotic drugs.
Clinical manifestations of NMS are hyperpyrexia, muscle rigidity, altered mental status and evidence of autonomic instability (irregular pulse or blood pressure, tachycardia, diaphoresis, and cardiac dysrhythmias). The diagnostic evaluation of patients with this syndrome is complicated. In arriving at a diagnosis, it is important to identify cases where the clinical presentation includes both serious medical illness (e.g., pneumonia, systemic infection, etc.) and untreated or inadequately treated extrapyramidal signs and symptoms (EPS).
Other important considerations in the differential diagnosis include central anticholinergic toxicity, heat stroke, drug fever and primary central nervous system (CNS) pathology. The management of NMS should include 1) immediate discontinuation of antipsychotic drugs and other drugs not essential to concurrent therapy, 2) intensive symptomatic treatment and medical monitoring, and 3) treatment of any concomitant serious medical problems for which specific treatments are available. There is no general agreement about specific pharmacologic… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Drowsiness, dizziness, skin reactions, rash, dry mouth, insomnia, amenorrhea, fatigue, muscular weakness, anorexia, lactation, blurred vision and neuromuscular (extrapyramidal) reactions. Neuromuscular (Extrapyramidal) Reactions These symptoms are seen in a significant number of hospitalized mental patients. They may be characterized by motor restlessness, be of the dystonic type, or they may resemble parkinsonism.
Depending on the severity of symptoms, dosage should be reduced or discontinued. If therapy is reinstituted, it should be at a lower dosage. Should these symptoms occur in children or pregnant patients, the drug should be stopped and not reinstituted.
In most cases, barbiturates by suitable route of administration will suffice. (Or, injectable diphenhydramine hydrochloride may be useful.) In more severe cases, the administration of an antiparkinsonism agent, except levodopa, usually produces rapid reversal of symptoms. Suitable supportive measures such as maintaining a clear airway and adequate hydration should be employed.
Motor Restlessness Symptoms may include agitation or jitteriness and sometimes insomnia. These symptoms often disappear spontaneously. At times these symptoms may be similar to the original neurotic or psychotic symptoms.
Dosage should not be increased until these side effects have subsided. If this phase becomes too troublesome, the symptoms can usually be controlled by a reduction of dosage or change of drug. Treatment with antiparkinsonism agents, benzodiazepines or propranolol may be helpful.
Dystonia Class Effect Symptoms of dystonia, prolonged abnormal contractions of muscle groups, may occur in susceptible individuals during the first few days of treatment. Dystonic symptoms include: spasm of the neck muscles, sometimes progressing to tightness of the throat, swallowing difficulty, difficulty breathing, and/or protrusion of the tongue. While these symptoms can occur at low doses, they occur more frequently and with greater severity with high potency and at higher doses of first generation antipsychotic drugs.
An elevated risk of acute dystonia is observed in males and younger age groups. Pseudoparkinsonism Symptoms may include: mask-like facies; drooling; tremors; pill-rolling motion; cogwheel rigidity; and shuffling gait. Reassurance and sedation are important.
In most cases these symptoms are readily controlled when an antiparkinsonism agent is administered concomitantly. Antiparkinsonism agents should be used only when required. Generally, therapy of a few weeks to 2 or 3 months will suffice.
After this time, patients should be evaluated to determine their need for continued treatment. (Note: Levodopa has not been found effective in pseudoparkinsonism.) Occasionally it is necessary to lower the dosage of trifluoperazine hydrochloride or to discontinue the drug. Tardive Dyskinesia As with all antipsychotic agents, tardive dyskinesia may appear in some patients on long-term therapy or may appear after drug therapy has been discontinued.
The syndrome can also develop, although much less frequently, after relatively brief treatment periods at low doses. This syndrome appears in all age groups. Although its prevalence appears to be highest among elderly patients, especially elderly women, it is impossible to rely upon prevalence estimates to predict at the inception of antipsychotic treatment which patients are likely to develop the syndrome.
The symptoms are persistent and in some patients appear to be irreversible. The syndrome is characterized by rhythmical involuntary movements of the tongue, face, mouth or jaw (e.g., protrusion of tongue, puffing of cheeks, puckering of mouth, chewing movements). Sometimes these may be accompanied by involuntary movements of extremities.
In rare instances, these involuntary movements of the extremities are the only manifestations of tardive dyskinesia. A variant of tardive dyskinesia, tardive dystonia, has also been described. There is… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
Pregnancy Nonteratogenic Effects Neonates exposed to antipsychotic drugs, during the third trimester of pregnancy are at risk for extrapyramidal and/or withdrawal symptoms following delivery. There have been reports of agitation, hypertonia, hypotonia, tremor, somnolence, respiratory distress and feeding disorder in these neonates. These complications have varied in severity; while in some cases symptoms have been self-limited, in other cases neonates have required intensive care unit support and prolonged hospitalization.
Trifluoperazine hydrochloride should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
🆘 Overdosage ▾
OVERDOSAGE (See also under ADVERSE REACTIONS .) Symptoms Primarily involvement of the extrapyramidal mechanism producing some of the dystonic reactions described above. Symptoms of central nervous system depression to the point of somnolence or coma. Agitation and restlessness may also occur.
Other possible manifestations include convulsions, EKG changes and cardiac arrhythmias, fever and autonomic reactions such as hypotension, dry mouth and ileus. Treatment It is important to determine other medications taken by the patient since multiple dose therapy is common in overdosage situations. Treatment is essentially symptomatic and supportive.
Early gastric lavage is helpful. Keep patient under observation and maintain an open airway, since involvement of the extrapyramidal mechanism may produce dysphagia and respiratory difficulty in severe overdosage. Do not attempt to induce emesis because a dystonic reaction of the head or neck may develop that could result in aspiration of vomitus.
Extrapyramidal symptoms may be treated with antiparkinsonism drugs, barbiturates, or diphenhydramine hydrochloride. See prescribing information for these products. Care should be taken to avoid increasing respiratory depression.
If administration of a stimulant is desirable, amphetamine, dextroamphetamine, or caffeine with sodium benzoate is recommended. Stimulants that may cause convulsions (e.g., picrotoxin or pentylenetetrazol) should be avoided. If hypotension occurs, the standard measures for managing circulatory shock should be initiated.
If it is desirable to administer a vasoconstrictor, norepinephrine bitartrate and phenylephrine hydrochloride are most suitable. Other pressor agents, including epinephrine, are not recommended because phenothiazine derivatives may reverse the usual elevating action of these agents and cause a further lowering of blood pressure. Limited experience indicates that phenothiazines are not dialyzable.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Trifluoperazine Hydrochloride Tablets, USP are available containing trifluoperazine hydrochloride, USP equivalent to 1 mg, 2 mg, 5 mg or 10 mg of trifluoperazine. The 1 mg tablets are white, film-coated, round, unscored tablets debossed with T3 on one side of the tablet and M on the other side. They are available as follows: NDC 0378-2401-01 bottles of 100 tablets The 2 mg tablets are white, film-coated, round, unscored tablets debossed with T4 on one side of the tablet and M on the other side.
They are available as follows: NDC 0378-2402-01 bottles of 100 tablets For psychiatric patients who are hospitalized under close supervision. The 5 mg tablets are lavender, film-coated, round, unscored tablets debossed with T5 on one side of the tablet and M on the other side. They are available as follows: NDC 0378-2405-01 bottles of 100 tablets The 10 mg tablets are lavender, film-coated, round, unscored tablets debossed with T6 on one side of the tablet and M on the other side.
They are available as follows: NDC 0378-2410-01 bottles of 100 tablets Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.] Dispense in a tight, light-resistant container as defined in the USP using a child-resistant closure. Manufactured for: Mylan Pharmaceuticals Inc. Morgantown, WV 26505 U.S.A.
Manufactured by: Mylan Laboratories Limited Hyderabad — 500 096, India 75108197 Revised: 1/2025 MXA:TFPZ:R3
📋 Description ▾
DESCRIPTION Each film-coated tablet, for oral administration, contains trifluoperazine hydrochloride, USP equivalent to 1 mg, 2 mg, 5 mg, or 10 mg trifluoperazine. The structural formula is: C 21 H 24 F 3 N 3 S•2HCl M.W. 480.43 10-[3-(4-Methyl-1-piperazinyl)propyl]-2-(trifluoromethyl) phenothiazine dihydrochloride In addition, each tablet contains the following inactive ingredients: colloidal silicon dioxide, croscarmellose sodium, hypromellose, lactose monohydrate, magnesium stearate, microcrystalline cellulose, polydextrose, polyethylene glycol, pregelatinized starch (corn), sodium lauryl sulfate, titanium dioxide, and triacetin.
The 5 mg and 10 mg tablets also contain D&C Red No. 30 Aluminum Lake, FD&C Blue No. 2 Aluminum Lake and FD&C Yellow No.
6 Aluminum Lake. Structural Formula
⚠️ Precautions ▾
PRECAUTIONS General Given the likelihood that some patients exposed chronically to antipsychotics will develop tardive dyskinesia, it is advised that all patients in whom chronic use is contemplated be given, if possible, full information about this risk. The decision to inform patients and/or their guardians must obviously take into account the clinical circumstances and the competency of the patient to understand the information provided. Thrombocytopenia and anemia have been reported in patients receiving the drug.
Agranulocytosis and pancytopenia have also been reported-warn patients to report the sudden appearance of sore throat or other signs of infection. If white blood cell and differential counts indicate cellular depression, stop treatment and start antibiotic and other suitable therapy. Jaundice of the cholestatic type of hepatitis or liver damage has been reported.
If fever with grippe-like symptoms occurs, appropriate liver studies should be conducted. If tests indicate an abnormality, stop treatment. One result of therapy may be an increase in mental and physical activity.
For example, a few patients with angina pectoris have complained of increased pain while taking the drug. Therefore, angina patients should be observed carefully and, if an unfavorable response is noted, the drug should be withdrawn. Because hypotension has occurred, large doses and parenteral administration should be avoided in patients with impaired cardiovascular systems.
To minimize the occurrence of hypotension after injection, keep patient lying down and observe for at least 1/2 hour. If hypotension occurs from parenteral or oral dosing, place patient in head-low position with legs raised. If a vasoconstrictor is required, norepinephrine bitartrate and phenylephrine hydrochloride are suitable.
Other pressor agents, including epinephrine, should not be used as they may cause a paradoxical further lowering of blood pressure. Since certain phenothiazines have been reported to produce retinopathy, the drug should be discontinued if ophthalmoscopic examination or visual field studies should demonstrate retinal changes. An antiemetic action of trifluoperazine hydrochloride may mask the signs and symptoms of toxicity or overdosage of other drugs and may obscure the diagnosis and treatment of other conditions such as intestinal obstruction, brain tumor and Reye’s syndrome.
With prolonged administration at high dosages, the possibility of cumulative effects, with sudden onset of severe central nervous system or vasomotor symptoms, should be kept in mind. Antipsychotic drugs elevate prolactin levels; the elevation persists during chronic administration. Tissue culture experiments indicate that approximately 1/3 of human breast cancers are prolactin-dependent in vitro , a factor of potential importance if the prescribing of these drugs is contemplated in a patient with a previously detected breast cancer.
Although disturbances such as galactorrhea, amenorrhea, gynecomastia and impotence have been reported, the clinical significance of elevated serum prolactin levels is unknown for most patients. An increase in mammary neoplasms has been found in rodents after chronic administration of antipsychotic drugs. Published epidemiologic studies have shown inconsistent results when exploring the association between hyperprolactinemia and breast cancer.
Chromosomal aberrations in spermatocytes and abnormal sperm have been demonstrated in rodents treated with certain antipsychotics. Because phenothiazines may interfere with thermoregulatory mechanisms, use with caution in persons who will be exposed to extreme heat. As with all drugs which exert an anticholinergic effect, and/or cause mydriasis, trifluoperazine should be used with caution in patients with glaucoma.
Phenothiazines may diminish the effect of oral anticoagulants. Phenothiazines can produce alpha-adrenergic blockade. Concomitant administration of propranolol with phenothiazines results in increase… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers There is evidence that phenothiazines are excreted in the breast milk of nursing mothers. Because of the potential for serious adverse reactions in nursing infants from trifluoperazine, a decision should be made whether to discontinue nursing or to discontinue the drug, taking into account the importance of the drug to the mother.
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 1 mg NDC 0378-2401-01 Trifluoperazine Hydrochloride Tablets, USP 1 mg* Rx only 100 Tablets *Each film-coated tablet contains: Trifluoperazine hydrochloride, USP equivalent to 1 mg trifluoperazine. Usual Dosage: 2 mg to 4 mg daily. Doses above 6 mg should be reserved for more severe conditions.
See accompanying prescribing information. Keep this and all medication out of the reach of children. Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.] Manufactured for: Mylan Pharmaceuticals Inc.
Morgantown, WV 26505 U.S.A. Made in India Mylan.com RMXA2401A1 Dispense in a tight, light-resistant container as defined in the USP using a child-resistant closure. Keep container tightly closed.
Code No.: MH/DRUGS/AD/089 Trifluoperazine Hydrochloride Tablets, USP 2 mg Bottle Label
PRINCIPAL DISPLAY PANEL - 2 mg NDC 0378-2402-01 Trifluoperazine Hydrochloride Tablets, USP 2 mg* Rx only 100 Tablets *Each film-coated tablet contains: Trifluoperazine hydrochloride, USP equivalent to 2 mg trifluoperazine. Usual Dosage: 2 mg to 4 mg daily. Doses above 6 mg should be reserved for more severe conditions.
See accompanying prescribing information. Keep this and all medication out of the reach of children. Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.] Manufactured for: Mylan Pharmaceuticals Inc.
Morgantown, WV 26505 U.S.A. Made in India Mylan.com RMXA2402A1 Dispense in a tight, light-resistant container as defined in the USP using a child-resistant closure. Keep container tightly closed.
Code No.: MH/DRUGS/AD/089 Trifluoperazine Hydrochloride Tablets, USP 2 mg Bottle Label
PRINCIPAL DISPLAY PANEL - 5 mg NDC 0378-2405-01 Trifluoperazine Hydrochloride Tablets, USP 5 mg* Rx only 100 Tablets *Each film-coated tablet contains: Trifluoperazine hydrochloride, USP equivalent to 5 mg trifluoperazine. Usual Dosage: 2 mg to 4 mg daily. Doses above 6 mg should be reserved for more severe conditions.
See accompanying prescribing information. Keep this and all medication out of the reach of children. Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.] Manufactured for: Mylan Pharmaceuticals Inc.
Morgantown, WV 26505 U.S.A. Made in India Mylan.com RMXA2405A1 Dispense in a tight, light-resistant container as defined in the USP using a child-resistant closure. Keep container tightly closed.
Code No.: MH/DRUGS/AD/089 Trifluoperazine Hydrochloride Tablets, USP 5 mg Bottle Label
PRINCIPAL DISPLAY PANEL - 10 mg NDC 0378-2410-01 Trifluoperazine Hydrochloride Tablets, USP 10 mg* Rx only 100 Tablets *Each film-coated tablet contains: Trifluoperazine hydrochloride, USP equivalent to 10 mg trifluoperazine. Usual Dosage: 2 mg to 4 mg daily. Doses above 6 mg should be reserved for more severe conditions.
See accompanying prescribing information. Keep this and all medication out of the reach of children. Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.] Manufactured for: Mylan Pharmaceuticals Inc.
Morgantown, WV 26505 U.S.A. Made in India Mylan.com RMXA2410A1 Dispense in a tight, light-resistant container as defined in the USP using a child-resistant closure. Keep container tightly closed.
Code No.: MH/DRUGS/AD/089 Trifluoperazine Hydrochloride Tablets, USP 10 mg Bottle Label