
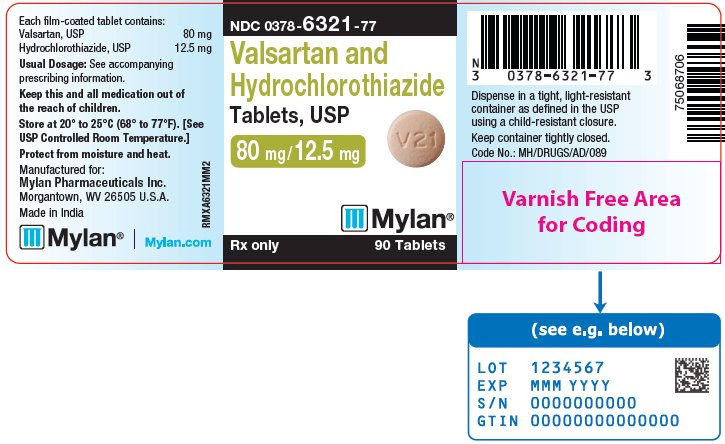
Valsartan and Hydrochlorothiazide 80 mg; 12.5 mg Tablet, Film Coated, 90-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Thiazide Diuretic class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- This tablet combines two different blood pressure-lowering medicines in one pill: valsartan, which relaxes your blood vessels, and hydrochlorothiazide, a water pill that helps your...
- What exactly is this medication and why did my doctor prescribe it?
- You can take it either way — with or without food. The hydrochlorothiazide part isn't affected by food at all. Food does reduce how much valsartan your body absorbs, but since you...
- Does it matter if I take it with food or on an empty stomach?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.097 | $8.76 / 90 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.3302 | $29.72 / 90 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.3156 | $28.40 / 90 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Valsartan and Hydrochlorothiazide 80 mg/1; 12.5 mgthis 00378-6321-77 | Mylan | 90 tablets | $0.097 | AB | Availability likely | — |
| Valsartan and Hydrochlorothiazide 80 mg/1; 12.5 mg 33342-0074-10 | Macleods | 90 tablets | $0.097 | AB | Availability likely | — |
| Diovan HCT 80 mg/1; 12.5 mg 00078-0314-34 | Novartis | 90 tablets | $10.565 | AB | Availability likely | +10756% |
| Valsartan and Hydrochlorothiazide 80 mg/1; 12.5 mg 42291-0965-90 | AvKARE | 90 tablets | — | AB | FDA listed | — |
| Valsartan And Hydrochlorothiazide 80 mg/1; 12.5 mg 43547-0311-03 | Solco | 30 tablets | — | AB | FDA listed | — |
| Valsartan and Hydrochlorothiazide 80 mg/1; 12.5 mg 46708-0453-10 | Alembic | 100 tablets | — | AB | FDA listed | — |
| Valsartan and Hydrochlorothiazide 80 mg/1; 12.5 mg 50090-3292-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Valsartan and Hydrochlorothiazide 80 mg/1; 12.5 mg 50090-3576-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Valsartan and Hydrochlorothiazide 80 mg/1; 12.5 mg 53746-0845-90 | Amneal | 90 tablets | — | AB | FDA listed | — |
| Valsartan and Hydrochlorothiazide 80 mg/1; 12.5 mg 62332-0079-10 | Alembic | 100 tablets | — | AB | FDA listed | — |
| Valsartan and Hydrochlorothiazide 80 mg/1; 12.5 mg 63187-0571-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Valsartan and Hydrochlorothiazide 80 mg/1; 12.5 mg 63187-0943-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Valsartan and Hydrochlorothiazide 80 mg/1; 12.5 mg 65162-0845-03 | Amneal | 30 tablets | — | AB | FDA listed | — |
| Valsartan and Hydrochlorothiazide 80 mg/1; 12.5 mg 65862-0547-10 | Aurobindo | 10 tablets | — | — | FDA listed | — |
| valsartan and hydrochlorothiazide 80 mg/1; 12.5 mg 70771-1485-00 | Zydus | 1000 tablets | — | — | FDA listed | — |
| Valsartan and Hydrochlorothiazide 12.5 mg/1; 80 mg 71205-0249-30 | Proficient | 30 tablets | — | — | FDA listed | — |
| Valsartan and Hydrochlorothiazide 80 mg/1; 12.5 mg 71205-0327-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Valsartan And Hydrochlorothiazide 80 mg/1; 12.5 mg 71335-2618-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Valsartan And Hydrochlorothiazide 80 mg/1; 12.5 mg 50228-0147-10 | ScieGen | 1000 tablets | — | AB | FDA listed | — |
| Valsartan And Hydrochlorothiazide 80 mg/1; 12.5 mg 84677-0072-90 | Golden | 90 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00378-6321-77 You're viewing this | 90 TABLET, FILM COATED in 1 BOTTLE, PLASTIC (0378-6321-77) | 2012-09-21 | Active |
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: FETAL TOXICITY • When pregnancy is detected, discontinue valsartan and hydrochlorothiazide tablets as soon as possible. ( 5.1 ) • Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus. ( 5.1 ) WARNING: FETAL TOXICITY See full prescribing information for complete boxed warning. • When pregnancy is detected, discontinue valsartan and hydrochlorothiazide tablets as soon as possible.
( 5.1 ) • Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus. ( 5.1 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Valsartan and hydrochlorothiazide tablets are indicated for the treatment of hypertension, to lower blood pressure. Lowering blood pressure reduces the risk of fatal and nonfatal cardiovascular events, primarily strokes and myocardial infarctions. These benefits have been seen in controlled trials of antihypertensive drugs from a wide variety of pharmacologic classes, including hydrochlorothiazide and the angiotensin II receptor blocker (ARB) class to which valsartan principally belongs.
There are no controlled trials demonstrating risk reduction with valsartan and hydrochlorothiazide tablets. Control of high blood pressure should be part of comprehensive cardiovascular risk management, including, as appropriate, lipid control, diabetes management, antithrombotic therapy, smoking cessation, exercise, and limited sodium intake. Many patients will require more than 1 drug to achieve blood pressure goals.
For specific advice on goals and management, see published guidelines, such as those of the National High Blood Pressure Education Program’s Joint National Committee on Prevention, Detection, Evaluation, and Treatment of High Blood Pressure (JNC). Numerous antihypertensive drugs, from a variety of pharmacologic classes and with different mechanisms of action, have been shown in randomized controlled trials to reduce cardiovascular morbidity and mortality, and it can be concluded that it is blood pressure reduction, and not some other pharmacologic property of the drugs, that is largely responsible for those benefits.
The largest and most consistent cardiovascular outcome benefit has been a reduction in the risk of stroke, but reductions in myocardial infarction and cardiovascular mortality have also been seen regularly. Elevated systolic or diastolic pressure causes increased cardiovascular risk, and the absolute risk increase per mmHg is greater at higher blood pressures, so that even modest reductions of severe hypertension can provide substantial benefit. Relative risk reduction from blood pressure reduction is similar across populations with varying absolute risk, so the absolute benefit is greater in patients who are at higher risk independent of their hypertension (e.g., patients with diabetes or hyperlipidemia), and such patients would be expected to benefit from more aggressive treatment to a lower blood pressure goal.
Some antihypertensive drugs have smaller blood pressure effects (as monotherapy) in black patients, and many antihypertensive drugs have additional approved indications and effects (e.g., on angina, heart failure, or diabetic kidney disease). These considerations may guide selection of therapy. Add-On Therapy: Valsartan and hydrochlorothiazide tablets may be used in patients whose blood pressure is not adequately controlled on monotherapy.
Replacement Therapy: Valsartan and hydrochlorothiazide tablets may be substituted for the titrated components. Initial Therapy: Valsartan and hydrochlorothiazide tablets may be used as initial therapy in patients who are likely to need multiple drugs to achieve blood pressure goals. The choice of valsartan and hydrochlorothiazide tablets as initial therapy for hypertension should be based on an assessment of potential benefits and risks.
Patients with stage 2 hypertension are at a relatively high risk for cardiovascular events (such as strokes, heart attacks, and heart failure), kidney failure, and vision problems, so prompt treatment is clinically relevant. The decision to use a combination as initial therapy should be individualized and should be shaped by considerations such as baseline blood pressure, the target goal, and the incremental likelihood of achieving goal with a combination compared to monotherapy. Individual blood pressure goals may vary based upon the patient’s risk.
Data from the high dose multifactorial trial [see Clinical Studies (14.1) ] provides estimates of the probability of reaching a target blood pressure with valsartan a…
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Dose once daily. Titrate as needed to a maximum dose of 320/25 mg ( 2 ) • May be used as add-on/switch therapy for patients not adequately controlled on any of the components (valsartan or HCTZ) ( 2 ) • May be substituted for titrated components ( 2.3 )
2.1General Considerations The usual starting dose is valsartan and hydrochlorothiazide tablets 160/12.5 mg once daily. The dosage can be increased after 1 to 2 weeks of therapy to a maximum of one 320/25 tablet once daily as needed to control blood pressure [see Clinical Studies (14.2) ]. Maximum antihypertensive effects are attained within 2 to 4 weeks after a change in dose.
2.2Add-On Therapy A patient whose blood pressure is not adequately controlled with valsartan (or another ARB) alone or hydrochlorothiazide alone may be switched to combination therapy with valsartan and hydrochlorothiazide tablets. A patient who experiences dose-limiting adverse reactions on either component alone may be switched to valsartan and hydrochlorothiazide tablets containing a lower dose of that component in combination with the other to achieve similar blood pressure reductions. The clinical response to valsartan and hydrochlorothiazide tablets should be subsequently evaluated and if blood pressure remains uncontrolled after 3 to 4 weeks of therapy, the dose may be titrated up to a maximum of 320/25 mg.
2.3Replacement Therapy Valsartan and hydrochlorothiazide tablets may be substituted for the titrated components.
2.4Initial Therapy Valsartan and hydrochlorothiazide tablets are not recommended as initial therapy in patients with intravascular volume depletion [see Warnings and Precautions (5.2) ] .
2.5Use with Other Antihypertensive Drugs Valsartan and hydrochlorothiazide tablets may be administered with other antihypertensive agents.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Valsartan and Hydrochlorothiazide Tablets, USP are available containing 80 mg/12.5 mg, 160 mg/12.5 mg, 160 mg/25 mg, 320 mg/12.5 mg or 320 mg/25 mg of valsartan, USP and hydrochlorothiazide, USP. • The 80 mg/12.5 mg tablets are orange, film-coated, round, unscored tablets debossed with M on one side of the tablet and V21 on the other side. • The 160 mg/12.5 mg tablets are orange, film-coated, round, unscored tablets debossed with M on one side of the tablet and V22 on the other side. • The 160 mg/25 mg tablets are orange, film-coated, oval, unscored tablets debossed with M on one side of the tablet and V23 on the other side. • The 320 mg/12.5 mg tablets are orange, film-coated, oval, unscored tablets debossed with M on one side of the tablet and V24 on the other side. • The 320 mg/25 mg tablets are beige, film-coated, oval, unscored tablets debossed with M on one side of the tablet and V25 on the other side.
Tablets (valsartan and HCTZ): 80 mg/12.5 mg, 160 mg/12.5 mg, 160 mg/25 mg, 320 mg/12.5 mg, 320 mg/25 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Valsartan and hydrochlorothiazide tablets are contraindicated in patients who are hypersensitive to any component of this product. Because of the hydrochlorothiazide component, this product is contraindicated in patients with anuria or hypersensitivity to other sulfonamide-derived drugs. Do not coadminister aliskiren with valsartan and hydrochlorothiazide tablets in patients with diabetes [see Drug Interactions (7) ] .
Anuria; Hypersensitivity to any sulfonamide-derived drugs or any component; Do not coadminister aliskiren with valsartan and hydrochlorothiazide tablets in patients with diabetes. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Hypotension: Correct volume depletion prior to initiation ( 5.2 ) • Observe for signs of fluid or electrolyte imbalance ( 5.9 ) • Monitor renal function and potassium in susceptible patients ( 5.3 , 5.7 ) • Exacerbation or activation of systemic lupus erythematosus ( 5.5 ) • Acute angle-closure glaucoma ( 5.8 )
5.1Fetal Toxicity Valsartan and hydrochlorothiazide tablets can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Resulting oligohydramnios can be associated with fetal lung hypoplasia and skeletal deformations.
Potential neonatal adverse effects include skull hypoplasia, anuria, hypotension, renal failure, and death. Thiazides cross the placenta, and use of thiazides during pregnancy is associated with fetal or neonatal jaundice, thrombocytopenia, and possibly other adverse reactions that have occurred in adults. When pregnancy is detected, discontinue valsartan and hydrochlorothiazide tablets as soon as possible [see Use in Specific Populations (8.1) ] .
5.2Hypotension in Volume- and/or Salt-Depleted Patients Excessive reduction of blood pressure was rarely seen (0.7%) in patients with uncomplicated hypertension treated with valsartan and hydrochlorothiazide tablets in controlled trials. In patients with an activated renin-angiotensin system, such as volume- and/or salt-depleted patients receiving high doses of diuretics, symptomatic hypotension may occur. This condition should be corrected prior to administration of valsartan and hydrochlorothiazide tablets, or the treatment should start under close medical supervision.
If hypotension occurs, place the patient in the supine position and, if necessary, give intravenous normal saline. A transient hypotensive response is not a contraindication to further treatment, which usually can be continued without difficulty once the blood pressure has stabilized.
5.3Impaired Renal Function Changes in renal function including acute renal failure can be caused by drugs that inhibit the renin-angiotensin system and by diuretics. Patients whose renal function may depend in part on the activity of the renin-angiotensin system (e.g., patients with renal artery stenosis, chronic kidney disease, severe congestive heart failure, or volume depletion) may be at particular risk of developing acute renal failure on valsartan and hydrochlorothiazide tablets. Monitor renal function periodically in these patients.
Consider withholding or discontinuing therapy in patients who develop a clinically significant decrease in renal function on valsartan and hydrochlorothiazide tablets [see Drug Interactions (7) ] .
5.4Hypersensitivity Reaction Hypersensitivity reactions to hydrochlorothiazide may occur in patients with or without a history of allergy or bronchial asthma, but are more likely in patients with such a history.
5.5Systemic Lupus Erythematosus Thiazide diuretics have been reported to cause exacerbation or activation of systemic lupus erythematosus.
5.6Lithium Interaction Increases in serum lithium concentrations and lithium toxicity have been reported with concomitant use of valsartan or thiazide diuretics. Monitor lithium levels in patients receiving valsartan and hydrochlorothiazide tablets and lithium [see Drug Interactions (7) ] .
5.7Potassium Abnormalities In the controlled trials of various doses of valsartan and hydrochlorothiazide tablets, the incidence of hypertensive patients who developed hypokalemia (serum potassium < 3.5 mEq/L) was 3.0%; the incidence of hyperkalemia (serum potassium > 5.7 mEq/L) was 0.4%. Hydrochlorothiazide can cause hypokalemia and hyponatremia. Hypomagnesemia can result in hypokalemia which appears difficult to treat despite potassium repletion.
Drugs that inhibit the renin-angiotensin system can cause hyperkalemia. Monitor serum e…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The most common reasons for discontinuation of therapy with valsartan and hydrochlorothiazide tablets were headache and dizziness. The only adverse experience that occurred in ≥ 2% of patients treated with valsartan and hydrochlorothiazide tablets and at a higher incidence than placebo was nasopharyngitis (2.4% vs. 1.9%).
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Mylan at 1-877-446-3679 (1-877-4-INFO-RX) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical studies are conducted under widely varying conditions, adverse reactions rates observed in the clinical studies of a drug cannot be directly compared to rates in the clinical studies of another drug and may not reflect the rates observed in practice. The adverse reaction information from clinical trials does, however, provide a basis for identifying the adverse events that appear to be related to drug use and for approximating rates. Hypertension Valsartan and hydrochlorothiazide tablets have been evaluated for safety in more than 5700 patients, including over 990 treated for over 6 months, and over 370 for over 1 year.
Adverse experiences have generally been mild and transient in nature and have only infrequently required discontinuation of therapy. The overall incidence of adverse reactions with valsartan and hydrochlorothiazide was comparable to placebo. The overall frequency of adverse reactions was neither dose-related nor related to gender, age, or race.
In controlled clinical trials, discontinuation of therapy due to side effects was required in 2.3% of valsartan-hydrochlorothiazide patients and 3.1% of placebo patients. The most common reasons for discontinuation of therapy with valsartan and hydrochlorothiazide tablets were headache and dizziness. The only adverse reaction that occurred in controlled clinical trials in at least 2% of patients treated with valsartan and hydrochlorothiazide tablets and at a higher incidence in valsartan-hydrochlorothiazide (n = 4372) than placebo (n = 262) patients was nasopharyngitis (2.4% vs.
1.9%). Dose-related orthostatic effects were seen in fewer than 1% of patients. In individual trials, a dose-related increase in the incidence of dizziness was observed in patients treated with valsartan and hydrochlorothiazide tablets.
Initial Therapy – Hypertension In a clinical study in patients with severe hypertension (diastolic blood pressure ≥ 110 mmHg and systolic blood pressure ≥ 140 mmHg), the overall pattern of adverse reactions reported through 6 weeks of follow-up was similar in patients treated with valsartan and hydrochlorothiazide tablets as initial therapy and in patients treated with valsartan as initial therapy. Comparing the groups treated with valsartan and hydrochlorothiazide tablets (force-titrated to 320/25 mg) and valsartan (force-titrated to 320 mg), dizziness was observed in 6% and 2% of patients, respectively.
Hypotension was observed in 1% of those patients receiving valsartan and hydrochlorothiazide tablets and 0% of patients receiving valsartan. There were no reported cases of syncope in either treatment group. Laboratory changes with valsartan and hydrochlorothiazide tablets as initial therapy in patients with severe hypertension were similar to those reported with valsartan and hydrochlorothiazide tablets in patients with less severe hypertension [see Clinical Studies (14.2) , Drug Interactions (7) ] .
Valsartan In trials in which valsartan was compared to an ACE inhibitor with or without placebo, the incidence of dry cough was significantly greater in the ACE inhibitor group (7.9%) than in the groups who received valsartan (2.6%) or placebo (1.5%). In a 129-patient trial limited to patients who had had dry cough when they had previously received ACE inhibitors, the incidences of cough in patients who received valsartan, hydrochlorothiazide, or lisinopril were 20%, 19%, 69% respectively (p < 0.001).
6.2 Postmarketing Experience The fol…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Valsartan-Hydrochlorothiazide: Lithium: Increases in serum lithium concentrations and lithium toxicity have been reported during concomitant administration of lithium with angiotensin II receptor antagonists or thiazides. Monitor lithium levels in patients taking valsartan and hydrochlorothiazide tablets. Valsartan: Agents Increasing Serum Potassium: Concomitant use of valsartan with other agents that block the renin-angiotensin system, potassium-sparing diuretics (e.g., spironolactone, triamterene, amiloride), potassium supplements, salt substitutes containing potassium or other drugs that may increase potassium levels (e.g., heparin) may lead to increases in serum potassium and in heart failure patients to increases in serum creatinine.
If co-medication is considered necessary, monitoring of serum potassium is advisable. Non-Steroidal Anti-Inflammatory Agents including Selective Cyclooxygenase-2 Inhibitors (COX-2 Inhibitors): In patients who are elderly, volume-depleted (including those on diuretic therapy), or with compromised renal function, coadministration of NSAIDs, including selective COX-2 inhibitors, with angiotensin II receptor antagonists, including valsartan, may result in deterioration of renal function, including possible acute renal failure.
These effects are usually reversible. Monitor renal function periodically in patients receiving valsartan and NSAID therapy. The antihypertensive effect of angiotensin II receptor antagonists, including valsartan, may be attenuated by NSAIDs including selective COX-2 inhibitors.
Dual Blockade of the Renin-Angiotensin System (RAS): Dual blockade of the RAS with angiotensin receptor blockers, ACE inhibitors, or aliskiren is associated with increased risks of hypotension, hyperkalemia, and changes in renal function (including acute renal failure) compared to monotherapy. Most patients receiving the combination of two RAS inhibitors do not obtain any additional benefit compared to monotherapy. In general, avoid combined use of RAS inhibitors.
Closely monitor blood pressure, renal function and electrolytes in patients on valsartan and other agents that affect the RAS. Do not coadminister aliskiren with valsartan in patients with diabetes. Avoid use of aliskiren with valsartan in patients with renal impairment (GFR < 60 mL/min).
Hydrochlorothiazide: When administered concurrently, the following drugs may interact with thiazide diuretics: Antidiabetic Drugs (oral agents and insulin): Dosage adjustment of the antidiabetic drug may be required. Nonsteroidal Anti-inflammatory Drugs (NSAIDs and COX-2 selective inhibitors): When valsartan and hydrochlorothiazide tablets and nonsteroidal anti-inflammatory agents are used concomitantly, the patient should be observed closely to determine if the desired effect of the diuretic is obtained. Carbamazepine: May lead to symptomatic hyponatremia.
Ion exchange resins: Staggering the dosage of hydrochlorothiazide and ion exchange resins (e.g., cholestyramine, colestipol) such that hydrochlorothiazide is administered at least 4 hours before or 4 to 6 hours after the administration of resins would potentially minimize the interaction [see Clinical Pharmacology (12.3) ]. Cyclosporine: Concomitant treatment with cyclosporine may increase the risk of hyperuricemia and gout-type complications. • Antidiabetic drugs: Dosage adjustment of antidiabetic may be required. ( 7 ) • Cholestyramine and colestipol: Reduced absorption of thiazides.
( 12.3 ) • Lithium: Increased risk of lithium toxicity. Monitor serum lithium concentrations during concurrent use. ( 7 ) • Non-Steroidal Anti-Inflammatory Drugs (NSAIDs): May increase risk of renal impairment.
Can reduce diuretic, natriuretic and antihypertensive effects of diuretics. ( 7 ) • Dual inhibition of the renin-angiotensin system: Increased risk of renal impairment, hypotension, and hyperkalemia. ( 7 )
Pharmacodynamic Drug Interactions Hydrochlorothiazide Alcohol, Barbiturates, or Narcotic…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Breastfeeding is not recommended ( 8.2 )
8.1Pregnancy Risk Summary Valsartan and hydrochlorothiazide tablets can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Most epidemiologic studies examining fetal abnormalities after exposure to antihypertensive use in the first trimester have not distinguished drugs affecting the renin-angiotensin system from other antihypertensive agents.
Published reports include cases of anhydramnios and oligohydramnios in pregnant women treated with valsartan [see Clinical Considerations ] . When pregnancy is detected discontinue valsartan and hydrochlorothiazide tablets as soon as possible. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk Hypertension in pregnancy increases the maternal risk for pre-eclampsia, gestational diabetes, premature delivery, and delivery complications (e.g., need for cesarean section and post-partum hemorrhage).
Hypertension increases the fetal risk for intrauterine growth restriction and intrauterine death. Pregnant women with hypertension should be carefully monitored and managed accordingly. Fetal/Neonatal Adverse Reactions Valsartan: Oligohydramnios in pregnant women who use drugs affecting the renin-angiotensin system in the second and third trimesters of pregnancy can result in the following: reduced fetal renal function leading to anuria and renal failure, fetal lung hypoplasia, skeletal deformations, including skull hypoplasia, hypotension and death.
Perform serial ultrasound examinations to assess the intra-amniotic environment. Fetal testing may be appropriate, based on the week of gestation. Patients and physicians should be aware, however, that oligohydramnios may not appear until after the fetus has sustained irreversible injury.
If oligohydramnios is observed, consider alternative drug treatment. Closely observe neonates with histories of in utero exposure to valsartan and hydrochlorothiazide tablets for hypotension, oliguria, and hyperkalemia. In neonates with a history of in utero exposure to valsartan and hydrochlorothiazide tablets, if oliguria or hypotension occurs, support blood pressure and renal perfusion.
Exchange transfusions or dialysis may be required as a means of reversing hypotension and replacing renal function. Hydrochlorothiazide: Thiazides can cross the placenta, and concentrations reached in the umbilical vein approach those in the maternal plasma. Hydrochlorothiazide, like other diuretics, can cause placental hypoperfusion.
It accumulates in the amniotic fluid, with reported concentrations up to 19 times higher than in umbilical vein plasma. Use of thiazides during pregnancy is associated with a risk of fetal or neonatal jaundice or thrombocytopenia. Since they do not prevent or alter the course of EPH (Edema, Proteinuria, Hypertension) gestosis (pre-eclampsia), these drugs should not be used to treat hypertension in pregnant women.
The use of hydrochlorothiazide for other indications (e.g., heart disease) in pregnancy should be avoided. Data Animal Data Valsartan Plus Hydrochlorothiazide There was no evidence of teratogenicity in mice, rats, or rabbits treated orally with valsartan at doses of up to 600, 100, and 10 mg/kg/day [9, 3.5 and 0.5 times the maximum recommended human dose (MRHD)], respectively, in combination with hydrochlorothiazide at doses up to 188, 31, and 3 mg/kg/day (38, 13 and 2 times the MRH…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Valsartan and hydrochlorothiazide tablets can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Most epidemiologic studies examining fetal abnormalities after exposure to antihypertensive use in the first trimester have not distinguished drugs affecting the renin-angiotensin system from other antihypertensive agents.
Published reports include cases of anhydramnios and oligohydramnios in pregnant women treated with valsartan [see Clinical Considerations ] . When pregnancy is detected discontinue valsartan and hydrochlorothiazide tablets as soon as possible. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk Hypertension in pregnancy increases the maternal risk for pre-eclampsia, gestational diabetes, premature delivery, and delivery complications (e.g., need for cesarean section and post-partum hemorrhage).
Hypertension increases the fetal risk for intrauterine growth restriction and intrauterine death. Pregnant women with hypertension should be carefully monitored and managed accordingly. Fetal/Neonatal Adverse Reactions Valsartan: Oligohydramnios in pregnant women who use drugs affecting the renin-angiotensin system in the second and third trimesters of pregnancy can result in the following: reduced fetal renal function leading to anuria and renal failure, fetal lung hypoplasia, skeletal deformations, including skull hypoplasia, hypotension and death.
Perform serial ultrasound examinations to assess the intra-amniotic environment. Fetal testing may be appropriate, based on the week of gestation. Patients and physicians should be aware, however, that oligohydramnios may not appear until after the fetus has sustained irreversible injury.
If oligohydramnios is observed, consider alternative drug treatment. Closely observe neonates with histories of in utero exposure to valsartan and hydrochlorothiazide tablets for hypotension, oliguria, and hyperkalemia. In neonates with a history of in utero exposure to valsartan and hydrochlorothiazide tablets, if oliguria or hypotension occurs, support blood pressure and renal perfusion.
Exchange transfusions or dialysis may be required as a means of reversing hypotension and replacing renal function. Hydrochlorothiazide: Thiazides can cross the placenta, and concentrations reached in the umbilical vein approach those in the maternal plasma. Hydrochlorothiazide, like other diuretics, can cause placental hypoperfusion.
It accumulates in the amniotic fluid, with reported concentrations up to 19 times higher than in umbilical vein plasma. Use of thiazides during pregnancy is associated with a risk of fetal or neonatal jaundice or thrombocytopenia. Since they do not prevent or alter the course of EPH (Edema, Proteinuria, Hypertension) gestosis (pre-eclampsia), these drugs should not be used to treat hypertension in pregnant women.
The use of hydrochlorothiazide for other indications (e.g., heart disease) in pregnancy should be avoided. Data Animal Data Valsartan Plus Hydrochlorothiazide There was no evidence of teratogenicity in mice, rats, or rabbits treated orally with valsartan at doses of up to 600, 100, and 10 mg/kg/day [9, 3.5 and 0.5 times the maximum recommended human dose (MRHD)], respectively, in combination with hydrochlorothiazide at doses up to 188, 31, and 3 mg/kg/day (38, 13 and 2 times the MRHD). Fetotoxicity was observed in association with maternal toxicity in rats at val…
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of valsartan and hydrochlorothiazide in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use In the controlled clinical trials of valsartan and hydrochlorothiazide tablets, 764 (17.5%) patients treated with valsartan-hydrochlorothiazide were ≥ 65 years and 118 (2.7%) were ≥ 75 years. No overall difference in the efficacy or safety of valsartan-hydrochlorothiazide was observed between these patients and younger patients, but greater sensitivity of some older individuals cannot be ruled out.
🆘 Overdosage ▾
10 OVERDOSAGE Limited data are available related to overdosage in humans. The most likely manifestations of overdosage would be hypotension and tachycardia; bradycardia could occur from parasympathetic (vagal) stimulation. Depressed level of consciousness, circulatory collapse and shock have been reported.
If symptomatic hypotension should occur institute supportive treatment. Valsartan is not removed from the plasma by dialysis. The degree to which hydrochlorothiazide is removed by hemodialysis has not been established.
The most common signs and symptoms observed in patients are those caused by electrolyte depletion (hypokalemia, hypochloremia, hyponatremia) and dehydration resulting from excessive diuresis. If digitalis has also been administered, hypokalemia may accentuate cardiac arrhythmias. In rats and marmosets, single oral doses of valsartan up to 1524 and 762 mg/kg in combination with hydrochlorothiazide at doses up to 476 and 238 mg/kg, respectively, did not show any adverse treatment-related effects.
These no adverse effect doses in rats and marmosets, respectively, represent 46.5 and 23 times the MRHD of valsartan and 188 and 113 times the MRHD of hydrochlorothiazide on a mg/m 2 basis. (Calculations assume an oral dose of 320 mg/day valsartan in combination with 25 mg/day hydrochlorothiazide and a 60-kg patient.) Valsartan was without grossly observable adverse effects at single oral doses up to 2000 mg/kg in rats and up to 1000 mg/kg in marmosets, except for salivation and diarrhea in the rat and vomiting in the marmoset at the highest dose (60 and 31 times, respectively, the MRHD on a mg/m 2 basis).
(Calculations assume an oral dose of 320 mg/day and a 60-kg patient.) The oral LD 50 of hydrochlorothiazide is greater than 10 g/kg in both mice and rats, which represents 2027 and 4054 times, respectively, the MRHD on a mg/m 2 basis. (Calculations assume an oral dose of 25 mg/day and a 60-kg patient.)
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Angiotensin II is formed from angiotensin I in a reaction catalyzed by angiotensin-converting enzyme (ACE, kininase II). Angiotensin II is the principal pressor agent of the renin-angiotensin system, with effects that include vasoconstriction, stimulation of synthesis and release of aldosterone, cardiac stimulation, and renal reabsorption of sodium. Valsartan blocks the vasoconstrictor and aldosterone-secreting effects of angiotensin II by selectively blocking the binding of angiotensin II to the AT 1 receptor in many tissues, such as vascular smooth muscle and the adrenal gland.
Its action is therefore independent of the pathways for angiotensin II synthesis. There is also an AT 2 receptor found in many tissues, but AT 2 is not known to be associated with cardiovascular homeostasis. Valsartan has much greater affinity (about 20,000-fold) for the AT 1 receptor than for the AT 2 receptor.
The primary metabolite of valsartan is essentially inactive with an affinity for the AT 1 receptor about one 200 th that of valsartan itself. Blockade of the renin-angiotensin system with ACE inhibitors, which inhibit the biosynthesis of angiotensin II from angiotensin I, is widely used in the treatment of hypertension. ACE inhibitors also inhibit the degradation of bradykinin, a reaction also catalyzed by ACE.
Because valsartan does not inhibit ACE (kininase II), it does not affect the response to bradykinin. Whether this difference has clinical relevance is not yet known. Valsartan does not bind to or block other hormone receptors or ion channels known to be important in cardiovascular regulation.
Blockade of the angiotensin II receptor inhibits the negative regulatory feedback of angiotensin II on renin secretion, but the resulting increased plasma renin activity and angiotensin II circulating levels do not overcome the effect of valsartan on blood pressure. Hydrochlorothiazide is a thiazide diuretic. Thiazides affect the renal tubular mechanisms of electrolyte reabsorption, directly increasing excretion of sodium and chloride in approximately equivalent amounts.
Indirectly, the diuretic action of hydrochlorothiazide reduces plasma volume, with consequent increases in plasma renin activity, increases in aldosterone secretion, increases in urinary potassium loss, and decreases in serum potassium. The renin-aldosterone link is mediated by angiotensin II, so coadministration of an angiotensin II receptor antagonist tends to reverse the potassium loss associated with these diuretics. The mechanism of the antihypertensive effect of thiazides is unknown.
12.2Pharmacodynamics Valsartan Valsartan inhibits the pressor effect of angiotensin II infusions. An oral dose of 80 mg inhibits the pressor effect by about 80% at peak with approximately 30% inhibition persisting for 24 hours. No information on the effect of larger doses is available.
Removal of the negative feedback of angiotensin II causes a 2- to 3-fold rise in plasma renin and consequent rise in angiotensin II plasma concentration in hypertensive patients. Minimal decreases in plasma aldosterone were observed after administration of valsartan; very little effect on serum potassium was observed. Hydrochlorothiazide After oral administration of hydrochlorothiazide, diuresis begins within 2 hours, peaks in about 4 hours and lasts about 6 to 12 hours.
Pharmacodynamic Drug Interactions Hydrochlorothiazide Alcohol, Barbiturates, or Narcotics Potentiation of orthostatic hypotension may occur. Skeletal Muscle Relaxants Possible increased responsiveness to muscle relaxants such as curare derivatives. Digitalis Glycosides Thiazide-induced hypokalemia or hypomagnesemia may predispose the patient to digoxin toxicity.
12.3Pharmacokinetics Valsartan Valsartan peak plasma concentration is reached 2 to 4 hours after dosing. Valsartan shows bi-exponential decay kinetics following intravenous administration, with an average elimination half-life of about 6 h…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Angiotensin II is formed from angiotensin I in a reaction catalyzed by angiotensin-converting enzyme (ACE, kininase II). Angiotensin II is the principal pressor agent of the renin-angiotensin system, with effects that include vasoconstriction, stimulation of synthesis and release of aldosterone, cardiac stimulation, and renal reabsorption of sodium. Valsartan blocks the vasoconstrictor and aldosterone-secreting effects of angiotensin II by selectively blocking the binding of angiotensin II to the AT 1 receptor in many tissues, such as vascular smooth muscle and the adrenal gland.
Its action is therefore independent of the pathways for angiotensin II synthesis. There is also an AT 2 receptor found in many tissues, but AT 2 is not known to be associated with cardiovascular homeostasis. Valsartan has much greater affinity (about 20,000-fold) for the AT 1 receptor than for the AT 2 receptor.
The primary metabolite of valsartan is essentially inactive with an affinity for the AT 1 receptor about one 200 th that of valsartan itself. Blockade of the renin-angiotensin system with ACE inhibitors, which inhibit the biosynthesis of angiotensin II from angiotensin I, is widely used in the treatment of hypertension. ACE inhibitors also inhibit the degradation of bradykinin, a reaction also catalyzed by ACE.
Because valsartan does not inhibit ACE (kininase II), it does not affect the response to bradykinin. Whether this difference has clinical relevance is not yet known. Valsartan does not bind to or block other hormone receptors or ion channels known to be important in cardiovascular regulation.
Blockade of the angiotensin II receptor inhibits the negative regulatory feedback of angiotensin II on renin secretion, but the resulting increased plasma renin activity and angiotensin II circulating levels do not overcome the effect of valsartan on blood pressure. Hydrochlorothiazide is a thiazide diuretic. Thiazides affect the renal tubular mechanisms of electrolyte reabsorption, directly increasing excretion of sodium and chloride in approximately equivalent amounts.
Indirectly, the diuretic action of hydrochlorothiazide reduces plasma volume, with consequent increases in plasma renin activity, increases in aldosterone secretion, increases in urinary potassium loss, and decreases in serum potassium. The renin-aldosterone link is mediated by angiotensin II, so coadministration of an angiotensin II receptor antagonist tends to reverse the potassium loss associated with these diuretics. The mechanism of the antihypertensive effect of thiazides is unknown.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Valsartan and Hydrochlorothiazide Tablets, USP are available containing 80 mg/12.5 mg, 160 mg/12.5 mg, 160 mg/25 mg, 320 mg/12.5 mg or 320 mg/25 mg of valsartan, USP and hydrochlorothiazide, USP. The 80 mg/12.5 mg tablets are orange, film-coated, round, unscored tablets, debossed with M on one side of the tablet and V21 on the other side. They are available as follows: NDC 0378-6321-77 bottles of 90 tablets The 160 mg/12.5 mg tablets are orange, film-coated, round, unscored tablets, debossed with M on one side of the tablet and V22 on the other side.
They are available as follows: NDC 0378-6322-77 bottles of 90 tablets The 160 mg/25 mg tablets are orange, film-coated, oval, unscored tablets, debossed with M on one side of the tablet and V23 on the other side. They are available as follows: NDC 0378-6323-77 bottles of 90 tablets The 320 mg/12.5 mg tablets are orange, film-coated, oval, unscored tablets debossed with M on one side of the tablet and V24 on the other side. They are available as follows: NDC 0378-6324-77 bottles of 90 tablets The 320 mg/25 mg tablets are beige, film-coated, oval, unscored tablets debossed with M on one side of the tablet and V25 on the other side.
They are available as follows: NDC 0378-6325-77 bottles of 90 tablets Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.] Protect from moisture and heat. Dispense in a tight, light-resistant container as defined in the USP using a child-resistant closure.
📋 Description ▾
11 DESCRIPTION Valsartan and hydrochlorothiazide tablets, USP are a combination of valsartan, an orally active, specific angiotensin II receptor blocker (ARB) acting on the AT 1 receptor subtype, and hydrochlorothiazide, a diuretic. Valsartan, a nonpeptide molecule, is chemically described as N -[p-(o-1 H -Tetrazol-5-ylphenyl)benzyl- N -valeryl- L -valine. Its molecular formula is C 24 H 29 N 5 O 3 , its molecular weight is 435.5, and its structural formula is: Valsartan, USP is a white to practically white fine powder.
It is soluble in ethanol and methanol and slightly soluble in water. Hydrochlorothiazide, USP is a white, or practically white, practically odorless, crystalline powder. It is slightly soluble in water; freely soluble in sodium hydroxide solution, in n -butylamine, and in dimethylformamide; sparingly soluble in methanol; and insoluble in ether, in chloroform, and in dilute mineral acids.
Hydrochlorothiazide is chemically described as 6-Chloro-3,4-dihydro-2 H -1,2,4-benzothiadiazine-7-sulfonamide 1,1-dioxide. Hydrochlorothiazide is a thiazide diuretic. Its molecular formula is C 7 H 8 ClN 3 O 4 S 2 , its molecular weight is 297.73, and its structural formula is: Valsartan and hydrochlorothiazide tablets are formulated for oral administration to contain valsartan and hydrochlorothiazide 80 mg/12.5 mg, 160 mg/12.5 mg, 160 mg/25 mg, 320 mg/12.5 mg and 320 mg/25 mg.
The inactive ingredients of the tablets are colloidal silicon dioxide, crospovidone, hypromellose, lactose monohydrate, magnesium stearate, microcrystalline cellulose, polydextrose, polyethylene glycol, povidone, pregelatinized starch (corn), sodium lauryl sulfate, titanium dioxide, triacetin and vanillin. The 80 mg/12.5 mg, 160 mg/12.5 mg, 160 mg/25 mg and 320 mg/12.5 mg tablets also contain red iron oxide and yellow iron oxide. The 320 mg/25 mg tablet also contains FD&C Blue No.
2 Aluminum Lake and FD&C Yellow No. 6 Aluminum Lake. Valsartan Structural Formula Hydrochlorothiazide Structural Formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Information for Patients: Advise the patient to read the FDA-approved patient labeling ( Patient Information ). Pregnancy: Advise female patients of childbearing age about the consequences of exposure to valsartan and hydrochlorothiazide tablets during pregnancy. Discuss treatment options with women planning to become pregnant.
Ask patients to report pregnancies to their physicians as soon as possible [see Warnings and Precautions (5.1) , Use in Specific Populations (8.1) ] . Lactation: Advise women not to breastfeed during treatment with valsartan and hydrochlorothiazide tablets [see Use in Specific Populations (8.2) ] . Symptomatic Hypotension: Advise patients that lightheadedness can occur, especially during the first days of therapy, and that it should be reported to their healthcare provider.
Tell patients that if syncope occurs, to discontinue valsartan and hydrochlorothiazide tablets until the physician has been consulted. Caution all patients that inadequate fluid intake, excessive perspiration, diarrhea, or vomiting can lead to an excessive fall in blood pressure, with the same consequences of lightheadedness and possible syncope [see Warnings and Precautions (5.2) ] . Potassium Supplements: Advise patients not to use salt substitutes without consulting their healthcare provider [see Drug Interactions (7) ] .
Non-Melanoma Skin Cancer: Instruct patients taking hydrochlorothiazide to protect skin from the sun and undergo regular skin cancer screening.