
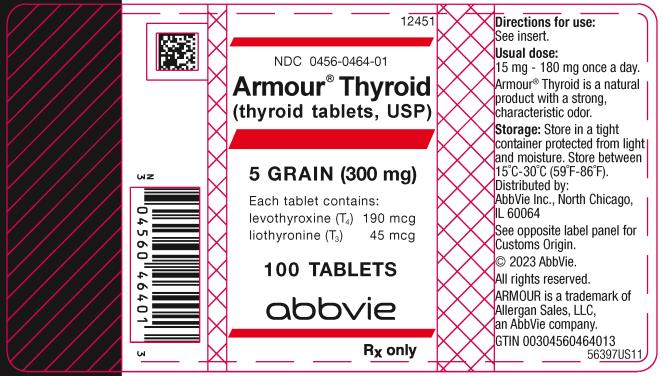
Armour Thyroid THYROID, PORCINE 300 mg Tablet, 100-count — NDC 0456-0464-01 (Billing 00456-0464-01)
This is a package of 100 tablets of Armour Thyroid THYROID, PORCINE 300 mg Tablet from Allergan, Inc., marketed since Apr 1996 and currently FDA-listed, this package's marketing is listed to end Nov 2026; retail pharmacies pay about $2.21 per tablet (NADAC). It is this product's only package size.
Past resolved recalls for this product (1)
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 065428
- GCN: 27389
- HICL (First Databank): 002846
- AHFS class code: 68:36.04.00
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
Clinical
Thyroid is used to treat the symptoms of hypothyroidism (a condition where the thyroid gland does not produce enough thyroid hormone). Symptoms of hypothyroidism include lack of energy, depression, constipation, weight gain, hair loss, dry skin, dry coarse hair, muscle cramps, decreased concentration, aches and pains, swelling of the legs, and increased sensitivity to cold. Thyroid is also used to treat goiter (enlarged thyroid gland). Thyroid is in a class of medications called thyroid agents. It works by supplying the thyroid hormone normally produced by the body.
Read the full MedlinePlus article ↗- Great question. Desiccated thyroid — the active ingredient in products like Amerithroid and Thyroid Tablets — is made from dried pig (porcine) thyroid glands. It naturally contains...
- What exactly is desiccated thyroid, and is it different from the synthetic thyroid hormone my friend takes?
- It does matter a bit. Fasting actually increases the absorption of thyroid hormones, so many people take their tablet first thing in the morning, about 30–60 minutes before eating....
- Can I take my thyroid tablet with breakfast, or does it matter?
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $2.205 | $220.50 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | $2.26 | $225.95 / 100 tablets |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q4 2025
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00456-0464-01 You're viewing this Main listing | 100 TABLET in 1 BOTTLE | 1996-04-01 | Nov 30, 2026 | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Armour Thyroid 300 mgthis 00456-0464-01 | Allergan, | 100 tablets | $2.205 | — | Availability likely | — |
| Niva Thyroid 300 mg 75834-0317-01 | Nivagen | 100 tablets | — | — | FDA listed | — |
| Amerithroid 300 mg 82685-0348-01 | Oliva | 100 tablets | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 776XM7047L
Calcium stearate is a white powder derived from stearic acid and calcium. It works as a lubricant and glidant to help the medicine flow smoothly during manufacturing and prevent ingredients from sticking to equipment.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII IY9XDZ35W2
Dextrose is a simple sugar derived from corn or other sources. It serves as a filler and sweetener in medicines to add bulk, improve taste, and help stabilize the medication's form.
-
UNII H8AV0SQX4D
A modified starch derived from potato or corn starch. It absorbs water quickly and helps tablets or capsules break apart and dissolve in the stomach, acting as a disintegrant to ensure the medicine releases its active ingredients properly.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
Drugs with thyroid hormone activity, alone or together with other therapeutic agents, have been used for the treatment of obesity. In euthyroid patients, doses within the range of daily hormonal requirements are ineffective for weight reduction. Larger doses may produce serious or even life-threatening manifestations of toxicity, particularly when given in association with sympathomimetic amines such as those used for their anorectic effects.
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Armour Thyroid (thyroid tablets, USP) are indicated: 1. As replacement or supplemental therapy in patients with hypothyroidism of any etiology, except transient hypothyroidism during the recovery phase of subacute thyroiditis. This category includes cretinism, myxedema, and ordinary hypothyroidism in patients of any age (children, adults, the elderly), or state (including pregnancy); primary hypothyroidism resulting from functional deficiency, primary atrophy, partial or total absence of thyroid gland, or the effects of surgery, radiation, or drugs, with or without the presence of goiter; and secondary (pituitary), or tertiary (hypothalamic) hypothyroidism (See WARNINGS ).
2. As pituitary TSH suppressants, in the treatment or prevention of various types of euthyroid goiters, including thyroid nodules, subacute or chronic lymphocytic thyroiditis (Hashimoto’s), multinodular goiter, and in the management of thyroid cancer.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION The dosage of thyroid hormones is determined by the indication and must in every case be individualized according to patient response and laboratory findings. Biotin supplementation may interfere with immunoassays for TSH, T4, and T3, resulting in erroneous thyroid hormone test results. Inquire whether patients are taking biotin or biotin-containing supplements.
If so, advise them to stop biotin supplementation at least 2 days before assessing TSH and/or T4 levels (see PRECAUTIONS). Thyroid hormones are given orally. In acute, emergency conditions, injectable levothyroxine sodium (T4) may be given intravenously when oral administration is not feasible or desirable, as in the treatment of myxedema coma, or during total parenteral nutrition.
Intramuscular administration is not advisable because of reported poor absorption. Hypothyroidism — Therapy is usually instituted using low doses, with increments which depend on the cardiovascular status of the patient. The usual starting dose is 30 mg Armour Thyroid (thyroid tablets, USP), with increments of 15 mg every 2 to 3 weeks.
A lower starting dosage, 15 mg/day, is recommended in patients with long-standing myxedema, particularly if cardiovascular impairment is suspected, in which case extreme caution is recommended. The appearance of angina is an indication for a reduction in dosage. Most patients require 60 to 120 mg/day.
Failure to respond to doses of 180 mg suggests lack of compliance or malabsorption. Maintenance dosages 60 to 120 mg/day usually result in normal serum T4 and T3 levels. Adequate therapy usually results in normal TSH and T4 levels after 2 to 3 weeks of therapy.
Readjustment of thyroid hormone dosage should be made within the first four weeks of therapy, after proper clinical and laboratory evaluations, including serum levels of T4, bound and free, and TSH. Liothyronine (T3) may be used in preference to levothyroxine (T4) during radio-isotope scanning procedures, since induction of hypothyroidism in those cases is more abrupt and can be of shorter duration. It may also be preferred when impairment of peripheral conversion of levothyroxine (T4) and liothyronine (T3) is suspected.
Myxedema Coma — Myxedema coma is usually precipitated in the hypothyroid patient of long-standing by intercurrent illness or drugs such as sedatives and anesthetics and should be considered a medical emergency. Therapy should be directed at the correction of electrolyte disturbances and possible infection besides the administration of thyroid hormones. Corticosteroids should be administered routinely.
Levothyroxine (T4) and liothyronine (T3) may be administered via a nasogastric tube but the preferred route of administration of both hormones is intravenous. Levothyroxine sodium (T4) is given at a starting dose of 400 mcg (100 mcg/mL) given rapidly, and is usually well tolerated, even in the elderly. This initial dose is followed by daily supplements of 100 to 200 mcg given IV.
Normal T4 levels are achieved in 24 hours followed in 3 days by threefold elevation of T3. Oral therapy with thyroid hormone would be resumed as soon as the clinical situation has been stabilized and the patient is able to take oral medication. Thyroid Cancer — Exogenous thyroid hormone may produce regression of metastases from follicular and papillary carcinoma of the thyroid and is used as ancillary therapy of these conditions with radioactive iodine.
TSH should be suppressed to low or undetectable levels. Therefore, larger amounts of thyroid hormone than those used for replacement therapy are required. Medullary carcinoma of the thyroid is usually unresponsive to this therapy.
Thyroid Suppression Therapy — Administration of thyroid hormone in doses higher than those produced physiologically by the gland results in suppression of the production of endogenous hormone. This is the basis for the thyroid suppression test and is used as an aid in the diagnosis of patients with signs of mild hyp… [Excerpted — this section continues on DailyMed.]
⛔ Contraindications ▾
CONTRAINDICATIONS Thyroid hormone preparations are generally contraindicated in patients with diagnosed but as yet uncorrected adrenal cortical insufficiency, untreated thyrotoxicosis, and apparent hypersensitivity to any of their active or extraneous constituents. There is no well-documented evidence from the literature, however, of true allergic or idiosyncratic reactions to thyroid hormone.
⚠️ Warnings ▾
WARNINGS
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Adverse reactions other than those indicative of hyperthyroidism because of therapeutic overdosage, either initially or during the maintenance period, are rare (See OVERDOSAGE ).
🆘 Overdosage ▾
OVERDOSAGE Signs and Symptoms — Excessive doses of thyroid result in a hypermetabolic state resembling in every respect the condition of endogenous origin. The condition may be self-induced. Treatment of Overdosage — Dosage should be reduced or therapy temporarily discontinued if signs and symptoms of overdosage appear.
Treatment may be reinstituted at a lower dosage. In normal individuals, normal hypothalamic-pituitary-thyroid axis function is restored in 6 to 8 weeks after thyroid suppression. Treatment of acute massive thyroid hormone overdosage is aimed at reducing gastrointestinal absorption of the drugs and counteracting central and peripheral effects, mainly those of increased sympathetic activity.
Vomiting may be induced initially if further gastrointestinal absorption can reasonably be prevented and barring contraindications such as coma, convulsions, or loss of the gagging reflex. Treatment is symptomatic and supportive. Oxygen may be administered and ventilation maintained.
Cardiac glycosides may be indicated if congestive heart failure develops. Measures to control fever, hypoglycemia, or fluid loss should be instituted if needed. Antiadrenergic agents, particularly propranolol, have been used advantageously in the treatment of increased sympathetic activity.
Propranolol may be administered intravenously at a dosage of 1 to 3 mg, over a 10-minute period or orally, 80 to 160 mg/day, initially, especially when no contraindications exist for its use. Other adjunctive measures may include administration of cholestyramine to interfere with thyroxine absorption, and glucocorticoids to inhibit conversion of T4 to T3.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY The steps in the synthesis of the thyroid hormones are controlled by thyrotropin (Thyroid Stimulating Hormone, TSH) secreted by the anterior pituitary. This hormone’s secretion is in turn controlled by a feedback mechanism effected by the thyroid hormones themselves and by thyrotropin releasing hormone (TRH), a tripeptide of hypothalamic origin. Endogenous thyroid hormone secretion is suppressed when exogenous thyroid hormones are administered to euthyroid individuals in excess of the normal gland’s secretion.
The mechanisms by which thyroid hormones exert their physiologic action are not well understood. These hormones enhance oxygen consumption by most tissues of the body, increase the basal metabolic rate, and the metabolism of carbohydrates, lipids, and proteins. Thus, they exert a profound influence on every organ system in the body and are of particular importance in the development of the central nervous system.
The normal thyroid gland contains approximately 200 mcg of levothyroxine (T4) per gram of gland, and 15 mcg of liothyronine (T3) per gram. The ratio of these two hormones in the circulation does not represent the ratio in the thyroid gland, since about 80% of peripheral liothyronine (T3) comes from monodeiodination of levothyroxine (T4). Peripheral monodeiodination of levothyroxine (T4) at the 5 position (inner ring) also results in the formation of reverse liothyronine (T3), which is calorigenically inactive.
Liothyronine (T3) levels are low in the fetus and newborn, in old age, in chronic caloric deprivation, hepatic cirrhosis, renal failure, surgical stress, and chronic illnesses representing what has been called the “T3 thyronine syndrome.” Pharmacokinetics – Animal studies have shown that levothyroxine (T4) is only partially absorbed from the gastrointestinal tract. The degree of absorption is dependent on the vehicle used for its administration and by the character of the intestinal contents, the intestinal flora, including plasma protein, and soluble dietary factors, all of which bind thyroid and thereby make it unavailable for diffusion.
Only 41% is absorbed when given in a gelatin capsule as opposed to a 74% absorption when given with an albumin carrier. Depending on other factors, absorption has varied from 48 to 79% of the administered dose. Fasting increases absorption.
Malabsorption syndromes, as well as dietary factors, (children’s soybean formula, concomitant use of anionic exchange resins such as cholestyramine) cause excessive fecal loss. Liothyronine (T3) is almost totally absorbed, 95% in 4 hours. The hormones contained in desiccated thyroid extract preparations are absorbed in a manner similar to the synthetic hormones.
More than 99% of circulating hormones are bound to serum proteins, including thyroid-binding globulin (TBg), thyroid-binding prealbumin (TBPA), and albumin (TBa), whose capacities and affinities vary for the hormones. The higher affinity of levothyroxine (T4) for both TBg and TBPA as compared to liothyronine (T3) partially explains the higher serum levels and longer half-life of the former hormone. Both protein-bound hormones exist in reverse equilibrium with minute amounts of free hormone, the latter accounting for the metabolic activity.
Deiodination of levothyroxine (T4) occurs at a number of sites, including liver, kidney, and other tissues. The conjugated hormone, in the form of glucuronide or sulfate, is found in the bile and gut where it may complete an enterohepatic circulation. 85% of levothyroxine (T4) metabolized daily is deiodinated.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Armour Thyroid (thyroid tablets, USP) are supplied as follows: 15 mg (1/4 grain) are available in bottles of 100 (NDC 0456-0457-01 or NDC 0456-1045-01). 30 mg (1/2 grain) are available in bottles of 100 (NDC 0456-0458-01) and unit dose cartons of 100 (NDC 0456-0458-63). 60 mg (1 grain) are available in bottles of 100 (NDC 0456-0459-01) and unit dose cartons of 100 (NDC 0456-0459-63).
90 mg (1 1/2 grain) are available in bottles of 100 (NDC 0456-0460-01). 120 mg (2 grain) are available in bottles of 100 (NDC 0456-0461-01) and unit dose cartons of 100 (NDC 0456-0461-63). 180 mg (3 grain) are available in bottles of 100 (NDC 0456-0462-01).
240 mg (4 grain) are available in bottles of 100 (NDC 0456-0463-01). 300 mg (5 grain) are available in bottles of 100 (NDC 0456-0464-01). The bottles of 100 are special dispensing bottles with child-resistant closures.
Armour Thyroid (thyroid tablets, USP) are evenly colored, light tan, round tablets, with convex surfaces. The ¼ grain strength has: One side debossed with a mortar and pestle beneath the letter “A” on the top and TC on the bottom (NDC 0456-0457-01); or One side debossed with a mortar and pestle beneath the letter “A” and the opposite side debossed with TC (NDC 0456-1045-01). Other tablet strengths have one side debossed with a mortar and pestle beneath the letter “A” on the top and strength code letters on the bottom as defined below Strength Code ½ grain TD 1 grain TE 1 ½ grain TJ 2 grain TF 3 grain TG (bisected) 4 grain TH 5 grain TI (bisected) Note: (T3 liothyronine is approximately four times as potent as T4 levothyroxine on a microgram for microgram basis.) Store in a tight container protected from light and moisture.
Store between 15°C and 30°C (59°F and 86°F). *Armour Thyroid (thyroid tablets, USP) has not been approved by FDA as a new drug . Distributed by: AbbVie, Inc., North Chicago, IL 60064 © 2024 AbbVie. All rights reserved.
ARMOUR is a trademark of Allergan Sales, LLC, an AbbVie company. Revised: March 2024 20084309
📋 Description ▾
DESCRIPTION Armour Thyroid (thyroid tablets, USP)* for oral use is a desiccated thyroid extract that is derived from porcine thyroid glands. (T3 liothyronine is approximately four times as potent as T4 levothyroxine on a microgram for microgram basis.) They provide 38 mcg levothyroxine (T4) and 9 mcg liothyronine (T3) per grain of thyroid. The inactive ingredients are calcium stearate, dextrose, microcrystalline cellulose, sodium starch glycolate and opadry white.
Armour Thyroid may have a strong, characteristic odor due to its thyroid extract component. Structural Formulas
⚠️ Precautions ▾
PRECAUTIONS General — Thyroid hormones should be used with great caution in a number of circumstances where the integrity of the cardiovascular system, particularly the coronary arteries, is suspected. These include patients with angina pectoris or the elderly, in whom there is a greater likelihood of occult cardiac disease. In these patients, therapy should be initiated with low doses, i.e., 15-30 mg Armour Thyroid (thyroid tablets, USP).
When, in such patients, a euthyroid state can only be reached at the expense of an aggravation of the cardiovascular disease, thyroid hormone dosage should be reduced. Thyroid hormone therapy in patients with concomitant diabetes mellitus or diabetes insipidus or adrenal cortical insufficiency aggravates the intensity of their symptoms. Appropriate adjustments of the various therapeutic measures directed at these concomitant endocrine diseases are required.
The therapy of myxedema coma requires simultaneous administration of glucocorticoids (See DOSAGE AND ADMINISTRATION ). Hypothyroidism decreases and hyperthyroidism increases the sensitivity to oral anticoagulants. Prothrombin time should be closely monitored in thyroid-treated patients on oral anticoagulants and dosage of the latter agents adjusted on the basis of frequent prothrombin time determinations.
In infants, excessive doses of thyroid hormone preparations may produce craniosynostosis. Information for the Patient — Patients on thyroid hormone preparations and parents of children on thyroid therapy should be informed that: 1. Replacement therapy is to be taken essentially for life, with the exception of cases of transient hypothyroidism, usually associated with thyroiditis, and in those patients receiving a therapeutic trial of the drug.
2. They should immediately report during the course of therapy any signs or symptoms of thyroid hormone toxicity, e.g., chest pain, increased pulse rate, palpitations, excessive sweating, heat intolerance, nervousness, or any other unusual event. 3.
In case of concomitant diabetes mellitus, the daily dosage of antidiabetic medication may need readjustment as thyroid hormone replacement is achieved. If thyroid medication is stopped, a downward readjustment of the dosage of insulin or oral hypoglycemic agent may be necessary to avoid hypoglycemia. At all times, close monitoring of urinary glucose levels is mandatory in such patients.
4. In case of concomitant oral anticoagulant therapy, the prothrombin time should be measured frequently to determine if the dosage of oral anticoagulants is to be readjusted. 5.
Instruct patients to discontinue biotin or any biotin-containing supplements for at least 2 days before thyroid function testing is conducted. 6. Partial loss of hair may be experienced by children in the first few months of thyroid therapy, but this is usually a transient phenomenon and later recovery is usually the rule.
Laboratory Tests — Treatment of patients with thyroid hormones requires the periodic assessment of thyroid status by means of appropriate laboratory tests besides the full clinical evaluation. The TSH suppression test can be used to test the effectiveness of any thyroid preparation bearing in mind the relative insensitivity of the infant pituitary to the negative feedback effect of thyroid hormones. Serum T4 levels can be used to test the effectiveness of all thyroid medications except T3.
When the total serum T4 is low but TSH is normal, a test specific to assess unbound (free) T4 levels is warranted. Specific measurements of T4 and T3 by competitive protein binding or radioimmunoassay are not influenced by blood levels of organic or inorganic iodine. Drug Interactions — Oral Anticoagulants – Thyroid hormones appear to increase catabolism of vitamin K-dependent clotting factors.
If oral anticoagulants are also being given, compensatory increases in clotting factor synthesis are impaired. Patients stabilized on oral anticoagulants who are found to require thyroid replacement t… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
Pharmacokinetics – Animal studies have shown that levothyroxine (T4) is only partially absorbed from the gastrointestinal tract. The degree of absorption is dependent on the vehicle used for its administration and by the character of the intestinal contents, the intestinal flora, including plasma protein, and soluble dietary factors, all of which bind thyroid and thereby make it unavailable for diffusion. Only 41% is absorbed when given in a gelatin capsule as opposed to a 74% absorption when given with an albumin carrier.
Depending on other factors, absorption has varied from 48 to 79% of the administered dose. Fasting increases absorption. Malabsorption syndromes, as well as dietary factors, (children’s soybean formula, concomitant use of anionic exchange resins such as cholestyramine) cause excessive fecal loss.
Liothyronine (T3) is almost totally absorbed, 95% in 4 hours. The hormones contained in desiccated thyroid extract preparations are absorbed in a manner similar to the synthetic hormones. More than 99% of circulating hormones are bound to serum proteins, including thyroid-binding globulin (TBg), thyroid-binding prealbumin (TBPA), and albumin (TBa), whose capacities and affinities vary for the hormones.
The higher affinity of levothyroxine (T4) for both TBg and TBPA as compared to liothyronine (T3) partially explains the higher serum levels and longer half-life of the former hormone. Both protein-bound hormones exist in reverse equilibrium with minute amounts of free hormone, the latter accounting for the metabolic activity. Deiodination of levothyroxine (T4) occurs at a number of sites, including liver, kidney, and other tissues.
The conjugated hormone, in the form of glucuronide or sulfate, is found in the bile and gut where it may complete an enterohepatic circulation. 85% of levothyroxine (T4) metabolized daily is deiodinated.
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL NDC 0456-0457-01 Armour ® Thyroid (thyroid tablets, USP) ¼ GRAIN (15 mg) Each tablet contains: levothyroxine (T 4 ) 9.5 mcg liothyronine (T 3 ) 2.25 mcg 100 TABLETS abbvie Rx only NDC 0456-0457-01 Armour® Thyroid (thyroid tablets, USP) ¼ GRAIN (15 mg) Each tablet contains: levothyroxine (T4) 9.5 mcg liothyronine (T3) 2.25 mcg 100 TABLETS abbvie Rx only
PRINCIPAL DISPLAY PANEL NDC 0456-0458-01 Armour ® Thyroid (thyroid tablets, USP) ½ GRAIN (30 mg) Each tablet contains: levothyroxine (T 4 ) 19 mcg liothyronine (T 3 ) 4.5 mcg 100 TABLETS abbvie Rx only NDC 0456-0458-01 Armour® Thyroid (thyroid tablets, USP) ½ GRAIN (30 mg) Each tablet contains: levothyroxine (T4) 19 mcg liothyronine (T3) 4.5 mcg 100 TABLETS abbvie Rx only
PRINCIPAL DISPLAY PANEL NDC 0456-0459-01 Armour ® Thyroid (thyroid tablets, USP) 1 GRAIN (60 mg) Each tablet contains: levothyroxine (T 4 ) 38 mcg liothyronine (T 3 ) 9 mcg 100 TABLETS abbvie Rx only NDC 0456-0459-01 Armour® Thyroid (thyroid tablets, USP) 1 GRAIN (60 mg) Each tablet contains: levothyroxine (T4) 38 mcg liothyronine (T3) 9 mcg 100 TABLETS abbvie Rx only
PRINCIPAL DISPLAY PANEL NDC 0456-0460-01 Armour ® Thyroid (thyroid tablets, USP) 1½ GRAIN (90 mg) Each tablet contains: levothyroxine (T 4 ) 57 mcg liothyronine (T 3 ) 13.5 mcg 100 TABLETS abbvie Rx only NDC 0456-0460-01 Armour® Thyroid (thyroid tablets, USP) 1½ GRAIN (90 mg) Each tablet contains: levothyroxine (T4) 57 mcg liothyronine (T3) 13.5 mcg 100 TABLETS abbvie Rx only
PRINCIPAL DISPLAY PANEL NDC 0456-0461-01 Armour ® Thyroid (thyroid tablets, USP) 2 GRAIN (120 mg) Each tablet contains: levothyroxine (T 4 ) 76 mcg liothyronine (T 3 ) 18 mcg 100 TABLETS abbvie Rx only NDC 0456-0461-01 Armour® Thyroid (thyroid tablets, USP) 2 GRAIN (120 mg) Each tablet contains: levothyroxine (T4) 76 mcg liothyronine (T3) 18 mcg 100 TABLETS abbvie Rx only
PRINCIPAL DISPLAY PANEL NDC 0456-0462-01 Armour ® Thyroid (thyroid tablets, USP) 3 GRAIN (180 mg) Each tablet contains: levothyroxine (T 4 ) 114 mcg liothyronine (T 3 ) 27 mcg 100 TABLETS abbvie Rx only NDC 0456-0462-01 Armour® Thyroid (thyroid tablets, USP) 3 GRAIN (180 mg) Each tablet contains: levothyroxine (T4) 114 mcg liothyronine (T3) 27 mcg 100 TABLETS abbvie Rx only
PRINCIPAL DISPLAY PANEL NDC 0456-0463-01 Armour ® Thyroid (thyroid tablets, USP) 4 GRAIN (240 mg) Each tablet contains: levothyroxine (T 4 ) 152 mcg liothyronine (T 3 ) 36 mcg 100 TABLETS abbvie Rx only NDC 0456-0463-01 Armour® Thyroid (thyroid tablets, USP) 4 GRAIN (240 mg) Each tablet contains: levothyroxine (T4) 152 mcg liothyronine (T3) 36 mcg 100 TABLETS abbvie Rx only
PRINCIPAL DISPLAY PANEL NDC 0456-0464-01 Armour ® Thyroid (thyroid tablets, USP) 5 GRAIN (300 mg) Each tablet contains: levothyroxine (T 4 ) 190 mcg liothyronine (T 3 ) 45 mcg 100 TABLETS abbvie Rx only NDC 0456-0464-01 Armour® Thyroid (thyroid tablets, USP) 5 GRAIN (300 mg) Each tablet contains: levothyroxine (T4) 190 mcg liothyronine (T3) 45 mcg 100 TABLETS abbvie Rx only
PRINCIPAL DISPLAY PANEL NDC 0456-1045-01 Armour ® Thyroid (thyroid tablets, USP) 1/4 GRAIN ( 15 mg) Each tablet contains: levothyroxine (T 4 ) 9.5 mcg liothyronine (T 3 ) 2.25 mcg 100 TABLETS abbvie Rx only NDC 0456-1045-01 Armour® Thyroid (thyroid tablets, USP) 1/4 GRAIN (15 mg) Each tablet contains: levothyroxine (T4) 9.5 mcg liothyronine (T3) 2.25 mcg 100 TABLETS abbvie Rx only
Medicaid utilization & spend
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
Listed without an FDA application
This product's marketing category indicates it is marketed without an approved FDA application (no NDA, ANDA, or BLA on file). Having an NDC does not by itself establish FDA approval — the NDC Directory is a listing system, not an approval decision. Approval-linked data such as Orange Book therapeutic-equivalence ratings therefore does not apply.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | ✓ Available |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |