
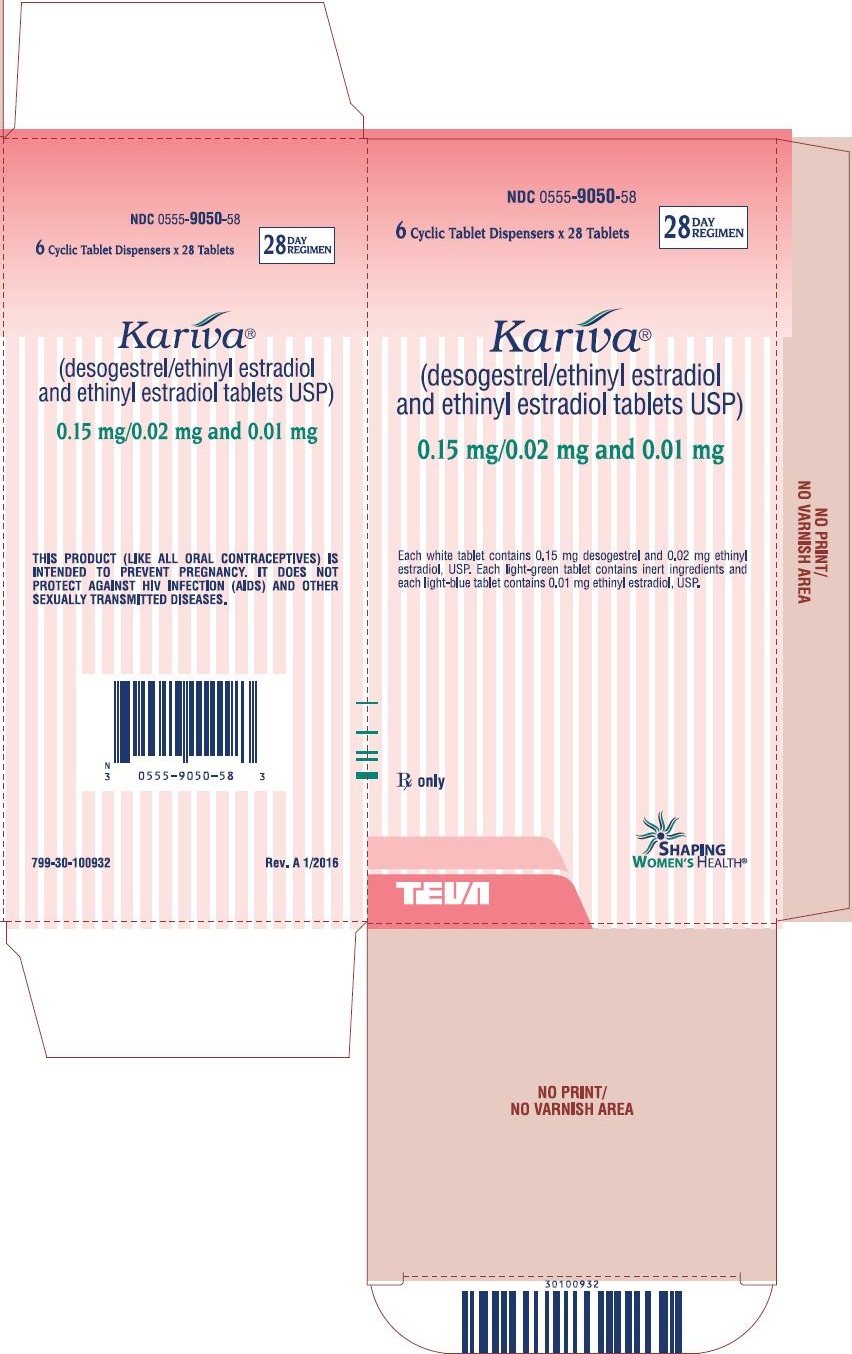
Kariva Desogestrel/Ethinyl Estradiol and Ethinyl Kit, 6 pouches — NDC 0555-9050-58 (Billing 00555-9050-58)
This is a package of 6 pouches of Kariva Desogestrel/Ethinyl Estradiol and Ethinyl Kit from Teva Pharmaceuticals USA, Inc., marketed since Apr 2002 and currently FDA-listed; retail pharmacies pay about $0.1725 per pouche (NADAC). It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 0555-9050-58 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0555 labeler · 9050 product · 58 package
- Package marketed since
- Apr 8, 2002
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Billing quantity
- 6 EA per package
- Barcode (UPC-A, from the NDC)
- 3 0555905058 3
- Medicaid fills, this package
- 11,129 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 040125
- GCN: 94868
- GPI-14 (Medi-Span): 25991002050320
- HICL (First Databank): 018520
- AHFS class code: 68:12.00.00
- RxCUI (RxNorm): 248310
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Estrogen class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.173 | $1.04 / 6 kit |
| Medicaid paysCMS SDUD · 12 mo | $0.3634 | $2.18 / 6 kit |
| Medicare drug plans payPart D · Q2 2026 | $0.3500 | $2.10 / 6 kit |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00555-9050-58 You're viewing this Main listing | 6 POUCH in 1 CARTON / 1 BLISTER PACK in 1 POUCH / 1 KIT in 1 BLISTER PACK | 2002-04-08 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Azurette 51862-0890-01 | Mayne | 1 packet | $0.160 | AB | FDA listed | save 7% |
| Pimtrea 16714-0404-01 | Northstar | 1 packet | $0.172 | AB | Availability likely | — |
| Azurette 75907-0091-28 | Dr. | 1 packet | $0.172 | AB | Availability likely | — |
| Karivathis 00555-9050-58 | Teva | 6 pouches | $0.172 | AB | Availability likely | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 5, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Teva Pharmaceuticals USA, Inc. labeler code 00555
- Junel Fe 28 Day Norethindrone Acetate and Ethinyl Estradiol and Ferrous Fumarate Kit NDC 0555-9028-58
- Tri-Legest Fe 28 Day Norethindrone Acetate and Ethinyl Estradiol Kit NDC 0555-9032-70
- Balziva Norethindrone and Ethinyl Estradiol Kit NDC 0555-9034-58
- Apri 28 Day Desogestrel and Ethinyl Estradiol Kit NDC 0555-9043-58
- Aviane Levonorgestrel and Ethinyl Estradiol Kit NDC 0555-9045-58
- Cryselle Norgestrel and Ethinyl Estradiol Kit NDC 0555-9049-58
- Velivet Triphasic Regimen Desogestrel and Ethinyl Estradiol Kit NDC 0555-9051-67
- Kelnor 1/35 Ethynodiol Diacetate and Ethinyl Estradiol Kit NDC 0555-9064-58
- Aranelle norethindrone and ethinyl estradiol Kit NDC 0555-9066-67
- Jolessa Levonorgestrel / Ethinyl Estradiol Kit NDC 0555-9123-66
- OCELLA drospirenone and ethinyl estradiol Kit NDC 0555-9131-67
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: CIGARETTE SMOKING AND SERIOUS CARDIOVASCULAR EVENTS Cigarette smoking increases the risk of serious cardiovascular events from combination oral contraceptive (COC) use. This risk increases with age, particularly in women over 35 years of age, and with the number of cigarettes smoked. For this reason, COCs, including Kariva ® , are contraindicated in women who are over 35 years of age and smoke (see CONTRAINDICATIONS and WARNINGS ).
Cigarette smoking increases the risk of serious cardiovascular side effects from oral contraceptive use. This risk increases with age and with heavy smoking (15 or more cigarettes per day) and is quite marked in women over 35 years of age. Women who use oral contraceptives are strongly advised not to smoke.
Cigarette smoking increases the risk of serious cardiovascular side effects from oral contraceptive use. This risk increases with age and with heavy smoking (15 or more cigarettes per day) and is quite marked in women over 35 years of age. Women who use oral contraceptives are strongly advised not to smoke.
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Kariva ® (desogestrel/ethinyl estradiol and ethinyl estradiol tablets USP) is indicated for the prevention of pregnancy in women who elect to use this product as a method of contraception. Oral contraceptives are highly effective. Table II lists the typical accidental pregnancy rates for users of combination oral contraceptives and other methods of contraception.
The efficacy of these contraceptive methods, except sterilization, depends upon the reliability with which they are used. Correct and consistent use of these methods can result in lower failure rates. TABLE II: Percentage of women experiencing an unintended pregnancy during the first year of typical use and the first year of perfect use of contraception and the percentage continuing use at the end of the first year, United States. % of Women Experiencing an Unintended Pregnancy within the First Year of Use % of Women Continuing Use at One Year a (4) Method (1) Typical Use b (2) Perfect Use c (3) Chance d 85 85 Spermicides e 26 6 40 Periodic abstinence 25 63 Calendar 9 Ovulation Method 3 Sympto-Thermal f 2 Post-Ovulation 1 Withdrawal 19 4 Cap g Parous Women 40 26 42 Nulliparous Women 20 9 56 Sponge Parous Women 40 20 42 Nulliparous Women 20 9 56 Diaphragm g 20 6 56 Condom h Female (Reality) 21 5 56 Male 14 3 61 Pill 5 71 Progestin Only
0.5 Combined
0.1IUD Progesterone T 2.0 1.5 81 Copper T 380A 0.8 0.6 78 LNg 20 0.1 0.1 81 Depo-Provera 0.3 0.3 70 Norplant and Norplant-2 0.05 0.05 88 Female sterilization 0.5 0.5 100 Male sterilization 0.15 0.10 100 Adapted from Hatcher et al., 1998, ref #1. a) Among couples attempting to avoid pregnancy, the percentage who continue to use a method for one year. b) Among typical couples who initiate use of a method (not necessarily for the first time), the percentage who experience an accidental pregnancy during the first year if they do not stop use for any other reason. c) Among couples who initiate use of a method (not necessarily for the first time) and who use it perfectly (both consistently and correctly), the percentage who experience an accidental pregnancy during the first year if they do not stop use for any other reason. d) The percents becoming pregnant in columns (2) and (3) are based on data from populations where contraception is not used and from women who cease using contraception in order to become pregnant.
Among such populations, about 89% become pregnant within one year. This estimate was lowered slightly (to 85%) to represent the percent who would become pregnant within one year among women now relying on reversible methods of contraception if they abandoned contraception altogether. e) Foams, creams, gels, vaginal suppositories, and vaginal film. f) Cervical mucus (ovulation) method supplemented by calendar in the pre-ovulatory and basal body temperature in the post-ovulatory phases. g) With spermicidal cream or jelly. h) Without spermicides.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION To achieve maximum contraceptive effectiveness, Kariva ® must be taken exactly as directed and at intervals not exceeding 24 hours. Kariva ® may be initiated using either a Sunday start or a Day 1 start. NOTE: Each cycle pack dispenser is preprinted with the days of the week, starting with Sunday, to facilitate a Sunday start regimen.
Six different “day label strips” are provided with each cycle pack dispenser in order to accommodate a Day 1 start regimen. In this case, the patient should place the self-adhesive “day label strip” that corresponds to her starting day over the preprinted days. IMPORTANT: The possibility of ovulation and conception prior to initiation of use of Kariva ® should be considered.
The use of Kariva ® for contraception may be initiated 4 weeks postpartum in women who elect not to breastfeed. When the tablets are administered during the postpartum period, the increased risk of thromboembolic disease associated with the postpartum period must be considered (see CONTRAINDICATIONS and WARNINGS concerning thromboembolic disease. See also PRECAUTIONS for Nursing mothers ).
If the patient starts on Kariva ® postpartum, and has not yet had a period, she should be instructed to use another method of contraception until a white tablet has been taken daily for 7 days. SUNDAY START When initiating a Sunday start regimen, another method of contraception should be used until after the first 7 consecutive days of administration. Using a Sunday start, tablets are taken daily without interruption as follows: The first white tablet should be taken on the first Sunday after menstruation begins (if menstruation begins on Sunday, the first white tablet is taken on that day).
One white tablet is taken daily for 21 days, followed by 1 light-green (inert) tablet daily for 2 days and 1 light-blue (active) tablet daily for 5 days. For all subsequent cycles, the patient then begins a new 28-tablet regimen on the next day (Sunday) after taking the last light-blue tablet. [If switching from a Sunday start oral contraceptive, the first Kariva ® (desogestrel/ethinyl estradiol and ethinyl estradiol) tablet should be taken on the second Sunday after the last tablet of a 21 day regimen or should be taken on the first Sunday after the last inactive tablet of a 28 day regimen.] If a patient misses 1 white tablet, she should take the missed tablet as soon as she remembers.
If the patient misses 2 consecutive white tablets in Week 1 or Week 2, the patient should take 2 tablets the day she remembers and 2 tablets the next day; thereafter, the patient should resume taking 1 tablet daily until she finishes the cycle pack. The patient should be instructed to use a back-up method of birth control if she has intercourse in the 7 days after missing pills. If the patient misses 2 consecutive white tablets in the third week or misses 3 or more white tablets in a row at any time during the cycle, the patient should keep taking 1 white tablet daily until the next Sunday.
On Sunday the patient should throw out the rest of that cycle pack and start a new cycle pack that same day. The patient should be instructed to use a back-up method of birth control if she has intercourse in the 7 days after missing pills. DAY 1 START Counting the first day of menstruation as “Day 1”, tablets are taken without interruption as follows: One white tablet daily for 21 days, one light-green (inert) tablet daily for 2 days followed by 1 light-blue (ethinyl estradiol) tablet daily for 5 days.
For all subsequent cycles, the patient then begins a new 28-tablet regimen on the next day after taking the last light-blue tablet. [If switching directly from another oral contraceptive, the first white tablet should be taken on the first day of menstruation which begins after the last ACTIVE tablet of the previous product.] If a patient misses 1 white tablet, she should take the missed tablet as soon as she remembers. If the patient misses 2 consecutive whit… [Excerpted — this section continues on DailyMed.]
⛔ Contraindications ▾
CONTRAINDICATIONS Oral contraceptives should not be used in women who currently have the following conditions: Thrombophlebitis or thromboembolic disorders A past history of deep vein thrombophlebitis or thromboembolic disorders Cerebral vascular or coronary artery disease Current diagnosis of, or history of, breast cancer, which may be hormone-sensitive Undiagnosed abnormal genital bleeding Cholestatic jaundice of pregnancy or jaundice with prior pill use Hepatic adenomas or carcinomas Are receiving Hepatitis C drug combinations containing ombitasvir/paritaprevir/ritonavir, with or without dasabuvir, due to the potential for ALT elevations (see WARNINGS, Risk of Liver Enzyme Elevations with Concomitant Hepatitis C Treatment )
⚠️ Warnings ▾
WARNINGS The use of oral contraceptives is associated with increased risks of several serious conditions including myocardial infarction, thromboembolism, stroke, hepatic neoplasia, and gallbladder disease, although the risk of serious morbidity or mortality is very small in healthy women without underlying risk factors. The risk of morbidity and mortality increases significantly in the presence of other underlying risk factors such as hypertension, hyperlipidemias, obesity, and diabetes. Practitioners prescribing oral contraceptives should be familiar with the following information relating to these risks.
The information contained in this package insert is principally based on studies carried out in patients who used oral contraceptives with formulations of higher doses of estrogens and progestogens than those in common use today. The effect of long-term use of the oral contraceptives with formulations of lower doses of both estrogens and progestogens remains to be determined. Throughout this labeling, epidemiologic studies reported are of two types: retrospective or case control studies and prospective or cohort studies.
Case control studies provide a measure of the relative risk of a disease, namely, a ratio of the incidence of a disease among oral contraceptive users to that among non-users. The relative risk does not provide information on the actual clinical occurrence of a disease. Cohort studies provide a measure of attributable risk, which is the difference in the incidence of disease between oral contraceptive users and non-users.
The attributable risk does provide information about the actual occurrence of a disease in the population (Adapted from refs. 2 and 3 with the author’s permission). For further information, the reader is referred to a text on epidemiologic methods.
1. Thromboembolic disorders and other vascular problems a. Thromboembolism An increased risk of thromboembolic and thrombotic disease associated with the use of oral contraceptives is well established.
Case control studies have found the relative risk of users compared to non-users to be 3 for the first episode of superficial venous thromboembolic disease, 4 to 11 for deep vein thrombosis or pulmonary embolism, and 1.5 to 6 for women with predisposing conditions for venous thromboembolic disease (2, 3, 19 to 24). Cohort studies have shown the relative risk to be somewhat lower, about 3 for new cases and about 4.5 for new cases requiring hospitalization (25). The risk of thromboembolic disease associated with oral contraceptives is not related to length of use and disappears after pill use is stopped (2).
Several epidemiologic studies indicate that third generation oral contraceptives, including those containing desogestrel, are associated with a higher risk of venous thromboembolism than certain second generation oral contraceptives (102 to 104). In general, these studies indicate an approximate two-fold increased risk, which corresponds to an additional 1 to 2 cases of venous thromboembolism per 10,000 women-years of use. However, data from additional studies have not shown this two-fold increase in risk.
A two- to four-fold increase in relative risk of post-operative thromboembolic complications has been reported with the use of oral contraceptives (9, 26). The relative risk of venous thrombosis in women who have predisposing conditions is twice that of women without such medical conditions (9, 26). If feasible, oral contraceptives should be discontinued at least four weeks prior to and for two weeks after elective surgery of a type associated with an increase in risk of thromboembolism and during and following prolonged immobilization.
Since the immediate postpartum period is also associated with an increased risk of thromboembolism, oral contraceptives should be started no earlier than four weeks after delivery in women who elect not to breastfeed. b. Myocardial infarction An increased risk of myocardial infarction has been attributed to ora… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
ADVERSE REACTIONS An increased risk of the following serious adverse reactions has been associated with the use of oral contraceptives (see WARNINGS section): Thrombophlebitis and venous thrombosis with or without embolism Arterial thromboembolism Pulmonary embolism Myocardial infarction Cerebral hemorrhage Cerebral thrombosis Hypertension Gallbladder disease Hepatic adenomas or benign liver tumors Post Marketing Experience Five studies that compared breast cancer risk between ever-users (current or past use) of COCs and never-users of COCs reported no association between ever use of COCs and breast cancer risk, with effect estimates ranging from 0.90 to 1.12 (Figure 2) (64 to 68).
Three studies compared breast cancer risk between current or recent COC users (<6 months since last use) and never users of COCs (Figure 2) (64, 67, 69). One of these studies reported no association between breast cancer risk and COC use. The other two studies found an increased relative risk of 1.19 to 1.33 with current or recent use.
Both of these studies found an increased risk of breast cancer with current use of longer duration, with relative risks ranging from 1.03 with less than one year of COC use to approximately 1.4 with more than 8 to 10 years of COC use. FIGURE 2: RELEVANT STUDIES OF RISK OF BREAST CANCER WITH COMBINED ORAL CONTRACEPTIVES RR = relative risk; OR = odds ratio; HR = hazard ratio. “ever COC” are females with current or past COC use; “never COC use” are females that never used COCs. There is evidence of an association between the following conditions and the use of oral contraceptives: Mesenteric thrombosis Retinal thrombosis The following adverse reactions have been reported in patients receiving oral contraceptives and are believed to be drug-related: Nausea Vomiting Gastrointestinal symptoms (such as abdominal cramps and bloating) Breakthrough bleeding Spotting Change in menstrual flow Amenorrhea Temporary infertility after discontinuation of treatment Edema Melasma which may persist Breast changes: tenderness, enlargement, secretion Change in weight (increase or decrease) Change in cervical erosion and secretion Diminution in lactation when given immediately postpartum Cholestatic jaundice Migraine Rash (allergic) Mental depression Reduced tolerance to carbohydrates Vaginal candidiasis Change in corneal curvature (steepening) Intolerance to contact lenses The following adverse reactions have been reported in users of oral contraceptives and the association has been neither confirmed nor refuted: Pre-menstrual syndrome Cataracts Changes in appetite Cystitis-like syndrome Headache Nervousness Dizziness Hirsutism Loss of scalp hair Erythema multiforme Erythema nodosum Hemorrhagic eruption Vaginitis Porphyria Impaired renal function Hemolytic uremic syndrome Acne Changes in libido Colitis Budd-Chiari syndrome 1
🧒 Pediatric Use ▾
12. Pediatric use Safety and efficacy of Kariva ® tablets have been established in women of reproductive age. Safety and efficacy are expected to be the same for postpubertal adolescents under the age of 16 and for users 16 years and older. Use of this product before menarche is not indicated.
🆘 Overdosage ▾
OVERDOSAGE Serious ill effects have not been reported following acute ingestion of large doses of oral contraceptives by young children. Overdosage may cause nausea, and withdrawal bleeding may occur in females.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Combination oral contraceptives act by suppression of gonadotropins. Although the primary mechanism of this action is inhibition of ovulation, other alterations include changes in the cervical mucus (which increase the difficulty of sperm entry into the uterus) and the endometrium (which reduce the likelihood of implantation). Receptor binding studies, as well as studies in animals, have shown that etonogestrel, the biologically active metabolite of desogestrel, combines high progestational activity with minimal intrinsic androgenicity (91, 92).
The relevance of this latter finding in humans is unknown. Pharmacokinetics Absorption Desogestrel is rapidly and almost completely absorbed and converted into etonogestrel, its biologically active metabolite. Following oral administration, the relative bioavailability of desogestrel compared to a solution, as measured by serum levels of etonogestrel, is approximately 100%.
Kariva ® (desogestrel/ethinyl estradiol and ethinyl estradiol) Tablets provide two different regimens of ethinyl estradiol; 0.02 mg in the combination tablet [white] as well as 0.01 mg in the light-blue tablet. Ethinyl estradiol is rapidly and almost completely absorbed. After a single dose of Kariva ® combination tablet [white], the relative bioavailability of ethinyl estradiol is approximately 93% while the relative bioavailability of the 0.01 mg tablet [light-blue] is 99%.
The effect of food on the bioavailability of Kariva ® tablets following oral administration has not been evaluated. The pharmacokinetics of etonogestrel and ethinyl estradiol following multiple dose administration of Kariva ® tablets were determined during the third cycle in 17 subjects. Plasma concentrations of etonogestrel and ethinyl estradiol reached steady-state by Day 21.
The AUC (0–24) for etonogestrel at steady-state on Day 21 was approximately 2.2 times higher than AUC (0–24) on Day 1 of the third cycle. The pharmacokinetic parameters of etonogestrel and ethinyl estradiol during the third cycle following multiple dose administration of Kariva ® tablets are summarized in Table I. TABLE I: MEAN (SD) PHARMACOKINETIC PARAMETERS OF Kariva® OVER A 28-DAY DOSING PERIOD IN THE THIRD CYCLE (n=17).
Etonogestrel Day Dose a mg C max pg/mL T max h t 1/2 h AUC 0–24 pg/mL•hr CL/F L/h 1 0.15 2503.6 (987.6) 2.4 (1.0) 29.8 (16.3) 17,832 (5674) 5.4 (2.5) 21 0.15 4091.2 (1186.2) 1.6 (0.7) 27.8 (7.2) 39,391 (12,134) 4.4 (1.4) a) Desogestrel Ethinyl Estradiol Day Dose mg C max pg/mL T max h t 1/2 h AUC 0–24 pg/mL•hr CL/F L/h 1 0.02 51.9 (15.4) 2.9 (1.2) 16.5 (4.8) 566 (173) a 25.7 (9.1) 21 0.02 62.2 (25.9) 2.0 (0.8) 23.9 (25.5) 597 (127) a 35.1 (8.2) 24 0.01 24.6 (10.8) 2.4 (1.0) 18.8 (10.3) 246 (65) 43.6 (12.2) 28 0.01 35.3 (27.5) 2.1 (1.3) 18.9 (8.3) 312 (62) 33.2 (6.6) C max – measured peak concentration T max – observed time of peak concentration t 1/2 – elimination half-life, calculated by 0.693/K elim AUC 0–24 – area under the concentration-time curve calculated by the linear trapezoidal rule (Time 0 to 24 hours) CL/F – apparent clearance a) n=16 Distribution Etonogestrel, the active metabolite of desogestrel, was found to be 99% protein bound, primarily to sex hormone-binding globulin (SHBG).
Ethinyl estradiol is approximately 98.3% bound, mainly to plasma albumin. Ethinyl estradiol does not bind to SHBG, but induces SHBG synthesis. Desogestrel, in combination with ethinyl estradiol, does not counteract the estrogen-induced increase in SHBG, resulting in lower serum levels of free testosterone (96 to 99).
Metabolism Desogestrel: Desogestrel is rapidly and completely metabolized by hydroxylation in the intestinal mucosa and on first pass through the liver to etonogestrel. Other metabolites (i.e., 3α-OH-desogestrel, 3β-OH-desogestrel, and 3α-OH-5α-H-desogestrel) with no pharmacologic actions also have been identified and these metabolites may undergo glucuronide and sulfate conjugation. Ethinyl estradiol: Ethinyl estradiol is subj… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Kariva ® (desogestrel/ethinyl estradiol and ethinyl estradiol tablets USP) contains 21 round, white, film-coated, biconvex tablets, 2 round, light-green tablets and 5 round, light-blue, film-coated, biconvex tablets in a blister card. Each white tablet (debossed with “ dp ” on one side and “ 021 ” on the other side) contains 0.15 mg desogestrel and 0.02 mg ethinyl estradiol, USP. Each light-green tablet (debossed with “ dp ” on one side and “ 331 ” on the other side) contains inert ingredients.
Each light-blue tablet (debossed with “ dp ” on one side and “ 022 ” on the other side) contains 0.01 mg ethinyl estradiol, USP. Box of 6 Blister Cards (NDC: 0555-9050-58) Store at 20° to 25°C (68° to 77°F) [See USP Controlled Room Temperature]. Keep this and all medications out of the reach of children.
📋 Description ▾
DESCRIPTION Kariva ® (desogestrel/ethinyl estradiol and ethinyl estradiol tablets USP) provides an oral contraceptive regimen of 21 white, round tablets each containing 0.15 mg desogestrel (13-ethyl-11-methylene-18,19-dinor-17 alpha-pregn-4-en-20-yn-17-ol), 0.02 mg ethinyl estradiol, USP (19-nor-17 alpha-pregna-1,3,5 (10)-trien-20-yne-3,17-diol), and inactive ingredients which include colloidal silicon dioxide, hypromellose, lactose monohydrate, polyethylene glycol, povidone, pregelatinized corn starch, stearic acid, and vitamin E, followed by 2 inert light-green, round tablets with the following inactive ingredients: FD&C blue no.
1 aluminum lake, FD&C yellow no. 6 aluminum lake, D&C yellow no. 10 aluminum lake, lactose monohydrate, magnesium stearate, microcrystalline cellulose and pregelatinized corn starch.
Kariva ® also contains 5 light-blue, round tablets containing 0.01 mg ethinyl estradiol, USP (19-nor-17 alpha-pregna-1,3,5 (10)-trien-20-yne-3,17-diol) and inactive ingredients which include colloidal silicon dioxide, FD&C blue no. 1 aluminum lake, FD&C blue no. 2 aluminum lake, hypromellose, lactose monohydrate, polydextrose, polyethylene glycol, povidone, pregelatinized corn starch, stearic acid, titanium dioxide, triacetin and vitamin E.
The structural formulas are as follows: DESOGESTREL C 22 H 30 O M.W. 310.48 ETHINYL ESTRADIOL, USP C 20 H 24 O 2 M.W. 296.40 The 21 white tablets meet USP Dissolution Test 2.
1 Ethinyl Estradiol, USP
⚠️ Precautions ▾
PRECAUTIONS 1. General Patients should be counseled that this product does not protect against HIV infection (AIDS) and other sexually transmitted infections. 2.
Physical examination and follow up It is good medical practice for all women to have annual history and physical examinations, including women using oral contraceptives. The physical examination, however, may be deferred until after initiation of oral contraceptives if requested by the woman and judged appropriate by the clinician. The physical examination should include special reference to blood pressure, breasts, abdomen, and pelvic organs, including cervical cytology, and relevant laboratory tests.
In case of undiagnosed, persistent or recurrent abnormal vaginal bleeding, appropriate measures should be conducted to rule out malignancy. Women with a strong family history of breast cancer or who have breast nodules should be monitored with particular care. 3.
Lipid disorders Women who are being treated for hyperlipidemias should be followed closely if they elect to use oral contraceptives. Some progestogens may elevate LDL levels and may render the control of hyperlipidemias more difficult. 4.
Liver function If jaundice develops in any woman receiving such drugs, the medication should be discontinued. Steroid hormones may be poorly metabolized in patients with impaired liver function. 5.
Fluid retention Oral contraceptives may cause some degree of fluid retention. They should be prescribed with caution, and only with careful monitoring, in patients with conditions which might be aggravated by fluid retention. 6.
Contact lenses Contact lens wearers who develop visual changes or changes in lens tolerance should be assessed by an ophthalmologist. 7. Drug interactions Reduced efficacy and increased incidence of breakthrough bleeding and menstrual irregularities have been associated with concomitant use of rifampin.
A similar association, though less marked, has been suggested with barbiturates, phenylbutazone, phenytoin sodium, carbamazepine and possibly with griseofulvin, ampicillin, and tetracyclines (72). Combined hormonal contraceptives have been shown to significantly decrease plasma concentrations of lamotrigine when co-administered, likely due to induction of lamotrigine glucuronidation. This may reduce seizure control; therefore, dosage adjustments of lamotrigine may be necessary.
Concomitant Use with Hepatitis C Virus (HCV) Combination Therapy – Liver Enzyme Elevation Co-administration of Kariva ® with HCV drug combinations containing ombitasvir/paritaprevir/ritonavir, with or without dasabuvir is contraindicated due to potential for ALT elevations (see CONTRAINDICATIONS and WARNINGS, Risk of Liver Enzyme Elevations with Concomitant Hepatitis C Treatment ). Co-administration of Kariva ® and glecaprevir/pibrentasvir is not recommended due to potential for ALT elevations. Consult the labeling of the concurrently-used drug to obtain further information about interactions with hormonal contraceptives or the potential for enzyme alterations.
8. Interactions with laboratory tests Certain endocrine and liver function tests and blood components may be affected by oral contraceptives: Increased prothrombin and factors VII, VIII, IX and X; decreased antithrombin 3; increased norepinephrine-induced platelet aggregability. Increased thyroid binding globulin (TBG) leading to increased circulating total thyroid hormone, as measured by protein-bound iodine (PBI), T4 by column or by radioimmunoassay.
Free T3 resin uptake is decreased, reflecting the elevated TBG; free T4 concentration is unaltered. Other binding proteins may be elevated in serum. Sex hormone-binding globulins are increased and result in elevated levels of total circulating sex steroids; however, free or biologically active levels either decrease or remain unchanged.
High-density lipoprotein cholesterol (HDL-C) and triglycerides may be increased, while low-density lipoprotein cholesterol (LDL-C) and total chole… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
11. Lactation Small amounts of oral contraceptive steroids have been identified in human milk, and a few adverse effects on the child have been reported, including jaundice and breast enlargement. In addition, oral contraceptives given in the postpartum period may interfere with lactation by decreasing the quantity and quality of breast milk.
If possible, the nursing mother should be advised not to use oral contraceptives but to use other forms of contraception until she has completely weaned her child.
🧬 Pharmacokinetics ▾
Pharmacokinetics Absorption Desogestrel is rapidly and almost completely absorbed and converted into etonogestrel, its biologically active metabolite. Following oral administration, the relative bioavailability of desogestrel compared to a solution, as measured by serum levels of etonogestrel, is approximately 100%. Kariva ® (desogestrel/ethinyl estradiol and ethinyl estradiol) Tablets provide two different regimens of ethinyl estradiol; 0.02 mg in the combination tablet [white] as well as 0.01 mg in the light-blue tablet.
Ethinyl estradiol is rapidly and almost completely absorbed. After a single dose of Kariva ® combination tablet [white], the relative bioavailability of ethinyl estradiol is approximately 93% while the relative bioavailability of the 0.01 mg tablet [light-blue] is 99%. The effect of food on the bioavailability of Kariva ® tablets following oral administration has not been evaluated.
The pharmacokinetics of etonogestrel and ethinyl estradiol following multiple dose administration of Kariva ® tablets were determined during the third cycle in 17 subjects. Plasma concentrations of etonogestrel and ethinyl estradiol reached steady-state by Day 21. The AUC (0–24) for etonogestrel at steady-state on Day 21 was approximately 2.2 times higher than AUC (0–24) on Day 1 of the third cycle.
The pharmacokinetic parameters of etonogestrel and ethinyl estradiol during the third cycle following multiple dose administration of Kariva ® tablets are summarized in Table I. TABLE I: MEAN (SD) PHARMACOKINETIC PARAMETERS OF Kariva® OVER A 28-DAY DOSING PERIOD IN THE THIRD CYCLE (n=17). Etonogestrel Day Dose a mg C max pg/mL T max h t 1/2 h AUC 0–24 pg/mL•hr CL/F L/h 1 0.15 2503.6 (987.6) 2.4 (1.0) 29.8 (16.3) 17,832 (5674) 5.4 (2.5) 21 0.15 4091.2 (1186.2) 1.6 (0.7) 27.8 (7.2) 39,391 (12,134) 4.4 (1.4) a) Desogestrel Ethinyl Estradiol Day Dose mg C max pg/mL T max h t 1/2 h AUC 0–24 pg/mL•hr CL/F L/h 1 0.02 51.9 (15.4) 2.9 (1.2) 16.5 (4.8) 566 (173) a 25.7 (9.1) 21 0.02 62.2 (25.9) 2.0 (0.8) 23.9 (25.5) 597 (127) a 35.1 (8.2) 24 0.01 24.6 (10.8) 2.4 (1.0) 18.8 (10.3) 246 (65) 43.6 (12.2) 28 0.01 35.3 (27.5) 2.1 (1.3) 18.9 (8.3) 312 (62) 33.2 (6.6) C max – measured peak concentration T max – observed time of peak concentration t 1/2 – elimination half-life, calculated by 0.693/K elim AUC 0–24 – area under the concentration-time curve calculated by the linear trapezoidal rule (Time 0 to 24 hours) CL/F – apparent clearance a) n=16 Distribution Etonogestrel, the active metabolite of desogestrel, was found to be 99% protein bound, primarily to sex hormone-binding globulin (SHBG).
Ethinyl estradiol is approximately 98.3% bound, mainly to plasma albumin. Ethinyl estradiol does not bind to SHBG, but induces SHBG synthesis. Desogestrel, in combination with ethinyl estradiol, does not counteract the estrogen-induced increase in SHBG, resulting in lower serum levels of free testosterone (96 to 99).
Metabolism Desogestrel: Desogestrel is rapidly and completely metabolized by hydroxylation in the intestinal mucosa and on first pass through the liver to etonogestrel. Other metabolites (i.e., 3α-OH-desogestrel, 3β-OH-desogestrel, and 3α-OH-5α-H-desogestrel) with no pharmacologic actions also have been identified and these metabolites may undergo glucuronide and sulfate conjugation. Ethinyl estradiol: Ethinyl estradiol is subject to a significant degree of presystemic conjugation (phase II metabolism).
Ethinyl estradiol escaping gut wall conjugation undergoes phase I metabolism and hepatic conjugation (phase II metabolism). Major phase I metabolites are 2-OH-ethinyl estradiol and 2-methoxy-ethinyl estradiol. Sulfate and glucuronide conjugates of both ethinyl estradiol and phase I metabolites, which are excreted in bile, can undergo enterohepatic circulation.
Excretion Etonogestrel and ethinyl estradiol are excreted in urine, bile, and feces. At steady state, on Day 21, the elimination half-life of etonogestrel is 27.8 ± 7.2 hours and the eliminati… [Excerpted — this section continues on DailyMed.]
📚 References ▾
REFERENCES 1. Hatcher RA, Trussell J, Stewart F et al. Contraceptive Technology: Seventeenth Revised Edition, New York: Irvington Publishers, 1998, in press.
2. Stadel BV. Oral contraceptives and cardiovascular disease.
(Pt. 1). N Engl J Med 1981; 305:612–618.
3. Stadel BV. Oral contraceptives and cardiovascular disease.
(Pt. 2). N Engl J Med 1981; 305:672–677.
4. Adam SA, Thorogood M. Oral contraception and myocardial infarction revisited: the effects of new preparations and prescribing patterns.
Br J Obstet and Gynecol 1981; 88:838–845. 5. Mann JI, Inman WH.
Oral contraceptives and death from myocardial infarction. Br Med J 1975; 2(5965):245–248. 6.
Mann JI, Vessey MP, Thorogood M, Doll R. Myocardial infarction in young women with special reference to oral contraceptive practice. Br Med J 1975; 2(5956):241–245.
7. Royal College of General Practitioners’ Oral Contraception Study: Further analyses of mortality in oral contraceptive users. Lancet 1981; 1:541–546.
8. Slone D, Shapiro S, Kaufman DW, Rosenberg L, Miettinen OS, Stolley PD. Risk of myocardial infarction in relation to current and discontinued use of oral contraceptives.
N Engl J Med 1981; 305:420–424. 9. Vessey MP.
Female hormones and vascular disease—an epidemiological overview. Br J Fam Plann 1980; 6:1–12. 10.
Russell-Briefel RG, Ezzati TM, Fulwood R, Perlman JA, Murphy RS. Cardiovascular risk status and oral contraceptive use, United States, 1976–80. Prevent Med 1986; 15:352–362.
11. Goldbaum GM, Kendrick JS, Hogelin GC, Gentry EM. The relative impact of smoking and oral contraceptive use on women in the United States.
JAMA 1987; 258:1339–1342. 12. Layde PM, Beral V.
Further analyses of mortality in oral contraceptive users: Royal College General Practitioners’ Oral Contraception Study. (Table 5) Lancet 1981; 1:541–546. 13.
Knopp RH. Arteriosclerosis risk: the roles of oral contraceptives and postmenopausal estrogens. J Reprod Med 1986; 31(9) (Supplement):913–921.
14. Krauss RM, Roy S, Mishell DR, Casagrande J, Pike MC. Effects of two low-dose oral contraceptives on serum lipids and lipoproteins: Differential changes in high-density lipoproteins subclasses.
Am J Obstet 1983; 145:446–452. 15. Wahl P, Walden C, Knopp R, Hoover J, Wallace R, Heiss G, Rifkind B.
Effect of estrogen/progestin potency on lipid/lipoprotein cholesterol. N Engl J Med 1983; 308:862–867. 16.
Wynn V, Niththyananthan R. The effect of progestin in combined oral contraceptives on serum lipids with special reference to high-density lipoproteins. Am J Obstet Gynecol 1982; 142:766–771.
17. Wynn V, Godsland I. Effects of oral contraceptives and carbohydrate metabolism.
J Reprod Med 1986; 31 (9) (Supplement):892–897. 18. LaRosa JC.
Atherosclerotic risk factors in cardiovascular disease. J Reprod Med 1986; 31 (9) (Supplement):906–912. 19.
Inman WH, Vessey MP. Investigation of death from pulmonary, coronary, and cerebral thrombosis and embolism in women of child-bearing age. Br Med J 1968; 2 (5599):193–199.
20. Maguire MG, Tonascia J, Sartwell PE, Stolley PD, Tockman MS. Increased risk of thrombosis due to oral contraceptives: a further report.
Am J Epidemiol 1979; 110 (2):188–195. 21. Pettiti DB, Wingerd J, Pellegrin F, Ramacharan S.
Risk of vascular disease in women: smoking, oral contraceptives, noncontraceptive estrogens, and other factors. JAMA 1979; 242:1150–1154. 22.
Vessey MP, Doll R. Investigation of relation between use of oral contraceptives and thromboembolic disease. Br Med J 1968; 2 (5599):199–205.
23. Vessey MP, Doll R. Investigation of relation between use of oral contraceptives and thromboembolic disease.
A further report. Br Med J 1969; 2 (5658):651–657. 24.
Porter JB, Hunter JR, Danielson DA, Jick H, Stergachis A. Oral contraceptives and non-fatal vascular disease—recent experience. Obstet Gynecol 1982; 59 (3):299–302.
25. Vessey M, Doll R, Peto R, Johnson B, Wiggins P. A long-term follow-up study of women using different methods of contraception: an interim report.
Biosocial Sci 197… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
Package/Label Display Panel, PART 1 OF 2 NDC 0555-9050-58 28 Day Regimen 6 Cyclic Tablet Dispensers x 28 Tablets Kariva® (desogestrel/ethinyl estradiol and ethinyl estradiol tablets USP) 0.15 mg/0.02 mg and 0.01 mg Each white tablet contains 0.15 mg desogestrel and 0.02 mg ethinyl estradiol, USP. Each light-green tablet contains inert ingredients and each light-blue tablet contains 0.01 mg ethinyl estradiol, USP. Rx only 1
Package/Label Display Panel, PART 2 OF 2 2
Medicaid utilization & spend
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | ✓ Available |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |