
Dextroamphetamine Sulfate 5 mg Tablet, 100-count — NDC 10702-065-01 (Billing 10702-0065-01)
This is a package of 100 tablets of Dextroamphetamine Sulfate 5 mg Tablet from KVK-Tech, Inc., marketed since Nov 2015 and currently FDA-listed; retail pharmacies pay about $0.3836 per tablet (NADAC). It is the main listing for this product, which comes in 3 package sizes.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 005011
- GCN: 19881
- GPI-14 (Medi-Span): 61100020100305
- HICL (First Databank): 002065
- AHFS class code: 28:20.04.00
- RxCUI (RxNorm): 884385
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Central Nervous System Stimulant class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Dextroamphetamine is used to control symptoms of attention deficit hyperactivity disorder (ADHD; more difficulty focusing, controlling actions, and remaining still or quiet than other people who are the same age) and to treat narcolepsy (a sleep disorder that causes excessive daytime sleepiness and sudden attacks of sleep). Dextroamphetamine is in a class of medications called central nervous system stimulants. It works by changing the amounts of certain natural substances in the brain.
Read the full MedlinePlus article ↗- It treats ADHD, and some oral forms are also used for narcolepsy. Which use and age range applies depends on the product you have. Your prescriber decides if it fits you or your ch...
- Take it exactly as prescribed, usually at the lowest dose that works. Avoid late-evening doses because they can keep you awake. If you use the Xelstrym patch, put it on about 2 hou...
- Common ones are reduced appetite, trouble sleeping, headache, stomach upset and irritability. Kids may lose weight, so we watch growth. Call your doctor for chest pain, a racing he...
- Check with me first. MAO inhibitors are a serious problem, and antidepressants, triptans, tramadol and St. John’s Wort can raise the risk of serotonin syndrome. Vitamin C and fruit...
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.384 | $38.36 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.7336 | $73.36 / 100 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.8511 | $85.11 / 100 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 10702-0065-01 You're viewing this Main listing | 100 TABLET in 1 BOTTLE | $0.3836 / ea | $38.36 | 2015-11-23 | — | Active |
| 10702-0065-03 10702-065-03 | 30 TABLET in 1 BOTTLE | — | — | 2015-11-23 | — | Active |
| 10702-0065-06 10702-065-06 | 60 TABLET in 1 BOTTLE | — | — | 2015-11-23 | — | Active |
You're viewing the largest of 3 pack sizes for this product.
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 10702-0065-03?
What NDC number is used to bill for this package of Dextroamphetamine Sulfate 5 mg Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Dextroamphetamine Sulfate 5 mg 00406-8958-01 | SpecGx | 100 tablets | $0.384 | AA | Availability likely | — |
| Dextroamphetamine Sulfate 5 mg 00555-0952-02 | Teva | 100 tablets | $0.384 | AA | Availability likely | — |
| Dextroamphetamine Sulfate 5 mgthis 10702-0065-01 | KVK-Tech, | 100 tablets | $0.384 | AA | Availability likely | — |
| Dextroamphetamine Sulfate 5 mg 11534-0188-01 | SUNRISE | 100 tablets | $0.384 | AA | Availability likely | — |
| Dextroamphetamine Sulfate 5 mg 13107-0035-01 | Aurolife | 100 tablets | $0.384 | AA | Availability likely | — |
| Dextroamphetamine Sulfate 5 mg 52536-0500-01 | Wilshire | 100 tablets | $0.384 | AA | Availability likely | — |
| Dextroamphetamine Sulfate 5 mg 43386-0870-01 | Lupin | 100 tablets | $0.409 | AA | FDA listed | +7% |
| Zenzedi 5 mg 24338-0851-03 | Azurity | 30 tablets | — | AA | FDA listed | — |
| Dextroamphetamine Sulfate 5 mg 27808-0089-01 | Cranbury | 100 tablets | — | — | FDA listed | — |
| Dextroamphetamine Sulfate 5 mg 63629-2375-01 | Bryant | 100 tablets | — | AA | FDA listed | — |
| Dextroamphetamine Sulfate 5 mg 72162-1233-01 | Bryant | 100 tablets | — | AA | FDA listed | — |
| Dextroamphetamine Sulfate 5 mg 72162-2349-03 | Bryant | 30 tablets | — | AA | FDA listed | — |
| Dextroamphetamine Sulfate 5 mg 75826-0121-10 | Winder | 100 tablets | — | AA | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 35SW5USQ3G
A synthetic yellow dye used to color medicines. It helps make tablets, capsules, and liquids visually distinct so patients can easily identify their medication.
-
UNII WZB9127XOA
A synthetic red dye used to color medications and make them easier to identify. It serves as a colorant in tablets, capsules, and liquid formulations.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Dextroamphetamine Sulfate Tablets USP are indicated for: 1. Narcolepsy. 2.
Attention Deficit Disorder with Hyperactivity , as an integral part of a total treatment program which typically includes other remedial measures (psychological, educational, social) for a stabilizing effect in pediatric patients (ages 3 to 16 years) with a behavioral syndrome characterized by the following group of developmentally inappropriate symptoms: moderate to severe distractibility, short attention span, hyperactivity, emotional lability, and impulsivity. The diagnosis of this syndrome should not be made with finality when these symptoms are only of comparatively recent origin.
Nonlocalizing (soft) neurological signs, learning disability, and abnormal EEG may or may not be present, and a diagnosis of central nervous system dysfunction may or may not be warranted.
⏱️ Dosage and Administration ▾
DOSAGE & ADMINISTRATION Amphetamines should be administered at the lowest effective dosage and dosage should be individually adjusted. Late evening doses should be avoided because of the resulting insomnia. Narcolepsy Usual dose is 5 to 60 mg per day in divided doses, depending on the individual patient response.
Narcolepsy seldom occurs in children under 12 years of age; however, when it does, dextroamphetamine sulfate may be used. The suggested initial dose for patients aged 6 to 12 is 5 mg daily; daily dose may be raised in increments of 5 mg at weekly intervals until an optimal response is obtained. In patients 12 years of age and older, start with 10 mg daily; daily dosage may be raised in increments of 10 mg at weekly intervals until optimal response is obtained.
If bothersome adverse reactions appear (e.g., insomnia or anorexia), dosage should be reduced. Give first dose on awakening; additional doses (1 or 2) at intervals of 4 to 6 hours. Attention Deficit Disorder with Hyperactivity Not recommended for pediatric patients under 3 years of age.
In pediatric patients from 3 to 5 years of age, start with 2.5 mg daily; daily dosage may be raised in increments of 2.5 mg at weekly intervals until optimal response is obtained. In pediatric patients 6 years of age and older, start with 5 mg once or twice daily; daily dosage may be raised in increments of 5 mg at weekly intervals until optimal response is obtained. Only in rare cases will it be necessary to exceed a total of 40 mg per day.
Give first dose on awakening; additional doses (1 or 2) at intervals of 4 to 6 hours. Where possible, drug administration should be interrupted occasionally to determine if there is a recurrence of behavioral symptoms sufficient to require continued therapy. Prior to treating patients with dextroamphetamine sulfate tablets assess: • for the presence of cardiac disease (i.e., perform a careful history, family history of sudden death or ventricular arrhythmia, and physical exam) (see WARNINGS ). • the family history and clinically evaluate patients for motor or verbal tics or Tourette’s syndrome (see WARNINGS )
⛔ Contraindications ▾
CONTRAINDICATIONS Known hypersensitivity to amphetamine products. During or within 14 days following the administration of monoamine oxidase inhibitors (hypertensive crises may result).
⚠️ Warnings ▾
WARNING Dextroamphetamine sulfate has a high potential for abuse and misuse, which can lead to the development of a substance use disorder, including addiction. Misuse and abuse of CNS stimulants, including dextroamphetamine sulfate, can result in overdose and death (see OVERDOSAGE), and this risk is increased with higher doses or unapproved methods of administration, such as snorting or injection. Before prescribing dextroamphetamine sulfate, assess each patient’s risk for abuse, misuse, and addiction.
Educate patients and their families about these risks, proper storage of the drug, and proper disposal of any unused drug. Throughout dextroamphetamine sulfate treatment, reassess each patient’s risk of abuse, misuse, and addiction and frequently monitor for signs and symptoms of abuse, misuse, and addiction (see WARNINGS and DRUG ABUSE and DEPENDENCE).
WARNINGS Abuse, Misuse, and Addiction Dextroamphetamine sulfate has a high potential for abuse and misuse. The use of dextroamphetamine sulfate exposes individuals to the risks of abuse and misuse, which can lead to the development of a substance use disorder, including addiction. Amphetamine sulfate can be diverted for non-medical use into illicit channels or distribution (see DRUG ABUSE and DEPENDENCE ).
Misuse and abuse of CNS stimulants, including dextroamphetamine sulfate, can result in overdose and death (see OVERDOSAGE ), and this risk is increased with higher doses or unapproved methods of administration, such as snorting or injection. Before prescribing dextroamphetamine sulfate, assess each patient’s risk for abuse, misuse, and addiction. Educate patients and their families about these risks and proper disposal of any unused drug.
Advise patients to store amphetamine sulfate in a safe place, preferably locked, and instruct patients to not give dextroamphetamine sulfate to anyone else. Throughout dextroamphetamine sulfate treatment, reassess each patient’s risk of abuse, misuse, and addiction and frequently monitor for signs and symptoms of abuse, misuse, and addiction. Risks to Patients with Serious Cardiac Disease Sudden death has been reported in patients with structural cardiac abnormalities or other serious cardiac disease who are treated with CNS stimulants at the recommended ADHD dosages.
Avoid dextroamphetamine sulfate use in patients with known structural cardiac abnormalities, cardiomyopathy, serious cardiac arrhythmia, coronary artery disease, or other serious cardiac disease. Increased Blood Pressure and Heart Rate CNS stimulants cause an increase in blood pressure (mean increase about 2 to 4 mm Hg) and heart rate (mean increase about 3 to 6 bpm). Monitor all patients for potential tachycardia and hypertension.
Psychiatric Adverse Reactions Exacerbation of Pre-Existing Psychosis CNS stimulants may exacerbate symptoms of behavior disturbance and thought disorder in patients with a pre-existing psychotic disorder. Induction of a Manic Episode in Patients with Bipolar Disorder CNS stimulants may induce a manic or mixed episode in patients. Prior to initiating treatment, screen patients for risk factors for developing a manic episode (e.g., comorbid or history of depressive symptoms or a family history of suicide, bipolar disorder, or depression).
New Psychotic or Manic Symptoms CNS stimulants, at recommended doses, may cause psychotic or manic symptoms (e.g., hallucinations, delusional thinking, or mania) in patients without a prior history of psychotic illness or mania. In a pooled analysis of multiple short-term, placebo- controlled studies of CNS stimulants, psychotic or manic symptoms occurred in approximately 0.1% of CNS stimulant-treated patients, compared with 0% of placebo-treated patients. If such symptoms occur, consideration discontinuing dextroamphetamine sulfate.
Long-Term Suppression of Growth in Pediatric Patients CNS stimulants have been associated with weight loss and slowing of growth rate in pediatric patients, including dextroamphetamine su… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Cardiovascular Palpitations, tachycardia, elevation of blood pressure. There have been isolated reports of cardiomyopathy associated with chronic amphetamine use. Central Nervous System Psychotic episodes at recommended doses (rare), overstimulation, restlessness, dizziness, insomnia, euphoria, dyskinesia, dysphoria, tremor, headache, exacerbation of motor and verbal tics and Tourette's syndrome.
Gastrointestinal Dryness of the mouth, unpleasant taste, diarrhea, constipation, intestinal ischemia and other gastrointestinal disturbances. Anorexia and weight loss may occur as undesirable effects. Allergic Urticaria.
Endocrine Impotence, changes in libido, frequent or prolonged erections. Musculoskeletal Rhabdomyolysis
🔄 Drug Interactions ▾
Drug Interactions MAO Inhibitors MAOI antidepressants, as well as a metabolite of furazolidone, slow amphetamine metabolism. This slowing potentiates amphetamines, increasing their effect on the release of norepinephrine and other monoamines from adrenergic nerve endings; this can cause headaches and other signs of hypertensive crisis. A variety of neurological toxic effects and malignant hyperpyrexia can occur, sometimes with fatal results.
Serotonergic Drugs The concomitant use of dextroamphetamine sulfate tablets and serotonergic drugs increases the risk of serotonin syndrome. Initiate with lower doses and monitor patients for signs and symptoms of serotonin syndrome, particularly during dextroamphetamine sulfate tablets initiation or dosage increase. If serotonin syndrome occurs, discontinue dextroamphetamine sulfate tablets and the concomitant serotonergic drug(s) (see WARNINGS and PRECAUTIONS ).
Examples of serotonergic drugs include selective serotonin reuptake inhibitors (SSRI), serotonin norepinephrine reuptake inhibitors (SNRI), triptans, tricyclic antidepressants, fentanyl, lithium, tramadol, tryptophan, buspirone, St. John’s Wort. CYP2D6 Inhibitors The concomitant use of dextroamphetamine sulfate tablets and CYP2D6 inhibitors may increase the exposure of dextroamphetamine sulfate tablets compared to the use of the drug alone and increase the risk of serotonin syndrome.
Initiate with lower doses and monitor patients for signs and symptoms of serotonin syndrome particularly during dextroamphetamine sulfate tablets initiation and after a dosage increase. If serotonin syndrome occurs, discontinue dextroamphetamine sulfate tablets and the CYP2D6 inhibitor (see WARNINGS, OVERDOSAGE ). Acidifying Agents Gastrointestinal acidifying agents (guanethidine, reserpine, glutamic acid HCl, ascorbic acid, fruit juices, etc.) lower absorption of amphetamines.
Urinary acidifying agents (ammonium chloride, sodium acid phosphate, etc.) increase the concentration of the ionized species of the amphetamine molecule, thereby increasing urinary excretion. Both groups of agents lower blood levels and efficacy of amphetamines. Adrenergic Blockers Adrenergic blockers are inhibited by amphetamines.
Alkalinizing Agents Gastrointestinal alkalinizing agents (sodium bicarbonate, etc.) increase absorption of amphetamines. Urinary alkalinizing agents (acetazolamide, some thiazides) increase the concentration of the non-ionized species of the amphetamine molecule, thereby decreasing urinary excretion. Both groups of agents increase blood levels and therefore potentiate the actions of amphetamines.
Antidepressants, Tricyclic Amphetamines may enhance the activity of tricyclic or sympathomimetic agents; d -amphetamine with desipramine or protriptyline and possibly other tricyclics cause striking and sustained increases in the concentration of d -amphetamine in the brain; cardiovascular effects can be potentiated. Antihistamines Amphetamines may counteract the sedative effect of antihistamines. Antihypertensives Amphetamines may antagonize the hypotensive effects of antihypertensives.
Chlorpromazine Chlorpromazine blocks dopamine and norepinephrine reuptake, thus inhibiting the central stimulant effects of amphetamines, and can be used to treat amphetamine poisoning. Ethosuximide Amphetamines may delay intestinal absorption of ethosuximide. Haloperidol Haloperidol blocks dopamine and norepinephrine reuptake, thus inhibiting the central stimulant effects of amphetamines.
Lithium Carbonate The stimulatory effects of amphetamines may be inhibited by lithium carbonate. Meperidine Amphetamines potentiate the analgesic effect of meperidine. Methenamine Therapy Urinary excretion of amphetamines is increased, and efficacy is reduced, by acidifying agents used in methenamine therapy.
Norepinephrine Amphetamines enhance the adrenergic effect of norepinephrine. Phenobarbital Amphetamines may delay intestinal absorption of phenobarbital; co-administration of phenoba… [Excerpted — this section continues on DailyMed.]
🆘 Overdosage ▾
OVERDOSAGE Clinical Effects of Overdose Overdose of CNS stimulants is characterized by the following sympathomimetic effects: • Cardiovascular effects including tachyarrhythmias, and hypertension or hypotension. Vasospasm, myocardial infarction, or aortic dissection may precipitate sudden cardiac death. Takotsubo cardiomyopathy may develop. • CNS effects including psychomotor agitation, confusion, and hallucinations.
Serotonin syndrome, seizures, cerebral vascular accidents, and coma may occur. • Life-threatening hyperthermia (temperatures greater than 104°F) and rhabdomyolysis may develop. Overdose Management Consider the possibility of multiple drug ingestion. D-amphetamine is not dialyzable.
Consider contacting the Poison Help line (1-800-222-1222) or a medical toxicologist for additional overdose management recommendations.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Amphetamines are non-catecholamine, sympathomimetic amines with CNS stimulant activity. Peripheral actions include elevations of systolic and diastolic blood pressures and weak bronchodilator and respiratory stimulant action. There is neither specific evidence which clearly establishes the mechanism whereby amphetamines produce mental and behavioral effects in children, nor conclusive evidence regarding how these effects relate to the condition of the central nervous system.
Pharmacokinetics The pharmacokinetics of the tablet and sustained-release capsule were compared in 12 healthy subjects. The extent of bioavailability of the sustained-release capsule was similar compared to the immediate-release tablet. Following administration of three 5 mg tablets, average maximal dextroamphetamine plasma concentrations (C max ) of 36.6 ng/mL were achieved at approximately 3 hours.
Following administration of one 15 mg sustained-release capsule, maximal dextroamphetamine plasma concentrations were obtained approximately 8 hours after dosing. The average C max was 23.5 ng/mL. The average plasma T 1/2 was similar for both the tablet and sustained-release capsule and was approximately 12 hours.
In 12 healthy subjects, the rate and extent of dextroamphetamine absorption were similar following administration of the sustained-release capsule formulation in the fed (58 to 75 gm fat) and fasted state.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Dextroamphetamine Sulfate Tablets USP are available as: 5 mg: Peach, round, flat face, beveled edge tablets, debossed "K" above bisect “65” on one side and plain on the other side, packaged as follows: NDC #: 10702-065-03 Bottle of 30 tablets NDC #: 10702-065-06 Bottle of 60 tablets NDC #: 10702-065-01 Bottle of 100 tablets 10 mg: Pink, round, flat face, beveled edge tablets, debossed "K" above bisect “66” on one side and plain on the other side, packaged as follows: NDC #: 10702-066-03 Bottle of 30 tablets NDC #: 10702-066-06 Bottle of 60 tablets NDC #: 10702-066-01 Bottle of 100 tablets Store at 20° to 25°C (68° to 77°F) [See USP Controlled Room Temperature].
Dispense in a tight, light-resistant container as defined in the USP, with a child-resistant closure (as required). KEEP THIS AND ALL MEDICATIONS OUT OF THE REACH OF CHILDREN. DEA Order Form Required.
Manufactured by: KVK-TECH, INC. 110 Terry Dr. Newtown, PA 18940-1850 Manufacturer's code: 10702 Item ID #: 6109/11 01/2024 Company logo
📋 Description ▾
DESCRIPTION Dextroamphetamine sulfate, USP is the dextro isomer of the compound d , l -amphetamine sulfate, a sympathomimetic amine of the amphetamine group. Chemically, dextroamphetamine is d -alpha-methylphenethylamine, and is present in all forms of dextroamphetamine sulfate, USP as the neutral sulfate. The structural formula is as follows: Inactive Ingredients Magnesium stearate, microcrystalline cellulose, and silicon dioxide.
The 5 mg tablet also contains D&C yellow no. 10 aluminum lake and FD&C red no. 40 aluminum lake.
The 10 mg tablet also contains FD&C red no. 40 aluminum lake and FD&C yellow no. 6 aluminum lake.
Chemical Structure
💬 Information for Patients ▾
Information for Patients Advise the patient to read the FDA-approved patient labeling (Medication Guide). Abuse, Misuse, and Addiction Educate patients and their families about the risks of abuse, misuse, and addiction of dextroamphetamine sulfate, which can lead to overdose and death, and proper disposal of any unused drug (see WARNINGS, DRUG ABUSE AND DEPENDENCE , and OVERDOSAGE ). Advise patients to store dextroamphetamine sulfate in a safe place, preferably locked, and instruct patients to not give dextroamphetamine sulfate to anyone else.
Risks to Patients with Serious Cardiac Disease Advise patients that there are potential risks to patients with serious cardiac disease, including sudden death, with dextroamphetamine sulfate use. Instruct patients to contact a healthcare provider immediately if they develop symptoms such as exertional chest pain, unexplained syncope, or other symptoms suggestive of cardiac disease (see WARNINGS ). Increased Blood Pressure and Heart Rate Advise patients that dextroamphetamine sulfate can elevate blood pressure and heart rate (see WARNINGS ).
Psychiatric Adverse Reactions Advise patients that dextroamphetamine sulfate, at recommended doses, can cause psychotic or manic symptoms, even in patients without prior history of psychotic symptoms or mania (see WARNINGS ). Long-Term Suppression of Growth in Pediatric Patients Advise patients that dextroamphetamine sulfate, may cause slowing of growth including weight loss (see WARNINGS ). Circulation problems in fingers and toes [Peripheral vasculopathy, including Raynaud’s phenomenon] Instruct patients beginning treatment with dextroamphetamine sulfate tablets about the risk of peripheral vasculopathy, including Raynaud’s Phenomenon, and associated signs and symptoms: fingers or toes may feel numb, cool, painful, and/or may change color from pale, to blue, to red.
Instruct patients to report to their physician any new numbness, pain, skin color change, or sensitivity to temperature in fingers or toes. Instruct patients to call their physician immediately with any signs of unexplained wounds appearing on fingers or toes while taking dextroamphetamine sulfate tablets. Further clinical evaluation (e.g., rheumatology referral) may be appropriate for certain patients.
Serotonin Syndrome Caution patients about the risk of serotonin syndrome with concomitant use of dextroamphetamine sulfate and other serotonergic drugs including SSRIs, SNRIs, triptans, tricyclic antidepressants, fentanyl, lithium, tramadol, tryptophan, buspirone, St. John's Wort, and with drugs that impair metabolism of serotonin (in particular MAOIs, both those intended to treat psychiatric disorders and also others such as linezolid [see CONTRAINDICATIONS, WARNINGS and DRUG INTERACTIONS ]. Advise patients to contact their healthcare provider or report to the emergency room if they experience signs or symptoms of serotonin syndrome.
Motor and Verbal Tics, and Worsening of Tourette’s Syndrome Advise patients that motor and verbal tics and worsening of Tourette’s Syndrome may occur during treatment with dextroamphetamine sulfate. Instruct the patients to notify their healthcare provider if emergence or worsening of tics or Tourette’s syndrome occurs (see WARNINGS ). Amphetamines may impair the ability of the patient to engage in potentially hazardous activities such as operating machinery or vehicles; the patient should therefore be cautioned accordingly.
💬 Medication Guide ▾
MEDICATION GUIDE DEXTROAMPHETAMINE SULFATE TABLETS USP, CII (DEX-troe-am-FET-uh-meen SULL-fate) What is the most important information I should know about Dextroamphetamine Sulfate Tablets? Dextroamphetamine Sulfate Tablets may cause serious side effects, including: Abuse misuse, and addiction. Dextroamphetamine Sulfate Tablets has a high chance for abuse and misuse and may lead to substance use problems, including addiction.
Misuse and abuse of dextroamphetamine sulfate tablets, other amphetamine containing medicines, and methylphenidate containing medicines, can lead to overdose and death. The risk of overdose and death is increased with higher doses of dextroamphetamine sulfate tablets or when it is used in ways that are not approved, such as snorting or injection. Your healthcare provider should check you or your child’s risk for abuse, misuse, and addiction before starting treatment with dextroamphetamine sulfate tablets and will monitor you or your child during treatment. dextroamphetamine sulfate tablets may lead to physical dependence after prolonged use, even if taken as directed by your healthcare provider.
Do not give dextroamphetamine sulfate tablets to anyone else. See “What is dextroamphetamine sulfate tablets?” for more information. Keep dextroamphetamine sulfate tablets in a safe place and properly dispose of any unused medicine.
See “How should I store dextroamphetamine sulfate tablets?” for more information. Tell your healthcare provider if you or your child have ever abused or been dependent on alcohol, prescription medicines, or street drugs. Risks for people with serious heart disease: Sudden death has happened in people who have heart defects or other serious heart disease.
Your healthcare provider should check you or your child carefully for heart problems before starting treatment with dextroamphetamine sulfate tablets. Tell your healthcare provider if you or your child have any heart problems, heart diseases, or heart defects. Call your healthcare provider right away or go to the nearest hospital emergency room right away if you or your child have any signs of heart problems such as chest pain, shortness of breath, or fainting during treatment with Dextroamphetamine Sulfate Tablets.
Increased blood pressure and heart rate. Your healthcare provider should check you or your child’s blood pressure and heart rate regularly during treatment with dextroamphetamine sulfate tablets. Mental (psychiatric) problems, including: new or worse behavior or thought problems new or worse bipolar illness new psychotic symptoms (such as hearing voices, or seeing or believing things that are not real) or new manic symptoms Tell your healthcare provider about any mental problems you or your child have, or about a family history of suicide, bipolar illness, or depression.
Call your healthcare provider right away if you or your child have any new or worsening mental symptoms or problems during treatment with Dextroamphetamine Sulfate Tablets, especially hearing voices, seeing or believing things that are not real, or new manic symptoms. What are Dextroamphetamine Sulfate Tablets? Dextroamphetamine Sulfate Tablets are a central nervous system stimulant prescription medicine used for the treatment of: a sleep disorder called narcolepsy.
Attention Deficit Hyperactivity Disorder (ADHD) in children 6 to 17 years of age. Dextroamphetamine Sulfate Tablets may help increase attention and decrease impulsiveness and hyperactivity in people with ADHD. It is not known if Dextroamphetamine Sulfate Tablets are safe and effective in children under 6 years of age.
Dextroamphetamine Sulfate Tablets is a federally controlled substance (CII) because it contains dextroamphetamine that can be a target for people who abuse prescription medicines or street drugs. Keep Dextroamphetamine Sulfate Tablets in a safe place to protect it from theft. Never give your Dextroamphetamine Sulfate Tablets to anyone else because it may cause death or harm them.… [Excerpted — this section continues on DailyMed.]
⚠️ Precautions ▾
PRECAUTIONS Information for Patients Advise the patient to read the FDA-approved patient labeling (Medication Guide). Abuse, Misuse, and Addiction Educate patients and their families about the risks of abuse, misuse, and addiction of dextroamphetamine sulfate, which can lead to overdose and death, and proper disposal of any unused drug (see WARNINGS, DRUG ABUSE AND DEPENDENCE , and OVERDOSAGE ). Advise patients to store dextroamphetamine sulfate in a safe place, preferably locked, and instruct patients to not give dextroamphetamine sulfate to anyone else.
Risks to Patients with Serious Cardiac Disease Advise patients that there are potential risks to patients with serious cardiac disease, including sudden death, with dextroamphetamine sulfate use. Instruct patients to contact a healthcare provider immediately if they develop symptoms such as exertional chest pain, unexplained syncope, or other symptoms suggestive of cardiac disease (see WARNINGS ). Increased Blood Pressure and Heart Rate Advise patients that dextroamphetamine sulfate can elevate blood pressure and heart rate (see WARNINGS ).
Psychiatric Adverse Reactions Advise patients that dextroamphetamine sulfate, at recommended doses, can cause psychotic or manic symptoms, even in patients without prior history of psychotic symptoms or mania (see WARNINGS ). Long-Term Suppression of Growth in Pediatric Patients Advise patients that dextroamphetamine sulfate, may cause slowing of growth including weight loss (see WARNINGS ). Circulation problems in fingers and toes [Peripheral vasculopathy, including Raynaud’s phenomenon] Instruct patients beginning treatment with dextroamphetamine sulfate tablets about the risk of peripheral vasculopathy, including Raynaud’s Phenomenon, and associated signs and symptoms: fingers or toes may feel numb, cool, painful, and/or may change color from pale, to blue, to red.
Instruct patients to report to their physician any new numbness, pain, skin color change, or sensitivity to temperature in fingers or toes. Instruct patients to call their physician immediately with any signs of unexplained wounds appearing on fingers or toes while taking dextroamphetamine sulfate tablets. Further clinical evaluation (e.g., rheumatology referral) may be appropriate for certain patients.
Serotonin Syndrome Caution patients about the risk of serotonin syndrome with concomitant use of dextroamphetamine sulfate and other serotonergic drugs including SSRIs, SNRIs, triptans, tricyclic antidepressants, fentanyl, lithium, tramadol, tryptophan, buspirone, St. John's Wort, and with drugs that impair metabolism of serotonin (in particular MAOIs, both those intended to treat psychiatric disorders and also others such as linezolid [see CONTRAINDICATIONS, WARNINGS and DRUG INTERACTIONS ]. Advise patients to contact their healthcare provider or report to the emergency room if they experience signs or symptoms of serotonin syndrome.
Motor and Verbal Tics, and Worsening of Tourette’s Syndrome Advise patients that motor and verbal tics and worsening of Tourette’s Syndrome may occur during treatment with dextroamphetamine sulfate. Instruct the patients to notify their healthcare provider if emergence or worsening of tics or Tourette’s syndrome occurs (see WARNINGS ). Amphetamines may impair the ability of the patient to engage in potentially hazardous activities such as operating machinery or vehicles; the patient should therefore be cautioned accordingly.
Drug Interactions MAO Inhibitors MAOI antidepressants, as well as a metabolite of furazolidone, slow amphetamine metabolism. This slowing potentiates amphetamines, increasing their effect on the release of norepinephrine and other monoamines from adrenergic nerve endings; this can cause headaches and other signs of hypertensive crisis. A variety of neurological toxic effects and malignant hyperpyrexia can occur, sometimes with fatal results.
Serotonergic Drugs The concomitant use of dextroamphetamine sulfate tablets and serot… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
Pharmacokinetics The pharmacokinetics of the tablet and sustained-release capsule were compared in 12 healthy subjects. The extent of bioavailability of the sustained-release capsule was similar compared to the immediate-release tablet. Following administration of three 5 mg tablets, average maximal dextroamphetamine plasma concentrations (C max ) of 36.6 ng/mL were achieved at approximately 3 hours.
Following administration of one 15 mg sustained-release capsule, maximal dextroamphetamine plasma concentrations were obtained approximately 8 hours after dosing. The average C max was 23.5 ng/mL. The average plasma T 1/2 was similar for both the tablet and sustained-release capsule and was approximately 12 hours.
In 12 healthy subjects, the rate and extent of dextroamphetamine absorption were similar following administration of the sustained-release capsule formulation in the fed (58 to 75 gm fat) and fasted state.
🔒 Drug Abuse and Dependence ▾
DRUG ABUSE AND DEPENDENCE Controlled Substance Dextroamphetamine sulfate is a Schedule II controlled substance. Abuse Dextroamphetamine sulfate has a high potential for abuse and misuse which can lead to the development of a substance use disorder, including addiction (see WARNINGS). Dextroamphetamine sulfate can be diverted for non-medical use into illicit channels or distribution.
Abuse is the intentional non-therapeutic use of a drug, even once, to achieve a desired psychological or physiological effect. Misuse is the intentional use, for therapeutic purposes, of a drug by an individual in a way other than prescribed by a health care provider or for whom it was not prescribed. Drug addiction is a cluster of behavioral, cognitive, and physiological phenomena that may include a strong desire to take the drug, difficulties in controlling drug use (e.g., continuing drug use despite harmful consequences, giving a higher priority to drug use than other activities and obligations), and possible tolerance or physical dependence.
Misuse and abuse of amphetamines may cause increased heart rate, respiratory rate, or blood pressure; sweating; dilated pupils; hyperactivity; restlessness; insomnia; decreased appetite; loss of coordination; tremors; flushed skin; vomiting; and/or abdominal pain. Anxiety, psychosis, hostility, aggression, and suicidal or homicidal ideation have also been observed with CNS stimulants abuse and/or misuse. Misuse and abuse of CNS stimulants, including dextroamphetamine sulfate, can result in overdose and death (see OVERDOSAGE ), and this risk is increased with higher doses or unapproved methods of administration, such as snorting or injection.
Dependence Physical Dependence Dextroamphetamine sulfate may produce physical dependence. Physical dependence is a state that develops as a result of physiological adaptation in response to repeated drug use, manifested by withdrawal signs and symptoms after abrupt discontinuation or a significant dose reduction of a drug. Withdrawal signs and symptoms after abrupt discontinuation or dose reduction following prolonged use of CNS stimulants including dextroamphetamine sulfate include dysphoric mood; depression; fatigue; vivid, unpleasant dreams; insomnia or hypersomnia; increased appetite; and psychomotor retardation or agitation.
Tolerance Dextroamphetamine sulfate may produce tolerance. Tolerance is a physiological state characterized by a reduced response to a drug after repeated administration (i.e., a higher dose of a drug is required to produce the same effect that was once obtained at a lower dose).
📄 Package Label / Principal Display Panel ▾
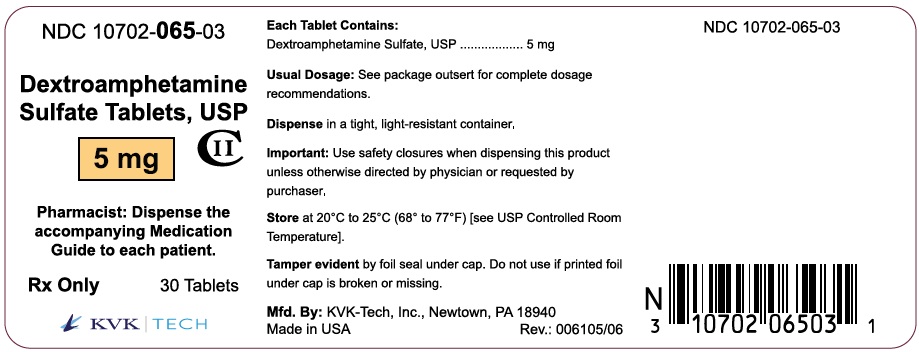
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL - 5 mg Pack Size: 30 Tablets: NDC 10702 -0065- 03 Dextroamphetamine Sulfate Tablets, USP 5 mg CII Pharmacist: Dispense the accompanying Medication Guide to each patient. 30 Tablets Rx Only KVK-TECH, INC. Pack Size: 60 Tablets: NDC 10702 -0065- 06 Dextroamphetamine Sulfate Tablets, USP 5 mg CII Pharmacist: Dispense the accompanying Medication Guide to each patient.
60 Tablets Rx Only KVK-TECH, INC. Pack Size: 100 Tablets: NDC 10702- 0065 -01 Dextroamphetamine Sulfate Tablets, USP 5 mg CII Pharmacist: Dispense the accompanying Medication Guide to each patient. 100 Tablets Rx Only KVK-TECH, INC.
5 mg - 30s 5 mg - 60s 5 mg - 100s
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL Pack Size: 30 Tablets: NDC 10702 -0066- 03 Dextroamphetamine Sulfate Tablets, USP 10 mg CII Pharmacist: Dispense the accompanying Medication Guide to each patient. 30 Tablets Rx Only KVK-TECH, INC. Pack Size: 60 Tablets: NDC 10702 -0066- 06 Dextroamphetamine Sulfate Tablets, USP 10 mg CII Pharmacist: Dispense the accompanying Medication Guide to each patient.
60 Tablets Rx Only KVK-TECH, INC. Pack Size: 100 Tablets: NDC 10702- 0066 -01 Dextroamphetamine Sulfate Tablets, USP 10 mg CII Pharmacist: Dispense the accompanying Medication Guide to each patient. 100 Tablets Rx Only KVK-TECH, INC.
10 mg - 30s 10 mg - 60s 10 mg - 100s