
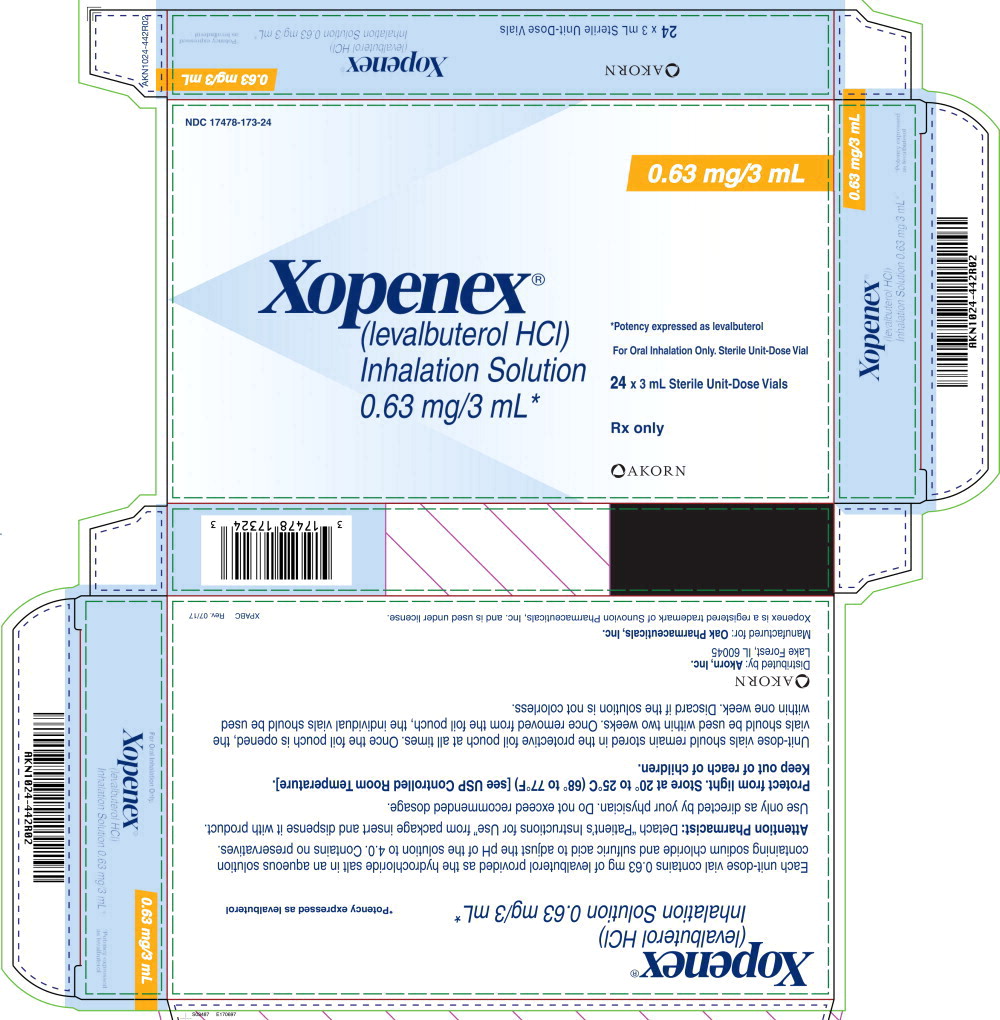
Xopenex Levalbuterol Hydrochloride 0.63 mg/3mL Solution
🆔 Identity & classification
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Levalbuterol is used to prevent or relieve the wheezing, shortness of breath, coughing, and chest tightness caused by lung disease such as asthma and chronic obstructive pulmonary disease (COPD; a group of diseases that affect the lungs and airways). Levalbuterol is in a class of medications called beta agonists. It works by relaxing and opening air passages to the lungs to make breathing easier.
Read the full MedlinePlus article ↗Patient education
Supplement & herbal interactions
Levalbuterol may be associated with lower levels of 2 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII N762921K75
A colorless, odorless gas that makes up most of the air we breathe. In medicines, it's used as a packaging gas or propellant to protect products from oxidation and maintain freshness.
-
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
UNII O40UQP6WCF
A strong acid used in small amounts to adjust and maintain the pH balance of a medicine, helping ensure stability and proper dissolution of the active ingredients.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J7614 | $0.075 / J7614 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Xopenex 0.63 mg/3mLthis 17478-0173-24 | Akorn | 2 pouches | — | — | Discontinued | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 17478-0173-24 You're viewing this | 2 POUCH in 1 CARTON (17478-173-24) / 12 VIAL, SINGLE-DOSE in 1 POUCH (17478-173-12) / 3 mL in 1 VIAL, SINGLE-DOSE | 2015-02-27 | Inactivated by FDA |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
What does the discontinued status mean for this NDC?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE XOPENEX (levalbuterol HCl) Inhalation Solution is indicated for the treatment or prevention of bronchospasm in adults, adolescents, and children 6 years of age and older with reversible obstructive airway disease. XOPENEX (levalbuterol hydrochloride) Inhalation Solution is a beta 2 -adrenergic agonist indicated for: Treatment or prevention of bronchospasm in adults, adolescents, and children 6 years of age and older with reversible obstructive airway disease. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION XOPENEX Inhalation Solution is for oral inhalation only. Administer by nebulization using with a standard jet nebulizer (with a face mask or mouthpiece) connected to an air compressor. Do not exceed recommended dose.
FOR ORAL INHALATION ONLY ( 2 ) Children 6 to 11 years old: 0.31 mg administered three times a day, by nebulization. Routine dosing should not exceed 0.63 mg three times a day. ( 2 ) Adults and Adolescents ≥12 years old: 0.63 mg administered three times a day, every 6 to 8 hours, by nebulization.
The maximum recommended dose is 1.25 mg three times a day. ( 2 ) For use with a standard jet nebulizer (with a face mask or mouthpiece) connected to an air compressor. ( 2 ) Children 6 to 11 years old: The recommended dosage of XOPENEX Inhalation Solution for patients 6 to11 years old is 0.31 mg administered three times a day, by nebulization.
Routine dosing should not exceed 0.63 mg three times a day. Adults and Adolescents ≥12 years old: The recommended starting dosage of XOPENEX Inhalation Solution for patients 12 years of age and older is 0.63 mg administered three times a day, every 6 to 8 hours, by nebulization. Patients 12 years of age and older with more severe asthma or patients who do not respond adequately to a dose of 0.63 mg of XOPENEX Inhalation Solution may benefit from a dosage of 1.25 mg three times a day.
Patients receiving the highest dose of XOPENEX Inhalation Solution should be monitored closely for adverse systemic effects, and the risks of such effects should be balanced against the potential for improved efficacy. The use of XOPENEX Inhalation Solution can be continued as medically indicated to help control recurring bouts of bronchospasm. During this time, most patients gain optimal benefit from regular use of the inhalation solution.
If a previously effective dosage regimen fails to provide the usual response this may be a marker of destabilization of asthma and requires reevaluation of the patient and the treatment regimen, giving special consideration to the possible need for anti-inflammatory treatment, e.g., corticosteroids. The drug compatibility (physical and chemical), efficacy, and safety of XOPENEX Inhalation Solution when mixed with other drugs in a nebulizer have not been established. The safety and efficacy of XOPENEX Inhalation Solution have been established in clinical trials when administered using the PARI LC Jet™ and PARI LC Plus™ nebulizers, and the PARI Master ® Dura-Neb ® 2000 and Dura-Neb ® 3000 compressors.
The safety and efficacy of XOPENEX Inhalation Solution when administered using other nebulizer systems have not been established.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Inhalation Solution 3 mL unit-dose, vials in three dosage strengths of levalbuterol; 0.31 mg, 0.63 mg, 1.25 mg. Each strength of XOPENEX Inhalation Solution is available in a shelf carton containing one or more foil pouches, each containing 12 unit-dose vials. Inhalation Solution (unit-dose vial for nebulization): 0.31 mg/3 mL, 0.63 mg/3 mL and 1.25 mg/3 mL. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS XOPENEX Inhalation Solution is contraindicated in patients with a history of hypersensitivity to levalbuterol or racemic albuterol. Reactions have included urticaria, angioedema, rash, bronchospasm, anaphylaxis, and oropharyngeal edema [see Warnings and Precautions ( 5.6 ) ]. Hypersensitivity to levalbuterol or racemic albuterol. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Life-threatening paradoxical bronchospasm may occur. Discontinue XOPENEX Inhalation Solution immediately and treat with alternative therapy. ( 5.1 ) Need for more doses of XOPENEX Inhalation Solution than usual may be a sign of deterioration of asthma and requires reevaluation of treatment.
( 5.2 ) XOPENEX Inhalation Solution is not a substitute for corticosteroids. ( 5.3 ) Cardiovascular effects may occur. Consider discontinuation of XOPENEX Inhalation Solution if these effects occur.
Use with caution in patients with underlying cardiovascular disorders. ( 5.4 ) Excessive use may be fatal. Do not exceed recommended dose.
( 5.5 ) Immediate hypersensitivity reactions may occur. Discontinue XOPENEX Inhalation Solution immediately. ( 5.6 ) Hypokalemia and changes in blood glucose may occur.
( 5.7 , 5.8 )
5.1Paradoxical Bronchospasm XOPENEX Inhalation Solution can produce paradoxical bronchospasm, which may be life-threatening. If paradoxical bronchospasm occurs, XOPENEX Inhalation Solution should be discontinued immediately and alternative therapy instituted. It should be recognized that paradoxical bronchospasm, when associated with inhaled formulations, frequently occurs with the first use of a new vial.
5.2Deterioration of Asthma Asthma may deteriorate acutely over a period of hours or chronically over several days or longer. If the patient needs more doses of XOPENEX Inhalation Solution than usual, this may be a marker of destabilization of asthma and requires reevaluation of the patient and treatment regimen, giving special consideration to the possible need for anti-inflammatory treatment, e.g., corticosteroids.
5.3Use of Anti-Inflammatory Agents XOPENEX Inhalation Solution is not a substitute for corticosteroids. The use of beta-adrenergic agonist alone may not be adequate to control asthma in many patients. Early consideration should be given to adding anti-inflammatory agents, e.g., corticosteroids, to the therapeutic regimen.
5.4Cardiovascular Effects XOPENEX Inhalation Solution, like other beta-adrenergic agonists, can produce clinically significant cardiovascular effects in some patients, as measured by heart rate, blood pressure, and symptoms. Although such effects are uncommon after administration of XOPENEX Inhalation Solution at recommended doses, if they occur, the drug may need to be discontinued. In addition, beta-agonists have been reported to produce electrocardiogram (ECG) changes, such as flattening of the t-wave, prolongation of the QTc interval, and ST segment depression.
The clinical significance of these findings is unknown. Therefore, XOPENEX Inhalation Solution, like all sympathomimetic amines, should be used with caution in patients with cardiovascular disorders, especially coronary insufficiency, cardiac arrhythmias, and hypertension.
5.5Do Not Exceed Recommended Dose Do not exceed the recommended dose. Fatalities have been reported in association with excessive use of inhaled sympathomimetic drugs in patients with asthma. The exact cause of death is unknown, but cardiac arrest following an unexpected development of a severe acute asthmatic crisis and subsequent hypoxia is suspected.
5.6Immediate Hypersensitivity Reactions Immediate hypersensitivity reactions may occur after administration of levalbuterol or racemic albuterol. Reactions have included urticaria, angioedema, rash, bronchospasm, anaphylaxis, and oropharyngeal edema. The potential for hypersensitivity must be considered in the clinical evaluation of patients who experience immediate hypersensitivity reactions while receiving XOPENEX Inhalation Solution.
5.7Coexisting Conditions XOPENEX Inhalation Solution, like all sympathomimetic amines, should be used with caution in patients with cardiovascular disorders, especially coronary insufficiency, hypertension, and cardiac arrhythmias; in patients with convulsive disorders, hyperthyroidism, or diabetes mellitus; and in patients who are unusually responsive t…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described below and elsewhere in the labeling: Paradoxical bronchospasm [see Warnings and Precautions ( 5.1 ) ] Cardiovascular effects [see Warnings and Precautions ( 5.4 ) ] Immediate hypersensitivity reactions [see Warnings and Precautions ( 5.6 ) ] Hypokalemia [see Warnings and Precautions ( 5.8 ) ] Most common adverse reactions are: palpitations, chest pain, tachycardia, headache, dizziness, tremor and nervousness. ( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Akorn, Inc. at 1-800-932-5676 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of the drug cannot be directly compared with rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adults and Adolescents 12 Years of Age and Older Adverse reaction information concerning XOPENEX Inhalation Solution in adults and adolescents is derived from one 4-week, multicenter, randomized, double-blind, active-, and placebo-controlled trial in 362 patients with asthma 12 years of age and older.
Adverse reactions reported in ≥2% of patients receiving XOPENEX Inhalation Solution or racemic albuterol and more frequently than in patients receiving placebo are listed in Table 1 . Table 1: Adverse Reactions Reported in a 4-Week, Controlled Clinical Trial in Adults and Adolescents ≥12 Years Old a One treatment group, racemic albuterol 1.25 mg, with 68 subjects is omitted. Percent of Patients a Body System Preferred Term Placebo (n=75) XOPENEX 1.25 mg (n=73) XOPENEX 0.63 mg (n=72) Racemic albuterol 2.5 mg (n=74) Body as a Whole Allergic reaction 1.3 0 0
2.7Flu syndrome 0 1.4 4.2
2.7Accidental injury 0 2.7 0 0 Pain 1.3 1.4 2.8
2.7 Back pain 0 0 0
2.7Cardiovascular System Tachycardia 0 2.7 2.8
2.7Migraine 0 2.7 0 0 Digestive System Dyspepsia 1.3 2.7 1.4
1.4Musculoskeletal System Leg cramps 1.3 2.7 0
1.4Central Nervous System Dizziness 1.3 2.7 1.4 0 Hypertonia 0 0 0
2.7Nervousness 0 9.6 2.8
8.1Tremor 0 6.8 0
2.7Anxiety 0 2.7 0 0 Respiratory System Cough increased 2.7 4.1 1.4
2.7Infection viral 9.3 12.3 6.9
12.2Rhinitis 2.7 2.7 11.1
6.8Sinusitis 2.7 1.4 4.2
2.7Turbinate edema 0 1.4 2.8 0 The incidence of certain systemic beta-adrenergic adverse reactions (e.g., tremor, nervousness) was slightly less in the XOPENEX Inhalation Solution 0.63 mg group compared with the other active treatment groups. The clinical significance of these small differences is unknown. Changes in heart rate 15 minutes after drug administration and in plasma glucose and potassium 1 hour after drug administration on day 1 and day 29 were clinically comparable in the XOPENEX Inhalation Solution 1.25 mg and racemic albuterol 2.5 mg groups (see Table 2 ).
Changes in heart rate and plasma glucose were slightly less in the XOPENEX Inhalation Solution 0.63 mg group compared with the other active treatment groups (see Table 2 ). The clinical significance of these small differences is unknown. After 4 weeks, effects on heart rate, plasma glucose, and plasma potassium were generally diminished compared with day 1 in all active treatment groups.
Table 2: Mean Changes from Baseline Heart Rate at 15 Minutes and Glucose and Potassium at 1 Hour after First Dose (Day 1) in Adults and Adolescents ≥12 Years Old Mean Changes (day 1) Treatment Heart Rate (bpm) Glucose (mg/dL) Potassium (mEq/L) XOPENEX 0.63 mg, n=72 2.4 4.6 -0.2 XOPENEX 1.25 mg, n=73 6.9 10.3 -0.3 Racemic albuterol 2.5 mg, n=74 5.7 8.2 -0.3 Placebo, n=75 -2.8 -0.2 -0.2 No other clinically relevant laboratory abnormalities related to administration of XOPENEX Inhalation Solution were observed in this study.
In the clinical trials, a slightly greater number of serious adverse events, discontinuations due to adverse events, and clinically significant ECG changes were reported in patients who received…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Other short-acting sympathomimetic aerosol bronchodilators and adrenergic drugs: May potentiate effect. ( 7.1 ) Beta-blockers: May block bronchodilatory effects of beta-agonists and produce severe bronchospasm. Patients with asthma should not normally be treated with beta-blockers.
( 7.2 ) Diuretic: May worsen electrocardiographic changes or hypokalemia associated with diuretic may worsen. Consider monitoring potassium levels. ( 7.3 ) Digoxin: May decrease serum digoxin levels.
Consider monitoring digoxin levels. ( 7.4 ) Monoamine oxidase inhibitors (MAOs) or tricyclic antidepressants: May potentiate effect of albuterol on the cardiovascular system. ( 7.5 )
7.1Short-Acting Bronchodilators Avoid concomitant use of other short-acting sympathomimetic bronchodilators or epinephrine in patients being treated with XOPENEX Inhalation Solution. If additional adrenergic drugs are to be administered by any route, they should be used with caution to avoid deleterious cardiovascular effects.
7.2Beta-blockers Beta-adrenergic receptor blocking agents not only block the pulmonary effect of beta-adrenergic agonists such as XOPENEX Inhalation Solution, but may produce severe bronchospasm in asthmatic patients. Therefore, patients with asthma should not normally be treated with beta-blockers. However, under certain circumstances, e.g., prophylaxis after myocardial infarction, there may be no acceptable alternatives to the use of beta-adrenergic blocking agents in patients with asthma.
In this setting, cardioselective beta-blockers should be considered, although they should be administered with caution.
7.3Diuretics The ECG changes or hypokalemia that may result from the administration of non-potassium-sparing diuretics (such as loop and thiazide diuretics) can be acutely worsened by beta-agonists, especially when the recommended dose of the beta-agonist is exceeded. Although the clinical significance of these effects is not known, caution is advised in the coadministration of beta-agonists with non-potassium-sparing diuretics. Consider monitoring potassium levels.
7.4Digoxin Mean decreases of 16% and 22% in serum digoxin levels were demonstrated after single-dose intravenous and oral administration of racemic albuterol, respectively, to normal volunteers who had received digoxin for 10 days. The clinical significance of these findings for patients with obstructive airway disease who are receiving XOPENEX Inhalation Solution and digoxin on a chronic basis is unclear. Nevertheless, it would be prudent to carefully evaluate the serum digoxin levels in patients who are currently receiving digoxin and XOPENEX Inhalation Solution.
7.5Monoamine Oxidase Inhibitors or Tricyclic Antidepressants XOPENEX Inhalation Solution should be administered with extreme caution to patients being treated with monoamine oxidase inhibitors or tricyclic antidepressants, or within 2 weeks of discontinuation of such agents, because the action of levalbuterol on the vascular system may be potentiated. Consider alternative therapy in patients taking MAO inhibitors or tricyclic antidepressants.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to asthma medication, including XOPENEX, during pregnancy. To enroll in MotherToBaby Pregnancy Studies' Asthma & Pregnancy Study or for more information about the registry, call 1-877-311-8972 or visit www.mothertobaby.org/ongoing-study/asthma. Risk Summary There are no adequate and well-controlled studies of XOPENEX Inhalation Solution in pregnant women.
There are clinical considerations with the use of XOPENEX Inhalation Solution in pregnant women [see Clinical Considerations ]. Following oral administration of levelbuterol HCl to pregnant rabbits, there was no evidence of teratogenicity at doses up to 25 mg/kg/day [approximately 108 times the maximum recommended human daily inhalation dose (MRHDID) of levalbuterol HCl for adults on a mg/m 2 basis]; however, racemic albuterol sulfate was teratogenic in mice (cleft palate) and rabbits (cramioschisis) at doses slightly higher than the human therapeutic range ( see Data ).
The estimated background risk of major birth defects and miscarriage for the indicated populations(s) are unknown. In the U.S. general population, the estimated risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20% respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk In women with poorly or moderately controlled asthma, there is an increased risk of preeclampsia in the mother and prematurity, low birth weight, and small for gestational age in the neonate.
Pregnant women should be closely monitored and medication adjusted as necessary to maintain optimal control. Labor or Delivery Because of the potential for beta-adrenergic agonists to interfere with uterine contractility, the use of XOPENEX Inhalation Solution for the treatment of bronchospasm during labor should be restricted to those patients for whom the benefits clearly outweigh the risk. XOPENEX Inhalation Solution has not been approved for the management of preterm labor.
The benefit-risk ratio when XOPENEX is administered for tocolysis has not been established. Serious adverse reactions, including maternal pulmonary edema, have been reported during or following treatment of premature labor with beta 2 -agonists, including racemic albuterol. Data Animal Data The oral administration of levalbuterol HCl to pregnant New Zealand White rabbits during the period of organogenesis found no evidence of teratogenicity at doses up to 25 mg/kg/day (approximately 108 times the MRHDID of levalbuterol HCl for adults on a mg/m 2 basis).
In a rat developmental study, racemic albuterol sulfate administered by inhalation did not produce any teratogenic effects at exposures approximately 63 times the MRHDID (on a mg/m 2 basis at a maternal dose of 10.5 mg/kg). However, other developmental studies with the racemic albuterol sulfate, did result in teratogenic effects in mice and rabbits at doses slightly higher than the human therapeutic range. In a rabbit developmental study, orally administered albuterol sulfate induced cranioschisis in 7 of 19 fetuses (37%) at approximately 215 times the MRHDID for adults (on a mg/m 2 basis at a maternal dose of 50 mg/kg).
In a mouse developmental study, subcutaneously administered albuterol sulfate produced cleft palate formation in 5 of 111 (4.5%) fetuses at an exposure approximately 0.3 times the MRHDID for adults (on a mg/m 2 basis at a maternal dose of 0.25 mg/kg/day) and in 10 of 108 (9.3%) fetuses at approximately 3 times the MRHDID (on a mg/m 2 basis at a maternal dose of 2.5 mg/kg/day). Similar effects were not observed at approximately 0.03 times the MRHDID for adults on a mg/m 2 basis at a maternal dose of 0.025 mg/kg/day (i.e., less than the therapeutic dose).
Cleft palate also occurred in 22 of 72 (30.5%) fetuses from females treated subcutaneously with isoproterenol (positive c…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to asthma medication, including XOPENEX, during pregnancy. To enroll in MotherToBaby Pregnancy Studies' Asthma & Pregnancy Study or for more information about the registry, call 1-877-311-8972 or visit www.mothertobaby.org/ongoing-study/asthma. Risk Summary There are no adequate and well-controlled studies of XOPENEX Inhalation Solution in pregnant women.
There are clinical considerations with the use of XOPENEX Inhalation Solution in pregnant women [see Clinical Considerations ]. Following oral administration of levelbuterol HCl to pregnant rabbits, there was no evidence of teratogenicity at doses up to 25 mg/kg/day [approximately 108 times the maximum recommended human daily inhalation dose (MRHDID) of levalbuterol HCl for adults on a mg/m 2 basis]; however, racemic albuterol sulfate was teratogenic in mice (cleft palate) and rabbits (cramioschisis) at doses slightly higher than the human therapeutic range ( see Data ).
The estimated background risk of major birth defects and miscarriage for the indicated populations(s) are unknown. In the U.S. general population, the estimated risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20% respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk In women with poorly or moderately controlled asthma, there is an increased risk of preeclampsia in the mother and prematurity, low birth weight, and small for gestational age in the neonate.
Pregnant women should be closely monitored and medication adjusted as necessary to maintain optimal control. Labor or Delivery Because of the potential for beta-adrenergic agonists to interfere with uterine contractility, the use of XOPENEX Inhalation Solution for the treatment of bronchospasm during labor should be restricted to those patients for whom the benefits clearly outweigh the risk. XOPENEX Inhalation Solution has not been approved for the management of preterm labor.
The benefit-risk ratio when XOPENEX is administered for tocolysis has not been established. Serious adverse reactions, including maternal pulmonary edema, have been reported during or following treatment of premature labor with beta 2 -agonists, including racemic albuterol. Data Animal Data The oral administration of levalbuterol HCl to pregnant New Zealand White rabbits during the period of organogenesis found no evidence of teratogenicity at doses up to 25 mg/kg/day (approximately 108 times the MRHDID of levalbuterol HCl for adults on a mg/m 2 basis).
In a rat developmental study, racemic albuterol sulfate administered by inhalation did not produce any teratogenic effects at exposures approximately 63 times the MRHDID (on a mg/m 2 basis at a maternal dose of 10.5 mg/kg). However, other developmental studies with the racemic albuterol sulfate, did result in teratogenic effects in mice and rabbits at doses slightly higher than the human therapeutic range. In a rabbit developmental study, orally administered albuterol sulfate induced cranioschisis in 7 of 19 fetuses (37%) at approximately 215 times the MRHDID for adults (on a mg/m 2 basis at a maternal dose of 50 mg/kg).
In a mouse developmental study, subcutaneously administered albuterol sulfate produced cleft palate formation in 5 of 111 (4.5%) fetuses at an exposure approximately 0.3 times the MRHDID for adults (on a mg/m 2 basis at a maternal dose of 0.25 mg/kg/day) and in 10 of 108 (9.3%) fetuses at approximately 3 times the MRHDID (on a mg/m 2 basis at a maternal dose of 2.5 mg/kg/day). Similar effects were not observed at approximately 0.03 times the MRHDID for adults on a mg/m 2 basis at a maternal dose of 0.025 mg/kg/day (i.e., less than the therapeutic dose).
Cleft palate also occurred in 22 of 72 (30.5%) fetuses from females treated subcutaneously with isoproterenol (positive control).
🧒 Pediatric Use ▾
8.4Pediatric Use Pediatric Patients 6 Years of Age and Older The safety and efficacy of XOPENEX Inhalation Solution have been established in pediatric patients 6 years of age and older in an adequate and well-controlled clinical trial [see Adverse Reactions ( 6 ) and Clinical Studies ( 14 ) ]. Pediatric Patients less than 6 Years of Age XOPENEX Inhalation Solution is not indicated for pediatric patients less than 6 years of age. Clinical trials with XOPENEX Inhalation Solution in this age group failed to meet the primary efficacy endpoint and demonstrated an increased number of asthma-related adverse reactions following chronic XOPENEX treatment.
XOPENEX Inhalation Solution was studied in 379 pediatric patients less than 6 years of age with asthma or reactive airway disease - (291 patients 2 to 5 years of age, and 88 patients from birth to less than 2 years of age). Efficacy and safety data for XOPENEX Inhalation Solution in this age group are primarily available from one 3-week, multicenter, randomized, double-blind, active and placebo-controlled study (Study 1) in 211 pediatric patients between the ages of 2 and 5 years, of whom 119 received XOPENEX Inhalation Solution.
Over the 3 week treatment period, there were no significant treatment differences in the Pediatric Asthma Questionnaire (PAQ) total score between groups receiving XOPENEX Inhalation Solution 0.31 mg, XOPENEX Inhalation Solution 0.63 mg, racemic albuterol, and placebo. Additional safety data following chronic dosing is available from a 4-week, multicenter, randomized, modified-blind, placebo-controlled study (Study 2) of 196 patients between the ages of birth and 3 years, of whom 63 received open-label XOPENEX Inhalation Solution.
In these two studies, treatment-emergent asthma exacerbations or asthma-related adverse reactions and treatment discontinuations due to asthma occurred at a higher frequency in XOPENEX Inhalation-treated subjects compared to control ( Table 5 ). Other adverse reactions were consistent with those observed in the clinical trial population of patients 6 years of age and older [see Adverse Reactions ( 6.1 ) ]. Table 5: Asthma-related Adverse Reactions in 3- and 4-Week Clinical Trials in Children Birth to <6 Years of Age * Asthma exacerbation defined as worsening of asthma symptoms or pulmonary function that required any of the following: emergency department visit, hospitalization, therapeutic intervention with oral or parenteral steroids, unscheduled clinic visit to treat acute asthma symptoms. ** Includes the following Preferred Terms (whether considered by the investigator to be related or unrelated to drug): asthma, cough, hypoxia, status asthmaticus, tachypnea.
Asthma Exacerbations* n (%) Treatment Discontinuations due to Asthma n (%) Asthma-related Adverse Reactions** n (%) Study 1 XOPENEX 0.31 mg, n=58 6 (10) 4 (7) — XOPENEX 0.63 mg, n=51 7 (14) 6 (12) — Racemic albuterol, n=52 3 (6) 2 (4) — Placebo, n=50 2 (4) 2 (4) — Study 2 XOPENEX 0.31 mg, n=63 — 2 (3) 6 (10) Levalbuterol HFA inhalation aerosol, n=65 — 1 (2) 8 (12) Placebo, n=68 — 0 3 (4)
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of XOPENEX Inhalation Solution did not include sufficient numbers of subjects aged 65 years and older to determine whether they respond differently from younger subjects. Only 5 patients 65 years of age and older were treated with XOPENEX Inhalation Solution in a 4-week clinical study [see Clinical Pharmacology ( 12 ) and Clinical Studies ( 14 ) ] (n=2 for 0.63 mg and n=3 for 1.25 mg). In these patients, bronchodilation was observed after the first dose on day 1 and after 4 weeks of treatment.
In general, patients 65 years of age and older should be started at a dose of 0.63 mg of XOPENEX Inhalation Solution. If clinically warranted due to insufficient bronchodilator response, the dose of XOPENEX Inhalation Solution may be increased in elderly patients as tolerated, in conjunction with frequent clinical and laboratory monitoring, to the maximum recommended daily dose [see Dosage and Administration ( 2 ) ].
🆘 Overdosage ▾
10 OVERDOSAGE The expected symptoms with overdosage are those of excessive beta-adrenergic receptor stimulation and/or occurrence or exaggeration of any of the symptoms listed under Adverse Reactions ( 6 ) , e.g., seizures, angina, hypertension or hypotension, tachycardia with rates up to 200 beats/min., arrhythmias, nervousness, headache, tremor, dry mouth, palpitation, nausea, dizziness, fatigue, malaise, and sleeplessness. Hypokalemia also may occur. As with all sympathomimetic medications, cardiac arrest and even death may be associated with the abuse of XOPENEX Inhalation Solution.
Treatment consists of discontinuation of XOPENEX Inhalation Solution together with appropriate symptomatic therapy. The judicious use of a cardioselective beta-receptor blocker may be considered, bearing in mind that such medication can produce bronchospasm. There is insufficient evidence to determine if dialysis is beneficial for overdosage of XOPENEX Inhalation Solution.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Activation of beta 2 -adrenergic receptors on airway smooth muscle leads to the activation of adenylate cyclase and to an increase in the intracellular concentration of cyclic-3′, 5′-adenosine monophosphate (cyclic AMP). The increase in cyclic AMP is associated with the activation of protein kinase A, which in turn inhibits the phosphorylation of myosin and lowers intracellular ionic calcium concentrations, resulting in muscle relaxation. Levalbuterol relaxes the smooth muscles of all airways, from the trachea to the terminal bronchioles.
Increased cyclic AMP concentrations are also associated with the inhibition of release of mediators from mast cells in the airway. Levalbuterol acts as a functional antagonist to relax the airway irrespective of the spasmogen involved, thus protecting against all bronchoconstrictor challenges. While it is recognized that beta 2 -adrenergic receptors are the predominant receptors on bronchial smooth muscle, data indicate that there are beta-receptors in the human heart, 10% to 50% of which are beta 2 -adrenergic receptors.
The precise function of these receptors has not been established [see Warnings and Precautions ( 5.4 ) ]. However, all beta-adrenergic agonist drugs can produce a significant cardiovascular effect in some patients, as measured by pulse rate, blood pressure, symptoms, and/or electrocardiographic changes.
12.2Pharmacodynamics Adults and Adolescents ≥12 Years Old In a randomized, double-blind, placebo-controlled, cross-over study, 20 adults with mild-to-moderate asthma received single doses of XOPENEX Inhalation Solution (0.31 mg, 0.63 mg, and 1.25 mg) and racemic albuterol sulfate inhalation solution (2.5 mg). All doses of active treatment produced a significantly greater degree of bronchodilation (as measured by percent change from pre-dose mean FEV 1 ) than placebo, and there were no significant differences between any of the active treatment arms.
The bronchodilator responses to 1.25 mg of XOPENEX Inhalation Solution and 2.5 mg of racemic albuterol sulfate inhalation solution were clinically comparable over the 6-hour evaluation period, except for a slightly longer duration of action (>15% increase in FEV 1 from baseline) after administration of 1.25 mg of XOPENEX Inhalation Solution. Systemic beta-adrenergic adverse effects were observed with all active doses and were generally dose-related for (R)-albuterol. XOPENEX Inhalation Solution at a dose of 1.25 mg produced a slightly higher rate of systemic beta-adrenergic adverse effects than the 2.5 mg dose of racemic albuterol sulfate inhalation solution.
In a randomized, double-blind, placebo-controlled, cross-over study, 12 adults with mild-to-moderate asthma were challenged with inhaled methacholine chloride 20 and 180 minutes following administration of a single dose of 2.5 mg of racemic albuterol sulfate, 1.25 mg of XOPENEX, 1.25 mg of (S)-albuterol, or placebo using a Pari LC Jet™ nebulizer. Racemic albuterol sulfate, XOPENEX, and (S)-albuterol had a protective effect against methacholine-induced bronchoconstriction 20 minutes after administration, although the effect of (S)-albuterol was minimal.
At 180 minutes after administration, the bronchoprotective effect of 1.25 mg of XOPENEX was comparable to that of 2.5 mg of racemic albuterol sulfate. At 180 minutes after administration, 1.25 mg of (S)-albuterol had no bronchoprotective effect. In a clinical study in adults with mild-to-moderate asthma, comparable efficacy (as measured by change from baseline FEV 1 ) and safety (as measured by heart rate, blood pressure, ECG, serum potassium, and tremor) were demonstrated after a cumulative dose of 5 mg of XOPENEX Inhalation Solution (four consecutive doses of 1.25 mg administered every 30 minutes) and 10 mg of racemic albuterol sulfate inhalation solution (four consecutive doses of 2.5 mg administered every 30 minutes).
12.3 Pharmacokinetics Adults and Adolescents ≥12 Years O…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Activation of beta 2 -adrenergic receptors on airway smooth muscle leads to the activation of adenylate cyclase and to an increase in the intracellular concentration of cyclic-3′, 5′-adenosine monophosphate (cyclic AMP). The increase in cyclic AMP is associated with the activation of protein kinase A, which in turn inhibits the phosphorylation of myosin and lowers intracellular ionic calcium concentrations, resulting in muscle relaxation. Levalbuterol relaxes the smooth muscles of all airways, from the trachea to the terminal bronchioles.
Increased cyclic AMP concentrations are also associated with the inhibition of release of mediators from mast cells in the airway. Levalbuterol acts as a functional antagonist to relax the airway irrespective of the spasmogen involved, thus protecting against all bronchoconstrictor challenges. While it is recognized that beta 2 -adrenergic receptors are the predominant receptors on bronchial smooth muscle, data indicate that there are beta-receptors in the human heart, 10% to 50% of which are beta 2 -adrenergic receptors.
The precise function of these receptors has not been established [see Warnings and Precautions ( 5.4 ) ]. However, all beta-adrenergic agonist drugs can produce a significant cardiovascular effect in some patients, as measured by pulse rate, blood pressure, symptoms, and/or electrocardiographic changes.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING XOPENEX Inhalation Solution is supplied in 3 mL unit-dose, low-density polyethylene (LDPE) vials as a clear, colorless, sterile, preservative-free, aqueous solution, in three different strengths of levalbuterol (0.31 mg, 0.63 mg, 1.25 mg). Each strength of XOPENEX Inhalation Solution is available in a shelf-carton containing one or more foil pouches, each containing 12 unit-dose LDPE vials. XOPENEX (levalbuterol HCl) Inhalation Solution, 0.31 mg (foil pouch label color green) contains 0.31 mg of levalbuterol (as 0.36 mg of levalbuterol HCl) and is available in cartons of 24 unit-dose LDPE vials (NDC 17478-172-24).
XOPENEX (levalbuterol HCl) Inhalation Solution, 0.63 mg (foil pouch label color yellow) contains 0.63 mg of levalbuterol (as 0.73 mg of levalbuterol HCl) and is available in cartons of 24 unit-dose LDPE vials (NDC 17478-173-24). XOPENEX (levalbuterol HCl) Inhalation Solution, 1.25 mg (foil pouch label color red) contains 1.25 mg of levalbuterol (as 1.44 mg of levalbuterol HCl) and is available in cartons of 24 unit-dose LDPE vials (NDC 17478-174-24). XOPENEX Inhalation Solution is also available as a concentrate in individually pouched 0.5 mL unit-dose vials containing 1.25 mg of levalbuterol (NDC 17478-171-30).
Storage: Store XOPENEX Inhalation Solution in the protective foil pouch at 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature]. Protect from light and excessive heat. Keep unopened vials in the foil pouch.
Once the foil pouch is opened, the vials should be used within 2 weeks. Vials removed from the pouch, if not used immediately, should be protected from light and used within 1 week. Discard any vial if the solution is not colorless.
📋 Description ▾
11 DESCRIPTION XOPENEX Inhalation Solution is a sterile, clear, colorless, preservative-free solution of the hydrochloride salt of levalbuterol, the (R)-enantiomer of the drug substance racemic albuterol. Levalbuterol HCl is a relatively selective beta 2 -adrenergic receptor agonist [see Clinical Pharmacology ( 12 ) ]. The chemical name for levalbuterol HCl is (R)-α 1 -[[(1,1-dimethylethyl) amino]methyl]-4-hydroxy-1,3-benzenedimethanol hydrochloride, and its established chemical structure is as follows: The molecular weight of levalbuterol HCl is 275.8, and its empirical formula is C 13 H 21 NO 3 •HCl.
It is a white to off-white, crystalline solid, with a melting point of approximately 187°C and solubility of approximately 180 mg/mL in water. Levalbuterol HCl is the USAN modified name for (R)-albuterol HCl in the United States. XOPENEX Inhalation Solution is supplied in unit-dose vials and requires no dilution before administration by nebulization.
Each 3 mL unit-dose vial contains 0.31 mg of levalbuterol (as 0.36 mg of levalbuterol HCl) or 0.63 mg of levalbuterol (as 0.73 mg of levalbuterol HCl) or 1.25 mg of levalbuterol (as 1.44 mg of levalbuterol HCl), sodium chloride to adjust tonicity, and sulfuric acid to adjust the pH to 4.0 (3.3 to 4.5). Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION See FDA-approved patient labeling ( Patient Information and Instructions for Using XOPENEX Inhalation Solution ). Patients should be given the following information: Hypersensitivity Query patients about previously experienced hypersensitivity to levalbuterol or racemic albuterol and counsel patients to report any hypersensitivity reactions to their physician. Frequency of Use Inform patients not to increase the dose or use XOPENEX Inhalation Solution more frequently than recommended without consulting their physician.
If patients find that treatment with XOPENEX Inhalation Solution becomes less effective for symptomatic relief, symptoms become worse, or they need to use the product more frequently than usual, they should seek medical attention immediately. Paradoxical Bronchospasm Inform patients that XOPENEX Inhalation Solution can produce paradoxical bronchospasm. Instruct patients to discontinue XOPENEX Inhalation Solution if paradoxical bronchospasm occurs.
Concomitant Drug Use Inform patients using XOPENEX Inhalation Solution, that other inhaled drugs and asthma medications should be taken only as directed by their physician. Common Adverse Reactions Advise patients of the common adverse reactions of treatment with XOPENEX Inhalation Solution including palpitations, chest pain, fast heart rate, headache, dizziness, tremor and nervousness. Pregnancy Advise patients who are pregnant or nursing to contact their physician about the use of XOPENEX Inhalation Solution.
There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to asthma medication, including XOPENEX, during pregnancy. To enroll in the Asthma & Pregnancy Study or for more information about the registry, call 1-877-311-8972 or visit www.mothertobaby.org/ongoing-study/asthma [see Use in Specific Populations ( 8.1 ) ]. General Information on Storage and Use Advise patients to store XOPENEX Inhalation Solution in the foil pouch between 20° to 25°C (68° to 77°F), protected from light and excessive heat.
Do not use after the expiration date stamped on the container. Store unused vials in the protective foil pouch. Once the foil pouch is opened, use the vials within 2 weeks.
Use vials removed from the pouch immediately, or protect from light and use within 1 week. Discard any vial if the solution is not colorless. Advise patients not to mix XOPENEX Inhalation Solution with other drugs in a nebulizer.
AKORN Distributed by: Akorn, Inc. Lake Forest, IL 60045 Manufactured for: Oak Pharmaceuticals, Inc. For customer service, call 1-800-932-5676.
To report adverse events, call 1-800-932-5676. For medical information, call 1-800-932-5676. Xopenex is a registered trademark of Sunovion Pharmaceuticals Inc. and is used under license.
XP00N December 2018 AKNX024-642R01