
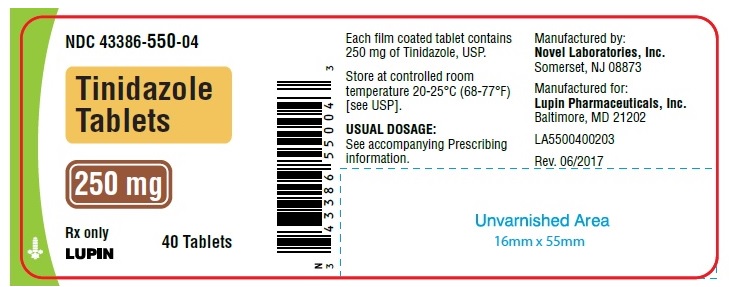
Tinidazole 250 mg Tablet, 40-count — NDC 43386-550-04 (Billing 43386-0550-04)
This is a package of 40 tablets of Tinidazole 250 mg Tablet from Lupin Pharmaceuticals,Inc., marketed since Apr 2012 and currently FDA-listed. It is this product's only package size.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 057691
- GCN: 22867
- GPI-14 (Medi-Span): 16000053000310
- HICL (First Databank): 007779
- AHFS class code: 08:30.16.00
- RxCUI (RxNorm): 199519
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Nitroimidazole Antimicrobial class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Tinidazole is used to treat trichomoniasis (a sexually transmitted disease), bacterial vaginosis (an infection caused by an overgrowth of harmful bacteria in the vagina),giardiasis (an infection of the intestine that can cause diarrhea, gas, and stomach cramps), and amebiasis (an infection of the intestine that can cause diarrhea, gas, and stomach cramps and can spread to other organs such as the liver). Tinidazole is in a class of medications called nitroimidazole antimicrobials. It works by killing the organisms that can cause infection.
Read the full MedlinePlus article ↗- It treats trichomoniasis, giardiasis, amebiasis and bacterial vaginosis. These are infections caused by parasites or bacteria. Your prescriber picks it based on the infection you h...
- Take it by mouth with food to help avoid stomach upset. Follow the exact schedule on your label. If swallowing tablets is hard, ask me about crushing them in cherry syrup.
- No. Avoid alcohol during treatment and for 3 days after your last dose. Mixing them can cause cramps, nausea, vomiting, headache and flushing. This includes products containing eth...
- A metallic or bitter taste, nausea, tiredness, an upset stomach and headache are the most common. Call your doctor right away if you have seizures, numbness or tingling, hives, swe...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Tinidazole — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $3.21 | $128.35 / 40 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 43386-0550-04 You're viewing this Main listing | 40 TABLET in 1 BOTTLE | 2012-04-30 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Tinidazole 250 mg 42799-0207-01 | Edenbridge | 40 tablets | $1.503 | AB | Availability likely | — |
| Tinidazole 250 mg 62135-0834-20 | Chartwell | 20 tablets | $1.503 | AB | Availability likely | — |
| Tindazole 250 mg 64980-0426-02 | Rising | 20 tablets | $1.503 | AB | Availability likely | — |
| Tindamax 250 mg 00178-8250-40 | Mission | 40 tablets | — | AB | FDA listed | — |
| Tinidazole 250 mgthis 43386-0550-04 | Lupin | 40 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII WZB9127XOA
A synthetic red dye used to color medications and make them easier to identify. It serves as a colorant in tablets, capsules, and liquid formulations.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII SA1B764746
A synthetic polymer commonly used as a solvent and binder in medicines. It helps dissolve active ingredients, improve texture, and ensure consistent tablet or capsule formation.
-
UNII 532B59J990
Polyvinyl alcohol is a synthetic polymer made from plant-derived materials. It's used as a binder to hold ingredients together, a film-former in coatings, and a thickener in liquid formulations.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
9 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: POTENTIAL RISK FOR CARCINOGENICITY WARNING: POTENTIAL RISK FOR CARCINOGENICITY See full prescribing information for complete boxed warning Carcinogenicity has been seen in mice and rats treated chronically with metronidazole, another nitroimidazole agent ( 13.1 ). Although such data have not been reported for tinidazole, the two drugs are structurally related and have similar biologic effects. Limit use of tinidazole tablets to approved indications only ( 1.1 , 1.2 , 1.3 ).
Avoid chronic use. ( 5.1 ) Carcinogenicity has been seen in mice and rats treated chronically with metronidazole, another nitroimidazole agent ( 13.1 ). Although such data have not been reported for tinidazole, the two drugs are structurally related and have similar biologic effects.
Its use should be reserved for the conditions described in INDICATIONS AND USAGE ( 1 ). Limit use of tinidazole to approved indications only [see Indications and Usage (1.1, 1.2, 1.3)]. Avoid chronic use [see Warnings and Precautions ( 5.1 )].
🎯 Indications and Usage ▾
1 INDICATIONS & USAGE Tinidazole Tablets is a nitroimidazole antimicrobial indicated for: Trichomoniasis ( 1.1 ) Giardiasis: in patients age 3 and older ( 1.2 ) Amebiasis: in patients age 3 and older ( 1.3 ) Bacterial Vaginosis: in adult women ( 1.4 , 8.1 ) To reduce the development of drug-resistant bacteria and maintain the effectiveness of tinidazole tablets and other antibacterial drugs, tinidazole tablets should be used only to treat or prevent infections that tinidazole tablets are proven or strongly suspected to be caused by bacteria (1.5).
1.1Trichomoniasis Tinidazole is indicated for the treatment of trichomoniasis caused by Trichomonas vaginalis. The organism should be identified by appropriate diagnostic procedures. Because trichomoniasis is a sexually transmitted disease with potentially serious sequelae, partners of infected patients should be treated simultaneously in order to prevent re-infection [see Clinical Studies ( 14.1 )].
1.2Giardiasis Tinidazole is indicated for the treatment of giardiasis caused by Giardia duodenalis (also termed G. lamblia ) in both adults and pediatric patients older than three years of age [ see Clinical Studies ( 14.2 ) ].
1.3Amebiasis Tinidazole is indicated for the treatment of intestinal amebiasis and amebic liver abscess caused by Entamoeba histolytica in both adults and pediatric patients older than three years of age. It is not indicated in the treatment of asymptomatic cyst passage [ see Clinical Studies ( 14.3 , 14.4 ) ].
1.4Bacterial Vaginosis Tinidazole is indicated for the treatment of bacterial vaginosis (formerly referred to as Haemophilus vaginitis, Gardnerella vaginitis, nonspecific vaginitis, or anaerobic vaginosis) in adult women [ see Use in Specific Populations ( 8.1 ) and Clinical Studies ( 14.5 ) ]. Other pathogens commonly associated with vulvovaginitis such as Trichomonas vaginalis, Chlamydia trachomatis, Neisseria gonorrhoeae, Candida albicans and Herpes simplex virus should be ruled out. To reduce the development of drug-resistant bacteria and maintain the effectiveness of tinidazole tablets and other antibacterial drugs, tinidazole tablets should be used only to treat or prevent infections that are proven or strongly suspected to be caused by susceptible bacteria.
When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
1.5Usage To reduce the development of drug-resistant bacteria and maintain the effectiveness of tinidazole tablets and other antibacterial drugs, tinidazole tablets should be used only to treat or prevent infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
⏱️ Dosage and Administration ▾
2 DOSAGE & ADMINISTRATION Trichomoniasis: a single 2 g oral dose taken with food. Treat sexual partner s with the same dose and at the same time ( 2.3 ) Giardiasis: Adults: a single 2 g dose taken with food. Pediatric patients older than three years of age: a single dose of 50 mg/kg (up to 2 g) with food ( 2.4 ) Amebiasis, Intestinal: Adults: 2 g per day for 3 days with food.
Pediatric patients older than three years of age: 50 mg/kg/day (up to 2 g per day) for 3 days with food ( 2.5 ). Amebic liver abscess: Adults: 2 g per day for 3-5 days with food. Pediatric patients older than three years of age: 50 mg/kg/day (up to 2 g per day) for 3-5 days with food ( 2.5 ).
Bacterial vaginosis: Adult women: 2 g once daily for 2 days taken with food, or 1 g once daily for 5 days taken with food ( 2.6 )
2.1Dosing Instructions It is advisable to take tinidazole with food to minimize the incidence of epigastric discomfort and other gastrointestinal side-effects. Food does not affect the oral bioavailability of tinidazole [ see Clinical Pharmacology ( 12.3 ) ]. Alcoholic beverages should be avoided when taking tinidazole and for 3 days afterwards [ see Drug Interactions ( 7.1 ) ].
2.2Compounding of the Oral Suspension For those unable to swallow tablets, tinidazole tablets may be crushed in artificial cherry syrup to be taken with food. Procedure for Extemporaneous Pharmacy Compounding of the Oral Suspension: Pulverize four 500 mg oral tablets with a mortar and pestle. Add approximately 10 mL of cherry syrup to the powder and mix until smooth.
Transfer the suspension to a graduated amber container. Use several small rinses of cherry syrup to transfer any remaining drug in the mortar to the final suspension for a final volume of 30 mL. The suspension of crushed tablets in artificial cherry syrup is stable for 7 days at room temperature.
When this suspension is used, it should be shaken well before each administration.
2.3Trichomoniasis The recommended dose in both females and males is a single 2 g oral dose taken with food. Since trichomoniasis is a sexually transmitted disease, sexual partners should be treated with the same dose and at the same time.
2.4Giardiasis The recommended dose in adults is a single 2 g dose taken with food. In pediatric patients older than three years of age, the recommended dose is a single dose of 50 mg/kg (up to 2 g) with food.
2.5Amebiasis Intestinal : The recommended dose in adults is a 2 g dose per day for 3 days taken with food. In pediatric patients older than three years of age, the recommended dose is 50 mg/kg/day (up to 2 g per day) for 3 days with food. Amebic Liver Abscess: The recommended dose in adults is a 2 g dose per day for 3-5 days taken with food.
In pediatric patients older than three years of age, the recommended dose is 50 mg/kg/day (up to 2 g per day) for 3-5 days with food. There are limited pediatric data on durations of therapy exceeding 3 days, although a small number of children were treated for 5 days without additional reported adverse reactions. Children should be closely monitored when treatment durations exceed 3 days.
2.6Bacterial Vaginosis The recommended dose is a 2 g oral dose once daily for 2 days taken with food or a 1 g oral dose once daily for 5 days taken with food. The use of tinidazole in pregnant patients has not been studied for bacterial vaginosis.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS & STRENGTHS Tablets: 250 mg and 500 mg ( 3 ) 250 mg tablets are pink, round, scored tablets debossed with "N" scored "L" on one side and "550" on the other side. 500 mg tablets are pink, oval, scored tablets debossed with "N" scored "L" on one side and "551" on the other side.
⛔ Contraindications ▾
4 CONTRAINDICATIONS Prior history of hypersensitivity to tinidazole or other nitroimidazole derivatives ( 4 , 6.1 , 6.2 ) Patients with Cockayne syndrome ( 4 , 6.2 ) The use of tinidazole is contraindicated: In patients with a previous history of hypersensitivity to tinidazole or other nitroimidazole derivatives. Reported reactions have ranged in severity from urticaria to Stevens-Johnson syndrome [ see Adverse Reactions ( 6.1 , 6.2 ) ]. In patients with Cockayne syndrome.
Severe irreversible hepatotoxicity/acute liver failure with fatal outcomes have been reported after initiation of metronidazole, another nitroimidazole drug, structurally related to tinidazole, in patients with Cockayne syndrome [see Adverse Reactions ( 6.2 )]
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Seizures and neuropathy have been reported. Discontinue tinidazole tablets if abnormal neurologic signs develop ( 5.1 ) Vaginal candidiasis may develop with tinidazole tablets and require treatment with an antifungal agent ( 5.2 ) Use tinidazole tablets with caution in patients with blood dyscrasias. Tinidazole tablets may produce transient leukopenia and neutropenia ( 5.3 , 7.3 )
5.1Potential for Genotoxicity and Carcinogenicity Carcinogenicity has been seen in mice and rats treated chronically with nitroimidazole derivatives, which are structurally related to tinidazole [see Nonclinical Toxicology (13.1)]. Although such data have not been reported for tinidazole, the two drugs are structurally related and have similar biologic effects. However, it is unclear if the positive tumor findings in lifetime rodent studies indicate a risk to patients taking a short course or single dose of tinidazole tablets.
Use should be limited to approved indications only. Avoid chronic use.
5.2Neurological Adverse Reactions Convulsive seizures and peripheral neuropathy, the latter characterized mainly by numbness or paresthesia of an extremity, have been reported in patients treated with tinidazole. The appearance of abnormal neurologic signs demands the prompt discontinuation of tinidazole therapy.
5.3Vaginal Candidiasis The use of tinidazole may result in Candida vaginitis. In a clinical study of 235 women who received tinidazole for bacterial vaginosis, a vaginal fungal infection developed in 11 (4.7%) of all study subjects [ see Clinical Studies ( 14.5 ) ].
5.4Blood Dyscrasia Tinidazole should be used with caution in patients with evidence of or history of blood dyscrasia [ see Drug Interactions ( 7.3 ) ].
5.5Development of Drug Resistant Bacteria Prescribing tinidazole tablets in the absence of a proven or strongly suspected bacterial infection or a prophylactic indication is unlikely to provide benefit to the patient and increases the risk of the development of drug-resistant bacteria.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Most common adverse reactions for a single 2 g dose of tinidazole (incidence >1%) are metallic/bitter taste, nausea, weakness/fatigue/malaise, dyspepsia/cramps/epigastric discomfort, vomiting, anorexia, headache, dizziness and constipation ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Lupin Pharmaceuticals, Inc. at 1-866-403-7592 or or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Studies Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Among 3669 patients treated with a single 2 g dose of tinidazole, in both controlled and uncontrolled trichomoniasis and giardiasis clinical studies, adverse reactions were reported by 11.0% of patients. For multi-day dosing in controlled and uncontrolled amebiasis studies, adverse reactions were reported by 13.8% of 1765 patients.
Common (≥ 1% incidence) adverse reactions reported by body system are as follows. (Note: Data described in Table 1 below are pooled from studies with variable designs and safety evaluations.) Other adverse reactions reported with tinidazole include: Central Nervous System: Two serious adverse reactions reported include convulsions and transient peripheral neuropathy including numbness and paresthesia [see Warnings and Precautions ( 5.1 )] . Other CNS reports include vertigo, ataxia, giddiness, insomnia, drowsiness.
Gastrointestinal: tongue discoloration, stomatitis, diarrhea Hypersensitivity: urticaria, pruritis, rash, flushing, sweating, dryness of mouth, fever, burning sensation, thirst, salivation, angioedema Renal: darkened urine Cardiovascular: palpitations Hematopoietic: transient neutropenia, transient leukopenia Other: Candida overgrowth, increased vaginal discharge, oral candidiasis, hepatic abnormalities including raised transaminase level, arthralgias, myalgias, and arthritis. Table 1. Adverse Reactions Summary of Published Reports 2 g single dose Multi-day dose GI: Metallic/bitter taste 3.7% 6.3% Nausea 3.2% 4.5% Anorexia 1.5% 2.5% Dyspepsia/cramps/epigastric discomfort 1.8% 1.4% Vomiting 1.5% 0.9% Constipation 0.4% 1.4% CNS: Weakness/fatigue/malaise 2.1% 1.1% Dizziness 1.1% 0.5% Other: Headache 1.3% 0.7% Total patients with adverse reactions 11.0% (403/3669) 13.8% (244/1765) Rare reported adverse reactions include bronchospasm, dyspnea, coma, confusion, depression, furry tongue, pharyngitis and reversible thrombocytopenia.
Adverse Reactions in Pediatric Patients: In pooled pediatric studies, adverse reactions reported in pediatric patients taking tinidazole were similar in nature and frequency to adult findings including nausea, vomiting, diarrhea, taste change, anorexia, and abdominal pain. Bacterial vaginosis: The most common adverse reactions in treated patients (incidence >2%), which were not identified in the trichomoniasis, giardiasis and amebiasis studies, are gastrointestinal: decreased appetite, and flatulence; renal: urinary tract infection, painful urination, and urine abnormality; and other reactions including pelvic pain, vulvo-vaginal discomfort, vaginal odor, menorrhagia, and upper respiratory tract infection [ See Clinical Studies ( 14.5 ) ].
6.2Postmarketing Experience The following adverse reactions have been identified and reported during post-approval use of tinidazole tablets. Because the reports of these reactions are voluntary and the population is of uncertain size, it is not always possible to reliably estimate the frequency of the reaction or establish a causal relationship to drug exposure. Tinidazole tablets Severe acute hypersensitivity reactions have been reported on initial or subsequent exposure to tinidazole.
Hypersensitivity reactions may include urticaria, pruritis, angioedema, Stevens-Johnson syndrome and erythema multiforme. Metronidazole, Another Nitro… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS The following drug interactions were reported for metronidazole, a chemically-related nitroimidazole and may therefore occur with tinidazole: Warfarin and other oral coumarin anticoagulants: Anticoagulant dosage may need adjustment during and up to 8 days after tinidazole therapy ( 7.1 ) Alcohol-containing beverages/preparations: Avoid during and up to 3 days after tinidazole therapy ( 7.1 ) Lithium: Monitor serum lithium concentrations ( 7.1 ) Cyclosporine, tacrolimus: Monitor for toxicities of these immunosuppressive drugs ( 7.1 ) Fluorouracil: Monitor for fluorouracil-associated toxicities ( 7.1 ) Phenytoin, fosphenytoin: Adjustment of anticonvulsant and/or tinidazole dose(s) may be needed ( 7.1 , 7.2 ) CYP3A4 inducers/inhibitors: Monitor for decreased tinidazole effect or increased adverse reactions ( 7.2 ) Although not specifically identified in studies with tinidazole, the following drug interactions were reported for metronidazole, a chemically-related nitroimidazole.
Therefore, these drug interactions may occur with tinidazole.
7.1Potential Effects of Tinidazole on Other Drugs Warfarin and Other Oral Coumarin Anticoagulants: As with metronidazole, tinidazole may enhance the effect of warfarin and other coumarin anticoagulants, resulting in a prolongation of prothrombin time. The dosage of oral anticoagulants may need to be adjusted during tinidazole co-administration and up to 8 days after discontinuation. Alcohols, Disulfiram: Alcoholic beverages and preparations containing ethanol or propylene glycol should be avoided during tinidazole therapy and for 3 days afterward because abdominal cramps, nausea, vomiting, headaches, and flushing may occur.
Psychotic reactions have been reported in alcoholic patients using metronidazole and disulfiram concurrently. Though no similar reactions have been reported with tinidazole, tinidazole should not be given to patients who have taken disulfiram within the last two weeks. Lithium : Metronidazole has been reported to elevate serum lithium levels.
It is not known if tinidazole shares this property with metronidazole, but consideration should be given to measuring serum lithium and creatinine levels after several days of simultaneous lithium and tinidazole treatment to detect potential lithium intoxication. Phenytoin, Fosphenytoin: Concomitant administration of oral metronidazole and intravenous phenytoin was reported to result in prolongation of the half-life and reduction in the clearance of phenytoin. Metronidazole did not significantly affect the pharmacokinetics of orally-administered phenytoin.
Cyclosporine, Tacrolimus : There are several case reports suggesting that metronidazole has the potential to increase the levels of cyclosporine and tacrolimus. During tinidazole co-administration with either of these drugs, the patient should be monitored for signs of calcineurin-inhibitor associated toxicities. Fluorouracil : Metronidazole was shown to decrease the clearance of fluorouracil, resulting in an increase in side-effects without an increase in therapeutic benefits.
If the concomitant use of tinidazole and fluorouracil cannot be avoided, the patient should be monitored for fluorouracil-associated toxicities.
7.2Potential Effects of Other Drugs on Tinidazole CYP3A4 Inducers and Inhibitors: Simultaneous administration of tinidazole with drugs that induce liver microsomal enzymes, i.e., CYP3A4 inducers such as phenobarbital , rifampin, phenytoin , and fosphenytoin (a pro-drug of phenytoin), may accelerate the elimination of tinidazole, decreasing the plasma level of tinidazole. Simultaneous administration of drugs that inhibit the activity of liver microsomal enzymes, i.e., CYP3A4 inhibitors such as cimetidine and ketoconazole , may prolong the half-life and decrease the plasma clearance of tinidazole, increasing the plasma concentrations of tinidazole.
Cholestyramine : Cholestyramine was shown to decrease the oral bioavailability of metronidazole by 21%.… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pediatric Use: Data on tinidazole use in children is limited to treatment of giardiasis and amebiasis in patients age 3 and older ( 8.4 ) Hemodialysis patients: If tinidazole is administered the same day and prior to hemodialysis, administer an additional ½ dose after end of hemodialysis ( 8.6 , 12.3 )
8.1Pregnancy Risk Summary Available published data from a case-control study and case report with tinidazole use in pregnant women are insufficient to identify a risk of major birth defects, miscarriage or adverse maternal or fetal outcomes. There are risks associated with untreated lower genital tract infections during pregnancy (see Clinical Considerations). In animal reproduction studies, oral administration of tinidazole to pregnant mice and rats during organogenesis at 6 and 3 times, respectively, the maximum recommended human dose (based on body surface area comparison) showed a slight increase in fetal mortality in rats at the highest dose, with no other adverse fetal effects noted in either species (see Data).
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data Animal Data Embryo-fetal developmental toxicity studies in pregnant mice administered oral tinidazole on gestation days (GD) 7 to 12 indicated no embryo-fetal toxicity or malformations at the highest dose level of 2,500 mg/kg (approximately 6.3-fold the highest human therapeutic dose based upon body surface area conversions). In a study with pregnant rats administered oral tinidazole on GD 9 to 14, a slightly higher incidence of fetal mortality was observed at a maternal dose of 500 mg/kg (2.5-fold the highest human therapeutic dose based upon body surface area conversions).
No biologically relevant neonatal developmental effects were observed in surviving rat neonates following maternal doses as high as 600 mg/kg (3-fold the highest human therapeutic dose based upon body surface area conversions).
8.2Lactation Risk Summary Limited published literature, based on breast milk sampling, reports that tinidazole is present in human milk. There are no reports of adverse effects on the breastfed infant and no information on the effects of tinidazole on milk production. Because of the potential for serious adverse reactions, including tumorigenicity, advise patients that breastfeeding is not recommended during treatment with tinidazole tablet and for 72 hours (based on half-life) after administration of tinidazole.
Clinical Considerations A nursing mother may choose to pump and discard her milk during treatment and for 72 hours after administration of tinidazole tablet to minimize exposure to the breastfeeding infant.
8.3Females and Males of Reproductive Potential Infertility Infertility Males Based on findings in rodents, tinidazole tablet may impair fertility in males of reproductive potential. It is not known whether effects on fertility are reversible [see Nonclinical Toxicology ( 13.1 )].
8.4Pediatric Use Other than for use in the treatment of giardiasis and amebiasis in pediatric patients older than three years of age, safety and effectiveness of tinidazole in pediatric patients have not been established. Pediatric Administration: For those unable to swallow tablets, tinidazole tablets may be crushed in artificial cherry syrup, to be taken with food [see Dosage and Administration ( 2.2 )].
8.5Geriatric Use Clinical studies of tinidazole did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. In general, dose selection for an elderly patient should be cautious, reflecting the greater frequency of decreased hepatic, renal, or cardia… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available published data from a case-control study and case report with tinidazole use in pregnant women are insufficient to identify a risk of major birth defects, miscarriage or adverse maternal or fetal outcomes. There are risks associated with untreated lower genital tract infections during pregnancy (see Clinical Considerations). In animal reproduction studies, oral administration of tinidazole to pregnant mice and rats during organogenesis at 6 and 3 times, respectively, the maximum recommended human dose (based on body surface area comparison) showed a slight increase in fetal mortality in rats at the highest dose, with no other adverse fetal effects noted in either species (see Data).
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data Animal Data Embryo-fetal developmental toxicity studies in pregnant mice administered oral tinidazole on gestation days (GD) 7 to 12 indicated no embryo-fetal toxicity or malformations at the highest dose level of 2,500 mg/kg (approximately 6.3-fold the highest human therapeutic dose based upon body surface area conversions). In a study with pregnant rats administered oral tinidazole on GD 9 to 14, a slightly higher incidence of fetal mortality was observed at a maternal dose of 500 mg/kg (2.5-fold the highest human therapeutic dose based upon body surface area conversions).
No biologically relevant neonatal developmental effects were observed in surviving rat neonates following maternal doses as high as 600 mg/kg (3-fold the highest human therapeutic dose based upon body surface area conversions).
🧒 Pediatric Use ▾
8.4Pediatric Use Other than for use in the treatment of giardiasis and amebiasis in pediatric patients older than three years of age, safety and effectiveness of tinidazole in pediatric patients have not been established. Pediatric Administration: For those unable to swallow tablets, tinidazole tablets may be crushed in artificial cherry syrup, to be taken with food [see Dosage and Administration ( 2.2 )].
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of tinidazole did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. In general, dose selection for an elderly patient should be cautious, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
10 OVERDOSAGE There are no reported overdoses with tinidazole in humans. Treatment of Overdosage : There is no specific antidote for the treatment of overdosage with tinidazole; therefore, treatment should be symptomatic and supportive. Gastric lavage may be helpful. Hemodialysis can be considered because approximately 43% of the amount present in the body is eliminated during a 6-hour hemodialysis session.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Tinidazole is an antiprotozoal, antibacterial agent. [ See Clinical Pharmacology ( 12.4 ) ].
12.2Pharmacodynamics Tinidazole exposure-response relationships and the time course of pharmacodynamics response are unknown.
12.3Pharmacokinetics Absorption : After oral administration, tinidazole is rapidly and completely absorbed. A bioavailability study of tinidazole tablets was conducted in adult healthy volunteers. All subjects received a single oral dose of 2 g (four 500 mg tablets) of tinidazole tablets following an overnight fast.
Oral administration of four 500 mg tablets of tinidazole tablets under fasted conditions produced a mean peak plasma concentration (C max ) of 47.7 (±7.5) µg/mL with a mean time to peak concentration (T max ) of 1.6 (±0.7) hours, and a mean area under the plasma concentration-time curve (AUC, 0-∞) of 901.6 (± 126.5) µg/hr/mL at 72 hours. The elimination half-life (T 1/2 ) was 13.2 (±1.4) hours. Mean plasma levels decreased to 14.3 µg/mL at 24 hours, 3.8 µg/mL at 48 hours and 0.8 µg/mL at 72 hours following administration.
Steady-state conditions are reached in 2½ -3 days of multi-day dosing. Administration of tinidazole tablets with food did not affect AUC or T 1/2 in this study. In healthy volunteers, administration of crushed tinidazole tablets in artificial cherry syrup, [prepared as described in Dosage and Administration ( 2.2 ) ] after an overnight fast had no effect on any pharmacokinetic parameter as compared to tablets swallowed whole under fasted conditions.
Distribution: Tinidazole is distributed into virtually all tissues and body fluids and also crosses the blood-brain barrier. The apparent volume of distribution is about 50 liters. Plasma protein binding of tinidazole is 12%.
Elimination The plasma half-life of tinidazole is approximately 12-14 hours. Metabolism : Tinidazole is significantly metabolized in humans prior to excretion. Tinidazole is partly metabolized by oxidation, hydroxylation, and conjugation.
Tinidazole is the major drug-related constituent in plasma after human treatment, along with a small amount of the 2-hydroxymethyl metabolite. Tinidazole is biotransformed mainly by CYP3A4. In an in vitro metabolic drug interaction study, tinidazole concentrations of up to 75 µg/mL did not inhibit the enzyme activities of CYP1A2, CYP2B6, CYP2C9, CYP2D6, CYP2E1, and CYP3A4.
The potential of tinidazole to induce the metabolism of other drugs has not been evaluated. Excretion :Tinidazole is excreted by the liver and the kidneys. Tinidazole is excreted in the urine mainly as unchanged drug (approximately 20 to 25% of the administered dose).
Approximately 12% of the drug is excreted in the feces. Specific Populations Patients with impaired renal function: The pharmacokinetics of tinidazole in patients with severe renal impairment (CrCL < 22 mL/min) are not significantly different from the pharmacokinetics seen in healthy subjects. However, during hemodialysis, clearance of tinidazole is significantly increased; the half-life is reduced from 12.0 hours to 4.9 hours.
Approximately 43% of the amount present in the body is eliminated during a 6-hour hemodialysis session [S ee Use in Specific Populations ( 8.6 ) ]. The pharmacokinetics of tinidazole in patients undergoing routine continuous peritoneal dialysis have not been investigated. Patients with impaired hepatic function: There are no data on tinidazole pharmacokinetics in patients with impaired hepatic function.
Reduction of metabolic elimination of metronidazole, a chemically-related nitroimidazole, in patients with hepatic dysfunction has been reported in several studies [see Use in Specific Populations ( 8.7 )].
12.4Microbiology Mechanism of Action : Tinidazole is an antiprotozoal, antibacterial agent. The nitro- group of tinidazole is reduced by cell extracts of Trichomonas . The free nitro- radical generated as a result of this reduction may be responsible for the antiprotozoal… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Tinidazole is an antiprotozoal, antibacterial agent. [ See Clinical Pharmacology ( 12.4 ) ].
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Tinidazole Tablets 250 mg tablets are pink, round, scored tablets, debossed with "N" scored "L" on one side and "550" on the other side, supplied in bottles with child-resistant caps as: NDC 43386-550-04 Bottle of 40 Tinidazole Tablets 500 mg tablets are pink, oval, scored tablets, debossed with "N" scored "L" on one side and "551" on the other side, supplied in bottles with child-resistant caps as: NDC 43386-551-06 Bottle of 60 NDC 43386-551-02 Bottle of 20 Storage: Store at controlled room temperature 20-25° C (68-77° F); excursions permitted to 15-30° C (59-86° F) [see USP].
Protect contents from light.
📋 Description ▾
11 DESCRIPTION Tinidazole is a synthetic antiprotozoal and antibacterial agent. It is 1-[2-(ethylsulfonyl)ethyl]-2-methyl-5-nitroimidazole, a second-generation 2-methyl-5-nitroimidazole, which has the following chemical structure: Tinidazole pink oral tablets contain 250 mg or 500 mg of tinidazole. Inactive ingredients include pregelatinized starch NF, croscarmellose sodium NF, magnesium stearate NF, microcrystalline cellulose NF, polyvinyl alcohol-part hydrolyzed USP, titanium dioxide USP, polyethylene glycol 3000 NF, talc USP, and FD&C red # 40 aluminum lake. structure
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption : After oral administration, tinidazole is rapidly and completely absorbed. A bioavailability study of tinidazole tablets was conducted in adult healthy volunteers. All subjects received a single oral dose of 2 g (four 500 mg tablets) of tinidazole tablets following an overnight fast.
Oral administration of four 500 mg tablets of tinidazole tablets under fasted conditions produced a mean peak plasma concentration (C max ) of 47.7 (±7.5) µg/mL with a mean time to peak concentration (T max ) of 1.6 (±0.7) hours, and a mean area under the plasma concentration-time curve (AUC, 0-∞) of 901.6 (± 126.5) µg/hr/mL at 72 hours. The elimination half-life (T 1/2 ) was 13.2 (±1.4) hours. Mean plasma levels decreased to 14.3 µg/mL at 24 hours, 3.8 µg/mL at 48 hours and 0.8 µg/mL at 72 hours following administration.
Steady-state conditions are reached in 2½ -3 days of multi-day dosing. Administration of tinidazole tablets with food did not affect AUC or T 1/2 in this study. In healthy volunteers, administration of crushed tinidazole tablets in artificial cherry syrup, [prepared as described in Dosage and Administration ( 2.2 ) ] after an overnight fast had no effect on any pharmacokinetic parameter as compared to tablets swallowed whole under fasted conditions.
Distribution: Tinidazole is distributed into virtually all tissues and body fluids and also crosses the blood-brain barrier. The apparent volume of distribution is about 50 liters. Plasma protein binding of tinidazole is 12%.
Elimination The plasma half-life of tinidazole is approximately 12-14 hours. Metabolism : Tinidazole is significantly metabolized in humans prior to excretion. Tinidazole is partly metabolized by oxidation, hydroxylation, and conjugation.
Tinidazole is the major drug-related constituent in plasma after human treatment, along with a small amount of the 2-hydroxymethyl metabolite. Tinidazole is biotransformed mainly by CYP3A4. In an in vitro metabolic drug interaction study, tinidazole concentrations of up to 75 µg/mL did not inhibit the enzyme activities of CYP1A2, CYP2B6, CYP2C9, CYP2D6, CYP2E1, and CYP3A4.
The potential of tinidazole to induce the metabolism of other drugs has not been evaluated. Excretion :Tinidazole is excreted by the liver and the kidneys. Tinidazole is excreted in the urine mainly as unchanged drug (approximately 20 to 25% of the administered dose).
Approximately 12% of the drug is excreted in the feces. Specific Populations Patients with impaired renal function: The pharmacokinetics of tinidazole in patients with severe renal impairment (CrCL < 22 mL/min) are not significantly different from the pharmacokinetics seen in healthy subjects. However, during hemodialysis, clearance of tinidazole is significantly increased; the half-life is reduced from 12.0 hours to 4.9 hours.
Approximately 43% of the amount present in the body is eliminated during a 6-hour hemodialysis session [S ee Use in Specific Populations ( 8.6 ) ]. The pharmacokinetics of tinidazole in patients undergoing routine continuous peritoneal dialysis have not been investigated. Patients with impaired hepatic function: There are no data on tinidazole pharmacokinetics in patients with impaired hepatic function.
Reduction of metabolic elimination of metronidazole, a chemically-related nitroimidazole, in patients with hepatic dysfunction has been reported in several studies [see Use in Specific Populations ( 8.7 )].
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Tinidazole exposure-response relationships and the time course of pharmacodynamics response are unknown.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Trichomoniasis Tinidazole (2 g single oral dose) use in trichomoniasis has been well documented in 34 published reports from the world literature involving over 2,800 patients treated with tinidazole. In four published, blinded, randomized, comparative studies of the 2 g tinidazole single oral dose where efficacy was assessed by culture at time points post-treatment ranging from one week to one month, reported cure rates ranged from 92% (37/40) to 100% (65/65) (n=172 total subjects). In four published, blinded, randomized, comparative studies where efficacy was assessed by wet mount between 7 -14 days post-treatment, reported cure rates ranged from 80% (8/10) to 100% (16/16) (n=116 total subjects).
In these studies, tinidazole was superior to placebo and comparable to other anti-trichomonal drugs. The single oral 2 g tinidazole dose was also assessed in four open-label trials in men (one comparative to metronidazole and 3 single-arm studies). Parasitological evaluation of the urine was performed both pre- and post-treatment and reported cure rates ranged from 83% (25/30) to 100% (80/80) (n=142 total subjects).
14.2Giardiasis Tinidazole (2 g single dose) use in giardiasis has been documented in 19 published reports from the world literature involving over 1,600 patients (adults and pediatric patients). In eight controlled studies involving a total of 619 subjects of whom 299 were given the 2 g × 1 day (50 mg/kg × 1 day in pediatric patients) oral dose of tinidazole, reported cure rates ranged from 80% (40/50) to 100% (15/15). In three of these trials where the comparator was 2 to 3 days of various doses of metronidazole, reported cure rates for metronidazole were 76% (19/25) to 93% (14/15).
Data comparing a single 2 g dose of tinidazole to usually recommended 5 - 7 days of metronidazole are limited.
14.3Intestinal Amebiasis Tinidazole use in intestinal amebiasis has been documented in 26 published reports from the world literature involving over 1,400 patients. Most reports utilized tinidazole 2 g/day × 3 days. In four published, randomized, controlled studies (1 investigator single-blind, 3 open-label) of the 2 g/day × 3 days oral dose of tinidazole, reported cure rates after 3 days of therapy among a total of 220 subjects ranged from 86% (25/29) to 93% (25/27).
14.4Amebic Liver Abscess Tinidazole use in amebic liver abscess has been documented in 18 published reports from the world literature involving over 470 patients. Most reports utilized tinidazole 2 g/day × 2 - 5 days. In seven published, randomized, controlled studies (1 double-blind, 1 single-blind, 5 open-label) of the 2 g/day × 2 - 5 days oral dose of tinidazole accompanied by aspiration of the liver abscess when clinically necessary, reported cure rates among 133 subjects ranged from 81% (17/21) to 100% (16/16).
Four of these studies utilized at least 3 days of tinidazole.
14.5Bacterial Vaginosis A randomized, double-blind, placebo-controlled clinical trial in 235 non-pregnant women was conducted to evaluate the efficacy of tinidazole for the treatment of bacterial vaginosis. A clinical diagnosis of bacterial vaginosis was based on Amsel's criteria and defined by the presence of an abnormal homogeneous vaginal discharge that (a) has a pH of greater than 4.5, (b) emits a "fishy" amine odor when mixed with a 10% KOH solution, and (c) contains ≥20% clue cells on microscopic examination.
Clinical cure required a return to normal vaginal discharge and resolution of all Amsel's criteria. A microbiologic diagnosis of bacterial vaginosis was based on Gram stain of the vaginal smear demonstrating (a) markedly reduced or absent Lactobacillus morphology, (b) predominance of Gardnerella morphotype, and (c) absent or few white blood cells, with quantification of these bacterial morphotypes to determine the Nugent score, where a score ≥4 was required for study inclusion and a score of 0 - 3 considered a microbiologic cure.
Therapeutic cure was a comp… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis & Impairment of Fertility Metronidazole, a chemically-related nitroimidazole, has been reported to be carcinogenic in mice and rats but not hamsters. In several studies metronidazole showed evidence of pulmonary, hepatic, and lymphatic tumorigenesis in mice and mammary and hepatic tumors in female rats. Tinidazole carcinogenicity studies in rats, mice or hamsters have not been reported.
Tinidazole was mutagenic in the TA 100, S. typhimurium tester strain both with and without the metabolic activation system and was negative for mutagenicity in the TA 98 strain. Mutagenicity results were mixed (positive and negative) in the TA 1535, 1537, and 1538 strains. Tinidazole was also mutagenic in a tester strain of Klebsiella pneumonia .
Tinidazole was negative for mutagenicity in a mammalian cell culture system utilizing Chinese hamster lung V79 cells (HGPRT test system) and negative for genotoxicity in the Chinese hamster ovary (CHO) sister chromatid exchange assay. Tinidazole was positive for in vivo genotoxicity in the mouse micronucleus assay. In a 60-day male rat fertility study, oral doses of 600 mg/kg (approximately 3-fold the highest human therapeutic dose based on body surface area conversions) reduced fertility and produced testicular histopathology, including tubular degeneration, vacuolation of the seminiferous epithelium in the testis, and hypospermia in the epididymis.
At 300 and 600 mg/kg dose levels, significant effects on sperm parameters were observed, including dose-related reduction in sperm motility, epididymal sperm numbers, percentage of normal sperm, retention of spermatids, and decreased epididymal weights. No effects on sperm parameters were observed at 100 mg/kg (approximately 0.5-fold the highest human therapeutic dose based upon body surface area conversions). This effect is characteristic of agents in the 5-nitroimidazole class.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis & Impairment of Fertility Metronidazole, a chemically-related nitroimidazole, has been reported to be carcinogenic in mice and rats but not hamsters. In several studies metronidazole showed evidence of pulmonary, hepatic, and lymphatic tumorigenesis in mice and mammary and hepatic tumors in female rats. Tinidazole carcinogenicity studies in rats, mice or hamsters have not been reported.
Tinidazole was mutagenic in the TA 100, S. typhimurium tester strain both with and without the metabolic activation system and was negative for mutagenicity in the TA 98 strain. Mutagenicity results were mixed (positive and negative) in the TA 1535, 1537, and 1538 strains. Tinidazole was also mutagenic in a tester strain of Klebsiella pneumonia .
Tinidazole was negative for mutagenicity in a mammalian cell culture system utilizing Chinese hamster lung V79 cells (HGPRT test system) and negative for genotoxicity in the Chinese hamster ovary (CHO) sister chromatid exchange assay. Tinidazole was positive for in vivo genotoxicity in the mouse micronucleus assay. In a 60-day male rat fertility study, oral doses of 600 mg/kg (approximately 3-fold the highest human therapeutic dose based on body surface area conversions) reduced fertility and produced testicular histopathology, including tubular degeneration, vacuolation of the seminiferous epithelium in the testis, and hypospermia in the epididymis.
At 300 and 600 mg/kg dose levels, significant effects on sperm parameters were observed, including dose-related reduction in sperm motility, epididymal sperm numbers, percentage of normal sperm, retention of spermatids, and decreased epididymal weights. No effects on sperm parameters were observed at 100 mg/kg (approximately 0.5-fold the highest human therapeutic dose based upon body surface area conversions). This effect is characteristic of agents in the 5-nitroimidazole class.
📄 Recent Major Changes ▾
RECENT MAJOR CHANGES Contraindications (4) 12/2021
📄 Package Label / Principal Display Panel ▾
Tinidazole Tablets, 250 mg 40 Tablets Tinidazole Tablets, 500 mg 20 Tablets Tinidazole Tablets, 500 mg 60 Tablets 250 mg 40 tablets 500 mg 20 tablets 500 mg 60 tablets
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |