
EPIPEN epinephrine .3 mg/.3mL Injection
Other active recalls for Epinephrine (different manufacturers) — 2 · tap to view
Past resolved recalls for this product (2)
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the alpha-Adrenergic Agonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Epinephrine injection is used along with emergency medical treatment to treat life-threatening allergic reactions caused by insect bites or stings, foods, medications, latex, and other causes. Epinephrine injection is also used to treat life-threatening low blood pressure associated with septic shock (a serious condition caused by a body-wide infection that can lead to dangerously low blood pressure and organ failure) in hospitalized patients. Epinephrine is in a class of medications called alpha- and beta-adrenergic agonists (sympathomimetic agents). It works by relaxing the muscles in the ai...
Read the full MedlinePlus article ↗- Epinephrine works fast but wears off quickly — sometimes in as little as 15 to 20 minutes. Anaphylaxis can come back (this is called a biphasic reaction), and you may need addition...
- Why do I need to go to the ER after using my EpiPen or Auvi-Q if I already feel better?
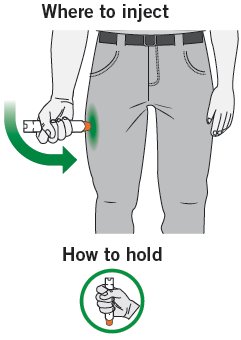
- Yes, it absolutely matters. Inject into the outer thigh — you can even go through your clothing if needed. Never inject into the buttocks (that spot carries a risk of serious infec...
- Where exactly do I inject it, and does it matter?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Epinephrine — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
UNII 4VON5FNS3C
Sodium metabisulfite is a preservative derived from sulfur compounds. It prevents microbial growth and oxidation in medicines, helping extend shelf life and maintain product stability.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $292.748 | $585.50 / 2 syringes |
| Medicaid paysCMS SDUD · 12 mo | $144.47 | $288.95 / 2 syringes |
| Medicare drug plans payPart D · Q2 2026 | $291.42 | $582.84 / 2 syringes |
| Medicare Part B allowsASP · J0165 | $0.234 / J0165 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Epinephrine 1 mg/mL 00093-5986-27 | Teva | 1 syringe | $132.829 | — | Availability likely | save 55% |
| Epinephrine .3 mg/.3mL 49502-0102-02 | Viatris | 1 syringe | $141.140 | AB | Availability likely | save 52% |
| Epipen .3 mg/.3mLthis 49502-0500-02 | Viatris | 1 syringe | $292.748 | AB | FDA listed | — |
| Auvi-Q .3 mg/.3mL 60842-0023-01 | kaleo, | 2 doses | $309.376 | BX | Discontinued | +6% |
| Epinephrine .3 mg/.3mL 50090-4543-00 | A-S | 1 ml | — | AB | FDA listed | — |
| Epinephrine .3 mg/.3mL 67296-1946-02 | Redpharm | 1 syringe | — | AB | FDA listed | — |
| Epinephrine 0.3 Adults .3 mg/.3mL 70385-2019-01 | Sina | 1 syringe | — | AB | FDA listed | — |
| Epinephrine .3 mg/.3mL 70518-2283-00 | REMEDYREPACK | 1 syringe | — | AB | FDA listed | — |
| Epinephrine .3 mg/.3mL 71872-7135-01 | Medical | 1 syringe | — | AB | FDA listed | — |
| Epinephrine .3 mg/.3mL 76420-0188-02 | Asclemed | 2 syringes | — | AB | FDA listed | — |
| Epipen .3 mg/.3mL 76420-0584-02 | Asclemed | 1 syringe | — | AB | FDA listed | — |
| Epinephrine .3 mg/.3mL 85766-0091-02 | Sportpharm | 1 syringe | — | AB | FDA listed | — |
| Epinephrine .3 mg/.3mL 51662-1224-01 | HF | 1 syringe | — | AB | FDA listed | — |
| Auvi-Q .3 mg/.3mL 71872-7173-01 | Medical | 1 dose | — | BX | FDA listed | — |
| Epinephrine .3 mg/.3mL 51662-1320-01 | HF | 3 ml | — | BX | FDA listed | — |
| Auvi-Q .3 mg/.3mL 71872-7329-01 | Medical | 1 dose | — | BX | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 49502-0500-02 You're viewing this | 2 CONTAINER in 1 CARTON (49502-500-02) / 1 SYRINGE, GLASS in 1 CONTAINER (49502-500-01) / .3 mL in 1 SYRINGE, GLASS | $292.75 / ea | $585.50 | 1987-12-22 | Active |
| 49502-0500-92 | 2 CONTAINER in 1 CARTON (49502-500-92) / 1 SYRINGE, GLASS in 1 CONTAINER / .3 mL in 1 SYRINGE, GLASS | — | — | 1987-12-22 | Active |
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 49502-0500-02?
What NDC number is used to bill for this package of EPIPEN epinephrine .3 mg/.3mL Injection?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE EpiPen and EpiPen Jr are indicated in the emergency treatment of allergic reactions (Type I) including anaphylaxis to stinging insects (e.g., order Hymenoptera, which include bees, wasps, hornets, yellow jackets and fire ants) and biting insects (e.g., triatoma, mosquitoes), allergen immunotherapy, foods, drugs, diagnostic testing substances (e.g., radiocontrast media) and other allergens, as well as idiopathic anaphylaxis or exercise-induced anaphylaxis. EpiPen and EpiPen Jr are intended for immediate administration in patients who are determined to be at increased risk for anaphylaxis, including individuals with a history of anaphylactic reactions.
Anaphylactic reactions may occur within minutes after exposure and consist of flushing, apprehension, syncope, tachycardia, thready or unobtainable pulse associated with a fall in blood pressure, convulsions, vomiting, diarrhea and abdominal cramps, involuntary voiding, wheezing, dyspnea due to laryngeal spasm, pruritus, rashes, urticaria or angioedema. EpiPen and EpiPen Jr are intended for immediate administration as emergency supportive therapy only and are not a substitute for immediate medical care. EpiPen and EpiPen Jr are non-selective alpha and beta-adrenergic receptor agonist indicated in the emergency treatment of allergic reactions (Type I) including anaphylaxis.
( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Patients greater than or equal to 30 kg (66 lbs): EpiPen 0.3 mg ( 2 ) • Patients 15 to 30 kg (33 lbs to 66 lbs): EpiPen Jr 0.15 mg ( 2 ) Inject intramuscularly or subcutaneously into the anterolateral aspect of the thigh, through clothing if necessary. Each device is a single-dose injection . ( 2 )
2.1Recommended Dosage According to Patient Body Weight • Patients greater than or equal to 30 kg (approximately 66 pounds or more): EpiPen 0.3 mg • Patients 15 kg to 30 kg (33 pounds to 66 pounds): EpiPen Jr 0.15 mg
2.2Administration Instructions • Inject the single-dose EpiPen or EpiPen Jr intramuscularly or subcutaneously into the anterolateral aspect of the thigh, through clothing if necessary. Do not inject intravenously, and do not inject into buttocks, into digits, hands or feet [see Warnings and Precautions (5.2) ]. • Instruct caregivers of young children who are prescribed an EpiPen or EpiPen Jr and who may be uncooperative and kick or move during an injection to hold the leg firmly in place and limit movement prior to and during an injection [see Warnings and Precautions (5.2) ] . • Each EpiPen or EpiPen Jr is a single-dose epinephrine injection for single use.
Since the doses of epinephrine delivered from EpiPen or EpiPen Jr are fixed, consider using other forms of injectable epinephrine if doses lower than 0.15 mg are deemed necessary. • With severe persistent anaphylaxis, repeat injections with an additional EpiPen or EpiPen Jr may be necessary. More than two sequential doses of epinephrine should only be administered under direct medical supervision [see Warnings and Precautions (5.1) ] . • The epinephrine solution in the clear window of the EpiPen or EpiPen Jr Auto-Injector should be inspected visually for particulate matter and discoloration.
Discarding After Use: The EpiPen and EpiPen Jr each contain 2 mL epinephrine solution. Approximately 1.7 mL remains in the auto-injector after activation, but is not available for future use, and should be discarded .
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS • Injection: 0.3 mg (0.3 mg/0.3 mL), clear and colorless solution in single-dose pre-filled auto-injector • Injection: 0.15 mg (0.15 mg/0.3 mL), clear and colorless solution in single-dose pre-filled auto-injector • Injection: 0.3 mg (0.3 mg/0.3 mL) single-dose pre-filled auto-injector ( 3 ) • Injection: 0.15 mg (0.15 mg/0.3 mL) single-dose pre-filled auto-injector ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None None ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • In conjunction with use, seek immediate medical or hospital care. ( 5.1 ) • Do not inject intravenously, into buttock, or into digits, hands, or feet. ( 5.2 ) • To minimize the risk of injection related injury, hold the child’s leg firmly in place and limit movement prior to and during injection when administering to young children.
( 5.2 ) • Rare cases of serious skin and soft tissue infections have been reported following epinephrine injection. Advise patients to seek medical care if they develop signs or symptoms of infection. ( 5.3 ) • The presence of a sulfite in this product should not deter use.
( 5.4 ) • Administer with caution in patients with heart disease; may aggravate angina pectoris or produce ventricular arrhythmias. ( 5.5 )
5.1Emergency Treatment EpiPen and EpiPen Jr are intended for immediate administration as emergency supportive therapy and are not intended as a substitute for immediate medical care. In conjunction with the administration of epinephrine, the patient should seek immediate medical or hospital care. More than two sequential doses of epinephrine should only be administered under direct medical supervision [ see Indications and Usage (1) , Dosage and Administration (2) and Patient Counseling Information (17) ].
5.2Injection-Related Complications EpiPen and EpiPen Jr should only be injected into the anterolateral aspect of the thigh [ see Dosage and Administration (2) and Patient Counseling Information (17) ]. Do not inject intravenously Large doses or accidental intravenous injection of epinephrine may result in cerebral hemorrhage due to sharp rise in blood pressure. Rapidly acting vasodilators can counteract the marked pressor effects of epinephrine if there is such inadvertent administration.
Do not inject into buttock Injection into the buttock may not provide effective treatment of anaphylaxis. Advise the patient to go immediately to the nearest emergency room for further treatment of anaphylaxis. Additionally, injection into the buttock has been associated with Clostridial infections (gas gangrene).
Cleansing with alcohol does not kill bacterial spores, and therefore, does not lower this risk. Do not inject into digits, hands or feet Since epinephrine is a strong vasoconstrictor, accidental injection into the digits, hands or feet may result in loss of blood flow to the affected area. Advise the patient to go immediately to the nearest emergency room and to inform the healthcare provider in the emergency room of the location of the accidental injection.
Treatment of such inadvertent administration should consist of vasodilation, in addition to further appropriate treatment of anaphylaxis [ see Adverse Reactions (6) ]. Hold leg firmly during injection Lacerations, bent needles, and embedded needles have been reported when EpiPen and EpiPen Jr have been injected into the thigh of young children who are uncooperative and kick or move during an injection. To minimize the risk of injection related injury when administering, hold the child’s leg firmly in place and limit movement prior to and during injection.
5.3Serious Infections at the Injection Site Rare cases of serious skin and soft tissue infections, including necrotizing fasciitis and myonecrosis caused by Clostridia (gas gangrene), have been reported at the injection site following epinephrine injection for anaphylaxis. Clostridium spores can be present on the skin and introduced into the deep tissue with subcutaneous or intramuscular injection. While cleansing with alcohol may reduce presence of bacteria on the skin, alcohol cleansing does not kill Clostridium spores.
To decrease the risk of Clostridium infection, do not inject EpiPen into the buttock [see Warnings and Precautions (5.2) ]. Advise patients to seek medical care if they develop signs or symptoms of infection, such as persistent redness, warmth, swelling, or tenderness, at the epinephrine injection site.
5.4 Allergic Reactions Associated with…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Due to the lack of randomized, controlled clinical trials of epinephrine for the treatment of anaphylaxis, the true incidence of adverse reactions associated with the systemic use of epinephrine is difficult to determine. Adverse reactions reported in observational trials, case reports, and studies are listed below. Common adverse reactions to systemically administered epinephrine include anxiety; apprehensiveness; restlessness; tremor; weakness; dizziness; sweating; palpitations; pallor; nausea and vomiting; headache; and/or respiratory difficulties.
These symptoms occur in some persons receiving therapeutic doses of epinephrine, but are more likely to occur in patients with hypertension or hyperthyroidism [ see Warnings and Precautions (5.5) ]. Cardiovascular Reactions • Arrhythmias, including fatal ventricular fibrillation, have been reported, particularly in patients with underlying cardiac disease or those receiving certain drugs [ see Warnings and Precautions (5.5) and Drug Interactions (7) ]. • Rapid rises in blood pressure have produced cerebral hemorrhage, particularly in elderly patients with cardiovascular disease [ see Warnings and Precautions (5.5) ]. • Angina may occur in patients with coronary artery disease [ see Warnings and Precautions (5.5) ]. • Rare cases of stress cardiomyopathy have been reported in patients treated with epinephrine.
Reactions from Accidental Injection and/or Improper Technique • Accidental injection into the digits, hands or feet may result in loss of blood flow to the affected area [ see Warnings and Precautions (5.2) ]. • Adverse reactions experienced as a result of accidental injections may include increased heart rate, local reactions including injection site pallor, coldness and hypoesthesia or injury at the injection site resulting in bruising, bleeding, discoloration, erythema or skeletal injury. • Lacerations, bent needles, and embedded needles have been reported when EpiPen has been injected into the thigh of young children who are uncooperative and kick or move during the injection [ see Warning and Precautions (5.2) ]. • Injection into the buttock has resulted in cases of gas gangrene [ see Warnings and Precautions (5.2) ] .
Skin and Soft Tissue Infections • Rare cases of serious skin and soft tissue infections, including necrotizing fasciitis and myonecrosis caused by Clostridia (gas gangrene), have been reported following epinephrine injection, including EpiPen, in the thigh [ see Warnings and Precautions (5.3) ]. Adverse reactions to epinephrine include anxiety, apprehensiveness, restlessness, tremor, weakness, dizziness, sweating, palpitations, pallor, nausea and vomiting, headache, and/or respiratory difficulties. ( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Mylan at 1-877-446-3679 (1-877-4-INFO-RX) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Cardiac Glycosides, Diuretics, and Anti-arrhythmics Patients who receive epinephrine while concomitantly taking cardiac glycosides, diuretics, or anti-arrhythmics should be observed carefully for the development of cardiac arrhythmias [see Warnings and Precautions (5.5) ] . Antidepressants, Monoamine Oxidase Inhibitors, Levothyroxine, and Antihistamines The effects of epinephrine may be potentiated by tricyclic antidepressants, monoamine oxidase inhibitors, levothyroxine sodium, and certain antihistamines, notably chlorpheniramine, tripelennamine, and diphenhydramine.
Beta-Adrenergic Blockers The cardiostimulating and bronchodilating effects of epinephrine are antagonized by beta- adrenergic blocking drugs, such as propranolol. Alpha-Adrenergic Blockers The vasoconstricting and hypertensive effects of epinephrine are antagonized by alpha- adrenergic blocking drugs, such as phentolamine. Ergot Alkaloids Ergot alkaloids may also reverse the pressor effects of epinephrine. • Cardiac glycosides or diuretics: observe for development of cardiac arrhythmias.
( 7 ) • Tricyclic antidepressants, monoamine oxidase inhibitors, levothyroxine sodium, and certain antihistamines potentiate effects of epinephrine. ( 7 ) • Beta-adrenergic blocking drugs antagonize cardiostimulating and bronchodilating effects of epinephrine. ( 7 ) • Alpha-adrenergic blocking drugs antagonize vasoconstricting and hypertensive effects of epinephrine.
( 7 ) • Ergot alkaloids may reverse the pressor effects of epinephrine. ( 7 )
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Elderly patients may be at greater risk of developing adverse reactions. ( 5.5 , 8.5 )
8.1Pregnancy Risk Summary There are no adequate and well controlled studies of the acute effect of epinephrine in pregnant women. In animal reproductive studies, epinephrine administered by the subcutaneous route to rabbits, mice, and hamsters during the period of organogenesis was teratogenic at doses 7 times and higher than the maximum recommended human intramuscular and subcutaneous dose on a mg/m 2 basis. Epinephrine is the first-line medication of choice for the treatment of anaphylaxis during pregnancy in humans.
Epinephrine should be used for treatment of anaphylaxis during pregnancy in the same manner as it is used in non-pregnant patients. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Disease-associated maternal and embryo/fetal risk During pregnancy, anaphylaxis can be catastrophic and can lead to hypoxic-ischemic encephalopathy and permanent central nervous system damage or death in the mother and, more commonly, in the fetus or neonate.
The prevalence of anaphylaxis occurring during pregnancy is reported to be approximately 3 cases per 100,000 deliveries. Management of anaphylaxis during pregnancy is similar to management in the general population. Epinephrine is the first line-medication of choice for treatment of anaphylaxis; it should be used in the same manner in pregnant and non-pregnant patients.
In conjunction with the administration of epinephrine, the patient should seek immediate medical or hospital care. Data Animal Data In an embryofetal development study with rabbits dosed during the period of organogenesis, epinephrine was shown to be teratogenic (including gastroschisis and embryonic lethality) at doses approximately 40 times the maximum recommended intramuscular or subcutaneous dose (on a mg/m 2 basis at a maternal subcutaneous dose of 1.2 mg/kg/day for two to three days). In an embryofetal development study with mice dosed during the period of organogenesis, epinephrine was shown to be teratogenic (including embryonic lethality) at doses approximately 8 times the maximum recommended intramuscular or subcutaneous dose (on a mg/m 2 basis at maternal subcutaneous dose of 1 mg/kg/day for 10 days).
These effects were not seen in mice at approximately 4 times the maximum recommended daily intramuscular or subcutaneous dose (on a mg/m 2 basis at a subcutaneous maternal dose of 0.5 mg/kg/day for 10 days). In an embryofetal development study with hamsters dosed during the period of organogenesis from gestation days 7 to 10, epinephrine was shown to be teratogenic at doses approximately 7 times the maximum recommended intramuscular or subcutaneous dose (on a mg/m 2 basis at a maternal subcutaneous dose of 0.5 mg/kg/day).
8.2Lactation Risk Summary There is no information on the presence of epinephrine in human milk, the effects on breastfed infants, or the effects on milk production. Epinephrine is the first line-medication of choice for treatment of anaphylaxis; it should be used in the same manner in breastfeeding and non-breastfeeding patients.
8.4Pediatric Use EpiPen or EpiPen Jr may be administered to pediatric patients at a dosage appropriate to body weight [ see Dosage and Administration (2.1) ] . Clinical experience with the use of epinephrine suggests that the adverse reactions seen in children are similar in nature and extent to those both expected and reported in adults. Since the doses of epinephrine delivered from EpiPen and EpiPen Jr are fixed, consider using other forms of injectable epinephrine if doses lower than 0.15 mg are deemed necessary.
8.5Geriatric Use Clinical studies for the treatment of anaphylaxis have not been performed in subjects aged 65 and over to determine whether they respond differently from younger…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no adequate and well controlled studies of the acute effect of epinephrine in pregnant women. In animal reproductive studies, epinephrine administered by the subcutaneous route to rabbits, mice, and hamsters during the period of organogenesis was teratogenic at doses 7 times and higher than the maximum recommended human intramuscular and subcutaneous dose on a mg/m 2 basis. Epinephrine is the first-line medication of choice for the treatment of anaphylaxis during pregnancy in humans.
Epinephrine should be used for treatment of anaphylaxis during pregnancy in the same manner as it is used in non-pregnant patients. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Disease-associated maternal and embryo/fetal risk During pregnancy, anaphylaxis can be catastrophic and can lead to hypoxic-ischemic encephalopathy and permanent central nervous system damage or death in the mother and, more commonly, in the fetus or neonate.
The prevalence of anaphylaxis occurring during pregnancy is reported to be approximately 3 cases per 100,000 deliveries. Management of anaphylaxis during pregnancy is similar to management in the general population. Epinephrine is the first line-medication of choice for treatment of anaphylaxis; it should be used in the same manner in pregnant and non-pregnant patients.
In conjunction with the administration of epinephrine, the patient should seek immediate medical or hospital care. Data Animal Data In an embryofetal development study with rabbits dosed during the period of organogenesis, epinephrine was shown to be teratogenic (including gastroschisis and embryonic lethality) at doses approximately 40 times the maximum recommended intramuscular or subcutaneous dose (on a mg/m 2 basis at a maternal subcutaneous dose of 1.2 mg/kg/day for two to three days). In an embryofetal development study with mice dosed during the period of organogenesis, epinephrine was shown to be teratogenic (including embryonic lethality) at doses approximately 8 times the maximum recommended intramuscular or subcutaneous dose (on a mg/m 2 basis at maternal subcutaneous dose of 1 mg/kg/day for 10 days).
These effects were not seen in mice at approximately 4 times the maximum recommended daily intramuscular or subcutaneous dose (on a mg/m 2 basis at a subcutaneous maternal dose of 0.5 mg/kg/day for 10 days). In an embryofetal development study with hamsters dosed during the period of organogenesis from gestation days 7 to 10, epinephrine was shown to be teratogenic at doses approximately 7 times the maximum recommended intramuscular or subcutaneous dose (on a mg/m 2 basis at a maternal subcutaneous dose of 0.5 mg/kg/day).
🧒 Pediatric Use ▾
8.4Pediatric Use EpiPen or EpiPen Jr may be administered to pediatric patients at a dosage appropriate to body weight [ see Dosage and Administration (2.1) ] . Clinical experience with the use of epinephrine suggests that the adverse reactions seen in children are similar in nature and extent to those both expected and reported in adults. Since the doses of epinephrine delivered from EpiPen and EpiPen Jr are fixed, consider using other forms of injectable epinephrine if doses lower than 0.15 mg are deemed necessary.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies for the treatment of anaphylaxis have not been performed in subjects aged 65 and over to determine whether they respond differently from younger subjects. However, other reported clinical experience with use of epinephrine for the treatment of anaphylaxis has identified that geriatric patients may be particularly sensitive to the effects of epinephrine. Therefore, EpiPen should be administered with caution in elderly individuals, who may be at greater risk for developing adverse reactions after epinephrine administration [ see Warnings and Precautions (5.5) , Overdosage (10) ].
🆘 Overdosage ▾
10 OVERDOSAGE Overdosage of epinephrine may produce extremely elevated arterial pressure, which may result in cerebrovascular hemorrhage, particularly in elderly patients. Overdosage may also result in pulmonary edema because of peripheral vascular constriction together with cardiac stimulation. Treatment consists of rapidly acting vasodilators or alpha-adrenergic blocking drugs and/or respiratory support.
Epinephrine overdosage can also cause transient bradycardia followed by tachycardia, and these may be accompanied by potentially fatal cardiac arrhythmias. Premature ventricular contractions may appear within one minute after injection and may be followed by multifocal ventricular tachycardia (prefibrillation rhythm). Subsidence of the ventricular effects may be followed by atrial tachycardia and occasionally by atrioventricular block.
Treatment of arrhythmias consists of administration of a beta-adrenergic blocking drug such as propranolol. Overdosage sometimes results in extreme pallor and coldness of the skin, metabolic acidosis, and kidney failure. Suitable corrective measures must be taken in such situations.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Epinephrine acts on both alpha- and beta-adrenergic receptors.
12.2Pharmacodynamics Through its action on alpha-adrenergic receptors, epinephrine lessens the vasodilation and increased vascular permeability that occurs during anaphylaxis, which can lead to loss of intravascular fluid volume and hypotension. Through its action on beta-adrenergic receptors, epinephrine causes bronchial smooth muscle relaxation and helps alleviate bronchospasm, wheezing and dyspnea that may occur during anaphylaxis. Epinephrine also alleviates pruritus, urticaria, and angioedema and may relieve gastrointestinal and genitourinary symptoms associated with anaphylaxis because of its relaxer effects on the smooth muscle of the stomach, intestine, uterus and urinary bladder.
When given subcutaneously or intramuscularly, epinephrine has a rapid onset and short duration of action.
🧬 Mechanism of Action ▾
12.1Mechanism of Action Epinephrine acts on both alpha- and beta-adrenergic receptors.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING How Supplied • EpiPen 2-Pak (epinephrine) injection is supplied with 2 single-dose pre-filled auto-injectors and 1 auto-injector trainer device: 0.3 mg/0.3 mL (NDC 49502-500-02) • EpiPen Jr 2-Pak (epinephrine) injection is supplied with 2 single-dose pre-filled auto-injectors and 1 auto-injector trainer device: 0.15 mg/0.3 mL (NDC 49502-501-02) EpiPen 2-Pak ® and EpiPen Jr 2-Pak ® also include an S-clip to clip two carrier tubes together. Storage and Handling • Protect from light.
Epinephrine is light sensitive and should be stored in the carrier tube provided to protect it from light. • Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [See USP Controlled Room Temperature]. • Do not refrigerate. • Before using, check to make sure the solution in the auto-injector is clear and colorless. • Replace the auto-injector if the solution is discolored (pinkish or brown color), cloudy, or contains particle. • Properly dispose all used, unwanted or expired EpiPen and EpiPen Jr auto-injectors.
📋 Description ▾
11 DESCRIPTION EpiPen (epinephrine injection, USP) 0.3 mg and EpiPen Jr (epinephrine injection, USP) 0.15 mg are single-dose auto-injectors and combination products containing drug and device components. Each EpiPen Auto-Injector, 0.3 mg delivers a single dose of 0.3 mg epinephrine from epinephrine injection, USP 0.3 mg/0.3 mL in a sterile solution. Each EpiPen Jr Auto-Injector, 0.15 mg delivers a single dose of 0.15 mg epinephrine from epinephrine injection, USP 0.15 mg/0.3 mL in a sterile solution.
Each 0.3 mL in the EpiPen Auto-Injector contains 0.3 mg epinephrine, 1.8 mg sodium chloride, 0.5 mg sodium metabisulfite, hydrochloric acid to adjust pH, and Water for Injection. The pH range is 2.2-5.0. Each 0.3 mL in the EpiPen Jr Auto-Injector contains 0.15 mg epinephrine, 1.8 mg sodium chloride, 0.5 mg sodium metabisulfite, hydrochloric acid to adjust pH, and Water for Injection.
The pH range is 2.2-5.0. Epinephrine is a sympathomimetic catecholamine. Chemically, epinephrine is (-)-3,4- Dihydroxy-α-[(methylamino)methyl]benzyl alcohol with the following structure: Epinephrine solution deteriorates rapidly on exposure to air or light, turning pink from oxidation to adrenochrome and brown from the formation of melanin.
Replace EpiPen and EpiPen Jr if the epinephrine solution appears discolored (pinkish or brown color), cloudy, or contains particles. Thoroughly review the patient instructions and operation of EpiPen or EpiPen Jr with patients and caregivers prior to use [ see Patient Counseling Information (17) ]. Epinephrine Structural Formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION See FDA-Approved Patient Labeling ( Error! Hyperlink reference not valid. ) A healthcare provider should review the patient instructions and operation of EpiPen and EpiPen Jr in detail, with the patient or caregiver. Epinephrine is essential for the treatment of anaphylaxis.
Patients who are at risk of or with a history of severe allergic reactions (anaphylaxis) to insect stings or bites, foods, drugs, and other allergens, as well as idiopathic and exercise-induced anaphylaxis, should be carefully instructed about the circumstances under which epinephrine should be used. Administration Instruct patients and/or caregivers in the appropriate use of EpiPen and EpiPen Jr. EpiPen should be injected into the middle of the outer thigh (through clothing, if necessary).
Each device is a single-use injection. Advise patients to seek immediate medical care in conjunction with administration of EpiPen. Instruct caregivers to hold the leg of young children firmly in place and limit movement prior to and during injection.
Lacerations, bent needles, and embedded needles have been reported when EpiPen and EpiPen Jr have been injected into the thigh of young children who are uncooperative and kick or move during an injection [ see Warnings and Precautions (5.2) ]. Instruct patients and/or caregivers to throw away the blue safety release immediately after using EpiPen and EpiPen Jr. This small part may pose a choking hazard for children.
Complete patient information, including dosage, directions for proper administration and precautions can be found inside each EpiPen or EpiPen Jr carton. A printed label on the surface of EpiPen shows instructions for use and a diagram depicting the injection process. Training Instruct patients and/or caregivers to use and practice with the Trainer to familiarize themselves with the use of EpiPen in an allergic emergency.
The Trainer may be used multiple times. A Trainer device is provided in 2-Pak cartons. Instruct patients and/or caregivers to immediately place the blue safety release back on the Trainer and reset it after practicing.
This small part may pose a choking hazard for children. Adverse Reactions Epinephrine may produce symptoms and signs that include an increase in heart rate, the sensation of a more forceful heartbeat, palpitations, sweating, nausea and vomiting, difficulty breathing, pallor, dizziness, weakness or shakiness, headache, apprehension, nervousness, or anxiety. These signs and symptoms usually subside rapidly, especially with rest, quiet and recumbency.
Patients with hypertension or hyperthyroidism may develop more severe or persistent effects, and patients with coronary artery disease could experience angina. Patients with diabetes may develop increased blood glucose levels following epinephrine administration. Patients with Parkinson’s disease may notice a temporary worsening of symptoms [ see Warnings and Precautions (5.5) ] .
Accidental Injection Advise patients to seek immediate medical care in the case of accidental injection. Since epinephrine is a strong vasoconstrictor when injected into the digits, hands, or feet, treatment should be directed at vasodilatation if there is such an accidental injection to these areas [ see Warnings and Precautions (5.2) ]. Serious Infections at the Injection Site Rare cases of serious skin and soft tissue infections, including necrotizing fasciitis and myonecrosis caused by Clostridia (gas gangrene), have been reported at the injection site following epinephrine injection for anaphylaxis.
Advise patients to seek medical care if they develop signs or symptoms of infection, such as persistent redness, warmth, swelling, or tenderness, at the epinephrine injection site [ see Warnings and Precautions (5.3) ]. Storage and Handling Instruct patients to inspect the epinephrine solution visually through the clear window of the auto-injector periodically. Replace EpiPen and EpiPen Jr if the epinephrine solution appears…