
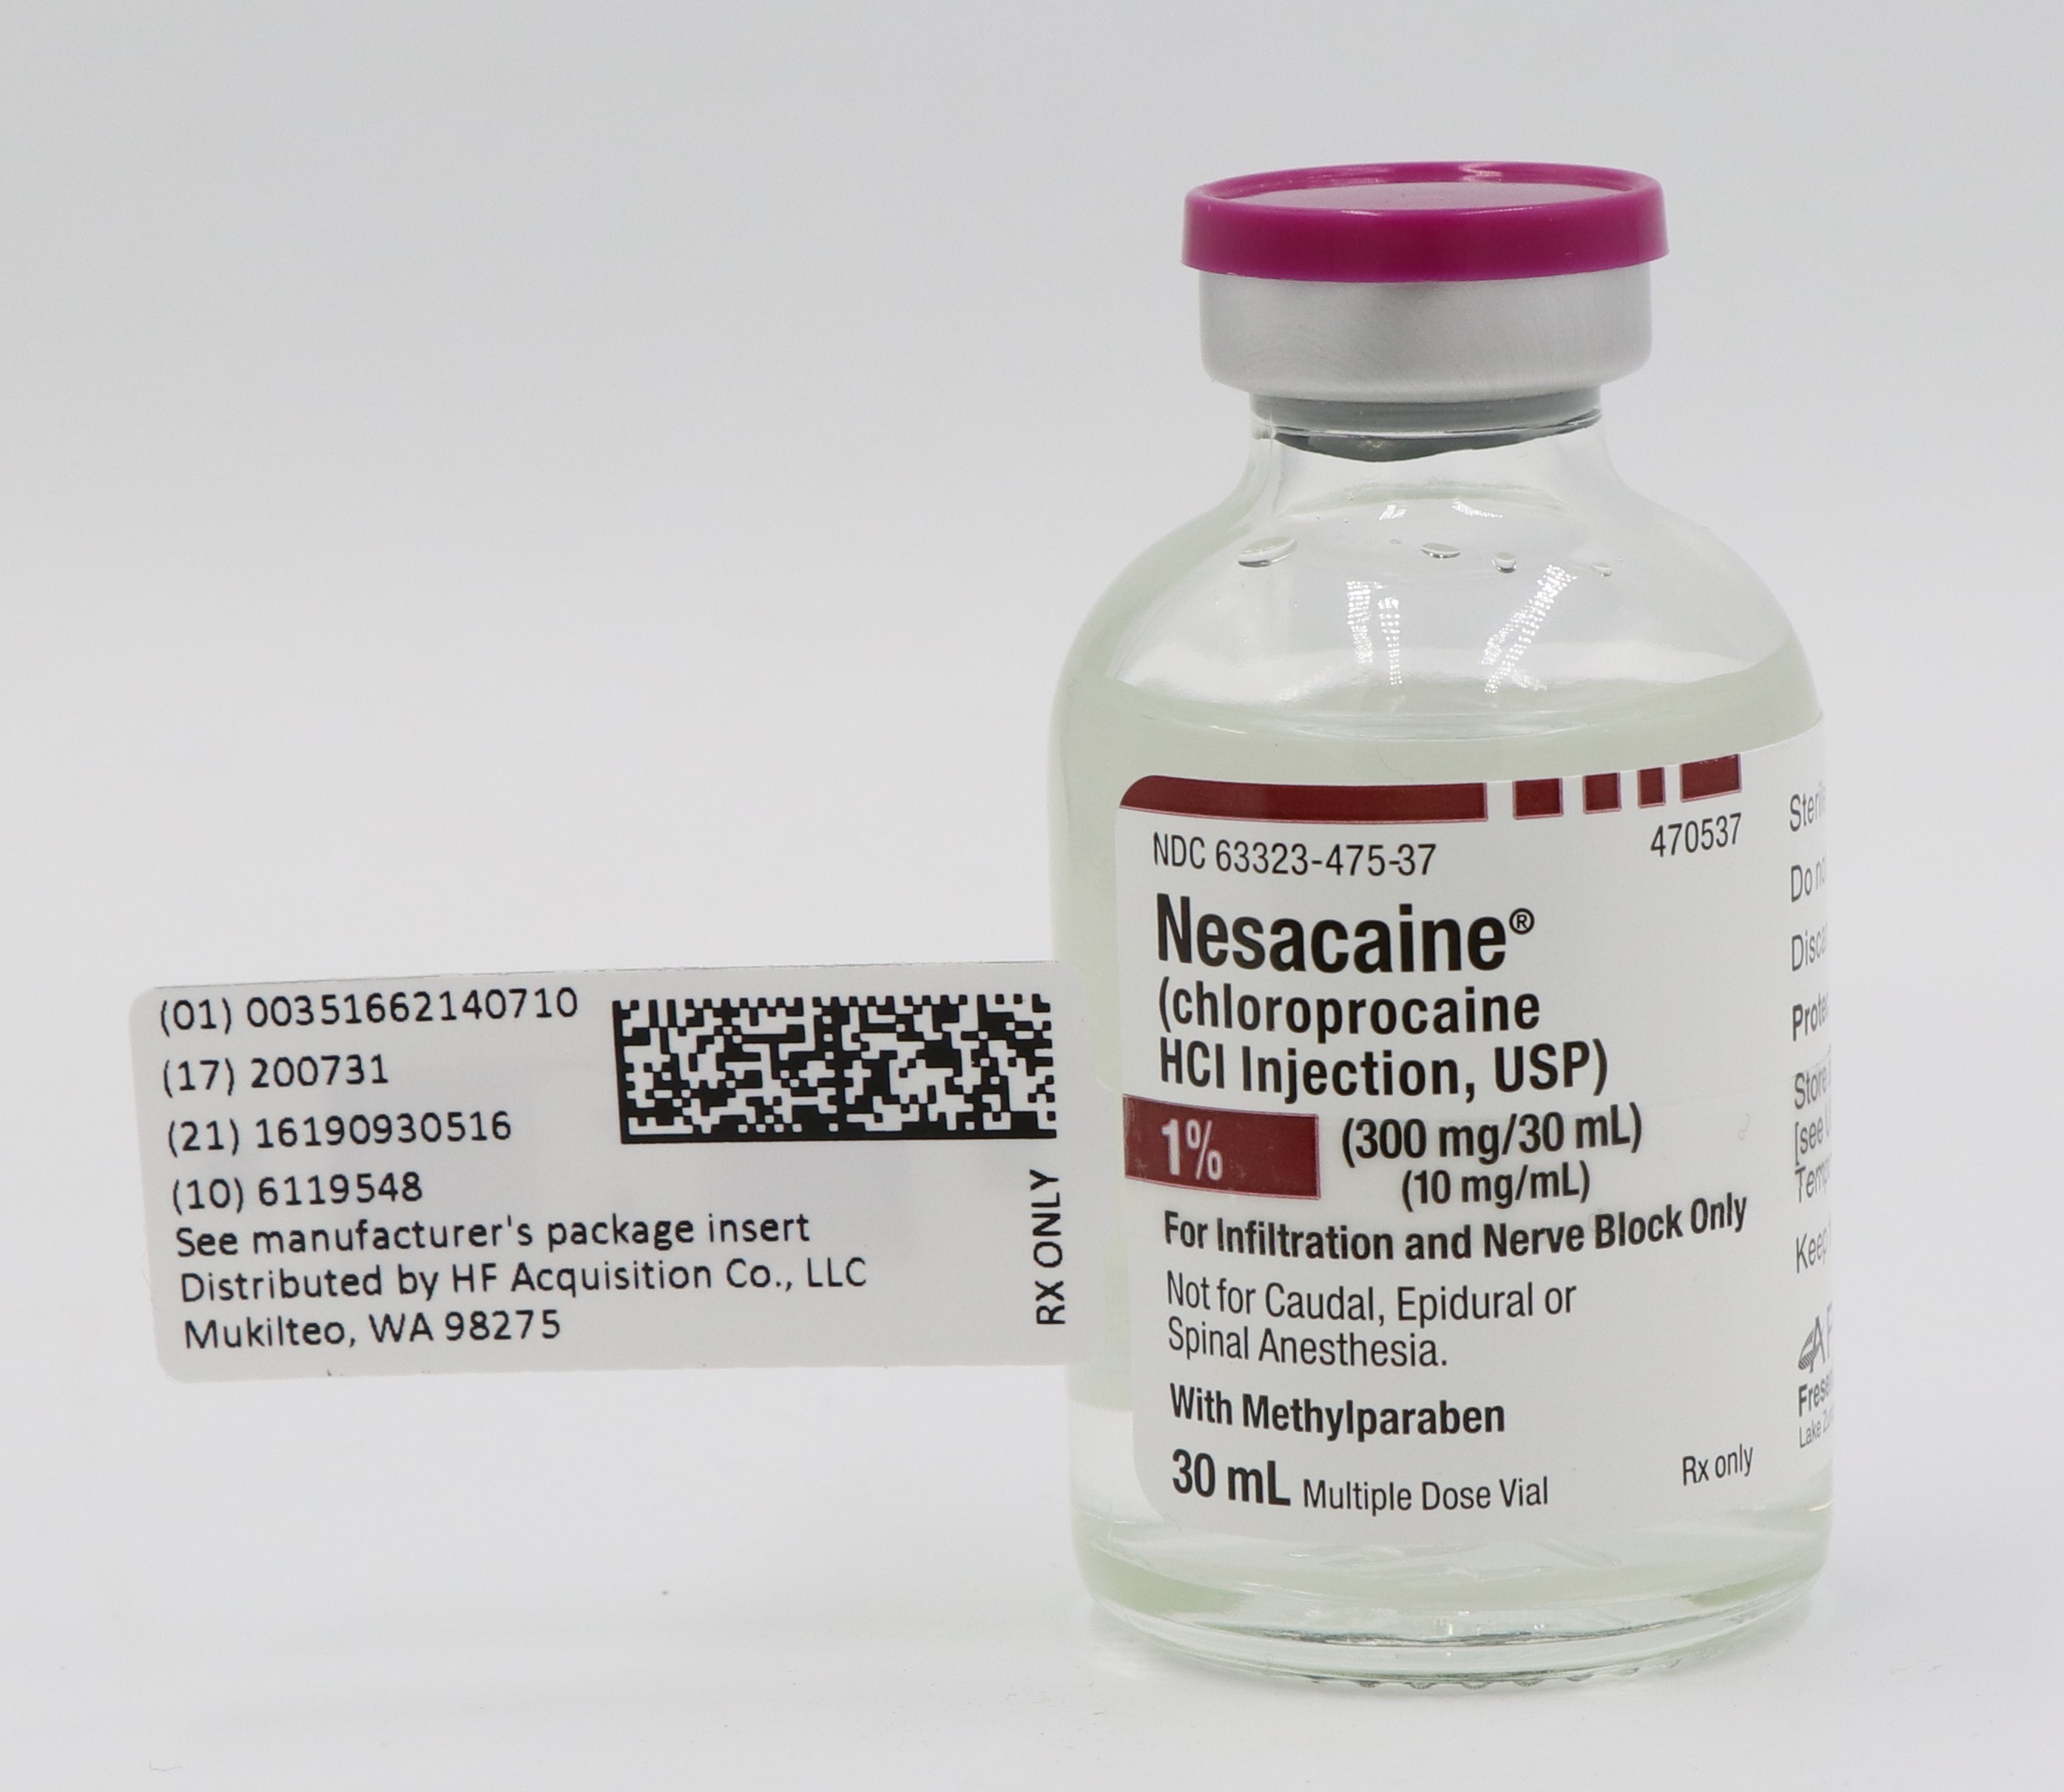
(CHLOROPROCAINE HCI 10 mg/mL Injection, Solution, 30 mL — NDC 51662-1407-1 (Billing 51662-1407-01)
This is a package of 30 mL of (CHLOROPROCAINE HCI 10 mg/mL Injection, Solution from HF Acquisition Co LLC, DBA HealthFirst, marketed since Oct 2019 and currently FDA-listed. It is the main listing for this product, which comes in 2 package sizes.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
- RxCUI (RxNorm): 992801
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Ester Local Anesthetic class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It numbs an area so a procedure doesn't hurt. The injection forms are used for nerve blocks and numbing tissue, and Iheezo is used to numb the surface of the eye. Your provider cho...
- It works fast, usually in about 6 to 12 minutes. Numbness can last up to an hour, depending on how much is used and where it is given.
- How long does it take to work and how long does it last?
- No. A healthcare provider gives it. Iheezo in particular is not meant for self-administration, and it should never be injected.
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J2401 | $0.042 / J2401 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 51662-1407-01 You're viewing this Main listing | 30 mL in 1 VIAL, MULTI-DOSE | 2019-10-13 | — | Active |
| 51662-1407-03 51662-1407-3 | 25 POUCH in 1 CASE / 1 VIAL, MULTI-DOSE in 1 POUCH / 30 mL in 1 VIAL, MULTI-DOSE | 2022-10-01 | — | Active |
Pack size FAQ
What quantity is in this package?
What NDC number is used to bill for this package of (CHLOROPROCAINE HCI 10 mg/mL Injection, Solution?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| (Chloroprocaine Hci 10 mg/mLthis 51662-1407-01 | HF | 30 ml | — | AP | FDA listed | — |
| Nesacaine 10 mg/mL 63323-0475-37 | Fresenius | 25 vials | — | AP | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
0.111 mg / 1 mL
UNII 7FLD91C86K
Edetate disodium is a chemical compound that binds and removes certain metal ions. In medicines, it acts as a preservative and stabilizer by preventing metals like calcium from interfering with the product's shelf life and consistency.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
1 mg / 1 mL
UNII A2I8C7HI9T
Methylparaben is a preservative derived from benzoic acid that prevents growth of bacteria, fungi, and mold in medicines. It extends the product's shelf life and maintains safety during storage.
-
6.7 mg / 1 mL
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS & USAGE Nesacaine 1% and 2% Injections, in multidose vials with methylparaben as preservative, are indicated for the production of local anesthesia by infiltration and peripheral nerve block. They are not to be used for lumbar or caudal epidural anesthesia. Nesacaine-MPF 2% and 3% Injections, in single dose vials without preservative and without EDTA, are indicated for the production of local anesthesia by infiltration, peripheral and central nerve block, including lumbar and caudal epidural blocks.
Nesacaine and Nesacaine-MPF Injections are not to be used for subarachnoid administration.
⏱️ Dosage and Administration ▾
DOSAGE & ADMINISTRATION Chloroprocaine may be administered as a single injection or continuously through an indwelling catheter. As with all local anesthetics, the dose administered varies with the anesthetic procedure, the vascularity of the tissues, the depth of anesthesia and degree of muscle relaxation required, the duration of anesthesia desired, and the physical condition of the patient. The smallest dose and concentration required to produce the desired result should be used.
Dosage should be reduced for children, elderly and debilitated patients and patients with cardiac and/or liver disease. The maximum single recommended doses of chloroprocaine in adults are: without epinephrine, 11 mg/kg, not to exceed a maximum total dose of 800 mg; with epinephrine (1:200,000), 14 mg/kg, not to exceed a maximum total dose of 1000 mg. For specific techniques and procedures, refer to standard textbooks.
There have been adverse event reports of chondrolysis in patients receiving intra-articular infusions of local anesthetics following arthroscopic and other surgical procedures. Nesacaine is not approved for this use (see WARNINGS and DOSAGE & ADMINISTRATION ). Caudal and Lumbar Epidural Block: In order to guard against adverse experiences sometimes noted following unintended penetration of the subarachnoid space, the following procedure modifications are recommended: Use an adequate test dose (3 mL of Nesacaine-MPF 3% Injection or 5 mL of Nesacaine-MPF 2% Injection) prior to induction of complete block.
This test dose should be repeated if the patient is moved in such a fashion as to have displaced the epidural catheter. Allow adequate time for onset of anesthesia following administration of each test dose. Avoid the rapid injection of a large volume of local anesthetic injection through the catheter.
Consider fractional doses, when feasible. In the event of the known injection of a large volume of local anesthetic injection into the subarachnoid space, after suitable resuscitation and if the catheter is in place, consider attempting the recovery of drug by draining a moderate amount of cerebrospinal fluid (such as 10 mL) through the epidural catheter. As a guide for some routine procedures, suggested doses are given below: Infiltration and Peripheral Nerve Block: NESACAINE or NESACAINE-MPF (chloroprocaine HCl Injection, USP) 2.
Caudal and Lumbar Epidural Block: NESACAINE-MPF INJECTION. For caudal anesthesia, the initial dose is 15 to 25 mL of a 2% or 3% solution. Repeated doses may be given at 40 to 60 minute intervals.
For lumbar epidural anesthesia, 2 to 2.5 mL per segment of a 2% or 3% solution can be used. The usual total volume of Nesacaine-MPF Injection is from 15 to 25 mL. Repeated doses 2 to 6 mL less than the original dose may be given at 40 to 50 minute intervals.
The above dosages are recommended as a guide for use in the average adult. Maximum dosages of all local anesthetics must be individualized after evaluating the size and physical condition of the patient and the rate of systemic absorption from a particular injection site. Pediatric Dosage: It is difficult to recommend a maximum dose of any drug for children, since this varies as a function of age and weight.
For children over 3 years of age who have a normal lean body mass and normal body development, the maximum dose is determined by the child’s age and weight and should not exceed 11 mg/kg (5 mg/lb). For example, in a child of 5 years weighing 50 lbs (23 kg), the dose of chloroprocaine HCl without epinephrine would be 250 mg. Concentrations of 0.5 to 1% are suggested for infiltration and 1 to 1.5% for nerve block.
In order to guard against systemic toxicity, the lowest effective concentration and lowest effective dose should be used at all times. Some of the lower concentrations for use in infants and smaller children are not available in prepackaged containers; it will be necessary to dilute available concentrations with the amount of 0.9% sodium chloride inje… [Excerpted — this section continues on DailyMed.]
⛔ Contraindications ▾
CONTRAINDICATIONS Nesacaine and Nesacaine-MPF Injections are contraindicated in patients hypersensitive (allergic) to drugs of the PABA ester group. Lumbar and caudal epidural anesthesia should be used with extreme caution in persons with the following conditions: existing neurological disease, spinal deformities, septicemia, and severe hypertension.
⚠️ Warnings ▾
WARNINGS LOCAL ANESTHETICS SHOULD ONLY BE EMPLOYED BY CLINICIANS WHO ARE WELL VERSED IN DIAGNOSIS AND MANAGEMENT OF DOSE RELATED TOXICITY AND OTHER ACUTE EMERGENCIES WHICH MIGHT ARISE FROM THE BLOCK TO BE EMPLOYED, AND THEN ONLY AFTER ENSURING THE IMMEDIATE AVAILABILITY OF OXYGEN, OTHER RESUSCITATIVE DRUGS, CARDIOPULMONARY RESUSCITATIVE EQUIPMENT, AND THE PERSONNEL RESOURCES NEEDED FOR PROPER MANAGEMENT OF TOXIC REACTIONS AND RELATED EMERGENCIES (see also ADVERSE REACTIONS and PRECAUTIONS ). DELAY IN PROPER MANAGEMENT OF DOSE RELATED TOXICITY, UNDERVENTILATION FROM ANY CAUSE AND/OR ALTERED SENSITIVITY MAY LEAD TO THE DEVELOPMENT OF ACIDOSIS, CARDIAC ARREST AND, POSSIBLY, DEATH.
NESACAINE (chloroprocaine HCl Injection, USP) contains methylparaben and should not be used for lumbar or caudal epidural anesthesia because safety of this antimicrobial preservative has not been established with regard to intrathecal injection, either intentional or unintentional. NESACAINE-MPF Injection contains no preservative; discard unused injection remaining in vial after initial use. Intra-articular infusions of local anesthetics following arthroscopic and other surgical procedures is an unapproved use, and there have been post-marketing reports of chondrolysis in patients receiving such infusions.
The majority of reported cases of chondrolysis have involved the shoulder joint; cases of gleno-humeral chondrolysis have been described in pediatric and adult patients following intra-articular infusions of local anesthetics with and without epinephrine for periods of 48 to 72 hours. There is insufficient information to determine whether shorter infusion periods are not associated with these findings. The time of onset of symptoms, such as joint pain, stiffness and loss of motion can be variable, but may begin as early as the 2nd month after surgery.
Currently, there is no effective treatment for chondrolysis; patients who experienced chondrolysis have required additional diagnostic and therapeutic procedures and some required arthroplasty or shoulder replacement. Vasopressors should not be used in the presence of ergot-type oxytocic drugs, since a severe persistent hypertension may occur. To avoid intravascular injection, aspiration should be performed before the anesthetic solution is injected.
The needle must be repositioned until no blood return can be elicited. However, the absence of blood in the syringe does not guarantee that intravascular injection has been avoided. Mixtures of local anesthetics are sometimes employed to compensate for the slower onset of one drug and the shorter duration of action of the second drug.
Experiments in primates suggest that toxicity is probably additive when mixtures of local anesthetics are employed, but some experiments in rodents suggest synergism. Caution regarding toxic equivalence should be exercised when mixtures of local anesthetics are employed.
METHEMOGLOBINEMIA Cases of methemoglobinemia have been reported in association with local anesthetic use. Although all patients are at risk for methemoglobinemia, patients with glucose- 6-phosphate dehydrogenase deficiency, congenital or idiopathic methemoglobinemia, cardiac or pulmonary compromise, infants under 6 months of age, and concurrent exposure to oxidizing agents or their metabolites are more susceptible to developing clinical manifestations of the condition. If local anesthetics must be used in these patients, close monitoring for symptoms and signs of methemoglobinemia is recommended.
Signs of methemoglobinemia may occur immediately or may be delayed some hours after exposure, and are characterized by a cyanotic skin discoloration and/or abnormal coloration of the blood. Methemoglobin levels may continue to rise; therefore, immediate treatment is required to avert more serious central nervous system and cardiovascular adverse effects, including seizures, coma, arrhythmias, and death. Discontinue NESACAINE and any other oxidizing agents.
Depending o… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Systemic: The most commonly encountered acute adverse experiences that demand immediate countermeasures are related to the central nervous system and the cardiovascular system. These adverse experiences are generally dose related and may result from rapid absorption from the injection site, diminished tolerance, or from unintentional intravascular injection of the local anesthetic solution. In addition to systemic dose-related toxicity, unintentional subarachnoid injection of drug during the intended performance of caudal or lumbar epidural block or nerve blocks near the vertebral column (especially in the head and neck region) may result in underventilation or apnea (“Total Spinal”).
Factors influencing plasma protein binding, such as acidosis, systemic diseases that alter protein production, or competition of other drugs for protein binding sites, may diminish individual tolerance. Plasma cholinesterase deficiency may also account for diminished tolerance to ester-type local anesthetics. Central Nervous System Reactions: These are characterized by excitation and/or depression.
Restlessness, anxiety, dizziness, tinnitus, blurred vision or tremors may occur, possibly proceeding to convulsions. However, excitement may be transient or absent, with depression being the first manifestation of an adverse reaction. This may quickly be followed by drowsiness merging into unconsciousness and respiratory arrest.
The incidence of convulsions associated with the use of local anesthetics varies with the procedure used and the total dose administered. In a survey of studies of epidural anesthesia, overt toxicity progressing to convulsions occurred in approximately 0.1 percent of local anesthetic administrations. Cardiovascular System Reactions: High doses, or unintended intravascular injection, may lead to high plasma levels and related depression of the myocardium, hypotension, bradycardia, ventricular arrhythmias, and, possibly, cardiac arrest.
Allergic: Allergic type reactions are rare and may occur as a result of sensitivity to the local anesthetic or to other formulation ingredients, such as the antimicrobial preservative methylparaben, contained in multiple dose vials. These reactions are characterized by signs such as urticaria, pruritus, erythema, angioneurotic edema (including laryngeal edema), tachycardia, sneezing, nausea, vomiting, dizziness, syncope, excessive sweating, elevated temperature, and possibly, anaphylactoid type symptomatology (including severe hypotension).
Cross sensitivity among members of the ester-type local anesthetic group has been reported. The usefulness of screening for sensitivity has not been definitely established. Neurologic: In the practice of caudal or lumbar epidural block, occasional unintentional penetration of the subarachnoid space by the catheter may occur (see PRECAUTIONS ).
Subsequent adverse observations may depend partially on the amount of drug administered intrathecally. These observations may include spinal block of varying magnitude (including total spinal block), hypotension secondary to spinal block, loss of bladder and bowel control, and loss of perineal sensation and sexual function. Arachnoiditis, persistent motor, sensory and/or autonomic (sphincter control) deficit of some lower spinal segments with slow recovery (several months) or incomplete recovery have been reported in rare instances (see DOSAGE & ADMINISTRATION discussion of Caudal and Lumbar Epidural Block).
Backache and headache have also been noted following lumbar epidural or caudal block.
🆘 Overdosage ▾
OVERDOSAGE Acute emergencies from local anesthetics are generally related to high plasma levels encountered during therapeutic use of local anesthetics or to unintended subarachnoid injection of local anesthetic solution (see ADVERSE REACTIONS , WARNINGS and PRECAUTIONS ). In mice, the intravenous LD 50 of chloroprocaine HCl is 97 mg/kg and the subcutaneous LD 50 of chloroprocaine HCl is 950 mg/kg. Management of Local Anesthetic Emergencies: The first consideration is prevention, best accomplished by careful and constant monitoring of cardiovascular and respiratory vital signs and the patient’s state of consciousness after each local anesthetic injection.
At the first sign of change, oxygen should be administered. The first step in the management of convulsions, as well as underventilation or apnea due to unintentional subarachnoid injection of drug solution, consists of immediate attention to the maintenance of a patent airway and assisted or controlled ventilation with oxygen and a delivery system capable of permitting immediate positive airway pressure by mask. Immediately after the institution of these ventilatory measures, the adequacy of the circulation should be evaluated, keeping in mind that drugs used to treat convulsions sometimes depress the circulation when administered intravenously.
Should convulsions persist despite adequate respiratory support, and if the status of the circulation permits, small increments of an ultra-short acting barbiturate (such as thiopental or thiamylal) or a benzodiazepine (such as diazepam) may be administered intravenously; the clinician should be familiar, prior to the use of anesthetics, with these anticonvulsant drugs. Supportive treatment of circulatory depression may require administration of intravenous fluids and, when appropriate, a vasopressor dictated by the clinical situation (such as ephedrine to enhance myocardial contractile force).
If not treated immediately, both convulsions and cardiovascular depression can result in hypoxia, acidosis, bradycardia, arrhythmias and cardiac arrest. Underventilation or apnea due to unintentional subarachnoid injection of local anesthetic solution may produce these same signs and also lead to cardiac arrest if ventilatory support is not instituted. If cardiac arrest should occur, standard cardiopulmonary resuscitative measures should be instituted.
Recovery has been reported after prolonged resuscitative efforts. Endotracheal intubation, employing drugs and techniques familiar to the clinician, may be indicated, after initial administration of oxygen by mask, if difficulty is encountered in the maintenance of a patent airway or if prolonged ventilatory support (assisted or controlled) is indicated.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Chloroprocaine, like other local anesthetics, blocks the generation and the conduction of nerve impulses, presumably by increasing the threshold for electrical excitation in the nerve, by slowing the propagation of the nerve impulse and by reducing the rate of rise of the action potential. In general, the progression of anesthesia is related to the diameter, myelination and conduction velocity of affected nerve fibers. Clinically, the order of loss of nerve function is as follows: (1) pain, (2) temperature, (3) touch, (4) proprioception, and (5) skeletal muscle tone.
Systemic absorption of local anesthetics produces effects on the cardiovascular and central nervous systems. At blood concentrations achieved with normal therapeutic doses, changes in cardiac conduction, excitability, refractoriness, contractility, and peripheral vascular resistance are minimal. However, toxic blood concentrations depress cardiac conduction and excitability, which may lead to atrioventricular block and ultimately to cardiac arrest.
In addition, with toxic blood concentrations myocardial contractility may be depressed and peripheral vasodilation may occur, leading to decreased cardiac output and arterial blood pressure. Following systemic absorption, toxic blood concentrations of local anesthetics can produce central nervous system stimulation, depression, or both. Apparent central stimulation may be manifested as restlessness, tremors and shivering, which may progress to convulsions.
Depression and coma may occur, possibly progressing ultimately to respiratory arrest. However, the local anesthetics have a primary depressant effect on the medulla and on higher centers. The depressed stage may occur without a prior stage of central nervous system stimulation.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED NESACAINE(R) (CHLOROPROCAINE HCI INJECTION, USP) is supplied in the following dosage forms. NDC 51662-1407-1 NESACAINE(R) (CHLOROPROCAINE HCI INJECTION, USP) 1% (300mg per 30mL) (10mg per mL) 30mL VIAL NDC 51662-1407-2 NESACAINE(R) (CHLOROPROCAINE HCI INJECTION, USP) 1% (300mg per 30mL) (10mg per mL) 30mL VIAL IN A POUCH NDC 51662-1407-3 NESACAINE(R) (CHLOROPROCAINE HCI INJECTION, USP) 1% (300mg per 30mL) (10mg per mL) 30mL VIAL IN A POUCH, 25 POUCHES PER CASE HF Acquisition Co LLC, DBA HealthFirst Mukilteo, WA 98275 For single-dose vials: Discard unused portion.
Keep from freezing. Protect from light. Store at 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature].
📋 Description ▾
DESCRIPTION Nesacaine and Nesacaine-MPF Injections are sterile non-pyrogenic local anesthetics. The active ingredient in Nesacaine and Nesacaine-MPF Injections is chloroprocaine HCl (benzoic acid, 4-amino-2-chloro-2-(diethylamino) ethyl ester, monohydrochloride), which is represented by the following structural formula: Table 1: Composition of Available Injections The solutions are adjusted to pH 2.7 to 4.0 by means of sodium hydroxide and/or hydrochloric acid. Filled under nitrogen.
Nesacaine and Nesacaine-MPF Injections should not be resterilized by autoclaving. STRUCTURE DESCRIPTION
⚠️ Precautions ▾
PRECAUTIONS General The safety and effective use of chloroprocaine depend on proper dosage, correct technique, adequate precautions and readiness for emergencies. Resuscitative equipment, oxygen and other resuscitative drugs should be available for immediate use (see WARNINGS and ADVERSE REACTIONS ). The lowest dosage that results in effective anesthesia should be used to avoid high plasma levels and serious adverse effects.
Injections should be made slowly, with frequent aspirations before and during the injection to avoid intravascular injection. Syringe aspirations should also be performed before and during each supplemental injection in continuous (intermittent) catheter techniques. During the administration of epidural anesthesia, it is recommended that a test dose be administered (3 mL of 3% or 5 mL of 2% Nesacaine-MPF Injection) initially and that the patient be monitored for central nervous system toxicity and cardiovascular toxicity, as well as for signs of unintended intrathecal administration, before proceeding.
When clinical conditions permit, consideration should be given to employing a chloroprocaine solution that contains epinephrine for the test dose because circulatory changes characteristic of epinephrine may also serve as a warning sign of unintended intravascular injection. An intravascular injection is still possible even if aspirations for blood are negative. With the use of continuous catheter techniques, it is recommended that a fraction of each supplemental dose be administered as a test dose in order to verify proper location of the catheter.
Injection of repeated doses of local anesthetics may cause significant increases in plasma levels with each repeated dose due to slow accumulation of the drug or its metabolites. Tolerance to elevated blood levels varies with the physical condition of the patient. Debilitated, elderly patients, acutely ill patients, and children should be given reduced doses commensurate with their age and physical status.
Local anesthetics should also be used with caution in patients with hypotension or heart block. Careful and constant monitoring of cardiovascular and respiratory (adequacy of ventilation) vital signs and the patient’s state of consciousness should be accomplished after each local anesthetic injection. It should be kept in mind at such times that restlessness, anxiety, tinnitus, dizziness, blurred vision, tremors, depression or drowsiness may be early warning signs of central nervous system toxicity.
Local anesthetic injections containing a vasoconstrictor should be used cautiously and in carefully circumscribed quantities in areas of the body supplied by end arteries or having otherwise compromised blood supply. Patients with peripheral vascular disease and those with hypertensive vascular disease may exhibit exaggerated vasoconstrictor response. Ischemic injury or necrosis may result.
Since ester-type local anesthetics are hydrolyzed by plasma cholinesterase produced by the liver, chloroprocaine should be used cautiously in patients with hepatic disease. Local anesthetics should also be used with caution in patients with impaired cardiovascular function since they may be less able to compensate for functional changes associated with the prolongation of A-V conduction produced by these drugs. Use in Ophthalmic Surgery: When local anesthetic injections are employed for retrobulbar block, lack of corneal sensation should not be relied upon to determine whether or not the patient is ready for surgery.
This is because complete lack of corneal sensation usually precedes clinically acceptable external ocular muscle akinesia. Information for Patients When appropriate, patients should be informed in advance that they may experience temporary loss of sensation and motor activity, usually in the lower half of the body, following proper administration of epidural anesthesia. Inform patients that use of local anesthetics may cause methemoglobinemia, a serious condition tha… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
PHARMACOKINETICS The rate of systemic absorption of local anesthetic drugs is dependent upon the total dose and concentration of drug administered, the route of administration, the vascularity of the administration site, and the presence or absence of epinephrine in the anesthetic injection. Epinephrine usually reduces the rate of absorption and plasma concentration of local anesthetics and is sometimes added to local anesthetic injections in order to prolong the duration of action. The onset of action with chloroprocaine is rapid (usually within 6 to 12 minutes), and the duration of anesthesia, depending upon the amount used and the route of administration, may be up to 60 minutes.
Local anesthetics appear to cross the placenta by passive diffusion. However, the rate and degree of diffusion varies considerably among the different drugs as governed by: (1) the degree of plasma protein binding, (2) the degree of ionization, and (3) the degree of lipid solubility. Fetal/maternal ratios of local anesthetics appear to be inversely related to the degree of plasma protein binding, since only the free, unbound drug is available for placental transfer.
Thus, drugs with the highest protein binding capacity may have the lowest fetal/maternal ratios. The extent of placental transfer is also determined by the degree of ionization and lipid solubility of the drug. Lipid soluble, nonionized drugs readily enter the fetal blood from the maternal circulation.
Depending upon the route of administration, local anesthetics are distributed to some extent to all body tissues, with high concentrations found in highly perfused organs such as the liver, lungs, heart, and brain. Various pharmacokinetic parameters of the local anesthetics can be significantly altered by the presence of hepatic or renal disease, addition of epinephrine, factors affecting urinary pH, renal blood flow, the route of administration, and the age of the patient. The in vitro plasma half-life of chloroprocaine in adults is 21 ± 2 seconds for males and 25 ± 1 seconds for females.
The in vitro plasma half-life in neonates is 43 ± 2 seconds. Chloroprocaine is rapidly metabolized in plasma by hydrolysis of the ester linkage by pseudocholinesterase. The hydrolysis of chloroprocaine results in the production of ß-diethylaminoethanol and 2-chloro-4-aminobenzoic acid, which inhibits the action of the sulfonamides (see PRECAUTIONS ).
The kidney is the main excretory organ for most local anesthetics and their metabolites. Urinary excretion is affected by urinary perfusion and factors affecting urinary pH.
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - VIAL LABELING VIAL 1 VIAL 2 VIAL 3
PRINCIPAL DISPLAY PANEL - SERIALIZED LABELING NDC 51662-1407-1 SERIALIZED LABELING
PRINCIPAL DISPLAY PANEL NDC 51662-1407-2 POUCH LABELING POUCH LABELING VIAL LABELING POUCH LABELING VIAL LABEL
PRINCIPAL DISPLAY PANEL NDC 51662-1407-3 CASE LABELING CASE LABELING SERIALIZED RFID LABELING Case Labeling RFID Label
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |