
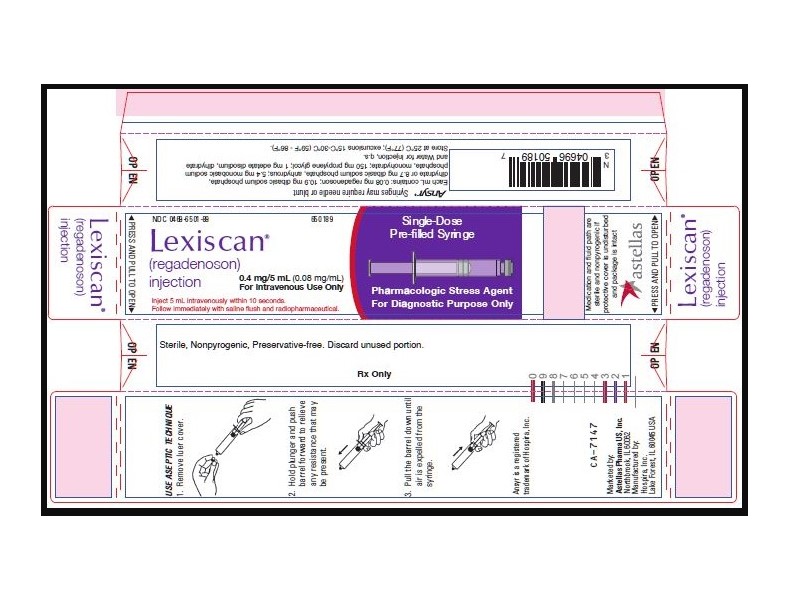
LEXISCAN(R) (REGADENOSON) .08 mg/mL Injection, Solution — NDC 51662-1448-1 (Billing 51662-1448-01)
This is a package of LEXISCAN(R) (REGADENOSON) .08 mg/mL Injection, Solution from HF Acquisition Co LLC, DBA HealthFirst, marketed since Dec 2019 and currently FDA-listed. It is this product's only package size.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
Clinical
- The nuclear heart imaging test — called a myocardial perfusion imaging (MPI) scan — needs your heart to be working hard so the doctor can see how blood flows through it. If you can...
- Why do I need regadenoson if I can't exercise on a treadmill?
- Most people feel something within a minute of the injection. Shortness of breath, headache, flushing (warmth or redness), chest discomfort, and dizziness are the most common reacti...
- What should I expect to feel during and after the injection?
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 51662-1448-01 You're viewing this Main listing | 1 SYRINGE, PLASTIC in 1 CARTON / 5 mL in 1 SYRINGE, PLASTIC | 2019-12-10 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Lexiscan(R) (Regadenoson) .08 mg/mLthis 51662-1448-01 | HF | 1 syringe | — | AP | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 8106183 ↗ | Drug substance | — | Feb 2, 2027 |
| US RE47301 ↗ | Drug product | — | Feb 2, 2027 |
Is there a generic version of this drug?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS & USAGE LEXISCAN® (regadenoson) injection is a pharmacologic stress agent indicated for radionuclide myocardial perfusion imaging (MPI) in patients unable to undergo adequate exercise stress.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION The recommended dose of LEXISCAN is 5 mL (0.4 mg regadenoson) administered as an intravenous injection within 10 seconds. • Patients should be instructed to avoid consumption of any products containing methylxanthines, including caffeinated coffee, tea or other caffeinated beverages, caffeine-containing drug products, aminophylline and theophylline for at least 12 hours before a scheduled radionuclide MPI [see Drug Interactions ( 7- 7.1) and Clinical Pharmacology ( 12- 12.2)]. • Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration, whenever solution and container permit.
Do not administer LEXISCAN if it contains particulate matter or is discolored. • Administer LEXISCAN as an intravenous injection within 10 seconds into a peripheral vein using a 22 gauge or larger catheter or needle. • Administer a 5 mL saline flush immediately after the injection of LEXISCAN. • Administer the radionuclide myocardial perfusion imaging agent 10–20 seconds after the saline flush. The radionuclide may be injected directly into the same catheter as LEXISCAN.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS & STRENGTHS Single-dose pre-filled syringe: clear, colorless solution containing regadenoson 0.4 mg/5 mL (0.08 mg/mL).
⛔ Contraindications ▾
4 CONTRAINDICATIONS Do not administer LEXISCAN to patients with: • Second- or third-degree AV block, or • sinus node dysfunction unless these patients have a functioning artificial pacemaker [see Warnings and Precautions ( 5- 5.2)].
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS
5.1Myocardial Ischemia Fatal and nonfatal myocardial infarction (MI), ventricular arrhythmias, and cardiac arrest have occurred following LEXISCAN injection. Avoid use in patients with symptoms or signs of acute myocardial ischemia, for example unstable angina or cardiovascular instability; these patients may be at greater risk of serious cardiovascular reactions to LEXISCAN. Cardiac resuscitation equipment and trained staff should be available before administering LEXISCAN.
Adhere to the recommended duration of injection [see Dosage and Administration ( 2 )]. As noted in an animal study, longer injection times may increase the duration and magnitude of increase in coronary blood flow [see Clinical Pharmacology ( 12- 12.2)]. If serious reactions to LEXISCAN occur, consider the use of aminophylline, an adenosine antagonist, to shorten the duration of increased coronary blood flow induced by LEXISCAN [see Overdosage ( 10 )].
5.2Sinoatrial and Atrioventricular Nodal Block Adenosine receptor agonists, including LEXISCAN, can depress the SA and AV nodes and may cause first-, second- or third-degree AV block, or sinus bradycardia requiring intervention. In clinical trials first-degree AV block (PR prolongation > 220 msec) developed in 3% of patients within 2 hours of LEXISCAN administration; transient second-degree AV block with one dropped beat was observed in one patient receiving LEXISCAN. In post-marketing experience, third-degree heart block and asystole within minutes of LEXISCAN administration have occurred [see Adverse Reactions ( 6- 6.2)].
5.3Atrial Fibrillation/Atrial Flutter New-onset or recurrent atrial fibrillation with rapid ventricular response and atrial flutter have been reported following LEXISCAN injection [see Adverse Reactions ( 6- 6.2)].
5.4Hypersensitivity, Including Anaphylaxis Anaphylaxis, angioedema, cardiac or respiratory arrest, respiratory distress, decreased oxygen saturation, hypotension, throat tightness, urticaria and rashes have occurred. In clinical trials, hypersensitivity reactions were reported in fewer than 1 percent of patients [see Adverse Reactions (6.1)]. Have personnel and resuscitative equipment immediately available.
5.5Hypotension Adenosine receptor agonists, including LEXISCAN, induce arterial vasodilation and hypotension. In clinical trials, decreased systolic blood pressure (> 35 mm Hg) was observed in 7% of patients and decreased diastolic blood pressure (> 25 mm Hg) was observed in 4% of patients within 45 minutes of LEXISCAN administration. The risk of serious hypotension may be higher in patients with autonomic dysfunction, hypovolemia, left main coronary artery stenosis, stenotic valvular heart disease, pericarditis or pericardial effusions, or stenotic carotid artery disease with cerebrovascular insufficiency.
In post-marketing experience, syncope, transient ischemic attacks and seizures have been observed [see Adverse Reactions ( 6- 6.2)].
5.6Hypertension Administration of adenosine receptor agonists, including LEXISCAN, may result in clinically significant increases in blood pressure in some patients. Among patients who experienced an increase in blood pressure in clinical trials, the increase was observed within minutes of LEXISCAN administration. Most increases resolved within 10 to 15 minutes, but in some cases, increases were observed at 45 minutes following administration [see Clinical Pharmacology ( 12- 12.2)].
In post-marketing experience, cases of potentially clinically significant hypertension have been reported, particularly with underlying hypertension and when low-level exercise was included in the MPI [see Adverse Reactions ( 6- 6.2)].
5.7Bronchoconstriction Adenosine receptor agonists, including LEXISCAN, may cause dyspnea, bronchoconstriction, and respiratory compromise. Appropriate bronchodilator therapy and resuscitative measures should be available prior to and following LEXISCAN administration [see Adverse Reactions ( 6- 6.… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in more detail in other sections of the labeling. • Myocardial Ischemia [see Warnings and Precautions ( 5- 5.1)] • Sinoatrial and Atrioventricular Nodal Block [see Warnings and Precautions ( 5- 5.2)] • Atrial Fibrillation/Atrial Flutter [see Warnings and Precautions ( 5- 5.3)] • Hypersensitivity, Including Anaphylaxis [see Warnings and Precautions ( 5- 5.4)] • Hypotension [see Warnings and Precautions ( 5- 5.5)] • Hypertension [see Warnings and Precautions ( 5- 5.6)] • Bronchoconstriction [see Warnings and Precautions ( 5- 5.7)] • Seizure [see Warnings and Precautions ( 5- 5.8)] • Cerebrovascular Accident (Stroke) [see Warnings and Precautions ( 5- 5.9)]
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. During clinical development, 1,651 patients were exposed to LEXISCAN, with most receiving 0.4 mg as a rapid (≤ 10 seconds) intravenous injection. Most of these patients received LEXISCAN in two clinical studies that enrolled patients who had no history of bronchospastic lung disease as well as no history of a cardiac conduction block of greater than first-degree AV block, except for patients with functioning artificial pacemakers.
In these studies (Studies 1 and 2), 2,015 patients underwent myocardial perfusion imaging after administration of LEXISCAN (N = 1,337) or ADENOSCAN (N = 678). The population was 26–93 years of age (median 66 years), 70% male and primarily Caucasian (76% Caucasian, 7% African American, 9% Hispanic, 5% Asian). Table 1 shows the most frequently reported adverse reactions.
Overall, any adverse reaction occurred at similar rates between the study groups (80% for the LEXISCAN group and 83% for the ADENOSCAN group). Aminophylline was used to treat the reactions in 3% of patients in the LEXISCAN group and 2% of patients in the ADENOSCAN group. Most adverse reactions began soon after dosing, and generally resolved within approximately 15 minutes, except for headache which resolved in most patients within 30 minutes.
Table 1 Adverse Reactions in Studies 1 and 2 Pooled (Frequency ≥ 5%) ECG Abnormalities The frequency of rhythm or conduction abnormalities following LEXISCAN or ADENOSCAN is shown in Table 2 [see Warnings and Precautions ( 5- 5.2)]. Table 2 Rhythm or Conduction Abnormalities* in Studies 1 and 2 * 12-lead ECGs were recorded before and for up to 2 hours after dosing. † includes rhythm abnormalities (PACs, PVCs, atrial fibrillation/flutter, wandering atrial pacemaker, supraventricular or ventricular arrhythmia) or conduction abnormalities, including AV block.
Respiratory Abnormalities In a randomized, placebo-controlled trial of 999 patients with asthma (n = 532) or stable chronic obstructive pulmonary disease (n = 467), the overall incidence of pre-specified respiratory adverse reactions was greater in the LEXISCAN group compared to the placebo group (p < 0.001). Most respiratory adverse reactions resolved without therapy; a few patients received aminophylline or a short-acting bronchodilator. No differences were observed between treatment arms in the reduction of >15% from baseline at two-hours in FEV1 (Table 3).
Table 3 Respiratory Adverse Effects* * All patients continued the use of their respiratory medications as prescribed prior to administration of LEXISCAN. † Patients may have reported more than one type of adverse reaction. Adverse reactions were collected up to 24 hours following drug administration. Pre-specified respiratory adverse reactions included dyspnea, wheezing, obstructive airway disorder, dyspnea exertional, and tachypnea. ‡ Change from baseline at 2 hours.
Renal Impairment In a randomized, placebo-controlled trial of 504 patients (LEXISCAN n=334 and placebo n=170) with a di… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS No formal pharmacokinetic drug interaction studies have been conducted with LEXISCAN.
7.1Effects of Other Drugs on LEXISCAN • Methylxanthines (e.g., caffeine, aminophylline and theophylline) are non-specific adenosine receptor antagonists that interfere with the vasodilation activity of LEXISCAN [see Clinical Pharmacology ( 12- 12.2) and Patient Counseling Information ( 17 )]. Patients should avoid consumption of any products containing methylxanthines as well as any drugs containing theophylline or aminophylline for at least 12 hours before LEXISCAN administration. Aminophylline may be used to attenuate severe or persistent adverse reactions to LEXISCAN [see Overdosage ( 10 )]. • In clinical studies, LEXISCAN was administered to patients taking other cardioactive drugs (i.e., β-blockers, calcium channel blockers, ACE inhibitors, nitrates, cardiac glycosides, and angiotensin receptor blockers) without reported adverse reactions or apparent effects on efficacy. • Dipyridamole may change the effects of LEXISCAN.
When possible, withhold dipyridamole for at least two days prior to LEXISCAN administration.
7.2Effect of LEXISCAN on Other Drugs Regadenoson does not inhibit the metabolism of substrates for CYP1A2, CYP2C8, CYP2C9, CYP2C19, CYP2D6, or CYP3A4 in human liver microsomes, indicating that it is unlikely to alter the pharmacokinetics of drugs metabolized by these cytochrome P450 enzymes.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary There are no available data on LEXISCAN use in pregnant women to inform a drug-associated risk. In animal reproduction studies, adverse developmental outcomes were observed with the administration of regadenoson to pregnant rats and rabbits during organogenesis only at doses that produced maternal toxicity (see Data). In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
Data Animal Data Reproductive studies in rats showed that regadenoson doses 10 and 20 times the maximum recommended human dose (MRHD) based on body surface area caused reduced fetal body weights and significant ossification delays in fore- and hind limb phalanges and metatarsals; maternal toxicity also occurred at these doses. Skeletal variations were increased in all treated groups. In rabbits, maternal toxicity occurred at regadenoson doses administered during organogenesis at 4 times the MRHD; however, there were no teratogenic effects in offspring at this dose.
At higher doses, 12 and 20 times the MRHD, maternal toxicity occurred along with increased embryo-fetal loss and fetal malformations.
8.2Lactation Risk Summary There is no information on the presence of regadenoson in human milk, the effects on the breastfed infant, or the effects on milk production. Because of the potential risk of serious cardiac reactions in the breastfed infant, advise the nursing mother to pump and discard breast milk for 10 hours after administration of LEXISCAN.
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established.
8.5Geriatric Use Of the 1,337 patients receiving LEXISCAN in Studies 1 and 2, 56% were 65 years of age and over and 24% were 75 years of age and over. Older patients (> 75 years of age) had a similar adverse event profile compared to younger patients (< 65 years of age), but had a higher incidence of hypotension (2% vs. ≤ 1%).
8.6Renal Impairment No dose adjustment is needed in patients with renal impairment including patients with end stage renal disease and/or dependent on dialysis [see Pharmacokinetics ( 12- 12.3)].
🆘 Overdosage ▾
10 OVERDOSAGE LEXISCAN overdosage may result in serious reactions [see Warnings and Precautions ( 5 )]. In a study of healthy volunteers, symptoms of flushing, dizziness and increased heart rate were assessed as intolerable at LEXISCAN doses greater than 0.02 mg/kg. Aminophylline to Reverse Effects Methylxanthines, such as caffeine, aminophylline, and theophylline, are competitive adenosine receptor antagonists and aminophylline has been used to terminate persistent pharmacodynamic effects.
Aminophylline may be administered in doses ranging from 50 mg to 250 mg by slow intravenous injection (50 mg to 100 mg over 30–60 seconds). Methylxanthine use is not recommended in patients who experience a seizure in association with LEXISCAN administration [see Warnings and Precautions ( 5- 5.8)].
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Regadenoson is a low affinity agonist (Ki ≈ 1.3 µM) for the A2A adenosine receptor, with at least 10-fold lower affinity for the A1 adenosine receptor (Ki > 16.5 µM), and weak, if any, affinity for the A2B and A3 adenosine receptors. Activation of the A2A adenosine receptor by regadenoson produces coronary vasodilation and increases coronary blood flow (CBF).
12.2Pharmacodynamics Coronary Blood Flow LEXISCAN causes a rapid increase in CBF which is sustained for a short duration. In patients undergoing coronary catheterization, pulsed-wave Doppler ultrasonography was used to measure the average peak velocity (APV) of coronary blood flow before and up to 30 minutes after administration of regadenoson (0.4 mg, intravenously). Mean APV increased to greater than twice baseline by 30 seconds and decreased to less than twice the baseline level within 10 minutes [see Clinical Pharmacology (12.3)].
Myocardial uptake of the radiopharmaceutical is proportional to CBF. Because LEXISCAN increases blood flow in normal coronary arteries with little or no increase in stenotic arteries, LEXISCAN causes relatively less uptake of the radiopharmaceutical in vascular territories supplied by stenotic arteries. MPI intensity after LEXISCAN administration is therefore greater in areas perfused by normal relative to stenosed arteries.
Effect of duration of injection A study in dogs compared the effects of intravenous injection of 2.5 μg/kg regadenoson (in 10 mL) over 10 seconds and 30 seconds on CBF. The duration of a two-fold increase in CBF was 97±14 seconds (n=6) and 221±20 seconds (n=4), respectively, for the 10 second and 30 second injections. The peak effects (i.e., maximal increase) on CBF after the 10 second and 30 second injections were 217±15% and 297±33% above baseline, respectively.
The times to peak effect on CBF were 17±2 seconds and 27±6 seconds, respectively. Effect of Aminophylline Aminophylline (100 mg, administered by slow intravenous injection over 60 seconds) injected 1 minute after 0.4 mg LEXISCAN in patients undergoing cardiac catheterization, was shown to shorten the duration of the coronary blood flow response to LEXISCAN as measured by pulsed-wave Doppler ultrasonography [see Overdosage ( 10 )]. Effect of Caffeine Ingestion of caffeine decreases the ability to detect reversible ischemic defects.
In a placebo-controlled, parallel group clinical study, patients with known or suspected myocardial ischemia received a baseline rest/stress MPI followed by a second stress MPI. Patients received caffeine or placebo 90 minutes before the second LEXISCAN stress MPI. Following caffeine administration (200 or 400 mg), the mean number of reversible defects identified was reduced by approximately 60%.
This decrease was statistically significant [see Drug Interactions ( 7- 7.1) and Patient Counseling Information ( 17 )]. Hemodynamic Effects In clinical studies, the majority of patients had an increase in heart rate and a decrease in blood pressure within 45 minutes after administration of LEXISCAN. Maximum hemodynamic changes after LEXISCAN and ADENOSCAN in Studies 1 and 2 are summarized in Table 5.
Table 5 Hemodynamic Effects in Studies 1 and 2 Hemodynamic Effects Following Inadequate Exercise In a clinical study, LEXISCAN was administered for MPI following inadequate exercise stress. More patients with LEXISCAN administration three minutes following inadequate exercise stress had an increase in heart rate and a decrease in systolic blood pressure compared with LEXISCAN administered at rest. The changes were not associated with any clinically significant adverse reactions.
Maximum hemodynamic changes are presented in Table 6. Table 6 Hemodynamic Effects in Inadequate Exercise Stress Study Respiratory Effects The A2B and A3 adenosine receptors have been implicated in the pathophysiology of bronchoconstriction in susceptible individuals (i.e., asthmatics). In in vitro studies, regadenoson ha… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING LEXISCAN(R) (REGADENOSON) INJECTION is supplied in the following dosage forms. NDC 51662-1448-1 LEXISCAN(R) (REGADENOSON) INJECTION 0.4mg/5mL (0.08 mg/mL) 5mL SYR HF Acquisition Co LLC, DBA HealthFirst Mukilteo, WA 98275 Also supplied in the following manufacture supplied dosage forms LEXISCAN is supplied as a sterile, preservative-free solution containing 0.08 mg/mL regadenoson in the following package: • Single-dose 5 mL pre-filled plastic Ansyr® syringes with luer-lock fitting (NDC 0469-6501-89).
Store at controlled room temperature, 25°C (77°F); excursions permitted to 15° to 30°C (59°– 86°F).
📋 Description ▾
11 DESCRIPTION Regadenoson is an A2A adenosine receptor agonist that is a coronary vasodilator [see Clinical Pharmacology ( 12- 12.1)]. Regadenoson is chemically described as adenosine, 2-[4-[(methylamino)carbonyl]-1H-pyrazol-1-yl]-, monohydrate. Its structural formula is: The molecular formula for regadenoson is C15H18N8O5 • H2O and its molecular weight is 408.37.
LEXISCAN is a sterile, nonpyrogenic solution for intravenous injection. The solution is clear and colorless. Each 1 mL in the 5 mL pre-filled syringe contains 0.084 mg of regadenoson monohydrate, corresponding to 0.08 mg regadenoson on an anhydrous basis, 10.9 mg dibasic sodium phosphate dihydrate or 8.7 mg dibasic sodium phosphate anhydrous, 5.4 mg monobasic sodium phosphate monohydrate, 150 mg propylene glycol, 1 mg edetate disodium dihydrate, and Water for Injection, with pH between 6.3 and 7.7.
STRUCTURE
🔬 Clinical Studies ▾
14 CLINICAL STUDIES Agreement between LEXISCAN and ADENOSCAN The efficacy and safety of LEXISCAN were determined relative to ADENOSCAN in two randomized, double-blind studies (Studies 1 and 2) in 2,015 patients with known or suspected coronary artery disease who were indicated for pharmacologic stress MPI. A total of 1,871 of these patients had images considered valid for the primary efficacy evaluation, including 1,294 (69%) men and 577 (31%) women with a median age of 66 years (range 26–93 years of age). Each patient received an initial stress scan using ADENOSCAN (6-minute infusion using a dose of 0.14 mg/kg/min, without exercise) with a radionuclide gated SPECT imaging protocol.
After the initial scan, patients were randomized to either LEXISCAN or ADENOSCAN, and received a second stress scan with the same radionuclide imaging protocol as that used for the initial scan. The median time between scans was 7 days (range of 1–104 days). The most common cardiovascular histories included hypertension (81%), CABG, PTCA or stenting (51%), angina (63%), and history of myocardial infarction (41%) or arrhythmia (33%); other medical history included diabetes (32%) and COPD (5%).
Patients with a recent history of serious uncontrolled ventricular arrhythmia, myocardial infarction, or unstable angina, a history of greater than first-degree AV block, or with symptomatic bradycardia, sick sinus syndrome, or a heart transplant were excluded. A number of patients took cardioactive medications on the day of the scan, including β-blockers (18%), calcium channel blockers (9%), and nitrates (6%). In the pooled study population, 68% of patients had 0–1 segments showing reversible defects on the initial scan, 24% had 2–4 segments, and 9% had ≥ 5 segments.
Comparison of the images obtained with LEXISCAN to those obtained with ADENOSCAN was performed as follows. Using the 17-segment model, the number of segments showing a reversible perfusion defect was calculated for the initial ADENOSCAN study and for the randomized study obtained using LEXISCAN or ADENOSCAN. The agreement rate for the image obtained with LEXISCAN or ADENOSCAN relative to the initial ADENOSCAN image was calculated by determining how frequently the patients assigned to each initial ADENOSCAN category (0–1, 2–4, 5–17 reversible segments) were placed in the same category with the randomized scan.
The agreement rates for LEXISCAN and ADENOSCAN were calculated as the average of the agreement rates across the three categories determined by the initial scan. Studies 1 and 2 each demonstrated that LEXISCAN is similar to ADENOSCAN in assessing the extent of reversible perfusion abnormalities (Table 7). Table 7 Agreement Rates in Studies 1 and 2 Use of LEXISCAN in Patients with Inadequate Exercise Stress The efficacy and safety of LEXISCAN administered 3 minutes (Group 1) or 1 hour (Group 2) following inadequate exercise stress were evaluated in an open-label randomized, multi-center, non-inferiority study.
Adequate exercise was defined as ≥ 85% maximum predicted heart rate and ≥ 5 METS. SPECT MPI was performed 60-90 minutes after LEXISCAN administration in each group (MPI 1). Patients returned 1-14 days later to undergo a second stress MPI with LEXISCAN without exercise (MPI 2).
All patients were referred for evaluation of coronary artery disease. Of the 1,147 patients randomized, a total of 1,073 patients received LEXISCAN and had interpretable SPECT scans at all visits; 538 in Group 1 and 535 in Group 2. The median age of the patients was 62 years (range 28 to 90 years) and included 633 (59%) men and 440 (41%) women.
Images from MPI 1 and MPI 2 for the two groups were compared for presence or absence of perfusion defects. The level of agreement between the MPI 1 and the MPI 2 reads in Group 1 was similar to the level of agreement between MPI 1 and MPI 2 reads in Group 2. However, two patients receiving LEXISCAN 3 minutes following inadequate exercise experienced a serious cardiac adverse… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Regadenoson was negative in the Ames bacterial mutation assay, chromosomal aberration assay in Chinese hamster ovary (CHO) cells, and mouse bone marrow micronucleus assay. Long-term animal studies have not been conducted to evaluate LEXISCAN's carcinogenic potential or potential effects on fertility.
13.2Animal Toxicology and/or Pharmacology Cardiomyopathy Minimal cardiomyopathy (myocyte necrosis and inflammation) was observed in rats following single-dose administration of regadenoson. Increased incidence of minimal cardiomyopathy was observed on day 2 in males at doses of 0.08, 0.2 and 0.8 mg/kg (1/5, 2/5, and 5/5) and in females (2/5) at 0.8 mg/kg. In a separate study in male rats, the mean arterial pressure was decreased by 30 to 50% of baseline values for up to 90 minutes at regadenoson doses of 0.2 and 0.8 mg/kg, respectively.
No cardiomyopathy was noted in rats sacrificed 15 days following single administration of regadenoson. The mechanism of the cardiomyopathy induced by regadenoson was not elucidated in this study but was associated with the hypotensive effects of regadenoson. Profound hypotension induced by vasoactive drugs is known to cause cardiomyopathy in rats.
Local Irritation Intravenous administration of LEXISCAN to rabbits resulted in perivascular hemorrhage, vein vasculitis, inflammation, thrombosis and necrosis, with inflammation and thrombosis persisting through day 8 (last observation day). Perivascular administration of LEXISCAN to rabbits resulted in hemorrhage, inflammation, pustule formation and epidermal hyperplasia, which persisted through day 8 except for the hemorrhage which resolved. Subcutaneous administration of LEXISCAN to rabbits resulted in hemorrhage, acute inflammation, and necrosis; on day 8 muscle fiber regeneration was observed.
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - SYRINGE CARTON LABELING SYRINGE CARTON LABELING
PRINCIPAL DISPLAY PANEL - SERIALIZED CARTON LABELING RFID Label
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |