
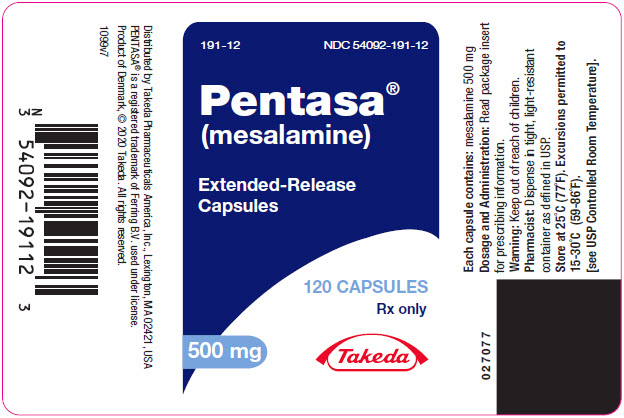
Pentasa mesalamine 500 mg Capsule, 120-count
Other active recalls for Mesalamine (different manufacturers) — 1 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Aminosalicylate class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Mesalamine is used to treat ulcerative colitis (a condition which causes swelling and sores in the lining of the colon [large intestine] and rectum) and also to maintain improvement of ulcerative colitis symptoms. Mesalamine is in a class of medications called anti-inflammatory agents. It works by stopping the body from producing a certain substance that may cause inflammation.
Read the full MedlinePlus article ↗- Mesalamine works to reduce inflammation directly in the lining of your colon or rectum. Depending on which product you've been prescribed, it can help bring an active flare of ulce...
- What exactly is mesalamine supposed to do for me?
- It really does matter, and they're not interchangeable. The form your doctor chose depends on where in your bowel the inflammation is. Rectal suppositories (like CANASA) treat infl...
- There are so many different forms — pills, enemas, suppositories. Does it matter which one I use?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Mesalamine — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII D5340Y2I9G
Castor oil is a natural plant-based oil used in medicines as a lubricant, laxative agent, and solvent. It helps medicine ingredients dissolve or flow smoothly and can aid bowel movement in formulations designed for that purpose.
-
UNII 5Z17386USF
A food-derived fat used as an emulsifier and stabilizer. It helps blend oil and water-based ingredients together and keeps the medicine's texture consistent throughout its shelf life.
-
UNII 7Z8S9VYZ4B
Ethylcellulose is a plant-derived thickener and film-former made by chemically modifying cellulose. It's used as a binder to hold tablet ingredients together, a coating to control how quickly medicine is released, or a thickener in liquid formulations.
-
UNII H3R47K3TBD
FD&C Blue No. 1 is a synthetic blue dye approved for use in foods and medicines. It serves as a colorant to give the medication its distinctive appearance and help with product identification.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 4ELV7Z65AP
Stearic acid is a fatty acid derived from plant or animal sources. It acts as a binder and lubricant in tablets and capsules, helping them hold together and flow smoothly during manufacturing.
-
UNII C151H8M554
A natural sugar derived from sugar cane or sugar beets. It's used as a sweetener, filler, and binder to improve taste, add bulk, and help hold tablet or capsule ingredients together.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII 7G1J5DA97F
White wax is a refined, bleached plant-based or mineral wax that serves as a coating and hardening agent in medicines. It helps control how fast the drug dissolves and improves the product's texture and appearance.
12 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $5.826 | $699.10 / 120 capsules |
| Medicaid paysCMS SDUD · 12 mo | $5.88 | $706.16 / 120 capsules |
| Medicare drug plans payPart D · Q2 2026 | $6.19 | $743.26 / 120 capsules |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Mesalamine 500 mg 63304-0089-13 | Sun | 120 capsules | $3.470 | AB | Availability likely | save 40% |
| Pentasa 500 mgthis 54092-0191-12 | Takeda | 120 capsules | $5.826 | AB | Availability likely | — |
Where does this data come from?
⏳ Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 54092-0191-12 You're viewing this | 120 CAPSULE in 1 BOTTLE (54092-191-12) | 2004-07-08 | Active |
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE PENTASA is indicated for the induction of remission and for the treatment of mildly to moderately active ulcerative colitis in adult patients. PENTASA is an aminosalicylate indicated for the induction of remission and for the treatment of mildly to moderately active ulcerative colitis in adult patients. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Evaluate renal function prior to initiation of PENTASA and periodically while on therapy [see Warnings and Precautions (5.1) ] . Recommended Dosage The recommended dosage for the induction of remission and the symptomatic treatment of mildly to moderately active ulcerative colitis in adults is 1 g (4 PENTASA 250 mg capsules or 2 PENTASA 500 mg capsules) administered orally four times daily. Administration Instructions Swallow PENTASA capsules whole; do not crush or chew.
Alternatively, the capsule(s) may be opened and the entire contents sprinkled onto applesauce or yogurt. Consume the entire mixture immediately. Drink an adequate amount of fluids during treatment [see Warnings and Precautions (5.7) ] .
Evaluate renal function prior to initiation of PENTASA and periodically while on therapy. ( 2 , 5.1 ) The recommended dosage is 1 g administered orally four times daily. ( 2 ) Swallow capsules whole; do not crush or chew.
( 2 ) Alternatively, the capsule(s) may be opened and the contents sprinkled onto applesauce or yogurt. ( 2 ) Drink an adequate amount of fluids. ( 2 , 5.7 )
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Extended-release capsules 250 mg as a green and blue capsule imprinted with a pentagonal starburst logo and the number 2010 on the green portion of the capsule and S429 250 mg on the blue portion of the capsule. 500 mg as a blue capsule imprinted with a pentagonal starburst logo and S429 500 mg. Extended-release capsules: 250 mg and 500 mg. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS PENTASA is contraindicated in patients with known or suspected hypersensitivity to salicylates, aminosalicylates, or any ingredients of PENTASA [see Warnings and Precautions (5.3) ] . Known or suspected hypersensitivity to salicylates or aminosalicylates or to any of the ingredients of PENTASA. ( 4 , 5.3 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Renal Impairment : Assess renal function at the beginning of treatment and periodically during treatment. Evaluate the risks and benefits of PENTASA in patients with known renal impairment or taking nephrotoxic drug. Discontinue PENTASA if renal function deteriorates while on therapy.
( 5.1 , 7.1 , 8.6 ) Mesalamine-Induced Acute Intolerance Syndrome : Discontinue treatment if acute intolerance syndrome (cramping, acute abdominal pain, bloody diarrhea, sometimes fever, headache and rash) is suspected. ( 5.2 ) Hypersensitivity Reactions, including myocarditis and pericarditis : Discontinue PENTASA if a hypersensitivity reaction is suspected. ( 5.3 ) Hepatic Failure : Evaluate the risks and benefits of using PENTASA in patients with known liver impairment.
( 5.4 ) Severe Cutaneous Adverse Reactions : Discontinue at the first signs or symptoms of severe cutaneous adverse reactions or other signs of hypersensitivity and consider further evaluation. ( 5.5 ) Photosensitivity : Avoid sun exposure if pre-existing skin conditions. ( 5.6 ) Nephrolithiasis : Cases of nephrolithiasis have been reported with the use of mesalamine.
Mesalamine-containing stones are undetectable by standard radiography or computed tomography (CT). Ensure adequate hydration during treatment. ( 5.7 ) Interference with Laboratory Tests : Mesalamine may lead to elevated urinary normetanephrine test results.
( 5.8 )
5.1Renal Impairment Renal impairment, including minimal change disease, acute and chronic interstitial nephritis, and renal failure have been reported in patients given PENTASA or other products that contain mesalamine or are converted to mesalamine. Evaluate the risks and benefits of using PENTASA in patients with known renal impairment or a history of renal disease or taking concomitant nephrotoxic drugs. Evaluate renal function in all patients prior to initiation and periodically while on therapy with PENTASA.
Discontinue PENTASA if renal function deteriorates while on therapy [see Drug Interactions (7.1) , Use in Specific Populations (8.6) ] .
5.2Mesalamine-Induced Acute Intolerance Syndrome Mesalamine has been associated with an acute intolerance syndrome that may be difficult to distinguish from an exacerbation of ulcerative colitis. Symptoms include cramping, acute abdominal pain, bloody diarrhea, and sometimes fever, headache, and rash. Monitor patients for worsening of these symptoms while on treatment.
If acute intolerance syndrome is suspected, promptly discontinue treatment with PENTASA.
5.3Hypersensitivity Reactions Hypersensitivity reactions have been reported in patients taking sulfasalazine. Some patients may have a similar reaction to PENTASA or to other compounds that contain or are converted to mesalamine. As with sulfasalazine, mesalamine-induced hypersensitivity reactions may present as internal organ involvement, including myocarditis, pericarditis, nephritis, hepatitis, pneumonitis, and hematologic abnormalities.
Evaluate patients immediately if signs or symptoms of a hypersensitivity reaction are present. Discontinue PENTASA if an alternative etiology for the signs and symptoms cannot be established.
5.4Hepatic Failure There have been reports of hepatic failure in patients with pre-existing liver disease who have been administered other products containing mesalamine. Evaluate the risks and benefits of using PENTASA in patients with known liver impairment.
5.5Severe Cutaneous Adverse Reactions Severe cutaneous adverse reactions, such as Stevens-Johnson syndrome (SJS) and toxic epidermal necrolysis (TEN), drug reaction with eosinophilia and systemic symptoms (DRESS), and acute generalized exanthematous pustulosis (AGEP) have been reported in with the use of mesalamine [see Adverse Reactions (6.2) ] . Discontinue PENTASA at the first signs or symptoms of severe cutaneous adverse reactions or other signs of hypersensitivity and consider further evaluation.
5.6 Photosensitivity Patients with pre-existi…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: Renal impairment [see Warnings and Precautions (5.1) ] Mesalamine-induced acute intolerance syndrome [see Warnings and Precautions (5.2) ] Hypersensitivity reactions [see Warnings and Precautions (5.3) ] Hepatic failure [see Warnings and Precautions (5.4) ] Severe cutaneous adverse reactions [see Warnings and Precautions (5.5) ] Photosensitivity [see Warnings and Precautions (5.6) ] Nephrolithiasis [see Warnings and Precautions (5.7) ] Most common adverse reactions are nausea and vomiting (1%).
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Takeda Pharmaceuticals U.S.A., Inc. at 1-877-TAKEDA-7 (1-877-825-3327) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. More than 2100 patients were exposed to PENTASA in clinical trials of ulcerative colitis or another gastrointestinal condition. The most common adverse reactions (i.e., greater than or equal to 1%) were diarrhea (3%), headache (2%), nausea (2%), abdominal pain (2%), dyspepsia (2%), vomiting (2%), and rash (1%).
The safety of PENTASA was evaluated in two randomized, double-blind, placebo-controlled, dose-response trials (UC-1 and UC-2) of 624 patients with mildly to moderately active ulcerative colitis for up to 8 weeks of treatment [see Clinical Studies (14) ] . The most common adverse reaction was nausea and vomiting: 1% in the PENTASA group (N=451) and 0% in the placebo group (N=173). Withdrawal from therapy due to adverse reactions was 7% in the PENTASA group and 4% in the placebo group.
The following adverse reactions, presented by body system, were reported in less than 1% of patients in UC-1, UC-2, and clinical trials for another gastrointestinal condition. Blood and lymphatic system disorders: thrombocythemia, thrombocytopenia Cardiac Disorders: palpitations, pericarditis, vasodilation Gastrointestinal Disorders: abdominal distention, constipation, duodenal ulcer, dysphagia, eructation, esophageal ulcer, fecal incontinence, GI bleeding, mouth ulcer, pancreatitis, rectal bleeding, stool abnormalities (color or texture change) General disorders and administration site conditions: fever, malaise Infections and infestations: oral moniliasis, conjunctivitis Investigations: GGTP increase, increased alkaline phosphatase, LDH increase, SGOT increase, SGPT increase, lipase increase, amylase increase Metabolism and nutritional disorders: anorexia, edema, thirst Musculoskeletal and connective tissue disorders: arthralgia, leg cramps, myalgia Nervous System Disorders: dizziness, insomnia, somnolence, paresthesia Psychiatric disorders: depression, asthenia Renal and urinary disorders: albuminuria, hematuria, urinary frequency Reproductive system and breast disorders: amenorrhea, breast pain, hypomenorrhea, menorrhagia, metrorrhagia Respiratory, Thoracic and Mediastinal Disorders: pulmonary infiltrates, one week after completion of an 8-week ulcerative colitis study, a 72-year-old male, with no previous history of pulmonary problems, developed dyspnea.
The patient was subsequently diagnosed with interstitial pulmonary fibrosis without eosinophilia by one physician and bronchiolitis obliterans with organizing pneumonitis by a second physician. Skin and Subcutaneous Tissue Disorders: acne, alopecia, dry skin, eczema, erythema nodosum, nail disorder, photosensitivity, pruritus, sweating, urticaria, ecchymosis, lichen planus
6.2Postmarketing Experience The following adverse reactions have been identified during post-approval use of mesalamine. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably esti…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Nephrotoxic Agents including Non-Steroidal Anti-inflammatory Drugs (NSAIDs) : Increased risk of nephrotoxicity; monitor for changes in renal function and mesalamine-related adverse reactions. ( 7.1 ) Azathioprine or 6-Mercaptopurine : Increased risk of blood dyscrasias; monitor complete blood cell counts and platelet counts. ( 7.2 )
7.1Nephrotoxic Agents, Including Non-Steroidal Anti-Inflammatory Drugs The concurrent use of mesalamine with known nephrotoxic agents, including non-steroidal anti-inflammatory drugs (NSAIDs), may increase the risk of nephrotoxicity. Monitor patients taking nephrotoxic drugs for changes in renal function and mesalamine-related adverse reactions [see Warnings and Precautions (5.1) ] .
7.2Azathioprine or 6-Mercaptopurine The concurrent use of mesalamine with azathioprine or 6-mercaptopurine and/or any other drugs known to cause myelotoxicity may increase the risk for blood disorders, bone marrow failure, and associated complications. If concomitant use of PENTASA and azathioprine or 6-mercaptopurine cannot be avoided, monitor blood tests, including complete blood cell counts and platelet counts.
7.3Interference with Urinary Normetanephrine Measurements Use of PENTASA may lead to spuriously elevated test results when measuring urinary normetanephrine by liquid chromatography with electrochemical detection [see Warnings and Precautions (5.8) ] . Consider an alternative, selective assay for normetanephrine.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Geriatric Patients : Increased risk of blood dyscrasias; monitor complete blood cell counts and platelet counts. ( 8.5 )
8.1Pregnancy Risk Summary Published data from meta-analyses, cohort studies, and case series on the use of mesalamine during pregnancy have not reliably informed an association with mesalamine and major birth defects, miscarriage, or adverse maternal or fetal outcomes (see Data ) . There are adverse effects on maternal and fetal outcomes associated with ulcerative colitis in pregnancy (see Clinical Considerations ) . In animal reproduction studies, oral administration of mesalamine during organogenesis to pregnant rats at doses up to 1000 mg/kg/day (approximately 2.4 times the maximum recommended human dose of 4 g/day, based on a body surface area comparison) and rabbits at doses of 800 mg/kg/day (approximately 3.9 times the maximum recommended human dose of 4 g/day, based on a body surface area comparison) revealed no evidence of adverse developmental effects (see Data ) .
The background risk of major birth defects and miscarriage for the indicated populations is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriages in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Disease-associated maternal and embryo/fetal risk Published data suggest that increased disease activity is associated with the risk of developing adverse pregnancy outcomes in women with ulcerative colitis. Adverse pregnancy outcomes include preterm delivery (before 37 weeks of gestation), low birth weight (less than 2500 g) infants, and small for gestational age at birth. Data Human Data Published data from meta-analyses, cohort studies, and case series on the use of mesalamine during early pregnancy (first trimester) and throughout pregnancy have not reliably informed an association of mesalamine and major birth defects, miscarriage, or adverse maternal or fetal outcomes.
There is no clear evidence that mesalamine exposure in early pregnancy is associated with an increased risk of major congenital malformations, including cardiac malformations. Published epidemiologic studies have important methodological limitations which hinder interpretation of the data, including inability to control for confounders, such as underlying maternal disease, maternal use of concomitant medications, and missing information on the dose and duration of use for mesalamine products. Animal Data Reproduction studies with mesalamine during organogenesis have been performed in pregnant rats at doses up to 1000 mg/kg/day (approximately 2.4 times the maximum recommended human dose of 4 g/day, based on a body surface area comparison) and rabbits at doses up to 800 mg/kg/day (approximately 3.9 times the maximum recommended human dose of 4 g/day based on a body surface area comparison) and have revealed no evidence of harm to the fetus due to mesalamine.
8.2Lactation Risk Summary Data from published literature report the presence of mesalamine and its metabolite, N-acetyl-5-aminosalicylic acid in human milk in small amounts with relative infant doses (RID) of 0.1% or less for mesalamine (see Data ) . There are case reports of diarrhea observed in breastfed infants exposed to mesalamine (see Clinical Considerations ) . There is no information on the effects of mesalamine on milk production.
The lack of clinical data during lactation precludes a clear determination of the risk of PENTASA to an infant during lactation; therefore, the developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for PENTASA and any potential adverse effects on the breastfed child from PENTASA or from the underlying maternal condition. Clinical Considerations Advise the caregiver to monitor the breastfed infant for diarrh…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Published data from meta-analyses, cohort studies, and case series on the use of mesalamine during pregnancy have not reliably informed an association with mesalamine and major birth defects, miscarriage, or adverse maternal or fetal outcomes (see Data ) . There are adverse effects on maternal and fetal outcomes associated with ulcerative colitis in pregnancy (see Clinical Considerations ) . In animal reproduction studies, oral administration of mesalamine during organogenesis to pregnant rats at doses up to 1000 mg/kg/day (approximately 2.4 times the maximum recommended human dose of 4 g/day, based on a body surface area comparison) and rabbits at doses of 800 mg/kg/day (approximately 3.9 times the maximum recommended human dose of 4 g/day, based on a body surface area comparison) revealed no evidence of adverse developmental effects (see Data ) .
The background risk of major birth defects and miscarriage for the indicated populations is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriages in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Disease-associated maternal and embryo/fetal risk Published data suggest that increased disease activity is associated with the risk of developing adverse pregnancy outcomes in women with ulcerative colitis. Adverse pregnancy outcomes include preterm delivery (before 37 weeks of gestation), low birth weight (less than 2500 g) infants, and small for gestational age at birth. Data Human Data Published data from meta-analyses, cohort studies, and case series on the use of mesalamine during early pregnancy (first trimester) and throughout pregnancy have not reliably informed an association of mesalamine and major birth defects, miscarriage, or adverse maternal or fetal outcomes.
There is no clear evidence that mesalamine exposure in early pregnancy is associated with an increased risk of major congenital malformations, including cardiac malformations. Published epidemiologic studies have important methodological limitations which hinder interpretation of the data, including inability to control for confounders, such as underlying maternal disease, maternal use of concomitant medications, and missing information on the dose and duration of use for mesalamine products. Animal Data Reproduction studies with mesalamine during organogenesis have been performed in pregnant rats at doses up to 1000 mg/kg/day (approximately 2.4 times the maximum recommended human dose of 4 g/day, based on a body surface area comparison) and rabbits at doses up to 800 mg/kg/day (approximately 3.9 times the maximum recommended human dose of 4 g/day based on a body surface area comparison) and have revealed no evidence of harm to the fetus due to mesalamine.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical trials of PENTASA did not include sufficient numbers of patients aged 65 years and over to determine whether they respond differently from younger patients. Reports from uncontrolled clinical studies and postmarketing reporting systems suggested a higher incidence of blood dyscrasias (i.e., agranulocytosis, neutropenia, and pancytopenia) in patients receiving mesalamine-containing products such as PENTASA who were 65 years or older compared to younger adult patients, which may also be associated with ulcerative colitis, use of interacting drugs, or reduced renal function.
Monitor complete blood cell counts and platelet counts in patients 65 years and over during treatment with PENTASA. In general, consider the greater frequency of decreased hepatic, renal, or cardiac function, and of concurrent disease or other drug therapy in patients 65 years and over when prescribing PENTASA.
🆘 Overdosage ▾
10 OVERDOSAGE PENTASA is an aminosalicylate, and symptoms of salicylate toxicity may be possible, such as: nausea, vomiting, abdominal pain, tachypnea, hyperpnea, tinnitus, and neurologic symptoms (headache, dizziness, confusion, seizures). Severe intoxication with salicylates may lead to electrolyte and blood pH imbalance and potentially to other organ (e.g., renal and liver) damage. There is no specific antidote for mesalamine overdose; however, conventional therapy for salicylate toxicity may be beneficial in the event of acute overdosage and may include gastrointestinal tract decontamination to prevent further absorption.
Correct fluid and electrolyte imbalance by the administration of appropriate intravenous therapy and maintain adequate renal function.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The mechanism of action of mesalamine is not fully understood, but it appears to be a topical anti-inflammatory effect on colonic epithelial cells. Mucosal production of arachidonic acid metabolites, both through the cyclooxygenase pathways (i.e., prostanoids) and through the lipoxygenase pathways (i.e., leukotrienes and hydroxyeicosatetraenoic acids), is increased in patients with ulcerative colitis, and it is possible that mesalamine diminishes inflammation by blocking cyclooxygenase and inhibiting prostaglandin production in the colon.
12.2Pharmacodynamics The exposure-response relationship and time course of pharmacodynamic response for the safety and effectiveness of mesalamine have not been fully characterized.
12.3Pharmacokinetics Absorption Following oral administration 20% to 30% of the mesalamine in PENTASA is absorbed based on urinary excretion data. Plasma mesalamine concentration peaked at approximately 1 mcg/mL 3 hours following a 1 g PENTASA dose. Oral mesalamine pharmacokinetics were nonlinear when PENTASA capsules were dosed from 250 mg to 1 g four times daily, with steady-state mesalamine plasma concentrations increasing about nine times, from 0.14 mcg/mL to 1.21 mcg/mL.
The major metabolite of mesalamine (5-aminosalicylic acid), N-acetyl-5-aminosalicylic acid, peaked at approximately 3 hours at 1.8 mcg/mL. N-acetyl-5-aminosalicylic acid pharmacokinetics were linear. Distribution Mesalamine is approximately 43% bound to plasma proteins at the concentration of 2.5 mcg/mL.
Elimination Metabolism The greater than dose proportional increase in PK of mesalamine suggests saturable first pass metabolism. The major metabolite of mesalamine, N-acetyl-5-aminosalicylic acid, is formed due to action of N-acetyltransferase in the liver and intestinal mucosa. Pharmacological activities of N-acetyl-5-aminosalicylic acid are unknown, and other metabolites have not been identified.
Excretion Following oral administration, plasma mesalamine concentration declined in a biphasic manner after reaching peak concentration. The literature describes a mean terminal half-life of 42 minutes for mesalamine following intravenous administration. Because of the continuous release and absorption of mesalamine from PENTASA throughout the gastrointestinal tract, the true elimination half-life cannot be determined after oral administration.
N-acetyl-5-aminosalicylic acid was the primary compound excreted in the urine (19% to 30%) following PENTASA dosing. About 130 mg free mesalamine was recovered in the feces following a single 1g PENTASA dose. Elimination of free mesalamine and salicylates in feces increased proportionately with PENTASA dose.
🧬 Mechanism of Action ▾
12.1Mechanism of Action The mechanism of action of mesalamine is not fully understood, but it appears to be a topical anti-inflammatory effect on colonic epithelial cells. Mucosal production of arachidonic acid metabolites, both through the cyclooxygenase pathways (i.e., prostanoids) and through the lipoxygenase pathways (i.e., leukotrienes and hydroxyeicosatetraenoic acids), is increased in patients with ulcerative colitis, and it is possible that mesalamine diminishes inflammation by blocking cyclooxygenase and inhibiting prostaglandin production in the colon.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING PENTASA (mesalamine) extended-release capsules are supplied as shown in the table: Strength Description Supplied As NDC Number 250 mg extended-release capsules green and blue capsule with a pentagonal starburst logo and the number 2010 on the green portion of the capsule and S429 250 mg on the blue portion of the capsule bottles of 240 capsules NDC 54092-189-81 500 mg extended-release capsules blue capsule with a pentagonal starburst logo and S429 500 mg on the capsule bottles of 120 capsules NDC 54092-191-12 Store at 25°C (77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
📦 Storage and Handling ▾
Store at 25°C (77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION PENTASA (mesalamine) for oral administration is an extended-release formulation of mesalamine, an aminosalicylate anti-inflammatory agent for gastrointestinal use. Mesalamine (also referred to as 5-aminosalicylic acid or 5-ASA) has the chemical name 5-amino-2-hydroxybenzoic acid. It has a molecular weight of 153.14.
The structural formula is: Each 250 mg capsule contains 250 mg of mesalamine. It also contains the following inactive ingredients: acetylated monoglyceride, castor oil, colloidal silicon dioxide, ethylcellulose, hydroxypropyl methylcellulose, starch, stearic acid, sugar, talc, and white wax. The capsule shell contains D&C Yellow #10, FD&C Blue #1, FD&C Green #3, gelatin, titanium dioxide, and other ingredients.
Each 500 mg capsule contains 500 mg of mesalamine. It also contains the following inactive ingredients: acetylated monoglyceride, castor oil, colloidal silicon dioxide, ethylcellulose, hydroxypropyl methylcellulose, starch, stearic acid, sugar, talc, and white wax. The capsule shell contains FD&C Blue #1, gelatin, titanium dioxide, and other ingredients.
Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Renal Impairment Inform patients that PENTASA may decrease their renal function, especially if they have known renal impairment or are taking nephrotoxic drugs, and periodic monitoring of renal function will be performed while they are on therapy. Advise patients to complete all blood tests ordered by their healthcare provider [see Warnings and Precautions (5.1) ] . Mesalamine-Induced Acute Intolerance Syndrome and Other Hypersensitivity Reactions Instruct patients to stop taking PENTASA and report to their healthcare provider if they experience new or worsening symptoms of acute intolerance syndrome (cramping, abdominal pain, bloody diarrhea, fever, headache, and rash) or other symptoms suggestive of mesalamine-induced hypersensitivity [see Warnings and Precautions (5.2 , 5.3) ] .
Hepatic Failure Advise patients with known liver disease to contact their healthcare provider if they experience signs or symptoms of worsening liver function [see Warnings and Precautions (5.4) ] . Severe Cutaneous Adverse Reactions Inform patients of the signs and symptoms of severe cutaneous adverse reactions. Instruct patients to stop taking PENTASA and report to their healthcare provider at first appearance of a severe cutaneous adverse reaction or other sign of hypersensitivity [see Warnings and Precautions (5.5) ] .
Photosensitivity Advise patients with pre-existing skin conditions to avoid sun exposure, wear protective clothing, and use a broad-spectrum sunscreen when outdoors [see Warnings and Precautions (5.6) ] . Nephrolithiasis Instruct patients to drink an adequate amount of fluids during treatment in order to minimize the risk of kidney stone formation and to contact their healthcare provider if they experience signs or symptoms of a kidney stone (e.g., severe side or back pain, blood in the urine) [see Warnings and Precautions (5.7) ] .
Blood Disorders Inform elderly patients and those taking azathioprine or 6-mercaptopurine of the risk for blood disorders and the need for periodic monitoring of complete blood cell counts and platelet counts while on therapy. Advise patients to complete all blood tests ordered by their healthcare provider [see Drug Interactions (7.2) , Use in Specific Populations (8.5) ] . Administration Instruct patients: Swallow PENTASA capsules whole; do not crush or chew.
Alternatively, the capsule(s) may be opened and the contents sprinkled onto applesauce or yogurt. Urine may become discolored reddish-brown while taking PENTASA when it comes in contact with surfaces or water treated with hypochlorite-containing bleach. If discolored urine is observed, advise patients to observe their urine flow.
Report to the healthcare provider only if urine is discolored on leaving the body, before contact with any surface or water (e.g., in the toilet). Drink an adequate amount of fluids [see Dosage and Administration (2) , Warnings and Precautions (5.7) ] .