
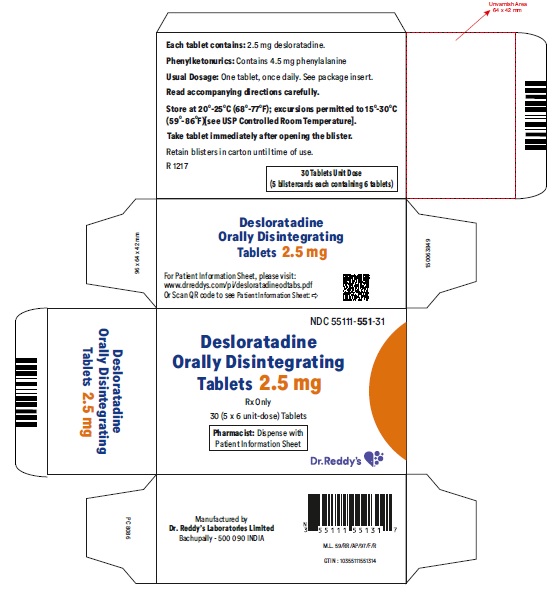
Desloratadine 2.5 mg Tablet, Orally Disintegrating, 6-count — NDC 55111-551-06 (Billing 55111-0551-06)
This is a package of 6 tablets of Desloratadine 2.5 mg Tablet, Orally Disintegrating from Dr. Reddy's Laboratories Limited, marketed since Jan 2013 and currently FDA-listed.
NDC database record
One package, one record: these facts belong to NDC 55111-551-06 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 55111 labeler · 551 product · 06 package
- Package marketed since
- Jan 11, 2013
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Billing quantity
- 6 EA per package
- Barcode (UPC)
- 0355111551317, 0355111360315
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 059683
- GCN: 25439
- GPI-14 (Medi-Span): 41550021007210
- HICL (First Databank): 021934
- AHFS class code: 04:08.00.00
- RxCUI (RxNorm): 403841
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Histamine-1 Receptor Antagonist class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It relieves allergy symptoms from seasonal and year-round allergic rhinitis, like nasal and non-nasal symptoms. It also helps with chronic idiopathic urticaria, which means long-la...
- Take it by mouth once a day, with or without food. If you use the dissolving tablet, put it on your tongue and let it melt right after opening the blister. For liquid, use a droppe...
- Most people have few problems. Some get a sore throat, dry mouth, muscle aches, tiredness or sleepiness. People treated for hives also reported headache, nausea and dizziness.
- Stop the medicine and get help right away if you get a rash, hives, swelling or trouble breathing. Also call about a racing heartbeat, seizures, unusual movements or signs of liver...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Desloratadine — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $4.56 | $27.35 / 6 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 8, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 55111-0551-06 You're viewing this | 6 TABLET, ORALLY DISINTEGRATING in 1 BLISTER PACK | 2013-01-11 | — | Active |
| 55111-0551-31 55111-551-31 Main listing | 5 BLISTER PACK in 1 CARTON / 6 TABLET, ORALLY DISINTEGRATING in 1 BLISTER PACK | 2013-01-11 | — | Active |
This pack shows little to no recent Medicaid volume — a different pack size carries most fills. See all packs ↓
Pack size FAQ
What quantity is in this package?
What NDC number is used to bill for this package of Desloratadine 2.5 mg Tablet, Orally Disintegrating?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Desloratadine 2.5 mgthis 55111-0551-06 | Dr. | 6 tablets | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Desloratadine inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII XF417D3PSL
Anhydrous citric acid is a sour, crystalline powder derived from citric acid with water removed. In medicines, it acts as a buffer to control pH, adds tartness to improve taste, and helps tablets disintegrate.
-
UNII 3SY5LH9PMK
Anhydrous lactose is a milk sugar with no water content. It acts as a filler and binder in tablets and capsules, adding bulk and helping ingredients stick together.
-
UNII Z0H242BBR1
Aspartame is an artificial sweetener made from amino acids. It's added to medicines to improve taste, making bitter or unpleasant-tasting drugs easier to take.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 2S7830E561
Crospovidone is a synthetic polymer derived from povidone. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the active ingredient can be absorbed.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII RCZ785HI7S
A synthetic polymer made from acrylic acid that absorbs moisture. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the active drug can be released and absorbed.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 7CV7WJK4UI
Sodium stearyl fumarate is a synthetic compound made from stearyl alcohol and fumaric acid. It acts as a lubricant and glidant in tablets and capsules, helping ingredients flow smoothly during manufacturing and preventing sticking.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
11 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 8, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Dr. Reddy's Laboratories Limited labeler code 55111
- Divalproex Sodium 500 mg Tablet, Film Coated, Extended Release NDC 55111-534-01
- Venlafaxine hydrochloride 25 mg Tablet NDC 55111-545-01
- Venlafaxine hydrochloride 37.5 mg Tablet NDC 55111-546-01
- Venlafaxine hydrochloride 50 mg Tablet NDC 55111-547-01
- Venlafaxine hydrochloride 75 mg Tablet NDC 55111-548-01
- Venlafaxine hydrochloride 100 mg Tablet NDC 55111-549-01
- Decitabine 50 mg/10mL Injection, Powder, Lyophilized, For Solution NDC 55111-556-10
- Fexofenadine HCl and Pseudoephedrine HCI 180 mg; 240 mg Tablet, Extended Release NDC 55111-557-07
- Atomoxetine 80 mg Capsule NDC 55111-563-05
- Atomoxetine 100 mg Capsule NDC 55111-564-05
- Ibuprofen and Diphenhydramine Citrate 200 mg; 38 mg Tablet NDC 55111-565-05
- Ibandronate sodium 150 mg Tablet NDC 55111-575-03
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Desloratadine is a histamine-1 (H 1 ) receptor antagonist indicated for: Seasonal Allergic Rhinitis: relief of nasal and non-nasal symptoms in patients 2 years of age and older. (1.1) Perennial Allergic Rhinitis: relief of nasal and non-nasal symptoms in patients 6 months of age and older. (1.2) Chronic Idiopathic Urticaria: symptomatic relief of pruritus, reduction in the number of hives, and size of hives in patients 6 months of age and older.
( 1.3 )
1.1Seasonal Allergic Rhinitis Desloratadine orally disintegrating tablets are indicated for the relief of the nasal and non-nasal symptoms of seasonal allergic rhinitis in patients 2 years of age and older.
1.2Perennial Allergic Rhinitis Desloratadine orally disintegrating tablets are indicated for the relief of the nasal and non-nasal symptoms of perennial allergic rhinitis in patients 6 months of age and older.
1.3Chronic Idiopathic Urticaria Desloratadine orally disintegrating tablets are indicated for the symptomatic relief of pruritus, reduction in the number of hives, and size of hives, in patients with chronic idiopathic urticaria 6 months of age and older.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Desloratadine orally disintegrating tablets may be taken without regard to meals. Place desloratadine orally disintegrating tablets on the tongue and allow to disintegrate before swallowing. Tablet disintegration occurs rapidly.
Administer with or without water. Take tablet immediately after opening the blister. Dosage (by age): Adults and Adolescents 12 Years of Age and Over: Desloratadine orally disintegrating tablets - one 5 mg tablet once daily (2) Children 6 to 11 Years of Age: Desloratadine orally disintegrating tablets - one 2.5 mg tablet once daily (2)
2.1Adults and Adolescents 12 Years of Age and Over The recommended dose of desloratadine orally disintegrating tablets is one 5 mg tablet once daily.
2.2Children 6 to 11 Years of Age The recommended dose of desloratadine orally disintegrating tablet is one 2.5 mg tablet once daily. NOTE: Desloratadine orally disintegrating tablets are not recommended for use in pediatric patients under 6 years of age as desloratadine syrup is better suited for these patients.
2.5Adults with Hepatic or Renal Impairment In adult patients with liver or renal impairment, a starting dose of one 5 mg tablet every other day is recommended based on pharmacokinetic data. Dosing recommendation for children with liver or renal impairment cannot be made due to lack of data [see Clinical Pharmacology (12.3) ].
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Desloratadine orally disintegrating tablets USP, 2.5 mg are light red colored, speckled, round, flat, uncoated, beveled edged debossed with “R” on one side and “551” on the other side. Desloratadine orally disintegrating tablets USP, 5 mg are light red colored, speckled, round, flat, uncoated, beveled edged debossed with “RDY” on one side and “360” on the other side. Desloratadine orally-disintegrating tablets - 5 mg (3) Desloratadine orally-disintegrating tablets - 2.5 mg (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Desloratadine orally disintegrating tablets are contraindicated in patients who are hypersensitive to this medication or to any of its ingredients or to loratadine [see Warnings and Precautions (5.1) and Adverse Reactions (6.2) ]. Hypersensitivity ( 4 , 6.2 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hypersensitivity reactions including rash, pruritus, urticaria, edema, dyspnea, and anaphylaxis have been reported. In such cases, stop desloratadine orally disintegrating tablets at once and consider alternative treatments. (5.1)
5.1Hypersensitivity Reactions Hypersensitivity reactions including rash, pruritus, urticaria, edema, dyspnea, and anaphylaxis have been reported after administration of desloratadine. If such a reaction occurs, therapy with desloratadine should be stopped and alternative treatment should be considered. [see Adverse Reactions (6.2) ]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in greater detail in other sections of the label: Hypersensitivity reactions [see Warnings and Precautions (5.1) . ] The most common adverse reactions (reported in ≥2% of adult and adolescent patients with allergic rhinitis and greater than placebo) were pharyngitis, dry mouth, myalgia, fatigue, somnolence, dysmenorrhea. (6.1) To report SUSPECTED ADVERSE REACTIONS, contact Dr. Reddy’s Laboratories Inc., at 1-888-375-3784 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. Adults and Adolescents Allergic Rhinitis: In multiple-dose placebo-controlled trials, 2,834 patients ages 12 years or older received desloratadine tablets at doses of 2.5 mg to 20 mg daily, of whom 1,655 patients received the recommended daily dose of 5 mg.
In patients receiving 5 mg daily, the rate of adverse events was similar between desloratadine and placebo-treated patients. The percent of patients who withdrew prematurely due to adverse events was 2.4% in the desloratadine group and 2.6% in the placebo group. There were no serious adverse events in these trials in patients receiving desloratadine.
All adverse events that were reported by greater than or equal to 2% of patients who received the recommended daily dose of desloratadine tablets (5 mg once daily), and that were more common with desloratadine tablets than placebo, are listed in Table 1. Table 1: Incidence of Adverse Events Reported by ≥2% of Adult and Adolescent Allergic Rhinitis Patients Receiving Desloratadine Tablets Adverse Event Desloratadine Tablets 5 mg (n=1655) Placebo (n=1652) Infections and Infestations Pharyngitis 4.1% 2.0% Nervous System Disorders Somnolence 2.1% 1.8% Gastrointestinal Disorders Dry Mouth 3.0% 1.9% Musculoskeletal and Connective Tissue Disorders Myalgia 2.1% 1.8% Reproductive System and Breast Disorders Dysmenorrhea 2.1% 1.6% General Disorders and Administration Site Conditions Fatigue 2.1% 1.2% The frequency and magnitude of laboratory and electrocardiographic abnormalities were similar in desloratadine and placebo-treated patients.
There were no differences in adverse events for subgroups of patients as defined by gender, age, or race. Chronic Idiopathic Urticaria: In multiple-dose, placebo-controlled trials of chronic idiopathic urticaria, 211 patients ages 12 years or older received desloratadine and 205 received placebo. Adverse events that were reported by greater than or equal to 2% of patients who received desloratadine and that were more common with desloratadine than placebo were (rates for desloratadine and placebo, respectively): headache (14%, 13%), nausea (5%, 2%), fatigue (5%, 1%), dizziness (4%, 3%), pharyngitis (3%, 2%), dyspepsia (3%, 1%), and myalgia (3%, 1%).
Pediatrics Two hundred and forty-six pediatric subjects 6 months to 11 years of age received desloratadine for 15 days in three placebo-controlled clinical trials. Pediatric subjects aged 6 to 11 years received 2.5 mg once a day, subjects aged 1 to 5 years received 1.25 mg once a day, and subjects 6 to 11 months of age received 1 mg once a day. In subjects 6 to 11 years of age, no individual adverse event was reported by 2 percent or more of the subjects.
In subjects 2 to 5 years of age, adverse events reported for desloratadine and placebo in at least 2 percent of subjects receiving desloratadine and at a frequency greater than placebo were fever (5.5%, 5.4%), urinary tract infection (3.6%, 0%) and varicella (3.6%, 0%). In subjects 12 months to 23 months of age, adverse events reported for the desloratadine product and placebo in at least 2 percent of subjects receiving desloratadine and at a frequency greater than placebo were… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS
7.1Inhibitors of Cytochrome P450 3A4 In controlled clinical studies co-administration of desloratadine with ketoconazole, erythromycin, or azithromycin resulted in increased plasma concentrations of desloratadine and 3 hydroxy desloratadine, but there were no clinically relevant changes in the safety profile of desloratadine. [see Clinical Pharmacology (12.3) . ]
7.2Fluoxetine In controlled clinical studies co-administration of desloratadine with fluoxetine, a selective serotonin reuptake inhibitor (SSRI), resulted in increased plasma concentrations of desloratadine and 3 hydroxydesloratadine, but there were no clinically relevant changes in the safety profile of desloratadine. [see Clinical Pharmacology (12.3) .]
7.3Cimetidine In controlled clinical studies co-administration of desloratadine with cimetidine, a histamine H 2 -receptor antagonist, resulted in increased plasma concentrations of desloratadine and 3 hydroxydesloratadine, but there were no clinically relevant changes in the safety profile of desloratadine. [see Clinical Pharmacology (12.3) .]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Renal impairment: dosage adjustment is recommended ( 2.5 , 8.6 , 12.3 ) Hepatic impairment: dosage adjustment is recommended ( 2.5 , 8.7 , 12.3 )
8.1Pregnancy Risk Summary The limited available data with desloratadine in pregnant women are not sufficient to inform a drug-associated risk for major birth defects and miscarriage. There are no adequate and well‑controlled studies in pregnant women. Desloratadine given during organogenesis to pregnant rats was not teratogenic at the summed area under the concentration-time curve (AUC)‑based exposures of desloratadine and its metabolite approximately 320 times that at the recommended human daily oral dose (RHD) of 5 mg/day.
Desloratadine given during organogenesis to pregnant rabbits was not teratogenic at the AUC-based exposures of desloratadine approximately 230 times that at the RHD. Desloratadine given to pregnant rats during organogenesis through lactation resulted in reduced body weight and slow righting reflex of F 1 pups at the summed AUC-based exposures of desloratadine and its metabolite approximately 70 times or greater than that at the RHD [see Data]. The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data Desloratadine was given orally during organogenesis to pregnant rats at doses of 6, 24 and 48 mg/kg/day (approximately 50, 200 and 320 times the summed AUC-based exposure of desloratadine and its metabolite at the RHD). No fetal malformations were present.
Reduced fetal weights and skeletal variations noted at doses of 24 and 48 mg/kg/day were likely secondary to the maternal toxicities of reduced body weight gain and food consumption observed at the same doses. Desloratadine was also given orally during organogenesis to pregnant rabbits at doses of 15, 30 and 60 mg/kg/day (approximately 30, 70 and 230 times the AUC-based exposure of desloratadine at the RHD). No adverse effects to the fetus were noted.
Reduced maternal body weight gain was noted in rabbits at 60 mg/kg/day. In a peri-and post-natal development study, desloratadine was given to rats orally during the peri-natal (Gestation Day 6) through lactation periods (Postpartum Day 21) at doses of 3, 9 and 18 mg/kg/day. Reduced body weight and slow righting reflex were reported in F 1 pups at doses of 9 mg/kg/day or greater (approximately 70 times or greater than the summed AUC-based exposure of desloratadine and its metabolite at the RHD).
Desloratadine had no effect on F 1 pup development at 3 mg/kg/day (approximately 10 times the summed AUC-based exposure of desloratadine and its metabolite at the RHD). Maternal toxicities including reduced body weight gain and food consumption were noted at 18 mg/kg/day for F 0 dams. F 1 offspring were subsequently mated and there was no developmental toxicity for F 2 pups observed.
8.2Lactation Risk Summary Desloratadine passes into breast milk. There are not sufficient data on the effects of desloratadine on the breastfed infant or the effects of desloratadine on milk production. The decision should be made whether to discontinue nursing or to discontinue desloratadine, taking into account the developmental and health benefits of breastfeeding, the nursing mother’s clinical need, and any potential adverse effects on the breastfed infant from desloratadine or from the underlying maternal condition.
8.3Females and Males of Reproductive Potential Infertility There are no data available on human infertility associated with desloratadine. There were no clinically relevant effects of desloratadine on female fertility in rats. A male specific decrease in fertility occurred at an oral desloratadine dose of 12 mg/kg or greater in rats (approximately 65 times the summed AUC-based exposure of desloratadine… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary The limited available data with desloratadine in pregnant women are not sufficient to inform a drug-associated risk for major birth defects and miscarriage. There are no adequate and well‑controlled studies in pregnant women. Desloratadine given during organogenesis to pregnant rats was not teratogenic at the summed area under the concentration-time curve (AUC)‑based exposures of desloratadine and its metabolite approximately 320 times that at the recommended human daily oral dose (RHD) of 5 mg/day.
Desloratadine given during organogenesis to pregnant rabbits was not teratogenic at the AUC-based exposures of desloratadine approximately 230 times that at the RHD. Desloratadine given to pregnant rats during organogenesis through lactation resulted in reduced body weight and slow righting reflex of F 1 pups at the summed AUC-based exposures of desloratadine and its metabolite approximately 70 times or greater than that at the RHD [see Data]. The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data Desloratadine was given orally during organogenesis to pregnant rats at doses of 6, 24 and 48 mg/kg/day (approximately 50, 200 and 320 times the summed AUC-based exposure of desloratadine and its metabolite at the RHD). No fetal malformations were present.
Reduced fetal weights and skeletal variations noted at doses of 24 and 48 mg/kg/day were likely secondary to the maternal toxicities of reduced body weight gain and food consumption observed at the same doses. Desloratadine was also given orally during organogenesis to pregnant rabbits at doses of 15, 30 and 60 mg/kg/day (approximately 30, 70 and 230 times the AUC-based exposure of desloratadine at the RHD). No adverse effects to the fetus were noted.
Reduced maternal body weight gain was noted in rabbits at 60 mg/kg/day. In a peri-and post-natal development study, desloratadine was given to rats orally during the peri-natal (Gestation Day 6) through lactation periods (Postpartum Day 21) at doses of 3, 9 and 18 mg/kg/day. Reduced body weight and slow righting reflex were reported in F 1 pups at doses of 9 mg/kg/day or greater (approximately 70 times or greater than the summed AUC-based exposure of desloratadine and its metabolite at the RHD).
Desloratadine had no effect on F 1 pup development at 3 mg/kg/day (approximately 10 times the summed AUC-based exposure of desloratadine and its metabolite at the RHD). Maternal toxicities including reduced body weight gain and food consumption were noted at 18 mg/kg/day for F 0 dams. F 1 offspring were subsequently mated and there was no developmental toxicity for F 2 pups observed.
🧒 Pediatric Use ▾
8.4Pediatric Use The desloratadine orally disintegrating 2.5 mg tablet has not been evaluated in pediatric patients. Bioequivalence of the desloratadine orally disintegrating tablet and the previously marketed orally disintegrating tablet was established in adults. In conjunction with the dose finding studies in pediatrics described, the pharmacokinetic data for desloratadine orally disintegrating tablet supports the use of the 2.5 mg dose strength in pediatric patients 6 to 11 years of age.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of desloratadine did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identifiied differences between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy [see Clinical Pharmacology (12.3) ]
🆘 Overdosage ▾
10 OVERDOSAGE In the event of overdose, consider standard measures to remove any unabsorbed drug. Symptomatic and supportive treatment is recommended. Desloratadine and 3-hydroxydesloratadine are not eliminated by hemodialysis.
Information regarding acute overdosage is limited to experience from post-marketing adverse event reports and from clinical trials conducted during the development of the desloratadine product. In a dose-ranging trial, at doses of 10 mg and 20 mg/day somnolence was reported. In another study, no clinically relevant adverse events were reported in normal male and female volunteers who were given single daily doses of desloratadine 45 mg for 10 days [see Clinical Pharmacology (12.2) ].
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Desloratadine is a long-acting tricyclic histamine antagonist with selective H 1 -receptor histamine antagonist activity. Receptor binding data indicates that at a concentration of 2 to 3 ng/mL (7 nanomolar), desloratadine shows significant interaction with the human histamine H 1 -receptor. Desloratadine inhibited histamine release from human mast cells in vitro.
Results of a radiolabeled tissue distribution study in rats and a radioligand H 1 -receptor binding study in guinea pigs showed that desloratadine did not readily cross the blood brain barrier. The clinical significance of this finding is unknown.
12.2Pharmacodynamics Wheal and Flare: Human histamine skin wheal studies following single and repeated 5 mg doses of desloratadine have shown that the drug exhibits an antihistaminic effect by 1 hour; this activity may persist for as long as 24 hours. There was no evidence of histamine-induced skin wheal tachyphylaxis within the desloratadine 5 mg group over the 28-day treatment period. The clinical relevance of histamine wheal skin testing is unknown.
Effects on QT c : Single daily doses of 45 mg were given to normal male and female volunteers for 10 days. All ECGs obtained in this study were manually read in a blinded fashion by a cardiologist. In desloratadine-treated subjects, there was an increase in mean heart rate of 9.2 bpm relative to placebo.
The QT interval was corrected for heart rate (QT c ) by both the Bazett and Fridericia methods. Using the QT c (Bazett) there was a mean increase of 8.1 msec in desloratadine-treated subjects relative to placebo. Using QT c (Fridericia) there was a mean increase of 0.4 msec in desloratadine-treated subjects relative to placebo.
No clinically relevant adverse events were reported.
12.3Pharmacokinetics Absorption The pharmacokinetic profile of desloratadine orally disintegrating tablets was evaluated in a three-way crossover study in 24 adult volunteers. A single desloratadine orally disintegrating tablets containing 5 mg of desloratadine was bioequivalent to a single 5 mg desloratadine orally disintegrating tablets (original formulation) for both desloratadine and 3-hydroxydesloratadine. Food and water had no effect on the bioavailability (AUC and C max ) of desloratadine orally disintegrating tablets.
Distribution Desloratadine and 3-hydroxydesloratadine are approximately 82% to 87% and 85% to 89% bound to plasma proteins, respectively. Protein binding of desloratadine and 3-hydroxydesloratadine was unaltered in subjects with impaired renal function. Metabolism Desloratadine (a major metabolite of loratadine) is extensively metabolized to 3-hydroxydesloratadine, an active metabolite, which is subsequently glucuronidated.
The enzyme(s) responsible for the formation of 3-hydroxydesloratadine have not been identified. Data from clinical trials indicate that a subset of the general population has a decreased ability to form 3-hydroxydesloratadine, and are poor metabolizers of desloratadine. In pharmacokinetic studies (n=3748), approximately 6% of subjects were poor metabolizers of desloratadine (defined as a subject with an AUC ratio of 3-hydroxydesloratadine to desloratadine less than 0.1, or a subject with a desloratadine half-life exceeding 50 hours).
These pharmacokinetic studies included subjects between the ages of 2 and 70 years, including 977 subjects aged 2 to 5 years, 1,575 subjects aged 6 to 11 years, and 1,196 subjects aged 12 to 70 years. There was no difference in the prevalence of poor metabolizers across age groups. The frequency of poor metabolizers was higher in Blacks (17%, n=988) as compared to Caucasians (2%, n=1,462) and Hispanics (2%, n=1,063).
The median exposure (AUC) to desloratadine in the poor metabolizers was approximately 6-fold greater than in the subjects who are not poor metabolizers. Subjects who are poor metabolizers of desloratadine cannot be prospectively identified and will be exposed to hig… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Desloratadine is a long-acting tricyclic histamine antagonist with selective H 1 -receptor histamine antagonist activity. Receptor binding data indicates that at a concentration of 2 to 3 ng/mL (7 nanomolar), desloratadine shows significant interaction with the human histamine H 1 -receptor. Desloratadine inhibited histamine release from human mast cells in vitro.
Results of a radiolabeled tissue distribution study in rats and a radioligand H 1 -receptor binding study in guinea pigs showed that desloratadine did not readily cross the blood brain barrier. The clinical significance of this finding is unknown.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Desloratadine Orally Disintegrating Tablets USP, 2.5 mg: Desloratadine orally disintegrating tablets USP, tablets 2.5 mg are light red colored, speckled, round, flat, uncoated, beveled edged debossed with “R” on one side and “551” on the other side and are supplied in carton of 5 packs containing 6 tablets each. Carton of 5 packs (NDC 55111-551-31), each pack containing 6 tablets (55111-551-06) Desloratadine Orally Disintegrating Tablets USP, 5 mg: Desloratadine orally disintegrating tablets USP, tablets 5 mg are light red colored, speckled, round, flat, uncoated, beveled edged debossed with “RDY” on one side and “360” on the other side and are supplied in carton of 5 packs containing 6 tablets each.
Carton of 5 packs (NDC 55111-360-31), each pack containing 6 tablets (55111-360-06) Storage: Store orally disintegrating tablets at 20°C to 25°C (68°F to 77°F) excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION The desloratadine orally disintegrating tablets, USP light red colored, speckled, round, flat, uncoated, beveled edged debossed with “R” on one side and “551” on the other side for the 2.5 mg tablets and a “light red colored, speckled, round, flat, uncoated, beveled edged debossed with “RDY” on one side and “360” on the other side for the 5 mg tablets. Each orally disintegrating tablet contains either 5 mg or 2.5 mg of desloratadine. It also contains the following inactive ingredients: anhydrous citric acid, aspartame, colloidal silicon dioxide, crospovidone, ferric oxide, mannitol, lactose anhydrous, microcrystalline cellulose, polacrilex resin, sodium stearyl fumarate, talc, tutti frutti flavor.
Desloratadine, USP is a white to light pink colored powder that is soluble in dichloromethane. It has an molecular formula: C 19 H 19 ClN 2 and a molecular weight of 310.8. The chemical name is 8-chloro-6,11-dihydro-11-(4-piperdinylidene)-5H-benzo[5,6]cyclohepta[1,2-b]pyridine and has the following structure:
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information).
17.1Information for Patients Patients should be instructed to use desloratadine as directed. As there are no food effects on bioavailability, patients can be instructed that desloratadine orally disintegrating tablets may be taken without regard to meals. Patients should be advised not to increase the dose or dosing frequency as studies have not demonstrated increased effectiveness at higher doses and somnolence may occur.
Phenylketonurics: Desloratadine orally disintegrating tablets contain phenylalanine 10.08 mg per 5 mg or 5.04 mg per 2.5 mg desloratadine orally disintegrating tablets.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption The pharmacokinetic profile of desloratadine orally disintegrating tablets was evaluated in a three-way crossover study in 24 adult volunteers. A single desloratadine orally disintegrating tablets containing 5 mg of desloratadine was bioequivalent to a single 5 mg desloratadine orally disintegrating tablets (original formulation) for both desloratadine and 3-hydroxydesloratadine. Food and water had no effect on the bioavailability (AUC and C max ) of desloratadine orally disintegrating tablets.
Distribution Desloratadine and 3-hydroxydesloratadine are approximately 82% to 87% and 85% to 89% bound to plasma proteins, respectively. Protein binding of desloratadine and 3-hydroxydesloratadine was unaltered in subjects with impaired renal function. Metabolism Desloratadine (a major metabolite of loratadine) is extensively metabolized to 3-hydroxydesloratadine, an active metabolite, which is subsequently glucuronidated.
The enzyme(s) responsible for the formation of 3-hydroxydesloratadine have not been identified. Data from clinical trials indicate that a subset of the general population has a decreased ability to form 3-hydroxydesloratadine, and are poor metabolizers of desloratadine. In pharmacokinetic studies (n=3748), approximately 6% of subjects were poor metabolizers of desloratadine (defined as a subject with an AUC ratio of 3-hydroxydesloratadine to desloratadine less than 0.1, or a subject with a desloratadine half-life exceeding 50 hours).
These pharmacokinetic studies included subjects between the ages of 2 and 70 years, including 977 subjects aged 2 to 5 years, 1,575 subjects aged 6 to 11 years, and 1,196 subjects aged 12 to 70 years. There was no difference in the prevalence of poor metabolizers across age groups. The frequency of poor metabolizers was higher in Blacks (17%, n=988) as compared to Caucasians (2%, n=1,462) and Hispanics (2%, n=1,063).
The median exposure (AUC) to desloratadine in the poor metabolizers was approximately 6-fold greater than in the subjects who are not poor metabolizers. Subjects who are poor metabolizers of desloratadine cannot be prospectively identified and will be exposed to higher levels of desloratadine following dosing with the recommended dose of desloratadine. In multidose clinical safety studies, where metabolizer status was identified, a total of 94 poor metabolizers and 123 normal metabolizers were enrolled and treated with desloratadine oral solution for 15 to 35 days.
In these studies, no overall differences in safety were observed between poor metabolizers and normal metabolizers. Although not seen in these studies, an increased risk of exposure-related adverse events in patients who are poor metabolizers cannot be ruled out. Elimination The mean plasma elimination half-life of desloratadine was approximately 27 hours.
C max and AUC values increased in a dose proportional manner following single oral doses between 5 and 20 mg. The degree of accumulation after 14 days of dosing was consistent with the half-life and dosing frequency. A human mass balance study documented a recovery of approximately 87% of the 14 C-desloratadine dose, which was equally distributed in urine and feces as metabolic products.
Analysis of plasma 3-hydroxydesloratadine showed similar T max and half-life values compared to desloratadine. Special Populations Geriatric Subjects: In older subjects (≥65 years old; n=17) following multiple-dose administration of desloratadine tablets, the mean C max and AUC values for desloratadine were 20% greater than in younger subjects (<65 years old). The oral total body clearance (CL/F) when normalized for body weight was similar between the two age groups.
The mean plasma elimination half-life of desloratadine was 33.7 hr in subjects ≥65 years old. The pharmacokinetics for 3-hydroxydesloratadine appeared unchanged in older versus younger subjects. These age-related differences are unlikely to be clinically relevant and no dosage adjust… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Wheal and Flare: Human histamine skin wheal studies following single and repeated 5 mg doses of desloratadine have shown that the drug exhibits an antihistaminic effect by 1 hour; this activity may persist for as long as 24 hours. There was no evidence of histamine-induced skin wheal tachyphylaxis within the desloratadine 5 mg group over the 28-day treatment period. The clinical relevance of histamine wheal skin testing is unknown.
Effects on QT c : Single daily doses of 45 mg were given to normal male and female volunteers for 10 days. All ECGs obtained in this study were manually read in a blinded fashion by a cardiologist. In desloratadine-treated subjects, there was an increase in mean heart rate of 9.2 bpm relative to placebo.
The QT interval was corrected for heart rate (QT c ) by both the Bazett and Fridericia methods. Using the QT c (Bazett) there was a mean increase of 8.1 msec in desloratadine-treated subjects relative to placebo. Using QT c (Fridericia) there was a mean increase of 0.4 msec in desloratadine-treated subjects relative to placebo.
No clinically relevant adverse events were reported.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Seasonal Allergic Rhinitis The clinical efficacy and safety of desloratadine tablets were evaluated in over 2,300 patients 12 to 75 years of age with seasonal allergic rhinitis. A total of 1,838 patients received 2.5 to 20 mg/day of desloratadine in 4 double-blind, randomized, placebo-controlled clinical trials of 2 to 4 weeks’ duration conducted in the United States. The results of these studies demonstrated the efficacy and safety of desloratadine 5 mg in the treatment of adult and adolescent patients with seasonal allergic rhinitis.
In a dose-ranging trial, desloratadine 2.5 to 20 mg/day was studied. Doses of 5, 7.5, 10, and 20 mg/day were superior to placebo; and no additional benefit was seen at doses above 5.0 mg. In the same study, an increase in the incidence of somnolence was observed at doses of 10 mg/day and 20 mg/day (5.2% and 7.6%, respectively), compared to placebo (2.3%).
In two 4-week studies of 924 patients (aged 15 to 75 years) with seasonal allergic rhinitis and concomitant asthma, desloratadine tablets 5 mg once daily improved rhinitis symptoms, with no decrease in pulmonary function. This supports the safety of administering desloratadine tablets to adult patients with seasonal allergic rhinitis with mild to moderate asthma. Desloratadine tablets 5 mg once daily significantly reduced the Total Symptom Score (the sum of individual scores of nasal and non-nasal symptoms) in patients with seasonal allergic rhinitis.
See Table 3. Table 3: TOTAL SYMPTOM SCORE (TSS) Changes in a 2-Week Clinical Trial in Patients with Seasonal Allergic Rhinitis Treatment Group (n) Mean Baseline* (SEM) Change from Baseline † (SEM) Placebo Comparison (P-value) Desloratadine 5.0 mg (171) 14.2 (0.3) -4.3 (0.3) P<0.01 Placebo (173) 13.7 (0.3) -2.5 (0.3) SEM=Standard Error of the Mean *At baseline, a total nasal symptom score (sum of 4 individual symptoms) of at least 6 and a total non-nasal symptom score (sum of 4 individual symptoms) of at least 5 (each symptom scored 0 to 3 where 0=no symptom and 3=severe symptoms) was required for trial eligibility.
TSS ranges from 0=no symptoms to 24=maximal symptoms. † Mean reduction in TSS averaged over the 2-week treatment period. There were no significant differences in the effectiveness of desloratadine tablets 5 mg across subgroups of patients defined by gender, age, or race.
14.2Perennial Allergic Rhinitis The clinical efficacy and safety of desloratadine tablets 5 mg were evaluated in over 1,300 patients 12 to 80 years of age with perennial allergic rhinitis. A total of 685 patients received 5 mg/day of desloratadine in two double-blind, randomized, placebo-controlled clinical trials of 4 weeks’ duration conducted in the United States and internationally. In one of these studies desloratadine tablets 5 mg once daily was shown to significantly reduce the Total Symptom Score in patients with perennial allergic rhinitis (Table 4).
Table 4: TOTAL SYMPTOM SCORE (TSS) Changes in a 4-Week Clinical Trial in Patients with Perennial Allergic Rhinitis Treatment Group (n) Mean Baseline* (SEM) Change from Baseline † (SEM) Placebo Comparison (P-value) Desloratadine 5.0 mg (337) 12.37 (0.18) -4.06 (0.21) P=0.01 Placebo (337) 12.30 (0.18) -3.27 (0.21) SEM=Standard Error of the Mean * At baseline, average of total symptom score (sum of 5 individual nasal symptoms and 3 non-nasal symptoms, each symptom scored 0 to 3 where 0=no symptom and 3=severe symptoms) of atleast 10 was required for trial eligibility.
TSS ranges from 0=no symptoms to 24=maximal symptoms. † Mean reduction in TSS averaged over the 4-week treatment period.
14.3Chronic Idiopathic Urticaria The efficacy and safety of desloratadine 5 mg once daily was studied in 416 chronic idiopathic urticaria patients 12 to 84 years of age, of whom 211 received desloratadine. In two double-blind, placebo-controlled, randomized clinical trials of six weeks duration, at the pre-specified one-week primary time point evaluation, desl… [Excerpted — this section continues on DailyMed.]
🔒 Drug Abuse and Dependence ▾
9 DRUG ABUSE AND DEPENDENCE There is no information to indicate that abuse or dependency occurs with desloratadine tablets.
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity Studies The carcinogenic potential of desloratadine was assessed using a loratadine study in rats and a desloratadine study in mice. In a 2-year study in rats, loratadine was administered in the diet at doses up to 25 mg/kg/day (approximately 45 times the summed AUC-based exposure of desloratadine and its metabolite at the RHD). A significantly higher incidence of hepatocellular tumors (combined adenomas and carcinomas) was observed in males given 10 mg/kg/day of loratadine (approximately 10 times the summed AUC-based exposure of desloratadine and its metabolite at the RHD) and in males and females given 25 mg/kg/day of loratadine.
The clinical significance of these findings during long-term use of desloratadine is not known. In a 2-year dietary study in mice, males and females given up to 16 mg/kg/day and 32 mg/kg/day desloratadine, respectively (approximately 30 and 70 times the summed AUC-based exposure of desloratadine and its metabolite at the RHD, respectively), did not show significant increases in the incidence of any tumors. Genotoxicity Studies In genotoxicity studies with desloratadine, there was no evidence of genotoxic potential in a reverse mutation assay ( Salmonella/E. coli mammalian microsome bacterial mutagenicity assay) or in 2 assays for chromosomal aberrations (human peripheral blood lymphocyte clastogenicity assay and mouse bone marrow micronucleus assay).
Impairment of Fertility In a female fertility study, desloratadine was given to female rats orally 14 days prior to and throughout mating until Gestation Day 7 at doses of 6, 12 and 24 mg/kg/day. An increase in preimplantation loss and a decrease in number of implantations and fetuses noted at 24 mg/kg (approximately 200 times the summed AUC-based exposure of desloratadine and its metabolite at the RHD) was likely due to maternal toxicities including reduced body weight gain and food consumption. In a male fertility study in rats, desloratadine was given orally to male rats for 70 days prior to mating and throughout the mating period (total dosing period 106 to 108 days) at doses of 3, 12 and 40 mg/kg/day.
Reduced body weight gain, food consumption, and absolute organ weights of testes, epididymis, and cauda epididymis were noted at 40 mg/kg/day. A male‑specific decrease in fertility, demonstrated by reduced female conception rates, decreased sperm numbers and motility, and histopathologic changes in testes and epididymis, occurred at a dose of 12 mg/kg or greater (approximately 65 times or greater than the summed AUC-based exposure of desloratadine and its metabolite at the RHD). Desloratadine had no effect on male fertility in rats at 3 mg/kg/day (approximately 10 times the summed AUC-based exposure of desloratadine and its metabolite at the RHD).
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity Studies The carcinogenic potential of desloratadine was assessed using a loratadine study in rats and a desloratadine study in mice. In a 2-year study in rats, loratadine was administered in the diet at doses up to 25 mg/kg/day (approximately 45 times the summed AUC-based exposure of desloratadine and its metabolite at the RHD). A significantly higher incidence of hepatocellular tumors (combined adenomas and carcinomas) was observed in males given 10 mg/kg/day of loratadine (approximately 10 times the summed AUC-based exposure of desloratadine and its metabolite at the RHD) and in males and females given 25 mg/kg/day of loratadine.
The clinical significance of these findings during long-term use of desloratadine is not known. In a 2-year dietary study in mice, males and females given up to 16 mg/kg/day and 32 mg/kg/day desloratadine, respectively (approximately 30 and 70 times the summed AUC-based exposure of desloratadine and its metabolite at the RHD, respectively), did not show significant increases in the incidence of any tumors. Genotoxicity Studies In genotoxicity studies with desloratadine, there was no evidence of genotoxic potential in a reverse mutation assay ( Salmonella/E. coli mammalian microsome bacterial mutagenicity assay) or in 2 assays for chromosomal aberrations (human peripheral blood lymphocyte clastogenicity assay and mouse bone marrow micronucleus assay).
Impairment of Fertility In a female fertility study, desloratadine was given to female rats orally 14 days prior to and throughout mating until Gestation Day 7 at doses of 6, 12 and 24 mg/kg/day. An increase in preimplantation loss and a decrease in number of implantations and fetuses noted at 24 mg/kg (approximately 200 times the summed AUC-based exposure of desloratadine and its metabolite at the RHD) was likely due to maternal toxicities including reduced body weight gain and food consumption. In a male fertility study in rats, desloratadine was given orally to male rats for 70 days prior to mating and throughout the mating period (total dosing period 106 to 108 days) at doses of 3, 12 and 40 mg/kg/day.
Reduced body weight gain, food consumption, and absolute organ weights of testes, epididymis, and cauda epididymis were noted at 40 mg/kg/day. A male‑specific decrease in fertility, demonstrated by reduced female conception rates, decreased sperm numbers and motility, and histopathologic changes in testes and epididymis, occurred at a dose of 12 mg/kg or greater (approximately 65 times or greater than the summed AUC-based exposure of desloratadine and its metabolite at the RHD). Desloratadine had no effect on male fertility in rats at 3 mg/kg/day (approximately 10 times the summed AUC-based exposure of desloratadine and its metabolite at the RHD).
📄 Patient Package Insert ▾
PATIENT INFORMATION Desloratadine Orally Disintegrating Tablets, USP (des′′ lor a′ ta deen) Read the Patient Information that comes with desloratadine before you start taking it and each time you get a refill. There may be new information. This leaflet is a summary of the information for patients.
Your doctor or pharmacist can give you additional information. This leaflet does not take the place of talking to your doctor about your medical condition or treatment. What is desloratadine?
Desloratadine is a prescription medicine that contains the medicine desloratadine (an antihistamine). Desloratadine is used to help control the symptoms of: seasonal allergic rhinitis (sneezing, stuffy nose, runny nose and itching of the nose) in people 2 years of age and older. perennial allergic rhinitis (sneezing, stuffy nose, runny nose and itching of the nose) in people 6 months of age and older. chronic idiopathic urticaria (long-term itching) and to reduce the number and size of hives in people 6 months of age and older.
Desloratadine is not for children younger than 6 months of age. Who should not take desloratadine orally disintegrating tablets? Do not take desloratadine if you: are allergic to desloratadine or any of the ingredients in desloratadine orally disintegrating tablets.
See the end of this leaflet for a complete list of ingredients. are allergic to loratadine (Alavert, Claritin). Talk to your doctor before taking this medicine if you have any questions about whether or not to take this medicine. What should I tell my doctor before taking desloratadine orally disintegrating tablets?
Before you take desloratadine, tell your doctor if you: have liver or kidney problems. have any other medical conditions. are pregnant or plan to become pregnant. It is not known if desloratadine will harm your unborn baby. Talk to your doctor if you are pregnant or plan to become pregnant. are breast-feeding or plan to breast-feed.
Desloratadine can pass into your breast milk . Talk to your doctor about the best way to feed your baby if you take desloratadine. Tell your doctor about all the medicines you take, including prescription and non-prescription medicines, vitamins and herbal supplements.
Desloratadine may affect the way other medicines work, and other medicines may affect how desloratadine works. Especially tell your doctor if you take: ketoconazole (Nizoral) erythromycin (Ery-tab, Eryc, PCE) azithromycin (Zithromax, Zmax) antihistaminesfluoxetine (Prozac) cimetidine (Tagamet) Know the medicines you take. Keep a list of your medicines and show it to your doctor and pharmacist when you get a new medicine.
How should I take desloratadine orally disintegrating tablets? Take desloratadine exactly as your doctor tells you to take it. Do not change your dose of desloratadine or take more often than prescribed.
Desloratadine can be taken with or without food. Place desloratadine orally disintegrating tablets on your tongue and allow it to dissolve before swallowing. Desloratadine orally disintegrating tablets can be taken with or without water.
Take your desloratadine orally disintegrating tablets right away after opening the blister. If you take too much desloratadine, call your doctor or get medical attention right away. What are the possible side effects of desloratadine orally disintegrating tablets?
Desloratadine may cause serious side effects, including: Allergic reactions. Stop taking desloratadine and call your doctor right away or get emergency help if you have any of these symptoms: rash itching hives swelling of your lips, tongue, face, and throat shortness of breath or trouble breathing The most common side effects of desloratadine in adults and children 12 years of age and older with allergic rhinitis include: sore throat dry mouth muscle pain tiredness sleepiness menstrual pain Increased sleepiness or tiredness can happen if you take more desloratadine than your doctor prescribed to you.
Tell your doctor if you have any side effect… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
Package Label. Principal Display Panel Desloratadine Orally Disintegrating Tablets, 2.5 mg - Blister Carton Label
Desloratadine Orally Disintegrating Tablets , 5 mg - Blister Carton Label
Medicaid utilization by pack size
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |