
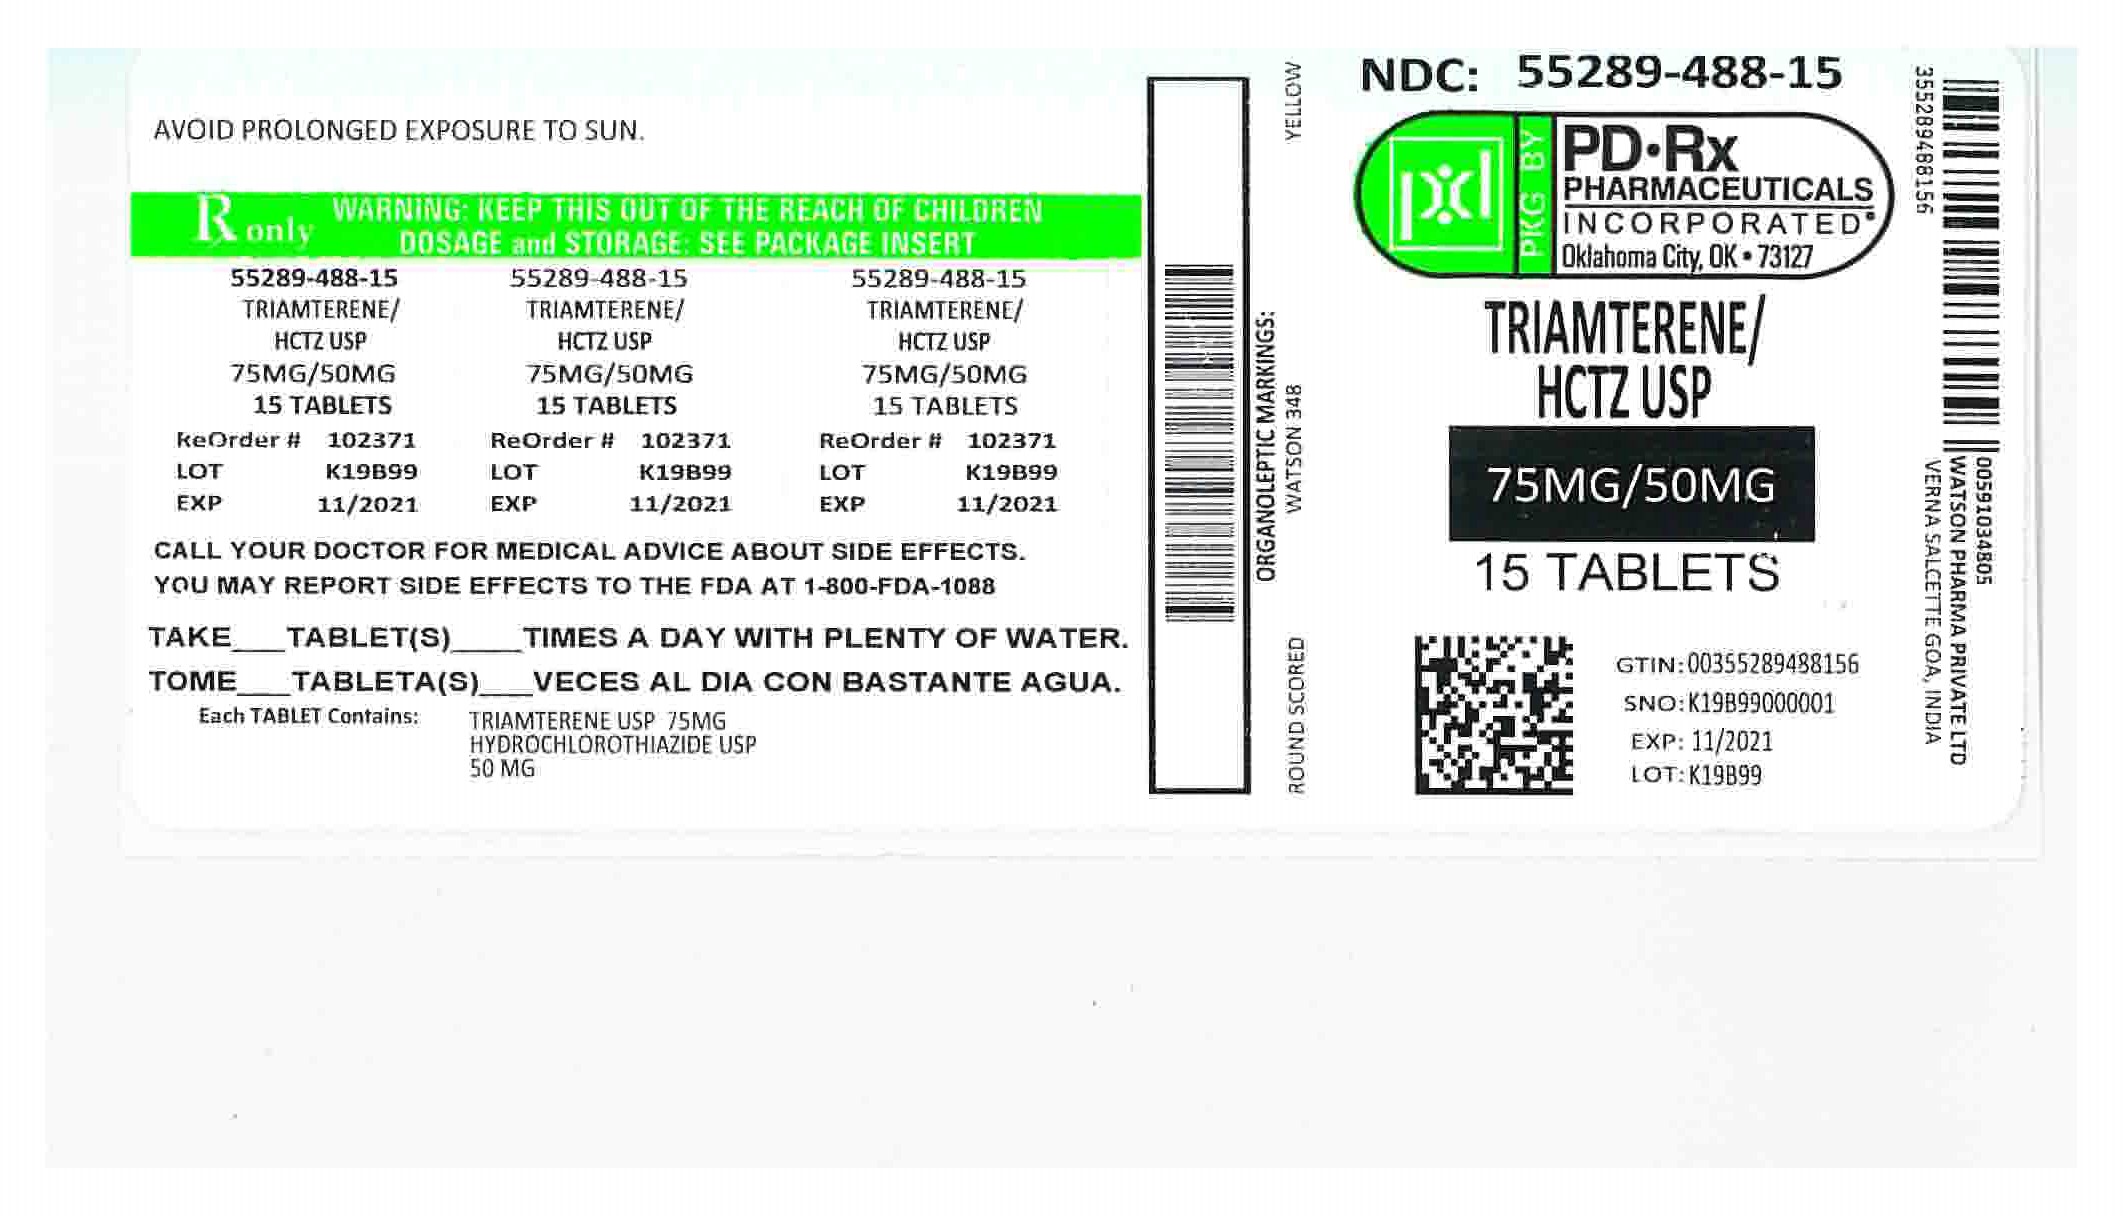
Triamterene and Hydrochlorothiazide 75 mg; 50 mg Tablet, 30-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Potassium-sparing Diuretic class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
The combination of triamterene and hydrochlorothiazide is used to treat high blood pressure and edema (fluid retention; excess fluid held in body tissues) in patients who have lower amounts of potassium in their bodies or for whom low potassium levels in the body could be dangerous. The combination of triamterene and hydrochlorothiazide is in a class of medications called diuretics ('water pills'). They work by causing the kidneys to get rid of unneeded water and salt from the body into the urine. High blood pressure is a common condition, and when not treated it can cause damage to the brain,...
Read the full MedlinePlus article ↗- Great question. Hydrochlorothiazide on its own works well for blood pressure and fluid retention, but it tends to flush out potassium along with the water — and low potassium can c...
- Why am I on this combination instead of just a regular water pill?
- Most people notice things like mild nausea, dizziness, headache, or muscle cramps, especially early on. You might also feel more tired or notice your urine looks a different color...
- What side effects should I actually watch out for day to day?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3SY5LH9PMK
Anhydrous lactose is a milk sugar with no water content. It acts as a filler and binder in tablets and capsules, adding bulk and helping ingredients stick together.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 0BZ5A00FQU
Polacrilin potassium is a synthetic polymer that absorbs water and swells. It acts as a disintegrant, helping tablets or capsules break apart quickly so the active ingredient can be absorbed in your body.
-
UNII Q662QK8M3B
Polyethylene glycol 8000 is a synthetic polymer made from ethylene oxide. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and add bulk to the medicine.
-
UNII FZ989GH94E
Povidone is a synthetic polymer made from a plastic-like material. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in your stomach so the medicine can be absorbed.
6 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.1535 | $4.61 / 30 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Triamterene and Hydrochlorothiazide 75 mg/1; 50 mg 00591-0348-01 | Actavis | 100 tablets | $0.125 | — | Availability likely | — |
| Triamterene and Hydrochlorothiazide 75 mg/1; 50 mg 60505-2657-01 | Apotex | 100 tablets | $0.125 | AB | Availability likely | — |
| Triamterene and Hydrochlorothiazide 75 mg/1; 50 mg 68001-0328-00 | BluePoint | 100 tablets | $0.125 | AB | Availability likely | — |
| triamterene and hydrochlorothiazide 75 mg/1; 50 mg 68382-0857-01 | Zydus | 100 tablets | $0.125 | AB | Availability likely | — |
| Triamterene and Hydrochlorothiazide 75 mg/1; 50 mg 68001-0388-00 | BluePoint | 100 tablets | $0.126 | AB | FDA listed | — |
| Triamterene and Hydrochlorothiazide 75 mg/1; 50 mg 50090-1834-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| triamterene and hydrochlorothiazide 75 mg/1; 50 mg 50090-6736-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Triamterene and Hydrochlorothiazide 75 mg/1; 50 mg 51655-0582-26 | Northwind | 90 tablets | — | AB | FDA listed | — |
| Triamterene and Hydrochlorothiazide 75 mg/1; 50 mgthis 55289-0488-30 | PD-Rx | 30 tablets | — | AB | FDA listed | — |
| Triamterene and Hydrochlorothiazide 75 mg/1; 50 mg 63629-2585-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Triamterene and Hydrochlorothiazide 75 mg/1; 50 mg 68071-4687-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Triamterene and Hydrochlorothiazide 75 mg/1; 50 mg 68788-8624-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Triamterene and Hydrochlorothiazide 75 mg/1; 50 mg 70518-4351-00 | REMEDYREPACK | 90 tablets | — | AB | FDA listed | — |
| triamterene and hydrochlorothiazide 75 mg/1; 50 mg 70771-1362-00 | Zydus | 1000 tablets | — | AB | FDA listed | — |
| Triamterene and Hydrochlorothiazide 75 mg/1; 50 mg 71335-0326-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Triamterene and Hydrochlorothiazide 75 mg/1; 50 mg 71335-2338-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Triamterene and Hydrochlorothiazide 75 mg/1; 50 mg 71610-0431-45 | Aphena | 45 tablets | — | AB | FDA listed | — |
| Triamterene and Hydrochlorothiazide 75 mg/1; 50 mg 72888-0095-00 | Advagen | 1000 tablets | — | AB | FDA listed | — |
| Triamterene and Hydrochlorothiazide 75 mg/1; 50 mg 82868-0032-30 | Northwind | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 55289-0488-01 | 100 TABLET in 1 BOTTLE, PLASTIC (55289-488-01) | 2011-02-16 | Active |
| 55289-0488-15 | 15 TABLET in 1 BOTTLE, PLASTIC (55289-488-15) | 2011-02-16 | Active |
| 55289-0488-30 You're viewing this | 30 TABLET in 1 BOTTLE, PLASTIC (55289-488-30) | 2011-02-16 | Active |
| 55289-0488-90 | 90 TABLET in 1 BOTTLE, PLASTIC (55289-488-90) | 2011-02-16 | Active |
You're viewing one of 4 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 55289-0488-30?
What is the difference between NDC 55289-0488-30 and NDC 55289-0488-15?
What NDC number is used to bill for this package of Triamterene and Hydrochlorothiazide 75 mg; 50 mg Tablet?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE This fixed combination drug is not indicated for the initial therapy of edema or hypertension except in individuals in whom the development of hypokalemia cannot be risked. Triamterene and hydrochlorothiazide tablets are indicated for the treatment of hypertension or edema in patients who develop hypokalemia on hydrochlorothiazide alone. Triamterene and hydrochlorothiazide tablets are also indicated for those patients who require a thiazide diuretic and in whom the development of hypokalemia cannot be risked (e.g., patients on concomitant digitalis preparations, or with a history of cardiac arrhythmias, etc.).
Triamterene and hydrochlorothiazide tablets may be used alone or in combination with other antihypertensive drugs, such as beta-blockers. Since triamterene and hydrochlorothiazide may enhance the actions of these drugs, dosage adjustments may be necessary. Usage in Pregnancy: The routine use of diuretics in an otherwise healthy woman is inappropriate and exposes mother and fetus to unnecessary hazard.
Diuretics do not prevent development of toxemia of pregnancy, and there is no satisfactory evidence that they are useful in the treatment of developed toxemia. Edema during pregnancy may arise from pathological causes or from the physiologic and mechanical consequences of pregnancy. Thiazides are indicated in pregnancy when edema is due to pathologic causes, just as they are in the absence of pregnancy.
Dependent edema in pregnancy, resulting from restriction of venous return by the expanded uterus, is properly treated through elevation of the lower extremities and use of support hose; use of diuretics to lower intravascular volume in this case is illogical and unnecessary. There is hypervolemia during normal pregnancy which is harmful to neither the fetus nor the mother (in the absence of cardiovascular disease), but which is associated with edema, including generalized edema, in the majority of pregnant women. If this edema produces discomfort, increased recumbency will often provide relief.
In rare instances, this edema may cause extreme discomfort which is not relieved by rest. In these cases, a short course of diuretics may provide relief and may be appropriate.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Note: 37.5 mg/25 mg=37.5 mg triamterene and 25 mg hydrochlorothiazide 75 mg/50 mg=75 mg triamterene and 50 mg hydrochlorothiazide The usual dose of triamterene and hydrochlorothiazide 37.5 mg/25 mg, is one or two tablets daily, given as a single dose, with appropriate monitoring of serum potassium (see WARNINGS ). The usual dose of triamterene and hydrochlorothiazide 75 mg/50 mg, is one tablet daily, with appropriate monitoring of serum potassium (see WARNINGS ). There is no experience with the use of more than one 75 mg/50 mg tablet, daily or more than two 37.5 mg/25 mg tablets, daily.
Clinical experience with the administration of two 37.5 mg/25 mg tablets, daily in divided doses (rather than as a single dose) suggests an increased risk of electrolyte imbalance and renal dysfunction. Patients receiving 50 mg of hydrochlorothiazide who become hypokalemic may be transferred to the 75 mg/50 mg product, directly. Patients receiving 25 mg hydrochlorothiazide who become hypokalemic may be transferred to the 37.5 mg/25 mg product, directly.
In patients requiring hydrochlorothiazide therapy and in whom hypokalemia cannot be risked, therapy may be initiated with 37.5 mg/25 mg of triamterene and hydrochlorothiazide. If an optimal blood pressure response is not obtained with 37.5 mg/25 mg of triamterene and hydrochlorothiazide, the dose should be increased to two 37.5 mg/25 mg tablets daily as a single dose, or one 75 mg/50 mg tablet daily. If blood pressure still is not controlled, another antihypertensive agent may be added (see PRECAUTIONS: Drug Interactions ).
Clinical studies have shown that patients taking less bioavailable formulations of triamterene and hydrochlorothiazide in daily doses of 25 mg to 50 mg of hydrochlorothiazide and 50 mg to 100 mg of triamterene may be safely changed to one triamterene and hydrochlorothiazide 37.5 mg/25 mg tablet daily. All patients changed from less bioavailable formulations to triamterene and hydrochlorothiazide tablets should be monitored clinically and for serum potassium after the transfer.
⛔ Contraindications ▾
CONTRAINDICATIONS Hyperkalemia: Triamterene and hydrochlorothiazide should not be used in the presence of elevated serum potassium levels (greater than or equal to 5.5 mEq/liter). If hyperkalemia develops, this drug should be discontinued and a thiazide alone should be substituted. Antikaliuretic Therapy or Potassium Supplementation: Triamterene and hydrochlorothiazide should not be given to patients receiving other potassium-conserving agents such as spironolactone, amiloride hydrochloride or other formulations containing triamterene.
Concomitant potassium supplementation in the form of medication, potassium-containing salt substitute or potassium-enriched diets should also not be used. Impaired Renal Function: Triamterene and hydrochlorothiazide is contraindicated in patients with anuria, acute and chronic renal insufficiency or significant renal impairment. Hypersensitivity: Triamterene and hydrochlorothiazide should not be used in patients who are hypersensitive to triamterene or hydrochlorothiazide or other sulfonamide-derived drugs.
⚠️ Warnings ▾
WARNINGS: Hyperkalemia: Abnormal elevation of serum potassium levels (greater than or equal to 5.5 mEq/liter) can occur with all potassium-conserving diuretic combinations, including triamterene and hydrochlorothiazide. Hyperkalemia is more likely to occur in patients with renal impairment, diabetes (even without evidence of renal impairment), or elderly or severely ill patients. Since uncorrected hyperkalemia may be fatal, serum potassium levels must be monitored at frequent intervals especially in patients first receiving triamterene and hydrochlorothiazide, when dosages are changed or with any illness that may influence renal function.
If hyperkalemia is suspected, (warning signs include paresthesias, muscular weakness, fatigue, flaccid paralysis of the extremities, bradycardia and shock), an electrocardiogram (ECG) should be obtained. However, it is important to monitor serum potassium levels because mild hyperkalemia may not be associated with ECG changes. If hyperkalemia is present, triamterene and hydrochlorothiazide should be discontinued immediately and a thiazide alone should be substituted.
If the serum potassium exceeds 6.5 mEq/liter, more vigorous therapy is required. The clinical situation dictates the procedures to be employed. These include the intravenous administration of calcium chloride solution, sodium bicarbonate solution and/or the oral or parenteral administration of glucose with a rapid-acting insulin preparation.
Cationic exchange resins such as sodium polystyrene sulfonate may be orally or rectally administered. Persistent hyperkalemia may require dialysis. The development of hyperkalemia associated with potassium-sparing diuretics is accentuated in the presence of renal impairment (see CONTRAINDICATIONS ).
Patients with mild renal functional impairment should not receive this drug without frequent and continuing monitoring of serum electrolytes. Cumulative drug effects may be observed in patients with impaired renal function. The renal clearances of hydrochlorothiazide and the pharmacologically active metabolite of triamterene, the sulfate ester of hydroxytriamterene, have been shown to be reduced and the plasma levels increased following triamterene and hydrochlorothiazide administration to elderly patients and patients with impaired renal function.
Hyperkalemia has been reported in diabetic patients with the use of potassium-conserving agents even in the absence of apparent renal impairment. Accordingly, triamterene and hydrochlorothiazide should be avoided in diabetic patients. If it is employed, serum electrolytes must be frequently monitored.
Because of the potassium-sparing properties of angiotensin-converting enzyme (ACE) inhibitors, triamterene and hydrochlorothiazide should be used cautiously, if at all, with these agents (see PRECAUTIONS : Drug Interactions ). Metabolic or Respiratory Acidosis: Potassium-conserving therapy should also be avoided in severely ill patients in whom respiratory or metabolic acidosis may occur. Acidosis may be associated with rapid elevations in serum potassium levels.
If triamterene and hydrochlorothiazide is employed, frequent evaluations of acid/base balance and serum electrolytes are necessary. Acute Myopia and Secondary Angle-Closure Glaucoma: Hydrochlorothiazide, a sulfonamide, can cause an idiosyncratic reaction, resulting in acute transient myopia and acute angle-closure glaucoma. Symptoms include acute onset of decreased visual acuity or ocular pain and typically occur within hours to weeks of drug initiation.
Untreated acute angle-closure glaucoma can lead to permanent vision loss. The primary treatment is to discontinue hydrochlorothiazide as rapidly as possible. Prompt medical or surgical treatments may need to be considered if the intraocular pressure remains uncontrolled.
Risk factors for developing acute angle-closure glaucoma may include a history of sulfonamide or penicillin allergy.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Side effects observed in association with the use of triamterene and hydrochlorothiazide tablets, other combination products containing triamterene and hydrochlorothiazide, and products containing triamterene or hydrochlorothiazide include the following: Gastrointestinal: jaundice (intrahepatic cholestatic jaundice), pancreatitis, nausea, appetite disturbance, taste alteration, vomiting, diarrhea, constipation, anorexia, gastric irritation, cramping. Central Nervous System: drowsiness and fatigue, insomnia, headache, dizziness, dry mouth, depression, anxiety, vertigo, restlessness, paresthesias.
Cardiovascular: tachycardia, shortness of breath and chest pain, orthostatic hypotension (may be aggravated by alcohol, barbiturates or narcotics). Renal: acute renal failure, acute interstitial nephritis, renal stones composed of triamterene in association with other calculus materials, urine discoloration. Hematologic: leukopenia, agranulocytosis, thrombocytopenia, aplastic anemia, hemolytic anemia and megaloblastosis.
Ophthalmic: xanthopsia, transient blurred vision. Hypersensitivity: anaphylaxis, photosensitivity, rash, urticaria, purpura, necrotizing angiitis (vasculitis, cutaneous vasculitis), fever, respiratory distress including pneumonitis. Other: muscle cramps and weakness, decreased sexual performance and sialadenitis.
Whenever adverse reactions are moderate to severe, therapy should be reduced or withdrawn. Altered Laboratory Findings: Serum Electrolytes: hyperkalemia, hypokalemia, hyponatremia, hypomagnesemia, hypochloremia (see WARNINGS and PRECAUTIONS ). Creatinine, Blood Urea Nitrogen: Reversible elevations in BUN and serum creatinine have been observed in hypertensive patients treated with triamterene and hydrochlorothiazide tablets.
Glucose: hyperglycemia, glycosuria and diabetes mellitus (see PRECAUTIONS ). Serum Uric Acid, PBI and Calcium: (see PRECAUTIONS ). Other: Elevated liver enzymes have been reported in patients receiving triamterene and hydrochlorothiazide tablets.
Postmarketing Experience: Non-melanoma Skin Cancer: Hydrochlorothiazide is associated with an increased risk of non-melanoma skin cancer. In a study conducted in the Sentinel System, increased risk was predominantly for squamous cell carcinoma (SCC) and in white patients taking large cumulative doses. The increased risk for SCC in the overall population was approximately 1 additional case per 16,000 patients per year, and for white patients taking a cumulative dose of ≥ 50,000 mg the risk increase was approximately 1 additional SCC case for every 6,700 patients per year.
To report SUSPECTED ADVERSE REACTIONS, contact Teva at 1-888-838-2872 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
🔄 Drug Interactions ▾
Drug Interactions: Thiazides may add to or potentiate the action of other antihypertensive drugs. The thiazides may decrease arterial responsiveness to norepinephrine. This diminution is not sufficient to preclude effectiveness of the pressor agent for therapeutic use.
Thiazides have also been shown to increase the responsiveness to tubocurarine. Lithium generally should not be given with diuretics because they reduce its renal clearance and add a high risk of lithium toxicity. Refer to the package insert on lithium before use of such concomitant therapy.
Acute renal failure has been reported in a few patients receiving indomethacin and formulations containing triamterene and hydrochlorothiazide. Caution is therefore advised when administering non-steroidal anti-inflammatory agents with triamterene and hydrochlorothiazide. Potassium-sparing agents should be used very cautiously, if at all, in conjunction with angiotensin-converting enzyme (ACE) inhibitors due to a greatly increased risk of hyperkalemia.
Serum potassium should be monitored frequently.
🔄 Drug / Laboratory Test Interactions ▾
Drug/Laboratory Test Interactions: Triamterene and quinidine have similar fluorescence spectra; thus, triamterene and hydrochlorothiazide may interfere with the measurement of quinidine.
🤰 Pregnancy ▾
Pregnancy: Teratogenic Effects: Triamterene and Hydrochlorothiazide Tablets: Animal reproduction studies to determine the potential for fetal harm by triamterene and hydrochlorothiazide tablets have not been conducted. Nevertheless, a One Generation Study in the rat approximated triamterene and hydrochlorothiazide’s composition by using a 1:1 ratio of triamterene to hydrochlorothiazide (30:30 mg/kg/day). There was no evidence of teratogenicity at those doses that were, on a body-weight basis, 15 and 30 times, respectively, the MRHD, and, on the basis of body-surface area, 3.1 and 6.2 times, respectively, the MRHD.
The safe use of triamterene and hydrochlorothiazide tablets in pregnancy has not been established since there are no adequate and well-controlled studies with triamterene and hydrochlorothiazide tablets in pregnant women. Triamterene and hydrochlorothiazide tablets should be used during pregnancy only if the potential benefit justifies the risk to the fetus. Triamterene: Reproduction studies have been performed in rats at doses as high as 20 times the Maximum Recommended Human Dose (MRHD) on the basis of body-weight, and 6 times the MRHD on the basis of body-surface area without evidence of harm to the fetus due to triamterene.
Because animal reproduction studies are not always predictive of human response, this drug should be used during pregnancy only if clearly needed. Hydrochlorothiazide: Hydrochlorothiazide was orally administered to pregnant mice and rats during respective periods of major organogenesis at doses up to 3,000 and 1,000 mg/kg/day, respectively. At these doses, which are multiples of the MRHD equal to 3,000 for mice and 1,000 for rats, based on body-weight, and equal to 282 for mice and 206 for rats, based on body-surface area, there was no evidence of harm to the fetus.
There are, however, no adequate and well-controlled studies in pregnant women. Because animal reproduction studies are not always predictive of human response, this drug should be used during pregnancy only if clearly needed. Nonteratogenic Effects: Thiazides and triamterene have been shown to cross the placental barrier and appear in cord blood.
The use of thiazides and triamterene in pregnant women requires that the anticipated benefits be weighed against possible hazards to the fetus. These hazards include fetal or neonatal jaundice, pancreatitis, thrombocytopenia, and possibly other adverse reactions that have occurred in the adult.
🧒 Pediatric Use ▾
Pediatric Use: Safety and effectiveness in pediatric patients have not been established.
🆘 Overdosage ▾
OVERDOSAGE No specific data are available regarding triamterene and hydrochlorothiazide overdosage in humans and no specific antidote is available. Fluid and electrolyte imbalances are the most important concern. Excessive doses of the triamterene component may elicit hyperkalemia, dehydration, nausea, vomiting and weakness and possibly hypotension.
Overdosing with hydrochlorothiazide has been associated with hypokalemia, hypochloremia, hyponatremia, dehydration, lethargy (may progress to coma) and gastrointestinal irritation. Treatment is symptomatic and supportive. Therapy with triamterene and hydrochlorothiazide should be discontinued.
Induce emesis or institute gastric lavage. Monitor serum electrolyte levels and fluid balance. Institute supportive measures as required to maintain hydration, electrolyte balance, respiratory, cardiovascular, and renal function.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Triamterene and hydrochlorothiazide is a diuretic, antihypertensive drug product, principally due to its hydrochlorothiazide component; the triamterene component reduces the excessive potassium loss which may occur with hydrochlorothiazide use. Hydrochlorothiazide: Hydrochlorothiazide is a diuretic and antihypertensive agent. It blocks the renal tubular absorption of sodium and chloride ions.
This natriuresis and diuresis is accompanied by a secondary loss of potassium and bicarbonate. Onset of hydrochlorothiazide’s diuretic effect occurs within 2 hours and the peak action takes place in 4 hours. Diuretic activity persists for approximately 6 to 12 hours.
The exact mechanism of hydrochlorothiazide’s antihypertensive action is not known, although it may relate to the excretion and redistribution of body sodium. Hydrochlorothiazide does not affect normal blood pressure. Following oral administration, peak hydrochlorothiazide plasma levels are attained in approximately 2 hours.
It is excreted rapidly and unchanged in the urine. Well-controlled studies have demonstrated that doses of hydrochlorothiazide as low as 25 mg given once daily are effective in treating hypertension, but the dose-response has not been clearly established. Triamterene: Triamterene is a potassium-conserving (antikaliuretic) diuretic with relatively weak natriuretic properties.
It exerts its diuretic effect on the distal renal tubule to inhibit the reabsorption of sodium in exchange for potassium and hydrogen. With this action, triamterene increases sodium excretion and reduces the excessive loss of potassium and hydrogen associated with hydrochlorothiazide. Triamterene is not a competitive antagonist of the mineralocorticoids and its potassium-conserving effect is observed in patients with Addison’s disease, i.e., without aldosterone.
Triamterene’s onset and duration of activity is similar to hydrochlorothiazide. No predictable antihypertensive effect has been demonstrated with triamterene. Triamterene is rapidly absorbed following oral administration.
Peak plasma levels are achieved within one hour after dosing. Triamterene is primarily metabolized to the sulfate conjugate of hydroxytriamterene. Both the plasma and urine levels of this metabolite greatly exceed triamterene levels.
The amount of triamterene added to 50 mg of hydrochlorothiazide in triamterene and hydrochlorothiazide tablets, 75 mg/50 mg was determined from steady-state dose-response evaluations in which various doses of liquid preparations of triamterene were administered to hypertensive persons who developed hypokalemia with hydrochlorothiazide (50 mg given once daily). Single daily doses of 75 mg triamterene resulted in greater increases in serum potassium than lower doses (25 mg and 50 mg), while doses greater than 75 mg of triamterene resulted in no additional elevations in serum potassium levels.
The amount of triamterene added to the 25 mg of hydrochlorothiazide in triamterene and hydrochlorothiazide tablets, 37.5 mg/25 mg was also determined from steady-state dose-response evaluations in which various doses of liquid preparations of triamterene were administered to hypertensive persons who developed hypokalemia with hydrochlorothiazide (25 mg given once daily). Single daily doses of 37.5 mg triamterene resulted in greater increases in serum potassium than a lower dose (25 mg), while doses greater than 37.5 mg of triamterene, i.e., 75 mg and 100 mg, resulted in no additional elevations in serum potassium levels.
The dose-response relationship of triamterene was also evaluated in patients rendered hypokalemic by hydrochlorothiazide given 25 mg twice daily. Triamterene given twice daily increased serum potassium levels in a dose-related fashion. However, the combination of triamterene and hydrochlorothiazide given twice daily also appeared to produce an increased frequency of elevation in serum BUN and creatinine levels.
The largest increases in serum potassium, BUN…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Triamterene and Hydrochlorothiazide Tablets, USP, 75 mg/50 mg, are yellow, round, scored tablets, debossed with Watson 348 and are available in bottles of: (NDC 55289-488-15) Bottles of 15 (NDC 55289-488-30) Bottles of 30 (NDC 55289-488-90) Bottles of 90 (NDC 55289-488-01) Bottles of 100 Store at 20° to 25°C (68° to 77°F) [See USP Controlled Room Temperature]. Protect from light. Dispense in a tight, light-resistant container as defined in the USP using a child-resistant closure.
📋 Description ▾
DESCRIPTION Triamterene and hydrochlorothiazide tablets, USP combine triamterene USP, a potassium-conserving diuretic, with the natriuretic agent, hydrochlorothiazide, USP. Triamterene and hydrochlorothiazide tablets, USP are available in two strengths. Each triamterene and hydrochlorothiazide tablet USP, 75 mg/50 mg, contains triamterene USP, 75 mg and hydrochlorothiazide USP, 50 mg.
Each triamterene and hydrochlorothiazide tablet USP, 37.5 mg/25 mg, contains triamterene USP, 37.5 mg and hydrochlorothiazide USP, 25 mg. Both strengths of triamterene and hydrochlorothiazide tablets, USP for oral administration contain the following inactive ingredients: anhydrous lactose, magnesium stearate, microcrystalline cellulose, polacrilin potassium, polyethylene glycol 8000, and povidone. Triamterene and hydrochlorothiazide tablets, 37.5 mg/25 mg also contain FD&C Blue No.
2 Aluminum Lake. Triamterene, USP is 2,4,7-triamino-6-phenylpteridine. Triamterene, USP is practically insoluble in water, benzene, chloroform, ether and dilute alkali hydroxides.
It is soluble in formic acid and sparingly soluble in methoxyethanol. Triamterene, USP is very slightly soluble in acetic acid, alcohol and dilute mineral acids. Its molecular weight is 253.27.
Its structural formula is: C 12 H 11 N 7 Triamterene, USP Hydrochlorothiazide, USP is 6-chloro-3,4-dihydro-2 H -1,2,4-benzothiadiazine-7-sulfonamide 1,1-dioxide. Hydrochlorothiazide, USP is slightly soluble in water and freely soluble in sodium hydroxide solution, n-butylamine and dimethylformamide. It is sparingly soluble in methanol and insoluble in ether, chloroform and dilute mineral acids.
Its molecular weight is 297.73. Its structural formula is: C 7 H 8 ClN 3 O 4 S 2 Hydrochlorothiazide, USP 1 1