
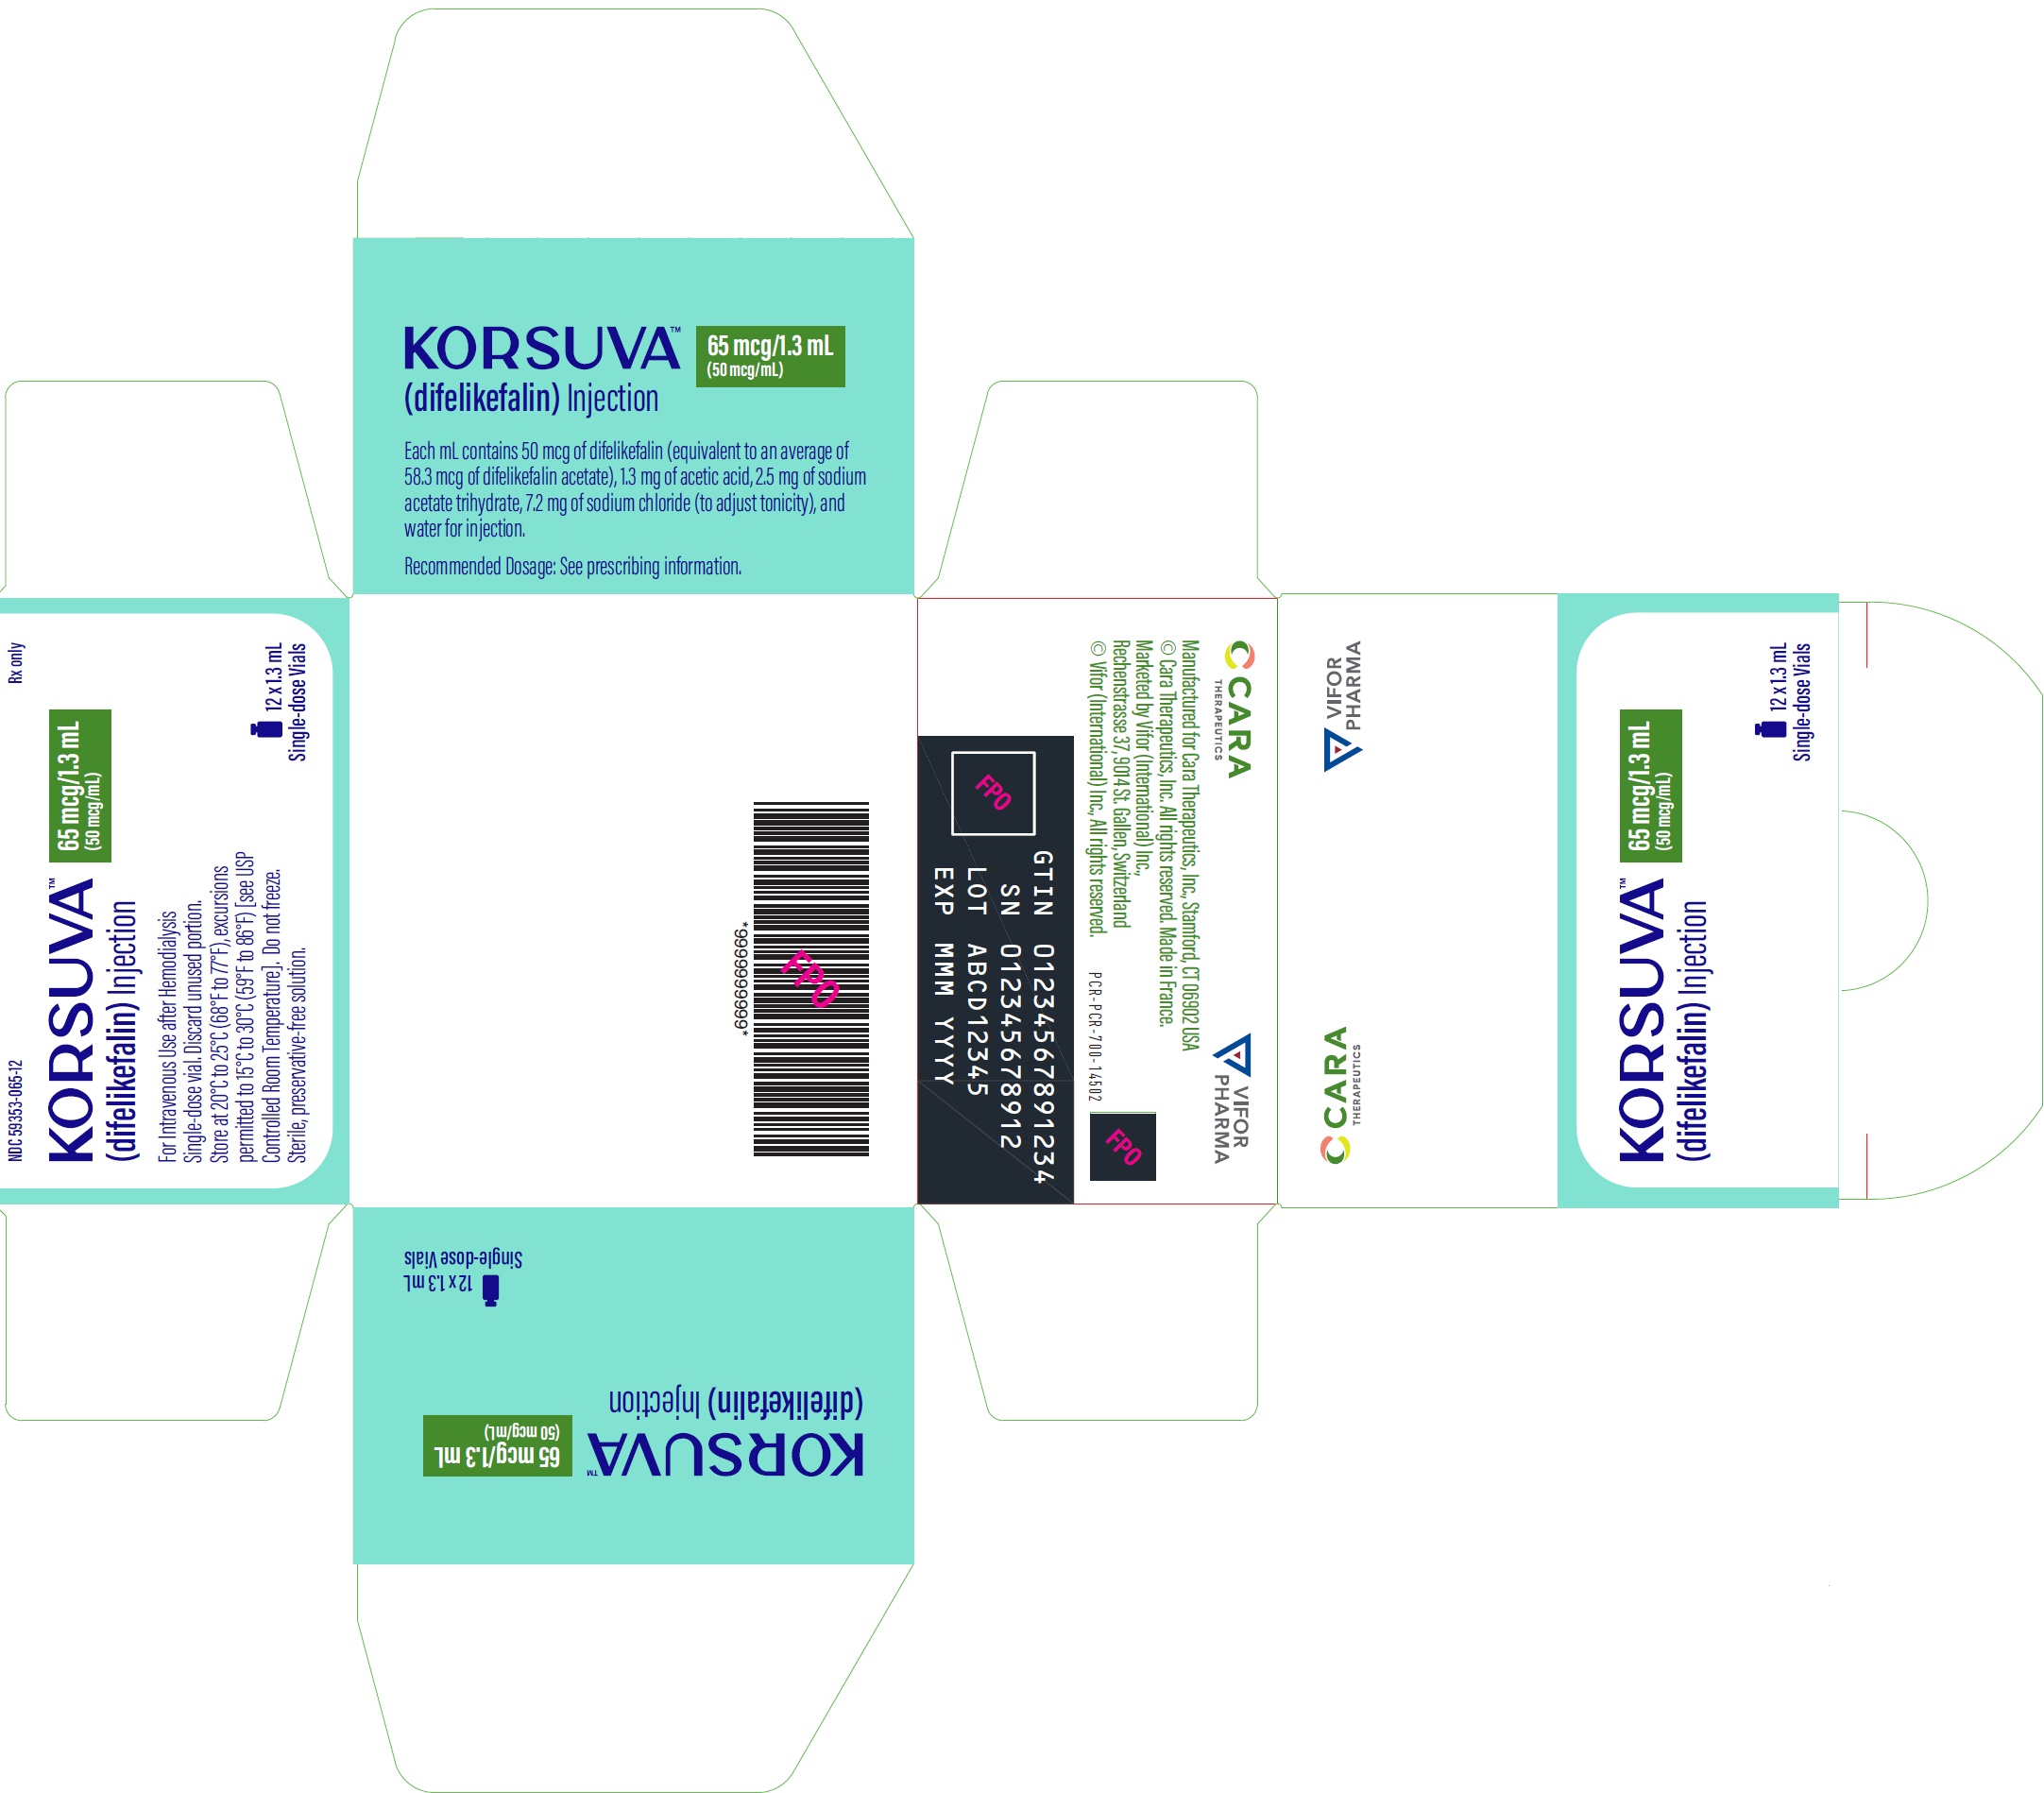
Korsuva difelikefalin 50 ug/mL Injection, Solution, 12 vials
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Kappa Opioid Receptor Agonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Difelikefalin injection is used to treat itching in people with chronic kidney disease who are on hemodialysis (medical treatment to remove waste from the blood when the kidneys are not working properly). Difelikefalin is in a class of medications called kappa opioid receptor agonists. It works by changing the way your nerves respond to itching.
Read the full MedlinePlus article ↗- Moderate-to-severe itching is actually a very common and often overlooked problem for people on hemodialysis. It's related to chronic kidney disease itself — not just dry skin. Kor...
- What exactly is Korsuva treating — why do I itch so much with kidney disease?
- You don't have to do anything at home. Korsuva is given as a small injection into the dialysis line by your care team at the end of every hemodialysis session. It takes just a mome...
- How and when do I get this medication — do I have to take it at home?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $1.24 | $19.34 / 15.6 ml |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Korsuva 50 ug/mLthis 59353-0065-12 | Vifor | 12 vials | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 10793596 ↗ | Drug substance | U-3204 | Nov 12, 2027 |
| US 10138270 ↗ | Method of use | U-3204 | Nov 12, 2027 |
| US 10017536 ↗ | Drug substance | U-3204 | Nov 12, 2027 |
| US 9359399 ↗ | Method of use | U-3204 | Nov 12, 2027 |
| US 9334305 ↗ | Method of use | U-3204 | Nov 12, 2027 |
| US 8536131 ↗ | Drug substance | U-3204 | Nov 12, 2027 |
| US 8486894 ↗ | Method of use | U-3204 | Nov 12, 2027 |
| US 8236766 ↗ | Method of use | U-3204 | Nov 12, 2027 |
| US 8217007 ↗ | Method of use | U-3204 | Nov 12, 2027 |
| US 7727963 ↗ | Drug substance | U-3204 | Nov 12, 2027 |
| US 7713937 ↗ | Drug substance | U-3204 | Nov 12, 2027 |
| US 7402564 ↗ | Drug substance | U-3204 | Nov 12, 2032 |
| Code | What it grants | Expires |
|---|---|---|
| NCE | New Chemical Entity (5-year) | Aug 23, 2026 |
Is there a generic version of KORSUVA 65 MCG/1.3 ML VIAL?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 59353-0065-12 You're viewing this | 12 VIAL, SINGLE-USE in 1 TRAY (59353-065-12) / 1.3 mL in 1 VIAL, SINGLE-USE (59353-065-01) | 2021-01-11 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE KORSUVA is indicated for the treatment of moderate-to-severe pruritus associated with chronic kidney disease (CKD-aP) in adults undergoing hemodialysis (HD). KORSUVA is a kappa opioid receptor agonist indicated for the treatment of moderate-to-severe pruritus associated with chronic kidney disease (CKD-aP) in adults undergoing hemodialysis (HD). ( 1 ) Limitation of Use Korsuva has not been studied in patients on peritoneal dialysis and is not recommended for use in this population.
( 1 ) Limitations of Use KORSUVA has not been studied in patients on peritoneal dialysis and is not recommended for use in this population.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Recommended dosage is 0.5 mcg/kg. ( 2.1 ) Administer by intravenous bolus injection into the venous line of the dialysis circuit at the end of each HD treatment. ( 2.1 ) Do not mix or dilute KORSUVA prior to administration. ( 2.2 ) Administer within 4 hours of syringe preparation. ( 2.3 ) See full prescribing information for additional recommendations on preparation and administration of KORSUVA. ( 2.2 , 2.3 )
2.1Dosage The recommended dosage of KORSUVA is 0.5 mcg/kg administered by intravenous bolus injection into the venous line of the dialysis circuit at the end of each HD treatment [see Dosage and Administration (2.3) ] . If a regularly scheduled HD treatment is missed, resume KORSUVA at the end of the next HD treatment.
2.2Preparation Instructions Do not mix or dilute KORSUVA prior to administration. Inspect KORSUVA for particulate matter and discoloration prior to administration. The solution should be clear and colorless.
Do not use KORSUVA vials if particulate matter or discoloration is observed. KORSUVA is supplied in a single-dose vial. Discard any unused product.
Injection volume to be administered is determined by patient's target dry body weight in kilograms (one patient may use less than the full contents of the vial or use more than one vial). See Table 1 . Table 1.
KORSUVA Injection Volumes Based on Target Dry Body Weight Target Dry Body Weight Range (kg) Injection Volume (mL) Total Injection Volume (mL) = Patient Target Dry Body Weight (kg) x 0.01, rounded to the nearest tenth (0.1 mL). For patient target dry body weight outside of the ranges in Table 1, use this formula. 36 – 44 0.4 45 – 54 0.5 55 – 64 0.6 65 – 74 0.7 75 – 84 0.8 85 – 94 0.9 95 – 104 1 105 – 114 1.1 115 – 124 1.2 125 – 134 1.3 135 – 144 1.4 145 – 154 1.5 155 – 164 1.6 165 – 174 1.7 175 – 184 1.8 185 – 194 1.9 195 – 204 2
2.3Administration Instructions KORSUVA is removed by the dialyzer membrane and must be administered after blood is no longer circulating through the dialyzer. Administer KORSUVA by intravenous bolus injection into the venous line of the dialysis circuit at the end of each HD session. The dose may be given either during or after rinse back of the dialysis circuit.
If the dose is given after rinse back, administer KORSUVA into the venous line followed by at least 10 mL of normal saline flush. If the dose is given during rinse back, no additional normal saline is needed to flush the line. The dose must be administered within 4 hours of the syringe preparation.
Discard any unused product.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Injection: 65 mcg/1.3 mL (50 mcg/mL) of difelikefalin as a clear, colorless solution in a single-dose glass vial. Injection : 65 mcg /1.3 mL (50 mcg/mL) of difelikefalin ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None None
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Dizziness, Somnolence, Mental Status Changes, and Gait Disturbances: Dizziness, somnolence, mental status changes, and gait disturbances, including falls, have occurred. Centrally-acting depressant medications, sedating antihistamines, and opioid analgesics should be used with caution during treatment with KORSUVA. ( 5.1 ) Risk of Driving and Operating Machinery: May impair mental or physical abilities.
Advise patients not to drive or operate dangerous machinery until the effect of KORSUVA on a patient's ability to drive or operate machinery is known. ( 5.2 )
5.1Dizziness, Somnolence, Mental Status Changes, and Gait Disturbances Dizziness, somnolence, mental status changes, and gait disturbances, including falls, have occurred in patients taking KORSUVA and may subside over time with continued treatment [see Adverse Reactions (6.1) ] . In Trial 1 and Trial 2, 17.0% of patients randomized to receive KORSUVA reported at least one of these adverse reactions, compared to 12.0% of patients who received placebo. The incidence of somnolence was higher in KORSUVA-treated subjects 65 years of age and older (7.0%) than in KORSUVA-treated subjects less than 65 years of age (2.8%).
Concomitant use of centrally-acting depressant medications, sedating antihistamines and opioid analgesics may increase the likelihood of these adverse reactions and should be used with caution during treatment with KORSUVA.
5.2Risk of Driving and Operating Machinery Dizziness, somnolence, and mental status changes have occurred in patients taking KORSUVA. KORSUVA may impair the mental or physical abilities needed to perform potentially hazardous activities such as driving a car and operating machinery. Advise patients not to drive or operate dangerous machinery until the effect of KORSUVA on a patient's ability to drive or operate machinery is known .
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: Dizziness, Somnolence, Mental Status Changes, and Gait Disturbances [see Warnings and Precautions (5.1) ] The most common adverse reactions (incidence ≥2% and ≥1% higher than placebo) were diarrhea, dizziness, nausea, gait disturbances, including falls, hyperkalemia, headache, somnolence, and mental status change. ( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Vifor (International) Inc. at 1-844-835-8277 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. A total of 1306 subjects undergoing HD who had moderate-to-severe pruritus were treated with KORSUVA in placebo-controlled and uncontrolled Phase 3 clinical trials. Of these, 711 were treated for at least 6 months and 400 were treated for at least one year.
Two placebo-controlled Phase 3 trials (Trial 1 and Trial 2), in subjects undergoing HD who had moderate-to-severe pruritus were pooled to evaluate the safety of KORSUVA in comparison to placebo up to 12 weeks. In total, 848 subjects were evaluated (424 in KORSUVA group and 424 in placebo group). The mean age of the subjects was 59 years (range 22 to 88 years), and 59% of the subjects were male.
Of the total subjects, 61% were White, 29% were Black or African American, and 5% were Asian. Table 2 summarizes the adverse reactions that occurred at a rate of ≥2% in the KORSUVA group and ≥1% higher than that of the placebo group during the 12-week placebo-controlled period of Trials 1 and 2. The percentage of subjects who discontinued treatment due to any adverse reaction was 2.6% for subjects taking KORSUVA and 0.7% for subjects taking placebo.
The most common adverse reactions (≥0.5% of subjects) leading to discontinuation were dizziness (0.9% for KORSUVA and 0.2% for placebo), mental status change (0.7% and 0.2%, respectively), nausea (0.5% and 0%, respectively), and headache (0.5% and 0%, respectively). The percentage of subjects who developed serious adverse reactions was 4.5% in the KORSUVA group and 2.8% in the placebo group. Table 2: Adverse Reactions in ≥ 2% of KORSUVA-Treated Subjects with Moderate-to-Severe CKD-aP Undergoing HD and ≥ 1% Higher Than Placebo in Trials 1 and 2 Adverse Reactions Placebo (N=424) n (%) KORSUVA (N=424) n (%) Diarrhea 24 (5.7) 38 (9.0) Dizziness 16 (3.8) 29 (6.8) Nausea 19 (4.5) 28 (6.6) Gait Disturbances Gait disturbances includes: preferred terms of falls and gait disturbances 23 (5.4) 28 (6.6) Hyperkalemia 15 (3.5) 20 (4.7) Headache 11 (2.6) 19 (4.5) Somnolence 10 (2.4) 18 (4.2) Mental Status Change Mental Status Change includes: preferred terms of confusional state and mental status change.
6 (1.4) 14 (3.3) Description of Selected Adverse Reactions Gait Disturbances, including Falls Gait disturbances, including falls, were reported in 6.6% of subjects receiving KORSUVA compared to 5.4% of subjects who received placebo. Falls were reported as serious adverse reactions in < 1% of subjects receiving KORSUVA and placebo, with one subject discontinuing KORSUVA due to gait disturbance. Dizziness Dizziness was reported in 6.8% of subjects randomized to KORSUVA compared to 3.8% of subjects who received placebo.
Dizziness occurred within the first 3 weeks of treatment and was generally transient. Dizziness was serious in 0.2% of KORSUVA-treated subjects compared to 0% of subjects who received placebo and led to discontinuation in 0.9% of KORSUVA-treated subjects compared to 0.2% of subjects who received placebo. Somnolence Somnolence was reported in 4.2% of subjects randomized to receive KORSUVA compared to 2.4% of subjects who received placebo.
Somnolence occurred within the first 3 weeks…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Severe Hepatic Impairment: Not recommended in patients with severe hepatic impairment. ( 8.6 )
8.1Pregnancy Risk Summary The limited human data on use of KORSUVA in pregnant women are not sufficient to evaluate a drug-associated risk for major birth defects or miscarriage. In animal reproduction studies, intravenous injection of difelikefalin to pregnant rats and rabbits during the period of organogenesis at doses 711 and 10 times the maximum recommended human dose (MRHD), respectively, resulted in no adverse effects in either rats or rabbits (see Data ) . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Data Animal Data In an embryofetal development study, difelikefalin was administered by intravenous injection to pregnant rats at doses of 0.25, 2.5, and 25 mg/kg/day during the period of organogenesis. Difelikefalin was not associated with embryofetal lethality or fetal malformations.
Difelikefalin increased the incidences of skeletal variations (wavy ribs and incompletely ossified ribs) at the dose of 25 mg/kg/day (711 times the MRHD based on AUC comparison). In an embryofetal development study, difelikefalin was administered by intravenous injection to pregnant rabbits at doses of 0.025, 0.05, and 0.1 mg/kg/day during the period of organogenesis. Maternal toxicity evidenced by decreased maternal body weight gain was noted in all dose groups.
Difelikefalin was not associated with embryofetal lethality or fetal malformations at doses up to 0.1 mg/kg/day (10 times the MRHD based on AUC comparison). In a prenatal and postnatal development study, difelikefalin was administered by intravenous injection to pregnant rats at doses of 0.6, 2.5, and 10 mg/kg/day beginning on gestation day 7 and continuing through lactation day 20. Persisting effects on decreased maternal body weight and/or maternal body weight gain as well as food consumption were noted at doses greater than or equal to 2.5 mg/kg/day (68 times the MRHD based on AUC comparison).
No maternal effects were observed at 0.6 mg/kg/day (14 times the MRHD based on AUC comparison). No difelikefalin-related effects on postnatal developmental, neurobehavioral, or reproductive performance of offspring were noted at doses up to 10 mg/kg/day (282 times the MRHD based on AUC comparison).
8.2Lactation Risk Summary There are no data regarding the presence of KORSUVA in human milk or effects on the breastfed infant or on milk production. Studies in rats showed difelikefalin was transferred into the milk in lactating rats. When a drug is present in animal milk, it is likely that the drug will be present in human milk.
The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for KORSUVA and any potential adverse effects on the breastfed child from KORSUVA or from the underlying maternal condition. Data Animal Data Difelikefalin was administered to lactating rats by intravenous injection at doses of 0.6, 2.5, or 10 mg/kg/day from gestation day 7 through lactation day 14. Difelikefalin was detected in the milk of the lactating rats with the concentration ratio for milk:plasma of 0.04 to 0.05 across the doses.
There was no measurable difelikefalin in the plasma of nursing pups.
8.4Pediatric Use The safety and effectiveness of KORSUVA in pediatric patients have not been established.
8.5Geriatric Use Of the 848 subjects in the placebo-controlled studies who received KORSUVA, 278 subjects (32.8%) were 65 years of age and older and 98 subjects (11.6%) were 75 years of age and older. No overall differences in safety or effectiveness of KORSUVA have been observed between patients 65 years of age and older and younger adult subjects, with the exception of the incidence of somnolen…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary The limited human data on use of KORSUVA in pregnant women are not sufficient to evaluate a drug-associated risk for major birth defects or miscarriage. In animal reproduction studies, intravenous injection of difelikefalin to pregnant rats and rabbits during the period of organogenesis at doses 711 and 10 times the maximum recommended human dose (MRHD), respectively, resulted in no adverse effects in either rats or rabbits (see Data ) . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Data Animal Data In an embryofetal development study, difelikefalin was administered by intravenous injection to pregnant rats at doses of 0.25, 2.5, and 25 mg/kg/day during the period of organogenesis. Difelikefalin was not associated with embryofetal lethality or fetal malformations.
Difelikefalin increased the incidences of skeletal variations (wavy ribs and incompletely ossified ribs) at the dose of 25 mg/kg/day (711 times the MRHD based on AUC comparison). In an embryofetal development study, difelikefalin was administered by intravenous injection to pregnant rabbits at doses of 0.025, 0.05, and 0.1 mg/kg/day during the period of organogenesis. Maternal toxicity evidenced by decreased maternal body weight gain was noted in all dose groups.
Difelikefalin was not associated with embryofetal lethality or fetal malformations at doses up to 0.1 mg/kg/day (10 times the MRHD based on AUC comparison). In a prenatal and postnatal development study, difelikefalin was administered by intravenous injection to pregnant rats at doses of 0.6, 2.5, and 10 mg/kg/day beginning on gestation day 7 and continuing through lactation day 20. Persisting effects on decreased maternal body weight and/or maternal body weight gain as well as food consumption were noted at doses greater than or equal to 2.5 mg/kg/day (68 times the MRHD based on AUC comparison).
No maternal effects were observed at 0.6 mg/kg/day (14 times the MRHD based on AUC comparison). No difelikefalin-related effects on postnatal developmental, neurobehavioral, or reproductive performance of offspring were noted at doses up to 10 mg/kg/day (282 times the MRHD based on AUC comparison).
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of KORSUVA in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the 848 subjects in the placebo-controlled studies who received KORSUVA, 278 subjects (32.8%) were 65 years of age and older and 98 subjects (11.6%) were 75 years of age and older. No overall differences in safety or effectiveness of KORSUVA have been observed between patients 65 years of age and older and younger adult subjects, with the exception of the incidence of somnolence which was higher in KORSUVA-treated subjects 65 years of age and older (7.0%) than in KORSUVA-treated subjects less than 65 years of age (2.8%), and was comparable in both placebo age groups (3.0% and 2.1%, respectively).
No differences in plasma concentrations of KORSUVA were observed between subjects 65 years of age and older and younger adult subjects [see Clinical Pharmacology (12.3) ] .
🆘 Overdosage ▾
10 OVERDOSAGE Single doses of KORSUVA up to 12 times and multiple doses of KORSUVA up to 5 times the recommended dosage of 0.5 mcg/kg were administered in clinical studies in subjects undergoing HD. A dose-dependent increase in adverse reactions, including dizziness, somnolence, mental status changes, paresthesia, fatigue, hypertension, and vomiting, were observed. In the event of overdosage, provide the appropriate medical attention based on patient's clinical status.
Difelikefalin is primarily eliminated by the kidneys with a low plasma protein binding of approximately 23% to 28% in dialysis patients. Hemodialysis for 4 hours using a high-flux dialyzer effectively cleared approximately 70% to 80% of difelikefalin from plasma, and difelikefalin was not detectable in plasma at the end of the second of two dialysis cycles. [see Clinical Pharmacology (12.3) ].
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action KORSUVA is a kappa opioid receptor (KOR) agonist. The relevance of KOR activation to therapeutic effectiveness is not known.
12.2Pharmacodynamics Difelikefalin exposure-response relationships and the time course of pharmacodynamic response are unknown. Cardiac Electrophysiology At a dose 6 times the recommended dosage, difelikefalin does not prolong the QTc interval to any clinically relevant extent.
12.3Pharmacokinetics The pharmacokinetics of difelikefalin is dose proportional over a single dosage range from 1 to 3 mcg/kg (2 to 6 times the recommended dosage) and multiple intravenous dosage range from 0.5 to 2.5 mcg/kg (1 to 5 times the recommended dosage) in chronic kidney disease patients undergoing HD. Steady-state was reached after the second administered dosage and the mean accumulation ratio was up to 1.6. Distribution The mean volume of distribution of difelikefalin is approximately 238 mL/kg.
Difelikefalin binding to human plasma protein in dialysis patients is 23% to 28%. Elimination The half-life of difelikefalin in HD subjects prior to dialysis ranged between 23 and 31 hours. Following administration of radiolabeled difelikefalin, >99% of circulating radioactivity was present in plasma as parent.
Hemodialysis reduced the difelikefalin plasma concentrations by 70% to 80% and difelikefalin was not detectable in plasma after 2 dialysis cycles. Metabolism Difelikefalin is not metabolized by cytochrome P450 (CYP) enzymes CYP1A2, CYP2C19, CYP2C8, CYP2C9, CYP2D6 or CYP3A observed in human hepatic microsomes or hepatocytes, in vitro. Excretion Following administration of difelikefalin to HD patients, 11% of the dosage was excreted in urine, 59% in feces, and 20% in dialysate fluid.
Specific Populations No clinically significant differences in the pharmacokinetics of difelikefalin were observed based on age (25 to 80 years of age), sex, race/ethnicity, or mild-to-moderate hepatic impairment. The effect of severe hepatic impairment on the pharmacokinetics of difelikefalin is unknown [see Use in Specific Populations (8.6) ] . Drug Interaction Studies Clinical Studies No clinical studies evaluating the drug interaction potential of difelikefalin were conducted.
In Vitro Studies Cytochrome P450 (CYP) Enzymes: Difelikefalin did not inhibit CYP enzymes (CYP1A2, CYP2B6, CYP2C8, CYP2C9, CYP2C19, CYP3A, or CYP2D6), or induce CYP enzymes (CYP1A2, CYP2B6, or CYP3A) and is not a substrate of CYP450 enzymes (CYP1A2, CYP2C19, CYP2C8, CYP2C9, CYP2D6 or CYP3A). Uridine diphosphate (UDP)-glucuronosyl transferase (UGT) Enzymes: Difelikefalin is not an inhibitor of UGT1A3, UGT1A9, or UGT2B7. Transporter Systems: Difelikefalin did not inhibit BCRP, Pgp, OAT1, OAT3, OCT1, OCT2, OATP1B1, OATP1B3, MATE1, or, MATE2-K human transporters and is not a substrate of OAT1, OAT2, OAT3, OATP1A2, OCT2, OCT3, LAT1, PEPT1, PEPT2, ASBT, BSEP, MRP2, OATP1B1, OATP1B3, OATP2B1, OCT1, OCTN1, OCTN2, Pgp, BCRP, OSTα/β, MATE1, or, MATE2-K.
🧬 Mechanism of Action ▾
12.1Mechanism of Action KORSUVA is a kappa opioid receptor (KOR) agonist. The relevance of KOR activation to therapeutic effectiveness is not known.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING How Supplied KORSUVA (difelikefalin) injection is supplied as a sterile, clear and colorless solution in 1.3 mL single-dose, glass vials: NDC 59353-065-01: 65 mcg/1.3 mL (50 mcg/mL) single-dose vial NDC 59353-065-12: Carton containing 12 vials Storage and Handling Store vials at 20°C to 25°C (68°F to 77°F), excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature]. Do not freeze. KORSUVA injection must be administered within 4 hours of syringe preparation; prepared syringes can be stored at ambient temperature 20°C to 25°C (68°F to 77°F) until dosing [see Dosage and Administration (2.2 , 2.3) ] .
KORSUVA injection is supplied in a single-dose vial. Any unused drug remaining after injection must be discarded.
📦 Storage and Handling ▾
Storage and Handling Store vials at 20°C to 25°C (68°F to 77°F), excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature]. Do not freeze. KORSUVA injection must be administered within 4 hours of syringe preparation; prepared syringes can be stored at ambient temperature 20°C to 25°C (68°F to 77°F) until dosing [see Dosage and Administration (2.2 , 2.3) ] .
KORSUVA injection is supplied in a single-dose vial. Any unused drug remaining after injection must be discarded.
📋 Description ▾
11 DESCRIPTION KORSUVA (difelikefalin) is a kappa opioid receptor agonist. Difelikefalin is a synthetic peptide with a single stereoisomer and is present as an acetate salt. Difelikefalin acetate is a white to off-white powder with a molecular formula of C 36 H 53 N 7 O 6 ∙xAcOH (1.0≤ × ≤2.0) and a molecular weight of 679.4 g/mol (mono- isotopic; free base).
It is soluble in water. The chemical name of difelikefalin acetate is 4-amino-1-(D-phenylalanyl-D-phenylalanyl-D-leucyl-D-lysyl)piperidine-4-carboxylic acid, acetate salt. The chemical structure is: KORSUVA (difelikefalin) injection is supplied in a single-dose vial containing 65 mcg/1.3 mL (50 mcg/mL) of difelikefalin as a sterile, preservative-free, clear and colorless solution for intravenous injection.
KORSUVA is formulated as an isotonic 40 mM acetate buffer solution with an osmolality of 250 to 350 mOsm and a pH of 4.5. Each milliliter of KORSUVA injection contains 50 mcg of difelikefalin (equivalent to an average of 58.3 mcg of difelikefalin acetate), 1.3 mg of acetic acid, 2.5 mg of sodium acetate trihydrate, 7.2 mg of sodium chloride (to adjust tonicity), and water for injection. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Dizziness, Somnolence, Mental Status Changes, and Gait Disturbances Inform patients that dizziness, somnolence, mental status changes, and gait disturbances, including falls, can occur during treatment with KORSUVA [see Adverse Reactions (6.1) ] . Somnolence is more likely to happen to patients who are age 65 years or older. Inform patients that concomitant treatment with centrally-acting depressants, sedating antihistamines and opioid analgesics may increase the likelihood of these adverse reactions and these medications should be used with caution during treatment with KORSUVA [see Warnings and Precautions (5.1) ] .
Driving or Operating Machinery Inform patients that KORSUVA may impair the ability to perform potentially hazardous activities such as driving a car or operating heavy machinery. Advise patients not to drive or operate machinery until they know how they will react to KORSUVA [see Warnings and Precautions (5.2) ].