
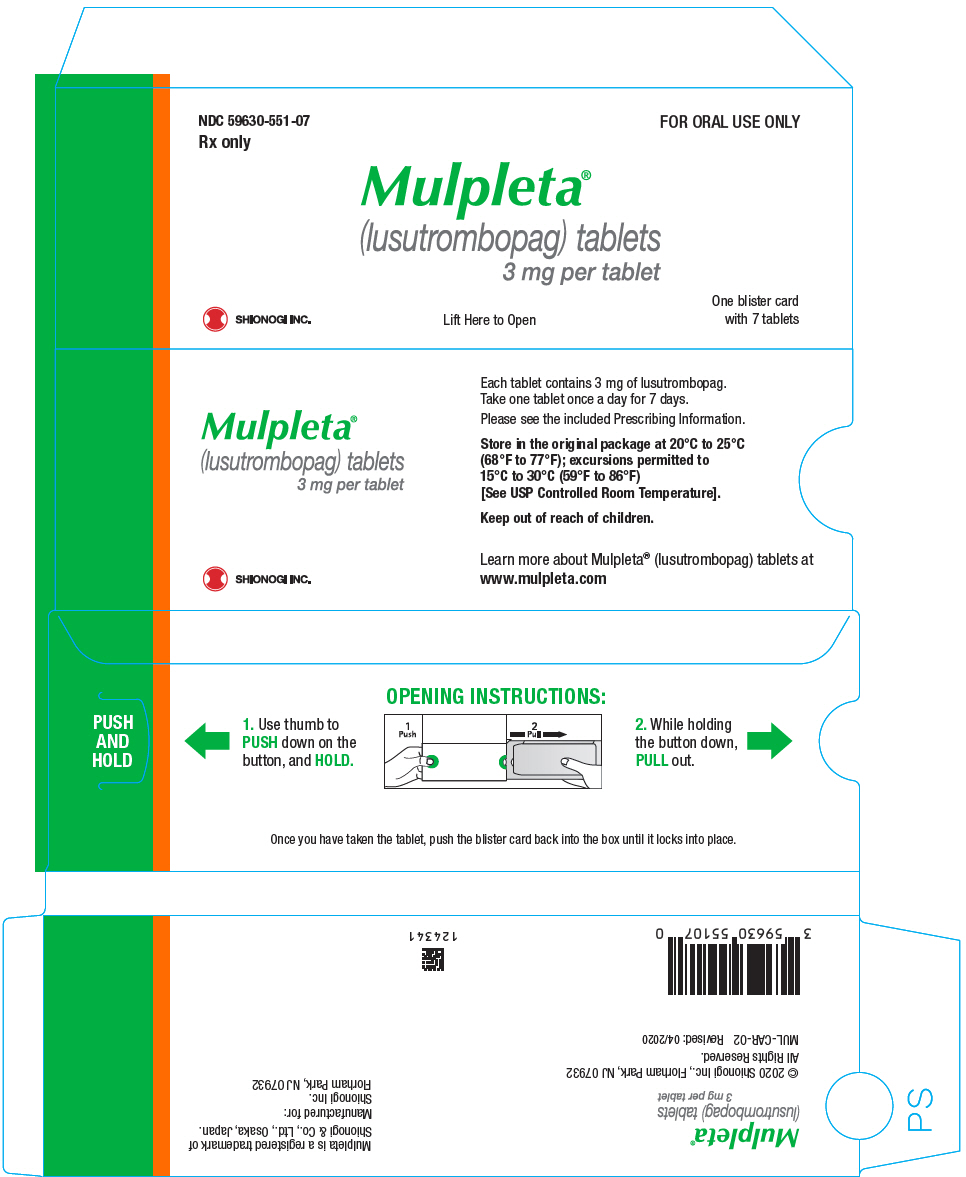
Mulpleta Lusutrombopag 3 mg Tablet, Film Coated, 7-count — NDC 59630-551-07 (Billing 59630-0551-07)
This is a package of 7 tablets of Mulpleta Lusutrombopag 3 mg Tablet, Film Coated from SHIONOGI INC., marketed since Aug 2018 and currently FDA-listed. It is the main listing for this product, which comes in 2 package sizes.
NDC database record
One package, one record: these facts belong to NDC 59630-551-07 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 59630 labeler · 551 product · 07 package
- Package marketed since
- Aug 27, 2018
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Billing quantity
- 7 EA per package
- Barcode (UPC-A, from the NDC)
- 3 5963055107 0
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 078683
- GCN: 45056
- GPI-14 (Medi-Span): 82405045000320
- HICL (First Databank): 045127
- AHFS class code: 20:16.00.00
- RxCUI (RxNorm): 2054989
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Other systemic hemostatics class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Lusutrombopag is used treat thrombocytopenia (a low number of platelets [type of blood cell needed for blood clotting]) in patients with chronic (ongoing) liver disease who are scheduled to have a medical or dental procedure to help prevent bleeding complications. Lusutrombopag is in a class of medications called thrombopoietin (TPO) receptor agonists. It works by causing the body to produce more platelets.
Read the full MedlinePlus article ↗- It raises low platelet counts in adults with chronic liver disease who are about to have a procedure. Platelets help your blood clot, so having enough of them matters before a proc...
- You take one tablet by mouth once a day for 7 days, with or without food. You start about 1 to 2 weeks before your procedure. If you miss a dose, take it as soon as you can that sa...
- Headache was the most common side effect in studies. Most people tolerate it well, but let me know if anything bothers you.
- Call right away if you notice signs of a blood clot, like leg swelling or pain, chest pain, shortness of breath, or new belly pain or swelling. Medicines like this one can raise cl...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Lusutrombopag — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $1,158.56 | $8,109.92 / 7 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 8, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 59630-0551-07 You're viewing this Main listing | 1 DOSE PACK in 1 CARTON / 7 TABLET, FILM COATED in 1 DOSE PACK | 2018-08-27 | — | Active |
| 59630-0551-77 59630-551-77 | 1 DOSE PACK in 1 CARTON / 7 TABLET, FILM COATED in 1 DOSE PACK Sample | 2018-08-27 | — | Active |
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 59630-0551-77?
What NDC number is used to bill for this package of Mulpleta Lusutrombopag 3 mg Tablet, Film Coated?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Mulpleta 3 mgthis 59630-0551-07 | SHIONOGI | 7 tablets | — | — | FDA listed | — |
| Mulpleta 3 mg 84230-0551-07 | VANCOCIN | 7 tablets | — | — | FDA listed | — |
| Mulpleta 3 mg 85320-0551-07 | Eddingpharm | 7 tablets | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 9427402 ↗ | Drug product | — | Sep 29, 2031 |
| US 8889722 ↗ | Drug substance | — | Jul 29, 2028 |
| US 8530668 ↗ | Drug substance | — | Jan 21, 2030 |
Is there a generic version of MULPLETA 3 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Lusutrombopag inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII UTY7PDF93L
A plant-derived thickening agent made from cellulose. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in your stomach so the medicine can be absorbed.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII 9XZ8H6N6OH
A plant-based cellulose derivative used as a binder to hold tablet ingredients together, a thickener in liquids, and a coating agent to control how fast the medicine dissolves.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII 3A3U0GI71G
Magnesium oxide is a mineral compound that acts as a buffer and filler in medications. It helps neutralize stomach acid and adds bulk to the tablet or capsule formulation.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII 8Z96QXD6UM
Triethyl citrate is a clear liquid derived from citric acid. It acts as a plasticizer and solvent in tablet coatings and film formulations, helping the coating remain flexible and adhere properly to the medicine.
12 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 6, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from SHIONOGI INC. labeler code 59630
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE MULPLETA is indicated for the treatment of thrombocytopenia in adult patients with chronic liver disease who are scheduled to undergo a procedure. MULPLETA is a thrombopoietin receptor agonist indicated for the treatment of thrombocytopenia in adult patients with chronic liver disease who are scheduled to undergo a procedure. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Begin MULPLETA dosing 8-14 days prior to a scheduled procedure. ( 2.1 ) Patients should undergo their procedure 2-8 days after the last dose. ( 2.1 ) Recommended Dosage: 3 mg orally once daily with or without food for 7 days. ( 2.1 )
2.1Recommended Dosage Begin MULPLETA dosing 8-14 days prior to a scheduled procedure. Patients should undergo their procedure 2-8 days after the last dose. The recommended dosage of MULPLETA is 3 mg taken orally once daily with or without food for 7 days.
In the case of a missed dose of MULPLETA, patients should take the missed dose as soon as possible on the same day and return to the normal schedule the following day. MULPLETA has been investigated only as a single 7-day once daily dosing regimen in clinical trials in patients with chronic liver disease [see Clinical Studies (14) ] . MULPLETA should not be administered to patients with chronic liver disease in an attempt to normalize platelet counts.
2.2Monitoring Obtain a platelet count prior to initiation of MULPLETA therapy and not more than 2 days before the procedure.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets: 3 mg lusutrombopag as a light red, round, film-coated tablet debossed with the Shionogi trademark ( ) above the identifier code "551" on one side and with a "3" on the other side. Tablet: 3 mg. ( 3 ) Trademark
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None.
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Thrombotic/Thromboembolic Complications: MULPLETA is a thrombopoietin (TPO) receptor agonist, and TPO receptor agonists have been associated with thrombotic and thromboembolic complications in patients with chronic liver disease. Monitor platelet counts and for thromboembolic events and institute treatment promptly. ( 5.1 )
5.1Thrombotic/Thromboembolic Complications MULPLETA is a thrombopoietin (TPO) receptor agonist, and TPO receptor agonists have been associated with thrombotic and thromboembolic complications in patients with chronic liver disease. Portal vein thrombosis has been reported in patients with chronic liver disease treated with TPO receptor agonists. Portal vein thrombosis was reported in 1% (2 of 171) of MULPLETA-treated patients and 1% (2 of 170) of placebo-treated patients in 3 randomized, double-blind trials and was identified post-procedure in protocol-specified imaging.
The thromboses were not associated with a marked increase in platelet count. Consider the potential increased thrombotic risk when administering MULPLETA to patients with known risk factors for thromboembolism, including genetic pro-thrombotic conditions (Factor V Leiden, Prothrombin 20210A, Antithrombin deficiency, or Protein C or S deficiency). In patients with ongoing or prior thrombosis or absence of hepatopetal blood flow, MULPLETA should only be used if the potential benefit to the patient justifies the potential risk.
MULPLETA should not be administered to patients with chronic liver disease in an attempt to normalize platelet counts.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are discussed in detail in other sections of the labeling: Thrombotic/Thromboembolic Complications [see Warnings and Precautions (5.1) ] The most common adverse reaction (≥3%): headache. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Shionogi Inc. at 1-800-849-9707 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The safety of MULPLETA was evaluated in 3 randomized, double-blind, placebo-controlled trials, L-PLUS 1, L-PLUS 2, and M0626, in which patients with chronic liver disease and thrombocytopenia were treated with MULPLETA (N=171) or placebo (N=170) at a dose of 3 mg daily for up to 7 days prior to a scheduled procedure.
The majority of patients were males (59%), and median age was 61 years (range 19-88). The racial and ethnic distribution was White (50%), Asian (47%), Black (<1%), and Other (3%). The most common adverse reactions (those occurring in at least 3%) in the MULPLETA-treated group across the pooled data from the three trials are summarized in table 1.
Table 1. Adverse Reactions with a Frequency ≥3% in Patients Treated with MULPLETA (Pooled Data (L-PLUS 1, L-PLUS 2, and M0626)) Adverse Reaction Includes treatment-emergent adverse reactions occurring at a rate higher than placebo. MULPLETA 3 mg (N=171) % Placebo (N=170) % Headache 5 4 The incidence of serious adverse events was 5% (9 of 171 patients) in the MULPLETA group and 7% (12 of 170 patients) in the placebo group.
The most common serious adverse reaction reported with MULPLETA was portal vein thrombosis [see Warnings and Precautions (5.1) ] . No adverse reactions resulted in discontinuation of MULPLETA.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Breastfeeding is not recommended during treatment. ( 8.2 )
8.1Pregnancy Risk Summary There are no available data on MULPLETA in pregnant women to inform the drug-associated risk. In animal reproduction studies, oral administration of lusutrombopag to pregnant rats during organogenesis and the lactation period resulted in adverse developmental outcomes. These findings were observed at exposures based on AUC that were substantially higher than the AUC observed in patients (approximately 89 times) at the recommended clinical dose of 3 mg once daily .
Advise pregnant women of the potential risk to a fetus (see Data ) . The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the general population in the United States, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data In an embryo-fetal development study in rats, lusutrombopag was orally administered during organogenesis at doses of 4, 12.5, 40, and 80 mg/kg/day. Low body weight and a decrease in the number of ossified sternebrae were noted in fetuses at 80 mg/kg/day (approximately 251 times the AUC observed in patients at the recommended clinical dose of 3 mg once daily).
Minor skeletal variations (supernumerary ribs) were observed at doses of 4 mg/kg/day (approximately 23 times the AUC observed in patients at the recommended clinical dose of 3 mg once daily). In an embryo-fetal development study in rabbits following oral administration of lusutrombopag at doses up to 1000 mg/kg/day, no effect of lusutrombopag was observed on any parameter of embryo-fetal development. In a pre- and postnatal development study in rats at oral doses of 1, 4, 12.5, and 40 mg/kg/day, there were adverse effects of lusutrombopag on postnatal development at 40 mg/kg/day (approximately 230 times the AUC observed in patients at the recommended clinical dose of 3 mg once daily).
The effects included prolongation of the gestation period in dams, low viability before weaning, delayed postnatal growth (delayed negative geotaxis, delayed eyelid opening, or low pup body weight), abnormal clinical signs (prominent annular rings on the tail after weaning), low fertility index, a low number of corpora lutea or implantations, and increased pre-implantation loss. The incidence of short thoracolumbar supernumerary ribs on postnatal Day 4 of F1 pups was high at doses of 12.5 mg/kg/day or more (approximately 89 times the AUC observed in patients at the recommended clinical dose of 3 mg once daily).
8.2Lactation Risk Summary There is no information regarding the presence of lusutrombopag in human milk, the effects on the breastfed child, and the effects on milk production. Lusutrombopag was present in the milk of lactating rats. Due to the potential for serious adverse reactions in a breastfed child, breastfeeding is not recommended during treatment with MULPLETA and for at least 28 days after the last dose (see Clinical Considerations ) .
Clinical Considerations Minimizing Exposure A lactating woman should interrupt breastfeeding and pump and discard breast milk during MULPLETA treatment and for 28 days after the last dose of MULPLETA in order to minimize exposure to a breastfed child.
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established.
8.5Geriatric Use Clinical studies of MULPLETA did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients.
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no available data on MULPLETA in pregnant women to inform the drug-associated risk. In animal reproduction studies, oral administration of lusutrombopag to pregnant rats during organogenesis and the lactation period resulted in adverse developmental outcomes. These findings were observed at exposures based on AUC that were substantially higher than the AUC observed in patients (approximately 89 times) at the recommended clinical dose of 3 mg once daily .
Advise pregnant women of the potential risk to a fetus (see Data ) . The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the general population in the United States, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data In an embryo-fetal development study in rats, lusutrombopag was orally administered during organogenesis at doses of 4, 12.5, 40, and 80 mg/kg/day. Low body weight and a decrease in the number of ossified sternebrae were noted in fetuses at 80 mg/kg/day (approximately 251 times the AUC observed in patients at the recommended clinical dose of 3 mg once daily).
Minor skeletal variations (supernumerary ribs) were observed at doses of 4 mg/kg/day (approximately 23 times the AUC observed in patients at the recommended clinical dose of 3 mg once daily). In an embryo-fetal development study in rabbits following oral administration of lusutrombopag at doses up to 1000 mg/kg/day, no effect of lusutrombopag was observed on any parameter of embryo-fetal development. In a pre- and postnatal development study in rats at oral doses of 1, 4, 12.5, and 40 mg/kg/day, there were adverse effects of lusutrombopag on postnatal development at 40 mg/kg/day (approximately 230 times the AUC observed in patients at the recommended clinical dose of 3 mg once daily).
The effects included prolongation of the gestation period in dams, low viability before weaning, delayed postnatal growth (delayed negative geotaxis, delayed eyelid opening, or low pup body weight), abnormal clinical signs (prominent annular rings on the tail after weaning), low fertility index, a low number of corpora lutea or implantations, and increased pre-implantation loss. The incidence of short thoracolumbar supernumerary ribs on postnatal Day 4 of F1 pups was high at doses of 12.5 mg/kg/day or more (approximately 89 times the AUC observed in patients at the recommended clinical dose of 3 mg once daily).
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of MULPLETA did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients.
🆘 Overdosage ▾
10 OVERDOSAGE No antidote for MULPLETA overdose is known. In the event of overdose, platelet count may increase excessively and result in thrombotic or thromboembolic complications. Closely monitor the patient and platelet count.
Treat thrombotic complications in accordance with standard of care. Hemodialysis is not expected to enhance the elimination of MULPLETA because lusutrombopag is highly bound to protein in plasma [see Clinical Pharmacology (12.3) ] .
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Lusutrombopag is an orally bioavailable, small molecule TPO receptor agonist that interacts with the transmembrane domain of human TPO receptors expressed on megakaryocytes to induce the proliferation and differentiation of megakaryocytic progenitor cells from hematopoietic stem cells and megakaryocyte maturation.
12.2Pharmacodynamics Platelet Response Lusutrombopag upregulates the production of platelets through its agonistic effect on human TPO receptors. The effect of lusutrombopag on platelet count increase was correlated with the AUC across the studied dose range of 0.25 mg to 4 mg in thrombocytopenic patients with chronic liver disease. With the 3 mg daily dose, the mean (standard deviation) maximum platelet count in patients (N=74) without platelet transfusion was 86.9 (27.2) × 10 9 /L, and the median time to reach the maximum platelet count was 12.0 (5 to 35) days.
Cardiac Electrophysiology At a dose 8 times the recommended dosage, MULPLETA does not prolong QT interval to any clinically relevant extent.
12.3Pharmacokinetics Lusutrombopag demonstrated dose-proportional pharmacokinetics after single doses ranging from 1 mg (0.33 times the lowest approved dosage) to 50 mg (16.7 times the highest recommended dosage). Healthy subjects administered 3 mg of lusutrombopag had a geometric mean (%CV) maximal concentration (C max ) of 111 (20.4) ng/mL and area under the time-concentration curve extrapolated to infinity (AUC 0-inf ) of 2931 (23.4) ng.hr/mL. The pharmacokinetics of lusutrombopag were similar in both healthy subjects and the chronic liver disease population.
The accumulation ratios of C max and AUC were approximately 2 with once-daily multiple-dose administration, and steady-state plasma lusutrombopag concentrations were achieved after Day 5. Absorption In patients with chronic liver disease, the time to peak lusutrombopag concentration (T max ) was observed 6 to 8 hours after oral administration. Food Effect Lusutrombopag AUC and C max were not affected when MULPLETA was co-administered with a high-fat meal (a total of approximately 900 calories, with 500, 250, and 150 calories from fat, carbohydrate, and protein, respectively) .
Distribution The mean (%CV) lusutrombopag apparent volume of distribution in healthy adult subjects was 39.5 (23.5) L. The plasma protein binding of lusutrombopag is more than 99.9%. Elimination The terminal elimination half-life (t 1/2 ) in healthy adult subjects was approximately 27 hours.
The mean (%CV) clearance of lusutrombopag in patients with chronic liver disease is estimated to be 1.1 (36.1) L/hr. Metabolism Lusutrombopag is primarily metabolized by CYP4 enzymes, including CYP4A11. Excretion Fecal excretion accounted for 83% of the administered dose, with 16% of the dose excreted as unchanged lusutrombopag, and urinary excretion accounted for approximately 1%.
Specific Populations No clinically significant differences in the pharmacokinetics of lusutrombopag were observed based on age or race/ethnicity. Though lusutrombopag exposure tends to decrease with increasing body weight, differences in exposure are not considered clinically relevant. Patients with Renal Impairment A population pharmacokinetic analysis did not find a clinically meaningful effect of mild (creatinine clearance (CLcr) 60 to less than 90 mL/min) and moderate (CLcr 30 to less than 60 mL/min) renal impairment on the pharmacokinetics of lusutrombopag.
Data in patients with severe renal impairment (CLcr less than 30 mL/min) are limited. Patients with Hepatic Impairment No clinically significant differences in the pharmacokinetics of lusutrombopag were observed based on mild to moderate (Child-Pugh class A and B) hepatic impairment. The mean observed lusutrombopag C max and AUC 0-τ decreased by 20% to 30% in patients (N=5) with severe (Child-Pugh class C) hepatic impairment compared to patients with Child-Pugh class A and class B liver disease.
However, the ranges… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Lusutrombopag is an orally bioavailable, small molecule TPO receptor agonist that interacts with the transmembrane domain of human TPO receptors expressed on megakaryocytes to induce the proliferation and differentiation of megakaryocytic progenitor cells from hematopoietic stem cells and megakaryocyte maturation.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING MULPLETA is supplied as 3 mg lusutrombopag tablets in a child-resistant blister pack containing 7 tablets - NDC 59630-551-07. Store MULPLETA in the original package at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [See USP Controlled Room Temperature].
📦 Storage and Handling ▾
Store MULPLETA in the original package at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [See USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION MULPLETA (lusutrombopag), a thrombopoietin (TPO) receptor agonist, contains lusutrombopag as the active ingredient. The chemical name for lusutrombopag is (2 E )-3-{2,6-Dichloro-4-[(4-{3-[(1 S )-1-(hexyloxy) ethyl]-2-methoxyphenyl}-1,3-thiazol-2-yl) carbamoyl]phenyl}-2-methylprop-2-enoic acid. The structural formula is: The empirical formula for lusutrombopag is C 29 H 32 Cl 2 N 2 O 5 S and the molecular weight is 591.54.
Lusutrombopag is a white to slightly yellowish white powder, and is freely soluble in N,N -dimethylformamide, slightly soluble in ethanol (99.5%) and methanol, very slightly soluble in acetonitrile, and practically insoluble in water. Lusutrombopag is slightly soluble in the buffer solution at pH 11 and practically insoluble in buffer solutions with pH ranges of 1 to 9. MULPLETA (lusutrombopag) tablets for oral use contain lusutrombopag 3 mg.
Excipients are D-mannitol, microcrystalline cellulose, magnesium oxide, sodium lauryl sulfate, hydroxypropyl cellulose, carboxymethylcellulose calcium, magnesium stearate, hypromellose, triethyl citrate, titanium dioxide, red ferric oxide, and talc. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Prior to treatment, patients should fully understand and be informed of the following risks and considerations for MULPLETA. Risks Thrombotic/Thromboembolic Complications MULPLETA is a thrombopoietin (TPO) receptor agonist, and TPO receptor agonists have been associated with thrombotic and thromboembolic complications in patients with chronic liver disease.
Portal vein thrombosis has been reported in patients with chronic liver disease treated with TPO receptor agonists. Pregnancy Advise women of reproductive potential who become pregnant or are planning to become pregnant that MULPLETA should be used during pregnancy only if the potential benefit to the mother justifies the potential risk to the fetus [see Use in Specific Populations (8.1) ] . Lactation Advise women not to breastfeed during treatment with MULPLETA and for 28 days after the last dose of MULPLETA.
Advise women to pump and discard breast milk during this period [see Use in Specific Populations (8.2) ] .
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Lusutrombopag demonstrated dose-proportional pharmacokinetics after single doses ranging from 1 mg (0.33 times the lowest approved dosage) to 50 mg (16.7 times the highest recommended dosage). Healthy subjects administered 3 mg of lusutrombopag had a geometric mean (%CV) maximal concentration (C max ) of 111 (20.4) ng/mL and area under the time-concentration curve extrapolated to infinity (AUC 0-inf ) of 2931 (23.4) ng.hr/mL. The pharmacokinetics of lusutrombopag were similar in both healthy subjects and the chronic liver disease population.
The accumulation ratios of C max and AUC were approximately 2 with once-daily multiple-dose administration, and steady-state plasma lusutrombopag concentrations were achieved after Day 5. Absorption In patients with chronic liver disease, the time to peak lusutrombopag concentration (T max ) was observed 6 to 8 hours after oral administration. Food Effect Lusutrombopag AUC and C max were not affected when MULPLETA was co-administered with a high-fat meal (a total of approximately 900 calories, with 500, 250, and 150 calories from fat, carbohydrate, and protein, respectively) .
Distribution The mean (%CV) lusutrombopag apparent volume of distribution in healthy adult subjects was 39.5 (23.5) L. The plasma protein binding of lusutrombopag is more than 99.9%. Elimination The terminal elimination half-life (t 1/2 ) in healthy adult subjects was approximately 27 hours.
The mean (%CV) clearance of lusutrombopag in patients with chronic liver disease is estimated to be 1.1 (36.1) L/hr. Metabolism Lusutrombopag is primarily metabolized by CYP4 enzymes, including CYP4A11. Excretion Fecal excretion accounted for 83% of the administered dose, with 16% of the dose excreted as unchanged lusutrombopag, and urinary excretion accounted for approximately 1%.
Specific Populations No clinically significant differences in the pharmacokinetics of lusutrombopag were observed based on age or race/ethnicity. Though lusutrombopag exposure tends to decrease with increasing body weight, differences in exposure are not considered clinically relevant. Patients with Renal Impairment A population pharmacokinetic analysis did not find a clinically meaningful effect of mild (creatinine clearance (CLcr) 60 to less than 90 mL/min) and moderate (CLcr 30 to less than 60 mL/min) renal impairment on the pharmacokinetics of lusutrombopag.
Data in patients with severe renal impairment (CLcr less than 30 mL/min) are limited. Patients with Hepatic Impairment No clinically significant differences in the pharmacokinetics of lusutrombopag were observed based on mild to moderate (Child-Pugh class A and B) hepatic impairment. The mean observed lusutrombopag C max and AUC 0-τ decreased by 20% to 30% in patients (N=5) with severe (Child-Pugh class C) hepatic impairment compared to patients with Child-Pugh class A and class B liver disease.
However, the ranges for C max and AUC 0-τ overlapped among patients with Child-Pugh class A, B, and C liver disease. Drug Interaction Studies Clinical Studies No clinically significant changes in lusutrombopag exposure were observed when co-administered with cyclosporine (an inhibitor of P-gp and BCRP) or an antacid containing a multivalent cation (calcium carbonate). No clinically significant changes in midazolam (a CYP3A substrate) exposure were observed when co-administered with lusutrombopag.
In Vitro Studies CYP Enzymes : lusutrombopag has low potential to inhibit CYP enzymes (CYP1A2, CYP2A6, CYP2B6, CYP2C8, CYP2C9, CYP2C19, CYP2D6, and CYP3A4/5). Lusutrombopag did not induce CYP1A2, CYP2C9, or CYP3A4. UGT Enzymes : lusutrombopag did not induce UGT1A2, UGT1A6, or UGT2B7.
Transporter Systems : lusutrombopag is a substrate of P-gp and BCRP. Lusutrombopag has low potential to inhibit P-gp, BCRP, OATP1B1, OATP1B3, OCT1, OCT2, OAT1, OAT3, MATE1, MATE2-K, and BSEP.
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Platelet Response Lusutrombopag upregulates the production of platelets through its agonistic effect on human TPO receptors. The effect of lusutrombopag on platelet count increase was correlated with the AUC across the studied dose range of 0.25 mg to 4 mg in thrombocytopenic patients with chronic liver disease. With the 3 mg daily dose, the mean (standard deviation) maximum platelet count in patients (N=74) without platelet transfusion was 86.9 (27.2) × 10 9 /L, and the median time to reach the maximum platelet count was 12.0 (5 to 35) days.
Cardiac Electrophysiology At a dose 8 times the recommended dosage, MULPLETA does not prolong QT interval to any clinically relevant extent.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES The efficacy of MULPLETA for the treatment of thrombocytopenia in patients with chronic liver disease who are scheduled to undergo a procedure was evaluated in 2 randomized, double-blind, placebo-controlled trials (L-PLUS 1 (N=97) and L-PLUS 2 (N=215; NCT02389621)). Patients with chronic liver disease who were undergoing an invasive procedure and had a platelet count less than 50 × 10 9 /L were eligible to participate. Patients undergoing laparotomy, thoracotomy, open-heart surgery, craniotomy, or organ resection were excluded.
Patients with a history of splenectomy, partial splenic embolization, or thrombosis and those with Child-Pugh class C liver disease, absence of hepatopetal blood flow, or a prothrombotic condition other than chronic liver disease were not allowed to participate. The patient populations were similar between the MULPLETA and placebo arms and consisted of 60% male and 40% female; median age was 60 years (range 19-88). The racial and ethnic distribution was White (55%), Asian (41%), and Other (4%).
Patients were randomized 1:1 to receive 3 mg of MULPLETA or placebo once daily for up to 7 days. Randomization was stratified by liver ablation/coagulation or other procedures and the platelet count at screening/baseline. In L-PLUS 1, 57% of patients underwent procedures other than liver ablation/coagulation and 43% underwent liver ablation/coagulation (RFA/MCT).
In L-PLUS 2, 98% of patients underwent procedures other than liver ablation/coagulation and 2% underwent liver ablation/coagulation (RFA/MCT). Procedures other than liver ablation/coagulation (RFA/MCT) included liver-related procedures (transcatheter arterial chemoembolization, liver biopsy, and others), upper and lower gastrointestinal endoscopy-related procedures (endoscopic variceal ligation, endoscopic injection sclerotherapy, polypectomy, and biopsy), and other procedures (dental extraction, diagnostic paracentesis or laparocentesis, septoplasty, embolization of splenic artery aneurysm, bone marrow biopsy, removal of cervical polyp, and inguinal hernia repair (non-laparotomy based)).
In L-PLUS 1, the major efficacy outcome was the proportion of patients who require no platelet transfusion prior to the primary invasive procedure. In L-PLUS 2, the major efficacy outcome was the proportion of patients who require no platelet transfusion prior to the primary invasive procedure and no rescue therapy for bleeding (i.e., platelet preparations, other blood preparations, including red blood cells and plasma, volume expanders) from randomization through 7 days after the primary invasive procedure. In both trials, additional efficacy outcomes included the proportion of patients who require no platelet transfusion during the study, proportion of responders, duration of the increase in platelet count defined as the number of days during which the platelet count was maintained as ≥50 × 10 9 /L, and the time course of platelet counts.
In both the L-PLUS 1 and L-PLUS 2 trials, responders were defined as patients who had a platelet count of ≥50 × 10 9 /L with an increase of ≥20 × 10 9 /L from baseline. Table 2. L-PLUS 1 Trial: Proportion of Patients Not Requiring Platelet Transfusion Prior to Invasive Procedure and Proportion of Responders Endpoint Proportion (n/N) Exact 95% Confidence Interval Treatment Difference (95% Confidence Interval) p value MULPLETA (N=49) Placebo (N=48) Not requiring platelet transfusion prior to invasive procedure A platelet transfusion was required if the platelet count was less than 50 × 10 9 /L.
78% (38/49) (63, 88) 13% (6/48) (4.7, 25) 64 (49, 79) <0.0001 Cochran-Mantel-Haenszel test with baseline platelet count as stratum; p value and confidence interval calculated using Wald method. Responder Platelet count reached at least 50 × 10 9 /L and increased at least 20 × 10 9 /L from baseline. during study 76% (37/49) (61, 87) 6% (3/48) (1.3, 17) 68 (54, 82) <0.0001 Table 3. L-PLUS 2 Trial: Proportion of Patients Not Req… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility In 2-year studies, lusutrombopag was not carcinogenic to rats at oral doses up to 20 mg/kg/day in males and 2 mg/kg/day in females (a dose 49 times and 30 times, respectively, the human exposure (AUC) at the recommended clinical dose of 3 mg/day for 7 days) and to mice at oral doses up to 20 mg/kg/day in males and females (a dose approximately 45 times the human exposure (AUC) at the recommended clinical dose of 3 mg/day for 7 days). Lusutrombopag was not genotoxic based on an in vitro bacterial reverse mutation (Ames) assay, a chromosomal aberration assay with cultured Chinese hamster lung cells, and an in vivo micronucleus assay with mouse bone marrow cells.
In a fertility and early embryonic development study, lusutrombopag did not affect fertility in male and female rats at oral doses up to 100 mg/kg/day (a dose in males and females approximately 176 and 252 times, respectively, the human exposure (AUC) at the recommended clinical dose of 3 mg/day for 7 days).
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility In 2-year studies, lusutrombopag was not carcinogenic to rats at oral doses up to 20 mg/kg/day in males and 2 mg/kg/day in females (a dose 49 times and 30 times, respectively, the human exposure (AUC) at the recommended clinical dose of 3 mg/day for 7 days) and to mice at oral doses up to 20 mg/kg/day in males and females (a dose approximately 45 times the human exposure (AUC) at the recommended clinical dose of 3 mg/day for 7 days). Lusutrombopag was not genotoxic based on an in vitro bacterial reverse mutation (Ames) assay, a chromosomal aberration assay with cultured Chinese hamster lung cells, and an in vivo micronucleus assay with mouse bone marrow cells.
In a fertility and early embryonic development study, lusutrombopag did not affect fertility in male and female rats at oral doses up to 100 mg/kg/day (a dose in males and females approximately 176 and 252 times, respectively, the human exposure (AUC) at the recommended clinical dose of 3 mg/day for 7 days).
📄 Patient Package Insert ▾
PATIENT INFORMATION MULPLETA ® (mul ple' tah) (lusutrombopag) Tablets This Patient Information has been approved by the U.S. Food and Drug Administration. Issued: 4/2020 What is MULPLETA?
MULPLETA is a prescription medicine used to treat low platelet count (thrombocytopenia) in adults with chronic liver disease who are scheduled to have a procedure. MULPLETA is not used to make platelet count normal in people with chronic liver disease. It is not known if MULPLETA is safe and effective in children.
Before taking MULPLETA, tell your healthcare provider about all of your medical conditions, including if you: have a blood clot or have had a history of a blood clot. have any blood clotting problems, other than thrombocytopenia. are pregnant or plan to become pregnant. MULPLETA may harm your baby. are breastfeeding or plan to breastfeed. It is not known if MULPLETA passes into your breast milk.
Do not breastfeed during your treatment with MULPLETA and for at least 28 days after your last dose. Talk to your healthcare provider about the best way to feed your baby during your treatment with MULPLETA. Tell your healthcare provider about all the medicines you take, including prescription and over-the-counter medicines, vitamins, and herbal supplements.
How should I take MULPLETA? Take MULPLETA exactly as your healthcare provider tells you to take it. Your healthcare provider will tell you when to start taking MULPLETA.
Take MULPLETA 1 time each day for 7 days. MULPLETA may be taken with or without food. If you miss a dose of MULPLETA, take the missed dose as soon as possible on the same day and return to your normal schedule the following day.
If you take too much MULPLETA, call your healthcare provider or go to the nearest hospital emergency room right away. Your healthcare provider will check your platelet count before you start treatment with MULPLETA and before your procedure. What are the possible side effects of MULPLETA?
MULPLETA may cause serious side effects, including: Blood clots, including blood clots in the liver, may happen in people with chronic liver disease and who take MULPLETA. You may have an increased risk of blood clots if you have certain blood clotting conditions. The most common side effect of MULPLETA is headache.
These are not all of the possible side effects of MULPLETA. Call your doctor for medical advice about side effects. You may report side effects to FDA at 1-800-FDA-1088.
How should I store MULPLETA? Store MULPLETA at room temperature between 68°F and 77°F (20°C to 25°C). MULPLETA comes in a child-resistant blister pack.
Keep MULPLETA in the packaging that it comes in. Keep MULPLETA and all medicines out of the reach of children. General information about the safe and effective use of MULPLETA.
Medicines are sometimes prescribed for purposes other than those listed in a Patient Information leaflet. Do not use MULPLETA for a condition for which it was not prescribed. Do not give MULPLETA to other people, even if they have the same symptoms that you have.
It may harm them. You can ask your pharmacist or healthcare provider for information about MULPLETA that is written for healthcare professionals. What are the ingredients of MULPLETA?
Active ingredient: lusutrombopag. Inactive ingredients: D-mannitol, microcrystalline cellulose, magnesium oxide, sodium lauryl sulfate, hydroxypropyl cellulose, carboxymethylcellulose calcium, magnesium stearate, hypromellose, triethyl citrate, titanium dioxide, red ferric oxide, and talc. Manufactured for: Shionogi Inc., Florham Park, NJ 07932 © Shionogi Inc.
2020 For more information, go to www.mulpleta.com or call 1-800-849-9707.
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 3 mg Tablet Blister Card Carton NDC 59630-551-07 Rx only FOR ORAL USE ONLY Mulpleta ® (lusutrombopag) tablets 3 mg per tablet SHIONOGI INC. Lift Here to Open One blister card with 7 tablets PRINCIPAL DISPLAY PANEL - 3 mg Tablet Blister Card Carton
PRINCIPAL DISPLAY PANEL - 3 mg Tablet Blister Card Carton - NDC 59630-551-77 NDC 59630-551-77 Rx only FOR ORAL USE ONLY Physician Sample Not For Sale Mulpleta ® (lusutrombopag) tablets 3 mg per tablet SHIONOGI INC. Lift Here to Open One blister card with 7 tablets PRINCIPAL DISPLAY PANEL - 3 mg Tablet Blister Card Carton - NDC 59630-551-77
Medicare Part D spend CMS · PART D · 2025 (Q1-Q4)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |