
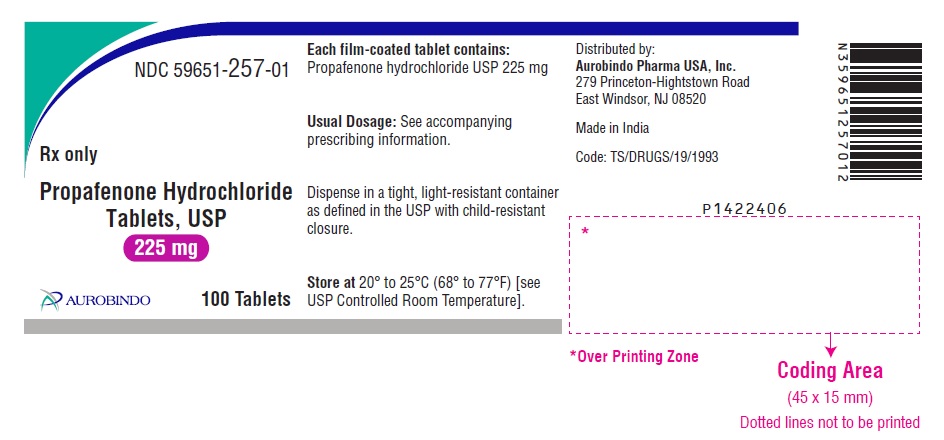
PROPAFENONE HYDROCHLORIDE 225 mg Tablet, Film Coated, 300-count
Other active recalls for Propafenone Hydrochloride (different manufacturers) — 4 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Antiarrhythmic class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Propafenone is used to treat arrhythmia (irregular heartbeat) and to maintain a normal heart rate. Propafenone is in a class of medications called antiarrhythmics. It works by acting on the heart muscle to improve the heart's rhythm.
Read the full MedlinePlus article ↗- Think of it as an electrical 'slow-down' for your heart. Your heart has channels that carry electrical signals triggering each beat — propafenone partially blocks those channels so...
- What exactly is propafenone doing for my heart?
- Yes, a few important ones. Grapefruit juice can raise propafenone levels in your blood, so it's best to avoid it. Several medications — including some antidepressants like paroxeti...
- Are there foods or common medications I should avoid while taking this?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 7T9FYH5QMK
A plant-derived powder that serves as a binder and filler in tablets and capsules. It helps hold ingredients together, adds bulk, and aids in smooth tablet disintegration when swallowed.
-
UNII G2M7P15E5P
Polyethylene glycol 3350 is a synthetic polymer used as a solvent, humectant, and thickening agent in medicines. It helps dissolve other ingredients, retain moisture in the product, and achieve the desired consistency.
-
UNII 532B59J990
Polyvinyl alcohol is a synthetic polymer made from plant-derived materials. It's used as a binder to hold ingredients together, a film-former in coatings, and a thickener in liquid formulations.
-
UNII U725QWY32X
Povidone K30 is a synthetic polymer made from petroleum. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in the stomach so the medicine can be absorbed.
-
UNII 5856J3G2A2
A starch-based powder made from potatoes and processed with sodium. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the medicine can be absorbed.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
9 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.2082 | $62.46 / 300 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Propafenone Hydrochloride 225 mg 62559-0231-01 | ANI | 100 tablets | $0.193 | AB | Availability likely | — |
| Propafenone Hydrochloride 225 mg 64380-0164-01 | Strides | 300 tablets | $0.193 | AB | Availability likely | — |
| Propafenone Hydrochloride 225 mg 64380-0268-01 | Strides | 300 tablets | $0.193 | AB | Availability likely | — |
| Propafenone Hydrochloride 225 mg 50090-4227-00 | A-S | 60 tablets | — | AB | FDA listed | — |
| Propafenone Hydrochloride 225 mg 51407-0016-01 | Golden | 100 tablets | — | AB | FDA listed | — |
| Propafenone Hydrochloride 225 mgthis 59651-0257-33 | Aurobindo | 300 tablets | — | AB | FDA listed | — |
| Propafenone Hydrochloride 225 mg 63629-1988-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Propafenone Hydrochloride 225 mg 72162-1752-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Propafenone Hydrochloride 225 mg 72162-2617-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
💊 Medicaid utilization by pack size
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 59651-0257-01 | 100 TABLET, FILM COATED in 1 BOTTLE (59651-257-01) | $0.1929 / ea | $19.29 | 2019-10-25 | Active |
| 59651-0257-33 You're viewing this | 300 TABLET, FILM COATED in 1 BOTTLE (59651-257-33) | — | — | 2019-10-25 | Active |
You're viewing the largest of 2 pack sizes for this product.
This pack shows little to no recent Medicaid volume — the 100 tablets pack carries most fills. See all packs ↓
Pack size FAQ
What quantity is in NDC 59651-0257-33?
What is the difference between NDC 59651-0257-33 and NDC 59651-0257-01?
What NDC number is used to bill for this package of PROPAFENONE HYDROCHLORIDE 225 mg Tablet, Film Coated?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: MORTALITY In the National Heart, Lung, and Blood Institute’s Cardiac Arrhythmia Suppression Trial (CAST), a long-term, multicenter, randomized, double-blind trial in subjects with asymptomatic non-life-threatening ventricular arrhythmias who had a myocardial infarction more than 6 days but less than 2 years previously, an increased rate of death or reversed cardiac arrest rate (7.7%; 56/730) was seen in subjects treated with encainide or flecainide (Class IC antiarrhythmics) compared with that seen in subjects assigned to placebo (3.0%; 22/725).
The average duration of treatment with encainide or flecainide in this trial was 10 months. The applicability of the CAST results to other populations (e.g., those without recent myocardial infarction) or other antiarrhythmic drugs is uncertain, but at present, it is prudent to consider any IC antiarrhythmic to have a significant proarrhythmic risk in patients with structural heart disease. Given the lack of any evidence that these drugs improve survival, antiarrhythmic agents should generally be avoided in patients with non-life-threatening ventricular arrhythmias, even if the patients are experiencing unpleasant, but not life-threatening, symptoms or signs.
WARNING: MORTALITY See full prescribing information for complete boxed warning. An increased rate of death or reversed cardiac arrest rate was seen in subjects treated with encainide or flecainide (Class IC antiarrhythmics) compared with that seen in subjects assigned to placebo. At present, it is prudent to consider any IC antiarrhythmic to have a significant risk of provoking proarrhythmic events in patients with structural heart disease.
Given the lack of any evidence that these drugs improve survival, antiarrhythmic agents should generally be avoided in patients with non-life-threatening ventricular arrhythmias, even if the patients are experiencing unpleasant, but not life-threatening, symptoms or signs.
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Propafenone hydrochloride tablets are indicated to: prolong the time to recurrence of paroxysmal atrial fibrillation/flutter (PAF) associated with disabling symptoms in patients without structural heart disease. prolong the time to recurrence of paroxysmal supraventricular tachycardia (PSVT) associated with disabling symptoms in patients without structural heart disease. treat documented ventricular arrhythmias, such as sustained ventricular tachycardia that, in the judgment of the physician, are life-threatening.
Initiate treatment in the hospital. Usage Considerations: The use of propafenone hydrochloride tablets in patients with permanent atrial fibrillation (AF) or in patients exclusively with atrial flutter or PSVT has not been evaluated. Do not use propafenone hydrochloride tablets to control ventricular rate during AF.
Some patients with atrial flutter treated with propafenone have developed 1:1 conduction, producing an increase in ventricular rate. Concomitant treatment with drugs that increase the functional atrioventricular (AV) nodal refractory period is recommended. The use of propafenone hydrochloride tablets in patients with chronic atrial fibrillation has not been evaluated.
Because of the proarrhythmic effects of propafenone hydrochloride tablets, its use with lesser ventricular arrhythmias is not recommended, even if patients are symptomatic, and any use of the drug should be reserved for patients in whom, in the opinion of the physician, the potential benefits outweigh the risks. The effect of propafenone on mortality has not been determined [see Boxed Warning ] . Propafenone hydrochloride is an antiarrhythmic indicated to: prolong the time to recurrence of symptomatic atrial fibrillation (AF) in patients with episodic (most likely paroxysmal or persistent) AF who do not have structural heart disease.
(1) prolong the time to recurrence of paroxysmal supraventricular tachycardia (PSVT) associated with disabling symptoms in patients who do not have structural heart disease. (1) treat documented life-threatening ventricular arrhythmias. (1) Usage Considerations: Use in patients with permanent atrial fibrillation or with atrial flutter or PSVT has not been evaluated.
Do not use to control ventricular rate during atrial fibrillation. (1) In patients with atrial fibrillation and atrial flutter, use propafenone hydrochloride tablets with drugs that increase the atrioventricular nodal refractory period. (1) Because of proarrhythmic effects, use with lesser ventricular arrhythmias is not recommended, even if patients are symptomatic.
(1) The effect of propafenone on mortality has not been determined. (1)
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION The dose of propafenone hydrochloride tablets must be individually titrated on the basis of response and tolerance. Initiate therapy with propafenone hydrochloride tablets 150 mg given every 8 hours (450 mg per day). Dosage may be increased at a minimum of 3- to 4- day intervals to 225 mg every 8 hours (675 mg per day).
If additional therapeutic effect is needed, the dose of propafenone hydrochloride tablets may be increased to 300 mg every 8 hours (900 mg per day). The usefulness and safety of dosages exceeding 900 mg per day have not been established. In patients with hepatic impairment or those with significant widening of the QRS complex or second- or third-degree AV block, consider reducing the dose.
As with other antiarrhythmic agents, in the elderly or in ventricular arrhythmia patients with marked previous myocardial damage, the dose of propafenone hydrochloride tablets should be increased more gradually during the initial phase of treatment. The combination of cytochrome P450 3A4 (CYP3A4) inhibition and either cytochrome P450 2D6 (CYP2D6) deficiency or CYP2D6 inhibition with the simultaneous administration of propafenone may significantly increase the concentration of propafenone and thereby increase the risk of proarrhythmia and other adverse events.
Therefore, avoid simultaneous use of propafenone hydrochloride tablets with both a CYP2D6 inhibitor and a CYP3A4 inhibitor [see Warnings and Precautions (5.4) , Drug Interactions (7.1) ] . Initiate therapy with 150 mg given every 8 hours. (2) As needed, uptitrate in 3 to 4 days to 225 to 300 mg every 8 hours.
(2) Consider reducing the dose in patients with hepatic impairment, significant widening of the QRS complex, or second- or third-degree AV block. (2)
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS 150 mg, 225 mg and 300 mg white to off-white, round, biconvex, film-coated tablets with a break line on one side. Tablets: 150 mg, 225 mg and 300 mg. (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Propafenone hydrochloride tablets are contraindicated in the following circumstances: Heart failure Cardiogenic shock Sinoatrial, atrioventricular, and intraventricular disorders of impulse generation or conduction (e.g., sick sinus node syndrome, AV block) in the absence of an artificial pacemaker Known Brugada Syndrome Bradycardia Marked hypotension Bronchospastic disorders or severe obstructive pulmonary disease Marked electrolyte imbalance Heart failure (4) Cardiogenic shock (4) Sinoatrial, atrioventricular, and intraventricular disorders of impulse generation or conduction in the absence of pacemaker (4) Known Brugada Syndrome (4) Bradycardia (4) Marked hypotension (4) Bronchospastic disorders and severe obstructive pulmonary disease (4) Marked electrolyte imbalance (4)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS May cause new or worsened arrhythmias. Evaluate patients via ECG prior to and during therapy. (5.1) Propafenone hydrochloride may unmask Brugada or Brugada-like Syndrome.
(4 , 5.2) Avoid use with other drugs that prolong the QT interval. (5.3) Avoid simultaneous use of propafenone with both a cytochrome P450 2D6 (CYP2D6) inhibitor and a 3A4 inhibitor (CYP3A4). (5.4) May provoke overt heart failure.
(5.5) May cause dose-related first-degree AV block or other conduction disturbances. Only use in patients with conduction disorders who have pacemakers. (5.6) May affect artificial pacemakers.
Monitor pacemaker function. (5.7) Agranulocytosis: Patients should report signs of infection. (5.8) May exacerbate myasthenia gravis.
(5.11)
5.1Proarrhythmic Effects Propafenone has caused new or worsened arrhythmias. Such proarrhythmic effects include sudden death and life-threatening ventricular arrhythmias such as ventricular fibrillation, ventricular tachycardia, asystole, and torsade de pointes. It may also worsen premature ventricular contractions or supraventricular arrhythmias, and it may prolong the QT interval.
It is therefore essential that each patient given propafenone hydrochloride be evaluated electrocardiographically prior to and during therapy to determine whether the response to propafenone hydrochloride supports continued treatment. Because propafenone prolongs the QRS interval in the electrocardiogram, changes in the QT interval are difficult to interpret [see Clinical Pharmacology (12.2) ]. In a U.S. uncontrolled, open-label, multicenter trial in subjects with symptomatic supraventricular tachycardia (SVT), 1.9% (9/474) of these subjects experienced ventricular tachycardia (VT) or ventricular fibrillation (VF) during the trial.
However, in 4 of the 9 subjects, the ventricular tachycardia was of atrial origin. Six of the 9 subjects that developed ventricular arrhythmias did so within 14 days of onset of therapy. About 2.3% (11/474) of all subjects had a recurrence of SVT during the trial which could have been a change in the subjects’ arrhythmia behavior or could represent a proarrhythmic event.
Case reports in patients treated with propafenone for atrial fibrillation/flutter have included increased premature ventricular contractions (PVCs), VT, VF, torsade de pointes, asystole, and death. Overall in clinical trials with propafenone hydrochloride (which included subjects treated for ventricular arrhythmias, atrial fibrillation/flutter, and PSVT), 4.7% of all subjects had new or worsened ventricular arrhythmia possibly representing a proarrhythmic event (0.7% was an increase in PVCs; 4.0% a worsening or new appearance of VT or VF).
Of the subjects who had worsening of VT (4%), 92% had a history of VT and/or VT/VF, 71% had coronary artery disease, and 68% had a prior myocardial infarction. The incidence of proarrhythmia in subjects with less serious or benign arrhythmias, which include subjects with an increase in frequency of PVCs, was 1.6%. Although most proarrhythmic events occurred during the first week of therapy, late events also were seen and the CAST trial [see Boxed Warning: Mortality ] suggests that an increased risk of proarrythmia is present throughout treatment.
In a trial of sustained-release propafenone, there were too few deaths to assess the long-term risk to patients. There were 5 deaths; 3 in the pooled group for sustained-release propafenone (0.8%), and 2 in the placebo group (1.6%). In the overall database of 8 trials of sustained-release propafenone and immediate-release propafenone hydrochloride, the mortality rate was 2.5% per year on propafenone and 4.0% per year on placebo.
Concurrent use of propafenone with other antiarrhythmic agents has not been well studied.
5.2Unmasking Brugada Syndrome Brugada Syndrome may be unmasked after exposure to propafenone hydrochloride. Perform an ECG after initiation of propafenone hydrochloride, and discontinue the drug if changes are sug…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The most commonly reported adverse events with propafenone (greater than 5%) included: unusual taste, nausea and/or vomiting, dizziness, constipation, headache, fatigue, first-degree AV block, and intraventricular conduction delay. (6.1) To report SUSPECTED ADVERSE REACTIONS, contact Aurobindo Pharma USA, Inc. at 1-866-850-2876 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared with rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adverse reactions associated with propafenone hydrochloride occur most frequently in the gastrointestinal, cardiovascular, and central nervous systems. About 20% of subjects treated with propafenone hydrochloride have discontinued treatment because of adverse reactions.
Adverse reactions reported for greater than 1.5% of 474 subjects with SVT who received propafenone hydrochloride in U.S. clinical trials are presented in Table 1 by incidence and percent discontinuation, reported to the nearest percent. Table 1. Adverse Reactions Reported for >1.5% of Subjects with Supraventricular Tachycardia Adverse Reaction Incidence (n = 480) % of Subjects Who Discontinued Unusual taste 14% 1.3% Nausea and/or vomiting 11% 2.9% Dizziness 9% 1.7% Constipation 8% 0.2% Headache 6% 0.8% Fatigue 6% 1.5% Blurred Vision 3% 0.6% Weakness 3% 1.3% Dyspnea 2% 1.0% Wide complex tachycardia 2% 1.9% CHF 2% 0.6% Bradycardia 2% 0.2% Palpitations 2% 0.2% Tremor 2% 0.4% Anorexia 2% 0.2% Diarrhea 2% 0.4% Ataxia 2% 0.0% In controlled trials in subjects with ventricular arrhythmia, the most common reactions reported for propafenone hydrochloride and more frequent than on placebo were unusual taste, dizziness, first-degree AV block, intraventricular conduction delay, nausea and/or vomiting, and constipation.
Headache was relatively common also, but was not increased compared with placebo. Other reactions reported more frequently than on placebo or comparator and not already reported elsewhere included anxiety, angina, second-degree AV block, bundle branch block, loss of balance, congestive heart failure, and dyspepsia. Adverse reactions reported for greater than or equal to 1% of 2,127 subjects with ventricular arrhythmia who received propafenone in U.S. clinical trials were evaluated by daily dose.
The most common adverse reactions appeared dose-related (but note that most subjects spent more time at the larger doses), especially dizziness, nausea and/or vomiting, unusual taste, constipation, and blurred vision. Some less common reactions may also have been dose-related such as first-degree AV block, congestive heart failure, dyspepsia, and weakness. Other adverse reactions included rash, syncope, chest pain, abdominal pain, ataxia, and hypotension.
In addition, the following adverse reactions were reported less frequently than 1% either in clinical trials or in marketing experience. Causality and relationship to propafenone therapy cannot necessarily be judged from these events. Cardiovascular System Atrial flutter, AV dissociation, cardiac arrest, flushing, hot flashes, sick sinus syndrome, sinus pause or arrest, supraventricular tachycardia.
Nervous System Abnormal dreams, abnormal speech, abnormal vision, confusion, depression, memory loss, numbness, paresthesias, psychosis/mania, seizures (0.3%), tinnitus, unusual smell sensation, vertigo. Gastrointestinal Cholestasis, elevated liver enzymes (alkaline phosphatase, serum transaminases), gastroenteritis, hepatitis. Hematologic Agranulocytosis, anemia, bruising, granulocytopenia, leukopenia, purpura, thrombocytopenia.
Other Alopecia, eye irritation, impotence, increased glucose, positive ANA (0.7%), muscle cramps, muscle weakness, nephrotic syndrome, pain, pruritus.
6.2 Postmarketing Experience The following adverse reactions…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Inhibitors of CYP2D6, 1A2, and 3A4 increase propafenone exposure. (7.1) Propafenone may increase digoxin or warfarin levels. (7.2 , 7.3) Orlistat may reduce propafenone exposure. Taper orlistat withdrawal. (7.4) Lidocaine may increase central nervous system side effects. (7.6)
7.1CYP2D6 and CYP3A4 Inhibitors Drugs that inhibit CYP2D6 (such as desipramine, paroxetine, ritonavir, sertraline) and CYP3A4 (such as ketoconazole, ritonavir, saquinavir, erythromycin, grapefruit juice) can be expected to cause increased plasma levels of propafenone. The combination of CYP3A4 inhibition and either CYP2D6 deficiency or CYP2D6 inhibition with administration of propafenone may increase the risk of adverse reactions, including proarrhythmia. Therefore, simultaneous use of propafenone hydrochloride with both a CYP2D6 inhibitor and a CYP3A4 inhibitor should be avoided [see Warnings and Precautions (5.4) , Dosage and Administration (2) ].
Amiodarone Concomitant administration of propafenone and amiodarone can affect conduction and repolarization and is not recommended. Cimetidine Concomitant administration of propafenone immediate-release tablets and cimetidine in 12 healthy subjects resulted in a 20% increase in steady-state plasma concentrations of propafenone. Fluoxetine Concomitant administration of propafenone and fluoxetine in extensive metabolizers increased the S-propafenone C max and AUC by 39% and 50%, respectively, and the R-propafenone C max and AUC by 71% and 50%, respectively.
Quinidine Small doses of quinidine completely inhibit the CYP2D6 hydroxylation metabolic pathway, making all patients, in effect, slow metabolizers [see Clinical Pharmacology (12.3) ] . Concomitant administration of quinidine (50 mg 3 times daily) with 150 mg immediate-release propafenone 3 times daily decreased the clearance of propafenone by 60% in extensive metabolizers, making them slow metabolizers. Steady-state plasma concentrations more than doubled for propafenone and decreased 50% for 5-OH-propafenone.
A 100 mg dose of quinidine tripled steady-state concentrations of propafenone. Avoid concomitant use of propafenone and quinidine. Rifampin Concomitant administration of rifampin and propafenone in extensive metabolizers decreased the plasma concentrations of propafenone by 67% with a corresponding decrease of 5-OH-propafenone by 65%.
The concentrations of norpropafenone increased by 30%. In slow metabolizers, there was a 50% decrease in propafenone plasma concentrations and an increase in the AUC and C max of norpropafenone by 74% and 20%, respectively. Urinary excretion of propafenone and its metabolites decreased significantly.
Similar results were noted in elderly patients: Both the AUC and C max of propafenone decreased by 84%, with a corresponding decrease in AUC and C max of 5-OH‑propafenone by 69% and 57%, respectively.
7.2Digoxin Concomitant use of propafenone and digoxin increased steady-state serum digoxin exposure (AUC) in patients by 60% to 270% and decreased the clearance of digoxin by 31% to 67%. Monitor plasma digoxin levels of patients receiving propafenone and adjust digoxin dosage as needed.
7.3Warfarin The concomitant administration of propafenone and warfarin increased warfarin plasma concentrations at steady state by 39% in healthy volunteers and prolonged the prothrombin time (PT) in patients taking warfarin. Adjust the warfarin dose as needed by monitoring INR (international normalized ratio).
7.4Orlistat Orlistat may limit the fraction of propafenone available for absorption. In postmarketing reports, abrupt cessation of orlistat in patients stabilized on propafenone has resulted in severe adverse events including convulsions, atrioventricular block, and acute circulatory failure.
7.5Beta-Antagonists Concomitant use of propafenone and propranolol in healthy subjects increased propranolol plasma concentrations at steady state by 113%. In 4 patients, administration of metoprolol with propafenone increas…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary There are no studies of propafenone hydrochloride in pregnant women. Available data from published case reports and several decades of postmarketing experience with use of propafenone hydrochloride in pregnancy have not identified any drug-associated risks of miscarriage, birth defects, or adverse maternal or fetal outcomes. Untreated arrhythmias during pregnancy may pose a risk to the pregnant woman and fetus (see Clinical Considerations).
Propafenone and its metabolite, 5-OH-propafenone, cross the placenta in humans. In animal studies, propafenone was not teratogenic. At maternally toxic doses (ranging from 2 to 6 times the maximum recommended human dose [MRHD]), there was evidence of adverse developmental outcomes when administered to pregnant rabbits and rats during organogenesis or when administered to pregnant rats during mid-gestation through weaning of their offspring (see Data) .
The estimated background risks of major birth defects and miscarriage for the indicated populations are unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk: The incidence of VT is increased and may be more symptomatic during pregnancy. Ventricular arrhythmias most often occur in pregnant women with underlying cardiomyopathy, congenital heart disease, valvular heart disease, or mitral valve prolapse. Breakthrough arrhythmias may also occur during pregnancy, as therapeutic treatment levels may be difficult to maintain due to the increased volume of distribution and increased drug metabolism inherent in the pregnant state.
Fetal/Neonatal Adverse Reactions: Propafenone and its metabolite have been shown to cross the placenta. Adverse reactions such as fetal/neonatal arrhythmias have been associated with the use of other antiarrhythmic agents by pregnant women. Fetal/neonatal monitoring for signs and symptoms of arrhythmia is recommended during and after treatment of pregnant women with propafenone.
Labor or Delivery: Risk of arrhythmias may increase during labor and delivery. Patients treated with propafenone hydrochloride should be monitored continuously for arrhythmias during labor and delivery [see Warnings and Precautions (5.1) ] . Data Propafenone has been shown to cause embryo-fetal mortality in rabbits and rats when given orally during organogenesis at maternally toxic doses of 150 mg/kg/day (rabbit: maternal mortality, decreased body weight gain and food consumption at approximately 3 times the MRHD on a mg/m 2 basis) and 600 mg/kg/day (rat: maternal decreased body weight gain and food consumption at approximately 6 times the MRHD on a mg/m 2 basis).
In addition, a maternally toxic dose of 600 mg/kg/day (approximately 6 times the MRHD on a mg/m 2 basis) also caused decreased fetal weights in rats. Increased placental weights and delayed ossification occurred in rabbits at a dose of 30 mg/kg/day (less than the MRHD on a mg/m 2 basis) in the absence of maternal toxicity. No adverse developmental outcomes in the absence of maternal toxicity were seen following oral doses of 15 mg/kg/day to rabbits or up to 270 mg/kg/day to rats administered during organogenesis (equivalent to 0.3 times or approximately 3 times the MRHD on a mg/m 2 basis, respectively).
In an oral study, female rats received propafenone up to 500 mg/kg/day from mid-gestation through weaning. At 90 mg/kg/day (equivalent to the MRHD on a mg/m 2 basis), there were no adverse developmental outcomes in the absence of maternal toxicity. However, doses ≥180 mg/kg/day (2 or more times the MRHD on a mg/m 2 basis) produced increases in maternal deaths and resulted in reductions in neonatal survival, body weight gain, and delayed dev…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no studies of propafenone hydrochloride in pregnant women. Available data from published case reports and several decades of postmarketing experience with use of propafenone hydrochloride in pregnancy have not identified any drug-associated risks of miscarriage, birth defects, or adverse maternal or fetal outcomes. Untreated arrhythmias during pregnancy may pose a risk to the pregnant woman and fetus (see Clinical Considerations).
Propafenone and its metabolite, 5-OH-propafenone, cross the placenta in humans. In animal studies, propafenone was not teratogenic. At maternally toxic doses (ranging from 2 to 6 times the maximum recommended human dose [MRHD]), there was evidence of adverse developmental outcomes when administered to pregnant rabbits and rats during organogenesis or when administered to pregnant rats during mid-gestation through weaning of their offspring (see Data) .
The estimated background risks of major birth defects and miscarriage for the indicated populations are unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk: The incidence of VT is increased and may be more symptomatic during pregnancy. Ventricular arrhythmias most often occur in pregnant women with underlying cardiomyopathy, congenital heart disease, valvular heart disease, or mitral valve prolapse. Breakthrough arrhythmias may also occur during pregnancy, as therapeutic treatment levels may be difficult to maintain due to the increased volume of distribution and increased drug metabolism inherent in the pregnant state.
Fetal/Neonatal Adverse Reactions: Propafenone and its metabolite have been shown to cross the placenta. Adverse reactions such as fetal/neonatal arrhythmias have been associated with the use of other antiarrhythmic agents by pregnant women. Fetal/neonatal monitoring for signs and symptoms of arrhythmia is recommended during and after treatment of pregnant women with propafenone.
Labor or Delivery: Risk of arrhythmias may increase during labor and delivery. Patients treated with propafenone hydrochloride should be monitored continuously for arrhythmias during labor and delivery [see Warnings and Precautions (5.1) ] . Data Propafenone has been shown to cause embryo-fetal mortality in rabbits and rats when given orally during organogenesis at maternally toxic doses of 150 mg/kg/day (rabbit: maternal mortality, decreased body weight gain and food consumption at approximately 3 times the MRHD on a mg/m 2 basis) and 600 mg/kg/day (rat: maternal decreased body weight gain and food consumption at approximately 6 times the MRHD on a mg/m 2 basis).
In addition, a maternally toxic dose of 600 mg/kg/day (approximately 6 times the MRHD on a mg/m 2 basis) also caused decreased fetal weights in rats. Increased placental weights and delayed ossification occurred in rabbits at a dose of 30 mg/kg/day (less than the MRHD on a mg/m 2 basis) in the absence of maternal toxicity. No adverse developmental outcomes in the absence of maternal toxicity were seen following oral doses of 15 mg/kg/day to rabbits or up to 270 mg/kg/day to rats administered during organogenesis (equivalent to 0.3 times or approximately 3 times the MRHD on a mg/m 2 basis, respectively).
In an oral study, female rats received propafenone up to 500 mg/kg/day from mid-gestation through weaning. At 90 mg/kg/day (equivalent to the MRHD on a mg/m 2 basis), there were no adverse developmental outcomes in the absence of maternal toxicity. However, doses ≥180 mg/kg/day (2 or more times the MRHD on a mg/m 2 basis) produced increases in maternal deaths and resulted in reductions in neonatal survival, body weight gain, and delayed development in the presence of ma…
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of propafenone in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical trials of propafenone hydrochloride did not include sufficient numbers of subjects aged 65 and older to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger subjects. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
10 OVERDOSAGE The symptoms of overdosage may include hypotension, somnolence, bradycardia, intra-atrial and intraventricular conduction disturbances, and rarely, convulsions and high-grade ventricular arrhythmias. Defibrillation, as well as infusion of dopamine and isoproterenol, has been effective in controlling abnormal rhythm and blood pressure. Convulsions have been alleviated with intravenous diazepam.
General supportive measures such as mechanical respiratory assistance and external cardiac massage may be necessary. The hemodialysis of propafenone in patients with an overdose is expected to be of limited value in the removal of propafenone as a result of both its high protein binding (greater than 95%) and large volume of distribution.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Propafenone is a Class 1C antiarrhythmic drug with local anesthetic effects and a direct stabilizing action on myocardial membranes. The electrophysiological effect of propafenone manifests itself in a reduction of upstroke velocity (Phase 0) of the monophasic action potential. In Purkinje fibers, and, to a lesser extent, myocardial fibers, propafenone reduces the fast inward current carried by sodium ions.
Diastolic excitability threshold is increased and effective refractory period prolonged. Propafenone reduces spontaneous automaticity and depresses triggered activity. Studies in anesthetized dogs and isolated organ preparations show that propafenone has beta-sympatholytic activity at about 1/50 the potency of propranolol.
Clinical studies employing isoproterenol challenge and exercise testing after single doses of propafenone indicate a beta-adrenergic blocking potency (per mg) about 1/40 that of propranolol in man. In clinical trials, resting heart rate decreases of about 8% were noted at the higher end of the therapeutic plasma concentration range. At very high concentrations in vitro , propafenone can inhibit the slow inward current carried by calcium, but this calcium antagonist effect probably does not contribute to antiarrhythmic efficacy.
Moreover, propafenone inhibits a variety of cardiac potassium currents in in vitro studies (i.e., the transient outward, the delayed rectifier, and the inward rectifier current). Propafenone has local anesthetic activity approximately equal to procaine. Compared with propafenone, the main metabolite, 5-hydroxypropafenone, has similar sodium and calcium channel activity, but about 10 times less beta-blocking activity.
(N-depropylpropafenone has weaker sodium channel activity but equivalent affinity for beta-receptors.)
12.2Pharmacodynamics Cardiac Electrophysiology Electrophysiology trials in subjects with ventricular tachycardia have shown that propafenone prolongs atrioventricular conduction while having little or no effect on sinus node function. Both atrioventricular nodal conduction time (AH interval) and His-Purkinje conduction time (HV interval) are prolonged. Propafenone has little or no effect on the atrial functional refractory period, but AV nodal functional and effective refractory periods are prolonged.
In patients with Wolff-Parkinson-White syndrome, propafenone hydrochloride reduces conduction and increases the effective refractory period of the accessory pathway in both directions. Electrocardiograms: Propafenone prolongs the PR and QRS intervals. Prolongation of the QRS interval makes it difficult to interpret the effect of propafenone on the QT interval.
Table 2. Mean Changes in Electrocardiogram Intervals a a Change and percent change based on mean baseline values for each treatment group. Interval Total Daily Dose (mg) 337.5 mg 450 mg 675 mg 900 mg msec % msec % msec % msec % RR -14.5 -1.8 30.6 3.8 31.5 3.9 41.7
5.1PR 3.6 2.1 19.1 11.6 28.9 17.8 35.6
21.9QRS 5.6 6.4 5.5 6.1 7.7 8.4 15.6
17.3QTc 2.7 0.7 -7.5 -1.8 5.0 1.2 14.7
3.7In any individual patient, the above ECG changes cannot be readily used to predict either efficacy or plasma concentration. Propafenone hydrochloride causes a dose-related and concentration-related decrease in the rate of single and multiple PVCs and can suppress recurrence of ventricular tachycardia. Based on the percent of patients attaining substantial (80% to 90%) suppression of ventricular ectopic activity, it appears that trough plasma levels of 0.2 to 1.5 mcg/mL can provide good suppression, with higher concentrations giving a greater rate of good response.
When 600 mg/day propafenone was administered to subjects with paroxysmal atrial tachyarrhythmias, mean heart rate during arrhythmia decreased 14 beats per min and 37 beats per min for subjects with PAF and subjects with PSVT, respectively. Hemodynamics Trials in humans have shown that propafenone hydrochloride exerts a negati…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Propafenone is a Class 1C antiarrhythmic drug with local anesthetic effects and a direct stabilizing action on myocardial membranes. The electrophysiological effect of propafenone manifests itself in a reduction of upstroke velocity (Phase 0) of the monophasic action potential. In Purkinje fibers, and, to a lesser extent, myocardial fibers, propafenone reduces the fast inward current carried by sodium ions.
Diastolic excitability threshold is increased and effective refractory period prolonged. Propafenone reduces spontaneous automaticity and depresses triggered activity. Studies in anesthetized dogs and isolated organ preparations show that propafenone has beta-sympatholytic activity at about 1/50 the potency of propranolol.
Clinical studies employing isoproterenol challenge and exercise testing after single doses of propafenone indicate a beta-adrenergic blocking potency (per mg) about 1/40 that of propranolol in man. In clinical trials, resting heart rate decreases of about 8% were noted at the higher end of the therapeutic plasma concentration range. At very high concentrations in vitro , propafenone can inhibit the slow inward current carried by calcium, but this calcium antagonist effect probably does not contribute to antiarrhythmic efficacy.
Moreover, propafenone inhibits a variety of cardiac potassium currents in in vitro studies (i.e., the transient outward, the delayed rectifier, and the inward rectifier current). Propafenone has local anesthetic activity approximately equal to procaine. Compared with propafenone, the main metabolite, 5-hydroxypropafenone, has similar sodium and calcium channel activity, but about 10 times less beta-blocking activity.
(N-depropylpropafenone has weaker sodium channel activity but equivalent affinity for beta-receptors.)
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Propafenone Hydrochloride Tablets, USP 150 mg is available for oral administration as white to off-white color, round shaped, biconvex, film-coated tablet debossed with “PR” above the break line, “OT” below the break line on one side and “150” on other side. Bottles of 100 NDC 59651-256-01 Bottles of 300 NDC 59651-256-33 Propafenone Hydrochloride Tablets, USP 225 mg is available for oral administration as white to off-white color, round shaped, biconvex, film-coated tablet debossed with “PR” above the break line, “OT” below the break line on one side and “225” on other side.
Bottles of 100 NDC 59651-257-01 Bottles of 300 NDC 59651-257-33 Propafenone Hydrochloride Tablets, USP 300 mg is available for oral administration as white to off-white color, round shaped, biconvex, film-coated tablet debossed with “PR” above the break line, “OT” below the break line on one side and “300” on other side. Bottles of 100 NDC 59651-258-01 Storage Store at 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature]. Dispense in a tight, light-resistant container.
📋 Description ▾
11 DESCRIPTION Propafenone hydrochloride is an antiarrhythmic drug supplied in film-coated tablets of 150 mg, 225 mg and 300 mg for oral administration. Propafenone has some structural similarities to beta-blocking agents. Chemically, propafenone hydrochloride is 2’-[2-hydroxy-3-(propylamino)-propoxy]-3-phenylpropiophenone hydrochloride, with a molecular weight of 377.92.
The molecular formula is C 21 H 27 NO 3 •HCl. The structural formula of propafenone hydrochloride is given below: Propafenone hydrochloride occurs as white crystalline powder. It is soluble in methanol and in hot water; slightly soluble in alcohol and in chloroform; very slightly soluble in acetone; insoluble in diethyl ether and in toluene.
The following inactive ingredients are contained in the tablet: corn starch, magnesium stearate, microcrystalline cellulose, polyethylene glycol, polyvinyl alcohol, povidone, sodium starch glycolate, talc and titanium dioxide. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Instruct patients to notify their healthcare providers of any change in over-the-counter, prescription, and supplement use. Instruct patients to report symptoms that may be associated with altered electrolyte balance, such as excessive or prolonged diarrhea, sweating, vomiting, or loss of appetite or thirst.
Instruct patients not to double the next dose if a dose is missed. The next dose should be taken at the usual time. Distributed by: Aurobindo Pharma USA, Inc.
279 Princeton-Hightstown Road East Windsor, NJ 08520 Manufactured by: Aurobindo Pharma Limited Hyderabad-500 032, India Revised: 12/2021