
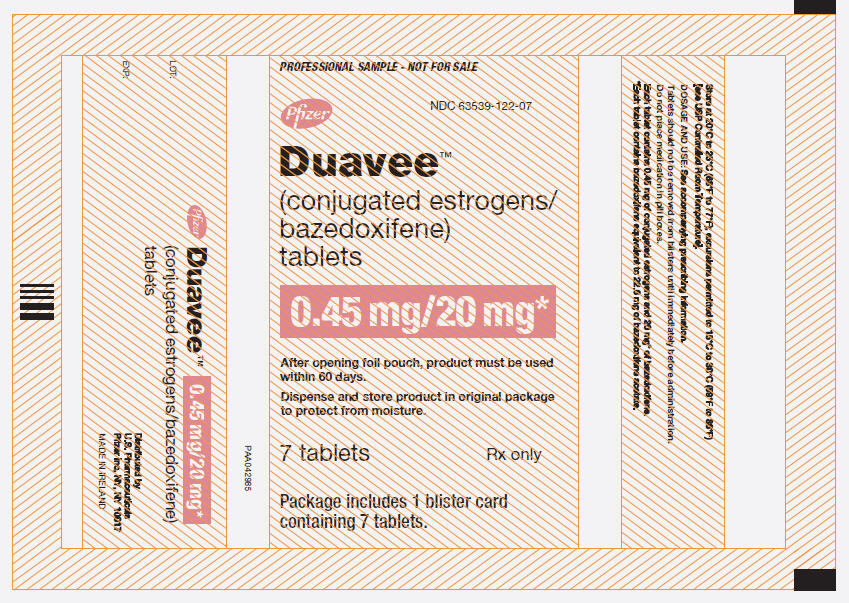
Duavee conjugated estrogens/bazedoxifene .45 mg; 20 mg Tablet, Film Coated, 7-count — NDC 63539-122-07 (Billing 63539-0122-07)
This is a package of 7 tablets of Duavee conjugated estrogens/bazedoxifene .45 mg; 20 mg Tablet, Film Coated from U.S. Pharmaceuticals, marketed since Nov 2013 and currently FDA-listed, this package's marketing is listed to end Dec 2026. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 63539-122-07 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 63539 labeler · 122 product · 07 package
- Package marketed since
- Nov 15, 2013
- Package marketing ended
- Dec 31, 2026
- Sample package
- Yes — professional sample, not for sale
- Barcode (UPC-A, from the NDC)
- 3 6353912207 1
- FDA record last changed
- Aug 27, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
- RxCUI (RxNorm): 1441392
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Estrogen Agonist/Antagonist class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Estrogen and bazedoxifene tablets are used to treat hot flashes (sudden feelings of warmth, especially in the face, neck, and chest) in women who are experiencing menopause (stage of life when menstrual periods become less frequent and stop and women may experience other symptoms and body changes). Estrogen and bazedoxifene tablets are also used to prevent osteoporosis (condition in which the bones become thin and weak and break easily) in women who have undergone menopause. Estrogen is in a class of medications called hormones and bazedoxifene is in a class of medications called estrogen agon...
Read the full MedlinePlus article ↗Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $6.65 | $46.57 / 7 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 5, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 63539-0122-07 You're viewing this Main listing | 1 BLISTER PACK in 1 CARTON / 7 TABLET, FILM COATED in 1 BLISTER PACK Sample | 2013-11-15 | Dec 31, 2026 | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Duavee .45 mg/1; 20 mg 00008-1123-12 | Wyeth | 15 tablets | $6.479 | — | Availability likely | — |
| Duavee .45 mg/1; 20 mgthis 63539-0122-07 | U.S. | 7 tablets | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 7683051 ↗ | Drug substance | U-594 | Mar 10, 2027 |
| US 7683051 ↗ | Drug substance | U-904 | Mar 10, 2027 |
Is there a generic version of this drug?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII PQ6CK8PD0R
Ascorbic acid, also known as vitamin C, is a white crystalline powder. It serves as an antioxidant to prevent degradation of other ingredients and may also function as a preservative in the formulation.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII R33S7TK2EP
Hydroxyethyl cellulose is a thickening agent made from processed plant cellulose. It's used in medicines to increase viscosity, improve texture, and help distribute active ingredients evenly throughout liquid or semi-solid formulations.
-
UNII RFW2ET671P
Hydroxypropyl cellulose is a plant-derived thickening agent made from cellulose. It acts as a binder to hold tablet ingredients together and as a film-former to coat tablets or control how fast the medicine releases.
-
UNII VM7F0B23ZI
Hypromellose 2208 is a plant-derived thickening agent that forms a protective coating on tablets and capsules. It slows down how quickly the medicine dissolves, controlling drug release into your body.
-
UNII ND2M416302
Isopropyl alcohol is a clear liquid solvent derived from petroleum. In medicines, it dissolves active ingredients and other components, helps the product flow smoothly, and aids in sterilization during manufacturing.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII D65DG142WK
Maltitol is a sugar alcohol made by hydrogenating maltose. It's used as a sweetener and filler in medicines to improve taste and add bulk to tablets and capsules.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII LQA7B6G8JG
A synthetic polymer made by combining water-soluble compounds. It acts as a surfactant and solubilizer to help mix oil and water-based ingredients, improving the medicine's texture and how active ingredients dissolve.
-
UNII VH2XOU12IE
Polydextrose is a synthetic polymer made from dextrose (sugar) that acts as a bulking agent and filler in medicines. It helps give tablets and capsules proper volume and texture while often adding slight sweetness.
-
UNII B697894SGQ
Polyethylene glycol 400 is a clear, thick liquid made from petroleum-derived polymers. It acts as a solvent and humectant in medicines, helping dissolve active ingredients and retain moisture in the formulation.
-
UNII FZ989GH94E
Povidone is a synthetic polymer made from a plastic-like material. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in your stomach so the medicine can be absorbed.
-
UNII SMD1X3XO9M
Powdered cellulose is a fine, plant-based powder made from purified wood fibers. In medicines, it acts as a filler to add bulk and volume, and helps tablets or capsules hold together during manufacturing and storage.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII C151H8M554
A natural sugar derived from sugar cane or sugar beets. It's used as a sweetener, filler, and binder to improve taste, add bulk, and help hold tablet or capsule ingredients together.
-
UNII 3OSQ643ZK5
Sucrose palmitate is a manufactured ingredient made by combining sugar with palmitic acid. It acts as an emulsifier and surfactant, helping oils and water mix together smoothly in liquid or semi-solid medicines.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII 91D9GV0Z28
A mineral salt made from calcium and phosphate. It acts as a filler to add bulk to the tablet or capsule, and helps bind ingredients together so the medicine holds its shape.
22 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 5, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from U.S. Pharmaceuticals labeler code 63539
- Talzenna talazoparib .5 mg Capsule, Liquid Filled NDC 63539-025-30
- Inlyta axitinib 1 mg Tablet, Film Coated NDC 63539-026-01
- XELJANZ tofacitinib 1 mg/mL Solution NDC 63539-029-02
- Talzenna talazoparib 1 mg Capsule, Liquid Filled NDC 63539-031-30
- Inlyta axitinib 5 mg Tablet, Film Coated NDC 63539-044-01
- Talzenna talazoparib .5 mg Capsule NDC 63539-051-30
- ZAVZPRET zavegepant 10 mg/.1mL Spray NDC 63539-135-02
- BOSULIF Bosutinib 400 mg Tablet, Film Coated NDC 63539-193-30
- Cibinqo abrocitinib 50 mg Tablet, Film Coated NDC 63539-236-14
- Elrexfio elranatamab-bcmm 44 mg/1.1mL Injection, Solution NDC 63539-252-02
- Ibrance palbociclib 75 mg Tablet, Film Coated NDC 63539-284-03
- Talzenna talazoparib 1 mg Capsule NDC 63539-295-30
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: ENDOMETRIAL CANCER, CARDIOVASCULAR DISORDERS, AND PROBABLE DEMENTIA • Women taking DUAVEE should not take additional estrogens [see Warnings and Precautions (5.1) ] • There is an increased risk of endometrial cancer in a woman with a uterus who uses unopposed estrogens. DUAVEE has been shown to reduce the risk of endometrial hyperplasia, which may be a precursor to endometrial cancer. Adequate diagnostic measures, including directed or random endometrial sampling when indicated, should be undertaken to rule out malignancy in postmenopausal women with undiagnosed persistent or recurring abnormal genital bleeding [see Warnings and Precautions (5.3) ] • Estrogen therapy should not be used for the prevention of cardiovascular disease or dementia [see Warnings and Precautions (5.2 , 5.4) ] • The Women's Health Initiative (WHI) estrogen-alone substudy reported increased risks of stroke and deep vein thrombosis (DVT) in postmenopausal women (50 to 79 years of age) during 7.1 years of treatment with daily oral conjugated estrogens (0.625 mg)-alone, relative to placebo [see Warnings and Precautions (5.2) ] • The WHI Memory Study (WHIMS) estrogen-alone ancillary study of WHI reported an increased risk of probable dementia in postmenopausal women 65 years of age and older during 5.2 years of treatment with daily conjugated estrogens (0.625 mg)-alone, relative to placebo.
It is unknown whether this finding applies to younger postmenopausal women [see Warnings and Precautions (5.4) ] Only daily oral 0.625 mg CE was studied in the estrogen-alone substudy of the WHI. Therefore, the relevance of the WHI findings regarding adverse cardiovascular events and dementia to lower CE doses, other routes of administration, or other estrogen-alone products is not known. Without such data, it is not possible to definitively exclude these risks or determine the extent of these risks for other products.
Discuss with your patient the benefits and risks of estrogen-alone therapy, taking into account her individual risk profile. Estrogens should be prescribed at the lowest effective doses and for the shortest duration consistent with treatment goals and risks for the individual woman. WARNING: ENDOMETRIAL CANCER, CARDIOVASCULAR DISORDERS, AND PROBABLE DEMENTIA See full prescribing information for complete Boxed Warning. • Women taking DUAVEE should not take additional estrogens ( 5.1 ) • There is an increased risk of endometrial cancer in a woman with a uterus who uses unopposed estrogens ( 5.1 , 5.3 ) • Estrogen therapy should not be used for the prevention of cardiovascular disease or dementia ( 5.2 , 5.4 ) • The Women's Health Initiative (WHI) estrogen-alone substudy reported increased risks of stroke and deep vein thrombosis (DVT) ( 5.2 ) • The WHI Memory Study (WHIMS) estrogen-alone ancillary study of WHI reported an increased risk of probable dementia in postmenopausal women 65 years of age and older ( 5.4 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE DUAVEE is indicated in women with a uterus for: DUAVEE is a combination of conjugated estrogens with an estrogen agonist/antagonist indicated for treatment of the following conditions in women with a uterus: • Treatment of moderate to severe vasomotor symptoms associated with menopause ( 1.1 ) • Prevention of postmenopausal osteoporosis ( 1.2 ) Limitation of Use : DUAVEE should be used for the shortest duration consistent with treatment goals and risks for the individual woman ( 1.3 )
1.1 Treatment of Moderate to Severe Vasomotor Symptoms Associated with Menopause
1.2 Prevention of Postmenopausal Osteoporosis
1.3Important Limitations of Use • Use DUAVEE for the shortest duration consistent with treatment goals and risks for the individual woman. Postmenopausal women should be re-evaluated periodically as clinically appropriate to determine if treatment is still necessary. • When prescribing solely for the prevention of postmenopausal osteoporosis, therapy should only be considered for women at significant risk of osteoporosis and non-estrogen medication should be carefully considered.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Take one tablet orally once daily ( 2 )
2.1Treatment of Moderate to Severe Vasomotor Symptoms Associated with Menopause The recommended dosage is one DUAVEE tablet daily.
2.2Prevention of Postmenopausal Osteoporosis The recommended dosage is one DUAVEE tablet daily.
2.3General Dosing Information Take DUAVEE once daily, without regard to meals. Tablets should be swallowed whole.
2.4Recommendations for Calcium and Vitamin D Supplementation Women taking DUAVEE for prevention of postmenopausal osteoporosis should add supplemental calcium and/or vitamin D to their diet if daily intake is inadequate.
2.5Administration Instructions for Missed Doses If a dose of DUAVEE is missed, instruct patients to take it as soon as remembered unless it is almost time for the next scheduled dose. They should not take two doses at the same time.
2.6Use in Patients with Renal Impairment The pharmacokinetics of DUAVEE have not been evaluated in patients with renal impairment. Use in patients with renal impairment is not recommended [see Use in Specific Populations (8.6) and Clinical Pharmacology (12.3) ] .
2.7Use in the Elderly DUAVEE has not been studied in women over 75 years of age. Use in women over 75 years of age is not recommended.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS DUAVEE (conjugated estrogens/bazedoxifene) tablets, 0.45 mg/20 mg are oval, biconvex, pink tablets, branded with "0.45/20" in black ink on one side. Tablet containing conjugated estrogens 0.45 mg and bazedoxifene 20 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS DUAVEE is contraindicated in women with any of the following conditions: • Undiagnosed abnormal uterine bleeding • Known, suspected, or past history of breast cancer • Known or suspected estrogen-dependent neoplasia • Active deep venous thrombosis, pulmonary embolism, or history of these conditions • Active arterial thromboembolic disease (for example, stroke, myocardial infarction) or history of these conditions • Hypersensitivity (for example, anaphylaxis, angioedema) to estrogens, bazedoxifene, or any ingredients • Known hepatic impairment or disease • Known protein C, protein S, or antithrombin deficiency or other known thrombophilic disorders • Pregnancy, as DUAVEE may cause fetal harm [see pregnancy (8.1) ] . • Undiagnosed abnormal uterine bleeding ( 4 , 5.3 ) • Known, suspected, or past history of breast cancer ( 4 , 5.3 ) • Known or suspected estrogen-dependent neoplasia ( 4 , 5.3 ) • Active or past history of venous thromboembolism ( 4 , 5.2 ) • Active or past history of arterial thromboembolism ( 4 , 5.2 ) • Hypersensitivity (angioedema, anaphylaxis) to estrogens, bazedoxifene, or any ingredients ( 4 ) • Known hepatic impairment or disease ( 4 , 5.9 , 8.7, 12.3 ) • Known protein C, protein S, or antithrombin deficiency or other known thrombophilic disorders ( 4 ) • Pregnancy ( 1 , 4 , 8.1 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Women taking DUAVEE should not take progestins, additional estrogens or additional estrogen agonist/antagonists ( 5.1 ) • Cardiovascular disorders, including venous thromboembolism, pulmonary embolism, stroke, and retinal vascular thrombosis ( 5.2 , 5.6 ) • Malignant neoplasms, including endometrial cancer, breast cancer, and ovarian cancer ( 5.3 ) • Estrogens increase the risk of gallbladder disease ( 5.5 ) • Discontinue estrogen if loss of vision, severe hypertriglyceridemia or cholestatic jaundice occurs ( 5.6 , 5.8 , 5.9 ) • Monitor thyroid function in women on thyroid replacement therapy ( 5.10 , 5.17 )
5.1Drugs Containing Progestins, Estrogens or Estrogen Agonist/Antagonists DUAVEE contains conjugated estrogens and bazedoxifene, an estrogen agonist/antagonist. Women taking DUAVEE should not take progestins, additional estrogens or additional estrogen agonist/antagonists.
5.2Cardiovascular Disorders Estrogen agonist/antagonists (including bazedoxifene, a component of DUAVEE) and estrogens individually are known to increase the risk of VTE. An increased risk of stroke and DVT has been reported with estrogen-alone therapy. Should any of these occur or be suspected, DUAVEE should be discontinued immediately.
Risk factors for arterial vascular disease (for example, hypertension, diabetes mellitus, tobacco use, hypercholesterolemia, and obesity) and/or VTE (for example, personal history or family history of VTE, obesity, and systemic lupus erythematosus) should be managed appropriately. Stroke In the WHI estrogen-alone substudy, a statistically significant increased risk of stroke was reported in women 50 to 79 years of age receiving daily conjugated estrogens (CE) (0.625 mg)-alone compared to women in the same age group receiving placebo (45 versus 33 per 10,000 women-years).
The increase in risk was demonstrated in year 1 and persisted [see Clinical Studies (14.5) ] . Subgroup analyses of women 50 to 59 years of age suggest no increased risk of stroke for those women receiving conjugated estrogens (0.625 mg)-alone versus those receiving placebo (18 versus 21 per 10,000 women-years). Should a stroke occur or be suspected, DUAVEE should be discontinued immediately [see Contraindications (4) ].
Coronary Heart Disease In the WHI estrogen-alone substudy, no overall effect on coronary heart disease (CHD) events (defined as nonfatal myocardial infarction, silent myocardial infarction, or CHD death) was reported in women receiving estrogen-alone compared to placebo [see Clinical Studies (14.5) ] . Subgroup analyses of women 50 to 59 years of age suggest a statistically non-significant reduction in CHD events (CE [0.625 mg]-alone compared to placebo) in women with less than 10 years since menopause (8 versus 16 per 10,000 women-years).
Venous Thromboembolism (VTE) In the WHI estrogen-alone substudy, the risk of VTE [DVT and pulmonary embolism (PE)] was increased for women receiving daily conjugated estrogens (0.625 mg)-alone compared to placebo (30 versus 22 per 10,000 women-years), although only the increased risk of DVT reached statistical significance (23 versus 15 per 10,000 women-years). The increase in VTE risk was demonstrated during the first 2 years [see Clinical Studies (14.5) ] . If feasible, DUAVEE should be discontinued at least 4 to 6 weeks before surgery of the type associated with an increased risk of thromboembolism, or during periods of prolonged immobilization.
Because immobilization increases the risk for venous thromboembolic events independent of therapy, DUAVEE should be discontinued prior to and during prolonged immobilization (e.g., post-surgical recovery, prolonged bed rest) and DUAVEE therapy should be resumed only after the patient is fully ambulatory. In addition, women taking DUAVEE should be advised to move about periodically during travel involving prolonged immobilization.
5.3Malignant Neoplasms Endometrial Cancer An increased risk of endometrial cancer has been reporte… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in greater detail in other sections of the label: • Cardiovascular Disorders [see Warnings and Precautions (5.2) ] • Malignant Neoplasms [see Warnings and Precautions (5.3) ] • Gallbladder Disease [see Warnings and Precautions (5.5) ] • Hypertriglyceridemia [see Warnings and Precautions (5.8) ] In four prospective, randomized, placebo-controlled trials the common adverse reactions (incidence ≥ 5%) were muscle spasms, nausea, diarrhea, dyspepsia, abdominal pain upper, oropharyngeal pain, dizziness, and neck pain ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Pfizer Inc. at 1-800-438-1985 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. The safety of conjugated estrogens/bazedoxifene was evaluated in four Phase 3 clinical trials ranging from 12 weeks to 24 months in duration and enrolling 6,210 postmenopausal women age 40 to 75 years (mean age 55 years).
A total of 1,224 patients were treated with DUAVEE and 1,069 patients received placebo. Women enrolled in Studies 1 and 2 received calcium (600–1200 mg) and vitamin D (200–400 IU) daily, while women in Studies 3 and 4 received no calcium and vitamin D supplementation as part of the protocol. The incidence of all-cause mortality was 0.0% in the DUAVEE group and 0.2% in the placebo group.
The incidence of serious adverse reactions was 3.5% in the DUAVEE group and 4.8% in the placebo group. The percentage of patients who withdrew from treatment due to adverse reactions was 7.5% in the DUAVEE group and 10.0% in the placebo group. The most common adverse reactions leading to discontinuation were hot flush, abdominal pain upper, and nausea.
The most commonly observed adverse reactions (incidence ≥ 5%) more frequently reported in women treated with DUAVEE than placebo are presented in Table 1. Table 1: Adverse Reactions (Incidence ≥ 5%) More Common in the DUAVEE Treatment Group in Placebo-controlled Trials DUAVEE (N=1224) n (%) Placebo (N=1069) n (%) Gastrointestinal disorders Nausea 100 (8) 58 (5) Diarrhea 96 (8) 57 (5) Dyspepsia 84 (7) 59 (6) Abdominal pain upper 81 (7) 58 (5) Musculoskeletal and connective tissue disorders Muscle spasms 110 (9) 63 (6) Neck pain 62 (5) 46 (4) Nervous system disorders Dizziness 65 (5) 37 (3) Respiratory, thoracic, and mediastinal disorders Oropharyngeal pain 80 (7) 61 (6) Venous thromboembolism : In the clinical studies with DUAVEE, the reporting rates for venous thromboembolism (deep venous thrombosis, pulmonary embolism, and retinal vein thrombosis) were low in all treatment groups.
Adverse reactions of venous thromboembolism were reported in 0.0% of patients treated with DUAVEE and 0.1% of patients treated with placebo. Due to the low rate of events in both groups, it is not possible to conclude that the risk of venous thromboembolism with DUAVEE is different from that seen with other estrogen therapies [see Warnings and Precautions (5.2) ] .
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS
7.1Cytochrome P450 (CYP) In vitro and in vivo studies have shown that estrogens are metabolized partially by cytochrome P450 3A4 (CYP3A4). Concomitant administration of itraconazole, a strong CYP3A4 inhibitor, with DUAVEE, resulted in increases in bazedoxifene exposure (40%) and, to a lesser extent, conjugated estrogens exposure (9% for baseline-adjusted total estrone, 5% for total equilin), compared to DUAVEE alone [see Pharmacokinetics (12.3) ] . Inducers of CYP3A4, such as St.
John's Wort (Hypericum perforatum) preparations, phenobarbital, carbamazepine, and rifampin, may reduce plasma concentrations of some estrogens, possibly resulting in a decrease in therapeutic effects and/or changes in the uterine bleeding profile. Bazedoxifene does not induce or inhibit the activities of major CYP isoenzymes. In vitro data suggest that bazedoxifene is unlikely to interact with co-administered drugs via CYP-mediated metabolism.
7.2Uridine Diphosphate Glucuronosyltransferase (UGT) Bazedoxifene undergoes metabolism by UGT enzymes in the intestinal tract and liver. The metabolism of bazedoxifene may be increased by concomitant use of substances known to induce UGTs, such as rifampin, phenobarbital, carbamazepine, and phenytoin. A reduction in bazedoxifene exposure may be associated with an increase risk of endometrial hyperplasia.
Adequate diagnostic measures, including directed or random endometrial sampling when indicated, should be undertaken to rule out malignancy in postmenopausal women with undiagnosed persistent or recurring abnormal genital bleeding.
7.3Atorvastatin Concomitant administration of bazedoxifene (40 mg daily) and atorvastatin (20 mg, single-dose) to healthy postmenopausal women did not affect the pharmacokinetics of bazedoxifene, atorvastatin or its active metabolites.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Geriatric Use: DUAVEE was not studied in women aged 75 or older ( 8.5 , 12.3 ); use in this population is not recommended ( 2.7 , 8.5 ) • An increased risk of probable dementia in women over 65 years of age was reported in the Women's Health Initiative Memory ancillary studies of the Women's Health Initiative ( 5.4 , 8.5 , 14.6 ) • Renal Impairment: DUAVEE was not studied in women with renal impairment; use in this population is not recommended ( 2.6 , 8.6 , 12.3 )
8.1Pregnancy Risk Summary DUAVEE is contraindicated for use in pregnant women and is not indicated for use in females of reproductive potential [see Contraindications (4) , Warnings and Precautions (5.15) ]. Conjugated Estrogens (CE) There are no data with the use of conjugated estrogens in pregnant women; however, epidemiologic studies and meta-analyses have not found an increased risk of genital and non-genital birth defects (including cardiac anomalies and limb-reduction defects) following exposure to combined hormonal contraceptives before conception or during early pregnancy.
Bazedoxifene There are no available data on bazedoxifene use in pregnant women to inform a drug associated risk of adverse developmental outcomes. Animal studies have shown that oral bazedoxifene administered during the period of organogenesis to pregnant rats or rabbits at 0.3 and 2 times, respectively, the exposure at the maximum recommended dose, can cause fetal harm [see Data ]. Based on mechanism of action, bazedoxifene may block the important functions that estrogen has during all stages of pregnancy [see Clinical Pharmacology (12.1) ] .
Data Animal data Bazedoxifene Administration of bazedoxifene to rats at maternally toxic dosages ≥1 mg/kg/day (≥ 0.3 times the human area under the curve (AUC) at the 20 mg dose) resulted in reduced numbers of live fetuses and/or reductions in fetal body weights. No fetal developmental anomalies were observed. In studies conducted with pregnant rabbits treated with bazedoxifene, abortion and an increased incidence of heart (ventricular septal defect) and skeletal system (ossification delays, misshapen or misaligned bones, primarily of the spine and skull) anomalies in the fetuses were present at maternally toxic dosages of ≥ 0.5 mg/kg/day (≥ 2 times the human AUC at the 20 mg dose).
8.2Lactation Risk Summary DUAVEE is not indicated for use in females of reproductive potential [see Warnings and Precautions (5.15) ] . Conjugated Estrogens Estrogens are present in human milk and can reduce milk production in breast-feeding females. This reduction can occur at any time but is less likely to occur once breast-feeding is well-established.
Bazedoxifene There are no data on the presence of bazedoxifene in either human or animal breast milk, the effect on the breastfed infant, or the effects on milk production. Based on mechanism of action, bazedoxifene may block the important functions that estrogen has in mammary tissue during lactation [see Clinical Pharmacology (12.1) ].
8.3Females and Males of Reproductive Potential Infertility Bazedoxifene Based on animal data, bazedoxifene administration may adversely affect female fertility. However, clinical fertility studies with bazedoxifene have not been conducted [see Nonclinical Toxicology (13.1) ] .
8.4Pediatric Use DUAVEE is not indicated for use in children [see Indications and Usage (1) ] .
8.5Geriatric Use DUAVEE is not recommended for use in women greater than 75 years of age [see Dosage and Administration (2.7) and Clinical Pharmacology 12.3) ] . Of the total number of women in phase 3 clinical studies who received DUAVEE, 4.60% (n=224) were 65 years and over. DUAVEE was not studied in women aged 75 and over.
No overall differences in safety or effectiveness were observed between women 65–74 years of age and younger women, and other reported clinical experience has not identified differences in responses between the elderly and younger women, but greater sensitivity of… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary DUAVEE is contraindicated for use in pregnant women and is not indicated for use in females of reproductive potential [see Contraindications (4) , Warnings and Precautions (5.15) ]. Conjugated Estrogens (CE) There are no data with the use of conjugated estrogens in pregnant women; however, epidemiologic studies and meta-analyses have not found an increased risk of genital and non-genital birth defects (including cardiac anomalies and limb-reduction defects) following exposure to combined hormonal contraceptives before conception or during early pregnancy.
Bazedoxifene There are no available data on bazedoxifene use in pregnant women to inform a drug associated risk of adverse developmental outcomes. Animal studies have shown that oral bazedoxifene administered during the period of organogenesis to pregnant rats or rabbits at 0.3 and 2 times, respectively, the exposure at the maximum recommended dose, can cause fetal harm [see Data ]. Based on mechanism of action, bazedoxifene may block the important functions that estrogen has during all stages of pregnancy [see Clinical Pharmacology (12.1) ] .
Data Animal data Bazedoxifene Administration of bazedoxifene to rats at maternally toxic dosages ≥1 mg/kg/day (≥ 0.3 times the human area under the curve (AUC) at the 20 mg dose) resulted in reduced numbers of live fetuses and/or reductions in fetal body weights. No fetal developmental anomalies were observed. In studies conducted with pregnant rabbits treated with bazedoxifene, abortion and an increased incidence of heart (ventricular septal defect) and skeletal system (ossification delays, misshapen or misaligned bones, primarily of the spine and skull) anomalies in the fetuses were present at maternally toxic dosages of ≥ 0.5 mg/kg/day (≥ 2 times the human AUC at the 20 mg dose).
🧒 Pediatric Use ▾
8.4Pediatric Use DUAVEE is not indicated for use in children [see Indications and Usage (1) ] .
🧓 Geriatric Use ▾
8.5Geriatric Use DUAVEE is not recommended for use in women greater than 75 years of age [see Dosage and Administration (2.7) and Clinical Pharmacology 12.3) ] . Of the total number of women in phase 3 clinical studies who received DUAVEE, 4.60% (n=224) were 65 years and over. DUAVEE was not studied in women aged 75 and over.
No overall differences in safety or effectiveness were observed between women 65–74 years of age and younger women, and other reported clinical experience has not identified differences in responses between the elderly and younger women, but greater sensitivity of some older women cannot be ruled out. An increased risk of probable dementia in women over 65 years of age was reported in the Women's Health Initiative Memory ancillary studies of the Women's Health Initiative using daily conjugated estrogens (0.625 mg) [see Clinical Studies (14.6) ].
🆘 Overdosage ▾
10 OVERDOSAGE In case of overdosage, there is no specific antidote, and the treatment should be symptomatic. Symptoms of overdosage of estrogen-containing products in adults and children may include nausea, vomiting, breast tenderness, dizziness, abdominal pain, drowsiness/fatigue; withdrawal bleeding may occur.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action DUAVEE pairs conjugated estrogens with bazedoxifene. Conjugated estrogens and bazedoxifene function by binding to and activating estrogen receptors (ER) α and β, which vary in proportion from tissue to tissue. Conjugated estrogens are composed of multiple estrogens and are agonists of ER- α and β.
Bazedoxifene is an estrogen agonist/antagonist that acts as an agonist in some estrogen-sensitive tissues and an antagonist in others (e.g., uterus). The pairing of conjugated estrogens with bazedoxifene produces a composite effect that is specific to each target tissue. The bazedoxifene component reduces the risk of endometrial hyperplasia that can occur with the conjugated estrogens component.
12.2Pharmacodynamics Generally, a serum estrogen concentration does not predict an individual woman’s therapeutic response to DUAVEE nor her risk for adverse outcomes. Likewise, exposure comparisons across different estrogen products to infer efficacy or safety for the individual woman may not be valid.
12.3Pharmacokinetics Absorption Following administration of multiple doses of conjugated estrogens 0.45 mg/bazedoxifene 20 mg to healthy women who were naturally postmenopausal or who had undergone bilateral oophorectomy, the mean steady state pharmacokinetic parameters at Day 10 for conjugated estrogens (baseline adjusted for total estrone) and bazedoxifene are summarized in Table 2. Table 2: Mean ± SD Steady-State Pharmacokinetic Parameters (n=24) C max (ng/mL) T max (hr) AUCss (ng∙hr/mL) Baseline-Adjusted Total Estrone 2.6 ± 0.8 6.5 ± 1.6 35 ± 12 Bazedoxifene 6.9 ± 3.9 2.5 ± 2.1 71 ± 34 Results from monotherapy studies with conjugated estrogens or bazedoxifene components of DUAVEE, are noted below: Conjugated estrogens are soluble in water and are well-absorbed from the gastrointestinal tract after release from the drug formulation.
Bazedoxifene exhibits a linear increase in plasma concentrations for single doses from 0.5 mg up to 120 mg and multiple daily doses from 1 mg to 80 mg. The absolute bioavailability of bazedoxifene is approximately 6%. Food Effect In a single-dose, crossover study in 23 postmenopausal women given conjugated estrogens 0.625 mg/bazedoxifene 20 mg with a high fat/high calorie meal, food increased AUC 0–inf of bazedoxifene by 25%.
The C max of bazedoxifene was unchanged. Distribution The distribution of conjugated estrogens and bazedoxifene after administration of DUAVEE has not been studied. Results from monotherapy studies with conjugated estrogens or bazedoxifene, components of DUAVEE, are noted below: The distribution of exogenous estrogens is similar to that of endogenous estrogens.
Estrogens are widely distributed in the body and are generally found in higher concentrations in the sex hormone target organs. Estrogens circulate in the blood largely bound to sex hormone binding globulin (SHBG) and albumin. Following intravenous (IV) administration of a 3 mg dose of bazedoxifene, the volume of distribution is 14.7 ±
3.9L/kg. Bazedoxifene is highly bound (98%–99%) to plasma proteins in vitro, but does not bind to SHBG. Metabolism The metabolic disposition of conjugated estrogens and bazedoxifene, after administration of DUAVEE, has not been studied.
Results from monotherapy studies with conjugated estrogens or bazedoxifene, components of DUAVEE, are noted below: Exogenous estrogens are metabolized in the same manner as endogenous estrogens. Circulating estrogens exist in a dynamic equilibrium of metabolic interconversions. 17-β estradiol is converted reversibly to estrone, and both can be converted to estriol, which is the major urinary metabolite.
In postmenopausal women, a significant proportion of the circulating estrogens exists as sulfate conjugates, especially estrone sulfate, which serves as a circulating reservoir for the formation of more active estrogens. The metabolic disposition of bazedoxifene has been determined following oral administration of 20 m… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action DUAVEE pairs conjugated estrogens with bazedoxifene. Conjugated estrogens and bazedoxifene function by binding to and activating estrogen receptors (ER) α and β, which vary in proportion from tissue to tissue. Conjugated estrogens are composed of multiple estrogens and are agonists of ER- α and β.
Bazedoxifene is an estrogen agonist/antagonist that acts as an agonist in some estrogen-sensitive tissues and an antagonist in others (e.g., uterus). The pairing of conjugated estrogens with bazedoxifene produces a composite effect that is specific to each target tissue. The bazedoxifene component reduces the risk of endometrial hyperplasia that can occur with the conjugated estrogens component.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING DUAVEE tablets contain 0.45 mg conjugated estrogens and 20 mg bazedoxifene. The tablets are oval, biconvex, and pink, branded with "0.45/20" in black ink on one side. DUAVEE ® tablets are supplied as follows: Package NDC number Conjugated estrogens 0.45 mg/bazedoxifene 20 mg 2 blisters of 15 tablets each NDC 0008-1123-12 Storage Blisters DUAVEE tablets should be stored at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F).
See USP Controlled Room Temperature. Dispense product in the original package. Tablets should not be removed from blisters until immediately before use.
Protect from moisture. After opening foil pouch, product must be used within 60 days.
📦 Storage and Handling ▾
Storage Blisters DUAVEE tablets should be stored at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F). See USP Controlled Room Temperature. Dispense product in the original package. Tablets should not be removed from blisters until immediately before use. Protect from moisture. After opening foil pouch, product must be used within 60 days.
📋 Description ▾
11 DESCRIPTION DUAVEE (conjugated estrogens/bazedoxifene), contains conjugated estrogens with bazedoxifene, an estrogen agonist/antagonist. Conjugated estrogens are purified from pregnant mares' urine and consist of the sodium salts of water-soluble estrogen sulfates blended to represent the average composition of material derived from pregnant mares' urine. Conjugated estrogens are a mixture of sodium estrone sulfate and sodium equilin sulfate, and also contain as concomitant components, sodium sulfate conjugates, 17α-dihydroequilin, 17α-estradiol, and 17β-dihydroequilin.
Bazedoxifene is supplied as the acetate salt (bazedoxifene acetate) and has the chemical name 1 H -Indol-5-ol, 1-[[4-[2-(hexahydro-1 H -azepin-1-yl) ethoxy]phenyl]methyl]-2-(4-hydroxyphenyl)-3-methyl-, monoacetate. The empirical formula is C 30 H 34 N 2 O 3 ∙ C 2 H 4 O 2, and the molecular weight is 530.65. Bazedoxifene acetate is a white to tan powder.
The aqueous solubility of bazedoxifene is pH-dependent. Solubility is higher at lower pH. The solubility of bazedoxifene acetate in unbuffered sterile water was measured to be 923 microgramsA/mL at pH 5.4.
The following represents the chemical structure of bazedoxifene acetate: DUAVEE is available for oral administration as tablets containing 0.45 mg of conjugated estrogens with 20 mg of bazedoxifene (equivalent to 22.6 mg of bazedoxifene acetate). Each tablet of DUAVEE contains the following inactive ingredients: calcium phosphate tribasic, hydroxypropyl cellulose, microcrystalline cellulose, powdered cellulose, hypromellose, lactose monohydrate, magnesium stearate, polyethylene glycol, sucrose, ascorbic acid, sucrose palmitic acid ester, hydroxyethylcellulose, titanium dioxide, red iron oxide, yellow iron oxide, black iron oxide, povidone, polydextrose, maltitol, poloxamer 188, propylene glycol, and isopropyl alcohol.
Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information) .
17.1Instructions for Patients • Keep DUAVEE in the original container to protect from moisture. Do not place DUAVEE in pill boxes or pill organizers. • If more than one blister package is dispensed to the patient, instruct them to open one foil pouch at a time. • Instruct patient to record the date the blister package is opened in the space provided on the blister package label. Do not use if the blister package has been open more than 60 days. • Instruct patient to remove only one tablet from the blister package at the time of use.
17.2Venous Thromboembolic Events Advise patients to immediately report to their physician any signs or symptoms related to venous thrombosis and thromboembolic events [see Warnings and Precautions (5.2) ] .
17.3Abnormal Vaginal Bleeding Inform postmenopausal women of the importance of reporting abnormal vaginal bleeding to their healthcare provider as soon as possible [see Warnings and Precautions (5.3) ].
17.4Possible Serious Adverse Reactions with Estrogen Therapy Inform postmenopausal women of possible serious adverse reactions of estrogen therapy including Cardiovascular Disorders, Malignant Neoplasms, and Probable Dementia [see Warnings and Precautions (5.2 , 5.3 , 5.4) ] .
17.5Possible Less Serious Adverse Reactions with DUAVEE Inform postmenopausal women of possible less serious but common adverse reactions of DUAVEE therapy such as muscle spasms, nausea, diarrhea, dyspepsia, upper abdominal pain, throat pain, dizziness and neck pain.
17.6Calcium and Vitamin D Intake Advise patients to add supplemental calcium and/or vitamin D to the diet if daily intake is inadequate.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption Following administration of multiple doses of conjugated estrogens 0.45 mg/bazedoxifene 20 mg to healthy women who were naturally postmenopausal or who had undergone bilateral oophorectomy, the mean steady state pharmacokinetic parameters at Day 10 for conjugated estrogens (baseline adjusted for total estrone) and bazedoxifene are summarized in Table 2. Table 2: Mean ± SD Steady-State Pharmacokinetic Parameters (n=24) C max (ng/mL) T max (hr) AUCss (ng∙hr/mL) Baseline-Adjusted Total Estrone 2.6 ± 0.8 6.5 ± 1.6 35 ± 12 Bazedoxifene 6.9 ± 3.9 2.5 ± 2.1 71 ± 34 Results from monotherapy studies with conjugated estrogens or bazedoxifene components of DUAVEE, are noted below: Conjugated estrogens are soluble in water and are well-absorbed from the gastrointestinal tract after release from the drug formulation.
Bazedoxifene exhibits a linear increase in plasma concentrations for single doses from 0.5 mg up to 120 mg and multiple daily doses from 1 mg to 80 mg. The absolute bioavailability of bazedoxifene is approximately 6%. Food Effect In a single-dose, crossover study in 23 postmenopausal women given conjugated estrogens 0.625 mg/bazedoxifene 20 mg with a high fat/high calorie meal, food increased AUC 0–inf of bazedoxifene by 25%.
The C max of bazedoxifene was unchanged. Distribution The distribution of conjugated estrogens and bazedoxifene after administration of DUAVEE has not been studied. Results from monotherapy studies with conjugated estrogens or bazedoxifene, components of DUAVEE, are noted below: The distribution of exogenous estrogens is similar to that of endogenous estrogens.
Estrogens are widely distributed in the body and are generally found in higher concentrations in the sex hormone target organs. Estrogens circulate in the blood largely bound to sex hormone binding globulin (SHBG) and albumin. Following intravenous (IV) administration of a 3 mg dose of bazedoxifene, the volume of distribution is 14.7 ±
3.9L/kg. Bazedoxifene is highly bound (98%–99%) to plasma proteins in vitro, but does not bind to SHBG. Metabolism The metabolic disposition of conjugated estrogens and bazedoxifene, after administration of DUAVEE, has not been studied.
Results from monotherapy studies with conjugated estrogens or bazedoxifene, components of DUAVEE, are noted below: Exogenous estrogens are metabolized in the same manner as endogenous estrogens. Circulating estrogens exist in a dynamic equilibrium of metabolic interconversions. 17-β estradiol is converted reversibly to estrone, and both can be converted to estriol, which is the major urinary metabolite.
In postmenopausal women, a significant proportion of the circulating estrogens exists as sulfate conjugates, especially estrone sulfate, which serves as a circulating reservoir for the formation of more active estrogens. The metabolic disposition of bazedoxifene has been determined following oral administration of 20 mg of radiolabeled bazedoxifene. Bazedoxifene is extensively metabolized in women.
Glucuronidation is the major metabolic pathway. Little or no cytochrome P450-mediated metabolism is evident. Bazedoxifene-5-glucuronide is the major circulating metabolite.
The concentrations of this glucuronide are approximately 10-fold higher than those of unchanged drug in plasma. Excretion After administration of a single dose of conjugated estrogens/bazedoxifene, baseline-adjusted total estrone (representing conjugated estrogens) is eliminated with a half-life of approximately 17 hours. Bazedoxifene is eliminated with a half-life of approximately 30 hours.
Steady-state concentrations are achieved by the second week of once-daily administration. Results from monotherapy studies with conjugated estrogens or bazedoxifene, components of DUAVEE, are noted below: The conjugated estrogens components, 17β-estradiol, estrone, and estriol are excreted in the urine, along with glucuronide and sulfate conjugates. The clearance of bazedoxifene is 0.4 ±
0.1L/h/kg ba… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Generally, a serum estrogen concentration does not predict an individual woman’s therapeutic response to DUAVEE nor her risk for adverse outcomes. Likewise, exposure comparisons across different estrogen products to infer efficacy or safety for the individual woman may not be valid.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Treatment of Moderate to Severe Vasomotor Symptoms Associated with Menopause in Women with a Uterus The safety and efficacy of DUAVEE as a treatment for moderate to severe vasomotor symptoms associated with menopause was established in a 12-week randomized, double-blind, placebo-controlled study (Study 3). Study 3 enrolled a total of 318 women, age 42–64 (mean age of 53 years), who had at least 7 moderate to severe hot flushes per day or at least 50 per week at baseline. The mean number of years since menopause was 4.5 years with all women undergoing natural menopause.
A total of 127 women were assigned to DUAVEE and 63 women were assigned to placebo. In Study 3, DUAVEE significantly reduced the number and severity of moderate to severe hot flushes, as measured by the daily severity score, compared with placebo at Weeks 4 and 12. The change from baseline in the number and severity of moderate to severe hot flushes observed and the difference from placebo in Study 3 are shown in Table 3.
Table 3: Adjusted Mean Change from Baseline in the Average Daily Frequency and Severity of Hot Flushes (Study 3) Frequency Severity DUAVEE Placebo DUAVEE Placebo N 122 63 122 63 Baseline 10.3 10.5 2.3
2.3Week 4 Mean Change Change from baseline using ANCOVA model -5.9 -2.8 -0.6 -0.1 Treatment Difference Based on raw data analysis using ANCOVA model: Difference= Treatment + Baseline + Site -3.1 (-4.4, -1.7) p<0.001 -- -0.5 (-0.7, -0.3) -- Week 12 Mean Change -7.6 -4.9 -0.9 -0.3 Treatment Difference -2.7 (-3.8, -1.6) -- -0.6 (-0.9, -0.4) --
14.2Prevention of Postmenopausal Osteoporosis in Women with a Uterus The safety and efficacy of DUAVEE for the prevention of postmenopausal osteoporosis was demonstrated in Study 1 and Study 2. Study 1 was a 24-month, double-blind, randomized, placebo- and active-controlled study evaluating the safety and efficacy of multiple combinations of conjugated estrogen/bazedoxifene (including conjugated estrogens 0.45 mg/bazedoxifene 20 mg) compared to placebo. The primary endpoint of the study was the incidence of endometrial hyperplasia at Year 1.
Bone mineral density change at the lumbar spine at Year 2 was the key secondary endpoint, assessed in two subsets of patients (Substudy I and Substudy II). Patients enrolled into Substudy I had to be more than 5 years postmenopausal, have a lumbar spine or total hip T-score of -1 to -2.5, and have at least one additional risk factor for osteoporosis (e.g., Caucasian race, family history of osteoporosis, early menopause, thin/small frame, inactive lifestyle, tobacco abuse). Those enrolled into Substudy II had to be 1–5 years postmenopausal with at least one additional risk factor for osteoporosis.
A total of 3,397 women age 40–75 (mean age of 56 years) were enrolled in the overall study. Substudy I enrolled a total of 1,454 women (182 women receiving DUAVEE) with mean baseline T-scores of -1.43 and -1.52 in the DUAVEE and placebo groups, respectively. Substudy II enrolled a total of 861 women (with 111 women receiving DUAVEE) with mean baseline T-scores of -0.81 and -0.94 in the DUAVEE and placebo groups, respectively.
Women also took calcium (600–1200 mg) and vitamin D (200–400 IU) daily. In these substudies, treatment with DUAVEE significantly increased lumbar spine bone mineral density (BMD) at 24 months compared to placebo in both groups of postmenopausal women (Table 4). Table 4: Lumbar Spine Bone Mineral Density Results at 24 Months (Study 1) DUAVEE Placebo ** Adjusted mean changes, confidence intervals, and p-values based on an ANCOVA model with treatment and region (U.S. or non-U.S.) as factors and baseline BMD value and years since menopause as covariates using the Modified Intention to Treat population with Last Observation Carried Forward.
Study 1 excludes those subjects with missing source documentation. Between 1 and 5 Years Postmenopausal N 95 95 % Mean Change 1.72 -1.90 Difference from Placebo (95% C.I.) 3.62 (2.64, 4.60) p-value < 0… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Carcinogenicity studies with conjugated estrogens/bazedoxifene have not been conducted. Long-term continuous administration of natural and synthetic estrogens in certain animal species increases the frequency of carcinomas of the breast, uterus, cervix, vagina, testis, and liver. In 6-month oral gavage carcinogenicity studies of bazedoxifene in transgenic Tg.RasH2 mice, there was a drug-related increased incidence of benign, ovarian granulosa-cell tumors in female mice given 150 or 500 mg/kg/day.
In a two-year dietary carcinogenicity study of bazedoxifene in rats (administered at 0.003%, 0.01%, 0.03%, or 0.1%) a drug-related marked increased incidence of benign, ovarian granulosa-cell tumors was observed in female rats at concentrations of 0.03% and 0.1%. Systemic exposure (AUC) of bazedoxifene in these groups was 3 and 8 times that observed in postmenopausal women administered 20 mg/day. In male rats, drug-related renal tumors (adenomas and carcinomas), in the presence of renal toxicity, were observed at all doses tested, which corresponded to exposure ratios of 0.06 to 5 times the clinical AUC at a dose of 20 mg.
Mutagenesis Mutagenicity studies with conjugated estrogens/bazedoxifene have not been conducted. Bazedoxifene was not genotoxic or mutagenic in a battery of tests, including in vitro bacterial reverse mutation assay, in vitro mammalian cell forward mutation assay at the thymidine kinase (TK+/-) locus in L5178Y mouse lymphoma cells, in vitro chromosome aberration assay in Chinese hamster ovary (CHO) cells, and in vivo mouse micronucleus assay. Impairment of Fertility Impairment of fertility studies with conjugated estrogens/bazedoxifene have not been conducted.
Female rats were administered daily dosages of 0.3 to 30 mg/kg bazedoxifene (0.03 to 10 times human AUC at the 20 mg dose) prior to and during mating with untreated males. Estrous cycles and fertility were adversely affected in all bazedoxifene-treated female groups.
13.2Animal Toxicology and/or Pharmacology In a 12-month study in ovariectomized rats, co-administration of conjugated estrogens (2.5 mg/kg/day) and bazedoxifene (0.1, 0.3, or 1 mg/kg/day) prevented the loss of bone mass at the spine, femur, and tibia with concomitant maintenance of biomechanical strength parameters.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Carcinogenicity studies with conjugated estrogens/bazedoxifene have not been conducted. Long-term continuous administration of natural and synthetic estrogens in certain animal species increases the frequency of carcinomas of the breast, uterus, cervix, vagina, testis, and liver. In 6-month oral gavage carcinogenicity studies of bazedoxifene in transgenic Tg.RasH2 mice, there was a drug-related increased incidence of benign, ovarian granulosa-cell tumors in female mice given 150 or 500 mg/kg/day.
In a two-year dietary carcinogenicity study of bazedoxifene in rats (administered at 0.003%, 0.01%, 0.03%, or 0.1%) a drug-related marked increased incidence of benign, ovarian granulosa-cell tumors was observed in female rats at concentrations of 0.03% and 0.1%. Systemic exposure (AUC) of bazedoxifene in these groups was 3 and 8 times that observed in postmenopausal women administered 20 mg/day. In male rats, drug-related renal tumors (adenomas and carcinomas), in the presence of renal toxicity, were observed at all doses tested, which corresponded to exposure ratios of 0.06 to 5 times the clinical AUC at a dose of 20 mg.
Mutagenesis Mutagenicity studies with conjugated estrogens/bazedoxifene have not been conducted. Bazedoxifene was not genotoxic or mutagenic in a battery of tests, including in vitro bacterial reverse mutation assay, in vitro mammalian cell forward mutation assay at the thymidine kinase (TK+/-) locus in L5178Y mouse lymphoma cells, in vitro chromosome aberration assay in Chinese hamster ovary (CHO) cells, and in vivo mouse micronucleus assay. Impairment of Fertility Impairment of fertility studies with conjugated estrogens/bazedoxifene have not been conducted.
Female rats were administered daily dosages of 0.3 to 30 mg/kg bazedoxifene (0.03 to 10 times human AUC at the 20 mg dose) prior to and during mating with untreated males. Estrous cycles and fertility were adversely affected in all bazedoxifene-treated female groups.
📄 Patient Package Insert ▾
Patient Information DUAVEE ® (DEW' ah-vee) (conjugated estrogens/bazedoxifene) Tablets Read this Patient Information before you start taking DUAVEE and each time you get a refill. There may be new information. This information does not take the place of talking to your healthcare provider about your medical condition or your treatment.
What is the most important information I should know about DUAVEE? • Do not take additional estrogen products while you are taking DUAVEE. • Using estrogen-alone may increase your chance of getting cancer of the uterus (womb). • Report any unusual vaginal bleeding right away while you are taking DUAVEE. Vaginal bleeding after menopause may be a warning sign of cancer of the uterus (womb). Your healthcare provider should check any unusual vaginal bleeding to find out the cause. • Do not use estrogens to prevent heart disease, heart attacks, strokes or dementia (decline in brain function). • Using estrogen-alone may increase your chances of getting strokes or blood clots. • Using estrogen-alone may increase your chances of getting dementia, based on a study of women 65 years of age or older. • The risks listed above are based on a study of an estrogen-alone oral product.
Since other products and doses have not been studied in the same way, it is not known how the use of DUAVEE will affect your chances of getting these conditions. You and your healthcare provider should talk regularly about whether you still need treatment with DUAVEE. What is DUAVEE?
DUAVEE is a prescription medicine that contains a mixture of estrogens and bazedoxifene. What is DUAVEE used for? DUAVEE is used after menopause for women with a uterus to: • reduce moderate to severe hot flushes Estrogens are hormones made by a woman's ovaries.
The ovaries normally stop making estrogens when a woman is between 45 and 55 years old. This drop in body estrogen levels causes the "change of life" or menopause (the end of monthly menstrual periods). Sometimes both ovaries are removed during an operation before natural menopause takes place.
The sudden drop in estrogen levels causes "surgical menopause." When the estrogen levels begin dropping, some women get very uncomfortable symptoms, such as feelings of warmth in the face, neck, and chest, or sudden intense episodes of heat and sweating ("hot flashes" or "hot flushes"). In some women, the symptoms are mild, and they will not need to take medicines. In other women, symptoms can be more severe. • help reduce your chances of developing osteoporosis (thin, weak bones) If you use DUAVEE only to prevent osteoporosis due to menopause, talk with your healthcare provider about whether a different treatment or medicine without estrogens might be better for you.
DUAVEE should be taken for the shortest time possible and only for as long as treatment is needed. You and your healthcare provider should talk regularly about whether you still need treatment with DUAVEE. DUAVEE is not for use in children.
It is not known if DUAVEE is safe and effective in people with kidney problems. Who should not take DUAVEE? Do not take DUAVEE if you: • currently have or have had blood clots • are allergic to estrogens or bazedoxifene, the active ingredients in DUAVEE, or any of its ingredients.
See the list of ingredients in DUAVEE at the end of this leaflet. • have unusual vaginal bleeding. Vaginal bleeding after menopause may be a warning sign of cancer of the uterus (womb). Your healthcare provider should check any unusual vaginal bleeding to find out the cause. • currently have or have had certain cancers.
Estrogens may increase the chances of getting certain types of cancers, including cancer of the breast or uterus. If you have or have had cancer, talk with your healthcare provider about whether you should use DUAVEE. • currently have or have had liver problems • have been diagnosed with a bleeding disorder • are pregnant. DUAVEE is not for pregnant women.
If you think you may be pregnant, you should have a pre… [Excerpted — this section continues on DailyMed.]
📄 Recent Major Changes ▾
Warnings and Precautions, Malignant Neoplasms ( 5.3 ) 03/2024
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 7 Tablet Blister Card PROFESSIONAL SAMPLE - NOT FOR SALE NDC 63539-122-07 Pfizer Duavee™ (conjugated estrogens/ bazedoxifene) tablets per tablet 0.45 mg/20 mg* *Each tablet contains bazedoxifene equivalent to 22.6 mg of bazedoxifene acetate 7 tablets After opening foil pouch, product must be used within 60 days. Date foil pouch opened: Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature]. DOSAGE AND USE: See accompanying prescribing information.
Store product in original package to keep from moisture. Tablets should not be removed from blisters until immediately before administration. Do not place medication in pill boxes.
Distributed by U.S. Pharmaceuticals Pfizer Inc, NY, NY 10017 MADE IN IRELAND Rx only PAA042983 LOT: EXP: PRINCIPAL DISPLAY PANEL - 15 Tablet Blister Card
PRINCIPAL DISPLAY PANEL - 7 Tablet Blister Pouch PROFESSIONAL SAMPLE - NOT FOR SALE NDC 63539-122-07 Pfizer Duavee ™ (conjugated estrogens/ bazedoxifene) tablets 0.45 mg/20 mg* After opening foil pouch, product must be used within 60 days. Dispense and store product in original package to protect from moisture. 7 tablets Rx only Package includes 1 blister card containing 7 tablets. PRINCIPAL DISPLAY PANEL - 7 Tablet Blister Pouch
PRINCIPAL DISPLAY PANEL - 7 Tablet Carton PROFESSIONAL SAMPLE - NOT FOR SALE NDC 63539-122-07 Pfizer Duavee ™ 0.45 mg/20 mg* (conjugated estrogens/ bazedoxifene) tablets After opening foil pouch, product must be used within 60 days. Dispense and store product in original package to protect from moisture. Rx only 7 tablets Package includes 1 blister card containing 7 tablets. PRINCIPAL DISPLAY PANEL - 7 Tablet Carton
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |