
Amlodipine, Valsartan, Hydrochlorothiazide 10 mg; 25 mg; 160 mg Tablet, Film Coated, 30-count — NDC 64380-200-01 (Billing 64380-0200-01)
This is a package of 30 tablets of Amlodipine, Valsartan, Hydrochlorothiazide 10 mg; 25 mg; 160 mg Tablet, Film Coated from Strides Pharma Science Limited, marketed since Jun 2022 and currently FDA-listed; retail pharmacies pay about $6.09 per tablet (NADAC). It is the main listing for this product, which comes in 3 package sizes.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 065151
- GCN: 22649
- GPI-14 (Medi-Span): 36994503200335
- HICL (First Databank): 036305
- AHFS class code: 24:28.00.00
- RxCUI (RxNorm): 848131
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Dihydropyridine Calcium Channel Blocker class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Amlodipine is used to treat high blood pressure and certain types of angina (chest pain) and coronary artery disease (narrowing of the blood vessels that supply blood to the heart). Amlodipine is in a class of medications called calcium channel blockers. It lowers blood pressure by relaxing the blood vessels so the heart does not have to pump as hard. It controls chest pain by increasing the supply of blood to the heart. If taken regularly, amlodipine controls chest pain, but it does not stop chest pain once it starts. Your doctor may prescribe a different medication to take when you have ches...
Read the full MedlinePlus article ↗Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $6.089 | $182.66 / 30 tablets |
| Medicaid paysCMS SDUD · 12 mo | $7.07 | $212.21 / 30 tablets |
| Medicare drug plans payPart D · Q2 2026 | $5.54 | $166.21 / 30 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 64380-0200-01 You're viewing this Main listing | 30 TABLET, FILM COATED in 1 BOTTLE | $6.09 / ea | $182.66 | 2022-06-27 | — | Active |
| 64380-0200-02 64380-200-02 | 90 TABLET, FILM COATED in 1 BOTTLE | — | — | 2022-06-27 | — | Active |
| 64380-0200-03 64380-200-03 | 500 TABLET, FILM COATED in 1 BOTTLE | — | — | 2022-06-27 | — | Active |
You're viewing the smallest of 3 pack sizes for this product.
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 64380-0200-02?
What NDC number is used to bill for this package of Amlodipine, Valsartan, Hydrochlorothiazide 10 mg; 25 mg; 160 mg Tablet, Film Coated?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| amlodipine,valsartan and hydrochlorothiazide 10 mg/1; 160 mg/1; 25 mg 33342-0286-07 | Macleods | 30 tablets | $6.089 | AB | Availability likely | — |
| Amlodipine, Valsartan, Hydrochlorothiazide 10 mg/1; 25 mg/1; 160 mgthis 64380-0200-01 | Strides | 30 tablets | $6.089 | AB | Availability likely | — |
| Exforge HCT 10 mg/1; 160 mg/1; 25 mg 00078-0562-15 | Novartis | 30 tablets | — | AB | FDA listed | — |
| Amlodipine, Valsartan, Hydrochlorothiazide 10 mg/1; 25 mg/1; 160 mg 51407-0671-30 | Golden | 30 tablets | — | AB | FDA listed | — |
| Amlodipine, Valsartan and Hydrochlorothiazide 10 mg/1; 160 mg/1; 25 mg 65862-0837-05 | Aurobindo | 500 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 2S7830E561
Crospovidone is a synthetic polymer derived from povidone. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the active ingredient can be absorbed.
-
UNII 35SW5USQ3G
A synthetic yellow dye used to color medicines. It helps make tablets, capsules, and liquids visually distinct so patients can easily identify their medication.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
9 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: FETAL TOXICITY • When pregnancy is detected, discontinue amlodipine/valsartan/hydrochlorothiazide as soon as possible (5.1). • Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus (5.1). WARNING: FETAL TOXICITY See full prescribing information for complete boxed warning. • When pregnancy is detected, discontinue amlodipine/valsartan/hydrochlorothiazide as soon as possible. (5.1) • Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus.
(5.1)
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Amlodipine/valsartan/hydrochlorothiazide is indicated for the treatment of hypertension, to lower blood pressure. Lowering blood pressure reduces the risk of fatal and nonfatal cardiovascular events, primarily strokes and myocardial infarctions. These benefits have been seen in controlled trials of antihypertensive drugs from a wide variety of pharmacologic classes, including amlodipine, hydrochlorothiazide, and the ARB class to which valsartan principally belongs.
There are no controlled trials demonstrating risk reduction with amlodipine/valsartan/hydrochlorothiazide. Control of high blood pressure should be part of comprehensive cardiovascular risk management, including, as appropriate, lipid control, diabetes management, antithrombotic therapy, smoking cessation, exercise, and limited sodium intake. Many patients will require more than 1 drug to achieve blood pressure goals.
For specific advice on goals and management, see published guidelines, such as those of the National High Blood Pressure Education Program's Joint National Committee on Prevention, Detection, Evaluation, and Treatment of High Blood Pressure (JNC). Numerous antihypertensive drugs, from a variety of pharmacologic classes and with different mechanisms of action, have been shown in randomized controlled trials to reduce cardiovascular morbidity and mortality, and it can be concluded that it is blood pressure reduction, and not some other pharmacologic property of the drugs, that is largely responsible for those benefits.
The largest and most consistent cardiovascular outcome benefit has been a reduction in the risk of stroke, but reductions in myocardial infarction and cardiovascular mortality also have been seen regularly. Elevated systolic or diastolic pressure causes increased cardiovascular risk, and the absolute risk increase per mmHg is greater at higher blood pressures, so that even modest reductions of severe hypertension can provide substantial benefit. Relative risk reduction from blood pressure reduction is similar across populations with varying absolute risk, so the absolute benefit is greater in patients who are at higher risk independent of their hypertension (e.g., patients with diabetes or hyperlipidemia), and such patients would be expected to benefit from more aggressive treatment to a lower blood pressure goal.
Some antihypertensive drugs have smaller blood pressure effects (as monotherapy) in black patients, and many antihypertensive drugs have additional approved indications and effects (e.g., on angina, heart failure, or diabetic kidney disease). These considerations may guide selection of therapy. Limitation of Use Amlodipine/valsartan/hydrochlorothiazide is not indicated for the initial therapy of hypertension [see Dosage and Administration (2)].
Amlodipine/valsartan/hydrochlorothiazide is a combination tablet of amlodipine, a dihydropyridine calcium channel blocker (DHP CCB), valsartan, an angiotensin II receptor blocker (ARB), and hydrochlorothiazide, a thiazide diuretic. Amlodipine/Valsartan/Hydrochlorothiazide is indicated for the treatment of hypertension to lower blood pressure. Lowering blood pressure reduces the risk of fatal and nonfatal cardiovascular events, primarily strokes, and myocardial infarctions.
(1) Limitation of Use Amlodipine/valsartan/hydrochlorothiazide is not indicated for initial treatment of hypertension.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Dose once-daily. Titrate up to a maximum dose of 10/320/25 mg. (2.1) Amlodipine/valsartan/hydrochlorothiazide may be used as add-on/switch therapy for patients not adequately controlled on any two of the following antihypertensive classes: calcium channel blockers, angiotensin receptor blockers, and diuretics. (2.2) Amlodipine/valsartan/hydrochlorothiazide may be substituted for its individually titrated components. (2.3)
2.1General Considerations Dose once-daily. The dosage may be increased after 2 weeks of therapy. The full blood pressure lowering effect was achieved 2 weeks after being on the maximal dose of amlodipine/valsartan/hydrochlorothiazide. The maximum recommended dose of amlodipine/valsartan/hydrochlorothiazide is 10/320/25 mg.
2.2Add-on/Switch Therapy Amlodipine/valsartan/hydrochlorothiazide may be used for patients not adequately controlled on any 2 of the following antihypertensive classes: calcium channel blockers, angiotensin receptor blockers, and diuretics. A patient who experiences dose-limiting adverse reactions to an individual component while on any dual combination of the components of amlodipine/valsartan/hydrochlorothiazide may be switched to amlodipine/valsartan/hydrochlorothiazide containing a lower dose of that component to achieve similar blood pressure reductions.
2.3Replacement Therapy Amlodipine/valsartan/hydrochlorothiazide may be substituted for the individually titrated components.
2.4Use With Other Antihypertensive Drugs Amlodipine/valsartan/hydrochlorothiazide may be administered with other antihypertensive agents.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Amlodipine/valsartan/hydrochlorothiazide tablets are available as follows: 5 mg amlodipine /160 mg valsartan /12.5 mg hydrochlorothiazide Tablets – White to off-white, film coated, oval shaped biconvex tablets, debossed with "P" on one side of the tablet and "172" on the other. 10 mg amlodipine /160 mg valsartan /12.5 mg hydrochlorothiazide Tablets – Peach to light brown, film coated, oval shaped biconvex tablets, debossed with "P" on one side of the tablet and "174" on the other. 5 mg amlodipine /160 mg valsartan /25 mg hydrochlorothiazide Tablets – Yellow, film-coated, oval shaped biconvex tablets debossed with "P" on one side of the tablet and "173" on the other.
10 mg amlodipine /160 mg valsartan /25 mg hydrochlorothiazide Tablets – Bright yellow, film-coated, oval shaped, biconvex tablets debossed with "P" on one side of the tablet and "185" on the other. 10 mg amlodipine /320 mg valsartan /25 mg hydrochlorothiazide Tablets – White to off-white, film coated, oval shaped biconvex tablets, debossed with "P" on one side of the tablet and "175" on the other. Tablets: (amlodipine/valsartan/hydrochlorothiazide mg) 5/160/12.5 10/160/12.5 5/160/25 10/160/25 10/320/25 (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Do not use in patients with anuria, hypersensitivity to other sulfonamide-derived drugs, or hypersensitivity to any component of this product. Do not coadminister aliskiren with amlodipine/valsartan/hydrochlorothiazide in patients with diabetes [see Drug Interactions (7)]. Anuria (4) Hypersensitivity to sulfonamide-derived drugs (4) Known hypersensitivity to any component (4) Do not coadminister aliskiren with amlodipine/valsartan/hydrochlorothiazide in patients with diabetes (4)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hypotension: Correct volume depletion prior to initiation (5.2) Increased angina and/or myocardial infarction (5.3) Monitor renal function and potassium in susceptible patients (5.4, 5.5) Exacerbation or activation of systemic lupus erythematosus (5.7) Observe for signs of fluid or electrolyte imbalance (5.9) Acute angle-closure glaucoma (5.10)
5.1Fetal Toxicity Valsartan Amlodipine/valsartan/hydrochlorothiazide can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Resulting oligohydramnios can be associated with fetal lung hypoplasia and skeletal deformations.
Potential neonatal adverse effects include skull hypoplasia, anuria, hypotension, renal failure, and death. When pregnancy is detected, discontinue Amlodipine/valsartan/hydrochlorothiazide as soon as possible [see Use in Specific Populations (8.1)]. Hydrochlorothiazide Thiazides cross the placenta, and use of thiazides during pregnancy is associated with fetal or neonatal jaundice, thrombocytopenia, and possibly other adverse reactions that have occurred in adults.
5.2Hypotension in Volume- or Salt-Depleted Patients Excessive hypotension, including orthostatic hypotension, was seen in 1.7% of patients treated with the maximum dose of amlodipine/valsartan/hydrochlorothiazide (10/320/25 mg) compared to 1.8% of valsartan/HCTZ (320/25 mg) patients, 0.4% of amlodipine/valsartan (10/320 mg) patients, and 0.2% of HCTZ/amlodipine (25/10 mg) patients in a controlled trial in patients with moderate to severe uncomplicated hypertension. In patients with an activated renin-angiotensin system, such as volume- or salt-depleted patients receiving high doses of diuretics, symptomatic hypotension may occur in patients receiving angiotensin receptor blockers.
Correct this condition prior to administration of amlodipine/valsartan/hydrochlorothiazide. Amlodipine/valsartan/hydrochlorothiazide has not been studied in patients with heart failure, recent myocardial infarction, or in patients undergoing surgery or dialysis. Patients with heart failure or post-myocardial infarction patients given valsartan commonly have some reduction in blood pressure, but discontinuation of therapy because of continuing symptomatic hypotension usually is not necessary when dosing instructions are followed.
In controlled trials in heart failure patients, the incidence of hypotension in valsartan-treated patients was 5.5% compared to 1.8% in placebo-treated patients. In the Valsartan in Acute Myocardial Infarction Trial (VALIANT), hypotension in post-myocardial infarction patients led to permanent discontinuation of therapy in 1.4% of valsartan-treated patients and 0.8% of captopril-treated patients. Since the vasodilation induced by amlodipine is gradual in onset, acute hypotension has rarely been reported after oral administration.
Do not initiate treatment with amlodipine/valsartan/hydrochlorothiazide in patients with aortic or mitral stenosis or obstructive hypertrophic cardiomyopathy. If excessive hypotension occurs with amlodipine/valsartan/hydrochlorothiazide, place the patient in a supine position and, if necessary, give intravenous normal saline. A transient hypotensive response is not a contraindication to further treatment, which usually can be continued without difficulty once the blood pressure has stabilized.
5.3Increased Angina and/or Myocardial Infarction Worsening angina and acute myocardial infarction can develop after starting or increasing the dose of amlodipine, particularly in patients with severe obstructive coronary artery disease.
5.4Impaired Renal Function Changes in renal function, including acute renal failure can be caused by drugs that inhibit the renin-angiotensin system and by diuretics. Patients whose renal function may depend in part on the activity of the… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Most common adverse events (≥2% incidence) are dizziness, peripheral edema, headache, dyspepsia, fatigue, muscle spasms, back pain, nausea and nasopharyngitis. (6.1) To report SUSPECTED ADVERSE REACTIONS, contact Strides Pharma Inc at 1-877-244-9825 and/or www.strides.com or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical studies are conducted under widely varying conditions, adverse reaction rates observed in the clinical studies of a drug cannot be directly compared to rates in the clinical studies of another drug and may not reflect the rates observed in clinical practice. In the controlled trial of amlodipine/valsartan/hydrochlorothiazide, where only the maximum dose (10/320/25 mg) was evaluated, safety data were obtained in 582 patients with hypertension. Adverse reactions have generally been mild and transient in nature and have only infrequently required discontinuation of therapy.
The overall frequency of adverse reactions was similar between men and women, younger (< 65 years) and older (≥ 65 years) patients, and black and white patients. In the active controlled clinical trial, discontinuation because of adverse events occurred in 4.0% of patients treated with amlodipine/valsartan/hydrochlorothiazide 10/320/25 mg compared to 2.9% of patients treated with valsartan/HCTZ 320/25 mg, 1.6% of patients treated with amlodipine/valsartan 10/320 mg, and 3.4% of patients treated with HCTZ/amlodipine 25/10 mg.
The most common reasons for discontinuation of therapy with amlodipine/valsartan/hydrochlorothiazide were dizziness (1.0%) and hypotension (0.7%). The most frequent adverse events that occurred in the active controlled clinical trial in at least 2% of patients treated with amlodipine/valsartan/hydrochlorothiazide are presented in the following table. Aml/Val/HCTZ Val/HCTZ Aml/Val HCTZ/Aml Preferred Term 10/320/25 mg N=582 n (%) 320/25 mg N=559 n (%) 10/320 mg N=566 n (%) 25/10 mg N=561 n (%) Dizziness 48 ( 8.2) 40 ( 7.2) 14 ( 2.5) 23 ( 4.1) Edema 38 ( 6.5) 8 ( 1.4) 65 (11.5) 63 ( 11.2) Headache 30 (5.2) 31 (5.5) 30 (5.3) 40 (7.1) Dyspepsia 13 ( 2.2) 5 ( 0.9) 6 ( 1.1) 2 ( 0.4) Fatigue 13 ( 2.2) 15 ( 2.7) 12 ( 2.1) 8 ( 1.4) Muscle spasms 13 ( 2.2) 7 ( 1.3) 7 ( 1.2) 5 ( 0.9) Back pain 12 ( 2.1) 13 ( 2.3) 5 ( 0.9) 12 ( 2.1) Nausea 12 ( 2.1) 7 ( 1.3) 10 ( 1.8) 12 ( 2.1) Nasopharyngitis 12 (2.1) 13 (2.3) 13 (2.3) 12 (2.1) Orthostatic events (orthostatic hypotension and postural dizziness) were seen in 0.5% of patients.
Valsartan Valsartan has been evaluated for safety in more than 4000 hypertensive patients in clinical trials. In trials in which valsartan was compared to an ACE inhibitor with or without placebo, the incidence of dry cough was significantly greater in the ACE inhibitor group (7.9%) than in the groups who received valsartan (2.6%) or placebo (1.5%). In a 129-patient trial limited to patients who had dry cough when they had previously received ACE inhibitors, the incidences of cough in patients who received valsartan, HCTZ, or lisinopril were 20%, 19%, and 69% respectively (p < 0.001).
Clinical Laboratory Test Findings Clinical laboratory test findings for amlodipine/valsartan/hydrochlorothiazide were obtained in a controlled trial of amlodipine/valsartan/hydrochlorothiazide administered at the maximal dose of 10/320/25 mg compared to maximal doses of dual therapies, i.e., valsartan/HCTZ 320/25 mg, amlodipine/valsartan 10/320 mg, and HCTZ/amlodipine 25/10 mg. Findings for the components of amlodipine/valsartan/hydrochlorothiazide were obtained from other trials. Creatinine: In heart failure patients, greater than 50% increases in creatinine were observed in 3.9% of valsartan-treated patients compared to 0.9% of placebo-treated patients.
In post-myocardial infarction patients, doubling of serum creatinine was observed in 4.2% of valsartan-treated patients and 3.4% of captopril-treated patients. Blood Urea Nitrogen (BUN): In hypertensive patients, g… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS No drug interaction studies have been conducted with amlodipine/valsartan/hydrochlorothiazide and other drugs, although studies have been conducted with the individual components. A pharmacokinetic drug-drug interaction study has been conducted to address the potential for pharmacokinetic interaction between the triple combination, amlodipine/valsartan/hydrochlorothiazide, and the corresponding 3 double combinations. No clinically relevant interaction was observed.
Amlodipine Impact of Other Drugs on Amlodipine CYP3A Inhibitors Coadministration with CYP3A inhibitors (moderate and strong) results in increased systemic exposure to amlodipine and may require dose reduction. Monitor for symptoms of hypotension and edema when amlodipine is coadministered with CYP3A inhibitors to determine the need for dose adjustment [see Clinical Pharmacology (12.3)]. CYP3A Inducers No information is available on the quantitative effects of CYP3A inducers on amlodipine.
Blood pressure should be closely monitored when amlodipine is coadministered with CYP3A inducers (e.g., rifampicin, St. John's Wort). Sildenafil Monitor for hypotension when sildenafil is coadministered with amlodipine [see Clinical Pharmacology (12.2)].
Impact of Amlodipine on Other Drugs Simvastatin Coadministration of simvastatin with amlodipine increases the systemic exposure of simvastatin. Limit the dose of simvastatin in patients on amlodipine to 20 mg daily [see Clinical Pharmacology (12.3)]. Immunosuppressants Amlodipine may increase the systemic exposure of cyclosporine or tacrolimus when coadministered.
Frequent monitoring of trough blood levels of cyclosporine and tacrolimus is recommended and adjust the dose when appropriate [see Clinical Pharmacology (12.3)]. Valsartan Agents Increasing Serum Potassium: Concomitant use of valsartan with other agents that block the renin-angiotensin system, potassium-sparing diuretics (e.g., spironolactone, triamterene, amiloride), potassium supplements, salt substitutes containing potassium or other drugs that may increase potassium levels (e.g., heparin) may lead to increases in serum potassium and in heart failure patients to increases in serum creatinine.
If co-medication is considered necessary, monitoring of serum potassium is advisable. Non-Steroidal Anti-Inflammatory Agents Including Selective Cyclooxygenase-2 Inhibitors (COX-2 Inhibitors): In patients who are elderly, volume-depleted (including those on diuretic therapy), or with compromised renal function, coadministration of NSAIDs, including selective COX-2 inhibitors, with angiotensin II receptor antagonists, including valsartan, may result in deterioration of renal function, including possible acute renal failure.
These effects are usually reversible. Monitor renal function periodically in patients receiving valsartan and NSAID therapy. The antihypertensive effect of angiotensin II receptor antagonists, including valsartan, may be attenuated by NSAIDs including selective COX-2 inhibitors.
Dual Blockade of the Renin-Angiotensin System (RAS): Dual blockade of the RAS with angiotensin receptor blockers, ACE inhibitors, or aliskiren is associated with increased risks of hypotension, hyperkalemia, and changes in renal function (including acute renal failure) compared to monotherapy. Most patients receiving the combination of two RAS inhibitors do not obtain any additional benefit compared to monotherapy. In general, avoid combined use of RAS inhibitors.
Closely monitor blood pressure, renal function and electrolytes in patients on valsartan and other agents that affect the RAS. Do not coadminister aliskiren with valsartan in patients with diabetes. Avoid use of aliskiren with valsartan in patients with renal impairment (GFR < 60 mL/min).
Valsartan – Hydrochlorothiazide Lithium : Increases in serum lithium concentrations and lithium toxicity have been reported during concomitant administration of lithium with angiotensin II receptor antagonists or thiazides.… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Breastfeeding is not recommended (8.2) Geriatric Patients: Not recommended for initial therapy (8.5) Hepatic Impairment: Not recommended for initial therapy (8.7)
8.1Pregnancy Risk Summary Amlodipine/valsartan/hydrochlorothiazide can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Most epidemiologic studies examining fetal abnormalities after exposure to antihypertensive use in the first trimester have not distinguished drugs affecting the renin-angiotensin system from other antihypertensive agents.
Published reports include cases of anhydramnios and oligohydramnios in pregnant women treated with valsartan (see Clinical Considerations). When pregnancy is detected, discontinue Amlodipine/valsartan/hydrochlorothiazide as soon as possible. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk Hypertension in pregnancy increases the maternal risk for pre-eclampsia, gestational diabetes, premature delivery, and delivery complications (e.g., need for cesarean section, and post-partum hemorrhage).
Hypertension increases the fetal risk for intrauterine growth restriction and intrauterine death. Pregnant women with hypertension should be carefully monitored and managed accordingly. Fetal/Neonatal Adverse Reactions Valsartan Oligohydramnios in pregnant women who use drugs affecting the renin-angiotensin system in the second and third trimesters of pregnancy can result in the following: reduced fetal renal function leading to anuria and renal failure, fetal lung hypoplasia, skeletal deformations, including skull hypoplasia, hypotension and death.
Perform serial ultrasound examinations to assess the intra-amniotic environment. Fetal testing may be appropriate, based on the week of gestation. Patients and physicians should be aware, however, that oligohydramnios may not appear until after the fetus has sustained irreversible injury.
If oligohydramnios is observed, consider alternative drug treatment. Closely observe neonates with histories of in utero exposure to Amlodipine/valsartan/hydrochlorothiazide for hypotension, oliguria, and hyperkalemia. In neonates with a history of in utero exposure to Amlodipine/valsartan/hydrochlorothiazide, if oliguria or hypotension occurs, support blood pressure and renal perfusion.
Exchange transfusions or dialysis may be required as a means of reversing hypotension and replacing renal function. Hydrochlorothiazide Thiazides can cross the placenta, and concentrations reached in the umbilical vein approach those in the maternal plasma. Hydrochlorothiazide, like other diuretics, can cause placental hypoperfusion.
It accumulates in the amniotic fluid, with reported concentrations up to 19 times higher than in umbilical vein plasma. Use of thiazides during pregnancy is associated with a risk of fetal or neonatal jaundice or thrombocytopenia. Since they do not prevent or alter the course of EPH (Edema, Proteinuria, Hypertension) gestosis (preeclampsia), these drugs should not be used to treat hypertension in pregnant women.
The use of HCTZ for other indications (e.g., heart disease) in pregnancy should be avoided. Data Animal Data Valsartan and Amlodipine In rats, administered 20 mg/kg/day amlodipine plus 320 mg/kg/day valsartan, treatment-related maternal and fetal effects (developmental delays and alterations noted in the presence of significant maternal toxicity) were noted with the hig… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Amlodipine/valsartan/hydrochlorothiazide can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Most epidemiologic studies examining fetal abnormalities after exposure to antihypertensive use in the first trimester have not distinguished drugs affecting the renin-angiotensin system from other antihypertensive agents.
Published reports include cases of anhydramnios and oligohydramnios in pregnant women treated with valsartan (see Clinical Considerations). When pregnancy is detected, discontinue Amlodipine/valsartan/hydrochlorothiazide as soon as possible. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk Hypertension in pregnancy increases the maternal risk for pre-eclampsia, gestational diabetes, premature delivery, and delivery complications (e.g., need for cesarean section, and post-partum hemorrhage).
Hypertension increases the fetal risk for intrauterine growth restriction and intrauterine death. Pregnant women with hypertension should be carefully monitored and managed accordingly. Fetal/Neonatal Adverse Reactions Valsartan Oligohydramnios in pregnant women who use drugs affecting the renin-angiotensin system in the second and third trimesters of pregnancy can result in the following: reduced fetal renal function leading to anuria and renal failure, fetal lung hypoplasia, skeletal deformations, including skull hypoplasia, hypotension and death.
Perform serial ultrasound examinations to assess the intra-amniotic environment. Fetal testing may be appropriate, based on the week of gestation. Patients and physicians should be aware, however, that oligohydramnios may not appear until after the fetus has sustained irreversible injury.
If oligohydramnios is observed, consider alternative drug treatment. Closely observe neonates with histories of in utero exposure to Amlodipine/valsartan/hydrochlorothiazide for hypotension, oliguria, and hyperkalemia. In neonates with a history of in utero exposure to Amlodipine/valsartan/hydrochlorothiazide, if oliguria or hypotension occurs, support blood pressure and renal perfusion.
Exchange transfusions or dialysis may be required as a means of reversing hypotension and replacing renal function. Hydrochlorothiazide Thiazides can cross the placenta, and concentrations reached in the umbilical vein approach those in the maternal plasma. Hydrochlorothiazide, like other diuretics, can cause placental hypoperfusion.
It accumulates in the amniotic fluid, with reported concentrations up to 19 times higher than in umbilical vein plasma. Use of thiazides during pregnancy is associated with a risk of fetal or neonatal jaundice or thrombocytopenia. Since they do not prevent or alter the course of EPH (Edema, Proteinuria, Hypertension) gestosis (preeclampsia), these drugs should not be used to treat hypertension in pregnant women.
The use of HCTZ for other indications (e.g., heart disease) in pregnancy should be avoided. Data Animal Data Valsartan and Amlodipine In rats, administered 20 mg/kg/day amlodipine plus 320 mg/kg/day valsartan, treatment-related maternal and fetal effects (developmental delays and alterations noted in the presence of significant maternal toxicity) were noted with the high dose combination. This corresponds to dose multiples of 9 and 19.5 times, respectively, the maximum recommended human dose (MRHD) of 10 mg/day for amlodipine and 320 mg/day for valsartan (based on body… [Excerpted — this section continues on DailyMed.]
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of amlodipine/valsartan/hydrochlorothiazide in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Amlodipine Clinical studies of amlodipine besylate tablets did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal or cardiac function, and of concomitant disease or other drug therapy.
Elderly patients have decreased clearance of amlodipine with a resulting increase of AUC of approximately 40% to 60% [see Clinical Pharmacology (12.3)] . The recommended starting dose of amlodipine 2.5 mg is not an available strength with amlodipine/valsartan/hydrochlorothiazide [see Clinical Studies (14)].
🆘 Overdosage ▾
10 OVERDOSAGE Limited data are available related to overdosage in humans. The most likely manifestations of overdosage would be hypotension and tachycardia; bradycardia could occur from parasympathetic (vagal) stimulation. If symptomatic hypotension should occur, institute supportive treatment.
Amlodipine Single oral doses of amlodipine maleate equivalent to 40 mg/kg and 100 mg/kg amlodipine in mice and rats, respectively, caused deaths. Single oral doses equivalent to 4 or more mg/kg amlodipine in dogs (11 or more times the MRHD on a mg/m 2 basis) caused a marked peripheral vasodilation and hypotension. Overdosage might be expected to cause excessive peripheral vasodilation with marked hypotension.
In humans, experience with intentional overdosage of amlodipine is limited. Marked and potentially prolonged systemic hypotension up to and including shock with fatal outcome have been reported. If massive overdose should occur, initiate active cardiac and respiratory monitoring.
Frequent blood pressure measurements are essential. Should hypotension occur, initiate cardiovascular support, including elevation of the extremities and the judicious administration of fluids. If hypotension remains unresponsive to these conservative measures, consider administration of vasopressors (such as phenylephrine) with attention to circulating volume and urine output.
As amlodipine is highly protein bound, hemodialysis is not likely to be of benefit. Administration of activated charcoal to healthy volunteers immediately or up to two hours after ingestion of amlodipine has been shown to significantly decrease amlodipine absorption. Valsartan Depressed level of consciousness, circulatory collapse, and shock have been reported.
Valsartan is not removed from the plasma by hemodialysis. Valsartan was without grossly observable adverse effects at single oral doses up to 2,000 mg/kg in rats and up to 1,000 mg/kg in marmosets, except for salivation and diarrhea in the rat and vomiting in the marmoset at the highest dose (60 and 31 times, respectively, the MRHD on a mg/m 2 basis) (Calculations assume an oral dose of 320 mg/day and a 60-kg patient). Hydrochlorothiazide The degree to which hydrochlorothiazide is removed by hemodialysis has not been established.
The most common signs and symptoms observed in patients are those caused by electrolyte depletion (hypokalemia, hypochloremia, hyponatremia) and dehydration resulting from excessive diuresis. If digitalis has also been administered, hypokalemia may accentuate cardiac arrhythmias. The oral LD 50 of hydrochlorothiazide is greater than 10 g/kg in both mice and rats, 2000 and 4000 times, respectively, the MRHD on a mg/m 2 basis (Calculations assume an oral dose of 25 mg/day and a 60-kg patient).
Valsartan and Hydrochlorothiazide In rats and marmosets, single oral doses of valsartan up to 1524 and 762 mg/kg in combination with hydrochlorothiazide at doses up to 476 and 238 mg/kg, respectively, were very well tolerated without any treatment-related effects. These no adverse effect doses in rats and marmosets, respectively, represent 46.5 and 23 times the MRHD of valsartan and 188 and 113 times the MRHD of hydrochlorothiazide on a mg/m 2 basis (Calculations assume an oral dose of 320 mg/day valsartan in combination with 25 mg/day hydrochlorothiazide and a 60 kg patient).
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The active ingredients of amlodipine/valsartan/hydrochlorothiazide target 3 separate mechanisms involved in blood pressure regulation. Specifically, amlodipine blocks the contractile effects of calcium on cardiac and vascular smooth muscle cells; valsartan blocks the vasoconstriction and sodium retaining effects of angiotensin II on cardiac, vascular smooth muscle, adrenal and renal cells; and hydrochlorothiazide directly promotes the excretion of sodium and chloride in the kidney leading to reductions in intravascular volume.
A more detailed description of the mechanism of action of each individual component follows. Amlodipine Amlodipine is a dihydropyridine calcium channel blocker that inhibits the transmembrane influx of calcium ions into vascular smooth muscle and cardiac muscle. Experimental data suggest that amlodipine binds to both dihydropyridine and nondihydropyridine binding sites.
The contractile processes of cardiac muscle and vascular smooth muscle are dependent upon the movement of extracellular calcium ions into these cells through specific ion channels. Amlodipine inhibits calcium ion influx across cell membranes selectively, with a greater effect on vascular smooth muscle cells than on cardiac muscle cells. Negative inotropic effects can be detected in vitro but such effects have not been seen in intact animals at therapeutic doses.
Serum calcium concentration is not affected by amlodipine. Within the physiologic pH range, amlodipine is an ionized compound (pKa = 8.6), and its kinetic interaction with the calcium channel receptor is characterized by a gradual rate of association and dissociation with the receptor binding site, resulting in a gradual onset of effect. Amlodipine is a peripheral arterial vasodilator that acts directly on vascular smooth muscle to cause a reduction in peripheral vascular resistance and reduction in blood pressure.
Valsartan Angiotensin II is formed from angiotensin I in a reaction catalyzed by angiotensin-converting enzyme (ACE, kininase II). Angiotensin II is the principal pressor agent of the renin-angiotensin system, with effects that include vasoconstriction, stimulation of synthesis and release of aldosterone, cardiac stimulation, and renal reabsorption of sodium. Valsartan blocks the vasoconstrictor and aldosterone-secreting effects of angiotensin II by selectively blocking the binding of angiotensin II to the AT 1 receptor in many tissues, such as vascular smooth muscle and the adrenal gland.
Its action is therefore independent of the pathways for angiotensin II synthesis. There is also an AT 2 receptor found in many tissues, but AT 2 is not known to be associated with cardiovascular homeostasis. Valsartan has much greater affinity (about 20000-fold) for the AT 1 receptor than for the AT 2 receptor.
The increased plasma levels of angiotensin following AT 1 receptor blockade with valsartan may stimulate the unblocked AT 2 receptor. The primary metabolite of valsartan is essentially inactive with an affinity for the AT 1 receptor about one-200 th that of valsartan itself. Blockade of the renin-angiotensin system with ACE inhibitors, which inhibit the biosynthesis of angiotensin II from angiotensin I, is widely used in the treatment of hypertension.
ACE inhibitors also inhibit the degradation of bradykinin, a reaction also catalyzed by ACE. Because valsartan does not inhibit ACE (kininase II), it does not affect the response to bradykinin. Whether this difference has clinical relevance is not yet known.
Valsartan does not bind to or block other hormone receptors or ion channels known to be important in cardiovascular regulation. Blockade of the angiotensin II receptor inhibits the negative regulatory feedback of angiotensin II on renin secretion, but the resulting increased plasma renin activity and angiotensin II circulating levels do not overcome the effect of valsartan on blood pressure. Hydrochlorothiazide Hydrochlorothiaz… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action The active ingredients of amlodipine/valsartan/hydrochlorothiazide target 3 separate mechanisms involved in blood pressure regulation. Specifically, amlodipine blocks the contractile effects of calcium on cardiac and vascular smooth muscle cells; valsartan blocks the vasoconstriction and sodium retaining effects of angiotensin II on cardiac, vascular smooth muscle, adrenal and renal cells; and hydrochlorothiazide directly promotes the excretion of sodium and chloride in the kidney leading to reductions in intravascular volume.
A more detailed description of the mechanism of action of each individual component follows. Amlodipine Amlodipine is a dihydropyridine calcium channel blocker that inhibits the transmembrane influx of calcium ions into vascular smooth muscle and cardiac muscle. Experimental data suggest that amlodipine binds to both dihydropyridine and nondihydropyridine binding sites.
The contractile processes of cardiac muscle and vascular smooth muscle are dependent upon the movement of extracellular calcium ions into these cells through specific ion channels. Amlodipine inhibits calcium ion influx across cell membranes selectively, with a greater effect on vascular smooth muscle cells than on cardiac muscle cells. Negative inotropic effects can be detected in vitro but such effects have not been seen in intact animals at therapeutic doses.
Serum calcium concentration is not affected by amlodipine. Within the physiologic pH range, amlodipine is an ionized compound (pKa = 8.6), and its kinetic interaction with the calcium channel receptor is characterized by a gradual rate of association and dissociation with the receptor binding site, resulting in a gradual onset of effect. Amlodipine is a peripheral arterial vasodilator that acts directly on vascular smooth muscle to cause a reduction in peripheral vascular resistance and reduction in blood pressure.
Valsartan Angiotensin II is formed from angiotensin I in a reaction catalyzed by angiotensin-converting enzyme (ACE, kininase II). Angiotensin II is the principal pressor agent of the renin-angiotensin system, with effects that include vasoconstriction, stimulation of synthesis and release of aldosterone, cardiac stimulation, and renal reabsorption of sodium. Valsartan blocks the vasoconstrictor and aldosterone-secreting effects of angiotensin II by selectively blocking the binding of angiotensin II to the AT 1 receptor in many tissues, such as vascular smooth muscle and the adrenal gland.
Its action is therefore independent of the pathways for angiotensin II synthesis. There is also an AT 2 receptor found in many tissues, but AT 2 is not known to be associated with cardiovascular homeostasis. Valsartan has much greater affinity (about 20000-fold) for the AT 1 receptor than for the AT 2 receptor.
The increased plasma levels of angiotensin following AT 1 receptor blockade with valsartan may stimulate the unblocked AT 2 receptor. The primary metabolite of valsartan is essentially inactive with an affinity for the AT 1 receptor about one-200 th that of valsartan itself. Blockade of the renin-angiotensin system with ACE inhibitors, which inhibit the biosynthesis of angiotensin II from angiotensin I, is widely used in the treatment of hypertension.
ACE inhibitors also inhibit the degradation of bradykinin, a reaction also catalyzed by ACE. Because valsartan does not inhibit ACE (kininase II), it does not affect the response to bradykinin. Whether this difference has clinical relevance is not yet known.
Valsartan does not bind to or block other hormone receptors or ion channels known to be important in cardiovascular regulation. Blockade of the angiotensin II receptor inhibits the negative regulatory feedback of angiotensin II on renin secretion, but the resulting increased plasma renin activity and angiotensin II circulating levels do not overcome the effect of valsartan on blood pressure. Hydrochlorothiazide Hydrochlorothiazide is a thiazide diureti… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
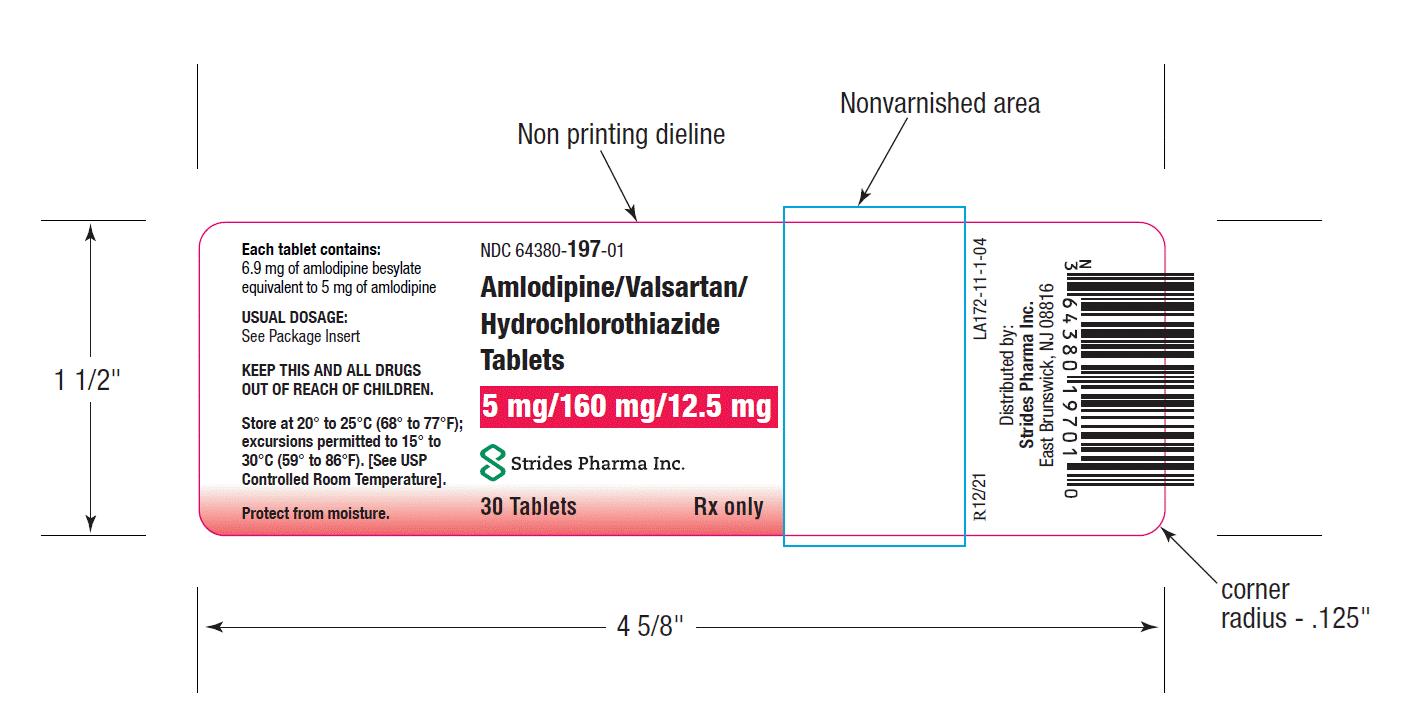
16 HOW SUPPLIED/STORAGE AND HANDLING Amlodipine/valsartan/hydrochlorothiazide is available as film-coated tablets containing amlodipine besylate equivalent to 5 mg or 10 mg of amlodipine free-base with valsartan 160 mg or 320 mg and hydrochlorothiazide 12.5 mg or 25 mg providing for the following available combinations: 5/160/12.5 mg, 10/160/12.5 mg, 5/160/25 mg, 10/160/25 mg or 10/320/25 mg. All strengths are packaged in bottles of 30, 90 and 500 tablets. 5 mg amlodipine /160 mg valsartan /12.5 mg hydrochlorothiazide Tablets - White to off-white, film coated, oval shaped biconvex tablets, debossed with "P" on one side of the tablet and "172" on the other Bottles of 30 NDC 64380-197-01 Bottles of 90 NDC 64380-197-02 Bottles of 500 NDC 64380-197-03 10 mg amlodipine /160 mg valsartan /12.5 mg hydrochlorothiazide Tablets – Peach to light brown, film coated, oval shaped biconvex tablets, debossed with "P" on one side of the tablet and "174" on the other.
Bottles of 30 NDC 64380-199-01 Bottles of 90 NDC 64380-199-02 Bottles of 500 NDC 64380-199-03 5 mg amlodipine /160 mg valsartan /25 mg hydrochlorothiazide Tablets – Yellow, film-coated, oval shaped biconvex tablets debossed with "P" on one side of the tablet and "173" on the other. Bottles of 30 NDC 64380-198-01 Bottles of 90 NDC 64380-198-02 Bottles of 500 NDC 64380-198-03 10 mg amlodipine /160 mg valsartan /25 mg hydrochlorothiazide Tablets – Bright yellow, film-coated oval shaped, biconvex tablets debossed with "P" on one side of the tablet and "185" on the other.
Bottles of 30 NDC 64380-200-01 Bottles of 90 NDC 64380-200-02 Bottles of 500 NDC 64380-200-03 10 mg amlodipine /320 mg valsartan /25 mg hydrochlorothiazide Tablets – White to off-white, film coated, oval shaped biconvex tablets, debossed with "P" on one side of the tablet and "175" on the other Bottles of 30 NDC 64380-201-01 Bottles of 90 NDC 64380-201-02 Bottles of 500 NDC 64380-201-03 Store at 20° to 25°C (68° to 77°F); excursions permitted to 15º to 30°C (59º to 86°F) [see USP Controlled Room Temperature.] Protect from moisture.
Dispense in tight container (USP).
📋 Description ▾
11 DESCRIPTION Amlodipine/valsartan/hydrochlorothiazide is a fixed combination of amlodipine, valsartan and hydrochlorothiazide. Amlodipine/valsartan/hydrochlorothiazide contains the besylate salt of amlodipine, a dihydropyridine calcium channel blocker (CCB). Amlodipine besylate, USP is a white to pale yellow crystalline powder, slightly soluble in water and sparingly soluble in ethanol.
Amlodipine besylate's chemical name is 3-Ethyl 5-methyl (±)-2-[(2-aminoethoxy)methyl]4-( o -chlorophenyl)-1,4-dihydro-6-methyl-3,5-pyridinedicarboxylate, monobenzenesulfonate; its structural formula is: Its empirical formula is C 20 H 25 ClN 2 O 5 •C 6 H 6 O 3 S and its molecular weight is 567.1. Valsartan, USP is a nonpeptide, orally active, and specific angiotensin II antagonist acting on the AT1 receptor subtype. Valsartan is a white to practically white fine powder, soluble in ethanol and methanol and slightly soluble in water.
Valsartan's chemical name is N-(1-oxopentyl)-N-[[2′-(1 H -tetrazol-5-yl) [1,1′-biphenyl]-4-yl]methyl]-L-valine; its structural formula is: Its empirical formula is C 24 H 29 N 5 O 3 and its molecular weight is 435.5. Hydrochlorothiazide, USP is a white, or practically white, practically odorless, crystalline powder. It is slightly soluble in water; freely soluble in sodium hydroxide solution, in n -butylamine, and in dimethylformamide; sparingly soluble in methanol; and insoluble in ether, in chloroform, and in dilute mineral acids.
Hydrochlorothiazide is chemically described as 6-chloro-3,4-dihydro-2 H -1,2,4-benzothiadiazine-7-sulfonamide 1,1-dioxide. Hydrochlorothiazide is a thiazide diuretic. Its empirical formula is C 7 H 8 ClN 3 O 4 S 2 , its molecular weight is 297.73, and its structural formula is: Amlodipine/valsartan/hydrochlorothiazide film-coated tablets are formulated in five strengths for oral administration with a combination of amlodipine besylate, valsartan and hydrochlorothiazide, providing for the following available combinations: 5/160/12.5 mg, 10/160/12.5 mg, 5/160/25 mg, 10/160/25 mg and 10/320/25 mg amlodipine besylate/valsartan/hydrochlo rothiazide.
The inactive ingredients for all strengths of the tablets include microcrystalline cellulose, crospovidone, colloidal silicon dioxide, and magnesium stearate, Additionally, the 5/160/12.5 mg strength contains polyethylene glycol, polyvinyl alcohol, titanium dioxide and talc; the 10/320/25 mg strength contains the same ingredients as the 5/160/12.5 mg strength; the 5/160/25 mg strength contains lactose monohydrate, hypromellose, triacetin, D&C Yellow #10, titanium dioxide, and FD&C Yellow #6; the 10/160/12.5 mg strength contains FD&C Yellow #6, triethyl citrate, yellow iron oxide, hypromellose and titanium dioxide, lactose monohydrate; and the 10/160/25 mg strength contains hypromellose, titanium dioxide, D&C Yellow #10, macrogol and polysorbate. amlodipine-structure Valsartan-structure HCTZ-structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Pregnancy: Advise female patients of childbearing age about the consequences of exposure to amlodipine/valsartan/ hydrochlorothiazide during pregnancy. Discuss treatment options with women planning to become pregnant.
Ask patients to report pregnancies to their physicians as soon as possible [see Warnings and Precautions (5.1) and Use in Specific Populations (8.1)] Lactation: Advise women not to breastfeed during treatment with amlodipine/valsartan/hydrochlorothiazide [see Use in Specific Populations (8.2)]. Symptomatic Hypotension: Advise patients that lightheadedness can occur, especially during the first days of therapy, and that it should be reported to their healthcare provider. Tell patients that if syncope occurs to discontinue amlodipine/valsartan/ hydrochlorothiazide until the physician has been consulted.
Caution all patients that inadequate fluid intake, excessive perspiration, diarrhea, or vomiting can lead to an excessive fall in blood pressure, with the same consequences of lightheadedness and possible syncope [see Warnings and Precautions (5.2)]. Potassium Supplements: Advise patients not to use salt substitutes without consulting their healthcare provider [see Drug Interactions (7)]. Non-melanoma Skin Cancer: Instruct patients taking hydrochlorothiazide to protect skin from the sun and undergo regular skin cancer screening [see Adverse Reactions (6.2)].
Information for Patients Patient Information Amlodipine/Valsartan/Hydrochlorothiazide (am-LOE-di-peen, val-SAR-tan, HYE-droe-klor-oh THYE-a-zide) Tablets Read the Patient Information that comes with amlodipine/valsartan/hydrochlorothiazide before you start taking it and each time you get a refill. There may be new information. This leaflet does not take the place of talking with your doctor about your medical condition or treatment.
What is the most important information I should know about Amlodipine/ Valsartan/Hydrochlorothiazide? Amlodipine/valsartan/hydrochlorothiazide can cause harm or death to an unborn baby. Talk to your doctor about other ways to lower your blood pressure if you plan to become pregnant.
If you get pregnant while taking amlodipine/valsartan/hydrochlorothiazide, tell your doctor right away. What is Amlodipine/Valsartan/Hydrochlorothiazide? Amlodipine/valsartan/hydrochlorothiazide contains 3 prescription medicines: amlodipine, a calcium channel blocker valsartan, an angiotensin receptor blocker, and hydrochlorothiazide, a diuretic (water pill) Amlodipine/valsartan/hydrochlorothiazide may be used to lower blood pressure in adults when 2 medicines to lower your high blood pressure are not enough.
Amlodipine/valsartan/hydrochlorothiazide has not been studied in children under 18 years of age. Who should not take Amlodipine/Valsartan/Hydrochlorothiazide? Do not take Amlodipine/Valsartan/Hydrochlorothiazide if you have low or no urine output (anuria).
What should I tell my doctor before taking Amlodipine/Valsartan/Hydrochlorothiazide? Tell your doctor about all of your medical conditions, including if you: are pregnant or plan to become pregnant . See "What is the most important information I should know about amlodipine/valsartan/hydrochlorothiazide?" are breastfeeding or plan to breastfeed .
Amlodipine/valsartan/hydrochlorothiazide is present in human milk. It is not known whether amlodipine/valsartan/ hydrochlorothiazide affects your breastfed baby or milk production. Do not breastfeed while you are taking amlodipine/valsartan/hydrochlorothiazide. are allergic to any of the ingredients in amlodipine/valsartan/hydrochlorothiazide.
See the end of this leaflet for a list of the ingredients in amlodipine/ valsartan/hydrochlorothiazide. have heart problems have liver problems have kidney problems are vomiting or having a lot of diarrhea have or had gallstones have Lupus have low levels of potassium (with or without symptoms such as… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
8.2Lactation Risk Summary There is limited information regarding the presence of Amlodipine/valsartan/hydrochlorothiazide in human milk, the effects on the breastfed infant, or the effects on milk production. Hydrochlorothiazide is present in human milk and valsartan is present in rat milk. Limited published studies report that amlodipine is present in human milk.
Because of the potential for serious adverse reactions in breastfed infants, advise a nursing woman that breastfeeding is not recommended during treatment with Amlodipine/valsartan/hydrochlorothiazide. Data Valsartan was detected in the milk of lactating rats 15 minutes after oral administration of a 3 mg/kg dose.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Amlodipine/Valsartan/Hydrochlorothiazide Following oral administration of amlodipine/valsartan/hydrochlorothiazide in normal healthy adults, peak plasma concentrations of amlodipine, valsartan and HCTZ are reached in about 6 hours, 3 hours, and 2 hours, respectively. The rate and extent of absorption of amlodipine, valsartan and HCTZ from Amlodipine/valsartan/hydrochlorothiazide are the same as when administered as individual dosage forms. The bioavailability of amlodipine, valsartan, and HCTZ were not altered when amlodipine/valsartan/hydrochlorothiazide was administered with food.
Amlodipine/valsartan/hydrochlorothiazide may be administered with or without food. Amlodipine Peak plasma concentrations of amlodipine are reached 6 to 12 hours after administration of amlodipine alone. Absolute bioavailability has been estimated to be between 64% and 90%.
The apparent volume of distribution of amlodipine is 21 L/kg. Approximately 93% of circulating amlodipine is bound to plasma proteins in hypertensive patients. Amlodipine is extensively (about 90%) converted to inactive metabolites via hepatic metabolism with 10% of the parent compound and 60% of the metabolites excreted in the urine.
Elimination of amlodipine from the plasma is biphasic with a terminal elimination half-life of about 30 to 50 hours. Steady state plasma levels of amlodipine are reached after 7 to 8 days of consecutive daily dosing. Valsartan Following oral administration of valsartan alone peak plasma concentrations of valsartan are reached in 2 to 4 hours.
Absolute bioavailability is about 25% (range 10% to 35%). The steady state volume of distribution of valsartan after intravenous administration is 17 L indicating that valsartan does not distribute into tissues extensively. Valsartan is highly bound to serum proteins (95%), mainly serum albumin.
Valsartan shows biexponential decay kinetics following intravenous administration with an average elimination half-life of about 6 hours. The recovery is mainly as unchanged drug, with only about 20% of dose recovered as metabolites. The primary metabolite, accounting for about 9% of dose, is valeryl 4-hydroxy valsartan.
In vitro metabolism studies involving recombinant CYP450 enzymes indicated that the CYP2C9 isoenzyme is responsible for the formation of valeryl-4-hydroxy valsartan. Valsartan does not inhibit CYP450 isozymes at clinically relevant concentrations. CYP450 mediated drug interaction between valsartan and coadministered drugs are unlikely because of the low extent of metabolism.
Valsartan, when administered as an oral solution, is primarily recovered in feces (about 83% of dose) and urine (about 13% of dose). Following intravenous administration, plasma clearance of valsartan is about 2 L/h and its renal clearance is
0.62L/h (about 30% of total clearance). Hydrochlorothiazide The estimated absolute bioavailability of hydrochlorothiazide after oral administration is about 70%. Peak plasma hydrochlorothiazide concentrations (C max ) are reached within 2 to 5 hours after oral administration.
There is no clinically significant effect of food on the bioavailability of hydrochlorothiazide. Hydrochlorothiazide binds to albumin (40% to 70%) and distributes into erythrocytes. Following oral administration, plasma hydrochlorothiazide concentrations decline biexponentially, with a mean distribution half-life of about 2 hours and an elimination half-life of about 10 hours.
About 70% of an orally administered dose of hydrochlorothiazide is eliminated in the urine as unchanged drug. Specific Populations Geriatric: Elderly patients have decreased clearance of amlodipine with a resulting increase in peak plasma levels, elimination half-life, and AUC. Exposure (measured by AUC) to valsartan is higher by 70% and the half-life is longer by 35% in the elderly than in the young.
Limited amount of data suggest that the systemic clearance of hydrochlorothiazide is reduced in both healthy and hypertensive el… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Amlodipine/valsartan/hydrochlorothiazide has been shown to be effective in lowering blood pressure. The 3 components of amlodipine/valsartan/hydrochlorothiazide lower the blood pressure through complementary mechanisms, each working at a separate site and blocking different effector pathways. The pharmacodynamics of each individual component is described below.
Amlodipine/valsartan/hydrochlorothiazide has not been studied in indications other than hypertension. Amlodipine Following administration of therapeutic doses to patients with hypertension, amlodipine produces vasodilation resulting in a reduction of supine and standing blood pressures. These decreases in blood pressure are not accompanied by a significant change in heart rate or plasma catecholamine levels with chronic dosing.
Although the acute intravenous administration of amlodipine decreases arterial blood pressure and increases heart rate in hemodynamic studies of patients with chronic stable angina, chronic oral administration of amlodipine in clinical trials did not lead to clinically significant changes in heart rate or blood pressures in normotensive patients with angina. With chronic, once-daily administration, antihypertensive effectiveness is maintained for at least 24 hours. Plasma concentrations correlate with effect in both young and elderly patients.
The magnitude of reduction in blood pressure with amlodipine is also correlated with the height of pretreatment elevation; thus, individuals with moderate hypertension (diastolic pressure 105-114 mmHg) had about a 50% greater response than patients with mild hypertension (diastolic pressure 90-104 mmHg). Normotensive subjects experienced no clinically significant change in blood pressure (+1/-2 mmHg). In hypertensive patients with normal renal function, therapeutic doses of amlodipine resulted in a decrease in renal vascular resistance and an increase in glomerular filtration rate and effective renal plasma flow without change in filtration fraction or proteinuria.
As with other calcium channel blockers, hemodynamic measurements of cardiac function at rest and during exercise (or pacing) in patients with normal ventricular function treated with amlodipine have generally demonstrated a small increase in cardiac index without significant influence on dP/dt or on left ventricular end diastolic pressure or volume. In hemodynamic studies, amlodipine has not been associated with a negative inotropic effect when administered in the therapeutic dose range to intact animals and man, even when coadministered with beta-blockers to man.
Similar findings, however, have been observed in normal or well-compensated patients with heart failure with agents possessing significant negative inotropic effects. Amlodipine does not change sinoatrial nodal function or atrioventricular conduction in intact animals or man. In patients with chronic stable angina, intravenous administration of 10 mg did not significantly alter A-H and H-V conduction and sinus node recovery time after pacing.
Similar results were obtained in patients receiving amlodipine and concomitant beta-blockers. In clinical studies in which amlodipine was administered in combination with beta-blockers to patients with either hypertension or angina, no adverse effects of electrocardiographic (ECG) parameters were observed. In clinical trials with angina patients alone, amlodipine therapy did not alter ECG intervals or produce higher degrees of AV blocks.
Amlodipine has indications other than hypertension which are described in its full prescribing information. Drug Interactions Sildenafil When amlodipine and sildenafil were used in combination, each agent independently exerted its own blood pressure lowering effect [see Drug Interactions (7)]. Valsartan Valsartan inhibits the pressor effect of angiotensin II infusions.
An oral dose of 80 mg inhibits the pressor effect by about 80% at peak with approximately 30% inhibition persisting for 24 hou… [Excerpted — this section continues on DailyMed.]
🔬 Clinical Studies ▾
14 CLINICAL STUDIES Amlodipine/valsartan/hydrochlorothiazide was studied in a double-blind, active controlled study in hypertensive patients. A total of 2271 patients with moderate to severe hypertension (mean baseline systolic/diastolic blood pressure was 170/107 mmHg) received treatments of amlodipine/valsartan/HCTZ 10/320/25 mg, valsartan/HCTZ 320/25 mg, amlodipine/ valsartan 10/320 mg, or HCTZ/amlodipine 25/10 mg. At study initiation, patients assigned to the 2-component arms received lower doses of their treatment combination while patients assigned to the amlodipine/valsartan/hydrochlorothiazide arm received 160/12.5 mg valsartan/hydrochlorothiazide.
After 1 week, amlodipine/valsartan/hydrochlorothiazide patients were titrated to 5/160/12.5 mg amlodipine/valsartan/hydrochlorothiazide, while all other patients continued receiving their initial doses. After 2 weeks, all patients were titrated to their full treatment dose. A total of 55% of patients were male, 14% were 65 years or older, 72% were Caucasian, and 17% were black.
At Week 8, the triple combination therapy produced greater reductions in blood pressure than each of the 3 dual combination treatments (p < 0.0001 for both diastolic and systolic blood pressures reductions). The reductions in systolic/ diastolic blood pressure with amlodipine/valsartan/hydrochlorothiazide were 7.6/5.0 mmHg greater than with valsartan/ HCTZ, 6.2/3.3 mmHg greater than with amlodipine/valsartan, and 8.2/5.3 mmHg greater than with amlodipine/HCTZ (see Figure 1). The full blood pressure lowering effect was achieved 2 weeks after being on the maximal dose of amlodipine/ valsartan/hydrochlorothiazide (see Figure 2 and Figure 3).
As the pivotal study was an active-controlled trial, the treatment effects shown in Figures 1, 2, and 3 include a placebo effect of unknown size. A subgroup of 283 patients was studied with ambulatory blood pressure monitoring. The blood pressure lowering effect in the triple therapy group was maintained throughout the 24-hour period (see Figure 4 and Figure 5).
There are no trials of the amlodipine/valsartan/hydrochlorothiazide combination tablet demonstrating reductions in cardiovascular risk in patients with hypertension, but both the amlodipine and hydrochlorothiazide components and several ARBs, which are the same pharmacological class as the valsartan component, have demonstrated such benefits. Figure1 Figure2 Figure3 Figure4 Figure5
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Studies with Amlodipine/Valsartan/Hydrochlorothiazide : No carcinogenicity, mutagenicity or fertility studies have been conducted with this combination. However, these studies have been conducted for amlodipine, valsartan and hydrochlorothiazide alone. Based on the preclinical safety and human pharmacokinetic studies, there is no indication of any toxicologically significant adverse interaction between these components.
Studies with Amlodipine : Rats and mice treated with amlodipine maleate in the diet for up to two years, at concentrations calculated to provide daily dosage levels of 0.5, 1.25, and 2.5 mg amlodipine/kg/day, showed no evidence of a carcinogenic effect of the drug. For the mouse, the highest dose was, on a mg/m 2 basis, similar to the MRHD of 10 mg amlodipine/day. For the rat, the highest dose was, on a mg/m 2 basis, about 2.5 times the MRHD.
(Calculations based on a 60 kg patient). Mutagenicity studies conducted with amlodipine maleate revealed no drug-related effects at either the gene or chromosome level. There was no effect on the fertility of rats treated orally with amlodipine maleate (males for 64 days and females for 14 days prior to mating) at doses of up to 10 mg amlodipine/kg/day (about 10 times the MRHD of 10 mg/day on a mg/m 2 basis).
Studies with Valsartan : There was no evidence of carcinogenicity when valsartan was administered in the diet to mice and rats for up to 2 years at concentrations calculated to provide doses of up to 160 and 200 mg/kg/day, respectively. These doses in mice and rats are about 2.4 and 6 times, respectively, the MRHD of 320 mg/day on a mg/m 2 basis (Calculations based on a 60 kg patient). Mutagenicity assays did not reveal any valsartan-related effects at either the gene or chromosome level.
These assays included bacterial mutagenicity tests with Salmonella and E. coli , a gene mutation test with Chinese hamster V79 cells, a cytogenetic test with Chinese hamster ovary cells, and a rat micronucleus test. Valsartan had no adverse effects on the reproductive performance of male or female rats at oral doses of up to 200 mg/kg/day. This dose is about 6 times the MRHD on a mg/m 2 basis.
Studies with Hydrochlorothiazide : Two-year feeding studies in mice and rats conducted under the auspices of the National Toxicology Program (NTP) uncovered no evidence of a carcinogenic potential of hydrochlorothiazide in female mice (at doses of up to approximately 600 mg/kg/day) or in male and female rats (at doses of up to approximately 100 mg/kg/day). The NTP, however, found equivocal evidence for hepatocarcinogenicity in male mice. Hydrochlorothiazide was not genotoxic in vitro in the Ames mutagenicity assay of Salmonella Typhimurium strains TA 98, TA 100, TA 1535, TA 1537, and TA 1538 and in the Chinese Hamster Ovary (CHO) test for chromosomal aberrations, or in vivo in assays using mouse germinal cell chromosomes, Chinese hamster bone marrow chromosomes, and the Drosophila sex-linked recessive lethal trait gene.
Positive test results were obtained in the in vitro CHO Sister Chromatid Exchange (clastogenicity) and Mouse Lymphoma Cell (mutagenicity) assays and in the Aspergillus Nidulans non-disjunction assay. Hydrochlorothiazide had no adverse effects on the fertility of mice and rats of either sex in studies wherein these species were exposed via diet at doses of up to 100 and 4 mg/kg, respectively, prior to mating and throughout gestation. These doses of hydrochlorothiazide in mice and rats are 19 and 1.5 times, respectively, the MRHD on a mg/m 2 basis (Calculations assume an oral dose of 25 mg/day and a 60-kg patient).
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Studies with Amlodipine/Valsartan/Hydrochlorothiazide : No carcinogenicity, mutagenicity or fertility studies have been conducted with this combination. However, these studies have been conducted for amlodipine, valsartan and hydrochlorothiazide alone. Based on the preclinical safety and human pharmacokinetic studies, there is no indication of any toxicologically significant adverse interaction between these components.
Studies with Amlodipine : Rats and mice treated with amlodipine maleate in the diet for up to two years, at concentrations calculated to provide daily dosage levels of 0.5, 1.25, and 2.5 mg amlodipine/kg/day, showed no evidence of a carcinogenic effect of the drug. For the mouse, the highest dose was, on a mg/m 2 basis, similar to the MRHD of 10 mg amlodipine/day. For the rat, the highest dose was, on a mg/m 2 basis, about 2.5 times the MRHD.
(Calculations based on a 60 kg patient). Mutagenicity studies conducted with amlodipine maleate revealed no drug-related effects at either the gene or chromosome level. There was no effect on the fertility of rats treated orally with amlodipine maleate (males for 64 days and females for 14 days prior to mating) at doses of up to 10 mg amlodipine/kg/day (about 10 times the MRHD of 10 mg/day on a mg/m 2 basis).
Studies with Valsartan : There was no evidence of carcinogenicity when valsartan was administered in the diet to mice and rats for up to 2 years at concentrations calculated to provide doses of up to 160 and 200 mg/kg/day, respectively. These doses in mice and rats are about 2.4 and 6 times, respectively, the MRHD of 320 mg/day on a mg/m 2 basis (Calculations based on a 60 kg patient). Mutagenicity assays did not reveal any valsartan-related effects at either the gene or chromosome level.
These assays included bacterial mutagenicity tests with Salmonella and E. coli , a gene mutation test with Chinese hamster V79 cells, a cytogenetic test with Chinese hamster ovary cells, and a rat micronucleus test. Valsartan had no adverse effects on the reproductive performance of male or female rats at oral doses of up to 200 mg/kg/day. This dose is about 6 times the MRHD on a mg/m 2 basis.
Studies with Hydrochlorothiazide : Two-year feeding studies in mice and rats conducted under the auspices of the National Toxicology Program (NTP) uncovered no evidence of a carcinogenic potential of hydrochlorothiazide in female mice (at doses of up to approximately 600 mg/kg/day) or in male and female rats (at doses of up to approximately 100 mg/kg/day). The NTP, however, found equivocal evidence for hepatocarcinogenicity in male mice. Hydrochlorothiazide was not genotoxic in vitro in the Ames mutagenicity assay of Salmonella Typhimurium strains TA 98, TA 100, TA 1535, TA 1537, and TA 1538 and in the Chinese Hamster Ovary (CHO) test for chromosomal aberrations, or in vivo in assays using mouse germinal cell chromosomes, Chinese hamster bone marrow chromosomes, and the Drosophila sex-linked recessive lethal trait gene.
Positive test results were obtained in the in vitro CHO Sister Chromatid Exchange (clastogenicity) and Mouse Lymphoma Cell (mutagenicity) assays and in the Aspergillus Nidulans non-disjunction assay. Hydrochlorothiazide had no adverse effects on the fertility of mice and rats of either sex in studies wherein these species were exposed via diet at doses of up to 100 and 4 mg/kg, respectively, prior to mating and throughout gestation. These doses of hydrochlorothiazide in mice and rats are 19 and 1.5 times, respectively, the MRHD on a mg/m 2 basis (Calculations assume an oral dose of 25 mg/day and a 60-kg patient).
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL 5 mg/160 mg/12.5 mg - 30 tablets
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL 5 mg/160 mg/25 mg - 30 tablets
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL 10 mg/160 mg/12.5 mg - 30 tablets
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL 10 mg/160 mg/25 mg - 30 tablets
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL Image