
Uloric febuxostat 80 mg Tablet, 100-count — NDC 64764-677-11 (Billing 64764-0677-11)
This is a package of 100 tablets of Uloric febuxostat 80 mg Tablet from Takeda Pharmaceuticals America, Inc., marketed since Feb 2009 and currently FDA-listed.
Other active recalls for Febuxostat (different manufacturers) — 2 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 064830
- GCN: 16809
- GPI-14 (Medi-Span): 68000030000330
- HICL (First Databank): 036106
- AHFS class code: 92:16.00.00
- RxCUI (RxNorm): 834235
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Xanthine Oxidase Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It lowers uric acid in adults with gout. It's meant for people who didn't respond to allopurinol, can't tolerate it, or can't use it. It isn't recommended if you have high uric aci...
- Take it by mouth once a day, with or without food or antacids. Your prescriber may adjust the dose after a couple of weeks based on your uric acid level. Follow your label closely.
- As uric acid drops, urate stored in your tissues is released, and that can trigger flares. It's common early on. Your doctor will likely recommend an NSAID or colchicine to help pr...
- Why did my gout flare up after I started?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Febuxostat — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 64764-0677-11 You're viewing this | 10 BLISTER PACK in 1 CARTON / 10 TABLET in 1 BLISTER PACK | — | — | 2009-02-13 | — | Active |
| 64764-0677-13 64764-677-13 | 100 TABLET in 1 BOTTLE | — | — | 2009-02-13 | — | Active |
| 64764-0677-19 64764-677-19 | 1000 TABLET in 1 BOTTLE | — | — | 2009-02-13 | — | Active |
| 64764-0677-30 64764-677-30 Main listing | 30 TABLET in 1 BOTTLE | $10.54 / ea | $316.13 | 2009-02-13 | — | Active |
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 64764-0677-30?
What NDC number is used to bill for this package of Uloric febuxostat 80 mg Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Febuxostat 80 mg 00054-0414-13 | Hikma | 30 tablets | $0.261 | AB | Availability likely | — |
| Febuxostat 80 mg 00527-2248-32 | Lannett | 30 tablets | $0.261 | AB | Availability likely | — |
| Febuxostat 80 mg 00904-7396-46 | MAJOR | 30 tablets | $0.261 | AB | Availability likely | — |
| Febuxostat 80 mg 16714-0060-01 | NorthStar | 30 tablets | $0.261 | AB | Availability likely | — |
| Febuxostat 80 mg 27808-0207-01 | Tris | 30 tablets | $0.261 | AB | Availability likely | — |
| Febuxostat 80 mg 33342-0275-07 | Macleods | 30 films | $0.261 | AB | Availability likely | — |
| Febuxostat 80 mg 43547-0296-03 | Solco | 30 tablets | $0.261 | AB | Availability likely | — |
| Febuxostat 80 mg 72205-0029-30 | Novadoz | 30 tablets | $0.261 | AB | Availability likely | — |
| Febuxostat 80 mg 00904-7485-03 | Major | 30 tablets | $0.281 | AB | Discontinued | — |
| Febuxostat 80 mg 46708-0191-06 | Alembic | 60 tablets | — | AB | FDA listed | — |
| Febuxostat 80 mg 47335-0722-18 | Sun | 1000 tablets | — | AB | FDA listed | — |
| Febuxostat 80 mg 51407-0294-30 | Golden | 30 tablets | — | AB | FDA listed | — |
| Febuxostat 80 mg 55111-0797-01 | DR | 100 tablets | — | AB | FDA listed | — |
| Febuxostat 80 mg 59651-0114-01 | Aurobindo | 100 tablets | — | AB | FDA listed | — |
| Febuxostat 80 mg 62332-0191-06 | Alembic | 60 tablets | — | AB | FDA listed | — |
| Uloric 80 mgthis 64764-0677-11 | Takeda | 100 tablets | — | AB | FDA listed | — |
| Febuxostat 80 mg 67877-0669-01 | Ascend | 100 tablets | — | AB | FDA listed | — |
| Febuxostat 80 mg 68071-3761-09 | NuCare | 90 tablets | — | AB | FDA listed | — |
| febuxostat 80 mg 70771-1553-00 | Zydus | 1000 tablets | — | AB | FDA listed | — |
| Febuxostat 80 mg 72303-0856-01 | HEC | 30 tablets | — | AB | FDA listed | — |
| febuxostat 80 mg 72578-0137-01 | Viona | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 8372872 ↗ | Method of use | U-1346 | Sep 8, 2031 |
| US 9107912 ↗ | Method of use | U-1346 | Sep 8, 2031 |
| US 8372872 ↗ | Method of use | U-1346 | Sep 8, 2031 |
| US 9107912 ↗ | Method of use | U-1346 | Sep 8, 2031 |
Is there a generic version of ULORIC 80 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 35SW5USQ3G
A synthetic yellow dye used to color medicines. It helps make tablets, capsules, and liquids visually distinct so patients can easily identify their medication.
-
UNII H3R47K3TBD
FD&C Blue No. 1 is a synthetic blue dye approved for use in foods and medicines. It serves as a colorant to give the medication its distinctive appearance and help with product identification.
-
UNII L06K8R7DQK
A synthetic blue dye approved by the FDA for use in medications and foods. It serves as a colorant to make pills and liquids visually distinct and easier to identify.
-
UNII 66O7AQV0RT
Hydroxypropyl cellulose is a plant-derived thickener and binder made from cellulose. In medicines, it helps hold tablet ingredients together, thickens liquids, and can form a coating on pills or capsules.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII 532B59J990
Polyvinyl alcohol is a synthetic polymer made from plant-derived materials. It's used as a binder to hold ingredients together, a film-former in coatings, and a thickener in liquid formulations.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
13 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: CARDIOVASCULAR DEATH Gout patients with established cardiovascular (CV) disease treated with ULORIC had a higher rate of CV death compared to those treated with allopurinol in a CV outcomes study [see Warnings and Precautions (5.1) ] . Consider the risks and benefits of ULORIC when deciding to prescribe or continue patients on ULORIC. ULORIC should only be used in patients who have an inadequate response to a maximally titrated dose of allopurinol, who are intolerant to allopurinol, or for whom treatment with allopurinol is not advisable [see Indications and Usage (1) ] .
WARNING: CARDIOVASCULAR DEATH See full prescribing information for complete boxed warning. Gout patients with established cardiovascular (CV) disease treated with ULORIC had a higher rate of CV death compared to those treated with allopurinol in a CV outcomes study. ( 5.1 ) Consider the risks and benefits of ULORIC when deciding to prescribe or continue patients on ULORIC.
ULORIC should only be used in patients who have an inadequate response to a maximally titrated dose of allopurinol, who are intolerant to allopurinol, or for whom treatment with allopurinol is not advisable. ( 1 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE ULORIC is a xanthine oxidase (XO) inhibitor indicated for the chronic management of hyperuricemia in adult patients with gout who have an inadequate response to a maximally titrated dose of allopurinol, who are intolerant to allopurinol, or for whom treatment with allopurinol is not advisable. ULORIC is a xanthine oxidase (XO) inhibitor indicated for the chronic management of hyperuricemia in adult patients with gout who have an inadequate response to a maximally titrated dose of allopurinol, who are intolerant to allopurinol, or for whom treatment with allopurinol is not advisable.
( 1 ) Limitations of Use : ULORIC is not recommended for the treatment of asymptomatic hyperuricemia. ( 1 ) Limitations of Use : ULORIC is not recommended for the treatment of asymptomatic hyperuricemia.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Recommended dosage is 40 mg or 80 mg once daily. The recommended starting dosage is 40 mg once daily. For patients who do not achieve a serum uric acid (sUA) less than 6 mg/dL after 2 weeks, the recommended dosage is 80 mg once daily.
( 2.1 ) Patients with severe renal impairment: Limit the dosage to 40 mg once daily. ( 2.2 , 8.6 ) Flare prophylaxis is recommended upon initiation of ULORIC. ( 2.4 ) Can be administered without regard to food or antacid use.
( 2.1 )
2.1Recommended Dosage The recommended ULORIC dosage is 40 mg or 80 mg once daily. The recommended starting dosage of ULORIC is 40 mg once daily. For patients who do not achieve a serum uric acid (sUA) less than 6 mg/dL after two weeks, the recommended ULORIC dosage is 80 mg once daily.
ULORIC can be taken without regard to food or antacid use [see Clinical Pharmacology (12.3) ]. Concurrent prophylactic treatment with a non-steroidal anti-inflammatory drug (NSAID) or colchicine is recommended [see Dosage and Administration (2.4) and Warnings and Precautions (5.2) ].
2.2Dosage Recommendations in Patients with Renal Impairment and Hepatic Impairment The recommended dosage of ULORIC is limited to 40 mg once daily in patients with severe renal impairment. No dose modification is necessary when administering ULORIC in patients with mild or moderate renal impairment [see Use in Specific Populations (8.6) and Clinical Pharmacology (12.3) ] . No dosage modification is necessary in patients with mild to moderate hepatic impairment [see Use in Specific Populations (8.7) and Clinical Pharmacology (12.3) ] .
2.3Serum Uric Acid Level Monitoring Testing for the target serum uric acid level of less than 6 mg/dL may be performed as early as two weeks after initiating ULORIC therapy.
2.4Recommended Prophylaxis for Gout Flares Gout flares may occur after initiation of ULORIC due to changing serum uric acid levels resulting in mobilization of urate from tissue deposits. Flare prophylaxis with a non-steroidal anti-inflammatory drug (NSAID) or colchicine is recommended upon initiation of ULORIC. Prophylactic therapy may be beneficial for up to six months [see Clinical Studies (14.1) ] .
If a gout flare occurs during ULORIC treatment, ULORIC need not be discontinued. The gout flare should be managed concurrently, as appropriate for the individual patient [see Warnings and Precautions (5.2) ] .
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS 40 mg tablets, light green to green, round, debossed with "TAP" and "40" 80 mg tablets, light green to green, teardrop shaped, debossed with "TAP" and "80" Tablet: 40 mg, 80 mg. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS ULORIC is contraindicated in patients being treated with azathioprine or mercaptopurine [see Drug Interactions (7) ] . ULORIC is contraindicated in patients being treated with azathioprine or mercaptopurine. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Gout Flares : An increase in gout flares is frequently observed after initiation of ULORIC. If a gout flare occurs during treatment, ULORIC need not be discontinued. Prophylactic therapy (i.e., non-steroidal anti-inflammatory drug or colchicine) upon initiation of treatment may be beneficial for up to six months.
( 2.4 , 5.2 ) Hepatic Effects : Cases of hepatic failure, some fatal, have been reported. If liver injury is detected, promptly interrupt ULORIC and treat cause, if possible, to resolution or stabilization. Permanently discontinue ULORIC if liver injury is confirmed, and no alternate etiology can be found.
( 5.3 ) Serious Skin Reactions : Serious skin and hypersensitivity reactions, including Stevens-Johnson Syndrome, drug reaction with eosinophilia and systemic symptoms and toxic epidermal necrolysis have been reported in patients taking ULORIC. Discontinue ULORIC if serious skin reactions are suspected. ( 5.4 )
5.1Cardiovascular Death In a cardiovascular (CV) outcome study, gout patients with established CV disease treated with ULORIC had a higher rate of CV death compared to those treated with allopurinol. Sudden cardiac death was the most common cause of adjudicated CV deaths, 2.7% in the ULORIC group (83 of 3,098) as compared to 1.8% in the allopurinol group (56 of 3,092). ULORIC was similar to allopurinol for nonfatal myocardial infarction (MI), nonfatal stroke and unstable angina with urgent coronary revascularization [see Clinical Studies (14.2) ] .
Because of the increased risk of CV death, ULORIC should only be used in patients who have an inadequate response to a maximally titrated dose of allopurinol, who are intolerant to allopurinol, or for whom treatment with allopurinol is not advisable [see Indications and Usage(1) ] . Consider the risks and benefits of ULORIC when deciding to prescribe or continue patients on ULORIC. Consider use of prophylactic low-dose aspirin therapy in patients with a history of CV disease.
Monitor patients for the development of CV events. Inform patients about the symptoms of serious CV events and the steps to take if they occur.
5.2Gout Flares After initiation of ULORIC, an increase in gout flares is frequently observed. This increase is due to reduction in serum uric acid levels, resulting in mobilization of urate from tissue deposits. In order to prevent gout flares when ULORIC is initiated, concurrent prophylactic treatment with an NSAID or colchicine is recommended [see Dosage and Administration (2.4) ].
5.3Hepatic Effects Cases of fatal and nonfatal hepatic failure in patients taking ULORIC have been reported. During randomized controlled studies, transaminase elevations greater than three times the upper limit of normal (ULN) were observed (AST: 2%, 2%, and ALT: 3%, 2% in ULORIC and allopurinol-treated patients, respectively). No dose-effect relationship for these transaminase elevations was noted [see Clinical Pharmacology (12.3) ] .
Obtain a liver test panel (serum alanine aminotransferase [ALT], aspartate aminotransferase [AST], alkaline phosphatase, and total bilirubin) as a baseline before initiating ULORIC. Measure liver tests promptly in patients who report symptoms that may indicate liver injury, including fatigue, anorexia, right upper abdominal discomfort, dark urine or jaundice. In this clinical context, if the patient presents abnormal liver tests (ALT or AST greater than three times the upper limit of the reference range), interrupt ULORIC treatment while investigating the probable cause.
Permanently discontinue ULORIC if liver injury is confirmed, and no alternate etiology can be found. Permanently discontinue ULORIC in patients who have serum ALT or AST greater than three times the reference range with serum total bilirubin greater than two times the reference range without alternative etiologies because they are at risk for severe drug-induced liver injury. For patients with lesser elevations of serum ALT or bilirubin and wit… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described elsewhere in the prescribing information: Cardiovascular Death [see Warnings and Precautions (5.1) ] Hepatic Effects [see Warnings and Precautions (5.3) ] Serious Skin Reactions [see Warnings and Precautions (5.4) ] Adverse reactions in ≥ 1% of patients treated with ULORIC are liver function abnormalities, nausea, arthralgia, and rash. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Takeda Pharmaceuticals America, Inc. at 1-877-TAKEDA-7 (1-877-825-3327) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. In Phase 2 and 3 clinical studies, a total of 2757 patients with hyperuricemia and gout were treated with ULORIC 40 mg or 80 mg daily. For ULORIC 40 mg, 559 patients were treated for ≥6 months.
For ULORIC 80 mg, 1377 patients were treated for ≥6 months, 674 patients were treated for ≥1 year and 515 patients were treated for ≥2 years. In the CARES study, a total of 3098 patients were treated with ULORIC 40 mg or 80 mg daily; of these, 2155 patients were treated for ≥1 year and 1539 were treated for ≥2 years [see Clinical Studies (14.2) ] . Most Common Adverse Reactions In three randomized, controlled clinical studies (Studies 1, 2 and 3), which were 6 to 12 months in duration, the following adverse reactions were reported by the treating physician as related to study drug.
Table 1 summarizes adverse reactions reported at a rate of at least 1% in ULORIC treatment groups and at least 0.5% greater than placebo. Table 1: Adverse Reactions Occurring in ≥1% of Patients Treated with ULORIC and at Least 0.5% Greater than in Patients Receiving Placebo in Controlled Studies Placebo ULORIC allopurinol Of the patients who received allopurinol, 10 received 100 mg, 145 received 200 mg, and 1122 received 300 mg, based on level of renal impairment. Adverse Reactions (N=134) 40 mg daily (N=757) 80 mg daily (N=1279) (N=1277) Liver Function Abnormalities 0.7% 6.6% 4.6% 4.2% Nausea 0.7% 1.1% 1.3% 0.8% Arthralgia 0% 1.1% 0.7% 0.7% Rash 0.7% 0.5% 1.6% 1.6% The most common adverse reaction leading to discontinuation from therapy was liver function abnormalities in 1.8% of ULORIC 40 mg, 1.2% of ULORIC 80 mg, and in 0.9% of patients treated with allopurinol.
In addition to the adverse reactions presented in Table 1, dizziness was reported in more than 1% of patients treated with ULORIC although not at a rate more than 0.5% greater than placebo. In the CARES study, liver function abnormalities and diarrhea were reported in more than 1% of patients treated with ULORIC, although not at a rate more than 0.5% greater than allopurinol. Less Common Adverse Reactions In clinical studies the following adverse reactions occurred in less than 1% of patients and in more than one subject treated with doses ranging from 40 mg to 240 mg of ULORIC.
This list also includes adverse reactions (less than 1% of patients) associated with organ systems from Warnings and Precautions. Blood and Lymphatic System Disorders: anemia, idiopathic thrombocytopenic purpura, leukocytosis/leukopenia, neutropenia, pancytopenia, splenomegaly, thrombocytopenia. Cardiac Disorders: angina pectoris, atrial fibrillation/flutter, cardiac murmur, ECG abnormal, palpitations, sinus bradycardia, tachycardia.
Ear and Labyrinth Disorders: deafness, tinnitus, vertigo. Eye Disorders: vision blurred. Gastrointestinal Disorders: abdominal distention, abdominal pain, constipation, dry mouth, dyspepsia, flatulence, frequent stools, gastritis, gastroesophageal reflux disease, gastrointestinal discomfort, gingival pain, hematemesis, hyperchlorhydria, hematochezia, mouth ulceration, pancreatitis, peptic ulcer, vomiting.
General Disorders and… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Concomitant administration of ULORIC with XO substrate drugs, azathioprine or mercaptopurine could increase plasma concentrations of these drugs resulting in severe toxicity. ( 7 )
7.1Xanthine Oxidase Substrate Drugs ULORIC is an XO inhibitor. Based on a drug interaction study in healthy patients, febuxostat altered the metabolism of theophylline (a substrate of XO) in humans [see Clinical Pharmacology (12.3) ]. Therefore, use with caution when coadministering ULORIC with theophylline.
A drug interaction study of ULORIC and azathioprine, also metabolized by XO, showed an increase in exposure of 6-mercaptopurine which may lead to toxicity [see Clinical Pharmacology (12.3) ] . Drug interaction studies of ULORIC with other drugs that are metabolized by XO (e.g., mercaptopurine) have not been conducted. ULORIC is contraindicated in patients being treated with azathioprine or mercaptopurine [see Contraindications (4) ].
7.2Cytotoxic Chemotherapy Drugs Drug interaction studies of ULORIC with cytotoxic chemotherapy have not been conducted. No data are available regarding the safety of ULORIC during cytotoxic chemotherapy.
7.3In Vivo Drug Interaction Studies Based on drug interaction studies in healthy patients, ULORIC does not have clinically significant interactions with colchicine, naproxen, indomethacin, hydrochlorothiazide, warfarin or desipramine [see Clinical Pharmacology (12.3) ]. Therefore, ULORIC may be used concomitantly with these medications.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Patients with severe hepatic impairment: No studies have been conducted in this patient population. Caution should be exercised in these patients. ( 8.7 ) Patients with secondary hyperuricemia (including patients being treated for Lesch-Nyhan syndrome or malignant disease, or in organ transplant recipients): ULORIC is not recommended for use as no studies have been conducted in this patient population. ( 8.8 )
8.1Pregnancy Risk Summary Limited available data with ULORIC use in pregnant women are insufficient to inform a drug associated risk of adverse developmental outcomes. No adverse developmental effects were observed in embryo-fetal development studies with oral administration of febuxostat to pregnant rats and rabbits during organogenesis at doses that produced maternal exposures up to 40 and 51 times, respectively, the exposure at the maximum recommended human dose (MRHD). No adverse developmental effects were observed in a pre- and postnatal development study with administration of febuxostat to pregnant rats from organogenesis through lactation at an exposure approximately 11 times the MRHD (see Data ) .
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the US general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data Animal Data In an embryo-fetal development study in pregnant rats dosed during the period of organogenesis from gestation Days 7 – 17, febuxostat was not teratogenic and did not affect fetal development or survival at exposures up to approximately 40 times the MRHD (on an AUC basis at maternal oral doses up to 48 mg/kg/day). In an embryo-fetal development study in pregnant rabbits dosed during the period of organogenesis from gestation Days 6 – 18, febuxostat was not teratogenic and did not affect fetal development at exposures up to approximately 51 times the MRHD (on an AUC basis at maternal oral doses up to 48 mg/kg/day).
In a pre- and postnatal development study in pregnant female rats dosed orally from gestation Day 7 through lactation Day 20, febuxostat had no effects on delivery or growth and development of offspring at a dose approximately 11 times the MRHD (on an AUC basis at a maternal oral dose of 12 mg/kg/day). However, increased neonatal mortality and a reduction in neonatal body weight gain were observed in the presence of maternal toxicity at a dose approximately 40 times the MRHD (on an AUC basis at a maternal oral dose of 48 mg/kg/day).
Febuxostat crossed the placental barrier following oral administration to pregnant rats and was detected in fetal tissues.
8.2Lactation Risk Summary There are no data on the presence of febuxostat in human milk, the effects on the breastfed infant, or the effects on milk production. Febuxostat is present in rat milk. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for ULORIC and any potential adverse effects on the breastfed child from ULORIC or from the underlying maternal condition.
Data Animal Data Orally administered febuxostat was detected in the milk of lactating rats at up to approximately 7 times the plasma concentration.
8.4Pediatric Use Safety and effectiveness of ULORIC in pediatric patients have not been established.
8.5Geriatric Use No dose adjustment is necessary in elderly patients. Of the total number of patients in Studies 1, 2, and 3 (clinical studies of ULORIC in the treatment of gout) [see Clinical Studies (14.1) ] , 16% were 65 and over, while 4% were 75 and over. Comparing patients in different age groups, no clinically significant differences in safety or effectiveness were observed but greater sensitivity of some older individuals cannot be ruled out.
The C max and AUC 24 of… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Limited available data with ULORIC use in pregnant women are insufficient to inform a drug associated risk of adverse developmental outcomes. No adverse developmental effects were observed in embryo-fetal development studies with oral administration of febuxostat to pregnant rats and rabbits during organogenesis at doses that produced maternal exposures up to 40 and 51 times, respectively, the exposure at the maximum recommended human dose (MRHD). No adverse developmental effects were observed in a pre- and postnatal development study with administration of febuxostat to pregnant rats from organogenesis through lactation at an exposure approximately 11 times the MRHD (see Data ) .
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the US general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data Animal Data In an embryo-fetal development study in pregnant rats dosed during the period of organogenesis from gestation Days 7 – 17, febuxostat was not teratogenic and did not affect fetal development or survival at exposures up to approximately 40 times the MRHD (on an AUC basis at maternal oral doses up to 48 mg/kg/day). In an embryo-fetal development study in pregnant rabbits dosed during the period of organogenesis from gestation Days 6 – 18, febuxostat was not teratogenic and did not affect fetal development at exposures up to approximately 51 times the MRHD (on an AUC basis at maternal oral doses up to 48 mg/kg/day).
In a pre- and postnatal development study in pregnant female rats dosed orally from gestation Day 7 through lactation Day 20, febuxostat had no effects on delivery or growth and development of offspring at a dose approximately 11 times the MRHD (on an AUC basis at a maternal oral dose of 12 mg/kg/day). However, increased neonatal mortality and a reduction in neonatal body weight gain were observed in the presence of maternal toxicity at a dose approximately 40 times the MRHD (on an AUC basis at a maternal oral dose of 48 mg/kg/day).
Febuxostat crossed the placental barrier following oral administration to pregnant rats and was detected in fetal tissues.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of ULORIC in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use No dose adjustment is necessary in elderly patients. Of the total number of patients in Studies 1, 2, and 3 (clinical studies of ULORIC in the treatment of gout) [see Clinical Studies (14.1) ] , 16% were 65 and over, while 4% were 75 and over. Comparing patients in different age groups, no clinically significant differences in safety or effectiveness were observed but greater sensitivity of some older individuals cannot be ruled out.
The C max and AUC 24 of febuxostat following multiple oral doses of ULORIC in geriatric patients (≥65 years) were similar to those in younger patients (18 to 40 years) [see Clinical Pharmacology (12.3) ].
🆘 Overdosage ▾
10 OVERDOSAGE ULORIC was studied in healthy patients in doses up to 300 mg daily for seven days without evidence of dose-limiting toxicities. No overdose of ULORIC was reported in clinical studies. Patients should be managed by symptomatic and supportive care should there be an overdose.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action ULORIC, a xanthine oxidase inhibitor, achieves its therapeutic effect by decreasing serum uric acid. ULORIC is not expected to inhibit other enzymes involved in purine and pyrimidine synthesis and metabolism at therapeutic concentrations.
12.2Pharmacodynamics Effect on Uric Acid and Xanthine Concentrations In healthy patients, ULORIC resulted in a dose dependent decrease in 24-hour mean serum uric acid concentrations and an increase in 24-hour mean serum xanthine concentrations. In addition, there was a decrease in the total daily urinary uric acid excretion. Also, there was an increase in total daily urinary xanthine excretion.
Percent reduction in 24-hour mean serum uric acid concentrations was between 40% and 55% at the exposure levels of 40 mg and 80 mg daily doses. Effect on Cardiac Repolarization The effect of ULORIC on cardiac repolarization as assessed by the QTc interval was evaluated in normal healthy patients and in patients with gout. ULORIC in doses up to 300 mg daily (3.75 times the maximum recommended daily dosage), at steady-state, did not demonstrate an effect on the QTc interval.
12.3Pharmacokinetics In healthy patients, maximum plasma concentrations (C max ) and AUC of febuxostat increased in a dose proportional manner following single and multiple doses of 10 mg (0.25 times the lowest recommended dosage) to 120 mg (1.5 times the maximum recommended dosage). There is no accumulation when therapeutic doses are administered every 24 hours. Febuxostat has an apparent mean terminal elimination half-life (t 1/2 ) of approximately 5 to 8 hours.
Febuxostat pharmacokinetic parameters for patients with hyperuricemia and gout estimated by population pharmacokinetic analyses were similar to those estimated in healthy patients. Absorption The absorption of radiolabeled febuxostat following oral dose administration was estimated to be at least 49% (based on total radioactivity recovered in urine). Maximum plasma concentrations of febuxostat occurred between 1 and 1.5 hours postdose.
After multiple oral 40 mg and 80 mg once daily doses, C max is approximately 1.6 ± 0.6 mcg/mL (N=30), and 2.6 ± 1.7 mcg/mL (N=227), respectively. Absolute bioavailability of the febuxostat tablet has not been studied. Following multiple 80 mg once daily doses with a high fat meal, there was a 49% decrease in C max and an 18% decrease in AUC, respectively.
However, no clinically significant change in the percent decrease in serum uric acid concentration was observed (58% fed vs 51% fasting). Thus, ULORIC may be taken without regard to food. Concomitant ingestion of an antacid containing magnesium hydroxide and aluminum hydroxide with an 80 mg single dose of ULORIC has been shown to delay absorption of febuxostat (approximately one hour) and to cause a 31% decrease in C max and a 15% decrease in AUC ∞ .
As AUC rather than C max was related to drug effect, change observed in AUC was not considered clinically significant. Therefore, ULORIC may be taken without regard to antacid use. Distribution The mean apparent steady state volume of distribution (V ss /F) of febuxostat was approximately 50 L (CV ~40%).
The plasma protein binding of febuxostat is approximately 99.2% (primarily to albumin), and is constant over the concentration range achieved with 40 mg and 80 mg doses. Metabolism Febuxostat is extensively metabolized by both conjugation via uridine diphosphate glucuronosyltransferase (UGT) enzymes including UGT1A1, UGT1A3, UGT1A9, and UGT2B7 and oxidation via cytochrome P450 (CYP) enzymes including CYP1A2, 2C8 and 2C9 and non-P450 enzymes. The relative contribution of each enzyme isoform in the metabolism of febuxostat is not clear.
The oxidation of the isobutyl side chain leads to the formation of four pharmacologically active hydroxy metabolites, all of which occur in plasma of humans at a much lower extent than febuxostat. In urine and feces, acyl glucuronide metabolites of febuxostat (~35… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action ULORIC, a xanthine oxidase inhibitor, achieves its therapeutic effect by decreasing serum uric acid. ULORIC is not expected to inhibit other enzymes involved in purine and pyrimidine synthesis and metabolism at therapeutic concentrations.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING ULORIC 40 mg tablets are light green to green in color, round, debossed with "TAP" on one side and "40" on the other side and supplied as: NDC Number Size 64764-918-11 Hospital Unit Dose Pack of 100 Tablets 64764-918-30 Bottle of 30 Tablets 64764-918-90 Bottle of 90 Tablets 64764-918-18 Bottle of 500 Tablets ULORIC 80 mg tablets are light green to green in color, teardrop shaped, debossed with "TAP" on one side and "80" on the other side and supplied as: NDC Number Size 64764-677-11 Hospital Unit Dose Pack of 100 Tablets 64764-677-30 Bottle of 30 Tablets 64764-677-13 Bottle of 100 Tablets 64764-677-19 Bottle of 1000 Tablets Protect from light.
Store at 25°C (77°F); excursions permitted to 15° to 30°C (59° to 86°F) [See USP Controlled Room Temperature].
📦 Storage and Handling ▾
Protect from light. Store at 25°C (77°F); excursions permitted to 15° to 30°C (59° to 86°F) [See USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION ULORIC (febuxostat) is a xanthine oxidase inhibitor. The active ingredient in ULORIC is 2-[3-cyano-4-(2-methylpropoxy) phenyl]-4-methylthiazole-5-carboxylic acid, with a molecular weight of 316.38. The empirical formula is C 16 H 16 N 2 O 3 S.
The chemical structure is: Febuxostat is a non-hygroscopic, white crystalline powder that is freely soluble in dimethylformamide; soluble in dimethylsulfoxide; sparingly soluble in ethanol; slightly soluble in methanol and acetonitrile; and practically insoluble in water. The melting range is 205°C to 208°C. ULORIC tablets for oral use contain the active ingredient, febuxostat, and are available in two dosage strengths, 40 mg and 80 mg.
Inactive ingredients include hydroxypropyl cellulose, lactose monohydrate, magnesium stearate, microcrystalline cellulose, silicon dioxide, and sodium croscarmellose. ULORIC tablets are coated with Opadry II, green. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). CV Death Inform patients that gout patients with established CV disease treated with ULORIC had a higher rate of CV death compared to those treated with allopurinol in a CV outcomes study. Inform all patients of the higher rate of CV death with ULORIC compared to allopurinol.
Alert all patients (those with and without CV disease) for the development of signs and symptoms of CV events and to seek medical care promptly should they occur [see Warnings and Precautions (5.1) ] . Gout Flares Inform patients that after initiation of ULORIC an increase in gout flares can occur and that is not reason to stop taking the medication. Instruct patients that it is recommended to initiate and continue gout prophylaxis therapy for six months while taking ULORIC [see Warnings and Precautions (5.2) ] .
Hepatic Effects Inform patients that hepatic effects, including fatal ones, have occurred in patients treated with ULORIC. Instruct them to inform their healthcare provider if they experience liver injury symptoms [see Warnings and Precautions (5.3) ] . Serious Skin Reactions Inform patients that serious skin and hypersensitivity reactions have occurred in patients treated with ULORIC.
Instruct patients to discontinue ULORIC if they develop symptoms of these reactions [see Warnings and Precautions (5.4) ] .
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics In healthy patients, maximum plasma concentrations (C max ) and AUC of febuxostat increased in a dose proportional manner following single and multiple doses of 10 mg (0.25 times the lowest recommended dosage) to 120 mg (1.5 times the maximum recommended dosage). There is no accumulation when therapeutic doses are administered every 24 hours. Febuxostat has an apparent mean terminal elimination half-life (t 1/2 ) of approximately 5 to 8 hours.
Febuxostat pharmacokinetic parameters for patients with hyperuricemia and gout estimated by population pharmacokinetic analyses were similar to those estimated in healthy patients. Absorption The absorption of radiolabeled febuxostat following oral dose administration was estimated to be at least 49% (based on total radioactivity recovered in urine). Maximum plasma concentrations of febuxostat occurred between 1 and 1.5 hours postdose.
After multiple oral 40 mg and 80 mg once daily doses, C max is approximately 1.6 ± 0.6 mcg/mL (N=30), and 2.6 ± 1.7 mcg/mL (N=227), respectively. Absolute bioavailability of the febuxostat tablet has not been studied. Following multiple 80 mg once daily doses with a high fat meal, there was a 49% decrease in C max and an 18% decrease in AUC, respectively.
However, no clinically significant change in the percent decrease in serum uric acid concentration was observed (58% fed vs 51% fasting). Thus, ULORIC may be taken without regard to food. Concomitant ingestion of an antacid containing magnesium hydroxide and aluminum hydroxide with an 80 mg single dose of ULORIC has been shown to delay absorption of febuxostat (approximately one hour) and to cause a 31% decrease in C max and a 15% decrease in AUC ∞ .
As AUC rather than C max was related to drug effect, change observed in AUC was not considered clinically significant. Therefore, ULORIC may be taken without regard to antacid use. Distribution The mean apparent steady state volume of distribution (V ss /F) of febuxostat was approximately 50 L (CV ~40%).
The plasma protein binding of febuxostat is approximately 99.2% (primarily to albumin), and is constant over the concentration range achieved with 40 mg and 80 mg doses. Metabolism Febuxostat is extensively metabolized by both conjugation via uridine diphosphate glucuronosyltransferase (UGT) enzymes including UGT1A1, UGT1A3, UGT1A9, and UGT2B7 and oxidation via cytochrome P450 (CYP) enzymes including CYP1A2, 2C8 and 2C9 and non-P450 enzymes. The relative contribution of each enzyme isoform in the metabolism of febuxostat is not clear.
The oxidation of the isobutyl side chain leads to the formation of four pharmacologically active hydroxy metabolites, all of which occur in plasma of humans at a much lower extent than febuxostat. In urine and feces, acyl glucuronide metabolites of febuxostat (~35% of the dose), and oxidative metabolites, 67M-1 (~10% of the dose), 67M-2 (~11% of the dose), and 67M-4, a secondary metabolite from 67M-1 (~14% of the dose), appeared to be the major metabolites of febuxostat in vivo . Elimination Febuxostat is eliminated by both hepatic and renal pathways.
Following an 80 mg oral dose of 14 C-labeled febuxostat, approximately 49% of the dose was recovered in the urine as unchanged febuxostat (3%), the acyl glucuronide of the drug (30%), its known oxidative metabolites and their conjugates (13%), and other unknown metabolites (3%). In addition to the urinary excretion, approximately 45% of the dose was recovered in the feces as the unchanged febuxostat (12%), the acyl glucuronide of the drug (1%), its known oxidative metabolites and their conjugates (25%), and other unknown metabolites (7%).
The apparent mean terminal elimination half-life (t 1/2 ) of febuxostat was approximately 5 to 8 hours. Specific Populations Geriatric Patients The C max and AUC of febuxostat and its metabolites following multiple oral doses of ULORIC in geriatric patients (≥65 years) were similar to those in younger patients (18 to 40 years… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Effect on Uric Acid and Xanthine Concentrations In healthy patients, ULORIC resulted in a dose dependent decrease in 24-hour mean serum uric acid concentrations and an increase in 24-hour mean serum xanthine concentrations. In addition, there was a decrease in the total daily urinary uric acid excretion. Also, there was an increase in total daily urinary xanthine excretion.
Percent reduction in 24-hour mean serum uric acid concentrations was between 40% and 55% at the exposure levels of 40 mg and 80 mg daily doses. Effect on Cardiac Repolarization The effect of ULORIC on cardiac repolarization as assessed by the QTc interval was evaluated in normal healthy patients and in patients with gout. ULORIC in doses up to 300 mg daily (3.75 times the maximum recommended daily dosage), at steady-state, did not demonstrate an effect on the QTc interval.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES A serum uric acid level of less than 6 mg/dL is the goal of antihyperuricemic therapy and has been established as appropriate for the treatment of gout.
14.1Management of Hyperuricemia in Gout The efficacy of ULORIC was demonstrated in three randomized, double-blind, controlled trials in patients with hyperuricemia and gout. Hyperuricemia was defined as a baseline serum uric acid level ≥8 mg/dL. Study 1 (NCT00430248) randomized patients to: ULORIC 40 mg daily, ULORIC 80 mg daily, or allopurinol (300 mg daily for patients with estimated creatinine clearance (Cl cr ) ≥60 mL/min or 200 mg daily for patients with estimated Cl cr ≥30 mL/min and ≤59 mL/min).
The duration of Study 1 was six months. Study 2 (NCT00174915) randomized patients to: placebo, ULORIC 80 mg daily, ULORIC 120 mg daily, ULORIC 240 mg daily or allopurinol (300 mg daily for patients with a baseline serum creatinine ≤1.5 mg/dL or 100 mg daily for patients with a baseline serum creatinine greater than 1.5 mg/dL and ≤2 mg/dL). The duration of Study 2 was six months.
Study 3 (NCT00102440), a year study, randomized patients to: ULORIC 80 mg daily, ULORIC 120 mg daily, or allopurinol 300 mg daily. Patients who completed Study 2 and Study 3 were eligible to enroll in a Phase 3 long-term extension study in which patients received treatment with ULORIC for over three years. In all three studies, patients received naproxen 250 mg twice daily or colchicine 0.6 mg once or twice daily for gout flare prophylaxis.
In Study 1 the duration of prophylaxis was six months; in Study 2 and Study 3 the duration of prophylaxis was eight weeks. The efficacy of ULORIC was also evaluated in a 4-week dose ranging study which randomized patients to: placebo, ULORIC 40 mg daily, ULORIC 80 mg daily, or ULORIC 120 mg daily. Patients who completed this study were eligible to enroll in a long-term extension study in which patients received treatment with ULORIC for up to five years.
Patients in these studies were representative of the patient population for which ULORIC use is intended. Table 2 summarizes the demographics and baseline characteristics for the patients enrolled in the studies. Table 2: Patient Demographics and Baseline Characteristics in Study 1, Study 2, and Study 3 Male 95% Race: Caucasian 80% African American 10% Ethnicity: Hispanic or Latino 7% Alcohol User 67% Mild to Moderate Renal Insufficiency (percent with estimated Cl cr less than 90 mL/min) 59% History of Hypertension 49% History of Hyperlipidemia 38% BMI ≥30 kg/m 2 63% Mean BMI 33 kg/m 2 Baseline sUA ≥10 mg/dL 36% Mean baseline sUA 9.7 mg/dL Experienced a gout flare in previous year 85% Serum Uric Acid Level less than 6 mg/dL at Final Visit ULORIC 80 mg was superior to allopurinol in lowering serum uric acid to less than 6 mg/dL at the final visit.
ULORIC 40 mg daily, although not superior to allopurinol, was effective in lowering serum uric acid to less than 6 mg/dL at the final visit (Table 3) . Table 3: Proportion of Patients with Serum Uric Acid Levels less than 6 mg/dL at Final Visit Difference in Proportion (95% CI) Study Randomization was balanced between treatment groups, except in Study 2 in which twice as many patients were randomized to each of the active treatment groups compared to placebo. ULORIC 40 mg daily ULORIC 80 mg daily allopurinol Placebo ULORIC 40 mg vs allopurinol ULORIC 80 mg vs allopurinol Study 1 (6 months) (N=2268) 45% 67% 42% 3% (-2%, 8%) 25% (20%, 30%) Study 2 (6 months) (N=643) 72% 39% 1% 33% (26%, 42%) Study 3 (12 months) (N=491) 74% 36% 38% (30%, 46%) In 76% of ULORIC 80 mg patients, reduction in serum uric acid levels to less than 6 mg/dL was noted by the Week 2 visit.
Average serum uric acid levels were maintained at 6 mg/dL or below throughout treatment in 83% of these patients. In all treatment groups, fewer patients with higher baseline serum urate levels (≥10 mg/dL) and/or tophi achieved the goal of lowering serum uric acid to less than 6 mg/dL at the final vis… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Two-year carcinogenicity studies were conducted in F344 rats and B6C3F1 mice. Increased transitional cell papilloma and carcinoma of the urinary bladder was observed at 24 mg/kg (25 times the MRHD on an AUC basis and 18.75 mg/kg (12.5 times the MRHD on an AUC basis) in male rats and female mice, respectively. The urinary bladder neoplasms were secondary to calculus formation in the kidney and urinary bladder.
Febuxostat showed a positive clastogenic response in a chromosomal aberration assay in a Chinese hamster lung fibroblast cell line with and without metabolic activation in vitro . Febuxostat was negative in the following genotoxicity assays: the in vitro Ames assay, in vitro chromosomal aberration assay in human peripheral lymphocytes, the L5178Y mouse lymphoma cell line assay, the in vivo mouse micronucleus assay, and the rat unscheduled DNA synthesis assay. Fertility and reproductive performance were unaffected in male or female rats that received febuxostat at oral doses up to 48 mg/kg/day (approximately 31 and 40 times the MRHD on an AUC basis in males and females respectively).
13.2Animal Toxicology A 12-month toxicity study in beagle dogs showed deposition of xanthine crystals and calculi in kidneys at 15 mg/kg (approximately 4 times the MRHD on an AUC basis). A similar effect of calculus formation was noted in rats in a 6-month study due to deposition of xanthine crystals at 48 mg/kg (approximately 31 and 40 times the MRHD on an AUC basis in males and females respectively).
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Two-year carcinogenicity studies were conducted in F344 rats and B6C3F1 mice. Increased transitional cell papilloma and carcinoma of the urinary bladder was observed at 24 mg/kg (25 times the MRHD on an AUC basis and 18.75 mg/kg (12.5 times the MRHD on an AUC basis) in male rats and female mice, respectively. The urinary bladder neoplasms were secondary to calculus formation in the kidney and urinary bladder.
Febuxostat showed a positive clastogenic response in a chromosomal aberration assay in a Chinese hamster lung fibroblast cell line with and without metabolic activation in vitro . Febuxostat was negative in the following genotoxicity assays: the in vitro Ames assay, in vitro chromosomal aberration assay in human peripheral lymphocytes, the L5178Y mouse lymphoma cell line assay, the in vivo mouse micronucleus assay, and the rat unscheduled DNA synthesis assay. Fertility and reproductive performance were unaffected in male or female rats that received febuxostat at oral doses up to 48 mg/kg/day (approximately 31 and 40 times the MRHD on an AUC basis in males and females respectively).
📄 Patient Package Insert ▾
This Medication Guide has been approved by the U.S. Food and Drug Administration ULR015 R10 Revised: April 2023 MEDICATION GUIDE ULORIC (Ū–'lor–ik) (febuxostat) tablets, for oral use Read the Medication Guide that comes with ULORIC before you start taking it and each time you get a refill. There may be new information.
The Medication Guide does not take the place of talking with your doctor about your medical condition or your treatment. What is the most important information that I should know about ULORIC? ULORIC may cause serious side effects, including: Heart-related deaths.
Call your doctor or get emergency medical help right away if you have any of the following symptoms, especially if they are new, worse, or worry you: chest pain shortness of breath or trouble breathing dizziness, fainting or feeling lightheaded rapid or irregular heartbeat numbness or weakness on one side of your body slurring of speech sudden blurry vision or sudden severe headache What is ULORIC? ULORIC is a prescription medicine called a xanthine oxidase (XO) inhibitor used to lower blood uric acid levels in adult patients with gout when allopurinol has not worked well enough or when allopurinol is not right for you.
ULORIC is not for use in people who do not have symptoms of high blood uric acid levels. It is not known if ULORIC is safe and effective in children. Who should not take ULORIC?
Do not take ULORIC if you: take azathioprine (Azasan, Imuran) take mercaptopurine (Purinethol, Purixan) What should I tell my doctor before taking ULORIC? Before taking ULORIC tell your doctor about all of your medical conditions, including if you: have taken allopurinol and what happened to you while you were taking it. have a history of heart disease or stroke. have liver or kidney problems. are pregnant or plan to become pregnant. It is not known if ULORIC will harm your unborn baby.
Talk with your doctor if you are pregnant or plan to become pregnant. are breastfeeding or plan to breastfeed. It is not known if ULORIC passes into your breast milk. You and your doctor should decide if you should take ULORIC while breastfeeding.
Tell your doctor about all the medicines you take , including prescription and over-the-counter medicines, vitamins, and herbal supplements. ULORIC may affect the way other medicines work, and other medicines may affect how ULORIC works. Know the medicines you take.
Keep a list of them to show your doctor and pharmacist when you get a new medicine. How should I take ULORIC? Take ULORIC exactly as your doctor tells you to take it.
ULORIC can be taken with or without food. ULORIC can be taken with antacids. Your gout may get worse (flare) when you start taking ULORIC.
Do not stop taking ULORIC because you have a flare. Your doctor may do certain tests while you take ULORIC. What are the possible side effects of ULORIC?
ULORIC may cause serious side effects, including: Heart problems. See " What is the most important information I should know about ULORIC? " . Gout Flares.
Gout flares can happen when you start taking ULORIC. Your doctor may give you other medicines to help prevent your gout flares. Liver problems.
Liver problems can happen in people who take ULORIC. Your doctor may do blood tests to check how well your liver is working before and during your treatment with ULORIC. Tell your doctor if you get any of the following signs or symptoms of liver problems: fatigue loss of appetite for several days or longer pain, aching, or tenderness on the right side of your stomach-area dark or "tea-colored" urine your skin or the white part of your eyes turns yellow (jaundice) Severe skin and allergic reactions.
Serious skin and allergic reactions that may affect different parts of the body such as your liver, kidneys, heart or lungs, can happen in people who take ULORIC. Call your doctor right away or get emergency medical help if you have any of the following symptoms: rash red and painful skin severe skin blisters peeling skin sores around… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
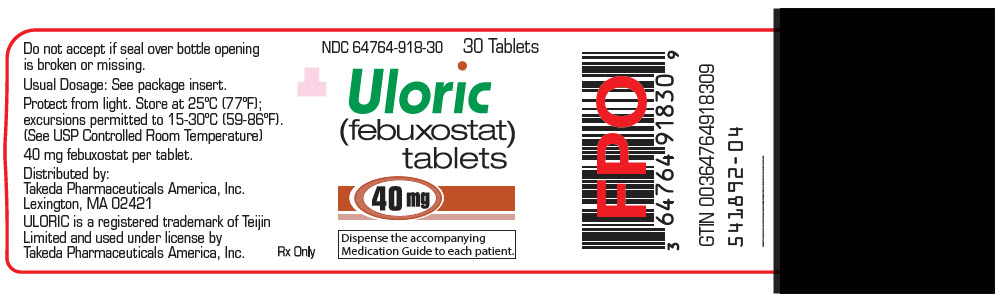
PRINCIPAL DISPLAY PANEL - 40 mg Tablet Bottle Label NDC 64764-918-30 30 Tablets Uloric (febuxostat) tablets 40 mg Dispense the accompanying Medication Guide to each patient. PRINCIPAL DISPLAY PANEL - 40 mg Tablet Bottle Label
PRINCIPAL DISPLAY PANEL - 80 mg Tablet Bottle Label NDC 64764-677-30 30 Tablets Uloric (febuxostat) tablets 80 mg Dispense the accompanying Medication Guide to each patient. PRINCIPAL DISPLAY PANEL - 80 mg Tablet Bottle Label
Medicaid utilization by pack size
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |