
Niacin 500 mg Tablet, Extended Release, 90-count
Other active recalls for Niacin (different manufacturers) — 4 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Nicotinic Acid class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Niacin is used with diet changes (restriction of cholesterol and fat intake) to reduce the amount of cholesterol (a fat-like substance) and other fatty substances in your blood and to increase the amount of high density lipoprotein (HDL; ''good cholesterol''). Niacin can be used in a number of situations including the following: alone or in combination with other medications, such as HMG-CoA inhibitors (statins) or bile acid-binding resins; to decrease the risk of another heart attack in patients with high cholesterol who have had a heart attack; to prevent worsening of atherosclerosis (b...
Read the full MedlinePlus article ↗- Yes, flushing — redness, warmth, tingling, or itching of the skin — is actually the most common side effect of niacin, and it's completely expected, especially when you first start...
- Why is my face turning red after I take niacin? Is that normal?
- Your doctor may prescribe them together, but you do need to be aware of one important risk: combining niacin with a statin raises your chances of muscle damage — a condition called...
- I take a statin for my cholesterol. Is it safe to take niacin at the same time?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Niacin (prescription drug) — tap one for details:
Niacin (prescription drug) may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII H77VEI93A8
A synthetic yellow dye used to color medications. It helps identify the drug and make it visually distinctive, with no effect on how the medicine works.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII ZYD53NBL45
Hydroxyethyl cellulose is a plant-based thickening agent derived from cellulose. It helps control the texture and consistency of liquid or semi-solid medicines, and may also help keep ingredients evenly mixed throughout the product.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII B697894SGQ
Polyethylene glycol 400 is a clear, thick liquid made from petroleum-derived polymers. It acts as a solvent and humectant in medicines, helping dissolve active ingredients and retain moisture in the formulation.
-
UNII 4ELV7Z65AP
Stearic acid is a fatty acid derived from plant or animal sources. It acts as a binder and lubricant in tablets and capsules, helping them hold together and flow smoothly during manufacturing.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.170 | $15.27 / 90 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.3763 | $33.87 / 90 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.3550 | $31.95 / 90 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Niacin 500 mg 33342-0187-10 | Macleods | 90 tablets | $0.170 | AB | Availability likely | — |
| Niacin 500 mg 50268-0584-13 | AvPAK | 1 tablet | $0.170 | AB | Availability likely | — |
| Niacin 500 mg 62135-0497-90 | Chartwell | 90 tablets | $0.170 | AB | Availability likely | — |
| Niacin 500 mgthis 65162-0321-09 | Amneal | 90 tablets | $0.170 | AB | Availability likely | — |
| Niacin 500 mg 47335-0539-08 | Sun | 100 tablets | — | AB | FDA listed | — |
| Niacin 500 mg 51407-0267-90 | Golden | 90 tablets | — | AB | FDA listed | — |
| Niacin 500 mg 59651-0018-05 | Aurobindo | 500 tablets | — | AB | FDA listed | — |
| Niacin 500 mg 62175-0320-43 | Lannett | 1000 tablets | — | AB | FDA listed | — |
| Niacin 500 mg 70752-0295-09 | QUAGEN | 90 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
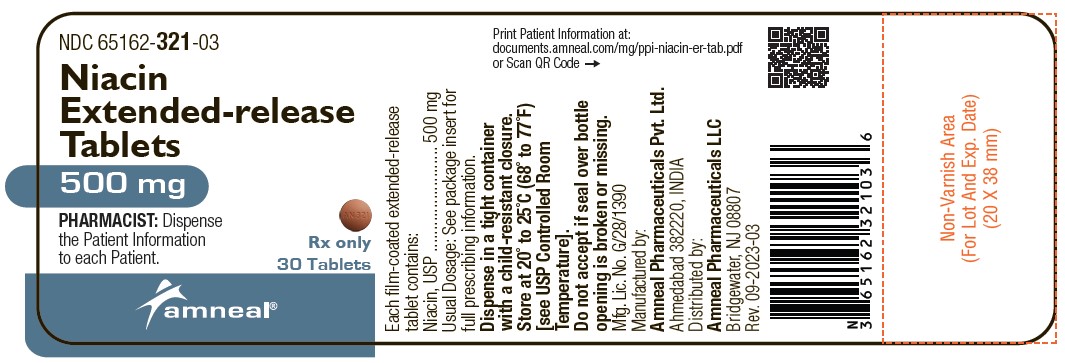
| 65162-0321-03 | 30 TABLET, EXTENDED RELEASE in 1 BOTTLE (65162-321-03) | — | — | 2015-07-27 | Active |
| 65162-0321-09 You're viewing this | 90 TABLET, EXTENDED RELEASE in 1 BOTTLE (65162-321-09) | $0.1697 / ea | $15.27 | 2015-07-27 | Active |
| 65162-0321-50 | 500 TABLET, EXTENDED RELEASE in 1 BOTTLE (65162-321-50) | — | — | 2015-07-27 | Active |
You're viewing one of 3 pack sizes for this product.
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 65162-0321-09?
What is the difference between NDC 65162-0321-09 and NDC 65162-0321-03?
What NDC number is used to bill for this package of Niacin 500 mg Tablet, Extended Release?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Therapy with lipid-altering agents should be only one component of multiple risk factor intervention in individuals at significantly increased risk for atherosclerotic vascular disease due to hyperlipidemia. Niacin therapy is indicated as an adjunct to diet when the response to a diet restricted in saturated fat and cholesterol and other nonpharmacologic measures alone has been inadequate. Niacin extended-release tablets are indicated to reduce elevated TC, LDL-C, Apo B and TG levels, and to increase HDL-C in patients with primary hyperlipidemia and mixed dyslipidemia.
In patients with a history of myocardial infarction and hyperlipidemia, niacin is indicated to reduce the risk of recurrent nonfatal myocardial infarction. In patients with a history of coronary artery disease (CAD) and hyperlipidemia, niacin, in combination with a bile acid binding resin, is indicated to slow progression or promote regression of atherosclerotic disease. Niacin extended-release tablets in combination with a bile acid binding resin is indicated to reduce elevated TC and LDL-C levels in adult patients with primary hyperlipidemia.
Niacin is also indicated as adjunctive therapy for treatment of adult patients with severe hypertriglyceridemia who present a risk of pancreatitis and who do not respond adequately to a determined dietary effort to control them. Limitations of Use Addition of niacin extended-release tablets did not reduce cardiovascular morbidity or mortality among patients treated with simvastatin in a large, randomized controlled trial (AIM-HIGH) [see Warnings and Precautions (5.1) ] . Niacin extended-release tablets contain extended-release niacin (nicotinic acid) and are indicated: To reduce elevated TC, LDL-C, Apo B and TG, and to increase HDL-C in patients with primary hyperlipidemia and mixed dyslipidemia.
( 1 ) To reduce the risk of recurrent nonfatal myocardial infarction in patients with a history of myocardial infarction and hyperlipidemia. ( 1 ) In combination with a bile acid binding resin: Slows progression or promotes regression of atherosclerotic disease in patients with a history of coronary artery disease (CAD) and hyperlipidemia. ( 1 ) As an adjunct to diet to reduce elevated TC and LDL-C in adult patients with primary hyperlipidemia.
( 1 ) To reduce TG in adult patients with severe hypertriglyceridemia. ( 1 ) Limitations of use: Addition of niacin extended-release tablets did not reduce cardiovascular morbidity or mortality among patients treated with simvastatin in a large, randomized controlled trial. ( 5.1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Niacin extended-release tablets should be taken at bedtime with a low-fat snack. ( 2.1 ) Dose range: 500 mg to 2,000 mg once daily. ( 2.1 ) Therapy with niacin extended-release tablets must be initiated at 500 mg at bedtime in order to reduce the incidence and severity of side effects which may occur during early therapy and should not be increased by more than 500 mg in any 4-week period.
(2.1 ) Maintenance dose: 1,000 to 2,000 mg once daily. ( 2.2 ) Doses greater than 2,000 mg daily are not recommended. ( 2.2 )
2.1Initial Dosing Niacin extended-release tablets should be taken at bedtime, after a low-fat snack, and doses should be individualized according to patient response. Therapy with niacin extended-release tablets must be initiated at 500 mg at bedtime in order to reduce the incidence and severity of side effects which may occur during early therapy. The recommended dose escalation is shown in Table 1 below.
Table 1. Recommended Dosing Week(s) Daily dose Niacin Extended-Release Tablets Dosage INITIAL TITRATION 1 to 4 500 mg 1 Niacin extended-release tablet 500 mg at bedtime SCHEDULE 5 to 8 1,000 mg 1 Niacin extended-release tablet 1,000 mg or 2 Niacin extended-release tablets 500 mg at bedtime * 1,500 mg 3 Niacin extended-release tablets 500 mg at bedtime * 2,000 mg 2 Niacin extended-release tablets 1,000 mg or 4 Niacin extended-release tablets 500 mg at bedtime * After Week 8, titrate to patient response and tolerance.
If response to 1,000 mg daily is inadequate, increase dose to 1,500 mg daily; may subsequently increase dose to 2,000 mg daily. Daily dose should not be increased more than 500 mg in a 4-week period, and doses above 2,000 mg daily are not recommended. Women may respond at lower doses than men.
2.2Maintenance Dose The daily dosage of niacin extended-release tablets should not be increased by more than 500 mg in any 4–week period. The recommended maintenance dose is 1,000 mg (two 500 mg tablets or one 1,000 mg tablet) to 2,000 mg (two 1,000 mg tablets or four 500 mg tablets) once daily at bedtime. Doses greater than 2,000 mg daily are not recommended.
Women may respond at lower niacin extended-release tablets doses than men [see Clinical Studies (14.2) ] . Single-dose bioavailability studies have demonstrated that two of the 500 mg and one of the 1,000 mg tablet strengths are interchangeable but three of the 500 mg and two of the 750 mg tablet strengths are not interchangeable. Flushing of the skin [see Adverse Reactions (6.1) ] may be reduced in frequency or severity by pretreatment with aspirin (up to the recommended dose of 325 mg taken 30 minutes prior to niacin extended-release tablets dose).
Tolerance to this flushing develops rapidly over the course of several weeks. Flushing, pruritus, and gastrointestinal distress are also greatly reduced by slowly increasing the dose of niacin and avoiding administration on an empty stomach. Concomitant alcoholic, hot drinks or spicy foods may increase the side effects of flushing and pruritus and should be avoided around the time of niacin extended-release tablets ingestion.
Equivalent doses of niacin extended-release tablets should not be substituted for sustained-release (modified-release, timed-release) niacin preparations or immediate-release (crystalline) niacin [see Warnings and Precautions (5) ] . Patients previously receiving other niacin products should be started with the recommended niacin extended-release tablets titration schedule (see Table 1), and the dose should subsequently be individualized based on patient response. If niacin extended-release tablets therapy is discontinued for an extended period, reinstitution of therapy should include a titration phase (see Table 1).
Niacin extended-release tablets should be taken whole and should not be broken, crushed or chewed before swallowing.
2.3Dosage in Patients with Renal or Hepatic Impairment Use of niacin extended-release tablets in patients with renal or hepatic imp…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS 500 mg light orange to orange colored, round shaped, film-coated tablets debossed with ‘AN 321’ on one side and plain on the other side. 1000 mg light orange to orange colored, capsule shaped, film-coated tablets debossed with ‘AN 323’ on one side and plain on the other side. Unscored film-coated tablets for oral administration: 500 mg and 1,000 mg niacin extended-release. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Niacin extended-release tablets are contraindicated in the following conditions: Active liver disease or unexplained persistent elevations in hepatic transaminases [see Warnings and Precautions (5.3) ] Patients with active peptic ulcer disease Patients with arterial bleeding Hypersensitivity to niacin or any component of this medication [see Adverse Reactions (6.1) ] Active liver disease, which may include unexplained persistent elevations in hepatic transaminase levels. ( 4 , 5.3 ) Active peptic ulcer disease.
( 4 ) Arterial bleeding. ( 4 ) Known hypersensitivity to product components. ( 4 , 6.1 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Niacin extended-release preparations should not be substituted for equivalent doses of immediate-release (crystalline) niacin. For patients switching from immediate-release niacin to niacin extended-release, therapy with niacin extended-release should be initiated with low doses (i.e. 500 mg at bedtime) and the niacin extended-release dose should then be titrated to the desired therapeutic response [see Dosage and Administration (2.1) ] .
Caution should also be used when niacin extended-release is used in patients with unstable angina or in the acute phase of an MI, particularly when such patients are also receiving vasoactive drugs such as nitrates, calcium channel blockers, or adrenergic blocking agents. Niacin is rapidly metabolized by the liver, and excreted through the kidneys. Niacin extended-release is contraindicated in patients with significant or unexplained hepatic impairment [see Contraindications (4) and Warnings and Precautions (5.3) ] and should be used with caution in patients with renal impairment.
Patients with a past history of jaundice, hepatobiliary disease, or peptic ulcer should be observed closely during niacin extended-release therapy. Severe hepatic toxicity has occurred in patients substituting sustained-release niacin for immediate-release niacin at equivalent doses. ( 5.3 ) Myopathy has been reported in patients taking niacin extended-release.
The risk for myopathy and rhabdomyolysis are increased among elderly patients; patients with diabetes, renal failure or uncontrolled hypothyroidism; and patients being treated with a statin. ( 5.2 ) Liver enzyme abnormalities and monitoring: Persistent elevations in hepatic transaminase can occur. Monitor liver enzymes before and during treatment.
( 5.3 ) Use with caution in patients with unstable angina or in the acute phase of an MI. ( 5 ) Niacin extended-release can increase serum glucose levels. Glucose levels should be closely monitored in diabetic or potentially diabetic patients particularly during the first few months of use or dose adjustment.
( 5.4 )
5.1Mortality and Coronary Heart Disease Morbidity Niacin extended-release has not been shown to reduce cardiovascular morbidity or mortality among patients already treated with a statin. The Atherothrombosis Intervention in Metabolic Syndrome with Low HDL/High Triglycerides: Impact on Global Health Outcomes (AIM-HIGH) trial was a randomized placebo-controlled trial of 3,414 patients with stable, previously diagnosed cardiovascular disease. Mean baseline lipid levels were LDL-C 74 mg/dL, HDL-C 35 mg/dL, non-HDL-C 111 mg/dL and median triglyceride level of 163 mg/dL to 177 mg/dL.
Ninety-four percent of patients were on background statin therapy prior to entering the trial. All participants received simvastatin, 40 to 80 mg per day, plus ezetimibe 10 mg per day if needed, to maintain an LDL-C level of 40 mg/dL to 80 mg/dL, and were randomized to receive niacin extended-release 1,500 mg/day to 2,000 mg/day (n = 1,718) or matching placebo (IR Niacin, 100 mg to 150 mg, n = 1,696). On-treatment lipid changes at two years for LDL-C were -12.0% for the simvastatin plus niacin extended-release group and -5.5% for the simvastatin plus placebo group.
HDL-C increased by 25.0% to 42 mg/dL in the simvastatin plus niacin extended-release group and by 9.8% to 38 mg/dL in the simvastatin plus placebo group (P < 0.001). Triglyceride levels decreased by 28.6% in the simvastatin plus niacin extended-release group and by 8.1% in the simvastatin plus placebo group. The primary outcome was an ITT composite of the first study occurrence of coronary heart disease death, nonfatal myocardial infarction, ischemic stroke, hospitalization for acute coronary syndrome or symptom-driven coronary or cerebral revascularization procedures.
The trial was stopped after a mean follow-up period of 3 years owing to a lack of efficacy. The primary outcome occurred in 282 patients in the simvastatin plus niacin extende…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in greater detail in other sections of the labeling: Mortality and Coronary Heart Disease Morbidity [see Warnings and Precautions (5.1) ] Skeletal Muscle (rhabdomyolysis) [see Warnings and Precautions (5.2) ] Liver Dysfunction [see Warnings and Precautions (5.3) ] Laboratory Abnormalities [see Warnings and Precautions (5.4) ] Most common adverse reactions (incidence > 5% and greater than placebo) are flushing, diarrhea, nausea, vomiting, increased cough, and pruritus.
( 6.1 ) Flushing of the skin may be reduced in frequency or severity by pretreatment with aspirin (up to the recommended dose of 325 mg taken 30 minutes prior to niacin extended-release dose). ( 2.2 ) To report SUSPECTED ADVERSE REACTIONS, contact Amneal Pharmaceuticals LLC at 1-877-835-5472 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Studies Experience Because clinical studies are conducted under widely varying conditions, adverse reaction rates observed in the clinical studies of a drug cannot be directly compared to rates in the clinical studies of another drug and may not reflect the rates observed in practice. In the placebo-controlled clinical trials database of 402 patients (age range 21 years to 75 years, 33% women, 89% Caucasians, 7% Blacks, 3% Hispanics, 1% Asians) with a median treatment duration of 16 weeks, 16% of patients on niacin extended-release and 4% of patients on placebo discontinued due to adverse reactions.
The most common adverse reactions in the group of patients treated with niacin extended-release that led to treatment discontinuation and occurred at a rate greater than placebo were flushing (6% vs. 0%), rash (2% vs. 0%), diarrhea (2% vs.
0%), nausea (1% vs. 0%), and vomiting (1% vs. 0%).
The most commonly reported adverse reactions (incidence > 5% and greater than placebo) in the niacin extended-release controlled clinical trial database of 402 patients were flushing, diarrhea, nausea, vomiting, increased cough and pruritus. In the placebo-controlled clinical trials, flushing episodes (i.e., warmth, redness, itching and/or tingling) were the most common treatment-emergent adverse reactions (reported by as many as 88% of patients) for niacin extended-release. Spontaneous reports suggest that flushing may also be accompanied by symptoms of dizziness, tachycardia, palpitations, shortness of breath, sweating, burning sensation/skin burning sensation, chills, and/or edema, which in rare cases may lead to syncope.
In pivotal studies, 6% (14/245) of niacin extended-release patients discontinued due to flushing. In comparisons of immediate-release (IR) niacin and niacin extended-release tablets, although the proportion of patients who flushed was similar, fewer flushing episodes were reported by patients who received niacin extended-release. Following 4 weeks of maintenance therapy at daily doses of 1,500 mg, the incidence of flushing over the 4-week period averaged 8.6 events per patient for IR niacin versus 1.9 following niacin extended-release.
Other adverse reactions occurring in ≥ 5% of patients treated with niacin extended-release and at an incidence greater than placebo are shown in Table 2 below. Table 2. Treatment-Emergent Adverse Reactions by Dose Level in ≥ 5% of Patients and at an Incidence Greater than Placebo; Regardless of Causality Assessment in Placebo-Controlled Clinical Trials Placebo-Controlled Studies Niacin Extended-release Treatment @ Recommended Daily Maintenance Doses † Placebo (n = 157) 500 mg ‡ (n = 87) 1,000 mg (n = 110) 1,500 mg (n = 136) 2,000 mg (n = 95) % % % % % Gastrointestinal Disorders Diarrhea 13 7 10 10 14 Nausea 7 5 6 4 11 Vomiting 4 0 2 4 9 Respiratory Cough, Increased 6 3 2 < 2 8 Skin and Subcutaneous Tissue Disorders Pruritus 2 8 0 3 0 Rash 0 5 5 5 0 Vascular Disorders Flushing & 19 68 69 63 55 Note: Percentages are calculated from the total number of patients in each column. † Adverse reactions are reported at the ini…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Statins: Caution should be used when prescribing niacin with statins as these agents can increase risk of myopathy/rhabdomyolysis. ( 5.2 , 7.1 ) Bile Acid Sequestrants: Bile acid sequestrants have a high niacin-binding capacity and should be taken at least 4 to 6 hours before niacin extended-release administration. ( 7.2 )
7.1Statins Caution should be used when prescribing niacin (≥ 1 gm/day) with statins as these drugs can increase risk of myopathy/rhabdomyolysis [see Warnings and Precautions (5) and Clinical Pharmacology (12.3) ] .
7.2Bile Acid Sequestrants An in vitro study results suggest that the bile acid-binding resins have high niacin binding capacity. Therefore, 4 to 6 hours, or as great an interval as possible, should elapse between the ingestion of bile acid-binding resins and the administration of niacin extended-release [see Clinical Pharmacology (12.3) ] .
7.3Aspirin Concomitant aspirin may decrease the metabolic clearance of nicotinic acid. The clinical relevance of this finding is unclear.
7.4Antihypertensive Therapy Niacin may potentiate the effects of ganglionic blocking agents and vasoactive drugs resulting in postural hypotension.
7.5Other Vitamins or other nutritional supplements containing large doses of niacin or related compounds such as nicotinamide may potentiate the adverse effects of niacin extended-release.
7.6Laboratory Test Interactions Niacin may produce false elevations in some fluorometric determinations of plasma or urinary catecholamines. Niacin may also give false-positive reactions with cupric sulfate solution (Benedict’s reagent) in urine glucose tests.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Discontinue in patients with hyperlipidemia; assess individual risks and benefits in patients with hypertriglyceridemia. ( 8.1 ) Lactation: Advise patients not to breastfeed during treatment. ( 8.2 ) Renal impairment: Niacin extended-release should be used with caution in patients with renal impairment.
( 5 , 8.6 ) Hepatic impairment: Niacin extended-release is contraindicated in active liver disease or significant or unexplained hepatic dysfunction or unexplained elevations of serum transaminases. ( 4 , 5 , 5.3 , 8.7 )
8.1Pregnancy Risk Summary Discontinue niacin extended-release when pregnancy is recognized in patients receiving the drug for the treatment of hyperlipidemia. Assess the individual risks and benefits of continuing niacin extended-release during pregnancy in patients receiving the drug for the treatment of hypertriglyceridemia. Advise patients to inform their healthcare provider of a known or suspected pregnancy.
The potential for embryofetal toxicity with the doses of niacin in niacin extended-release tablets is unknown. The available data on niacin extended-release use in pregnant women are insufficient to evaluate for a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. Animal reproduction studies have not been conducted with niacin or with niacin extended-release tablets.
Treatment of hypercholesterolemia is not generally necessary during pregnancy. Atherosclerosis is a chronic process and the discontinuation of lipid-lowering drugs during pregnancy should have little impact on the outcome of long-term therapy of primary hypercholesterolemia for most patients. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
8.2Lactation Risk Summary Niacin is present in human milk and the amount of niacin increases with maternal supplementation. There is no information on the effects of the doses of niacin in niacin extended-release tablets on the breastfed infant or the effects on milk production. Because of the potential for serious adverse reactions in breastfeeding infants, including hepatotoxicity, advise patients not to breastfeed during treatment with niacin extended-release.
8.4Pediatric Use Safety and effectiveness of niacin therapy in pediatric patients (≤ 16 years) have not been established.
8.5Geriatric Use Of 979 patients in clinical studies of niacin extended-release, 21% of the patients were age 65 and over. No overall differences in safety and effectiveness were observed between these patients and younger patients, and other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out.
8.6Renal Impairment No studies have been performed in this population. Niacin extended-release should be used with caution in patients with renal impairment [see Warnings and Precautions (5) ] .
8.7Hepatic Impairment No studies have been performed in this population. Niacin extended-release should be used with caution in patients with a past history of liver disease and/or who consume substantial quantities of alcohol. Active liver disease, unexplained transaminase elevations and significant or unexplained hepatic dysfunction are contraindications to the use of niacin extended-release [see Contraindications (4) and Warnings and Precautions (5.3) ] .
8.8Gender Data from the clinical trials suggest that women have a greater hypolipidemic response than men at equivalent doses of niacin extended-release.
🆘 Overdosage ▾
10 OVERDOSAGE Supportive measures should be undertaken in the event of an overdose.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The mechanism by which niacin alters lipid profiles has not been well defined. It may involve several actions including partial inhibition of release of free fatty acids from adipose tissue, and increased lipoprotein lipase activity, which may increase the rate of chylomicron triglyceride removal from plasma. Niacin decreases the rate of hepatic synthesis of VLDL and LDL, and does not appear to affect fecal excretion of fats, sterols, or bile acids.
12.3Pharmacokinetics Absorption Due to extensive and saturable first-pass metabolism, niacin concentrations in the general circulation are dose dependent and highly variable. Time to reach the maximum niacin plasma concentrations was about 5 hours following niacin extended-release. To reduce the risk of gastrointestinal (GI) upset, administration of niacin extended-release with a low-fat meal or snack is recommended.
Single-dose bioavailability studies have demonstrated that the 500 mg and 1,000 mg tablet strengths are dosage form equivalent but the 500 mg and 750 mg tablet strengths are not dosage form equivalent. Metabolism The pharmacokinetic profile of niacin is complicated due to extensive first-pass metabolism that is dose-rate specific and, at the doses used to treat dyslipidemia, saturable. In humans, one pathway is through a simple conjugation step with glycine to form nicotinuric acid (NUA).
NUA is then excreted in the urine, although there may be a small amount of reversible metabolism back to niacin. The other pathway results in the formation of nicotinamide adenine dinucleotide (NAD). It is unclear whether nicotinamide is formed as a precursor to, or following the synthesis of, NAD.
Nicotinamide is further metabolized to at least N-methylnicotinamide (MNA) and nicotinamide-N-oxide (NNO). MNA is further metabolized to two other compounds, N-methyl-2-pyridone-5-carboxamide (2PY) and N-methyl-4-pyridone-5-carboxamide (4PY). The formation of 2PY appears to predominate over 4PY in humans.
At the doses used to treat hyperlipidemia, these metabolic pathways are saturable, which explains the nonlinear relationship between niacin dose and plasma concentrations following multiple-dose niacin extended-release administration. Nicotinamide does not have hypolipidemic activity; the activity of the other metabolites is unknown. Elimination Following single and multiple doses, approximately 60% to 76% of the niacin dose administered as niacin extended-release was recovered in urine as niacin and metabolites; up to 12% was recovered as unchanged niacin after multiple dosing.
The ratio of metabolites recovered in the urine was dependent on the dose administered. Pediatric Use No pharmacokinetic studies have been performed in this population (≤ 16 years) [see Use in Specific Populations (8.4) ] . Geriatric Use No pharmacokinetic studies have been performed in this population (> 65 years) [see Use in Specific Populations (8.5) ] .
Renal Impairment No pharmacokinetic studies have been performed in this population. Niacin extended-release should be used with caution in patients with renal disease [see Warnings and Precautions (5) ] . Hepatic Impairment No pharmacokinetic studies have been performed in this population.
Active liver disease, unexplained transaminase elevations and significant or unexplained hepatic dysfunction are contraindications to the use of niacin extended-release [see Contraindications (4) and Warnings and Precautions (5.3) ] . Gender Steady-state plasma concentrations of niacin and metabolites after administration of niacin extended-release tablets are generally higher in women than in men, with the magnitude of the difference varying with dose and metabolite. This gender differences observed in plasma levels of niacin and its metabolites may be due to gender-specific differences in metabolic rate or volume of distribution.
Recovery of niacin and metabolites in urine, however, is generally similar for men and women, in…
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Niacin extended-release tablets USP, 500 mg are supplied as light orange to orange colored, round shaped, film-coated tablets debossed with “AN 321” on one side and plain on the other side. They are available as follows: Bottles of 30: NDC 65162-321-03 Bottles of 90: NDC 65162-321-09 Bottles of 500: NDC 65162-321-50 Niacin extended-release tablets USP, 1000 mg are supplied as light orange to orange colored, capsule shaped, film-coated tablets debossed with “AN 323” on one side and plain on the other side.
They are available as follows: Bottles of 30: NDC 65162-323-03 Bottles of 90: NDC 65162-323-09 Bottles of 500: NDC 65162-323-50 Storage: Store at 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Niacin extended-release tablets, USP contain niacin, USP which at therapeutic doses is an antihyperlipidemic agent. Niacin (nicotinic acid, or 3-pyridinecarboxylic acid) is a white, crystalline powder, very soluble in water, with the following structural formula: Niacin extended-release tablets, USP are unscored, light orange to orange, film-coated tablets for oral administration and are available in two tablet strengths containing 500 mg and 1,000 mg niacin, USP. Niacin extended-release tablets, USP also contain the following inactive ingredients: FD&C yellow #6/sunset yellow FCF aluminum lake, hydroxyethyl cellulose, hypromellose, iron oxide red, iron oxide yellow, polyethylene glycol 400, stearic acid and titanium dioxide.
FDA approved dissolution test specifications differ from USP. 4097803e-figure-01
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION
17.1Patient Counseling Patients should be advised to adhere to their National Cholesterol Education Program (NCEP) recommended diet, a regular exercise program, and periodic testing of a fasting lipid panel. Patients should be advised to inform other healthcare professionals prescribing a new medication that they are taking niacin extended-release. The patient should be informed of the following: Dosing Time Niacin extended-release tablets should be taken at bedtime, after a low-fat snack.
Administration on an empty stomach is not recommended. Tablet Integrity Niacin extended-release tablets should not be broken, crushed or chewed, but should be swallowed whole. Dosing Interruption If dosing is interrupted for any length of time, their physician should be contacted prior to restarting therapy; re-titration is recommended.
Muscle Pain Notify their physician of any unexplained muscle pain, tenderness, or weakness promptly. They should discuss all medication, both prescription and over the counter, with their physician. Flushing Flushing (warmth, redness, itching and/or tingling of the skin) is a common side effect of niacin therapy that may subside after several weeks of consistent niacin extended-release use.
Flushing may vary in severity and is more likely to occur with initiation of therapy, or during dose increases. By dosing at bedtime, flushing will most likely occur during sleep. However, if awakened by flushing at night, the patient should get up slowly, especially if feeling dizzy, feeling faint, or taking blood pressure medications.
Advise patients of the symptoms of flushing and how they differ from the symptoms of a myocardial infarction. Use of Aspirin Medication Taking aspirin (up to the recommended dose of 325 mg) approximately 30 minutes before dosing can minimize flushing. Diet Avoid ingestion of alcohol, hot beverages and spicy foods around the time of taking niacin extended-release to minimize flushing.
Supplements Notify their physician if they are taking vitamins or other nutritional supplements containing niacin or nicotinamide. Dizziness Notify their physician if symptoms of dizziness occur. Diabetics If diabetic, to notify their physician of changes in blood glucose.
Pregnancy Advise patients to inform their healthcare provider of a known or suspected pregnancy to discuss if niacin extended-release should be discontinued [see Use in Specific Populations (8.1) ] . Lactation Advise patients not to breastfeed during treatment with niacin extended-release tablet. Manufactured By: Amneal Pharmaceuticals Pvt.
Ltd. Ahmedabad 382220, INDIA Distributed By: Amneal Pharmaceuticals LLC Bridgewater, NJ 08807 Rev. 12-2025-06