
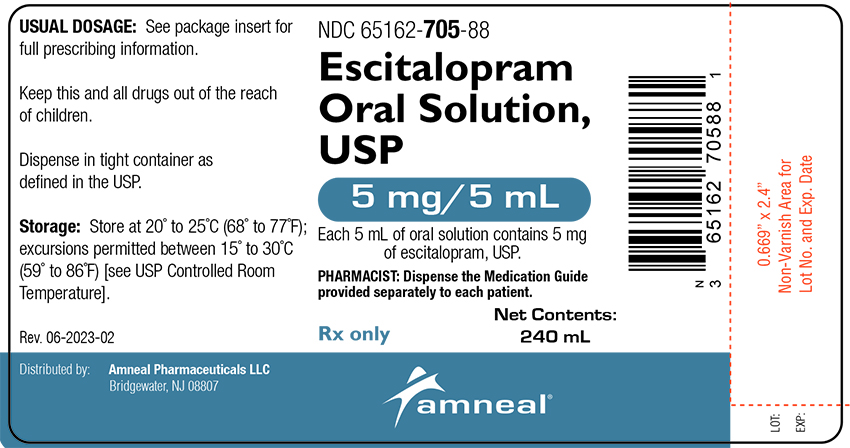
Escitalopram Oxalate 5 mg/5mL Solution, 240 mL — NDC 65162-705-88 (Billing 65162-0705-88)
This is a package of 240 mL of Escitalopram Oxalate 5 mg/5mL Solution from Amneal Pharmaceuticals LLC, marketed since Sep 2011 and currently FDA-listed; retail pharmacies pay about $0.1426 per mL (NADAC). It is this product's only package size.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 051698
- GCN: 19035
- GPI-14 (Medi-Span): 58160034102020
- HICL (First Databank): 024022
- AHFS class code: 28:16.04.20
- RxCUI (RxNorm): 351285
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Serotonin Reuptake Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Escitalopram is used to treat depression and generalized anxiety disorder (GAD; excessive worry and tension that disrupts daily life and lasts for 6 months or longer). Escitalopram is in a class of antidepressants called selective serotonin reuptake inhibitors (SSRIs). It works by increasing the amount of serotonin, a natural substance in the brain that helps maintain mental balance.
Read the full MedlinePlus article ↗- It treats major depressive disorder and generalized anxiety disorder. Age limits depend on the product, so check with me or your prescriber about yours.
- Take it once a day, morning or evening, with or without food. Capsules should be swallowed whole. Follow your prescriber's directions.
- Please don't stop suddenly. Stopping can cause withdrawal-type symptoms. Talk to your prescriber about lowering the dose gradually.
- The most common are nausea, trouble sleeping, sleepiness, tiredness, sweating and sexual side effects such as delayed ejaculation or lower sex drive. Tell us if sexual problems bot...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Escitalopram — tap one for details:
Escitalopram may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.143 | $34.22 / 240 ml |
| Medicaid paysCMS SDUD · 12 mo | $0.2125 | $51.00 / 240 ml |
| Medicare drug plans payPart D · Q2 2026 | $0.2860 | $68.64 / 240 ml |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 65162-0705-88 You're viewing this Main listing | 240 mL in 1 BOTTLE | 2011-09-03 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Escitalopram Oxalate 5 mg/5mL 16571-0769-24 | Rising | 240 ml | $0.143 | AA | Availability likely | — |
| Escitalopram Oxalate 5 mg/5mL 31722-0569-24 | Camber | 240 ml | $0.143 | AA | Availability likely | — |
| escitalopram 5 mg/5mL 33342-0053-28 | Macleods | 240 ml | $0.143 | AA | Availability likely | — |
| Escitalopram Oral Solution 5 mg/5mL 62135-0729-37 | Chartwell | 240 ml | $0.143 | AA | Availability likely | — |
| Escitalopram Oxalate 5 mg/5mLthis 65162-0705-88 | Amneal | 240 ml | $0.143 | AA | Availability likely | — |
| Escitalopram 5 mg/5mL 51672-1348-01 | Sun | 1 bottle | — | — | FDA listed | — |
| Escitalopram Oxalate 5 mg/5mL 65862-0248-24 | Aurobindo | 240 ml | — | AA | FDA listed | — |
| Escitalopram Oral Solution 5 mg/5mL 68999-0729-24 | Chartwell | 10 cups | — | AA | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII XF417D3PSL
Anhydrous citric acid is a sour, crystalline powder derived from citric acid with water removed. In medicines, it acts as a buffer to control pH, adds tartness to improve taste, and helps tablets disintegrate.
-
UNII PDC6A3C0OX
Glycerin is a clear, thick liquid derived from plant oils or fats. It acts as a humectant to retain moisture, a sweetener, and a solvent in medications.
-
UNII 817L1N4CKP
Malic acid is a naturally occurring organic acid found in fruits. It works as a buffer and flavor agent to maintain the medicine's pH balance and add tartness to the product.
-
UNII A2I8C7HI9T
Methylparaben is a preservative derived from benzoic acid that prevents growth of bacteria, fungi, and mold in medicines. It extends the product's shelf life and maintains safety during storage.
-
UNII V95R5KMY2B
Peppermint is a flavoring agent derived from the peppermint plant. It's added to medicines to improve taste and mask bitter or unpleasant flavors, making them easier to take.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII Z8IX2SC1OH
Propylparaben is a chemical preservative used to prevent bacterial and fungal growth in medicines and personal care products. It helps extend shelf life and maintain product safety during storage.
-
UNII 1Q73Q2JULR
Sodium citrate is a salt derived from citric acid. It works as a buffer to maintain the medicine's pH level and may also help improve taste or act as a preservative in the formulation.
-
UNII 506T60A25R
Sorbitol is a natural sugar alcohol derived from glucose. It serves as a sweetener, humectant, and bulking agent in medications to improve taste and help maintain moisture in the product.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
10 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: SUICIDAL THOUGHTS AND BEHAVIORS Antidepressants increased the risk of suicidal thoughts and behaviors in pediatric and young adult patients in short-term studies . Closely monitor all antidepressant-treated patients for clinical worsening, and for emergence of suicidal thoughts and behaviors [see Warnings and Precautions (5.1) ] . Escitalopram oxalate is not approved for use in pediatric patients less than 7 years of age [see Use in Specific Populations (8.4) ] .
WARNING: SUICIDAL THOUGHTS AND BEHAVIORS See full prescribing information for complete boxed warning. Increased risk of suicidal thoughts and behavior in pediatric and young adult patients taking antidepressants. Closely monitor all antidepressant-treated patients for clinical worsening and emergence of suicidal thoughts and behaviors (5.1).
Escitalopram oxalate is not approved for use in pediatric patients less than 7 years of age ( 8.4 ).
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Escitalopram oral solution is indicated for the treatment of: major depressive disorder (MDD) in adults and pediatric patients 12 years of age and older. generalized anxiety disorder (GAD) in adults. Additional pediatric use information is approved for AbbVie Inc.’s LEXAPRO (escitalopram) oral solution. However, due to AbbVie Inc.’s marketing exclusivity rights, this drug product is not labeled with that information.
Escitalopram oral solution is a selective serotonin reuptake inhibitor (SSRI) indicated for the: treatment of major depressive disorder (MDD) in adults and pediatric patients 12 years of age and older. ( 1 ) treatment of generalized anxiety disorder (GAD) in adults. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Indication and Population Recommended Dosage MDD in Adults (2.1) Initial: 10 mg once daily Recommended: 10 mg once daily Maximum: 20 mg once daily MDD in Pediatric Patients 12 years and older (2.1) Initial: 10 mg once daily Recommended: 10 mg once daily Maximum: 20 mg once daily GAD in Adults (2.2) Initial: 10 mg once daily Recommended: 10 mg once daily Maximum: 20 mg once daily No additional benefits were seen at 20 mg once daily. (2.1) Administer once daily, morning or evening, with or without food.
(2.3) Elderly patients: recommended dosage is 10 mg once daily. (2.4) Hepatic impairment: recommended dosage is 10 mg once daily. (2.4 , 8.6 ) When discontinuing escitalopram oral solution, reduce dose gradually whenever possible.
(2.5)
2.1Major Depressive Disorder Adults The recommended dosage of escitalopram oral solution in adults is 10 mg once daily. A fixed-dose trial of escitalopram oral solution demonstrated the effectiveness of both 10 mg and 20 mg of escitalopram oral solution, but failed to demonstrate a greater benefit of 20 mg over 10 mg [see Clinical Studies (14.1) ] . Depending on clinical response and tolerability, dosage may be increased to the maximum recommended dosage of 20 mg once daily at an interval of no less than 1 week.
Pediatric Patients 12 years of age and older The recommended dosage of escitalopram oral solution in pediatric patients 12 years of age and older is 10 mg once daily. Depending on clinical response and tolerability, dosage may be increased to the maximum recommended dosage of 20 mg once daily at an interval of no less than 3 weeks.
2.2Generalized Anxiety Disorder Adults The recommended starting dosage of escitalopram oral solution in adults is 10 mg once daily. Depending on clinical response and tolerability, dosage may be increased to the maximum recommended dosage of 20 mg once daily at an interval of no less than 1 week. Additional pediatric use information is approved for AbbVie Inc.’s LEXAPRO (escitalopram) oral solution.
However, due to AbbVie Inc.’s marketing exclusivity rights, this drug product is not labeled with that information.
2.3Administration Information Administer escitalopram oral solution orally once daily, in the morning or evening, with or without food.
2.4Screen for Bipolar Disorder Prior to Starting Escitalopram Oral Solution Prior to initiating treatment with escitalopram oral solution or another antidepressant, screen patients for a personal family history of bipolar disorder, mania, or hypomania [see Warnings and Precautions (5.5) ] .
2.5Recommended Dosage for Specific Populations The recommended dosage for most elderly patients and patients with hepatic impairment is 10 mg once daily [see Use in Specific Populations (8.5 , 8.6) ] . The recommended dosage for escitalopram oral solution in adults with a creatinine clearance less than 20 mL/minute has not been determined. No dosage adjustment is necessary for patients with mild or moderate renal impairment [see Use in Specific Populations (8.7) ] .
2.6Discontinuation of Treatment with Escitalopram Oral Solution Symptoms associated with discontinuation of escitalopram oral solution and other SSRIs and SNRIs have been reported [see Warnings and Precautions (5.3) ] . Patients should be monitored for these symptoms when discontinuing treatment. A gradual reduction in the dose rather than abrupt cessation is recommended whenever possible.
If intolerable symptoms occur following a decrease in the dose or upon discontinuation of treatment, then resuming the previously prescribed dose may be considered. Subsequently, the physician may continue decreasing the dose but at a more gradual rate.
2.7Switching Patients to or from a Monoamine Oxidase Inhibitor (MAOI) Antidepressant At least 14 days should elapse between discontinuation of an MAOI intended to treat psychiatric disorders and initiation of therapy with escitalopram oral solution. Conversely, at least 14 days should be allowed after s… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Oral Solution Escitalopram oral solution, USP, contains escitalopram oxalate, USP equivalent to 1 mg/mL escitalopram base. Oral solution: 1 mg per mL.
⛔ Contraindications ▾
4 CONTRAINDICATIONS Escitalopram oxalate is contraindicated in patients: taking MAOIs with escitalopram oxalate or within 14 days of stopping treatment with escitalopram oxalate because of an increased risk of serotonin syndrome. The use of escitalopram oxalate within 14 days of stopping an MAOI intended to treat psychiatric disorders is also contraindicated [see Dosage and Administration (2.7) and Warnings and Precautions (5.2) ] . Starting escitalopram oxalate in a patient who is being treated with MAOIs such as linezolid or intravenous methylene blue is also contraindicated because of an increased risk of serotonin syndrome [see Dosage and Administration (2.6) and Warnings and Precautions (5.2) ] . taking pimozide [see Drug Interactions (7) ] . with a hypersensitivity to escitalopram or citalopram or any of the inactive ingredients in escitalopram oral solution.
Do not use MAOIs intended to treat psychiatric disorders with escitalopram oxalate or within 14 days of stopping treatment with escitalopram oxalate. Do not use escitalopram oxalate within 14 days of stopping an MAOI intended to treat psychiatric disorders. In addition, do not start escitalopram oxalate in a patient who is being treated with linezolid or intravenous methylene blue.
(4) Concomitant use of pimozide. (4) Known hypersensitivity to escitalopram or citalopram or any of the inactive ingredients. (4)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Serotonin Syndrome: Increased risk when co-administered with other serotonergic agents but also when taken alone. If it occurs, discontinue escitalopram oxalate and serotonergic agents and initiate supportive treatment. ( 4 , 5.2 ) Discontinuation syndrome: When discontinuing escitalopram oxalate, reduce dosage gradually whenever possible, and monitor for discontinuation symptoms.
(5.3) Seizures: Use with caution in patients with a history of seizure. (5.4) Activation of Mania/Hypomania: Screen patients for bipolar disorder. (5.5) Hyponatremia: Can occur in association with syndrome of inappropriate antidiuretic hormone secretion.
(5.6) Increased Risk of Bleeding: Concomitant use of nonsteroidal anti-inflammatory drugs, aspirin, other antiplatelet drugs, warfarin and other drugs that affect coagulation may increase risk. (5.7) Interference with Cognitive and Motor Performance: Use caution when operating machinery. (5.8) Angle Closure Glaucoma: Angle closure glaucoma has occurred in patients with untreated anatomically narrow angles treated with antidepressants.
(5.9) Use in Patients with Concomitant Illness: Use caution in patients with diseases or conditions that produce altered metabolism or hemodynamic responses. (5.10) Sexual Dysfunction: Escitalopram oxalate may cause symptoms of sexual dysfunction. (5.11)
5.1Suicidal Thoughts and Behaviors in Adolescents and Young Adults In pooled analyses of placebo-controlled trials of antidepressant drugs (SSRIs and other antidepressant classes) that included approximately 77,000 adult patients and 4,500 pediatric patients, the incidence of suicidal thoughts and behaviors in the antidepressant-treated patients age 24 years and younger was greater than in placebo-treated patients. There was considerable variation in risk of suicidal thoughts and behaviors among drugs, but there was an increased risk identified in young patients for most drugs studied.
There were differences in absolute risk of suicidal thoughts and behaviors across the different indications, with the highest incidence in patients with MDD. The drug-placebo differences in the number of cases of suicidal thoughts and behaviors per 1,000 patients treated are provided in Table 1. TABLE 1: Risk Differences of the Number of Patients of Suicidal Thoughts and Behaviors in the Pooled Placebo-Controlled Trials of Antidepressants in Pediatric and Adult Patients Age Range Drug-Placebo Difference in Number of Patients of Suicidal Thoughts and Behaviors per 1,000 Patients Treated Increases Compared to Placebo < 18 years old 14 additional patients 18 to 24 years old 5 additional patients Decreases Compared to Placebo 25 to 64 years old 1 fewer patient ≥ 65 years old 6 fewer patients It is unknown whether the risk of suicidal thoughts and behaviors in children, adolescents, and young adults extends to longer-term use, i.e., beyond four months.
However, there is substantial evidence from placebo-controlled maintenance trials in adults with MDD that antidepressants delay the recurrence of depression and that depression itself is a risk factor for suicidal thoughts and behaviors. Monitor all antidepressant-treated patients for any indication for clinical worsening and emergence of suicidal thoughts and behaviors, especially during the initial few months of drug therapy, and at times of dosage changes. Counsel family members or caregivers of patients to monitor for changes in behavior and to alert the healthcare provider.
Consider changing the therapeutic regimen, including possibly discontinuing escitalopram oxalate, in patients whose depression is persistently worse, or who are experiencing emergent suicidal thoughts or behaviors.
5.2Serotonin Syndrome SSRIs, including escitalopram oxalate, can precipitate serotonin syndrome, a potentially life-threatening condition. The risk is increased with concomitant use of other serotonergic drugs (including triptans, tricyclic antidepressants, fentanyl, meperidine, me… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in greater detail in other sections of the labeling: Suicidal thoughts and behaviors in adolescents and young adults [see Warnings and Precautions (5.1) ] Serotonin syndrome [see Warnings and Precautions (5.2) ] Discontinuation syndrome [see Warnings and Precautions (5.3) ] Seizures [see Warnings and Precautions (5.4) ] Activation of mania or hypomania [see Warnings and Precautions (5.5) ] Hyponatremia [see Warnings and Precautions (5.6) ] Increased Risk of Bleeding [see Warnings and Precautions (5.7) ] Interference with Cognitive and Motor Performance [see Warnings and Precautions (5.8) ] Angle-closure glaucoma [see Warnings and Precautions (5.9) ] Use in Patients with Concomitant Illness [see Warnings and Precautions (5.10) ] Sexual Dysfunction [see Warnings and Precautions (5.11) ] Most commonly observed adverse reactions (incidence ≥ 5% and at least twice the incidence of placebo patients) are: insomnia, ejaculation disorder (primarily ejaculatory delay), nausea, sweating increased, fatigue and somnolence, decreased libido, and anorgasmia.
(6.1) To report SUSPECTED ADVERSE REACTIONS, contact Amneal Pharmaceuticals at 1-877-835-5472 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical studies are conducted under widely varying conditions, adverse reaction rates observed in the clinical studies of a drug cannot be directly compared to rates in the clinical studies of another drug and may not reflect the rates observed in practice. Clinical Trial Data Sources Adults Adverse reactions information for escitalopram oxalate was collected from 715 patients with major depressive disorder who were exposed to escitalopram and from 592 patients who were exposed to placebo in double-blind, placebo-controlled trials.
An additional 284 patients with major depressive disorder were newly exposed to escitalopram in open-label trials. The adverse reaction information for escitalopram oxalate in patients with GAD was collected from 429 patients exposed to escitalopram and from 427 patients exposed to placebo in double-blind, placebo-controlled trials. Adverse reactions during exposure were obtained primarily by general inquiry and recorded by clinical investigators using terminology of their own choosing.
Consequently, it is not possible to provide a meaningful estimate of the proportion of individuals experiencing adverse reactions without first grouping similar types of reactions into a smaller number of standardized event categories. In the tables and tabulations that follow, standard World Health Organization (WHO) terminology has been used to classify reported adverse reactions. The stated frequencies of adverse reactions represent the proportion of individuals who experienced, at least once, a treatment-emergent adverse event of the type listed.
An event was considered treatment-emergent if it occurred for the first time or worsened while receiving therapy following baseline evaluation. Pediatric Patients Adverse reaction information for pediatric patients was collected in double-blind placebo-controlled studies in 576 pediatric patients 6 to 17 years of age, (286 escitalopram oxalate, 290 placebo) with major depressive disorder. The safety and effectiveness of escitalopram oxalate have not been established in pediatric patients less than 12 years of age with MDD or less than 7 years of age with GAD.
Adverse Reactions Associated with Discontinuation of Treatment Major Depressive Disorder Adults Among the 715 depressed patients who received escitalopram oxalate in placebo-controlled trials, 6% discontinued treatment due to an adverse event, as compared to 2% of 592 patients receiving placebo. In two fixed-dose studies, the rate of discontinuation for adverse reactions in patients receiving 10 mg/day escitalopram oxalate was not significantly different from the rate of discontinuation for adverse reactions in patients receiving p… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Table 6 presents clinically important drug interactions with escitalopram oxalate. TABLE 6 Clinically Important Drug Interactions with Escitalopram Oxalate Monoamine Oxidase Inhibitors (MAOIs) Clinical Impact: Concomitant use of SSRIs, including escitalopram oxalate, and MAOIs increases the risk of serotonin syndrome. Intervention: Escitalopram oxalate is contraindicated in patients taking MAOIs, including MAOIs such as linezolid or intravenous methylene blue [see Dosage and Administration (2.7) , Contraindications (4) and Warnings and Precautions (5.2) ] .
Pimozide Clinical Impact: Concomitant use of racemic citalopram with pimozide increases plasma concentrations of pimozide, a drug with a narrow therapeutic index, and may increase the risk of QT prolongation and/or ventricular arrhythmias compared to use of racemic citalopram alone [see Clinical Pharmacology (12.3)] . Intervention: Escitalopram oxalate is contraindicated in patients taking pimozide [see Contraindications (4)] . Other Serotonergic Drugs Clinical Impact: Concomitant use of escitalopram oxalate and other serotonergic drugs (including other SSRIs, SNRIs, triptans, tricyclic antidepressants, opioids, lithium, buspirone, amphetamines, tryptophan, and St.
John's Wort) increases the risk of serotonin syndrome. Intervention: Monitor patients for signs and symptoms of serotonin syndrome, particularly during escitalopram oxalate initiation and dosage increases. If serotonin syndrome occurs, consider discontinuation of escitalopram oxalate and/or concomitant serotonergic drugs [see Warning and Precautions (5.2)] .
Drugs That Interfere With Hemostasis (NSAIDs, Aspirin, Warfarin, etc.) Clinical Impact: Concomitant use of escitalopram oxalate and an antiplatelet or anticoagulant may potentiate the risk of bleeding. Intervention: Inform patients of the increased risk of bleeding associated with the concomitant use of escitalopram oxalate and antiplatelet agents and anticoagulants. For patients taking warfarin, carefully monitor the international normalized ratio [see Warning and Precautions (5.7)] .
Sumatriptan Clinical Impact: There have been post-marketing reports describing patients with weakness, hyperreflexia, and incoordination following the use of an SSRI and sumatriptan. Intervention: If concomitant treatment with sumatriptan and an SSRI is clinically warranted, appropriate observation of the patient is advised [see Warning and Precautions (5.2)] . Carbamazepine Clinical Impact: Combined administration of racemic citalopram (40 mg/day for 14 days) and carbamazepine (titrated to 400 mg/day for 35 days) did not significantly affect the pharmacokinetics of carbamazepine, a CYP3A4 substrate.
Intervention: Although trough citalopram plasma levels were unaffected, given the enzyme-inducing properties of carbamazepine, the possibility that carbamazepine might increase the clearance of escitalopram should be considered if the two drugs are co-administered. Drugs Metabolized by CYP2D6 Clinical Impact: Co-administration of escitalopram (20 mg/day for 21 days) with the tricyclic antidepressant desipramine (single dose of 50 mg), a substrate for CYP2D6, resulted in a 40% increase in C max and a 100% increase in AUC of desipramine.
Intervention: The clinical significance of this finding is unknown. Exercise caution during co-administration of escitalopram and drugs metabolized by CYP2D6. Concomitant use with SSRIs, SNRIs or Tryptophan is not recommended.
(7) Use caution when concomitant use with drugs that affect Hemostasis (NSAIDs, Aspirin, Warfarin). (7)
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: SSRI use, particularly later in pregnancy, may increase the risk for persistent pulmonary hypertension and symptoms of poor adaptation (respiratory distress, temperature instability, feeding difficulties, hypotonia, tremor, irritability) in the neonate. ( 8.1 ) Additional pediatric use information is approved for AbbVie Inc.’s LEXAPRO (escitalopram) oral solution. However, due to AbbVie Inc.’s marketing exclusivity rights, this drug product is not labeled with that information.
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to antidepressants during pregnancy. Healthcare providers are encouraged to advise patients to register by calling the National Pregnancy Registry for Antidepressants at 1-844-405-6185 or visiting online at https://womensmentalhealth.org/research/pregnancyregistry/antidepressants . Risk Summary Based on data from published observational studies, exposure to SSRIs, particularly in the month before delivery, has been associated with a less than 2-fold increase in the risk of postpartum hemorrhage [see Warnings and Precautions (5.7) and Clinical Considerations ] .
Available data from published epidemiologic studies and post-marketing reports have not established an increased risk of major birth defects or miscarriage. There are risks of persistent pulmonary hypertension of the newborn (PPHN) (see Data ) and poor neonatal adaptation (see Clinical Considerations ) with exposure to selective serotonin reuptake inhibitors (SSRIs), including escitalopram, during pregnancy. There are risks associated with untreated depression in pregnancy (see Clinical Considerations ).
In animal reproduction studies, both escitalopram and racemic citalopram have been shown to have adverse effects on embryo/fetal and postnatal development, including fetal structural abnormalities, when administered at doses greater than human therapeutic doses (see Data ) . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in the clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Disease-associated maternal risk and/or embryo/fetal risk Women who discontinue antidepressants are more likely to experience a relapse of major depression than women who continue antidepressants. This finding is from a prospective longitudinal study of 201 pregnant women with a history of major depression, who were euthymic and taking antidepressants at the beginning of pregnancy.
Consider the risk of untreated depression when discontinuing or changing treatment with antidepressant medication during pregnancy and postpartum. Maternal Adverse Reactions Use of escitalopram oxalate in the month before delivery may be associated with an increased risk of postpartum hemorrhage [see Warnings and Precautions (5.7) ]. Fetal/Neonatal adverse reactions Neonates exposed to SSRIs or SNRIs, including escitalopram, late in third trimester have developed complications requiring prolonged hospitalization, respiratory support, and tube feeding.
Such complications can arise immediately upon delivery. Reported clinical findings have included respiratory distress, cyanosis, apnea, seizures, temperature instability, feeding difficulty, vomiting, hypoglycemia, hypotonia, hypertonia, hyperreflexia, tremor, jitteriness, irritability, and constant crying. These features are consistent with either a direct toxic effect of SSRIs and SNRIs or, possibly, a drug discontinuation syndrome.
It should be noted that, in some cases, the clinical picture is consistent with serotonin syndrome [see Warnings and Precautions (5.2) ] . Data Human Data Exposure to SSRIs, particularly later in pregnanc… [Excerpted — this section continues on DailyMed.]
🆘 Overdosage ▾
10 OVERDOSAGE Prolonged cardiac monitoring is recommended in escitalopram oxalate overdosage ingestions due to the arrhythmia risk. Gastrointestinal decontamination with activated charcoal should be considered in patients who present early after a escitalopram oxalate overdose. Consider contacting the Poison Help line (1-800-222-1222) or a medical toxicologist for additional overdose management recommendations.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The mechanism of antidepressant action of escitalopram, the S-enantiomer of racemic citalopram, is presumed to be linked to potentiation of serotonergic activity in the central nervous system (CNS) resulting from its inhibition of CNS neuronal reuptake of serotonin (5-HT).
12.2Pharmacodynamics In vitro and in vivo studies in animals suggest that escitalopram is a highly selective serotonin reuptake inhibitor (SSRI) with minimal effects on norepinephrine and dopamine neuronal reuptake. Escitalopram is at least 100-fold more potent than the R-enantiomer with respect to inhibition of 5-HT reuptake and inhibition of 5-HT neuronal firing rate. Tolerance to a model of antidepressant effect in rats was not induced by long-term (up to 5 weeks) treatment with escitalopram.
Escitalopram has no or very low affinity for serotonergic (5-HT 1-7 ) or other receptors including alpha- and beta-adrenergic, dopamine (D 1-5 ), histamine (H 1-3 ), muscarinic (M 1-5 ), and benzodiazepine receptors. Escitalopram also does not bind to, or has low affinity for, various ion channels including Na + , K + , Cl - , and Ca ++ channels. Antagonism of muscarinic, histaminergic, and adrenergic receptors has been hypothesized to be associated with various anticholinergic, sedative, and cardiovascular side effects of other psychotropic drugs.
12.3Pharmacokinetics The single- and multiple-dose pharmacokinetics of escitalopram are linear and dose-proportional in a dose range of 10 to 30 mg/day. With once-daily dosing, steady-state plasma concentrations are achieved within approximately one week. At steady-state, the extent of accumulation of escitalopram in plasma in young healthy subjects was 2.2 to 2.5 times the plasma concentrations observed after a single dose.
Absorption The absolute bioavailability of citalopram is about 80% relative to an intravenous dose. The tablet and the oral solution dosage forms of escitalopram oxalate are bioequivalent. Following a single oral dose (20 mg) of escitalopram, peak blood levels occur at about 5 hours.
Absorption of escitalopram is not affected by food. Distribution The binding of escitalopram to human plasma proteins is approximately 56%. The volume of distribution of citalopram is about 12 L/kg.
Data specific on escitalopram are unavailable. Elimination Biotransformation of escitalopram is mainly hepatic, with a mean terminal half-life of about 27 to 32 hours. The oral clearance of escitalopram is 600 mL/min, with approximately 7% of that due to renal clearance.
Metabolism Escitalopram is metabolized to S-DCT and S-didemethylcitalopram (S-DDCT). In humans, unchanged escitalopram is the predominant compound in plasma. At steady-state, the concentration of the escitalopram metabolite S-DCT in plasma is approximately one-third that of escitalopram.
The level of S-DDCT was not detectable in most subjects. In vitro studies show that escitalopram is at least 7 and 27 times more potent than S-DCT and S-DDCT, respectively, in the inhibition of serotonin reuptake, suggesting that the metabolites of escitalopram do not contribute significantly to the antidepressant actions of escitalopram. S-DCT and S-DDCT also have no or very low affinity for serotonergic (5-HT 1-7 ) or other receptors including alpha- and beta-adrenergic, dopamine (D 1-5 ), histamine (H 1-3 ), muscarinic (M 1-5 ), and benzodiazepine receptors.
S-DCT and S-DDCT also do not bind to various ion channels including Na + , K + , Cl - , and Ca ++ channels. In vitro studies using human liver microsomes indicated that CYP3A4 and CYP2C19 are the primary isozymes involved in the N-demethylation of escitalopram. Excretion Following oral administrations of escitalopram, the fraction of drug recovered in the urine as escitalopram and S-demethylcitalopram (S-DCT) is about 8% and 10%, respectively.
Specific Populations Pediatric Patients Pediatric patients 12 to 17 years of age: In a single dose study of 10 mg escitalopram,… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Oral Solution Escitalopram oral solution, USP, equivalent 5 mg base/5 mL , is a clear colorless to pale yellow, peppermint flavored solution, available as 240 mL; NDC 65162-705-88. Storage and Handling Store at 20° to 25°C (68° to 77°F); excursions permitted between 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Escitalopram oral solution, USP contains escitalopram oxalate USP, a selective serotonin reuptake inhibitor (SSRI), present as escitalopram oxalate salt. Escitalopram is the pure S-enantiomer (single isomer) of the racemic bicyclic phthalane derivative citalopram. Escitalopram oxalate, USP is designated S-(+)-1-[3-(dimethyl-amino)propyl]-1-(p - fluorophenyl)-5-phthalancarbonitrile oxalate with the following structural formula: •C 2 H 2 O 4 The molecular formula is C 20 H 21 FN 2 O • C 2 H 2 O 4 and the molecular weight is 414.40.
Escitalopram oxalate, USP occurs as a fine, white to slightly-yellow powder and is freely soluble in methanol and dimethyl sulfoxide (DMSO), soluble in isotonic saline solution, sparingly soluble in water and ethanol, slightly soluble in ethyl acetate, and insoluble in heptane. Escitalopram oral solution, USP contains 1.29 mg/mL escitalopram oxalate, USP equivalent to 1 mg/mL escitalopram base. It also contains the following inactive ingredients: anhydrous citric acid, glycerin, malic acid, methylparaben, natural peppermint flavor, propylene glycol, propylparaben, purified water, sodium citrate and sorbitol. ec45d723-figure-01
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Suicidal Thoughts and Behaviors Advise patients, their families and caregivers to look for the emergence of suicidal ideation and behavior, especially during treatment and when the dose is adjusted up or down, and instruct them to report such symptoms to their healthcare provider [see Boxed Warning and Warnings and Precautions (5.1) ] . Serotonin Syndrome Caution patients about the risk of serotonin syndrome, particularly with the concomitant use of escitalopram oxalate with other serotonergic drugs including triptans, tricyclic antidepressants, opioids, lithium, tryptophan, buspirone, amphetamines and St.
John’s Wort, and with drugs that impair metabolism of serotonin (in particular, MAOIs, both those intended to treat psychiatric disorders and also others, such as linezolid). Instruct patients to contact their health care provider or report to the emergency room if they experience signs or symptoms of serotonin syndrome [see Warnings and Precautions (5.2) , Drug Interactions (7) ] . Discontinuation Syndrome Advise patients not to abruptly discontinue escitalopram oxalate and to discuss any tapering regimen with their healthcare provider.
Inform patients that adverse reactions can occur when escitalopram oxalate is discontinued [see Warnings and Precautions (5.3) ] . Activation of Mania or Hypomania Advise patients and their caregivers to observe for signs of activation of mania/hypomania and instruct them to report such symptoms to the healthcare provider [see Warnings and Precautions (5.5) ] . Increased Risk of Bleeding Inform patients about the concomitant use of escitalopram oxalate with NSAIDs, aspirin, warfarin, other antiplatelet drugs, or other anticoagulants because the combined use has been associated with an increased risk of bleeding.
Advise patients to inform their healthcare providers if they are taking or planning to take any prescription or over-the-counter medications that increase the risk of bleeding [see Warnings and Precautions (5.7) ] . Angle Closure Glaucoma Advise patients that taking escitalopram oxalate can cause mild pupillary dilation, which in susceptible individuals, can lead to an episode of angle closure glaucoma. Pre-existing glaucoma is almost always open-angle glaucoma because angle closure glaucoma, when diagnosed, can be treated definitively with iridectomy.
Open-angle glaucoma is not a risk factor for angle closure glaucoma. Patients may wish to be examined to determine whether they are susceptible to angle closure, and have a prophylactic procedure (e.g., iridectomy), if they are susceptible [see Warnings and Precautions (5.9) ] . Sexual Dysfunction Advise patients that use of escitalopram oral solution may cause symptoms of sexual dysfunction in both male and female patients.
Inform patients that they should discuss any changes in sexual function and potential management strategies with their healthcare provider [see Warnings and Precautions (5.11) ]. Concomitant Medications Since escitalopram is the active isomer of racemic citalopram (Celexa), the two agents should not be co-administered. Patients should be advised to inform their physician if they are taking, or plan to take, any prescription or over-the-counter drugs, as there is a potential for interactions.
Interference with Psychomotor Performance Because psychoactive drugs may impair judgment, thinking, or motor skills, patients should be cautioned about operating hazardous machinery, including automobiles, until they are reasonably certain that escitalopram oxalate therapy does not affect their ability to engage in such activities. Alcohol Patients should be told that, although escitalopram oxalate has not been shown in experiments with normal subjects to increase the mental and motor skill impairments caused by alcohol, the concomitant use of escitalopram oxalate and alcohol in depressed patients is not advised.
P… [Excerpted — this section continues on DailyMed.]
💬 Medication Guide ▾
Medication Guide Escitalopram ( es“ sye tal‘ oh pram ) Oral Solution, USP What is the most important information I should know about escitalopram oral solution? Escitalopram oral solution may cause serious side effects, including: Increased risk of suicidal thoughts or actions. Escitalopram oral solution and other antidepressant medicines increase the risk of suicidal thoughts and actions in people 24 years of age and younger, especially within the first few months of treatment or when the dose is changed.
Depression or other mental illnesses are the most important causes of suicidal thoughts or actions. How can I watch for and try to prevent suicidal thoughts and actions? Pay close attention to any changes, especially sudden changes in mood, behavior, thoughts, or feelings, or if you or your child develop suicidal thoughts or actions.
This is very important when an antidepressant medicine is started or when the dose is changed. Call your healthcare provider right away to report new or sudden changes in mood, behavior, thoughts, or feelings or if you or your child develop suicidal thoughts or actions. Keep all follow-up visits with your healthcare provider as scheduled and call your healthcare provider between visits if you are worried about symptoms.
Call your healthcare provider or get emergency medical help right away if you or your child have any of the following symptoms, especially if they are new, worse, or worry you: attempts to commit suicide acting aggressive, being angry or violent new or worse depression panic attacks new or worse irritability an extreme increase in activity or talking (mania) acting on dangerous impulses thoughts about suicide or dying new or worsening anxiety feeling very agitated or restless trouble sleeping other unusual changes in behavior or mood What is escitalopram oral solution?
Escitalopram oral solution is a prescription medicine used to treat: a certain type of depression called Major Depressive Disorder (MDD) in adults and children 12 years of age and older Generalized Anxiety Disorder (GAD) in adults It is not known if escitalopram oral solution is safe and effective for use in children under 12 years of age with MDD or children under 7 years of age with GAD. Do not take escitalopram oral solution if you or your child: are taking, or have stopped taking within the last 14 days, a medicine called a monoamine oxidase inhibitor (MAOI), including the antibiotic linezolid or intravenous methylene blue are taking the antipsychotic medicine pimozide are allergic to escitalopram or citalopram or any of the ingredients in escitalopram oral solution.
See the end of this Medication Guide for a complete list of ingredients in escitalopram oral solution. Ask your healthcare provider or pharmacist if you are not sure if you or your child take an MAOI, including the antibiotic linezolid or intravenous methylene blue. Do not start taking an MAOI for at least 14 days after you or your child have stopped treatment with escitalopram oral solution.
Before taking escitalopram oral solution, tell your healthcare provider about all your medical conditions, including if you or your child : have or had seizures or convulsions have, or have a family history of bipolar disorder, mania, or hypomania have low blood sodium levels have or had bleeding problems have high pressure in the eye (glaucoma) have heart, liver, or kidney problems are pregnant or plan to become pregnant. Escitalopram oral solution may harm the unborn baby. Taking escitalopram oral solution during the third trimester of pregnancy may cause the baby to have withdrawal symptoms, or breathing, temperature control, feeding, or other problems after birth.
Talk to your healthcare provider about the risks to the baby if you or your child take escitalopram oral solution during pregnancy. Tell your healthcare provider right away if you or your child become pregnant or think you may be pregnant during treatment with escitalopram oral solution. There is… [Excerpted — this section continues on DailyMed.]
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Major Depressive Disorder Adults The efficacy of escitalopram oxalate as a treatment for major depressive disorder was established in three, 8-week, placebo-controlled studies conducted in outpatients between 18 and 65 years of age who met DSM-IV criteria for major depressive disorder. The primary outcome in all three studies was change from baseline to endpoint in the Montgomery Asberg Depression Rating Scale (MADRS). A fixed-dose study compared 10 mg daily escitalopram oxalate and 20 mg daily escitalopram oxalate to placebo and 40 mg daily citalopram.
The 10 mg daily and 20 mg daily escitalopram oxalate treatment groups showed statistically significant greater mean improvement compared to placebo on the MADRS. The 10 mg and 20 mg escitalopram oxalate groups were similar on this outcome measure. In a second fixed-dose study of 10 mg daily escitalopram oxalate and placebo, the 10 mg daily escitalopram oxalate treatment group showed statistically significant greater mean improvement compared to placebo on the MADRS.
In a flexible-dose study, comparing escitalopram oxalate, titrated between 10 mg and 20 mg daily, to placebo and citalopram, titrated between 20 mg and 40 mg daily, the escitalopram oxalate treatment group showed statistically significant greater mean improvement compared to placebo on the MADRS. Analyses of the relationship between treatment outcome and age, gender, and race did not suggest any differential responsiveness on the basis of these patient characteristics. In a longer-term trial, 274 patients meeting (DSM-IV) criteria for major depressive disorder, who had responded during an initial 8-week, open-label treatment phase with escitalopram oxalate 10 mg or 20 mg daily, were randomized to continuation of escitalopram oxalate at their same dose, or to placebo, for up to 36 weeks of observation for relapse.
Response during the open-label phase was defined by having a decrease of the MADRS total score to ≤ 12. Relapse during the double-blind phase was defined as an increase of the MADRS total score to ≥ 22, or discontinuation due to insufficient clinical response. Patients receiving continued escitalopram oxalate experienced a statistically significant longer time to relapse compared to those receiving placebo.
Pediatric Patients 12 years of age and older The efficacy of escitalopram oxalate as a treatment for major depressive disorder in pediatric patients 12 to 17 years was established in an 8-week, flexible-dose, placebo-controlled study that compared escitalopram oxalate (10 mg to 20 mg daily) to placebo in outpatients 12 to 17 years of age inclusive who met DSM-IV criteria for major depressive disorder (MDD). The primary outcome was change from baseline to endpoint in the Children's Depression Rating Scale - Revised (CDRS-R).
In this study, escitalopram oxalate showed statistically significant greater mean improvement compared to placebo on the CDRS-R. The efficacy of escitalopram oxalate in the treatment of major depressive disorder in pediatric patients 12 to 17 years was established, in part, on the basis of extrapolation from the 8-week, flexible-dose, placebo-controlled study with racemic citalopram 20 mg to 40 mg daily. In this outpatient study in pediatric patients 7 to 17 years of age who met DSM-IV criteria for major depressive disorder, citalopram treatment showed statistically significant greater mean improvement from baseline, compared to placebo, on the CDRS-R; the positive results for this trial largely came from the 12 to 17 year subgroup.
Two additional flexible-dose, placebo-controlled MDD studies (one escitalopram oxalate study in patients ages 7 to 17 years and one citalopram study patients 13 to 18 years) did not demonstrate efficacy. The safety and effectiveness of escitalopram oxalate have not been established in pediatric patients less than 12 years of age with MDD.
14.2Generalized Anxiety Disorder Adults The efficacy of escitalopram oxalate in the treatment… [Excerpted — this section continues on DailyMed.]
🔒 Drug Abuse and Dependence ▾
9 DRUG ABUSE AND DEPENDENCE
9.2Abuse and Dependence Physical and Psychological Dependence Animal studies suggest that the abuse liability of racemic citalopram is low. Escitalopram oxalate has not been systematically studied in humans for its potential for abuse, tolerance, or physical dependence. The premarketing clinical experience with escitalopram oxalate did not reveal any drug-seeking behavior.
However, these observations were not systematic and it is not possible to predict on the basis of this limited experience the extent to which a CNS-active drug will be misused, diverted, and/or abused once marketed. Consequently, physicians should carefully evaluate escitalopram oxalate patients for history of drug abuse and follow such patients closely, observing them for signs of misuse or abuse (e.g., development of tolerance, incrementations of dose, drug-seeking behavior).
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Racemic citalopram was administered in the diet to NMRI/BOM strain mice and COBS WI strain rats for 18 and 24 months, respectively. There was no evidence for carcinogenicity of racemic citalopram in mice receiving up to 240 mg/kg/day. There was an increased incidence of small intestine carcinoma in rats receiving 8 or 24 mg/kg/day racemic citalopram.
A no-effect dose for this finding was not established. The relevance of these findings to humans is unknown. Mutagenesis Racemic citalopram was mutagenic in the in vitro bacterial reverse mutation assay (Ames test) in 2 of 5 bacterial strains (Salmonella TA98 and TA1537) in the absence of metabolic activation.
It was clastogenic in the in vitro Chinese hamster lung cell assay for chromosomal aberrations in the presence and absence of metabolic activation. Racemic citalopram was not mutagenic in the in vitro mammalian forward gene mutation assay (HPRT) in mouse lymphoma cells or in a coupled in vitro/in vivo unscheduled DNA synthesis (UDS) assay in rat liver. It was not clastogenic in the in vitro chromosomal aberration assay in human lymphocytes or in two in vivo mouse micronucleus assays.
Impairment of Fertility When racemic citalopram was administered orally to 16 male and 24 female rats prior to and throughout mating and gestation at doses of 32, 48, and 72 mg/kg/day, mating was decreased at all doses, and fertility was decreased at doses ≥ 32 mg/kg/day. Gestation duration was increased at 48 mg/kg/day.
13.2Animal Toxicology and/or Pharmacology Retinal Changes in Rats Pathologic changes (degeneration/atrophy) were observed in the retinas of albino rats in the 2-year carcinogenicity study with racemic citalopram. There was an increase in both incidence and severity of retinal pathology in both male and female rats receiving 80 mg/kg/day. Similar findings were not present in rats receiving 24 mg/kg/day of racemic citalopram for two years, in mice receiving up to 240 mg/kg/day of racemic citalopram for 18 months, or in dogs receiving up to 20 mg/kg/day of racemic citalopram for one year.
Additional studies to investigate the mechanism for this pathology have not been performed, and the potential significance of this effect in humans has not been established. Cardiovascular Changes in Dogs In a one-year toxicology study, 5 of 10 beagle dogs receiving oral racemic citalopram doses of 8 mg/kg/day died suddenly between weeks 17 and 31 following initiation of treatment. Sudden deaths were not observed in rats at doses of racemic citalopram up to 120 mg/kg/day, which produced plasma levels of citalopram and its metabolites demethylcitalopram and didemethylcitalopram (DDCT) similar to those observed in dogs at 8 mg/kg/day.
A subsequent intravenous dosing study demonstrated that in beagle dogs, racemic DDCT caused QT prolongation, a known risk factor for the observed outcome in dogs.
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL label