
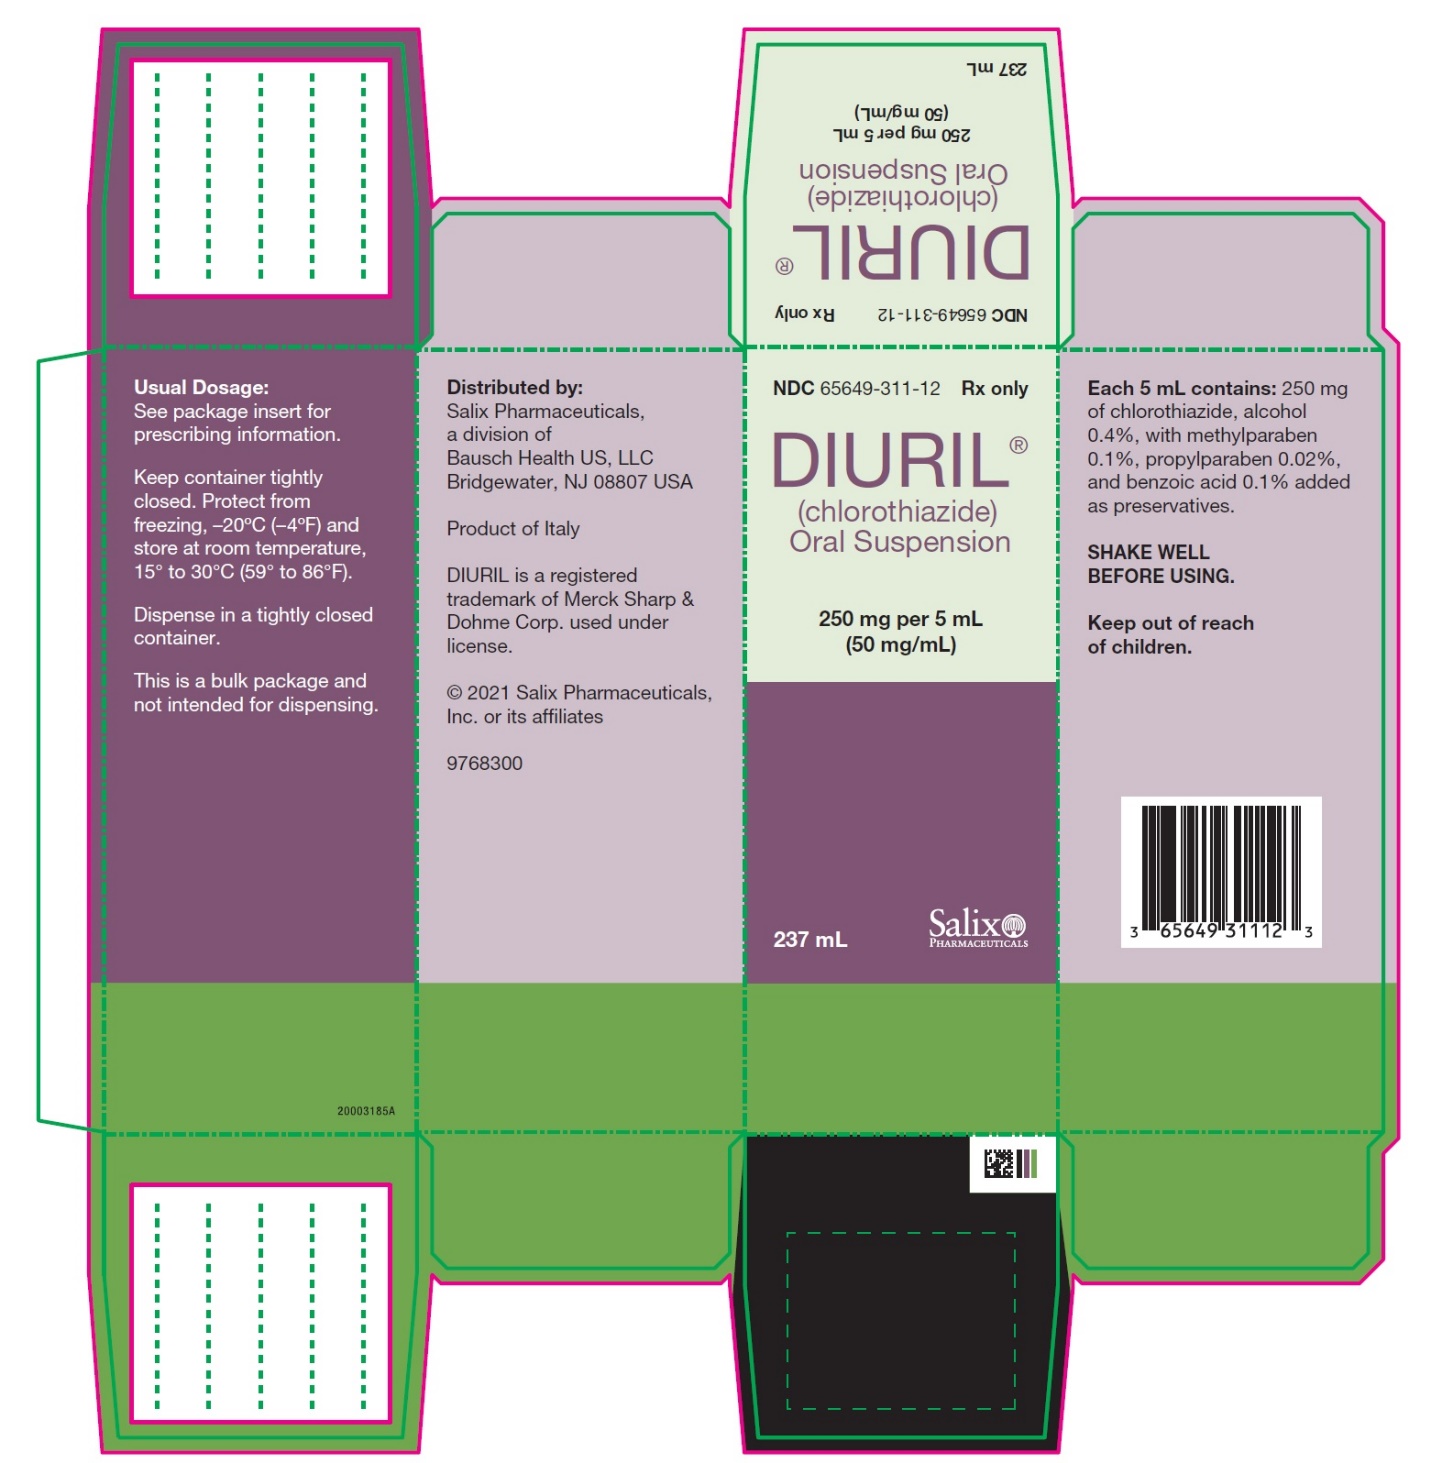
DIURIL CHLOROTHIAZIDE 250 mg/5mL Suspension — NDC 65649-311-12 (Billing 65649-0311-12)
This is a package of DIURIL CHLOROTHIAZIDE 250 mg/5mL Suspension from Salix Pharmaceuticals, Inc, marketed since Feb 1962 and currently FDA-listed, this package's marketing is listed to end Jan 2028; retail pharmacies pay about $0.2766 per mL (NADAC). It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 65649-311-12 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 65649 labeler · 311 product · 12 package
- Package marketed since
- Feb 15, 1962
- Package marketing ended
- Jan 31, 2028
- Sample package
- No — commercial package
- Barcode (UPC-A, from the NDC)
- 3 6564931112 3
- Medicaid fills, this package
- 7,744 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 008172
- GCN: 34790
- GPI-14 (Medi-Span): 37600020001805
- HICL (First Databank): 003646
- AHFS class code: 24:36.20.00
- RxCUI (RxNorm): 213439
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Thiazide Diuretic class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Chlorothiazide is used alone or in combination with other medications to treat high blood pressure. Chlorothiazide is used to treat edema (fluid retention; excess fluid held in body tissues) caused by various medical problems, including heart, kidney, and liver disease and to treat edema caused by using certain medications including estrogen and corticosteroids. Chlorothiazide is in a class of medications called diuretics ('water pills'). It works by causing the kidneys to get rid of unneeded water and salt from the body into the urine. High blood pressure is a common condition, and when not t...
Read the full MedlinePlus article ↗- It's a water pill — it helps your kidneys flush out extra salt and fluid that's building up in your body. Depending on the form you're taking, it treats fluid retention (edema) fro...
- What exactly is chlorothiazide supposed to do for me?
- You'll take it by mouth, usually once or twice a day. Your doctor might also put you on an every-other-day or a few-days-per-week schedule — that actually helps prevent your electr...
- How and when should I take the oral suspension (liquid)?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Chlorothiazide — tap one for details:
Chlorothiazide may be associated with lower levels of 8 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.277 | $65.55 / 237 ml |
| Medicaid paysCMS SDUD · 12 mo | $0.3303 | $78.28 / 237 ml |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file · file of Feb 21, 2024
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 65649-0311-12 You're viewing this Main listing | 1 BOTTLE in 1 CARTON / 237 mL in 1 BOTTLE | 1962-02-15 | Jan 31, 2028 | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Diuril 250 mg/5mLthis 65649-0311-12 | Salix | 1 bottle | $0.277 | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Feb 21, 2024
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Chlorothiazide inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3K9958V90M
A liquid solvent derived from fermentation or chemical synthesis. In medicines, alcohol dissolves active ingredients, helps preserve the product, and improves how the body absorbs certain drugs.
-
UNII 8SKN0B0MIM
Benzoic acid is a naturally occurring organic acid used as a preservative in medicines and foods. It helps prevent bacterial and fungal growth to extend shelf life and maintain product stability.
-
UNII 35SW5USQ3G
A synthetic yellow dye used to color medicines. It helps make tablets, capsules, and liquids visually distinct so patients can easily identify their medication.
-
UNII PDC6A3C0OX
Glycerin is a clear, thick liquid derived from plant oils or fats. It acts as a humectant to retain moisture, a sweetener, and a solvent in medications.
-
UNII A2I8C7HI9T
Methylparaben is a preservative derived from benzoic acid that prevents growth of bacteria, fungi, and mold in medicines. It extends the product's shelf life and maintains safety during storage.
-
UNII Z8IX2SC1OH
Propylparaben is a chemical preservative used to prevent bacterial and fungal growth in medicines and personal care products. It helps extend shelf life and maintain product safety during storage.
-
UNII C151H8M554
A natural sugar derived from sugar cane or sugar beets. It's used as a sweetener, filler, and binder to improve taste, add bulk, and help hold tablet or capsule ingredients together.
-
UNII 2944357O2O
A natural gum derived from the tragacanth shrub, used as a thickener, stabilizer, and binder in medicines. It helps create the right consistency and keeps ingredients evenly mixed throughout the product.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
9 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 6, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Salix Pharmaceuticals, Inc labeler code 65649
- Relistor Methylnaltrexone bromide 150 mg Tablet NDC 65649-150-06
- MoviPrep POLYETHYLENE GLYCOL 3350, SODIUM SULFATE, SODIUM CHLORIDE, POTASSIUM CHLORIDE, ASCORBIC ACID, SODIUM ASCORBATE Kit NDC 65649-201-75
- Azasan Azathioprine 75 mg Tablet NDC 65649-231-41
- Azasan Azathioprine 100 mg Tablet NDC 65649-241-41
- Xifaxan rifaximin 200 mg Tablet NDC 65649-301-03
- Xifaxan rifaximin 550 mg Tablet NDC 65649-303-01
- Plenvu POLYETHYLENE GLYCOL 3350, SODIUM SULFATE, SODIUM CHLORIDE, POTASSIUM CHLORIDE, ASCORBIC ACID, SODIUM ASCORBATE Kit NDC 65649-400-01
- Anusol HC hydrocortisone 25 mg/g Cream NDC 65649-401-30
- Anusol HC HYDROCORTISONE ACETATE 25 mg Suppository NDC 65649-411-12
- Proctocort HYDROCORTISONE 10 mg/g Cream NDC 65649-501-30
- Proctocort HYDROCORTISONE ACETATE 30 mg Suppository NDC 65649-511-12
- Relistor Methylnaltrexone bromide 12 mg/.6mL Injection, Solution NDC 65649-551-02
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE DIURIL is indicated as adjunctive therapy in edema associated with congestive heart failure, hepatic cirrhosis, and corticosteroid and estrogen therapy. DIURIL has also been found useful in edema due to various forms of renal dysfunction such as nephrotic syndrome, acute glomerulonephritis, and chronic renal failure. DIURIL is indicated in the management of hypertension either as the sole therapeutic agent or to enhance the effectiveness of other antihypertensive drugs in the more severe forms of hypertension.
Use in Pregnancy - Routine use of diuretics during normal pregnancy is inappropriate and exposes mother and fetus to unnecessary hazard. Diuretics do not prevent development of toxemia of pregnancy and there is no satisfactory evidence that they are useful in the treatment of toxemia. Edema during pregnancy may arise from pathologic causes or from the physiologic and mechanical consequences of pregnancy.
Thiazides are indicated in pregnancy when edema is due to pathologic causes, just as they are in the absence of pregnancy (see PRECAUTIONS, Pregnancy ). Dependent edema in pregnancy, resulting from restriction of venous return by the gravid uterus, is properly treated through elevation of the lower extremities and use of support stockings. Use of diuretics to lower intravascular volume in this instance is illogical and unnecessary.
During normal pregnancy there is hypervolemia which is not harmful to the fetus or the mother in the absence of cardiovascular disease. However, it may be associated with edema, rarely generalized edema. If such edema causes discomfort, increased recumbency will often provide relief.
Rarely this edema may cause extreme discomfort which is not relieved by rest. In these instances, a short course of diuretic therapy may provide relief and be appropriate.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Therapy should be individualized according to patient response. Use the smallest dosage necessary to achieve the required response. Adults For Edema The usual adult dosage is 500 mg to 1,000 mg (10 mL to 20 mL) once or twice a day.
Many patients with edema respond to intermittent therapy, i.e., administration on alternate days or on three to five days each week. With an intermittent schedule, excessive response and the resulting undesirable electrolyte imbalance are less likely to occur. For Control of Hypertension The usual adult starting dosage is 500 mg or 1,000 mg (10 mL to 20 mL) a day as a single or divided dose.
Dosage is increased or decreased according to blood pressure response. Rarely some patients may require up to 2,000 mg (40 mL) a day in divided doses. Infants and Children For Diuresis and For Control of Hypertension The usual pediatric dosage is 5 mg to 10 mg per pound (10 mg/kg to 20 mg/kg) per day in single or two divided doses, not to exceed 375 mg per day (2.5 mL to 7.5 mL or ½ to 1½ teaspoonfuls of the oral suspension daily) in infants up to 2 years of age or 1,000 mg per day in children 2 to 12 years of age.
In infants less than 6 months of age, doses up to 15 mg per pound (30 mg/kg) per day in two divided doses may be required (see PRECAUTIONS , Pediatric Use ).
⛔ Contraindications ▾
CONTRAINDICATIONS Anuria. Hypersensitivity to this product or to other sulfonamide-derived drugs.
⚠️ Warnings ▾
WARNINGS Use with caution in severe renal disease. In patients with renal disease, thiazides may precipitate azotemia. Cumulative effects of the drug may develop in patients with impaired renal function.
Thiazides should be used with caution in patients with impaired hepatic function or progressive liver disease, since minor alterations of fluid and electrolyte balance may precipitate hepatic coma. Thiazides may add to or potentiate the action of other antihypertensive drugs. Sensitivity reactions may occur in patients with or without a history of allergy or bronchial asthma.
The possibility of exacerbation or activation of systemic lupus erythematosus has been reported. Lithium generally should not be given with diuretics (see PRECAUTIONS , Drug Interactions ).
🤒 Adverse Reactions ▾
ADVERSE REACTIONS The following adverse reactions have been reported and, within each category, are listed in order of decreasing severity: Body as a Whole: Weakness. Cardiovascular: Hypotension, including orthostatic hypotension (may be aggravated by alcohol, barbiturates, narcotics or antihypertensive drugs). Digestive: Pancreatitis, jaundice (intrahepatic cholestatic jaundice), diarrhea, vomiting, sialadenitis, cramping, constipation, gastric irritation, nausea, anorexia.
Hematologic: Aplastic anemia, agranulocytosis, leukopenia, hemolytic anemia, thrombocytopenia. Hypersensitivity: Anaphylactic reactions, necrotizing angiitis (vasculitis and cutaneous vasculitis), respiratory distress including pneumonitis and pulmonary edema, photosensitivity, fever, urticaria, rash, purpura. Metabolic: Electrolyte imbalance (see PRECAUTIONS ), hyperglycemia, glycosuria, hyperuricemia.
Musculoskeletal: Muscle spasm. Nervous System/Psychiatric: Vertigo, paresthesias, dizziness, headache, restlessness. Renal: Renal failure, renal dysfunction, interstitial nephritis (see WARNINGS ).
Skin: Erythema multiforme including Stevens-Johnson syndrome, exfoliative dermatitis including toxic epidermal necrolysis, alopecia. Special Senses: Transient blurred vision, xanthopsia. Urogenital: Impotence.
Whenever adverse reactions are moderate or severe, thiazide dosage should be reduced or therapy withdrawn. To report SUSPECTED ADVERSE REACTIONS, contact Salix Pharmaceuticals at 1-800-321-4576 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
🔄 Drug Interactions ▾
Drug Interactions When given concurrently the following drugs may interact with thiazide diuretics. Alcohol, Barbiturates, or Narcotics - potentiation of orthostatic hypotension may occur. Antidiabetic Drugs (Oral Agents and Insulin) - dosage adjustment of the antidiabetic drug may be required.
Other Antihypertensive Drugs - additive effect or potentiation. Cholestyramine and Colestipol Resins - Both cholestyramine and colestipol resins have the potential of binding thiazide diuretics and reducing diuretic absorption from the gastrointestinal tract. Corticosteroids, ACTH - intensified electrolyte depletion, particularly hypokalemia.
Pressor Amines (e.g., Norepinephrine) - possible decreased response to pressor amines but not sufficient to preclude their use. Skeletal Muscle Relaxants, Nondepolarizing (e.g., Tubocurarine) - possible increased responsiveness to the muscle relaxant. Lithium - generally should not be given with diuretics.
Diuretic agents reduce the renal clearance of lithium and add a high risk of lithium toxicity. Refer to the package insert for lithium preparations before use of such preparations with DIURIL. Non-steroidal Anti-inflammatory Drugs (NSAIDs) Including Selective Cyclooxygenase-2 (COX-2) Inhibitors - In some patients, the administration of a non-steroidal anti-inflammatory agent including a selective COX-2 inhibitor can reduce the diuretic, natriuretic, and antihypertensive effects of loop, potassium-sparing and thiazide diuretics.
Therefore, when DIURIL and non-steroidal anti-inflammatory agents or selective COX-2 inhibitors are used concomitantly, the patient should be observed closely to determine if the desired effect of the diuretic is obtained. In some patients with compromised renal function (e.g., elderly patients or patients who are volume-depleted, including those on diuretic therapy) who are being treated with NSAIDs, including selective COX-2 inhibitors, the co-administration of angiotensin II receptor antagonists or ACE inhibitors may result in a further deterioration of renal function, including possible acute renal failure.
These effects are usually reversible. These interactions should be considered in patients taking NSAIDs including selective COX-2 inhibitors concomitantly with diuretics and angiotensin II antagonists or ACE inhibitors. Therefore, the combination should be administered with caution, especially in the elderly.
🔄 Drug / Laboratory Test Interactions ▾
Drug/Laboratory Test Interactions Thiazides should be discontinued before carrying out tests for parathyroid function (see PRECAUTIONS , General ).
🤰 Pregnancy ▾
Pregnancy Teratogenic Effects - Although reproduction studies performed with chlorothiazide doses of 50 mg/kg/day in rabbits, 60 mg/kg/day in rats and 500 mg/kg/day in mice revealed no external abnormalities of the fetus or impairment of growth and survival of the fetus due to chlorothiazide, such studies did not include complete examinations for visceral and skeletal abnormalities. It is not known whether chlorothiazide can cause fetal harm when administered to a pregnant woman; however, thiazides cross the placental barrier and appear in cord blood.
DIURIL should be used during pregnancy only if clearly needed (see INDICATIONS AND USAGE ). Nonteratogenic Effects - Chlorothiazide may cause fetal or neonatal jaundice, thrombocytopenia, and possibly other adverse reactions which have occurred in the adult.
🧒 Pediatric Use ▾
Pediatric Use There are no well-controlled clinical trials in pediatric patients. Information on dosing in this age group is supported by evidence from empiric use in pediatric patients and published literature regarding the treatment of hypertension in such patients (see DOSAGE AND ADMINISTRATION, Infants and Children ). _____________ **Calculations based on a human body weight of 50 kg
🧓 Geriatric Use ▾
Geriatric Use Clinical studies of DIURIL did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
This drug is known to be substantially excreted by the kidney, and the risk of toxic reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function (see WARNINGS ).
🆘 Overdosage ▾
OVERDOSAGE The most common signs and symptoms observed are those caused by electrolyte depletion (hypokalemia, hypochloremia, hyponatremia) and dehydration resulting from excessive diuresis. If digitalis has also been administered, hypokalemia may accentuate cardiac arrhythmias. In the event of overdosage, symptomatic and supportive measures should be employed.
Emesis should be induced or gastric lavage performed. Correct dehydration, electrolyte imbalance, hepatic coma and hypotension by established procedures. If required, give oxygen or artificial respiration for respiratory impairment.
The degree to which chlorothiazide sodium is removed by hemodialysis has not been established. The oral LD 50 of chlorothiazide is 8.5 g/kg, greater than 10 g/kg, and greater than 1 g/kg, in the mouse, rat and dog, respectively.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY The mechanism of the antihypertensive effect of thiazides is unknown. DIURIL does not usually affect normal blood pressure. DIURIL affects the distal renal tubular mechanism of electrolyte reabsorption.
At maximal therapeutic dosage all thiazides are approximately equal in their diuretic efficacy. DIURIL increases excretion of sodium and chloride in approximately equivalent amounts. Natriuresis may be accompanied by some loss of potassium and bicarbonate.
After oral use diuresis begins within 2 hours, peaks in about 4 hours and lasts about 6 to 12 hours. Pharmacokinetics and Metabolism DIURIL is not metabolized but is eliminated rapidly by the kidney. The plasma half-life of chlorothiazide is 45-120 minutes.
After oral doses, 10-15% of the dose is excreted unchanged in the urine. Chlorothiazide crosses the placental but not the blood-brain barrier and is excreted in breast milk.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED DIURIL ® (chlorothiazide) Oral Suspension, 250 mg of chlorothiazide per 5 mL, is a yellow, syrupy liquid, and is supplied as follows: NDC 65649-311-12 250 mg per 5 mL 237 mL Storage DIURIL (chlorothiazide) Oral Suspension: Keep container tightly closed. Protect from freezing, –20°C (–4°F) and store at room temperature, 15° to 30°C (59° to 86°F). Distributed by: Salix Pharmaceuticals, a division of Bausch Health US, LLC Bridgewater, NJ 08807 USA DIURIL is a registered trademark of Merck Sharp & Dohme Corp. used under license. © 2021 Salix Pharmaceuticals, Inc. or its affiliates Rev.
11/2021 9768400
📋 Description ▾
DESCRIPTION DIURIL ® (chlorothiazide) is a diuretic and antihypertensive. It is 6-chloro-2 H -1,2,4-benzothiadiazine-7-sulfonamide 1,1-dioxide. Its empirical formula is C 7 H 6 CIN 3 O 4 S 2 and its structural formula is: It is a white, or practically white, crystalline powder with a molecular weight of 295.72, which is very slightly soluble in water, but readily soluble in dilute aqueous sodium hydroxide.
It is soluble in urine to the extent of about 150 mg per 100 mL at pH 7. DIURIL Oral Suspension contains 250 mg of chlorothiazide per 5 mL, alcohol 0.4%, with methylparaben 0.1%, propylparaben 0.02%, and benzoic acid 0.1% added as preservatives. The inactive ingredients are D&C Yellow 10, flavors, glycerin, purified water, sodium saccharin, sucrose and tragacanth.
Chemical Structure
⚠️ Precautions ▾
PRECAUTIONS General All patients receiving diuretic therapy should be observed for evidence of fluid or electrolyte imbalance: namely, hyponatremia, hypochloremic alkalosis, and hypokalemia. Serum and urine electrolyte determinations are particularly important when the patient is vomiting excessively or receiving parenteral fluids. Warning signs or symptoms of fluid and electrolyte imbalance, irrespective of cause, include dryness of mouth, thirst, weakness, lethargy, drowsiness, restlessness, confusion, seizures, muscle pains or cramps, muscular fatigue, hypotension, oliguria, tachycardia, and gastrointestinal disturbances such as nausea and vomiting.
Hypokalemia may develop, especially with brisk diuresis, when severe cirrhosis is present or after prolonged therapy. Interference with adequate oral electrolyte intake will also contribute to hypokalemia. Hypokalemia may cause cardiac arrhythmias and may also sensitize or exaggerate the response of the heart to the toxic effects of digitalis (e.g., increased ventricular irritability).
Hypokalemia may be avoided or treated by use of potassium-sparing diuretics or potassium supplements such as foods with a high potassium content. Although any chloride deficit is generally mild and usually does not require specific treatment except under extraordinary circumstances (as in liver disease or renal disease), chloride replacement may be required in the treatment of metabolic alkalosis. Dilutional hyponatremia may occur in edematous patients in hot weather; appropriate therapy is water restriction, rather than administration of salt, except in rare instances when the hyponatremia is life-threatening.
In actual salt depletion, appropriate replacement is the therapy of choice. Hyperuricemia may occur or acute gout may be precipitated in certain patients receiving thiazides. In diabetic patients dosage adjustments of insulin or oral hypoglycemic agents may be required.
Hyperglycemia may occur with thiazide diuretics. Thus latent diabetes mellitus may become manifest during thiazide therapy. The antihypertensive effects of the drug may be enhanced in the post-sympathectomy patient.
If progressive renal impairment becomes evident, consider withholding or discontinuing diuretic therapy. Thiazides have been shown to increase the urinary excretion of magnesium; this may result in hypomagnesemia. Thiazides may decrease urinary calcium excretion.
Thiazides may cause intermittent and slight elevation of serum calcium in the absence of known disorders of calcium metabolism. Marked hypercalcemia may be evidence of hidden hyperparathyroidism. Thiazides should be discontinued before carrying out tests for parathyroid function.
Increases in cholesterol and triglyceride levels may be associated with thiazide diuretic therapy. Laboratory Tests Periodic determination of serum electrolytes to detect possible electrolyte imbalance should be done at appropriate intervals. Drug Interactions When given concurrently the following drugs may interact with thiazide diuretics.
Alcohol, Barbiturates, or Narcotics - potentiation of orthostatic hypotension may occur. Antidiabetic Drugs (Oral Agents and Insulin) - dosage adjustment of the antidiabetic drug may be required. Other Antihypertensive Drugs - additive effect or potentiation.
Cholestyramine and Colestipol Resins - Both cholestyramine and colestipol resins have the potential of binding thiazide diuretics and reducing diuretic absorption from the gastrointestinal tract. Corticosteroids, ACTH - intensified electrolyte depletion, particularly hypokalemia. Pressor Amines (e.g., Norepinephrine) - possible decreased response to pressor amines but not sufficient to preclude their use.
Skeletal Muscle Relaxants, Nondepolarizing (e.g., Tubocurarine) - possible increased responsiveness to the muscle relaxant. Lithium - generally should not be given with diuretics. Diuretic agents reduce the renal clearance of lithium and add a high risk of lithium toxicity.
Refer to the… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers Because of the potential for serious adverse reactions in nursing infants from DIURIL, a decision should be made whether to discontinue nursing or to discontinue the drug, taking into account the importance of the drug to the mother.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity studies have not been conducted with chlorothiazide. Chlorothiazide was not mutagenic in vitro in the Ames microbial mutagen test (using a maximum concentration of 5 mg/plate and Salmonella typhimurium strains TA98 and TA100) and was not mutagenic and did not induce mitotic nondisjunction in diploid-strains of Aspergillus nidulans . Chlorothiazide had no adverse effects on fertility in female rats at doses up to 60 mg/kg/day and no adverse effects on fertility in male rats at doses up to 40 mg/kg/day.
These doses are 1.5 and 1 times** the recommended maximum human dose, respectively, when compared on a body weight basis.
📄 Package Label / Principal Display Panel ▾
Package Carton- Principal Display Panel NDC 65649-311-12 Rx only DIURIL ® (chlorothiazide) Oral Suspension 250 mg per 5 mL (50 mg/mL) 237 mL Salix PHARMACEUTICALS carton