
Rivastigmine Tartrate 1.5 mg Capsule, 3,000-count — NDC 65862-648-39 (Billing 65862-0648-39)
This is a package of 3,000 capsules of Rivastigmine Tartrate 1.5 mg Capsule from Aurobindo Pharma Limited, marketed since Mar 2016 and currently FDA-listed.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 040155
- GCN: 90396
- GPI-14 (Medi-Span): 62051040200110
- HICL (First Databank): 018527
- AHFS class code: 12:04.00.00
- RxCUI (RxNorm): 312835
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Cholinesterase Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Rivastigmine is used to treat dementia (a brain disorder that affects memory, thinking, and behavior) ) in people with Alzheimer's disease (AD; a brain disease that affects memory, thinking and behavior) or in people with Parkinson's disease (PD; a disorder of the nervous system that causes difficulties with movement, muscle control, and balance). Rivastigmine is in a class of medications called cholinesterase inhibitors. It works by increasing the amount of a certain naturally occurring substance in the brain.
Read the full MedlinePlus article ↗- It treats dementia from Alzheimer’s disease and dementia linked to Parkinson’s disease. It can help with symptoms, but it does not change the course of the underlying disease.
- Capsules are taken twice a day with meals. The patch goes on intact skin once every 24 hours, and the old one must come off first. Your doctor will raise the dose slowly, so follow...
- Nausea, vomiting, diarrhea, lower appetite and weight loss are the most common, especially early on or after dose increases. Call us if they are severe or last, since dehydration c...
- No. Wearing multiple patches or leaving the old one on has led to serious overdoses. Use one patch at a time, and ask your doctor before changing anything.
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 65862-0648-05 65862-648-05 | 500 CAPSULE in 1 BOTTLE | — | — | 2016-03-25 | — | Active |
| 65862-0648-60 65862-648-60 Main listing | 60 CAPSULE in 1 BOTTLE | $0.1643 / ea | $9.86 | 2016-03-25 | — | Active |
| 65862-0648-78 65862-648-78 | 10 BLISTER PACK in 1 CARTON / 10 CAPSULE in 1 BLISTER PACK | — | — | 2016-03-25 | — | Active |
| 65862-0648-39 You're viewing this | 3000 CAPSULE in 1 BAG | — | — | — | — | Active |
This pack shows little to no recent Medicaid volume — the 60 capsules pack carries most fills. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 65862-0648-60?
What NDC number is used to bill for this package of Rivastigmine Tartrate 1.5 mg Capsule?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Rivastigmine Tartrate 1.5 mg 62756-0145-13 | Sun | 500 capsules | $0.151 | — | FDA listed | — |
| Rivastigmine Tartrate 1.5 mg 00904-7107-61 | Major | 100 capsules | $0.164 | AB | Availability likely | — |
| Rivastigmine Tartrate 1.5 mg 60687-0777-01 | American | 100 capsules | $0.164 | AB | Availability likely | — |
| Rivastigmine Tartrate 1.5 mg 62135-0900-60 | Chartwell | 60 capsules | $0.164 | AB | Availability likely | — |
| Rivastigmine Tartrate 1.5 mg 72241-0011-03 | Modavar | 60 capsules | $0.164 | AB | Availability likely | — |
| Rivastigmine Tartrate 1.5 mg 33342-0089-06 | Macleods | 30 capsules | — | AB | FDA listed | — |
| Rivastigmine Tartrate 1.5 mg 46708-0063-10 | Alembic | 1000 capsules | — | AB | FDA listed | — |
| Rivastigmine Tartrate 1.5 mg 55111-0352-01 | Dr. | 100 capsules | — | AB | FDA listed | — |
| Rivastigmine Tartrate 1.5 mg 62332-0063-10 | Alembic | 1000 capsules | — | AB | FDA listed | — |
| Rivastigmine Tartrate 1.5 mgthis 65862-0648-39 | Aurobindo | 3000 capsules | — | AB | FDA listed | — |
| Rivastigmine Tartrate 1.5 mg 71209-0012-03 | Cadila | 60 capsules | — | AB | FDA listed | — |
| Rivastigmine Tartrate 1.5 mg 75834-0133-05 | Nivagen | 500 capsules | — | AB | Discontinued | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 5138Q19F1X
Ammonia is a colorless gas made from nitrogen and hydrogen. It's used in medicines as a pH buffer to maintain the correct acidity level and help keep the product stable.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII R75537T0T4
Hypromellose 2910 is a plant-derived thickening agent made from cellulose. It serves as a binder that holds tablet ingredients together, a film-coating for pills, and a viscosity controller in liquids.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII WZH3C48M4T
Potassium hydroxide is a strong alkaline chemical used in medicines to adjust and maintain the pH level of liquid formulations, helping keep the product stable and the active ingredients effective.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 46N107B71O
Shellac is a natural resin secreted by the lac beetle. It's used as a coating on tablets and capsules to control how quickly the medicine dissolves and to improve appearance and stability.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
14 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Rivastigmine tartrate capsules are an acetylcholinesterase inhibitor indicated for treatment of: Mild-to-moderate dementia of the Alzheimer’s type (AD) ( 1.1 ) Mild-to-moderate dementia associated with Parkinson’s disease (PD) ( 1.2 )
1.1Alzheimer’s Disease Rivastigmine tartrate capsules are indicated for the treatment of mild-to-moderate dementia of the Alzheimer's type (AD).
1.2Parkinson’s Disease Dementia Rivastigmine tartrate capsules are indicated for the treatment of mild-to-moderate dementia associated with Parkinson’s disease (PD).
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Alzheimer’s Disease ( 2.1 ) : Initial Dose: Initiate treatment with 1.5 mg twice a day. Dose Titration: After a minimum of 2 weeks, if tolerated, increase dose to 3 mg twice a day and further to 4.5 mg twice a day and 6 mg twice a day if tolerated with a minimum of 2 weeks at each dose Parkinson’s Disease Dementia (PDD) ( 2.2 ) : Initial Dose: Initiate treatment with 1.5 mg twice a day. Dose Titration: After a minimum of 4 weeks, if tolerated, increase dose to 3 mg twice a day and further to 4.5 mg twice a day and 6 mg twice a day if tolerated with a minimum of 4 weeks at each dose.
Rivastigmine tartrate capsules should be taken with meals in divided doses in the morning and evening ( 2.1 , 2.2 ). Rivastigmine tartrate oral solution and rivastigmine tartrate capsules may be interchanged at equal doses ( 2.4 ).
2.1Dosing in Alzheimer's Disease Rivastigmine tartrate capsules should be taken with meals in divided doses in the morning and evening. The recommended dosage of rivastigmine tartrate capsules in Alzheimer’s disease (AD) is 6 mg to 12 mg per day, administered twice a day (daily doses of 3 mg to 6 mg twice a day). There is evidence from the clinical trials that doses at the higher end of this range may be more beneficial.
Initial Dose Initiate treatment with the 1.5 mg twice a day with rivastigmine tartrate capsules. Dose Titration After a minimum of 2 weeks and if well tolerated, increase the dose to 3 mg twice a day. Subsequent increases to 4.5 mg twice a day and 6 mg twice a day should be attempted after a minimum of 2 weeks at the previous dose and if well tolerated.
The maximum dose is 6 mg twice a day (12 mg per day).
2.2Dosing in Parkinson's Disease Dementia Rivastigmine tartrate capsules should be taken with meals in divided doses in the morning and evening. The dosage of rivastigmine tartrate capsules shown to be effective in the single controlled clinical trial conducted in dementia associated with Parkinson’s disease is 3 mg to 12 mg per day, administered twice a day (daily doses of 1.5 mg to 6 mg twice a day). Initial Dose Initiate treatment with the 1.5 mg twice a day with rivastigmine tartrate capsules.
Dose Titration After a minimum of 4 weeks and if well tolerated, increase the dose to 3 mg twice a day. Subsequent increases to 4.5 mg twice a day and 6 mg twice a day should be attempted after a minimum of 4 weeks at the previous dose and if well tolerated. The maximum dose is 6 mg twice a day (12 mg per day).
2.3Interruption of Treatment If adverse effects (e.g., nausea, vomiting, abdominal pain, loss of appetite) cause intolerance during treatment, the patient should be instructed to discontinue treatment for several doses and then restart at the same or next lower dose level. If dosing is interrupted for 3 days or fewer, restart treatment with the same or lower dose of rivastigmine tartrate capsules. If dosing is interrupted for more than 3 days, treatment should be restarted with 1.5 mg twice a day and titrated as described above [see Warnings and Precautions (5.1) ] .
2.4Dosing in Specific Populations Dosing Modifications in Patients with Renal Impairment Patients with moderate and severe renal impairment may be able to only tolerate lower doses. Dosing Modifications in Patients with Hepatic Impairment Patients with mild (Child-Pugh score 5 to 6) and moderate (Child-Pugh score 7 to 9) hepatic impairment may be able to only tolerate lower doses. No data are available on the use of rivastigmine in patients with severe hepatic impairment.
Dosing Modifications in Patients with Low Body Weight Carefully titrate and monitor patients with low body weight (less than 50 kg) for toxicities (e.g., excessive nausea, vomiting), and consider reducing the dose if such toxicities develop.
2.5Important Administration Instructions Rivastigmine tartrate oral solution and rivastigmine tartrate capsules may be interchanged at equal doses.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Capsules: 1.5 mg, 3 mg, 4.5 mg, or 6 mg (3.1)
3.1Rivastigmine Tartrate Capsules USP Capsules, containing rivastigmine tartrate USP equivalent to 1.5 mg, 3 mg, 4.5 mg, or 6 mg of rivastigmine base, are available as follows: 1.5 mg capsule – yellow cap and yellow body colored size ‘2’ capsules imprinted in black ink with ‘H’ on cap and ‘67’ on body, containing white to off-white granular powder. 3 mg capsule – orange cap and orange body colored size ‘2’ capsules imprinted in black ink with ‘H’ on cap and ‘68’ on body, containing white to off-white granular powder.
4.5mg capsule – red cap and red body colored size ‘2’ capsules imprinted in black ink with ‘H’ on cap and ‘69’ on body, containing white to off-white granular powder. 6 mg capsule – red cap and orange body colored size ‘2’ capsules imprinted in black ink with ‘H’ on cap and ‘70’ on body, containing white to off-white granular powder.
⛔ Contraindications ▾
4 CONTRAINDICATIONS Rivastigmine tartrate capsules are contraindicated in patients with: known hypersensitivity to rivastigmine, other carbamate derivatives or other components of the formulation [see Description ( 11 )] a previous history of application site reaction with rivastigmine transdermal patch suggestive of allergic contact dermatitis, in the absence of negative allergy testing [see Warnings and Precautions (5.2)] Isolated cases of generalized skin reactions have been described in postmarketing experience [see Adverse Reactions ( 6.2 )] .
Known hypersensitivity to rivastigmine, other carbamate derivatives or other components of the formulation. (4) History of application site reaction with rivastigmine transdermal patch suggestive of allergic contact dermatitis, in the absence of negative allergy testing. (4 , 5.2)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Gastrointestinal adverse reactions may include significant nausea, vomiting, diarrhea, anorexia/decreased appetite, and weight loss, and may necessitate treatment interruption. Dehydration may result from prolonged vomiting or diarrhea and can be associated with serious outcomes. ( 5.1 ) Discontinue rivastigmine in case of disseminated allergic dermatitis, which may occur after oral or transdermal administration ( 4 , 5.2 ).
In patients with suspected allergic contact dermatitis after transdermal rivastigmine use, switch to oral rivastigmine only after negative allergy testing.
5.1Gastrointestinal Adverse Reactions Rivastigmine tartrate can cause gastrointestinal adverse reactions, including significant nausea, vomiting, diarrhea, anorexia/decreased appetite, and weight loss. Dehydration may result from prolonged vomiting or diarrhea and can be associated with serious outcomes. The incidence and severity of these reactions are dose-related [see Adverse Reactions (6.1) ] .
For this reason, patients should always be started at a dose of 1.5 mg twice a day and titrated to their maintenance dose. If treatment is interrupted for longer than 3 days, treatment should be reinitiated with the lowest daily dose [see Dosage and Administration (2.3) ] to reduce the possibility of severe vomiting and its potentially serious sequelae (e.g., there has been one postmarketing report of severe vomiting with esophageal rupture following inappropriate reinitiation of treatment with a 4.5 mg dose after 8 weeks of treatment interruption).
Inform caregivers to monitor for gastrointestinal adverse reactions and to inform the physician if they occur. It is critical to inform caregivers that if therapy has been interrupted for more than 3 days because of intolerance, the next dose should not be administered without contacting the physician regarding proper retitration.
5.2Allergic Dermatitis There have been isolated postmarketing reports of patients experiencing disseminated allergic dermatitis when administered rivastigmine irrespective of the route of administration (oral or transdermal). Treatment should be discontinued if disseminated allergic dermatitis occurs [see Contraindications (4) ] . Patients and caregivers should be instructed accordingly [see Patient Counseling Information (17) ] .
In patients who develop application site reactions, suggestive of allergic contact dermatitis to rivastigmine tartrate patch and who still require rivastigmine, treatment should be switched to oral rivastigmine only after negative allergy testing and under close medical supervision. It is possible that some patients sensitized to rivastigmine by exposure to rivastigmine patch may not be able to take rivastigmine in any form.
5.3Other Adverse Reactions from Increased Cholinergic Activity Neurologic Effects Extrapyramidal Symptoms : Cholinomimetics, including rivastigmine may exacerbate or induce extrapyramidal symptoms. Worsening of parkinsonian symptoms, particularly tremor has been observed in patients with dementia associated with Parkinson’s disease who were treated with rivastigmine tartrate capsules. Seizures : Drugs that increase cholinergic activity are believed to have some potential for causing seizures.
However, seizure activity also may be a manifestation of Alzheimer's disease. Peptic Ulcers/Gastrointestinal Bleeding Cholinesterase inhibitors, including rivastigmine, may be expected to increase gastric acid secretion due to increased cholinergic activity. Monitor patients using rivastigmine tartrate for symptoms of active or occult gastrointestinal bleeding, especially those at increased risk for developing ulcers, e.g., those with a history of ulcer disease or those receiving concurrent nonsteroidal anti-inflammatory drugs (NSAIDs).
Clinical studies of rivastigmine have shown no significant increase, relative to placebo, in the incidence of either peptic ulcer disease or gastrointestinal bleeding. Use with Anesthesia R… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are described below and elsewhere in the labeling: Gastrointestinal Adverse Reactions [see Warnings and Precautions (5.1) ] Allergic Dermatitis [see Warnings and Precautions (5.2) ] Other Adverse Reactions from Increased Cholinergic Activity [see Warnings and Precautions (5.3) ] Most common adverse reactions (greater than 5% and 2 times greater than placebo): nausea, vomiting, anorexia, dyspepsia, and asthenia ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Aurobindo Pharma USA, Inc. at 1-866-850-2876 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Rivastigmine tartrate has been administered to over 5,297 individuals during clinical trials worldwide. Of these, 4,326 patients have been treated for at least 3 months, 3,407 patients have been treated for at least 6 months, 2,150 patients have been treated for 1 year, 1,250 patients have been treated for 2 years, and 168 patients have been treated for over 3 years.
With regard to exposure to the highest dose, 2,809 patients were exposed to doses of 10 mg to 12 mg, 2,615 patients treated for 3 months, 2,328 patients treated for 6 months, 1,378 patients treated for 1 year, 917 patients treated for 2 years, and 129 patients treated for over 3 years. Mild-to-Moderate Alzheimer’s Disease Most Common Adverse Reactions The most common adverse reactions, defined as those occurring at a frequency of at least 5% and twice the placebo rate, are largely predicted by rivastigmine tartrate's cholinergic effects.
These include nausea, vomiting, anorexia, dyspepsia, and asthenia. Gastrointestinal Adverse Reactions Rivastigmine tartrate use is associated with significant nausea, vomiting, and weight loss [see Warnings and Precautions (5.1)] . Discontinuation Rates The rate of discontinuation due to adverse events in controlled clinical trials of rivastigmine tartrate was 15% for patients receiving 6 mg to 12 mg per day compared to 5% for patients on placebo during forced weekly dose titration.
While on a maintenance dose, the rates were 6% for patients on rivastigmine tartrate compared to 4% for those on placebo. The most common adverse reactions leading to discontinuation, defined as those occurring in at least 2% of patients and at twice the incidence seen in placebo patients, are shown in Table 1. Table 1: Most Frequent Adverse Reactions Leading to Withdrawal from Clinical Trials During Titration and Maintenance in Patients Receiving 6 mg to 12 mg per day Rivastigmine Tartrate Using a Forced-Dose Titration Study Phase Titration Maintenance Overall Rivastigmine Tartrate ≥ 6 to 12 mg/day (n = 1,189) Placebo (n = 868) Rivastigmine Tartrate ≥ 6 to 12 mg/day (n = 987) Placebo (n = 788) Rivastigmine Tartrate ≥ 6 to 12 mg/day (n = 1,189) Placebo (n = 868) Event/% Discontinuing Nausea 8 < 1 1 < 1 8 1 Vomiting 4 < 1 1 < 1 5 < 1 Anorexia 2 0 1 < 1 3 < 1 Dizziness 2 < 1 1 < 1 2 < 1 Adverse Reactions Observed at an Incidence of at Least 2% Table 2 lists adverse reactions that occurred in at least 2% of patients in placebo-controlled trials, and for which the rate of occurrence was greater for patients treated with rivastigmine tartrate doses of 6 mg to 12 mg per day than for those treated with placebo.
In general, adverse reactions were less frequent later in the course of treatment. No systematic effect of race or age could be determined from the incidence of adverse reactions in the controlled studies. Nausea, vomiting and weight loss were more frequent in women than men.
Table 2: Proportion of Adverse Reactions Observed with a Frequency of Greater Than or Equal to 2% and at a Rate Greater than Placebo in Clinical Trials Body System/Adverse Reaction Riva… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Concomitant use with metoclopramide, beta-blockers, or cholinomimetic and anticholinergic drugs is not recommended ( 7.1 , 7.2 , 7.3 )
7.1Metoclopramide Due to the risk of additive extrapyramidal adverse reactions, the concomitant use of metoclopramide and rivastigmine tartrate is not recommended.
7.2Cholinomimetic and Anticholinergic Medications Rivastigmine tartrate may increase the cholinergic effects of other cholinomimetic medications and may also interfere with the activity of anticholinergic medications (e.g., oxybutynin, tolterodine). Concomitant use of rivastigmine tartrate with medications having these pharmacologic effects is not recommended unless deemed clinically necessary [see Warnings and Precautions (5.3) ] .
7.3Beta-blockers Additive bradycardic effects resulting in syncope may occur when rivastigmine tartrate is used concomitantly with beta-blockers, especially cardioselective beta-blockers (including atenolol). Concomitant use of rivastigmine tartrate with beta-blockers is not recommended.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary There are no adequate data on the developmental risks associated with the use of rivastigmine tartrate in pregnant women. In animals, no adverse effects on embryo-fetal development were observed at oral doses 2 to 4 times the maximum recommended human dose (MRHD) (see Data) . The background risk of major birth defects and miscarriage for the indicated population is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data Oral administration of rivastigmine to pregnant rats and rabbits throughout organogenesis produced no adverse effects on embryo-fetal development up to the highest dose tested (2.3 mg/kg/day), which is 2 and 4 times, respectively, the MRHD of 12 mg per day on a body surface area (mg/m 2 ) basis.
8.2Lactation Risk Summary There are no data on the presence of rivastigmine in human milk, the effects on the breastfed infant, or the effects of rivastigmine on milk production. Rivastigmine and its metabolites are excreted in rat milk following oral administration of rivastigmine; levels of rivastigmine plus metabolites in rat milk are approximately 2 times that in maternal plasma. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for rivastigmine tartrate and any potential adverse effects on the breastfed infant from rivastigmine tartrate or from the underlying maternal condition.
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established. The use of rivastigmine tartrate in pediatric patients (below 18 years of age) is not recommended.
8.5Geriatric Use Of the total number of patients in clinical studies of rivastigmine tartrate, 86% were 65 years and older while 46% were 75 years and older. No overall differences in safety or effectiveness were observed between these patients and younger patients, and other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out.
8.6Renal Impairment Patients with moderate to severe renal impairment may be able to only tolerate lower doses [see Dosage and Administration (2.4) , Clinical Pharmacology (12.3) ] .
8.7Hepatic Impairment Patients with mild or moderate hepatic impairment may be able to only tolerate lower doses [see Dosage and Administration (2.4) , Clinical Pharmacology (12.3) ] . No data are available on the use of rivastigmine tartrate in patients with severe hepatic impairment.
8.8Low or High Body Weight Because rivastigmine blood levels vary with weight, careful titration and monitoring should be performed in patients with low or high body weights [see Dosage and Administration (2.4) , Clinical Pharmacology (12.3) ] .
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no adequate data on the developmental risks associated with the use of rivastigmine tartrate in pregnant women. In animals, no adverse effects on embryo-fetal development were observed at oral doses 2 to 4 times the maximum recommended human dose (MRHD) (see Data) . The background risk of major birth defects and miscarriage for the indicated population is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data Oral administration of rivastigmine to pregnant rats and rabbits throughout organogenesis produced no adverse effects on embryo-fetal development up to the highest dose tested (2.3 mg/kg/day), which is 2 and 4 times, respectively, the MRHD of 12 mg per day on a body surface area (mg/m 2 ) basis.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established. The use of rivastigmine tartrate in pediatric patients (below 18 years of age) is not recommended.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the total number of patients in clinical studies of rivastigmine tartrate, 86% were 65 years and older while 46% were 75 years and older. No overall differences in safety or effectiveness were observed between these patients and younger patients, and other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out.
🆘 Overdosage ▾
10 OVERDOSAGE Because strategies for the management of overdose are continually evolving, it is advisable to contact a Poison Control Center to determine the latest recommendations for the management of an overdose of any drug. As rivastigmine has a short plasma half-life of about 1 hour and a moderate duration of acetylcholinesterase inhibition of 8 to 10 hours, it is recommended that in cases of asymptomatic overdoses, no further dose of rivastigmine tartrate should be administered for the next 24 hours. As in any case of overdose, general supportive measures should be utilized.
Overdosage with cholinesterase inhibitors can result in cholinergic crisis characterized by severe nausea, vomiting, salivation, sweating, bradycardia, hypotension, respiratory depression, collapse and convulsions. Increasing muscle weakness is a possibility and may result in death if respiratory muscles are involved. Atypical responses in blood pressure and heart rate have been reported with other drugs that increase cholinergic activity when coadministered with quaternary anticholinergics such as glycopyrrolate.
Additional symptoms associated with rivastigmine overdose are diarrhea, abdominal pain, dizziness, tremor, headache, somnolence, confusional state, hyperhidrosis, hypertension, hallucinations and malaise. Due to the short half-life of rivastigmine, dialysis (hemodialysis, peritoneal dialysis, or hemofiltration) would not be clinically indicated in the event of an overdose. In overdoses accompanied by severe nausea and vomiting, the use of antiemetics should be considered.
A fatal outcome has been rarely reported with rivastigmine.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Although the precise mechanism of action of rivastigmine is unknown, it is thought to exert its therapeutic effect by enhancing cholinergic function. This is accomplished by increasing the concentration of acetylcholine through reversible inhibition of its hydrolysis by cholinesterase. Therefore, the effect of rivastigmine may lessen as the disease process advances and fewer cholinergic neurons remain functionally intact.
There is no evidence that rivastigmine alters the course of the underlying dementing process.
12.2Pharmacodynamics After a 6 mg dose of rivastigmine, anticholinesterase activity is present in cerebrospinal fluid (CSF) for about 10 hours, with a maximum inhibition of about 60% 5 hours after dosing. In vitro and in vivo studies demonstrate that the inhibition of cholinesterase by rivastigmine is not affected by the concomitant administration of memantine, an N-methyl-D-aspartate receptor antagonist.
12.3Pharmacokinetics Rivastigmine shows linear pharmacokinetics up to 3 mg twice a day but is nonlinear at higher doses. Doubling the dose from 3 mg to 6 mg twice a day results in a 3-fold increase in area under the curve (AUC). The elimination half-life is about 1.5 hours, with most elimination as metabolites via the urine.
Absorption Rivastigmine is rapidly and completely absorbed. Peak plasma concentrations are reached in approximately 1 hour. Absolute bioavailability after a 3 mg dose is about 36%.
Administration of rivastigmine tartrate with food delays absorption (T max ) by 90 minutes lowers C max by approximately 30% and increases AUC by approximately 30%. Distribution Rivastigmine is weakly bound to plasma proteins (approximately 40%) over the therapeutic range. It readily crosses the blood-brain barrier, reaching CSF peak concentrations in 1.4 to 2.6 hours.
It has an apparent volume of distribution (V D ) in the range of 1.8 to
2.7L/kg. Metabolism Rivastigmine is rapidly and extensively metabolized, primarily via cholinesterase-mediated hydrolysis to the decarbamylated metabolite. Based on evidence from in vitro and animal studies, the major cytochrome P450 isozymes are minimally involved in rivastigmine metabolism.
Consistent with these observations is the finding that no drug interactions related to cytochrome P450 have been observed in humans. Elimination The major pathway of elimination is via the kidneys. Following administration of 14 C-rivastigmine to 6 healthy volunteers, total recovery of radioactivity over 120 hours was 97% in urine and 0.4% in feces.
No parent drug was detected in urine. The sulfate conjugate of the decarbamylated metabolite is the major component excreted in urine and represents 40% of the dose. Mean oral clearance of rivastigmine is 1.8 ±
0.6L/min after 6 mg twice a day. Age Following a single 2.5 mg oral dose to elderly volunteers (60 years and older, n = 24) and younger volunteers (n = 24), mean oral clearance of rivastigmine was 30% lower in elderly (7 L/min) than in younger subjects (10 L/min). Gender and Race Population pharmacokinetic analysis of oral rivastigmine indicated that neither gender (n = 277 males and 348 females) nor race (n = 575 Caucasian, 34 Black, 4 Asian, and 12 Other) affected clearance of the drug.
Body Weight A relationship between drug exposure at steady-state (rivastigmine and metabolite NAP226-90) and body weight was observed in Alzheimer’s dementia patients. Rivastigmine exposure is higher in subjects with low body weight. Compared to a patient with a body weight of 65 kg, the rivastigmine steady-state concentrations in a patient with a body weight of 35 kg would be approximately doubled, while for a patient with a body weight of 100 kg the concentrations would be approximately halved.
Renal Impairment Following a single 3 mg dose, mean oral clearance of rivastigmine is 64% lower in moderately impaired renal patients (n = 8, GFR = 10 to 50 mL/min) than in healthy subjects (n = 10, GFR greater t… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Although the precise mechanism of action of rivastigmine is unknown, it is thought to exert its therapeutic effect by enhancing cholinergic function. This is accomplished by increasing the concentration of acetylcholine through reversible inhibition of its hydrolysis by cholinesterase. Therefore, the effect of rivastigmine may lessen as the disease process advances and fewer cholinergic neurons remain functionally intact.
There is no evidence that rivastigmine alters the course of the underlying dementing process.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Rivastigmine tartrate capsules, USP equivalent to 1.5 mg, 3 mg, 4.5 mg, or 6 mg of rivastigmine base are available as follows: Rivastigmine Tartrate Capsules USP, 1.5 mg are yellow cap and yellow body colored size ‘2’ capsules imprinted in black ink with ‘H’ on cap and ‘67’ on body, containing white to off-white granular powder. Bottles of 60 NDC 65862-648-60 Bottles of 500 NDC 65862-648-05 10 x 10 Unit-dose Capsules NDC 65862-648-78 Rivastigmine Tartrate Capsules USP, 3 mg are orange cap and orange body colored size ‘2’ capsules imprinted in black ink with ‘H’ on cap and ‘68’ on body, containing white to off-white granular powder.
Bottles of 60 NDC 65862-649-60 Bottles of 500 NDC 65862-649-05 10 x 10 Unit-dose Capsules NDC 65862-649-78 Rivastigmine Tartrate Capsules USP, 4.5 mg are red cap and red body colored size ‘2’ capsules imprinted in black ink with ‘H’ on cap and ‘69’ on body, containing white to off-white granular powder. Bottles of 60 NDC 65862-650-60 Bottles of 500 NDC 65862-650-05 10 x 10 Unit-dose Capsules NDC 65862-650-78 Rivastigmine Tartrate Capsules USP, 6 mg are red cap and orange body colored size ‘2’ capsules imprinted in black ink with ‘H’ on cap and ‘70’ on body, containing white to off-white granular powder.
Bottles of 60 NDC 65862-651-60 Bottles of 500 NDC 65862-651-05 10 x 10 Unit-dose Capsules NDC 65862-651-78 Store at 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature]. Store in a tight container.
📋 Description ▾
11 DESCRIPTION Rivastigmine tartrate is a reversible cholinesterase inhibitor and is known chemically as (S)-N-Ethyl-N-methyl-3-[1-(dimethylamino)ethyl]-phenyl carbamate hydrogen-(2R,3R)-tartrate. Rivastigmine tartrate is commonly referred to in the pharmacological literature as SDZ ENA 713 or ENA 713. It has a molecular formula of C 14 H 22 N 2 O 2 • C 4 H 6 O 6 (hydrogen tartrate salt–hta salt) and a molecular weight of 400.43 g/mol (hta salt).
Rivastigmine tartrate USP is a white to off-white powder that is very soluble in water, soluble in ethanol and acetonitrile, slightly soluble in n-octanol and very slightly soluble in ethyl acetate. The distribution coefficient at 37°C in n-octanol/phosphate buffer solution pH 7 is 3.0. Rivastigmine tartrate capsules, USP contain rivastigmine tartrate USP, equivalent to 1.5 mg, 3 mg, 4.5 mg, and 6 mg of rivastigmine base for oral administration.
Inactive ingredients are colloidal silicon dioxide , hypromellose, magnesium stearate, and microcrystalline cellulose. Each hard-gelatin capsule contains gelatin, iron oxide red, iron oxide yellow, sodium lauryl sulfate, and titanium dioxide. The capsules are printed with edible ink containing black iron oxide, potassium hydroxide, propylene glycol, shellac and strong ammonia solution.
Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling. Gastrointestinal Adverse Reactions Caregivers should be advised of the high incidence of nausea and vomiting associated with the use of the drug along with the possibility of anorexia and weight loss. Caregivers should be encouraged to monitor for these adverse events and inform the physician if they occur.
It is critical to inform caregivers that if therapy has been interrupted for more than several days, the next dose should not be administered until they have discussed this with the physician [see Warnings and Precautions (5.1) ] . Skin Reactions Caregivers and patients should be advised that allergic skin reactions have been reported in association with rivastigmine tartrate regardless of formulation (capsules, oral solution or transdermal patch). In case of skin reaction while taking rivastigmine tartrate, patients should consult with their physician immediately [see Warnings and Precautions (5.2) ].
Concomitant Use of Drugs with Cholinergic Action Caregivers and patients should be advised that cholinomimetics, including rivastigmine, may exacerbate or induce extrapyramidal symptoms. Worsening in patients with Parkinson’s disease, including an increased incidence or intensity of tremor, has been observed [see Warnings and Precautions (5.3) ] . Pregnancy Advise patients to notify their healthcare provider if they are pregnant or plan to become pregnant.
Distributed by: Aurobindo Pharma USA, Inc. 279 Princeton-Hightstown Road East Windsor, NJ 08520 Manufactured by: Aurobindo Pharma Limited Hyderabad-500 038, India Revised: 04/2019
🍼 Nursing Mothers ▾
8.2Lactation Risk Summary There are no data on the presence of rivastigmine in human milk, the effects on the breastfed infant, or the effects of rivastigmine on milk production. Rivastigmine and its metabolites are excreted in rat milk following oral administration of rivastigmine; levels of rivastigmine plus metabolites in rat milk are approximately 2 times that in maternal plasma. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for rivastigmine tartrate and any potential adverse effects on the breastfed infant from rivastigmine tartrate or from the underlying maternal condition.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Rivastigmine shows linear pharmacokinetics up to 3 mg twice a day but is nonlinear at higher doses. Doubling the dose from 3 mg to 6 mg twice a day results in a 3-fold increase in area under the curve (AUC). The elimination half-life is about 1.5 hours, with most elimination as metabolites via the urine.
Absorption Rivastigmine is rapidly and completely absorbed. Peak plasma concentrations are reached in approximately 1 hour. Absolute bioavailability after a 3 mg dose is about 36%.
Administration of rivastigmine tartrate with food delays absorption (T max ) by 90 minutes lowers C max by approximately 30% and increases AUC by approximately 30%. Distribution Rivastigmine is weakly bound to plasma proteins (approximately 40%) over the therapeutic range. It readily crosses the blood-brain barrier, reaching CSF peak concentrations in 1.4 to 2.6 hours.
It has an apparent volume of distribution (V D ) in the range of 1.8 to
2.7L/kg. Metabolism Rivastigmine is rapidly and extensively metabolized, primarily via cholinesterase-mediated hydrolysis to the decarbamylated metabolite. Based on evidence from in vitro and animal studies, the major cytochrome P450 isozymes are minimally involved in rivastigmine metabolism.
Consistent with these observations is the finding that no drug interactions related to cytochrome P450 have been observed in humans. Elimination The major pathway of elimination is via the kidneys. Following administration of 14 C-rivastigmine to 6 healthy volunteers, total recovery of radioactivity over 120 hours was 97% in urine and 0.4% in feces.
No parent drug was detected in urine. The sulfate conjugate of the decarbamylated metabolite is the major component excreted in urine and represents 40% of the dose. Mean oral clearance of rivastigmine is 1.8 ±
0.6L/min after 6 mg twice a day. Age Following a single 2.5 mg oral dose to elderly volunteers (60 years and older, n = 24) and younger volunteers (n = 24), mean oral clearance of rivastigmine was 30% lower in elderly (7 L/min) than in younger subjects (10 L/min). Gender and Race Population pharmacokinetic analysis of oral rivastigmine indicated that neither gender (n = 277 males and 348 females) nor race (n = 575 Caucasian, 34 Black, 4 Asian, and 12 Other) affected clearance of the drug.
Body Weight A relationship between drug exposure at steady-state (rivastigmine and metabolite NAP226-90) and body weight was observed in Alzheimer’s dementia patients. Rivastigmine exposure is higher in subjects with low body weight. Compared to a patient with a body weight of 65 kg, the rivastigmine steady-state concentrations in a patient with a body weight of 35 kg would be approximately doubled, while for a patient with a body weight of 100 kg the concentrations would be approximately halved.
Renal Impairment Following a single 3 mg dose, mean oral clearance of rivastigmine is 64% lower in moderately impaired renal patients (n = 8, GFR = 10 to 50 mL/min) than in healthy subjects (n = 10, GFR greater than or equal to 60 mL/min); CL/F=1.7 L/min and
4.8L/min, respectively. In patients with severe renal impairment (n = 8, GFR less than 10 mL/min), mean oral clearance of rivastigmine is 43% higher than in healthy subjects (n = 10, GFR greater than or equal to 60 mL/min); CL/F =
6.9 L/min and
4.8L/min, respectively. For unexplained reasons, the severely impaired renal patients had a higher clearance of rivastigmine than moderately impaired patients. Hepatic Impairment Following a single 3 mg dose, mean oral clearance of rivastigmine was 60% lower in hepatically impaired patients (n = 10, biopsy proven) than in healthy subjects (n = 10).
After multiple 6 mg twice a day oral dosing, the mean clearance of rivastigmine was 65% lower in mild (n = 7, Child-Pugh score 5 to 6), and moderate (n = 3, Child-Pugh score 7 to 9) hepatically impaired patients (biopsy proven, liver cirrhosis) than in healthy subjects (n = 10). Smoking Following oral rivastigmine administration (up… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics After a 6 mg dose of rivastigmine, anticholinesterase activity is present in cerebrospinal fluid (CSF) for about 10 hours, with a maximum inhibition of about 60% 5 hours after dosing. In vitro and in vivo studies demonstrate that the inhibition of cholinesterase by rivastigmine is not affected by the concomitant administration of memantine, an N-methyl-D-aspartate receptor antagonist.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES Mild-to-Moderate Alzheimer’s Disease The effectiveness of rivastigmine tartrate as a treatment for Alzheimer's disease is demonstrated by the results of 2 randomized, double-blind, placebo-controlled clinical investigations ( Study 1 and Study 2 ) in patients with Alzheimer's disease [diagnosed by NINCDS-ADRDA and DSM-IV criteria, Mini-Mental State Examination (MMSE) greater than or equal to 10 and less than or equal to 26, and the Global Deterioration Scale (GDS)]. The mean age of patients participating in rivastigmine tartrate trials was 73 years with a range of 41 to 95.
Approximately 59% of patients were women and 41% were men. The racial distribution was Caucasian 87%, Black 4%, and other races 9%. In each study, the effectiveness of rivastigmine tartrate was evaluated using a dual outcome assessment strategy.
The ability of rivastigmine tartrate to improve cognitive performance was assessed with the cognitive subscale of the Alzheimer's Disease Assessment Scale (ADAS-cog), a multi-item instrument that has been extensively validated in longitudinal cohorts of Alzheimer's disease patients. The ADAS-cog examines selected aspects of cognitive performance including elements of memory, orientation, attention, reasoning, language, and praxis. The ADAS-cog scoring range is from 0 to 70, with higher scores indicating greater cognitive impairment.
Elderly normal adults may score as low as 0 or 1, but it is not unusual for non-demented adults to score slightly higher. The patients recruited as participants in each study had mean scores on ADAS-cog of approximately 23 units, with a range from 1 to 61. Experience gained in longitudinal studies of ambulatory patients with mild-to-moderate Alzheimer's disease suggests that they gain 6 to 12 units a year on the ADAS-cog.
Lesser degrees of change, however, are seen in patients with very mild or very advanced disease because the ADAS-cog is not uniformly sensitive to change over the course of the disease. The annualized rate of decline in the placebo patients participating in rivastigmine tartrate trials was approximately 3 to 8 units per year. The ability of rivastigmine tartrate to produce an overall clinical effect was assessed using a Clinician's Interview-Based Impression of Change (CIBIC) that required the use of caregiver information, the CIBIC-Plus.
The CIBIC-Plus is not a single instrument and is not a standardized instrument like the ADAS-cog. Clinical trials for investigational drugs have used a variety of CIBIC formats, each different in terms of depth and structure. As such, results from a CIBIC-Plus reflect clinical experience from the trial or trials in which it was used and cannot be compared directly with the results of CIBIC-Plus evaluations from other clinical trials.
The CIBIC-Plus used in the rivastigmine tartrate trials was a structured instrument based on a comprehensive evaluation at baseline and subsequent time-points of 3 domains: patient cognition, behavior and functioning, including assessment of activities of daily living. It represents the assessment of a skilled clinician using validated scales based on his/her observation at interviews conducted separately with the patient and the caregiver familiar with the behavior of the patient over the interval rated. The CIBIC-Plus is scored as a 7-point categorical rating, ranging from a score of 1, indicating "markedly improved," to a score of 4, indicating "no change" to a score of 7, indicating "marked worsening." The CIBIC-Plus has not been systematically compared directly to assessments not using information from caregivers or other global methods.
U.S. 26-Week Study of Rivastigmine Tartrate in Mild-to-Moderate Alzheimer’s Disease (Study 1) In a study of 26 weeks duration, 699 patients were randomized to either a dose range of 1 mg to 4 mg or 6 mg to 12 mg of rivastigmine tartrate per day or to placebo, each given in divided doses. The 26-week study was divided into a 12-week forced-dose titr… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis In oral carcinogenicity studies conducted at doses up to 1.1 mg/kg/day in rats and 1.6 mg/kg/day in mice, rivastigmine was not carcinogenic. These doses are less than the maximum recommended human dose (MRHD) of 12 mg per day on an mg/m 2 basis. Mutagenesis Rivastigmine was clastogenic in in vitro chromosomal aberration assays in mammalian cells in the presence, but not the absence, of metabolic activation.
Rivastigmine was negative in an in vitro bacterial reverse mutation (Ames) assay, an in vitro HGPRT assay, and in an in vivo mouse micronucleus test. Impairment of Fertility Rivastigmine had no effect on fertility or reproductive performance in rats at oral doses up to 1.1 mg/kg/day, a dose less than the MRHD on an mg/m 2 basis.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis In oral carcinogenicity studies conducted at doses up to 1.1 mg/kg/day in rats and 1.6 mg/kg/day in mice, rivastigmine was not carcinogenic. These doses are less than the maximum recommended human dose (MRHD) of 12 mg per day on an mg/m 2 basis. Mutagenesis Rivastigmine was clastogenic in in vitro chromosomal aberration assays in mammalian cells in the presence, but not the absence, of metabolic activation.
Rivastigmine was negative in an in vitro bacterial reverse mutation (Ames) assay, an in vitro HGPRT assay, and in an in vivo mouse micronucleus test. Impairment of Fertility Rivastigmine had no effect on fertility or reproductive performance in rats at oral doses up to 1.1 mg/kg/day, a dose less than the MRHD on an mg/m 2 basis.
📄 Package Label / Principal Display Panel ▾
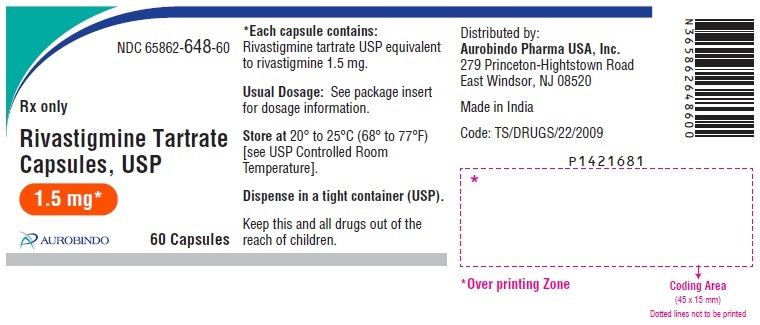
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 1.5 mg (60 Capsules Bottle) NDC 65862-648-60 Rx only Rivastigmine Tartrate Capsules, USP 1.5 mg* AUROBINDO 60 Capsules PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 1.5 mg (60 Capsules Bottle)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 1.5 mg Blister Carton (10 x 10 Unit-dose) NDC 65862-648-78 Rx only Rivastigmine Tartrate Capsules, USP 1.5 mg* AUROBINDO 100 (10 x 10) Unit-dose Capsules PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 1.5 mg Blister Carton (10 x 10 Unit-dose)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 3 mg (60 Capsules Bottle) NDC 65862-649-60 Rx only Rivastigmine Tartrate Capsules, USP 3 mg* AUROBINDO 60 Capsules PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 3 mg (60 Capsules Bottle)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 3 mg Blister Carton (10 x 10 Unit-dose) NDC 65862-649-78 Rx only Rivastigmine Tartrate Capsules, USP 3 mg* AUROBINDO 100 (10 x 10) Unit-dose Capsules PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 3 mg Blister Carton (10 x 10 Unit-dose)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 4.5 mg (60 Capsules Bottle) NDC 65862-650-60 Rx only Rivastigmine Tartrate Capsules, USP 4.5 mg* AUROBINDO 60 Capsules PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 4.5 mg (60 Capsules Bottle)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 4.5 mg Blister Carton (10 x 10 Unit-dose) NDC 65862-650-78 Rx only Rivastigmine Tartrate Capsules, USP 4.5 mg* AUROBINDO 100 (10 x 10) Unit-dose Capsules PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 4.5 mg Blister Carton (10 x 10 Unit-dose)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 6 mg (60 Capsules Bottle) NDC 65862-651-60 Rx only Rivastigmine Tartrate Capsules, USP 6 mg* AUROBINDO 60 Capsules PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 6 mg (60 Capsules Bottle)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 6 mg Blister Carton (10 x 10 Unit-dose) NDC 65862-651-78 Rx only Rivastigmine Tartrate Capsules, USP 6 mg* AUROBINDO 100 (10 x 10) Unit-dose Capsules PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 6 mg Blister Carton (10 x 10 Unit-dose)
Medicaid utilization by pack size
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |