
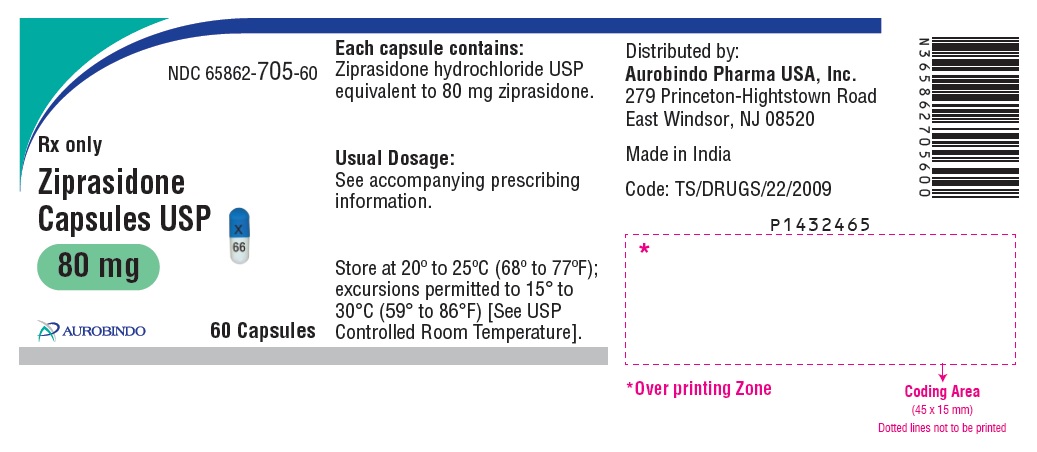
Ziprasidone Hydrochloride 80 mg Capsule, 60-count
🆔 Identity & classification
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Ziprasidone is used to treat schizophrenia (a mental illness that affects how a person thinks, feels and behaves) and bipolar disorder (a disease that causes depression, mania, and other abnormal moods). Ziprasidone is in a class of medications called atypical antipsychotics. It works by changing the activity of certain natural substances in the brain.
Read the full MedlinePlus article ↗- It's not just a suggestion — food actually doubles how much ziprasidone your body absorbs. If you take it on an empty stomach, you may only be getting half the medication you need,...
- Why do I have to take this with food every single time?
- It's a real consideration, which is why your prescriber chose this medication carefully. Ziprasidone can slightly lengthen a part of your heart's electrical cycle called the QT int...
- I've heard this can affect my heart. Should I be worried?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 5138Q19F1X
Ammonia is a colorless gas made from nitrogen and hydrogen. It's used in medicines as a pH buffer to maintain the correct acidity level and help keep the product stable.
-
UNII 3DYK7UYZ62
Ethylcellulose is a plant-fiber derivative used as a binder and film-coating agent in tablets and capsules. It helps hold ingredients together and can create a protective coating that controls how quickly the medicine dissolves.
-
UNII L06K8R7DQK
A synthetic blue dye approved by the FDA for use in medications and foods. It serves as a colorant to make pills and liquids visually distinct and easier to identify.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII WZH3C48M4T
Potassium hydroxide is a strong alkaline chemical used in medicines to adjust and maintain the pH level of liquid formulations, helping keep the product stable and the active ingredients effective.
-
UNII 46N107B71O
Shellac is a natural resin secreted by the lac beetle. It's used as a coating on tablets and capsules to control how quickly the medicine dissolves and to improve appearance and stability.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
12 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.337 | $20.23 / 60 capsules |
| Medicaid paysCMS SDUD · 12 mo | $0.4935 | $29.61 / 60 capsules |
| Medicare drug plans payPart D · Q2 2026 | $0.5539 | $33.23 / 60 capsules |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Ziprasidone 80 mg 00904-6272-08 | Major | 40 capsules | $0.337 | AB | Availability likely | — |
| ziprasidone 80 mg 16714-0838-01 | NorthStar | 60 capsules | $0.337 | AB | Availability likely | — |
| Ziprasidone Hydrochloride 80 mg 33342-0147-09 | Macleods | 60 capsules | $0.337 | AB | Availability likely | — |
| ziprasidone hydrochloride 80 mg 50268-0814-12 | AvPAK | 20 capsules | $0.337 | AB | Availability likely | — |
| ziprasidone hydrochloride 80 mg 60505-2531-06 | Apotex | 60 capsules | $0.337 | AB | Availability likely | — |
| Ziprasidone 80 mg 62135-0994-60 | Chartwell | 60 capsules | $0.337 | AB | Availability likely | — |
| Ziprasidone Hydrochloride 80 mgthis 65862-0705-60 | Aurobindo | 60 capsules | $0.337 | — | Availability likely | — |
| Ziprasidone Hydrochloride 80 mg 68001-0453-06 | BluePoint | 60 capsules | $0.337 | AB | Availability likely | — |
| Ziprasidone Hydrochloride 80 mg 68084-0106-09 | American | 80 capsules | $0.337 | AB | Availability likely | — |
| Geodon 80 mg 00049-0358-60 | ROERIG | 60 capsules | $31.108 | AB | Availability likely | +9127% |
| Geodon 80 mg 58151-0134-91 | Viatris | 60 capsules | $31.108 | AB | Availability likely | +9127% |
| Geodon 80 mg 00049-0058-60 | ROERIG | 60 capsules | — | AB | Discontinued | — |
| ziprasidone 80 mg 55111-0259-01 | Dr. | 100 capsules | — | AB | FDA listed | — |
| ziprasidone hydrochloride 80 mg 60429-0768-60 | Golden | 60 capsules | — | AB | FDA listed | — |
| ziprasidone hydrochloride 80 mg 63629-6916-01 | Bryant | 60 capsules | — | AB | FDA listed | — |
| ziprasidone hydrochloride 80 mg 70518-1604-00 | REMEDYREPACK | 30 capsules | — | AB | Discontinued | — |
| Ziprasidone Hydrochloride 80 mg 71335-0501-01 | Bryant | 60 capsules | — | AB | FDA listed | — |
| ziprasidone hydrochloride 80 mg 71335-1508-01 | Bryant | 60 capsules | — | AB | FDA listed | — |
| ziprasidone hydrochloride 80 mg 42816-0058-01 | Pfizer | 22160 capsules | — | — | FDA listed | — |
| ziprasidone hydrochloride 80 mg 42816-2004-01 | Pfizer | 22160 capsules | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 65862-0705-60 You're viewing this | 60 CAPSULE in 1 BOTTLE (65862-705-60) | $0.3372 / ea | $20.23 | 2016-12-27 | Active |
| 65862-0705-80 | 8 BLISTER PACK in 1 CARTON (65862-705-80) / 10 CAPSULE in 1 BLISTER PACK (65862-705-10) | — | — | 2016-12-27 | Active |
| 65862-0705-99 | 1000 CAPSULE in 1 BOTTLE (65862-705-99) | — | — | 2016-12-27 | Active |
| 65862-0705-22 | 2000 CAPSULE in 1 BAG (65862-705-22) | — | — | — | Active |
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 65862-0705-60?
What is the difference between NDC 65862-0705-60 and NDC 65862-0705-80?
What NDC number is used to bill for this package of Ziprasidone Hydrochloride 80 mg Capsule?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
🧭 About this NDC listing & data coverage
What "drug for further processing" means
FDA lists this package under the "drug for further processing" marketing category: Aurobindo Pharma Limited supplies it to other companies for further processing or repackaging (blister cards that are later repackaged or co-packaged are a common example). The units themselves are a finished dosage form — which is why pricing or Medicaid data can still appear — but this exact package code may not be the presentation a retail pharmacy dispenses.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | ✓ Available |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Is this NDC FDA-approved?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Where does this data come from?
📄 Full FDA label FDA SPL
🚨 Boxed Warning ▾
WARNING: INCREASED MORTALITY IN ELDERLY PATIENTS WITH DEMENTIA-RELATED PSYCHOSIS Elderly patients with dementia-related psychosis treated with antipsychotic drugs are at an increased risk of death. Ziprasidone hydrochloride is not approved for the treatment of patients with dementia-related psychosis [see Warnings and Precautions (5.1) ] . WARNING: INCREASED MORTALITY IN ELDERLY PATIENTS WITH DEMENTIA-RELATED PSYCHOSIS See full prescribing information for complete boxed warning.
Elderly patients with dementia-related psychosis treated with antipsychotic drugs are at an increased risk of death. Ziprasidone hydrochloride is not approved for the treatment of patients with dementia-related psychosis. ( 5.1 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Ziprasidone capsules are indicated for the treatment of schizophrenia, as monotherapy for the acute treatment of bipolar manic or mixed episodes, and as an adjunct to lithium or valproate for the maintenance treatment of bipolar disorder. When deciding among the alternative treatments available for the condition needing treatment, the prescriber should consider the finding of ziprasidone’s greater capacity to prolong the QT/QTc interval compared to several other antipsychotic drugs [see Warnings and Precautions (5.3) ] .
Prolongation of the QTc interval is associated in some other drugs with the ability to cause torsade de pointes-type arrhythmia, a potentially fatal polymorphic ventricular tachycardia, and sudden death. In many cases this would lead to the conclusion that other drugs should be tried first. Whether ziprasidone will cause torsade de pointes or increase the rate of sudden death is not yet known [see Warnings and Precautions (5.3) ].
Schizophrenia Ziprasidone capsules are indicated for the treatment of schizophrenia in adults [see Clinical Studies (14.1) ] . Bipolar I Disorder (Acute Mixed or Manic Episodes and Maintenance Treatment as an Adjunct to Lithium or Valproate) Ziprasidone capsules are indicated as monotherapy for the acute treatment of adults with manic or mixed episodes associated with bipolar I disorder [see Clinical Studies (14.2)] . Ziprasidone capsules are indicated as an adjunct to lithium or valproate for the maintenance treatment of bipolar I disorder in adults [see Clinical Studies (14.2)] .
Ziprasidone hydrochloride is an atypical antipsychotic. In choosing among treatments, prescribers should be aware of the capacity of ziprasidone capsules to prolong the QT interval and may consider the use of other drugs first. ( 1 ) Ziprasidone capsules are indicated for the: treatment of schizophrenia in adults.
( 1 ) acute treatment of adults as monotherapy of manic or mixed episodes associated with bipolar I disorder. ( 1 ) maintenance treatment of bipolar I disorder as an adjunct to lithium or valproate in adults. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Administer capsules orally with food. Do not open, crush, or chew. ( 2.1 ) Schizophrenia: Initiate at 20 mg twice daily.
Daily dosage may be adjusted up to 80 mg twice daily. Dose adjustments should occur at intervals of not less than 2 days. Safety and efficacy has been demonstrated in doses up to 100 mg twice daily.
The lowest effective dose should be used. ( 2.2 ) Acute treatment of manic/mixed episodes of bipolar I disorder: Initiate at 40 mg twice daily. Increase to 60 mg or 80 mg twice daily on day 2 of treatment.
Subsequent dose adjustments should be based on tolerability and efficacy within the range of 40 to 80 mg twice daily. ( 2.3 ) Maintenance treatment of bipolar I disorder as an adjunct to lithium or valproate: Continue treatment at the same dose on which the patient was initially stabilized, within the range of 40 to 80 mg twice daily. ( 2.3 )
2.1Administration Information for Ziprasidone Capsules Administer ziprasidone capsules orally with food. Swallow capsules whole, do not open, crush, or chew the capsules.
2.2Schizophrenia Dose Selection Ziprasidone capsules should be administered at an initial daily dose of 20 mg twice daily with food. In some patients, daily dosage may subsequently be adjusted on the basis of individual clinical status up to 80 mg twice daily. Dosage adjustments, if indicated, should generally occur at intervals of not less than 2 days, as steady-state is achieved within 1 to 3 days.
In order to ensure use of the lowest effective dose, patients should ordinarily be observed for improvement for several weeks before upward dosage adjustment. Efficacy in schizophrenia was demonstrated in a dose range of 20 mg to 100 mg twice daily in short-term, placebo-controlled clinical trials. There were trends toward dose response within the range of 20 mg to 80 mg twice daily, but results were not consistent.
An increase to a dose greater than 80 mg twice daily is not generally recommended. The safety of doses above 100 mg twice daily has not been systematically evaluated in clinical trials [see Clinical Studies (14.1) ] . Maintenance Treatment While there is no body of evidence available to answer the question of how long a patient treated with ziprasidone should remain on it, a maintenance study in patients who had been symptomatically stable and then randomized to continue ziprasidone or switch to placebo demonstrated a delay in time to relapse for patients receiving ziprasidone capsules [see Clinical Studies (14.1) ] .
No additional benefit was demonstrated for doses above 20 mg twice daily. Patients should be periodically reassessed to determine the need for maintenance treatment.
2.3Bipolar I Disorder (Acute Mixed or Manic Episodes and Maintenance Treatment as an Adjunct to Lithium or Valproate) Acute Treatment of Manic or Mixed Episodes In adults oral ziprasidone should be administered at an initial daily dose of 40 mg twice daily with food. The dose may then be increased to 60 mg or 80 mg twice daily on the second day of treatment and subsequently adjusted on the basis of tolerance and efficacy within the range 40 mg to 80 mg twice daily. In the flexible-dose clinical trials, the mean daily dose administered was approximately 120 mg [see Clinical Studies (14.2) ] .
Maintenance Treatment (as an adjunct to lithium or valproate) Continue treatment at the same dose on which the patient was initially stabilized, within the range of 40 mg to 80 mg twice daily with food. Patients should be periodically reassessed to determine the need for maintenance treatment [see Clinical Studies (14.2)] .
2.5Switching Patients to or from a Monoamine Oxidase Inhibitor (MAOI) Antidepressant At least 14 days must elapse between discontinuation of an MAOI (intended to treat psychiatric disorders) and initiation of therapy with ziprasidone. In addition, at least 3 days should be allowed after stopping ziprasidone before starting an MAOI intended to treat psychiatric disorders [see Contrai…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Ziprasidone Capsules USP, 20 mg are blue opaque cap/off-white opaque body, size “5” hard gelatin capsule shells, filled with creamy to pale pinkish granular powder, imprinted with “F” on cap and “26” on body with black ink. Ziprasidone Capsules USP, 40 mg are blue opaque cap/blue opaque body, size “3” hard gelatin capsule shells, filled with creamy to pale pinkish granular powder, imprinted with “F” on cap and “38” on body with black ink. Ziprasidone Capsules USP, 60 mg are off-white opaque cap/off-white opaque body, size “2” hard gelatin capsule shells, filled with creamy to pale pinkish granular powder, imprinted with “F” on cap and “39” on body with black ink.
Ziprasidone Capsules USP, 80 mg are blue opaque cap/off-white opaque body, size “1” hard gelatin capsule shells, filled with creamy to pale pinkish granular powder, imprinted with “X” on cap and “66” on body with black ink. Capsules: 20 mg, 40 mg, 60 mg, and 80 mg (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Do not use in patients with a known history of QT prolongation ( 4.1 ) Do not use in patients with recent acute myocardial infarction ( 4.1 ) Do not use in patients with uncompensated heart failure ( 4.1 ) Do not use in combination with other drugs that have demonstrated QT prolongation ( 4.1 ) Do not use in patients with known hypersensitivity to ziprasidone ( 4.2 ) Concomitant use of monoamine oxidase inhibitors (MAOIs), or use within 14 days of stopping MAOIs. ( 4.3 )
4.1QT Prolongation Because of ziprasidone’s dose-related prolongation of the QT interval and the known association of fatal arrhythmias with QT prolongation by some other drugs, ziprasidone is contraindicated: in patients with a known history of QT prolongation (including congenital long QT syndrome) in patients with recent acute myocardial infarction in patients with uncompensated heart failure Pharmacokinetic/pharmacodynamic studies between ziprasidone and other drugs that prolong the QT interval have not been performed.
An additive effect of ziprasidone and other drugs that prolong the QT interval cannot be excluded. Therefore, ziprasidone should not be given with: dofetilide, sotalol, quinidine, other Class Ia and III anti-arrhythmics, mesoridazine, thioridazine, chlorpromazine, droperidol, pimozide, sparfloxacin, gatifloxacin, moxifloxacin, halofantrine, mefloquine, pentamidine, arsenic trioxide, levomethadyl acetate, dolasetron mesylate, probucol or tacrolimus. other drugs that have demonstrated QT prolongation as one of their pharmacodynamic effects and have this effect described in the full prescribing information as a contraindication or a boxed or bolded warning [see Warnings and Precautions (5.3) ] .
4.2Hypersensitivity Ziprasidone is contraindicated in individuals with a known hypersensitivity to the product.
4.3Monoamine Oxidase Inhibitors (MAOIs) Ziprasidone is contraindicated in patients taking, or within 14 days of stopping, MAOIs (including the MAOIs linezolid and intravenous methylene blue) because of an increased risk of serotonin syndrome [see Warnings and Precautions (5.4) , Drug Interaction (7.3) ].
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Cerebrovascular Adverse Reactions in Elderly Patients with Dementia-Related Psychosis: Increased incidence of cerebrovascular adverse reactions (e.g., stroke, transient ischemic attack). ( 5.2 ) QT Interval Prolongation : Ziprasidone hydrochloride use should be avoided in patients with bradycardia, hypokalemia or hypomagnesemia, congenital prolongation of the QT interval, or in combination with other drugs that have demonstrated QT prolongation. ( 5.3 ) Serotonin Syndrome : Increased risk when co-administered with other serotonergic agents, but also when taken alone.
If it occurs, discontinue ziprasidone and serotonergic agents and initiate supportive treatment. ( 5.4 ) Neuroleptic Malignant Syndrome (NMS): Potentially fatal symptom complex has been reported with antipsychotic drugs. Manage with immediate discontinuation of drug and close monitoring.
( 5.5 ) Severe Cutaneous Adverse Reactions , such as Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS) and Stevens-Johnson syndrome has been reported with ziprasidone exposure. DRESS and other Severe Cutaneous Adverse Reactions (SCAR) are sometimes fatal. Discontinue ziprasidone hydrochloride if DRESS or SCAR are suspected.
( 5.6 ) Tardive Dyskinesia : May develop acutely or chronically. ( 5.7 ) Metabolic Changes : Atypical antipsychotic drugs have been associated with metabolic changes that may increase cardiovascular/cerebrovascular risk. These metabolic changes include hyperglycemia, dyslipidemia, and weight gain.
( 5.8 ) Hyperglycemia and Diabetes Mellitus (DM): Monitor all patients for symptoms of hyperglycemia including polydipsia, polyuria, polyphagia, and weakness. Patients with DM risk factors should undergo blood glucose testing before and during treatment. ( 5.8 ) Dyslipidemia : Undesirable alterations have been observed in patients treated with atypical antipsychotics.
( 5.8 ) Weight Gain : Weight gain has been reported. Monitor weight gain. ( 5.8 ) Rash : Discontinue in patients who develop a rash without an identified cause.
( 5.9 ) Orthostatic Hypotension : Use with caution in patients with known cardiovascular or cerebrovascular disease. ( 5.10 ) Leukopenia, Neutropenia, and Agranulocytosis has been reported with antipsychotics. Patients with a pre-existing low white blood cell count (WBC) or a history of leukopenia/neutropenia should have their complete blood count (CBC) monitored frequently during the first few months of therapy and should discontinue ziprasidone hydrochloride at the first sign of a decline in WBC in the absence of other causative factors.
( 5.12 ) Seizures : Use cautiously in patients with a history of seizures or with conditions that lower seizure threshold. ( 5.13 ) Potential for Cognitive and Motor Impairment : Patients should use caution when operating machinery. ( 5.16 ) Suicide : Closely supervise high-risk patients.
( 5.19 )
5.1Increased Mortality in Elderly Patients with Dementia-Related Psychosis Elderly patients with dementia-related psychosis treated with antipsychotic drugs are at an increased risk of death. Analyses of 17 placebo-controlled trials (modal duration of 10 weeks), largely in patients taking atypical antipsychotic drugs, revealed a risk of death in drug-treated patients of between 1.6 to 1.7 times the risk of death in placebo-treated patients. Over the course of a typical 10-week controlled trial, the rate of death in drug-treated patients was about 4.5%, compared to a rate of about 2.6% in the placebo group.
Although the causes of death were varied, most of the deaths appeared to be either cardiovascular (e.g., heart failure, sudden death) or infectious (e.g., pneumonia) in nature. Ziprasidone hydrochloride is not approved for the treatment of patients with dementia-related psychosis. [see Boxed Warning , Warnings and Precautions (5.2)] .
5.2Cerebrovascular Adverse Reactions, Including Stroke, in Elderly Patients with Dementia-Related Psychosis In placebo-controlled trials in eld…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are described in more detail in other sections of the prescribing information: Increased Mortality in Elderly Patients with Dementia-Related Psychosis [see Boxed Warning and Warnings and Precautions (5.1) ] Cerebrovascular Adverse Reactions, Including Stroke, in Elderly Patients with Dementia-Related Psychosis [see Warnings and Precautions (5.2) ] QT Prolongation and Risk of Sudden Death [see Contraindications (4.2) , Warnings and Precautions (5.3) ] Serotonin Syndrome [see Contraindications (4.3) , Warnings and Precautions (5.4) , Drug Interactions (7.1) ] Neuroleptic Malignant Syndrome (NMS) [see Warnings and Precautions (5.5) ] Severe Cutaneous Adverse Reactions [see Warnings and Precautions (5.6) ] Tardive Dyskinesia [see Warnings and Precautions (5.7) ] Metabolic Changes [see Warnings and Precautions (5.8) ] Rash [see Warnings and Precautions (5.9) ] Orthostatic Hypotension [see Warnings and Precautions (5.10) ] Falls [see Warnings and Precautions (5.11) ] Leukopenia, Neutropenia, and Agranulocytosis [see Warnings and Precautions (5.12) ] Seizures [see Warnings and Precautions (5.13) ] Dysphagia [see Warnings and Precautions (5.14) ] Hyperprolactinemia [see Warnings and Precautions (5.15) ] Potential for Cognitive and Motor Impairment [see Warnings and Precautions (5.16) ] Priapism [see Warnings and Precautions (5.17) ] Body Temperature Regulation [see Warnings and Precautions (5.18) ] Suicide [see Warnings and Precautions (5.19) ] Commonly observed adverse reactions (incidence ≥5% and at least twice the incidence for placebo) were: Schizophrenia : Somnolence, respiratory tract infection.
( 6.1 ) Manic and Mixed Episodes Associated with Bipolar Disorder: Somnolence, extrapyramidal symptoms, dizziness, akathisia, abnormal vision, asthenia, vomiting. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Aurobindo Pharma USA, Inc. at 1-866-850-2876 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Clinical trials in adults for oral ziprasidone included approximately 5700 patients and/or normal subjects exposed to one or more doses of ziprasidone. Of these 5700, over 4800 were patients who participated in multiple-dose effectiveness trials, and their experience corresponded to approximately 1831 patient-years.
These patients include: (1) 4331 patients who participated in multiple-dose trials, predominantly in schizophrenia, representing approximately 1698 patient-years of exposure as of February 5, 2000; and (2) 472 patients who participated in bipolar mania trials representing approximately 133 patient-years of exposure. An additional 127 patients with bipolar disorder participated in a long-term maintenance treatment study representing approximately 74.7 patient-years of exposure to ziprasidone. The conditions and duration of treatment with ziprasidone included open-label and double-blind studies, inpatient and outpatient studies, and short-term and longer-term exposure.
Adverse reactions during exposure were obtained by collecting voluntarily reported adverse experiences, as well as results of physical examinations, vital signs, weights, laboratory analyses, ECGs, and results of ophthalmologic examinations. The stated frequencies of adverse reactions represent the proportion of individuals who experienced, at least once, a treatment-emergent adverse reaction of the type listed. A reaction was considered treatment-emergent if it occurred for the first time or worsened while receiving therapy following baseline evaluation.
Adverse Findings Observed in Short-Term, Placebo-Controlled Trials with Oral Ziprasidone The following findings are based on the short-term placebo-controlled prem…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Drug-drug interactions can be pharmacodynamic (combined pharmacologic effects) or pharmacokinetic (alteration of plasma levels). The risks of using ziprasidone in combination with other drugs have been evaluated as described below. All interactions studies have been conducted with oral ziprasidone.
Based upon the pharmacodynamic and pharmacokinetic profile of ziprasidone, possible interactions could be anticipated: Ziprasidone should not be used in combination with other drugs that have demonstrated QT prolongation. ( 4.1 , 7.3 ) The absorption of ziprasidone is increased up to two-fold in the presence of food. ( 7.10 ) The full prescribing information contains additional drug interactions.
( 7 )
7.1Metabolic Pathway Approximately two-thirds of ziprasidone is metabolized via a combination of chemical reduction by glutathione and enzymatic reduction by aldehyde oxidase. There are no known clinically relevant inhibitors or inducers of aldehyde oxidase. Less than one-third of ziprasidone metabolic clearance is mediated by cytochrome P450 catalyzed oxidation.
7.2In Vitro Studies An in vitro enzyme inhibition study utilizing human liver microsomes showed that ziprasidone had little inhibitory effect on CYP1A2, CYP2C9, CYP2C19, CYP2D6 and CYP3A4, and thus would not likely interfere with the metabolism of drugs primarily metabolized by these enzymes. There is little potential for drug interactions with ziprasidone due to displacement [see Clinical Pharmacology (12.3) ] .
7.3Pharmacodynamic Interactions Ziprasidone should not be used with any drug that prolongs the QT interval [see Contraindications (4.1) ] . Given the primary CNS effects of ziprasidone, caution should be used when it is taken in combination with other centrally acting drugs. Because of its potential for inducing hypotension, ziprasidone may enhance the effects of certain antihypertensive agents.
Ziprasidone may antagonize the effects of levodopa and dopamine agonists. Risk of serotonin syndrome with concomitant therapy with other serotonergic drugs such as SNRIs, SSRIs, triptans, tricyclic antidepressants, opioids, lithium, tryptophan, buspirone, amphetamines, and St. John’s Wort [see Contraindications (4.3) , Warnings and Precautions (5.4) , Adverse Reactions (6.2) ].
7.4Pharmacokinetic Interactions Carbamazepine Carbamazepine is an inducer of CYP3A4; administration of 200 mg twice daily for 21 days resulted in a decrease of approximately 35% in the AUC of ziprasidone. This effect may be greater when higher doses of carbamazepine are administered. Ketoconazole Ketoconazole, a potent inhibitor of CYP3A4, at a dose of 400 mg QD for 5 days, increased the AUC and C max of ziprasidone by about 35 to 40%.
Other inhibitors of CYP3A4 would be expected to have similar effects. Cimetidine Cimetidine at a dose of 800 mg QD for 2 days did not affect ziprasidone pharmacokinetics. Antacid The co-administration of 30 mL of Maalox ® with ziprasidone did not affect the pharmacokinetics of ziprasidone.
7.5Lithium Ziprasidone at a dose of 40 mg twice daily administered concomitantly with lithium at a dose of 450 mg twice daily for 7 days did not affect the steady-state level or renal clearance of lithium. Ziprasidone dosed adjunctively to lithium in a maintenance trial of bipolar patients did not affect mean therapeutic lithium levels.
7.6Oral Contraceptives In vivo studies have revealed no effect of ziprasidone on the pharmacokinetics of estrogen or progesterone components. Ziprasidone at a dose of 20 mg twice daily did not affect the pharmacokinetics of concomitantly administered oral contraceptives, ethinyl estradiol (0.03 mg) and levonorgestrel (0.15 mg).
7.7Dextromethorphan Consistent with in vitro results, a study in normal healthy volunteers showed that ziprasidone did not alter the metabolism of dextromethorphan, a CYP2D6 model substrate, to its major metabolite, dextrorphan. There was no statistically significant change in the urinary dextromethorph…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy : May cause extrapyramidal and/or withdrawal symptoms in neonates with third trimester exposure. ( 8.1 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to atypical antipsychotics, including ziprasidone, during pregnancy. Healthcare providers are encouraged to register patients by contacting the National Pregnancy Registry for Atypical Antipsychotics at 1-866-961-2388 or online at http://womensmentalhealth.org/clinical-and-research-programs/pregnancyregistry/. Risk Summary Neonates exposed to antipsychotic drugs, including ziprasidone, during the third trimester are at risk for extrapyramidal and/or withdrawal symptoms following delivery (see Clinical Considerations) .
Overall available data from published epidemiologic studies of pregnant women exposed to ziprasidone have not established a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes (see Data). There are risks to the mother associated with untreated schizophrenia or bipolar I disorder and with exposure to antipsychotics, including ziprasidone, during pregnancy (see Clinical Considerations) . In animal studies, ziprasidone administration to pregnant rats and rabbits during organogenesis caused developmental toxicity at doses similar to recommended human doses, and was teratogenic in rabbits at 3 times the maximum recommended human dose (MRHD).
Rats exposed to ziprasidone during gestation and lactation exhibited increased perinatal pup mortality and delayed neurobehavioral and functional development of offspring at doses less than or similar to human therapeutic doses. (see Data) . The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Disease-associated Maternal and/or Embryo/Fetal Risk There is risk to the mother from untreated schizophrenia or bipolar I disorder, including increased risk of relapse, hospitalization, and suicide.
Schizophrenia and bipolar I disorder are associated with increased adverse perinatal outcomes, including preterm birth. It is not known if this is a direct result of the illness or other comorbid factors. Fetal/Neonatal Adverse Reactions Extrapyramidal and/or withdrawal symptoms, including agitation, hypertonia, hypotonia, tremor, somnolence, respiratory distress, and feeding disorder have been reported in neonates who were exposed to antipsychotic drugs, including ziprasidone, during the third trimester of pregnancy.
These symptoms have varied in severity. Monitor neonates for extrapyramidal and/or withdrawal symptoms and manage symptoms appropriately. Some neonates recovered within hours or days without specific treatment; others required prolonged hospitalization.
Data Human Data Published data from observational studies, birth registries, and case reports on the use of atypical antipsychotics during pregnancy do not report a clear association with antipsychotics and major birth defects. A retrospective cohort study from a Medicaid database of 9258 women exposed to antipsychotics during pregnancy did not indicate an overall increased risk for major birth defects. Animal Data When ziprasidone was administered to pregnant rabbits during the period of organogenesis, an increased incidence of fetal structural abnormalities (ventricular septal defects and other cardiovascular malformations, and kidney alterations) was observed at a dose of 30 mg/kg/day (3 times the MRHD of 200 mg/day based on mg/m 2 body surface area).
There was no evidence to suggest that these developmental effects were secondary to maternal toxicity. The developmental no…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to atypical antipsychotics, including ziprasidone, during pregnancy. Healthcare providers are encouraged to register patients by contacting the National Pregnancy Registry for Atypical Antipsychotics at 1-866-961-2388 or online at http://womensmentalhealth.org/clinical-and-research-programs/pregnancyregistry/. Risk Summary Neonates exposed to antipsychotic drugs, including ziprasidone, during the third trimester are at risk for extrapyramidal and/or withdrawal symptoms following delivery (see Clinical Considerations) .
Overall available data from published epidemiologic studies of pregnant women exposed to ziprasidone have not established a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes (see Data). There are risks to the mother associated with untreated schizophrenia or bipolar I disorder and with exposure to antipsychotics, including ziprasidone, during pregnancy (see Clinical Considerations) . In animal studies, ziprasidone administration to pregnant rats and rabbits during organogenesis caused developmental toxicity at doses similar to recommended human doses, and was teratogenic in rabbits at 3 times the maximum recommended human dose (MRHD).
Rats exposed to ziprasidone during gestation and lactation exhibited increased perinatal pup mortality and delayed neurobehavioral and functional development of offspring at doses less than or similar to human therapeutic doses. (see Data) . The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Disease-associated Maternal and/or Embryo/Fetal Risk There is risk to the mother from untreated schizophrenia or bipolar I disorder, including increased risk of relapse, hospitalization, and suicide.
Schizophrenia and bipolar I disorder are associated with increased adverse perinatal outcomes, including preterm birth. It is not known if this is a direct result of the illness or other comorbid factors. Fetal/Neonatal Adverse Reactions Extrapyramidal and/or withdrawal symptoms, including agitation, hypertonia, hypotonia, tremor, somnolence, respiratory distress, and feeding disorder have been reported in neonates who were exposed to antipsychotic drugs, including ziprasidone, during the third trimester of pregnancy.
These symptoms have varied in severity. Monitor neonates for extrapyramidal and/or withdrawal symptoms and manage symptoms appropriately. Some neonates recovered within hours or days without specific treatment; others required prolonged hospitalization.
Data Human Data Published data from observational studies, birth registries, and case reports on the use of atypical antipsychotics during pregnancy do not report a clear association with antipsychotics and major birth defects. A retrospective cohort study from a Medicaid database of 9258 women exposed to antipsychotics during pregnancy did not indicate an overall increased risk for major birth defects. Animal Data When ziprasidone was administered to pregnant rabbits during the period of organogenesis, an increased incidence of fetal structural abnormalities (ventricular septal defects and other cardiovascular malformations, and kidney alterations) was observed at a dose of 30 mg/kg/day (3 times the MRHD of 200 mg/day based on mg/m 2 body surface area).
There was no evidence to suggest that these developmental effects were secondary to maternal toxicity. The developmental no effect dose was 10 mg/kg/day (equivalent to the MRHD based on a mg/m 2 body surface area). In rats, embryofetal toxicity (decreased fetal weight…
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of ziprasidone have not been established in pediatric patients. Ziprasidone was studied in one 4-week, placebo-controlled trial in patients 10 to 17 years of age with bipolar I disorder. However, the data were insufficient to fully assess the safety of ziprasidone in pediatric patients. Therefore, a safe and effective dose for use could not be established.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the total number of subjects in clinical studies of ziprasidone, 2.4 percent were 65 and over. No overall differences in safety or effectiveness were observed between these subjects and younger subjects, and other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out. Nevertheless, the presence of multiple factors that might increase the pharmacodynamic response to ziprasidone, or cause poorer tolerance or orthostasis, should lead to consideration of a lower starting dose, slower titration, and careful monitoring during the initial dosing period for some elderly patients.
🆘 Overdosage ▾
10 OVERDOSAGE
10.1Human Experience In premarketing trials involving more than 5400 patients and/or normal subjects, accidental or intentional overdosage of oral ziprasidone was documented in 10 patients. All of these patients survived without sequelae. In the patient taking the largest confirmed amount, 3,240 mg, the only symptoms reported were minimal sedation, slurring of speech, and transitory hypertension (200/95).
Adverse reactions reported with ziprasidone overdose included extrapyramidal symptoms, somnolence, tremor, and anxiety. [see Adverse Reactions (6.2)]
10.2Management of Overdosage In case of acute overdosage, establish and maintain an airway and ensure adequate oxygenation and ventilation. Intravenous access should be established, and gastric lavage (after intubation, if patient is unconscious) and administration of activated charcoal together with a laxative should be considered. The possibility of obtundation, seizure, or dystonic reaction of the head and neck following overdose may create a risk of aspiration with induced emesis.
Cardiovascular monitoring should commence immediately and should include continuous electrocardiographic monitoring to detect possible arrhythmias. If antiarrhythmic therapy is administered, disopyramide, procainamide, and quinidine carry a theoretical hazard of additive QT-prolonging effects that might be additive to those of ziprasidone. Hypotension and circulatory collapse should be treated with appropriate measures such as intravenous fluids.
If sympathomimetic agents are used for vascular support, epinephrine and dopamine should not be used, since beta stimulation combined with α 1 antagonism associated with ziprasidone may worsen hypotension. Similarly, it is reasonable to expect that the alpha-adrenergic-blocking properties of bretylium might be additive to those of ziprasidone, resulting in problematic hypotension. In cases of severe extrapyramidal symptoms, anticholinergic medication should be administered.
There is no specific antidote to ziprasidone, and it is not dialyzable. The possibility of multiple drug involvement should be considered. Close medical supervision and monitoring should continue until the patient recovers.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The mechanism of action of ziprasidone in the treatment of the listed indications could be mediated through a combination of dopamine type 2 (D 2 ) and serotonin type 2 (5HT 2 ) antagonism.
12.2Pharmacodynamics Ziprasidone binds with relatively high affinity to the dopamine D 2 and D 3 , serotonin 5HT 2A , 5HT 2C , 5HT 1A , 5HT 1D , and α 1 -adrenergic receptors (K i s of 4.8, 7.2, 0.4, 1.3, 3.4, 2, and 10 nM, respectively), and with moderate affinity to the histamine H 1 receptor (K i =47 nM). Ziprasidone is an antagonist at the D 2 , 5HT 2A , and 5HT 1D receptors, and an agonist at the 5HT 1A receptor. Ziprasidone inhibited synaptic reuptake of serotonin and norepinephrine.
No appreciable affinity was exhibited for other receptor/binding sites tested, including the cholinergic muscarinic receptor (IC 50 >1 μM).
12.3Pharmacokinetics Oral Pharmacokinetics Ziprasidone’s activity is primarily due to the parent drug. The multiple-dose pharmacokinetics of ziprasidone are dose-proportional within the proposed clinical dose range, and ziprasidone accumulation is predictable with multiple dosing. Elimination of ziprasidone is mainly via hepatic metabolism with a mean terminal half-life of about 7 hours within the proposed clinical dose range.
Steady-state concentrations are achieved within one to three days of dosing. The mean apparent systemic clearance is 7.5 mL/min/kg. Ziprasidone is unlikely to interfere with the metabolism of drugs metabolized by cytochrome P450 enzymes.
Absorption: Ziprasidone is well absorbed after oral administration, reaching peak plasma concentrations in 6 to 8 hours. The absolute bioavailability of a 20 mg dose under fed conditions is approximately 60%. The absorption of ziprasidone is increased up to two-fold in the presence of food.
Distribution: Ziprasidone has a mean apparent volume of distribution of
1.5L/kg. It is greater than 99% bound to plasma proteins, binding primarily to albumin and α 1 -acid glycoprotein. The in vitro plasma protein binding of ziprasidone was not altered by warfarin or propranolol, two highly protein-bound drugs, nor did ziprasidone alter the binding of these drugs in human plasma.
Thus, the potential for drug interactions with ziprasidone due to displacement is minimal. Metabolism and Elimination : Ziprasidone is extensively metabolized after oral administration with only a small amount excreted in the urine (<1%) or feces (<4%) as unchanged drug. Ziprasidone is primarily cleared via three metabolic routes to yield four major circulating metabolites, benzisothiazole (BITP) sulphoxide, BITP-sulphone, ziprasidone sulphoxide, and S-methyldihydroziprasidone.
Approximately 20% of the dose is excreted in the urine, with approximately 66% being eliminated in the feces. Unchanged ziprasidone represents about 44% of total drug-related material in serum. In vitro studies using human liver subcellular fractions indicate that S-methyldihydroziprasidone is generated in two steps.
These studies indicate that the reduction reaction is mediated primarily by chemical reduction by glutathione as well as by enzymatic reduction by aldehyde oxidase and the subsequent methylation is mediated by thiol methyltransferase. In vitro studies using human liver microsomes and recombinant enzymes indicate that CYP3A4 is the major CYP contributing to the oxidative metabolism of ziprasidone. CYP1A2 may contribute to a much lesser extent.
Based on in vivo abundance of excretory metabolites, less than one-third of ziprasidone metabolic clearance is mediated by cytochrome P450 catalyzed oxidation and approximately two-thirds via reduction. There are no known clinically relevant inhibitors or inducers of aldehyde oxidase.
🧬 Mechanism of Action ▾
12.1Mechanism of Action The mechanism of action of ziprasidone in the treatment of the listed indications could be mediated through a combination of dopamine type 2 (D 2 ) and serotonin type 2 (5HT 2 ) antagonism.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Ziprasidone Capsules USP, 20 mg are blue opaque cap/off-white opaque body, size “5” hard gelatin capsule shells, filled with creamy to pale pinkish granular powder, imprinted with “F” on cap and “26” on body with black ink. Bottles of 60 NDC 65862-702-60 Bottles of 1,000 NDC 65862-702-99 8 x 10 Unit-dose Capsules NDC 65862-702-80 Ziprasidone Capsules USP, 40 mg are blue opaque cap/blue opaque body, size “3” hard gelatin capsule shells, filled with creamy to pale pinkish granular powder, imprinted with “F” on cap and “38” on body with black ink.
Bottles of 60 NDC 65862-703-60 Bottles of 1,000 NDC 65862-703-99 8 x 10 Unit-dose Capsules NDC 65862-703-80 Ziprasidone Capsules USP, 60 mg are off-white opaque cap/off-white opaque body, size “2” hard gelatin capsule shells, filled with creamy to pale pinkish granular powder, imprinted with “F” on cap and “39” on body with black ink. Bottles of 60 NDC 65862-704-60 Bottles of 1,000 NDC 65862-704-99 8 x 10 Unit-dose Capsules NDC 65862-704-80 Ziprasidone Capsules USP, 80 mg are blue opaque cap/off-white opaque body, size “1” hard gelatin capsule shells, filled with creamy to pale pinkish granular powder, imprinted with “X” on cap and “66” on body with black ink.
Bottles of 60 NDC 65862-705-60 Bottles of 1,000 NDC 65862-705-99 8 x 10 Unit-dose Capsules NDC 65862-705-80 Store at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [See USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Ziprasidone capsules contain the active moiety, ziprasidone, in the form of ziprasidone hydrochloride salt. Ziprasidone is a psychotropic agent that is chemically unrelated to phenothiazine or butyrophenone antipsychotic agents. It has a molecular weight of 412.94 (free base), with the following chemical name: 5-[2-[4-(1,2-benzisothiazol-3-yl)-1-piperazinyl]ethyl]-6-chloro-1,3-dihydro-2 H -indol-2-one.
The molecular formula of C 21 H 21 ClN 4 OS (free base of ziprasidone) represents the following structural formula: Ziprasidone capsules USP contain a monohydrochloride, monohydrate salt of ziprasidone. Chemically, ziprasidone hydrochloride monohydrate is 5-[2-[4-(1,2-benzisothiazol-3-yl)-1-piperazinyl]ethyl]-6-chloro-1,3-dihydro-2 H -indol-2-one, monohydrochloride, monohydrate. The molecular formula is C 21 H 21 ClN 4 OS·HCl·H 2 O and its molecular weight is 467.42.
Ziprasidone hydrochloride USP is a white to slightly pink powder. Ziprasidone capsules USP are supplied for oral administration in 20 mg (blue/off-white), 40 mg (blue/blue), 60 mg (off-white/off-white), and 80 mg (blue/off-white) capsules. Ziprasidone capsules USP contain ziprasidone hydrochloride USP, ethyl cellulose, lactose monohydrate, magnesium stearate, and pregelatinized starch (maize).
The empty hard gelatin capsule shells also contain gelatin, sodium lauryl sulfate, and titanium dioxide. In addition the 20 mg, 40 mg and 80 mg capsule shells contain FD & C Blue 2. The capsules are imprinted with edible ink containing black iron oxide, potassium hydroxide, shellac and strong ammonia solution.
Meets USP Dissolution Test 2. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Patient Information ). Administration Information for Capsules Advise patients to take ziprasidone capsules whole. Do not open, crush, or chew the capsules.
Instruct patients to take ziprasidone capsules with food for optimal absorption. The absorption of ziprasidone is increased up to two-fold in the presence of food [see Dosage and Administration (2.1) , Drug Interactions (7.10) , and Clinical Pharmacology (12.3) ] . QTc Prolongation Advise patients to inform their health care providers of the following: History of QT prolongation; recent acute myocardial infarction; uncompensated heart failure; prescription of other drugs that have demonstrated QT prolongation; risk for significant electrolyte abnormalities; and history of cardiac arrhythmia [see Contraindications (4.1) and Warnings and Precautions (5.3) ] .
Instruct patients to report the onset of any conditions that put them at risk for significant electrolyte disturbances, hypokalemia in particular, including but not limited to the initiation of diuretic therapy or prolonged diarrhea. In addition, instruct patients to report symptoms such as dizziness, palpitations, or syncope to the prescriber [see Warnings and Precautions (5.3) ] . Serotonin Syndrome Caution patients about the risk of serotonin syndrome, particularly with the concomitant use of ziprasidone with other serotonergic drugs including SSRIs, SNRIs, triptans, tricyclic antidepressants, opioids, lithium, tryptophan, buspirone, amphetamines, St.
John’s Wort, and with drugs that impair the metabolism of serotonin (in particular, MAOIs, which include those intended to treat psychiatric disorders and also others, such as linezolid). Instruct patients to contact their health care provider, or report to the emergency room, should they experience signs or symptoms of serotonin syndrome [see Contraindication (4.3) , Warnings and Precautions (5.4) , Drug Interactions (7.3) ]. Severe Cutaneous Adverse Reactions Instruct patients to report to their health care provider at the earliest onset any signs or symptoms that may be associated with Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS) or with severe cutaneous adverse reactions, such as Stevens-Johnson syndrome [see Warnings and Precautions (5.6) ] .
Pregnancy Advise pregnant women to notify their healthcare provider if they become pregnant or intend to become pregnant during treatment with ziprasidone. Advise patients that ziprasidone may cause extrapyramidal and/or withdrawal symptoms (agitation, hypertonia, hypotonia, tremor, somnolence, respiratory distress, and feeding disorder) in a neonate. Advise patients that there is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to ziprasidone during pregnancy [see Use in Specific Populations (8.1) ].
Lactation Advise breastfeeding women using ziprasidone to monitor infants for excess sedation, irritability, poor feeding, and extrapyramidal symptoms (tremors, and abnormal muscle movements) and to seek medical care if they notice these signs [see Use in Specific Populations (8.2) ]. Infertility Advise females of reproductive potential that ziprasidone may impair fertility due to an increase in serum prolactin levels. The effects on fertility are reversible [see Warnings and Precautions (5.15) and Use in Specific Populations (8.3) ].
The brands listed are trademarks of their respective owners. Distributed by: Aurobindo Pharma USA, Inc. 279 Princeton-Hightstown Road East Windsor, NJ 08520 Manufactured by: Aurobindo Pharma Limited Hyderabad-500 032, India Revised: 04/2025