
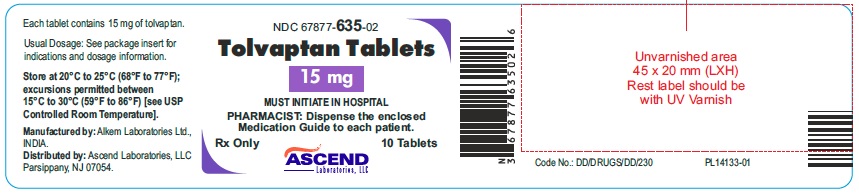
Tolvaptan 60 mg Tablet, 10-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Vasopressin V2 Receptor Antagonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Tolvaptan (Jynarque) is used to slow the worsening of kidney function in certain patients with autosomal dominant polycystic kidney disease (ADPKD; a certain type of inherited kidney disease). Tolvaptan (Jynarque) is in a class of medications called vasopressin V2 receptor antagonists. It works by increasing the amount of water released from the body as urine and decreases the growth of cysts in the kidneys. Removing fluid from the body and slowing the growth of cysts helps to slow the worsening of kidney function. Tolvaptan is also available as a tablet (Samsca) to treat low blood levels of s...
Read the full MedlinePlus article ↗- This is a safety requirement — not just a formality. When tolvaptan raises your blood sodium levels, it has to happen gradually. If sodium goes up too fast, it can cause a rare but...
- Why do I have to start this medication in a hospital?
- Tolvaptan can cause liver damage — and with Jynarque, which is used long-term for kidney disease, that risk needs to be watched carefully. Liver blood tests check for signs of inju...
- Why do I need regular liver blood tests if I'm on Jynarque?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Tolvaptan — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII L06K8R7DQK
A synthetic blue dye approved by the FDA for use in medications and foods. It serves as a colorant to make pills and liquids visually distinct and easier to identify.
-
UNII R75537T0T4
Hypromellose 2910 is a plant-derived thickening agent made from cellulose. It serves as a binder that holds tablet ingredients together, a film-coating for pills, and a viscosity controller in liquids.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
7 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $238.26 | $2,382.57 / 10 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Tolvaptan 60 mgthis 67877-0637-33 | Ascend | 10 tablets | — | AB1 | FDA listed | — |
| Tolvaptan 60 mg 67877-0918-30 | Ascend | 30 tablets | — | AB2 | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 67877-0637-01 | 100 TABLET in 1 BOTTLE (67877-637-01) | 2020-05-21 | Active |
| 67877-0637-02 | 10 TABLET in 1 BOTTLE (67877-637-02) | 2020-05-21 | Active |
| 67877-0637-33 You're viewing this | 1 BLISTER PACK in 1 CARTON (67877-637-33) / 10 TABLET in 1 BLISTER PACK | 2020-05-21 | Active |
Pack size FAQ
What quantity is in NDC 67877-0637-33?
What is the difference between NDC 67877-0637-33 and NDC 67877-0637-02?
What NDC number is used to bill for this package of Tolvaptan 60 mg Tablet?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: (A) INITIATE AND RE-INITIATE IN A HOSPITAL AND MONITOR SERUM SODIUM (B) NOT FOR USE FOR AUTOSOMAL DOMINANT POLYCYSTIC KIDNEY DISEASE (ADPKD) (A) Initiate and re-initiate in a hospital and monitor serum sodium Tolvaptan tablets should be initiated and re-initiated in patients only in a hospital where serum sodium can be monitored closely. Too rapid correction of hyponatremia (e.g., >12 mEq/L/24 hours) can cause osmotic demyelination resulting in dysarthria, mutism, dysphagia, lethargy, affective changes, spastic quadriparesis, seizures, coma and death.
In susceptible patients, including those with severe malnutrition, alcoholism or advanced liver disease, slower rates of correction may be advisable. (B) Not for use for autosomal dominant polycystic kidney disease (ADPKD) Because of the risk of hepatotoxicity, tolvaptan should not be used for ADPKD outside of the FDA-approved REMS [ see Contraindications (4)]. WARNING: (A) INITIATE AND RE-INITIATE IN A HOSPITAL AND MONITOR SERUM SODIUM (B) NOT FOR USE FOR AUTOSOMAL DOMINANT POLYCYSTIC KIDNEY DISEASE (ADPKD) See full prescribing information for complete boxed warning.
(A) Initiate and re-initiate in a hospital and monitor serum sodium Tolvaptan tablets should be initiated and re-initiated in patients only in a hospital where serum sodium can be monitored closely. Too rapid correction of hyponatremia (e.g., >12 mEq/L/24 hours) can cause osmotic demyelination resulting in dysarthria, mutism, dysphagia, lethargy, affective changes, spastic quadriparesis, seizures, coma and death. In susceptible patients, including those with severe malnutrition, alcoholism or advanced liver disease, slower rates of correction may be advisable.
(B) Not for use for autosomal dominant polycystic kidney disease (ADPKD) Because of the risk of hepatotoxicity, tolvaptan should not be used for ADPKD outside of the FDA-approved REMS (4)
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Tolvaptan tablets are indicated for the treatment of clinically significant hypervolemic and euvolemic hyponatremia (serum sodium <125 mEq/L or less marked hyponatremia that is symptomatic and has resisted correction with fluid restriction), including patients with heart failure and Syndrome of Inappropriate Antidiuretic Hormone (SIADH). Limitations of Use Patients requiring intervention to raise serum sodium urgently to prevent or to treat serious neurological symptoms should not be treated with tolvaptan tablets.
It has not been established that raising serum sodium with tolvaptan tablets provides a symptomatic benefit to patients. Tolvaptan tablets is a selective vasopressin V2-receptor antagonist indicated for the treatment of clinically significant hypervolemic and euvolemic hyponatremia [serum sodium <125 mEq/L or less marked hyponatremia that is symptomatic and has resisted correction with fluid restriction], including patients with heart failure and Syndrome of Inappropriate Antidiuretic Hormone (SIADH) ( 1 ) Limitations of Use: Patients requiring intervention to raise serum sodium urgently to prevent or to treat serious neurological symptoms should not be treated with tolvaptan tablets ( 1 ) It has not been established that tolvaptan tablets provides a symptomatic benefit to patients ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Tolvaptan tablets should be initiated and re-initiated in a hospital ( 2.1 ) The recommended starting dose is 15 mg once daily. Dosage may be increased at intervals ≥24 hr to 30 mg once daily, and to a maximum of 60 mg once daily as needed to raise serum sodium. ( 2.1 )
2.1Recommended Dosage Patients should be in a hospital for initiation and re-initiation of therapy to evaluate the therapeutic response and because too rapid correction of hyponatremia can cause osmotic demyelination resulting in dysarthria, mutism, dysphagia, lethargy, affective changes, spastic quadriparesis, seizures, coma and death. The usual starting dose for tolvaptan tablets is 15 mg administered once daily without regard to meals. Increase the dose to 30 mg once daily, after at least 24 hours, to a maximum of 60 mg once daily, as needed to achieve the desired level of serum sodium.
Do not administer tolvaptan tablets for more than 30 days to minimize the risk of liver injury [see Warnings and Precautions (5.2)]. During initiation and titration, frequently monitor for changes in serum electrolytes and volume. Avoid fluid restriction during the first 24 hours of therapy.
Patients receiving tolvaptan tablets should be advised that they can continue ingestion of fluid in response to thirst [see Warnings and Precautions (5.1)].
2.2Drug Withdrawal Following discontinuation from tolvaptan tablets, patients should be advised to resume fluid restriction and should be monitored for changes in serum sodium and volume status.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tolvaptan tablets are available in the following dosage forms and strengths: • 15 mg tablets are non-scored light blue to blue coloured, round shaped, uncoated tablets, debossed with "TOL" on one side and “15" on other side, may have mottled appearance. • 30mg tabletsarenon-scored, light blue to blue coloured, round shaped, uncoated tablets, debossed with "TOL" on one side and “30" on other side, may have mottled appearance. • 60 mg tabletsarenon-scored, light blue to blue coloured, round shaped, uncoated tablets, debossed with "TOL" on one side and “60" on other side, may have mottled appearance.
Tablets: 15 mg, 30 mg and 60 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Tolvaptan is contraindicated in the following conditions: Patients with autosomal dominant polycystic kidney disease (ADPKD) outside of FDA-approved REMS [see Warnings and Precautions (5.2)] Unable to sense or respond to thirst Hypovolemic hyponatremia Taking strong CYP3A inhibitors [see Warnings and Precautions (5.5)] Anuria Hypersensitivity (e.g., anaphylactic shock, rash generalized) to tolvaptan or any components of the product [see Adverse Reactions (6)] • Use in patients with autosomal dominant polycystic kidney disease (ADPKD) outside of FDA-approved REMS (4) • Patients who are unable to respond appropriately to thirst ( 4 ) • Hypovolemic hyponatremia ( 4 ) • Concomitant use of strong CYP 3A inhibitors ( 4 ) • Anuria ( 4 ) • Hypersensitivity ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Liver injury: Limit treatment duration to 30 days. If hepatic injury is suspected, discontinue tolvaptan. Avoid use in patients with underlying liver disease (5.2) Dehydration and hypovolemia may require intervention ( 5.3 ) Avoid use with hypertonic saline ( 5.4 ) Avoid use with moderate to strong CYP3A inhibitors (5.5) Monitor serum potassium in patients with potassium >5 mEq/L or on drugs known to increase potassium ( 5.6 ) Urinary outflow obstruction: Urinary output must be secured (5.7)
5.1Too Rapid Correction of Serum Sodium Can Cause Serious Neurologic Sequelae Osmotic demyelination syndrome is a risk associated with too rapid correction of hyponatremia (e.g., >12 mEq/L/24 hours). Osmotic demyelination results in dysarthria, mutism, dysphagia, lethargy, affective changes, spastic quadriparesis, seizures, coma or death. In susceptible patients, including those with severe malnutrition, alcoholism or advanced liver disease, slower rates of correction may be advisable.
In controlled clinical trials in which tolvaptan was administered in titrated doses starting at 15 mg once daily, 7% of tolvaptan-treated subjects with a serum sodium <130 mEq/L had an increase in serum sodium greater than 8 mEq/L at approximately 8 hours and 2% had an increase greater than 12 mEq/L at 24 hours. Approximately 1% of placebo-treated subjects with a serum sodium <130 mEq/L had a rise greater than 8 mEq/L at 8 hours and no patient had a rise greater than 12 mEq/L/24 hours. Osmotic demyelination syndrome has been reported in association with tolvaptan therapy [see Adverse Reactions (6.2)] .
Patients treated with tolvaptan should be monitored to assess serum sodium concentrations and neurologic status, especially during initiation and after titration. Subjects with SIADH or very low baseline serum sodium concentrations may be at greater risk for too-rapid correction of serum sodium. In patients receiving tolvaptan who develop too rapid a rise in serum sodium, discontinue or interrupt treatment with tolvaptan and consider administration of hypotonic fluid.
Fluid restriction during the first 24 hours of therapy with tolvaptan may increase the likelihood of overly rapid correction of serum sodium and should generally be avoided. Co-administration of diuretics also increases the risk of too rapid correction of serum sodium and such patients should undergo close monitoring of serum sodium.
5.3Dehydration and Hypovolemia Tolvaptan therapy induces copious aquaresis, which is normally partially offset by fluid intake. Dehydration and hypovolemia can occur, especially in potentially volume-depleted patients receiving diuretics or those who are fluid restricted. In multiple-dose, placebo-controlled trials in which 607 hyponatremic patients were treated with tolvaptan, the incidence of dehydration was 3.3% for tolvaptan and 1.5% for placebo-treated patients.
In patients receiving tolvaptan who develop medically significant signs or symptoms of hypovolemia, interrupt or discontinue tolvaptan therapy and provide supportive care with careful management of vital signs, fluid balance and electrolytes. Fluid restriction during therapy with tolvaptan may increase the risk of dehydration and hypovolemia. Patients receiving tolvaptan should continue ingestion of fluid in response to thirst
5.2Liver Injury Tolvaptan can cause serious and potentially fatal liver injury. In placebo-controlled studies and an open-label extension study of chronically administered tolvaptan in patients with ADPKD, cases of serious liver injury attributed to tolvaptan, generally occurring during the first 18 months of therapy, were observed. In postmarketing experience with tolvaptan in ADPKD, acute injury resulting in liver failure requiring liver transplantation has been reported.
Tolvaptan should not be used to treat ADPKD outside of the FDA-approved risk evaluation and mitigation strategy (REMS) for ADPKD patients [ see Contraindications (4)]. Patients with…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Most common adverse reactions (≥5% placebo) are thirst, dry mouth, asthenia, constipation, pollakiuria or polyuria, and hyperglycemia ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Ascend Laboratories, LLC at 1-877-ASC-RX01 (877-272-7901) or FDA at 1-800-FDA-1088 ( www.fda.gov/medwatch ).
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reactions rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The adverse event information from clinical trials does, however, provide a basis for identifying the adverse events that appear to be related to drug use and for approximating rates. In multiple-dose, placebo-controlled trials, 607 hyponatremic patients (serum sodium <135 mEq/L) were treated with tolvaptan.
The mean age of these patients was 62 years; 70% of patients were male and 82% were Caucasian. One hundred eighty-nine (189) tolvaptan-treated patients had a serum sodium <130 mEq/L, and 52 patients had a serum sodium <125 mEq/L. Hyponatremia was attributed to cirrhosis in 17% of patients, heart failure in 68% and SIADH/other in 16%.
Of these patients, 223 were treated with the recommended dose titration (15 mg titrated to 60 mg as needed to raise serum sodium). Overall, over 4,000 patients have been treated with oral doses of tolvaptan in open-label or placebo-controlled clinical trials. Approximately 650 of these patients had hyponatremia; approximately 219 of these hyponatremic patients were treated with tolvaptan for 6 months or more.
The most common adverse reactions (incidence ≥5% more than placebo) seen in two 30-day, double-blind, placebo-controlled hyponatremia trials in which tolvaptan was administered in titrated doses (15 mg to 60 mg once daily) were thirst, dry mouth, asthenia, constipation, pollakiuria or polyuria and hyperglycemia. In these trials, 10% (23/223) of tolvaptan-treated patients discontinued treatment because of an adverse event, compared to 12% (26/220) of placebo-treated patients; no adverse reaction resulting in discontinuation of trial medication occurred at an incidence of >1% in tolvaptan-treated patients.
1 lists the adverse reactions reported in tolvaptan-treated patients with hyponatremia (serum sodium <135 mEq/L) and at a rate at least 2% greater than placebo-treated patients in two 30-day, double-blind, placebo-controlled trials. In these studies, 223 patients were exposed to tolvaptan (starting dose 15 mg, titrated to 30 and 60 mg as needed to raise serum sodium). Adverse events resulting in death in these trials were 6% in tolvaptan-treated patients and 6% in placebo-treated patients.
Table 1. Adverse Reactions (>2% more than placebo) in Tolvaptan-Treated Patients in Double-Blind, Placebo-Controlled Hyponatremia Trials System Organ Class MedDRA Preferred Term Tolvaptan 15 mg/day to 60 mg/day (N = 223) n (%) Placebo (N = 220) n (%) Gastrointestinal Disorders Dry mouth 28 (13) 9 (4) Constipation 16 (7) 4 (2) General Disorders and Administration Site Conditions Thirst * 35 (16) 11 (5) Asthenia 19 (9) 9 (4) Pyrexia 9 (4) 2 (1) Metabolism and Nutrition Disorders Hyperglycemia † 14 (6) 2 (1) Anorexia ‡ 8 (4) 2 (1) Renal and Urinary Disorders Pollakiuria or polyuria § 25 (11) 7 (3) The following terms are subsumed under the referenced ADR in Table 1: * polydipsia, † diabetes mellitus, ‡ decreased appetite, § urine output increased, micturition urgency, nocturia In a subgroup of patients with hyponatremia (N = 475, serum sodium <135 mEq/L) enrolled in a double-blind, placebo-controlled trial (mean duration of treatment was 9 months) of patients with worsening heart failure, the following adverse reactions occurred in tolvaptan-treated patients at a rate at least 2% greater than placebo: mortality (42% tolvaptan, 38% placebo), nausea (21% tolvaptan, 16% placebo), thirst (12% tolvaptan, 2% p…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Avoid concomitant use with: • Moderate CYP3A inhibitors ( 7.1 ) • Strong CYP3A inducers ( 7.1 ) • V2-receptor antagonists ( 7.3 ) Monitor serum potassium during concomitant therapy with ( 7.2 ): • Angiotensin receptor blockers • Angiotensin converting enzyme inhibitors • Potassium sparing diuretics
7.1CYP3A Inhibitors and Inducers Strong CYP3A Inhibitors Tolvaptan's AUC was 5.4 times as large and C max was 3.5 times as large after co-administration of tolvaptan and 200 mg ketoconazole [see Warnings and Precautions (5.5) and Clinical Pharmacology (12.3) ] . Larger doses of the strong CYP3A inhibitor would be expected to produce larger increases in tolvaptan exposure. Concomitant use of tolvaptan with strong CYP3A inhibitors is contraindicated [see Contraindications (4) ] .
Moderate CYP3A Inhibitors A substantial increase in the exposure to tolvaptan would be expected when tolvaptan is co-administered with moderate CYP3A inhibitors. Avoid co-administration of tolvaptan with moderate CYP3A inhibitors [see Warnings and Precautions (5.5) ]. Patients should avoid grapefruit juice beverages while taking tolvaptan [see Clinical Pharmacology (12.3) ] .
Strong CYP3A Inducers Co-administration of tolvaptan with strong CYP3A inducers reduces exposure to tolvaptan [see Clinical Pharmacology (12.3) ] . Avoid concomitant use of tolvaptan with strong CYP3A inducers.
7.2Angiotensin Receptor Blockers, Angiotensin Converting Enzyme Inhibitors and Potassium Sparing Diuretics Although specific interaction studies were not performed, in clinical studies, tolvaptan was used concomitantly with beta-blockers, angiotensin receptor blockers, angiotensin converting enzyme inhibitors and potassium sparing diuretics. Adverse reactions of hyperkalemia were approximately 1 to 2% higher when tolvaptan was administered with angiotensin receptor blockers, angiotensin converting enzyme inhibitors and potassium sparing diuretics compared to administration of these medications with placebo.
Serum potassium levels should be monitored during concomitant drug therapy.
7.3V2-Receptor Agonist As a V 2 -receptor antagonist, tolvaptan may interfere with the V 2 -agonist activity of desmopressin (dDAVP). Avoid concomitant use of tolvaptan with a V 2 -agonist.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: May cause fetal harm ( 8.1 ) Lactation: Breastfeeding not recommended (8.2) Pediatric Use: There are no studies ( 8.4 )
8.1Pregnancy Risk Summary Available data with tolvaptan use in pregnant women are insufficient to determine if there is a drug-associated risk of adverse developmental outcomes. Tolvaptan did not cause any developmental toxicity in rats or in rabbits at exposures approximately 2.8 and 0.8 times, respectively, the exposure in congestive heart failure (CHF) patients at the maximum recommended human dose (MRHD) of 60 mg once daily. However, effects on embryo-fetal development occurred in both species at doses causing significant maternally toxic doses.
In rats, reduced fetal weights and delayed fetal ossification occurred at 11 times the exposure in CHF patients, based on AUC. In rabbits, increased abortions, embryo-fetal death, fetal microphthalmia, open eyelids, cleft palate, brachymelia and skeletal malformations occurred at approximately 1.6 times the exposure in CHF patients (see Data). The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. The estimated background risk of major birth defects and miscarriage in the U.S. general population is 2 to 4% and 15 to 20% of clinically recognized pregnancies, respectively. Data Animal Data Oral administration of tolvaptan during the period of organogenesis in Sprague-Dawley rats produced no evidence of teratogenesis at doses up to 100 mg/kg/day.
Delayed ossification was seen at 1,000 mg/kg, which is approximately 11 times the exposure in CHF patients at the MRHD of 60 mg (AUC 24h 10271 ng*h/mL). The fetal effects are likely secondary to maternal toxicity (decreased food intake and low body weights). In a prenatal and postnatal study in rats, tolvaptan had no effect on physical development, reflex function, learning ability or reproductive performance at doses up to 1,000 mg/kg/day (11 times the exposure in CHF patients at the MRHD of 60 mg).
In rabbits, teratogenicity (microphthalmia, embryo-fetal mortality, cleft palate, brachymelia and skeletal malformations) was observed in rabbits at 1,000 mg/kg (approximately 1.6 times the exposure in CHF patients at the MRHD of 60 mg dose). This dose also caused maternal toxicity (lower body weight gains and food consumption).
8.2Lactation Risk Summary There are no data on the presence of tolvaptan or its metabolites in human milk, the effects on the breastfed infant, or the effects on milk production. Tolvaptan is present in rat milk (see Data). When a drug is present in animal milk, it is possible that the drug will be present in human milk, but relative levels may vary (see Data) .
Because of the potential for serious adverse reactions, including electrolyte abnormalities (e.g., hypernatremia), hypotension, and volume depletion in breastfed infants, advise women not to breastfeed during treatment with tolvaptan. Data In lactating rats administered radiolabeled tolvaptan, lacteal radioactivity concentrations reached the highest level at 8 hours after administration and then decreased gradually with time with a half-life of 27.3 hours. The level of activity in milk ranged from 1.5-to 15.8-fold those in maternal blood over a period of 72 hours post-dose.
Increased perinatal death and decreased body weight of the offspring were observed during the lactation period and after weaning at approximately 11 times the exposure in CHF patients at the MRHD of 60 mg.
8.4Pediatric Use Safety and effectiveness of tolvaptan in pediatric patients have not been established.
8.5Geriatric Use Of the total number of hyponatremic subjects treated with tolvaptan in clinical studies, 42% were 65 years old and over, while 19% were 75 years old and over. No overall differences in safety or effectiveness were observed between these subjects and younger subjects, and…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available data with tolvaptan use in pregnant women are insufficient to determine if there is a drug-associated risk of adverse developmental outcomes. Tolvaptan did not cause any developmental toxicity in rats or in rabbits at exposures approximately 2.8 and 0.8 times, respectively, the exposure in congestive heart failure (CHF) patients at the maximum recommended human dose (MRHD) of 60 mg once daily. However, effects on embryo-fetal development occurred in both species at doses causing significant maternally toxic doses.
In rats, reduced fetal weights and delayed fetal ossification occurred at 11 times the exposure in CHF patients, based on AUC. In rabbits, increased abortions, embryo-fetal death, fetal microphthalmia, open eyelids, cleft palate, brachymelia and skeletal malformations occurred at approximately 1.6 times the exposure in CHF patients (see Data). The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. The estimated background risk of major birth defects and miscarriage in the U.S. general population is 2 to 4% and 15 to 20% of clinically recognized pregnancies, respectively. Data Animal Data Oral administration of tolvaptan during the period of organogenesis in Sprague-Dawley rats produced no evidence of teratogenesis at doses up to 100 mg/kg/day.
Delayed ossification was seen at 1,000 mg/kg, which is approximately 11 times the exposure in CHF patients at the MRHD of 60 mg (AUC 24h 10271 ng*h/mL). The fetal effects are likely secondary to maternal toxicity (decreased food intake and low body weights). In a prenatal and postnatal study in rats, tolvaptan had no effect on physical development, reflex function, learning ability or reproductive performance at doses up to 1,000 mg/kg/day (11 times the exposure in CHF patients at the MRHD of 60 mg).
In rabbits, teratogenicity (microphthalmia, embryo-fetal mortality, cleft palate, brachymelia and skeletal malformations) was observed in rabbits at 1,000 mg/kg (approximately 1.6 times the exposure in CHF patients at the MRHD of 60 mg dose). This dose also caused maternal toxicity (lower body weight gains and food consumption).
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of tolvaptan in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the total number of hyponatremic subjects treated with tolvaptan in clinical studies, 42% were 65 years old and over, while 19% were 75 years old and over. No overall differences in safety or effectiveness were observed between these subjects and younger subjects, and other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out. Increasing age has no effect on tolvaptan plasma concentrations.
🆘 Overdosage ▾
10 OVERDOSAGE Single oral doses up to 480 mg (8 times the maximum recommended daily dose) and multiple doses up to 300 mg once daily for 5 days have been well tolerated in studies in healthy subjects. There is no specific antidote for tolvaptan intoxication. The signs and symptoms of an acute overdose can be anticipated to be those of excessive pharmacologic effect: a rise in serum sodium concentration, polyuria, thirst, and dehydration/hypovolemia.
No mortality was observed in rats or dogs following single oral doses of 2,000 mg/kg (maximum feasible dose). A single oral dose of 2,000 mg/kg was lethal in mice, and symptoms of toxicity in affected mice included decreased locomotor activity, staggering gait, tremor and hypothermia. In patients with suspected tolvaptan overdosage, assessment of vital signs, electrolyte concentrations, ECG and fluid status are recommended.
Continue replacement of water and electrolytes until aquaresis abates. Dialysis may not be effective in removing tolvaptan because of its high binding affinity for human plasma protein (>98%).
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Tolvaptan is a selective vasopressin V 2 -receptor antagonist with an affinity for the V 2 -receptor that is 1.8 times that of native arginine vasopressin (AVP). Tolvaptan affinity for the V 2 -receptor is 29 times greater than for the V 1a -receptor. When taken orally, 15 to 60 mg doses of tolvaptan antagonize the effect of vasopressin and cause an increase in urine water excretion that results in an increase in free water clearance (aquaresis), a decrease in urine osmolality, and a resulting increase in serum sodium concentrations.
Urinary excretion of sodium and potassium and plasma potassium concentrations are not significantly changed. Tolvaptan metabolites have no or weak antagonist activity for human V 2 -receptors compared with tolvaptan.
12.2Pharmacodynamics In healthy subjects receiving a single dose of tolvaptan 60 mg, the onset of the aquaretic and sodium increasing effects occurs within 2 to 4 hours post-dose. A peak effect of about a 6 mEq increase in serum sodium and about 9 mL/min increase in urine excretion rate is observed between 4 and 8 hours post-dose; thus, the pharmacological activity lags behind the plasma concentrations of tolvaptan. About 60% of the peak effect on serum sodium is sustained at 24 hours post-dose, but the urinary excretion rate is no longer elevated by this time.
Doses above 60 mg tolvaptan do not increase aquaresis or serum sodium further. The effects of tolvaptan in the recommended dose range of 15 to 60 mg once daily appear to be limited to aquaresis and the resulting increase in sodium concentration. Plasma concentrations of native AVP may increase (avg.
2 to 9 pg/mL) with tolvaptan administration. Cardiac Electrophysiology No prolongation of the QT interval was observed with tolvaptan following multiple doses of 300 mg/day for 5 days.
12.3Pharmacokinetics In healthy subjects, the pharmacokinetics of tolvaptan after single doses of up to 480 mg and multiple doses up to 300 mg once daily have been examined. In hyponatremia subjects, single and multiple doses up to 60 mg have been studied. Absorption In healthy subjects, peak concentrations of tolvaptan are observed between 2 and 4 hours post-dose.
Peak concentrations increase less than dose proportionally with doses greater than 240 mg. The absolute bioavailability of tolvaptan decreases with increasing doses. The absolute bioavailability of tolvaptan following an oral dose of 30 mg is 56% (range 42 to 80%).
Co-administration of 90 mg tolvaptan with a high-fat meal (~1,000 calories, of which 50% are from fat) doubles peak concentrations but has no effect on the AUC of tolvaptan; tolvaptan may be administered with or without food. Distribution Tolvaptan binds to both albumin and α1-acid glycoprotein and the overall protein binding is >98%; binding is not affected by disease state. The volume of distribution of tolvaptan is about 3 L/kg.
The pharmacokinetic properties of tolvaptan are stereospecific, with a steady-state ratio of the S-(-) to the R-(+) enantiomer of about 3. When administered as multiple once-daily 300 mg doses to healthy subjects or to patients with congestive heart failure or ADPKD, tolvaptan’s accumulation factor is <1.2. There is marked inter-subject variation in peak and average exposure to tolvaptan with a percent coefficient of variation ranging between 30 and 60%.
Metabolism and Elimination Tolvaptan is metabolized almost exclusively by CYP3A. Fourteen metabolites have been identified in plasma, urine and feces; all but one were also metabolized by CYP3A and none are pharmacodynamically active. After oral administration of radiolabeled tolvaptan, tolvaptan was a minor component in plasma, representing 3% of total plasma radioactivity; the oxobutyric acid metabolite was present at 52.5% of total plasma radioactivity with all other metabolites present at lower concentrations than tolvaptan.
The oxobutyric acid metabolite shows a plasma half-life of ~180 h. About…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Tolvaptan is a selective vasopressin V 2 -receptor antagonist with an affinity for the V 2 -receptor that is 1.8 times that of native arginine vasopressin (AVP). Tolvaptan affinity for the V 2 -receptor is 29 times greater than for the V 1a -receptor. When taken orally, 15 to 60 mg doses of tolvaptan antagonize the effect of vasopressin and cause an increase in urine water excretion that results in an increase in free water clearance (aquaresis), a decrease in urine osmolality, and a resulting increase in serum sodium concentrations.
Urinary excretion of sodium and potassium and plasma potassium concentrations are not significantly changed. Tolvaptan metabolites have no or weak antagonist activity for human V 2 -receptors compared with tolvaptan.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING How Supplied Tolvaptan tablets are available in the following strengths and packages. Tolvaptan tablets 15 mg are non-scored, light blue to blue coloured, round shaped, uncoated tablets, debossed with "TOL" on one side and “15" on other side, may have mottled appearance. Bottles of 10 NDC 67877-635-02 Bottles of 100 NDC 67877-635-01 Carton of 10 (1 X 10 Unit-dose Tablets) NDC 67877-635-33 Tolvaptan tablets 30 mg are non-scored, light blue to blue coloured, round shaped, uncoated tablets, debossed with "TOL" on one side and “30" on other side, may have mottled appearance.
Bottles of 10 NDC 67877-636-02 Bottles of 100 NDC 67877-636-01 Carton of 10 (1 X 10 Unit-dose Tablets) NDC 67877-636-33 Tolvaptan tablets 60 mg are non-scored, light blue to blue coloured, round shaped, uncoated tablets, debossed with "TOL" on one side and “60" on other side, may have mottled appearance. Bottles of 10 NDC 67877-637-02 Bottles of 100 NDC 67877-637-01 Carton of 10 (1 X 10 Unit-dose Tablets) NDC 67877-637-33 Storage and Handling Store at 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
Keep out of reach of children.
📋 Description ▾
11 DESCRIPTION Tolvaptan tablets contains tolvaptan, a selective vasopressin V 2 -receptor antagonist in tablets for oral use available in 15 mg, 30 mg or 60 mg strengths. Tolvaptan is (±)-4'-[(7-chloro-2,3,4,5-tetrahydro-5-hydroxy-1 H -1-benzazepin-1-yl) carbonyl]- o -tolu- m -toluidide. The empirical formula is C 26 H 25 ClN 2 O 3 .
Molecular weight is 448.94. The chemical structure is: Inactive ingredients include croscarmellose sodium, hypromellose, lactose monohydrate, magnesium stearate, maize starch, microcrystalline cellulose, and FD&C Blue No. 2 Aluminum Lake as colorant. tolvaptan-structure-1
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION As a part of patient counseling, healthcare providers must review the tolvaptan tablets Medication Guide with every patient [see FDA-Approved Medication Guide]. Pregnancy Advise pregnant women of the potential risk to a fetus. Advise females of reproductive potential to inform their prescriber of a known or suspected pregnancy [see Use in Specific Populations (8.1)].
Lactation Advise patients not to breastfeed an infant if they are taking tolvaptan tablets [see Use in Specific Populations (8.2)]. Manufactured by: Alkem Laboratories Ltd., INDIA. Distributed by: Ascend Laboratories, LLC Parsippany, NJ 07054 Revised: May, 2022
💬 Medication Guide ▾
MEDICATION GUIDE Tolvaptan Tablets (tol vap' tan) Read the Medication Guide that comes with tolvaptan tablets before you take it and each time you get a new prescription. There may be new information. This Medication Guide does not take the place of talking to your healthcare provider about your medical condition or your treatment.
Share this important information with members of your household. What is the most important information I should know about tolvaptan tablets? 1) Tolvaptan tablets may make the salt (sodium) level in your blood rise too fast.
This can increase your risk of a serious condition called osmotic demyelination syndrome (ODS). ODS can lead to coma or death. ODS can also cause new symptoms such as: • trouble speaking • swallowing trouble or feeling like food or liquid gets stuck while swallowing • drowsiness • confusion • mood changes • trouble controlling body movement (involuntary movement) and weakness in muscles of the arms and legs • seizures You or a family member should tell your healthcare provider right away if you have any of these symptoms even if they begin later in treatment.
Also tell your healthcare provider about any other new symptoms while taking tolvaptan tablets. You may be more at risk for ODS if you have: • liver disease • not eaten enough for a long period of time (malnourished) • very low sodium level in your blood • been drinking large amounts of alcohol for a long period of time (chronic alcoholism) To lessen your risk of ODS while taking tolvaptan tablets: • Treatment with tolvaptan tablets should be started and re-started only in a hospital, where the sodium levels in your blood can be checked closely. • Do not take tolvaptan tablets if you cannot tell if you are thirsty. • To prevent losing too much body water (dehydration), have water available to drink at all times while taking tolvaptan tablets.
Unless your healthcare provider tells you otherwise, drink when you are thirsty. • If your healthcare provider tells you to keep taking tolvaptan tablets after you leave a hospital, it is important that you do not stop and re-start tolvaptan tablets on your own. You may need to go back to a hospital to re-start tolvaptan tablets. Talk to your healthcare provider right away if you stop taking tolvaptan tablets for any reason. • It is important to stay under the care of your healthcare provider while taking tolvaptan tablets and follow their instructions.
2) Tolvaptan tablets may cause liver problems, including life-threatening liver failure. Tolvaptan tablets should not be taken for more than 30 days. Tell your doctor right away if you develop or have worsening of any of these signs and symptoms of liver problems: • Loss of appetite, nausea, vomiting • Fever, feeling unwell, unusual tiredness • Itching • Yellowing of the skin or the whites of the eyes (jaundice) • Unusual darkening of the urine • Right upper stomach area pain or discomfort 3) If you have autosomal dominant polycystic kidney disease (ADPKD), do not use tolvaptan tablets because you should receive the medicine (tolvaptan) through a program that ensures laboratory monitoring of your liver.
What is tolvaptan tablets? Tolvaptan tablets is a prescription medicine used to help increase low sodium levels in the blood, in adults with conditions such as heart failure, and certain hormone imbalances. Tolvaptan tablets helps raise salt levels in your blood by removing extra body water as urine.
It is not known if tolvaptan tablets is safe or works in children. Who should not take tolvaptan tablets? Do not take tolvaptan tablets if: • you are allergic to tolvaptan or any of the ingredients in tolvaptan tablets.
See the end of this Medication Guide for a complete list of ingredients in tolvaptan tablets. • the sodium level in your blood must be increased right away. • you cannot replace fluids by drinking or you cannot feel if you are thirsty. • you are dizzy, faint, or your kidneys are not working normally because you have lost too…