
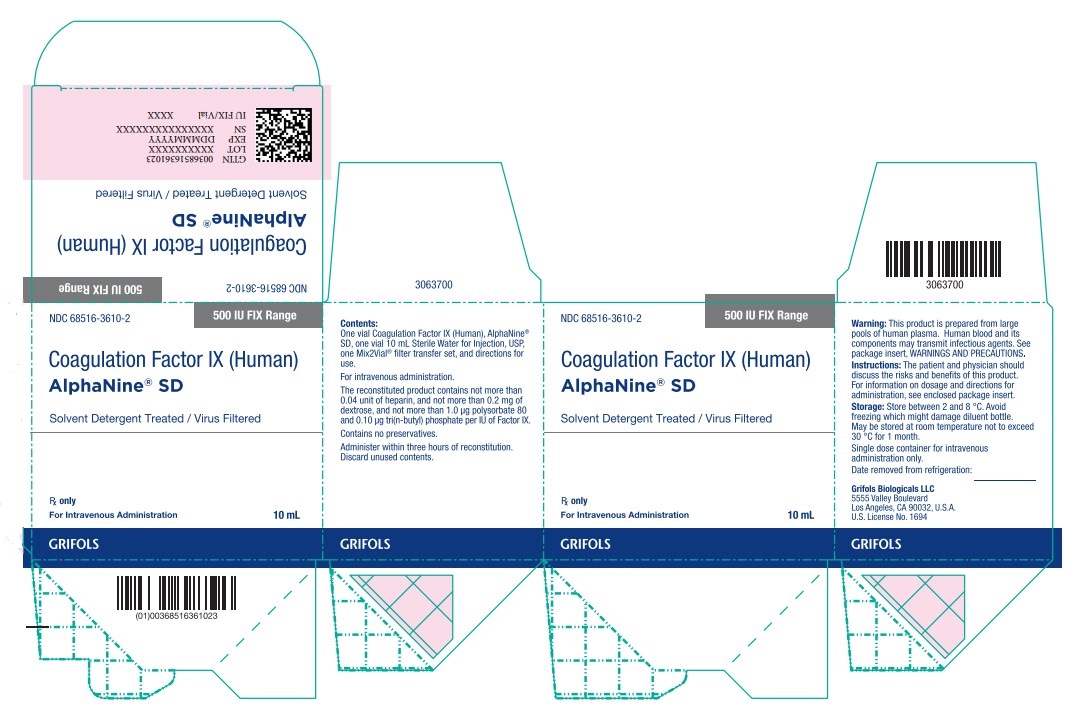
AlphaNine SD COAGULATION FACTOR IX (HUMAN) Kit
🆔 Identity & classification
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J7193 | $1.403 / J7193 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| AlphaNine SD 68516-3609-02 | GRIFOLS | 1 kit | — | — | FDA listed | — |
| AlphaNine SDthis 68516-3612-02 | GRIFOLS | 1 kit | — | — | FDA listed | — |
| AlphaNine SD 68516-3607-02 | GRIFOLS | 1 kit | — | — | FDA listed | — |
| AlphaNine SD 68516-3608-02 | GRIFOLS | 1 kit | — | — | FDA listed | — |
| AlphaNine SD 68516-3611-02 | GRIFOLS | 1 kit | — | — | FDA listed | — |
| AlphaNine SD 68516-3610-02 | GRIFOLS | 1 kit | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & biosimilar status
Biologics have no small-molecule generics; biosimilar competition is tracked in the FDA Purple Book.
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 68516-3612-02 You're viewing this | 1 KIT in 1 CARTON (68516-3612-2) * 10 mL in 1 VIAL (68516-3604-2) * 10 mL in 1 VIAL, GLASS (76297-002-12) | 1990-12-31 | Active |
🧭 About this NDC listing & data coverage
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Does this product have a billing J-code?
Where does this data come from?
📄 Full FDA label FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE AlphaNine SD is indicated for the prevention and control of bleeding in patients with Factor IX deficiency due to hemophilia B. AlphaNine SD contains low, non-therapeutic levels of Factors II, VII, and X, and, therefore, is not indicated for the treatment of Factor II, VII or X deficiencies. This product is also not indicated for the reversal of coumarin anticoagulant-induced hemorrhage, nor in the treatment of hemophilia A patients with inhibitors to Factor VIII.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION For adult usage: AlphaNine SD should be administered intravenously promptly following reconstitution. Administration of AlphaNine SD within three hours after reconstitution is recommended to avoid the potential ill effect of any inadvertent bacterial contamination occurring during reconstitution. Discard any unused contents into the appropriate safety container.
Each vial of AlphaNine SD is labeled with the total units expressed as International Units (IU) of Factor IX, which is referenced to the WHO International Standard. One unit approximates the activity in one mL of pooled normal human plasma. The amount of AlphaNine SD required to establish hemostasis will vary with each patient and depend upon the circumstances.
The following formula may be used as a guide in determining the number of units to be administered. 16 In clinical practice there is variability between patients and their clinical response. Therefore, the Factor IX level of each patient should be monitored frequently during replacement therapy.
Formula For pediatric usage: See PRECAUTIONS Treatment Guidelines for Hemorrhagic Events and Surgery in Patients Diagnosed with Hemophilia B Type of Hemorrhage or Surgical Procedure Examples Treatment Guidelines Minor Hemorrhages Bruises, cuts or scrapes, uncomplicated joint hemorrhage FIX levels should be brought to at least 20-30% (20-30 IU FIX/kg/twice daily) until hemorrhage stops and healing has been achieved (1-2 days). 17,18,19 Moderate Hemorrhages Nose bleeds, mouth and gum bleeds, dental extractions, hematuria FIX levels should be brought to 25-50% (25-50 IU FIX/kg/twice daily) until healing has been achieved (2-7 days, on average).
17,18,19,20,21 Major Hemorrhages Joint and muscle hemorrhages (especially in the large muscles), major trauma, hematuria, intracranial and intraperitoneal bleeding FIX levels should be brought to 50% for at least 3-5 days (30-50 IU FIX/kg/twice daily). Following this treatment period, FIX levels should be maintained at 20% (20 IU FIX/kg/twice daily) until healing has been achieved. Major hemorrhages may require treatment for up to 10 days.
17,18,19,20,21 Surgery Prior to surgery, FIX should be brought to 50-100% of normal (50-100 IU FIX/kg/twice daily). For the next 7 to 10 days, or until healing has been achieved, the patient should be maintained at 50-100% FIX levels (50-100 IU FIX/kg/twice daily). 17,18,19,20,21 Dosing requirements and frequency of dosing is calculated on the basis of an initial response of 1% FIX increase achieved per IU of FIX infused per kg body weight and an average half-life for FIX of 18 hours.
If dosing studies have revealed that a particular patient exhibits a lower response, the dose should be adjusted accordingly. For pediatric usage: See PRECAUTIONS RECONSTITUTION Use Aseptic Technique Warm diluent (Sterile Water for Injection, USP) and concentrate (AlphaNine SD) to at least room temperature (but not above 37 °C). Remove the plastic flip off cap from the diluent vial.
Gently swab the exposed stopper surface with a cleansing agent such as alcohol trying to avoid leaving any excess cleansing agent on the stopper. Open the Mix2Vial ® package by peeling away the lid (Figure 1). Leave the Mix2Vial in the clear outer packaging.
Place the diluent vial upright on an even surface and hold the vial tight and pick up the Mix2Vial in its clear outer packaging. Holding the diluent vial securely, push the blue end of the Mix2Vial vertically down through the diluent vial stopper (Figure 2). While holding onto the diluent vial, carefully remove the clear outer packaging from the Mix2Vial set, ensuring the Mix2Vial remains attached to the diluent vial (Figure 3).
Place the product vial upright on an even surface, invert the diluent vial with the Mix2Vial attached. While holding the product vial securely on a flat surface, push the clear end of the Mix2Vial set vertically down through the product vial stopper (Figure 4). The diluent will automat…
⛔ Contraindications ▾
CONTRAINDICATIONS None known.
⚠️ Warnings ▾
WARNINGS Because Coagulation Factor IX (Human), AlphaNine SD is made from pooled human plasma, it may carry a risk of transmitting infectious agents, e.g., viruses, and theoretically, the Creutzfeldt-Jakob disease (CJD) agent. Stringent procedures designed to reduce the risk of adventitious agent transmission have been employed in the manufacture of this product, from the screening of plasma donors and the collection and testing of plasma to the application of viral elimination/reduction steps such as column chromatography, solvent detergent treatment and nanofiltration in the manufacturing process.
Despite these measures, such product can potentially transmit disease, therefore the risk of infectious agents cannot be totally eliminated. The physician should weigh the risks and benefits of the use of this product and should discuss these with the patient. Individuals who receive infusions of blood or plasma products may develop signs and/or symptoms of some viral infections.
Scientific opinion encourages hepatitis B and hepatitis A vaccinations at birth or diagnosis for patients with hemophilia. Incidences of thrombosis or disseminated intravascular coagulation (DIC), have been reported following administration of Factor IX Complex concentrates which contain high amounts of Factor II, VII and X. Following administration of Coagulation Factor IX (Human), AlphaNine SD in surgery patients and individuals with known liver disease, the physician should closely observe the patient for signs or symptoms of potential disseminated intravascular coagulation (DIC).
Continued administration of the product should be left to the discretion of the physician. Allergic type hypersensitivity reactions, including anaphylaxis, have been reported for all factor IX products. Frequently these events have occurred in close temporal association with the development of factor IX inhibitors.
Patients should be informed of the early symptoms and signs of hypersensitivity reactions, including hives, generalized urticaria, angioedema, chest tightness, dyspnea, wheezing, faintness, hypotension, tachycardia and anaphylaxis. Patients should be advised to discontinue use of the product and contact physician and/or seek immediate emergency care, depending on the severity of the reactions, if any of these symptoms occur. Nephrotic syndrome has been reported following attempted immune tolerance induction with factor IX products in Hemophilia B patients with factor IX inhibitors and a history of severe allergic reactions to Factor IX.
The safety and efficacy of using AlphaNine SD in attempted immune tolerance induction has not been established. In Previously Untreated Patients (PUPs), it is possible that anaphylaxis may occur after a median exposure of eleven (11) days. 15 It is recommended that these patients are monitored closely between the tenth and twentieth exposure day.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS The administration of plasma preparations may cause allergic reactions, mild chills, nausea or stinging at the infusion site. For most reactive individuals, slowing the infusion rate relieves the symptoms. For those highly reactive individuals, a different lot may be satisfactory.
Adverse reactions, characterized by either thrombosis or disseminated intravascular coagulation (DIC), have been reported following administration of Factor IX Complex concentrates. Patients who receive Coagulation Factor IX (Human), AlphaNine SD, following operation, or those with known liver disease, should be kept under close observation for potential signs or symptoms of intravascular coagulation. Continued administration should be left to the discretion of the physician.
In the clinical study that compared the in vivo half-life and recovery of AlphaNine SD and HT products, no adverse events were associated with 18 infusions of AlphaNine SD administered to 18 individuals with severe to moderate hemophilia B. 2 Short term safety of the earlier version of this product, AlphaNine, was demonstrated by an absence of adverse events after 225 infusions of this product were received by 31 patients participating in three clinical trials. In the clinical trial to evaluate efficacy of AlphaNine in providing hemostatic protection during and after surgery, 13 patients received a total of 370,655 IU of AlphaNine.
In 208 total infusions, each patient received approximately 15,000 IU (range 3,295 to 52,200 IU Factor IX) in an average of 16 infusions (range 2 to 26 infusions). Results from this study showed no bleeding episodes during the course of postsurgery therapy. There was no hematological evidence (measured by hematocrit, partial thromboplastin time, prothrombin time, fibrinogen/fibrin degradation products, fibrin monomers, D-dimers and platelet counts) of thrombogenicity.
12 To report SUSPECTED ADVERSE REACTIONS, contact Grifols at 1-888-GRIFOLS (1-888-474-3657) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
🤰 Pregnancy ▾
Pregnancy Category C Animal reproduction studies have not been conducted with AlphaNine SD. It is also not known whether AlphaNine SD can cause fetal harm when administered to a pregnant woman or can affect reproduction capacity. AlphaNine SD should be given to a pregnant woman only if clearly indicated.
🧒 Pediatric Use ▾
Pediatric Use Clinical trials for safety and effectiveness in pediatric patients 16 years of age and younger have not been conducted. Across a well controlled half-life and recovery clinical trial in patients previously treated with Factor IX concentrates of Hemophilia B, the three pediatric patients receiving AlphaNine SD (solvent detergent treated) responded similarly when compared with 15 adult patients. 2 In an ongoing safety and efficacy clinical trial in patients not previously treated with Factor IX concentrates for Hemophilia B, 21 pediatric patients received AlphaNine SD (solvent detergent treated) responded similarly when compared with the five adult patients above the age of 16 years.
Adverse events were similar in this group compared to the patients above the age of 16 years. Anecdotal evaluation of the results indicates no safety and efficacy differences between pediatric and adult populations.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY AlphaNine SD is a purified formulation of Factor IX containing not less than 150 IU Factor IX activity/mg of total protein. 2 AlphaNine SD contains non-therapeutic levels of Factor II, Factor VII and Factor X. Thrombogenicity of AlphaNine SD in animals is markedly lower than that of Factor IX Complex, Profilnine ® Heat-Treated.
Five lots of AlphaNine SD (three lots of non-virus filtered product and two lots of virus filtered product) failed to show any evidence of thrombogenicity when tested directly in the Wessler rabbit stasis model for thrombogenicity 3-6 at a dose of 200 IU Factor IX/kg body weight. When various lots of AlphaNine SD were further tested at doses between 300 and 650 IU Factor IX/kg, only 5 out of 40 animals (12.5%) showed evidence of thrombus formation (Wessler scores of +1, +2, +1, +1, +1 out of +4 maximum). In comparison, Factor IX Complex concentrate, Profilnine, was thrombogenic in 100% of the animals tested at a dose of 100 IU Factor IX/kg.
At a dose of 200 IU Factor IX/kg body weight in a porcine model, the heptane heat-treated formulation of this product (AlphaNine) showed little evidence of disseminated intravascular coagulation (DIC) following infusion. 7 This model exhibited no depletion of coagulation factors, a minimal increase in fibrin monomer (+1 in protamine test), a slight temporary decrease in platelet counts, and no evidence of intravascular coagulation upon gross autopsy. 8 In contrast, Harrison, et al., report that all Factor IX Complex concentrates studied in the same porcine model were thrombogenic at doses between 50 and 100 IU of Factor IX/kg animal weight.
9 A clinical evaluation of AlphaNine SD half-life and recovery characteristics was performed. A total of 18 patients with severe to moderate hemophilia B each received a single infusion of 40 to 50 IU Factor IX/kg body weight of AlphaNine SD. Following the administration of AlphaNine SD, the mean half-life of Factor IX observed was approximately 21 hours.
2 This half-life value was computed using the biphasic linear regression model recommended by the International Society of Thrombosis and Haemostasis. 10 The half-life obtained for the solvent detergent treated product is comparable to that of AlphaNine (approximately 19 hours) as well as the range of 18 to 36 hours reported for Factor IX Complex preparations. 11 The mean recovery observed in clinical trials was approximately 48% and was comparable to that of AlphaNine (approximately 51%).
2 A clinical trial was conducted using the heptane heat-treated product, AlphaNine, to evaluate the efficacy of the product in providing hemostatic protection during and after surgery in 13 patients with hemophilia B. The types of surgical procedures performed included bilateral knee replacement (1), total knee replacement with synovectomy (2), hip replacement (1), below the knee amputation (1), herniorrhaphy (2), hemorrhoidectomy (1), rhinoplasty (2), oral surgery (2) and Hickman catheter insertion with temporalis muscle transfer (1).
Presurgery doses ranged from 30.1 to
65.0IU Factor IX/kg; postsurgery replacement therapy doses ranged from approximately 9.4 to
52.0IU Factor IX/kg. The number of postsurgery days of treatment ranged from 1 to 23; the number of postsurgery infusions ranged from 2 to 26. No bleeding episodes were reported and hemostasis was maintained during the course of postsurgery therapy.
None of the hematologic parameters examined (hematocrit, partial thromboplastin time, prothrombin time, fibrinogen/fibrin degradation products, fibrin monomers, D-dimers and platelet counts) provided any evidence that AlphaNine possessed thrombogenic potential. 12 A randomized crossover study with 11 hemophilia B patients was conducted with the heptane heat-treated version of the product, AlphaNine, to determine whether an infusion of AlphaNine caused less activation of the hemostatic system than the Factor IX Complex concentrate preparation, Profilnine Heat-Treated.…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED AlphaNine SD is supplied in sterile, lyophilized form in single dose vials accompanied by 10 mL diluent (Sterile Water for Injection, USP). Factor IX activity, expressed in International Units (IU) which is referenced to WHO International Standard, is stated on the label of each concentrate vial. AlphaNine SD is packaged with a Mix2Vial filter transfer set for use in administration.
It is available in the following potencies, and the product is also color coded based upon assay on the carton and vial label as follows: Potency NDC Assay Color Code 500 IU FIX/10 mL single dose vial 68516-3601-2 500 IU FIX Range - blue box 1000 IU FIX/10 mL single dose vial 68516-3602-2 1000 IU FIX Range - red box 1500 IU FIX/10 mL single dose vial 68516-3603-2 1500 IU FIX Range - black box STORAGE AlphaNine SD should be stored at temperatures between 2 and 8 °C. Do not freeze to prevent damage to diluent vial. May be stored at room temperature not to exceed 30 °C for 1 month.
When removed from refrigeration, record the date removed on the space provided on the carton. Rx only
📦 Storage and Handling ▾
STORAGE AlphaNine SD should be stored at temperatures between 2 and 8 °C. Do not freeze to prevent damage to diluent vial. May be stored at room temperature not to exceed 30 °C for 1 month. When removed from refrigeration, record the date removed on the space provided on the carton. Rx only
📋 Description ▾
DESCRIPTION Coagulation Factor IX (Human), AlphaNine ® SD, is a purified, solvent detergent treated, virus filtered preparation of Factor IX derived from human plasma. 1 It contains a minimum of 150 IU Factor IX/mg protein; levels of Factor VII (proconvertin), Factor II (prothrombin) and Factor X (Stuart-Prower Factor) which are below the limit of detection (less than
0.04 Factor VII unit, less than
0.05 Factor II unit, and less than
0.05Factor X unit per IU Factor IX). AlphaNine SD is a sterile, lyophilized preparation intended for intravenous administration only. Each vial is a single dose container. AlphaNine SD is labeled with the Factor IX potency expressed in International Units (IU). AlphaNine SD contains not more than (NMT) 0.04 unit of heparin, NMT 0.2 mg of dextrose, NMT 1.0 μg polysorbate 80 and NMT 0.10 μg tri(n-butyl) phosphate/IU of Factor IX.
💬 Information for Patients ▾
Information for Patients Patients should be informed of the early symptoms and signs of hypersensitivity reaction, including hives, generalized urticaria, chest tightness, dyspnea, wheezing, faintness, hypotension, and anaphylaxis. Patients should be advised to discontinue use of the product and contact their physician and/or seek immediate emergency care, depending on the severity of the reaction, if these symptoms occur. Some viruses, such as parvovirus B19 or hepatitis A, are particularly difficult to remove or inactivate at this time.
Parvovirus B19 may most seriously affect sero-negative pregnant women, or immunocompromised individuals. The majority of parvovirus B19 and hepatitis A infections are acquired by environmental (natural) sources. Preliminary information suggests a relationship may exist between the presence of major deletion mutations in the Factor IX gene and an increased risk of inhibitor formation and of acute hypersensitivity reactions.
Patients known to have major deletion mutations of the Factor IX gene should be observed closely for signs and symptoms of acute hypersensitivity reactions, particularly during the early phases of initial exposure to product.