
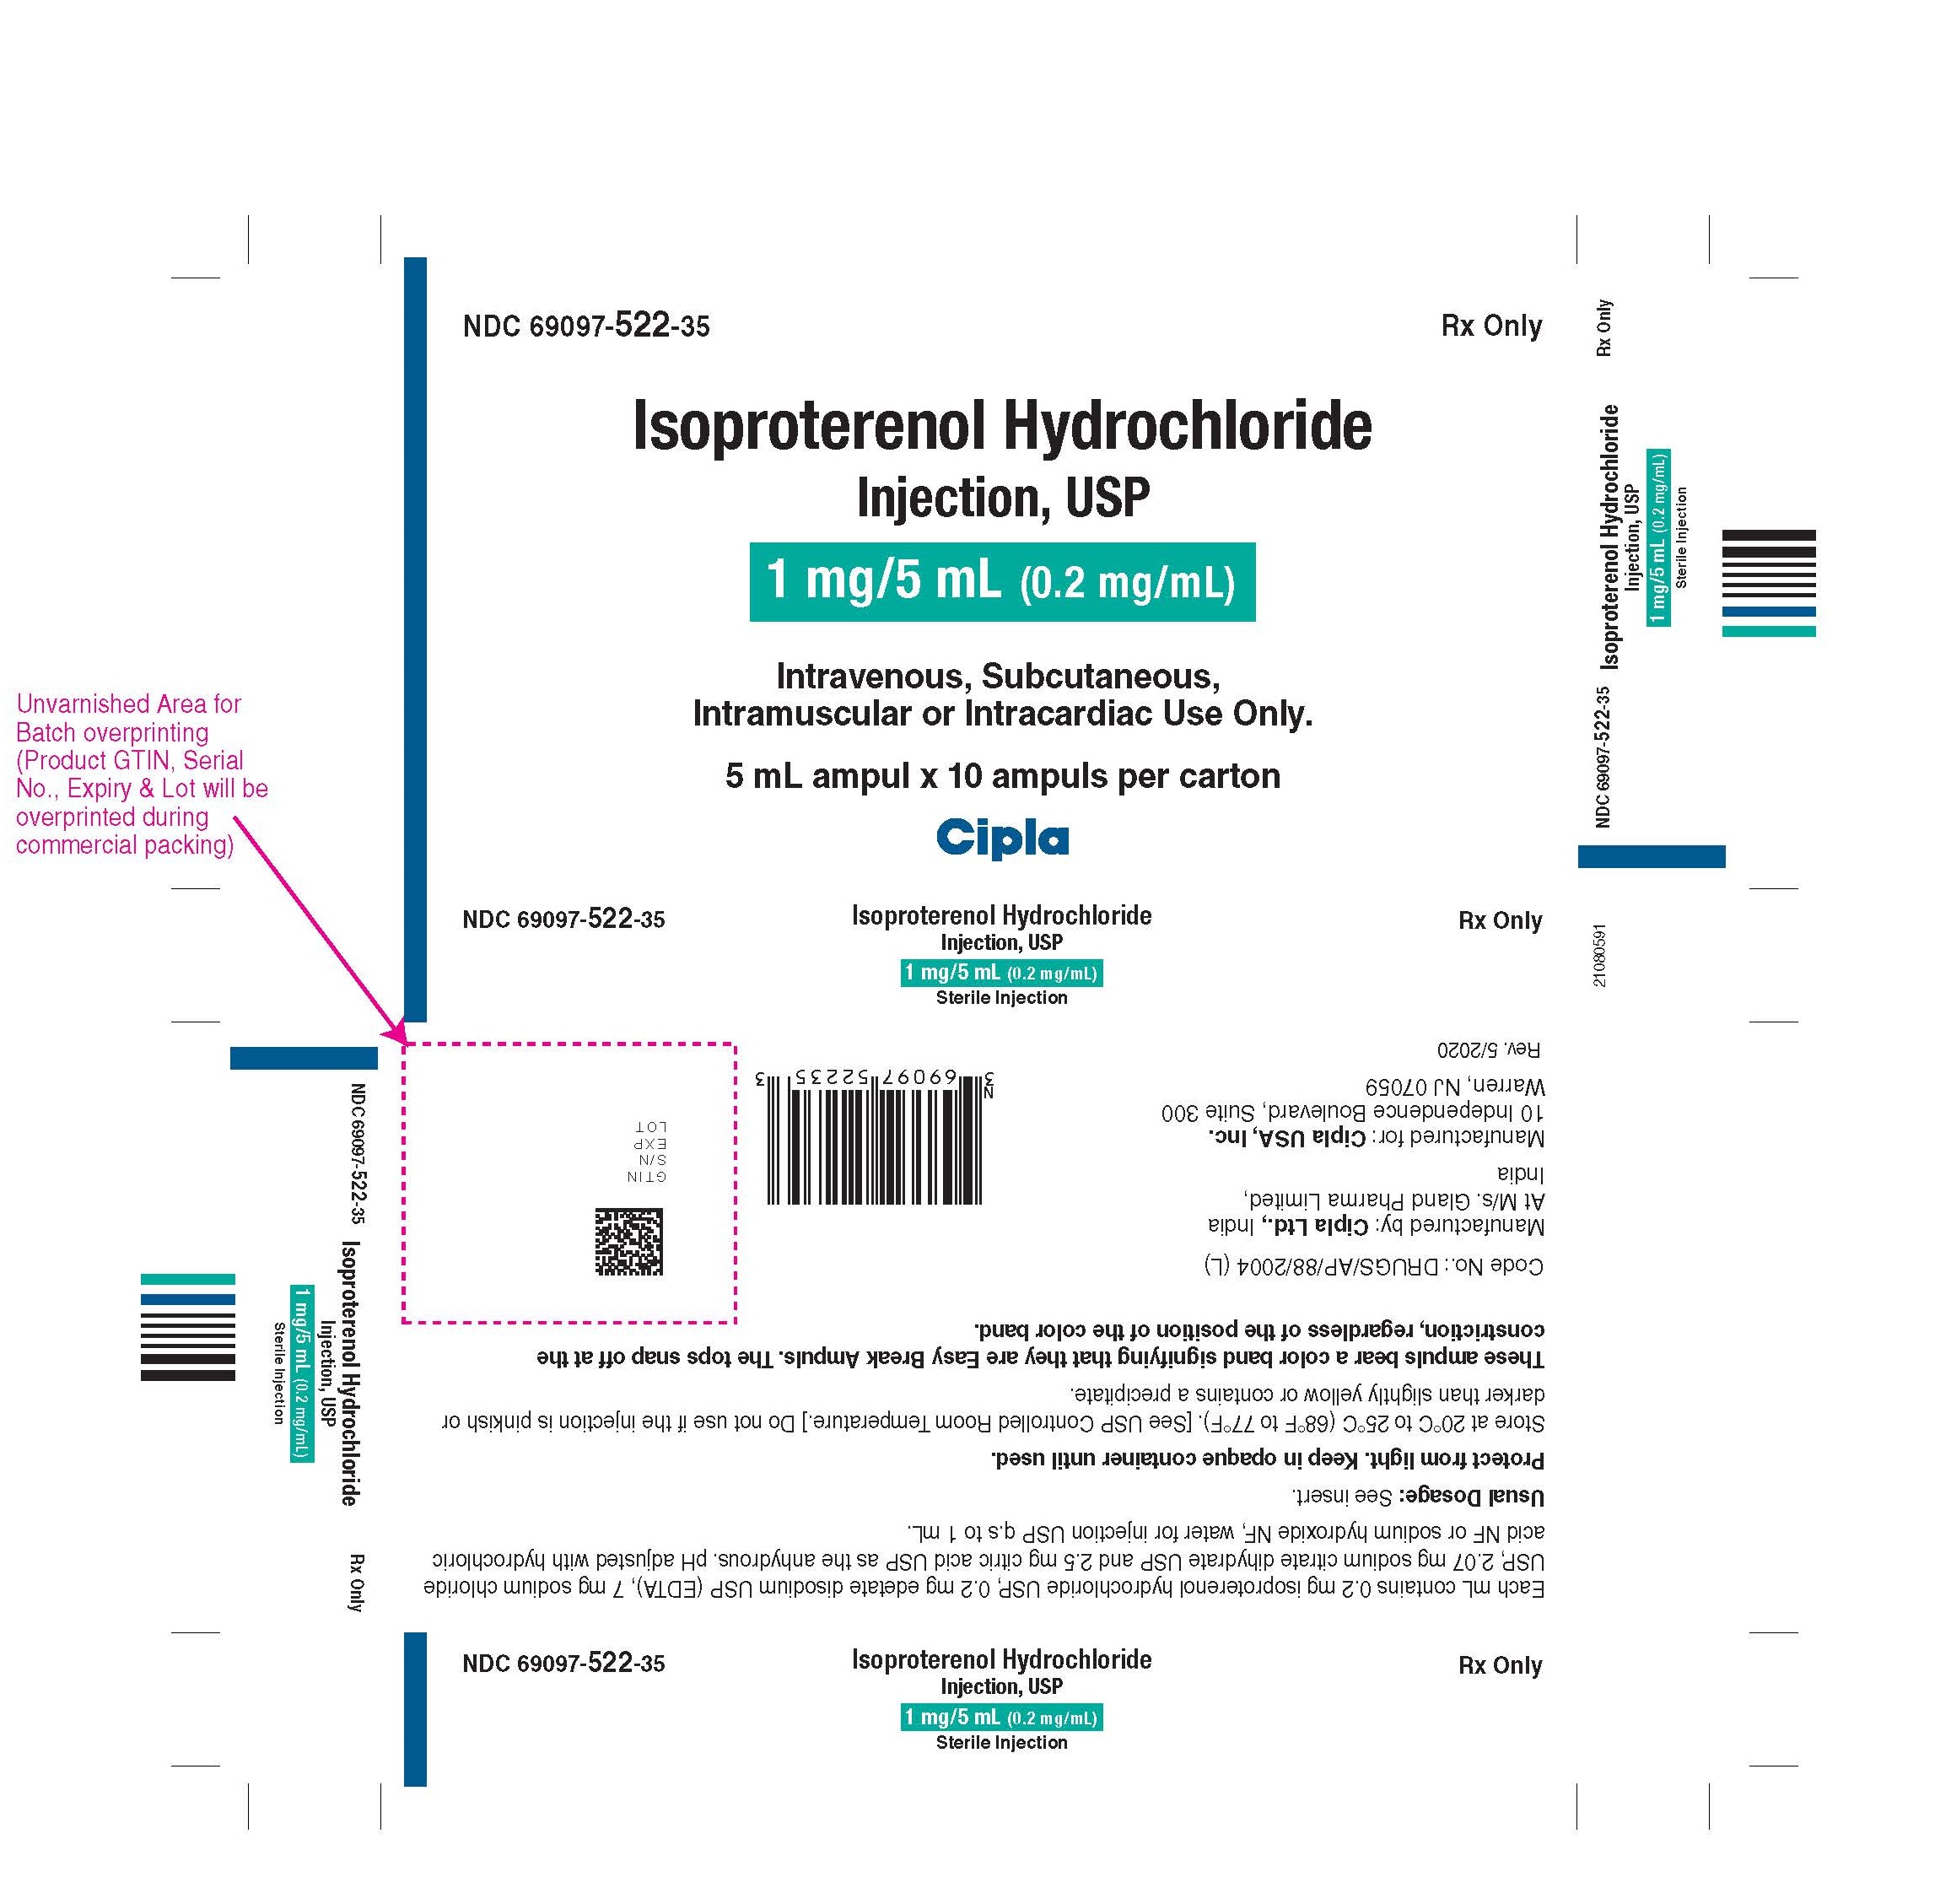
ISOPROTERENOL 1 mg/5mL Injection, Solution — NDC 69097-522-35 (Billing 69097-0522-35)
This is a package of ISOPROTERENOL 1 mg/5mL Injection, Solution from Cipla USA Inc., marketed since Jun 2018 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 69097-522-35 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 69097 labeler · 522 product · 35 package
- Package marketed since
- Jun 26, 2018
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC)
- 0369097521318, 0369097522353
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 004941
- GCN: 19490
- GPI-14 (Medi-Span): 44201040102005
- HICL (First Databank): 002053
- AHFS class code: 12:12.08.04
- RxCUI (RxNorm): 1667909
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the beta-Adrenergic Agonist class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Patient education
Supplement & herbal interactions
Isoproterenol may be associated with lower levels of 2 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 69097-0522-35 You're viewing this Main listing | 10 AMPULE in 1 CARTON / 5 mL in 1 AMPULE | 2018-06-26 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Isoproterenol Hydrochloride .2 mg/mL 00548-9502-00 | Amphastar | 10 vials | — | AP | FDA listed | — |
| Isoproterenol hydrochloride .2 mg/mL 10702-0364-51 | KVK-Tech, | 10 vials | — | AP | FDA listed | — |
| Isoproterenol Hydrochloride .2 mg/mL 14789-0015-05 | Nexus | 10 vials | — | AP | FDA listed | — |
| Isoproterenol Hydrochloride .2 mg/mL 23155-0661-41 | Heritage | 10 vials | — | AP | FDA listed | — |
| Isoproterenol Hydrochloride .2 mg/mL 25021-0324-01 | Sagent | 10 vials | — | AP | FDA listed | — |
| Isoproterenol Hydrochloride .2 mg/mL 42571-0330-80 | Micro | 10 ampules | — | AP | FDA listed | — |
| Isoproterenol Hydrochloride 1 mg/5mL 55150-0317-10 | Eugia | 10 ampules | — | — | FDA listed | — |
| isoproterenol hydrochloride 1 mg/5mL 68083-0586-10 | Gland | 10 vials | — | AP | FDA listed | — |
| Isoproterenol 1 mg/5mLthis 69097-0522-35 | Cipla | 10 ampules | — | — | FDA listed | — |
| Isoproterenol Hydrochloride .2 mg/mL 69918-0735-10 | Nordic | 10 vials | — | AP | FDA listed | — |
| Isoproterenol Hydrochloride 1 mg/5mL 70121-1605-07 | Amneal | 10 vials | — | AP | FDA listed | — |
| Isoproterenol Hydrochloride .2 mg/mL 72485-0113-10 | Armas | 10 ampules | — | AP | FDA listed | — |
| Isoproterenol Hydrochloride .2 mg/mL 83634-0303-01 | Avenacy, | 10 vials | — | AP | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Cipla USA Inc. labeler code 69097
- Esomeprazole magnesium 2.5 mg For Suspension NDC 69097-507-31
- Esomeprazole magnesium 5 mg For Suspension NDC 69097-508-31
- Abacavir 300 mg Tablet, Film Coated NDC 69097-514-03
- Cyclophosphamide 25 mg Capsule NDC 69097-516-07
- Cyclophosphamide 50 mg Capsule NDC 69097-517-07
- ISOPROTERENOL .2 mg/mL Injection, Solution NDC 69097-521-31
- Tadalafil 20 mg Tablet, Film Coated NDC 69097-526-03
- Esomeprazole Magnesium 10 mg Granule, For Suspension, Extended Release NDC 69097-527-34
- Esomeprazole magnesium 20 mg For Suspension NDC 69097-528-34
- Esomeprazole magnesium 40 mg For Suspension NDC 69097-529-34
- Pantoprazole Sodium Delayed-Release delayed release pantoprazole sodium granules 40 mg Suspension NDC 69097-531-53
- Tenofovir disoproxil fumarate 300 mg Tablet NDC 69097-533-02
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Isoproterenol hydrochloride injection is indicated: To improve hemodynamic status in patients in distributive shock and shock due to reduced cardiac output For bronchospasm occurring during anesthesia Isoproterenol hydrochloride injection is a beta-adrenergic agonist indicated: To improve hemodynamic status in patients in distributive shock and shock due to reduced cardiac output ( 1 ) For treatment of bronchospasm occurring during anesthesia ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Initiate Isoproterenol hydrochloride injection at the lowest recommended dose and increase gradually based on patient response ( 2.2 ) Recommended initial dosage: Shock: 0.5 mcg to 5 mcg per minute as an intravenous infusion ( 2.2 ) Bronchospasm: 10 mcg to 20 mcg intravenous injection ( 2.2 )
2.1General Considerations Inspect visually for particulate matter and discoloration prior to administration, whenever solution and container permit. Do not use if the injection is pinkish or darker than slightly yellow or contains a precipitate. Discard any unused portion. Diluted solution should be used immediately. Unused material should be discarded.
2.2Recommended Dosage Dosage should generally be started at the lowest recommended dose and increased gradually based on patient response. Recommended dosage for adults with shock and hypoperfusion states: Route of Administration Preparation of Dilution† Infusion Rate†† Intravenous infusion Dilute 5 mL (1 mg) in 500 mL of 5% Dextrose Injection, USP 0.5 mcg to 5 mcg per minute (0.25 mL to 2.5 mL of diluted solution) †Concentrations up to 10 times greater have been used when limitation of volume is essential. ††Rates over 30 mcg per minute have been used in advanced stages of shock.
Adjust the rate of infusion based on heart rate, central venous pressure, systemic blood pressure, and urine flow. If the heart rate exceeds 110 beats per minute, consider decreasing or temporarily discontinuing the infusion. Recommended dosage for adults with bronchospasm occurring during anesthesia: Route of Administration Preparation of Dilution Initial Dose Subsequent Dose Bolus intravenous injection Dilute 1 mL (0.2 mg) to 10 mL with Sodium Chloride Injection, USP, or 5% Dextrose Injection, USP 10 mcg to 20 mcg (0.5 mL to 1 mL of diluted solution) The initial dose may be repeated when necessary There are no well-controlled studies in children to establish appropriate dosing; however, the American Heart Association recommends an initial infusion rate of 0.1 mcg/kg/min, with the usual range being 0.1 mcg/kg/min to 1 mcg/kg/min.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Injection solution: single dose, clear glass ampules containing isoproterenol in a clear, colorless to practically colorless solution; 1 mL containing 0.2 mg/1 mL (0.2 mg/mL) 5 mL containing 1 mg/5 mL (0.2 mg/mL) Injection: 0.2 mg/mL and 1 mg/5 mL (0.2 mg/mL) single dose vial ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Isoproterenol hydrochloride injection is contraindicated in patients with: tachycardia ventricular arrhythmias angina pectoris Isoproterenol hydrochloride injection is contraindicated in patients with: Tachycardia ( 4 ) Ventricular arrhythmias ( 4 ) Angina pectoris ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Cardiac arrhythmias and ischemia may be induced by isoproterenol ( 5.1 ) Sulfite: Isoproterenol hydrochloride injection contains metabisulfite, which may cause allergic reaction ( 5.2 )
5.1Cardiac Arrhythmias and Ischemia Isoproterenol may induce cardiac arrhythmias and myocardial ischemia in patients, especially patients with coronary artery disease, or cardiomyopathy.
5.2Allergic Reactions associated with Sulfite Isoproterenol hydrochloride injection contains sodium metabisulfite, which may cause mild to severe allergic reactions including anaphylaxis or asthmatic episodes, particularly in patients with a history of allergies. However, the presence of metabisulfite in this product should not preclude its use for treatment in emergency situations, even if the patient is sulfite-sensitive, as the alternatives to using isoproterenol in a life-threatening situation may not be satisfactory.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions have been associated with use of isoproterenol. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to estimate their frequency reliably or to establish a causal relationship to drug exposure. Nervous system disorders: Nervousness, headache, dizziness, visual blurring Cardiovascular: Tachycardia, tachyarrhythmias, palpitations, angina, ventricular arrhythmias, Adams-Stokes attacks, pulmonary edema Respiratory: Dyspnea Other: Flushing of the skin, sweating, mild tremors, pallor, nausea Common adverse reactions with isoproterenol include tachycardia and palpitations (6) To report SUSPECTED ADVERSE REACTIONS, contact Cipla Limited, India at 1- 866 -604 -3268 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Table 1. Clinically Relevant Interactions with Isoproterenol Epinephrine Clinical Impact Both drugs are direct cardiac stimulants, and their combined effects may induce serious arrhythmias upon simultaneous administration. Intervention Isoproterenol hydrochloride injection and epinephrine should not be administered simultaneously.
Drugs that may potentiate clinical response of Isoproterenol Clinical Impact The effects of isoproterenol may be potentiated by tricyclic antidepressants, monoamine oxidase inhibitors, levothyroxine sodium, and certain antihistamines, notably chlorpheniramine, tripelennamine, and diphenhydramine. Intervention Monitor hemodynamic parameters in patients who concurrently are taking tricyclic antidepressants, monoamine oxidase inhibitors, levothyroxine sodium and certain antihistamines. Adjust doses appropriately.
Drugs that may reduce clinical response of Isoproterenol Clinical Impact The cardiostimulating and bronchodilating effects of isoproterenol are antagonized by beta-adrenergic blocking drugs, such as propranolol. Intervention Monitor for hemodynamic response and relief of bronchospasm and adjust dose appropriately. Do not administer Isoproterenol hydrochloride injection and epinephrine simultaneously due to combined effects may induce serious arrhythmias ( 7) ) Concomitant use of tricyclic antidepressants, monoamine oxidase inhibitors, levothyroxine sodium and certain antihistamines; hemodynamic parameters may potentiate a clinical response of isoproterenol ( 7 ) Beta-adrenergic blocking drugs may reduce cardiostimulating and bronchodilating effects of isoproterenol ( 7 ) See 17 for PATIENT COUNSELING INFORMATION.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Prolonged experience with isoproterenol use in pregnant women over several decades, based on published literature, do not identify a drug associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes. However, there are risks to the mother and fetus associated with isoproterenol use during labor or delivery (see Clinical Considerations). The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the United States general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Clinical Considerations Hypotension associated with shock is a medical emergency in pregnancy which can be fatal if left untreated.
Delaying treatment in pregnant women with hypotension associated with shock may increase the risk of maternal and fetal morbidity and mortality. Life-sustaining therapy for the pregnant woman should not be withheld due to potential concerns regarding the effects of isoproterenol on the fetus. Labor and Delivery Isoproterenol usually inhibits spontaneous or oxytocin induced contractions of the pregnant human uterus and may delay the second stage of labor.
Avoid isoproterenol during the second stage of labor. Avoid isoproterenol in obstetrics when maternal blood pressure exceeds 130/80 mmHg. Although isoproterenol may improve maternal hypotension associated with shock, it may result in uterine vasoconstriction, decreased uterine blood flow, uterine atony with hemorrhage, and fetal anoxia.
8.2Lactation Risk Summary There is no information regarding the presence of isoproterenol in milk or the effects of isoproterenol on the breastfed infant or on milk production. However, due to its short half-life, isoproterenol exposure is expected to be very low in the breastfed infant.
8.4Pediatric Use Safety and efficacy of isoproterenol in pediatric patients have not been established. Intravenous infusions of isoproterenol in refractory asthmatic children at rates of 0.05-2.7 µg/kg/min have caused clinical deterioration, myocardial necrosis, congestive heart failure and death. The risks of cardiac toxicity appear to be increased by some factors [acidosis, hypoxemia, coadministration of corticosteroids, coadministration of methylxanthines (theophylline, theobromine) or aminophylline] that are especially likely to be present in these patients.
If I.V. isoproterenol is used in children with refractory asthma, patient monitoring must include continuous assessment of vital signs, frequent electrocardiography, and daily measurements of cardiac enzymes, including CPK-MB.
8.5Geriatric Use Clinical studies of isoproterenol did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects in clinical circumstances. There are, however, some data that suggest that elderly healthy or hypertensive patients are less responsive to beta-adrenergic stimulation than are younger subjects. In general, dose selection for elderly patients should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal or cardiac function and of concomitant diseases or other drug therapy.
🆘 Overdosage ▾
10 OVERDOSAGE Overdosage of isoproterenol can cause tachycardia or other arrhythmias, palpitations, angina, hypotension, or hypertension. In case of overdosage, reduce the rate of administration or discontinue isoproterenol hydrochloride injection until patient's condition stabilizes. Monitor blood pressure, pulse, respiration, and EKG. It is not known whether isoproterenol hydrochloride is dialyzable.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Isoproterenol is a potent nonselective beta-adrenergic agonist with very low affinity for alpha-adrenergic receptors.
12.2Pharmacodynamics Intravenous infusion of isoproterenol in man lowers peripheral vascular resistance, primarily in skeletal muscle but also in renal and mesenteric vascular beds. Diastolic pressure falls. Renal blood flow is decreased in normotensive subjects but is increased markedly in shock.
Systolic blood pressure may remain unchanged or rise, although mean arterial pressure typically falls. Cardiac output is increased because of the positive inotropic and chronotropic effects of the drug in the face of diminished peripheral vascular resistance. Isoproterenol relaxes almost all varieties of smooth muscle when the tone is high, but this action is most pronounced on bronchial and gastrointestinal smooth muscle.
It prevents or relieves bronchoconstriction, but tolerance to this effect develops with overuse of the drug. In man, isoproterenol causes less hyperglycemia than does epinephrine. Isoproterenol and epinephrine are equally effective in stimulating the release of free fatty acids and energy production.
12.3Pharmacokinetics Absorption Isoproterenol is readily absorbed when given parenterally or as an aerosol. Elimination Isoproterenol is metabolized primarily in the liver and other tissues by COMT. Isoproterenol is a relatively poor substrate for MAO and is not taken up by sympathetic neurons to the same extent as are epinephrine and norepinephrine.
The duration of action of isoproterenol may therefore be longer than that of epinephrine but is still brief.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Isoproterenol Hydrochloride Injection, USP is a sterile, clear colorless to practically colorless solution. Each mL contains 0.2 mg of isoproterenol hydrochloride, USP. NDC Number Container Concentration Fill Quantity 69097-521-31 Single-dose ampul 0.2 mg/mL 1 mL 25 ampuls per carton 69097-522-35 Single-dose ampul 1 mg/5 mL (0.2 mg/mL) 5 mL 10 ampuls per carton Protect from light.
Keep in opaque container until used. Store at 20º to 25ºC (68º to 77ºF). [See USP Controlled Room Temperature.] Do not use if the injection is pinkish or darker than slightly yellow or contains a precipitate. Discard unused portion.
Manufactured by: Gland Pharma Limited, India. Manufactured for: Cipla USA, Inc. 10 Independence Boulevard, Suite 300 Warren, NJ 07059 Revised: 11/2023
📋 Description ▾
11 DESCRIPTION Isoproterenol hydrochloride is 3,4-Dihydroxy-α-[(isopropylamino)methyl] benzyl alcohol hydrochloride, a beta-adrenergic agonist and a synthetic sympathomimetic amine that is structurally related to epinephrine. The molecular formula is C 11 H 17 NO 3 ·HCl. It has a molecular weight of 247.72 and the following structural formula: Isoproterenol hydrochloride is a racemic compound.
Each milliliter of the sterile solution contains: Isoproterenol hydrochloride, USP 0.2 mg Edetate disodium USP (EDTA) 0.2 mg Sodium citrate, dihydrate USP 2.07 mg Citric acid, anhydrous USP 2.5 mg Sodium chloride USP 7.0 mg Hydrochloric acid NF q.s to adjust pH Sodium hydroxide NF q.s to adjust pH Water for Injection USP q.s to 1.0 mL The pH is adjusted between 2.5 and 4.5 with hydrochloric acid NF and/or sodium hydroxide NF. The sterile solution is nonpyrogenic and can be administered by the intravenous route. Image
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Long-term studies in animals to evaluate the carcinogenic potential of isoproterenol hydrochloride have not been done. Mutagenic potential and effect on fertility have not been determined. There is no evidence from human experience that isoproterenol hydrochloride injection may be carcinogenic or mutagenic or that it impairs fertility.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Long-term studies in animals to evaluate the carcinogenic potential of isoproterenol hydrochloride have not been done. Mutagenic potential and effect on fertility have not been determined. There is no evidence from human experience that isoproterenol hydrochloride injection may be carcinogenic or mutagenic or that it impairs fertility.
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL NDC 69097-522-35 Rx Only Isoproterenol Hydrochloride Injection, USP 1 mg/5 mL (0.2 mg/mL) Intravenous, Subcutaneous, Intramuscular or Intracardiac Use Only. 5 mL ampul x 10 ampuls per carton Cipla NDC 69097-521-31 Rx Only Isoproterenol Hydrochloride Injection, USP 0.2 mg/mL Intravenous, Subcutaneous, Intramuscular or Intracardiac Use Only. 5 mL ampul x 25 ampuls per carton Cipla carton-5ml carton-1ml
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |