
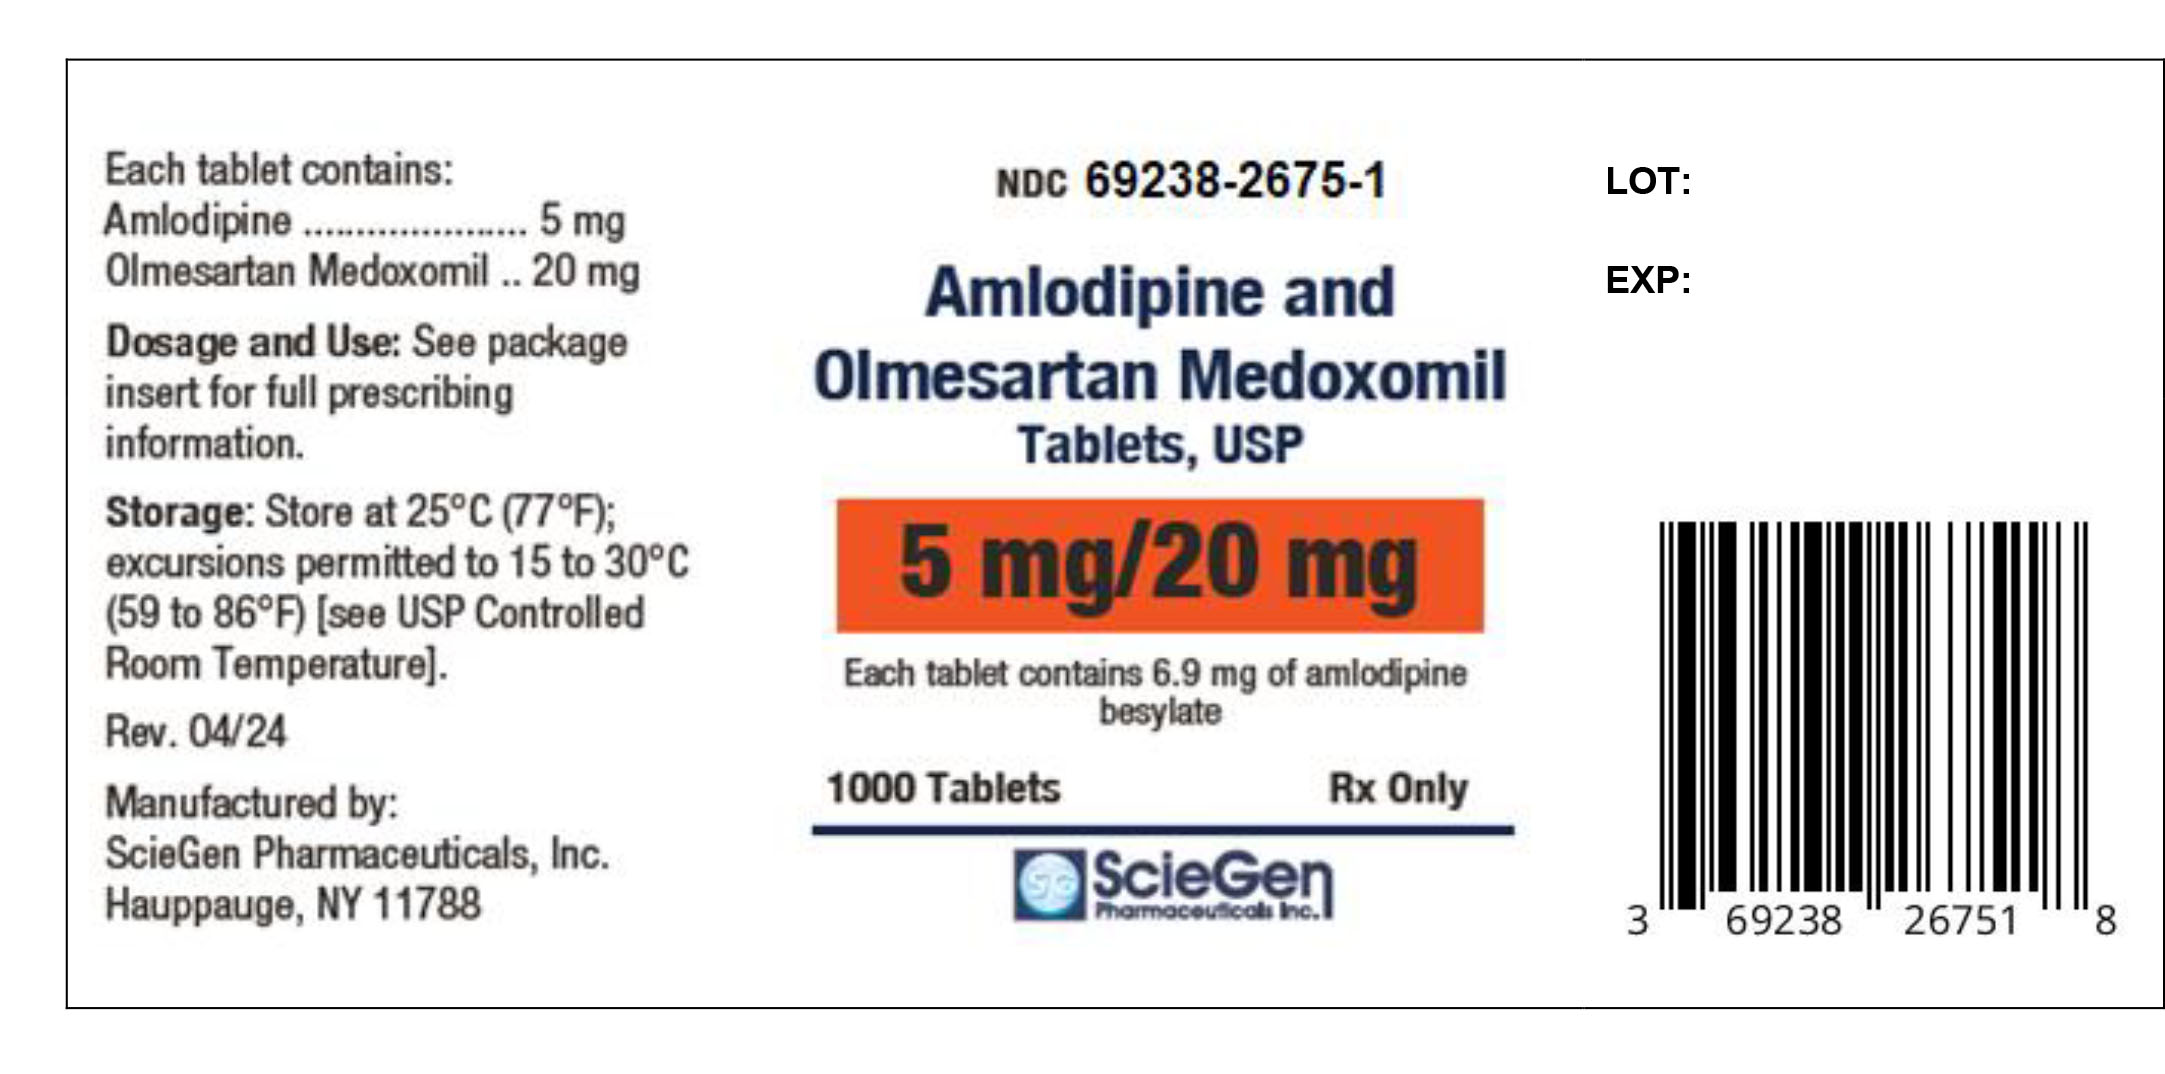
Amlodipine and Olmesartan Medoxomil 5 mg; 40 mg Tablet, Film Coated, 1,000-count
Other active recalls for Amlodipine And Olmesartan Medoxomil (different manufacturers) — 3 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Dihydropyridine Calcium Channel Blocker class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Amlodipine is used to treat high blood pressure and certain types of angina (chest pain) and coronary artery disease (narrowing of the blood vessels that supply blood to the heart). Amlodipine is in a class of medications called calcium channel blockers. It lowers blood pressure by relaxing the blood vessels so the heart does not have to pump as hard. It controls chest pain by increasing the supply of blood to the heart. If taken regularly, amlodipine controls chest pain, but it does not stop chest pain once it starts. Your doctor may prescribe a different medication to take when you have ches...
Read the full MedlinePlus article ↗Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII G2M7P15E5P
Polyethylene glycol 3350 is a synthetic polymer used as a solvent, humectant, and thickening agent in medicines. It helps dissolve other ingredients, retain moisture in the product, and achieve the desired consistency.
-
UNII Q662QK8M3B
Polyethylene glycol 8000 is a synthetic polymer made from ethylene oxide. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and add bulk to the medicine.
-
UNII 532B59J990
Polyvinyl alcohol is a synthetic polymer made from plant-derived materials. It's used as a binder to hold ingredients together, a film-former in coatings, and a thickener in liquid formulations.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
11 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.312 | $312.20 / 1000 tablets |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.4078 | $407.80 / 1000 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Amlodipine besylate and Olmesartan medoxomil 5 mg/1; 40 mg 27241-0084-03 | Ajanta | 30 tablets | $0.312 | AB | Availability likely | — |
| Amlodipine and Olmesartan Medoxomil 5 mg/1; 40 mg 31722-0446-30 | Camber | 30 tablets | $0.312 | AB | Availability likely | — |
| AMLODIPINE and OLMESARTAN medoxomil 5 mg/1; 40 mg 33342-0191-07 | Macleods | 30 tablets | $0.312 | AB | Availability likely | — |
| Amlodipine besylate and Olmesartran medoxomil 5 mg/1; 40 mg 62332-0213-30 | Alembic | 30 tablets | $0.312 | AB | Availability likely | — |
| Amlodipine and Olmesartan Medoxomil 5 mg/1; 40 mg 65862-0855-30 | Aurobindo | 30 tablets | $0.312 | AB | Availability likely | — |
| Amlodipine and olmesartan Medoxomil 5 mg/1; 40 mg 67877-0501-30 | Ascend | 30 tablets | $0.312 | AB | Availability likely | — |
| Amlodipine and Olmesartan Medoxomil 5 mg/1; 40 mgthis 69238-2676-01 | Amneal | 1000 tablets | $0.312 | AB | Availability likely | — |
| Azor 5 mg/1; 40 mg 00713-0872-30 | Cosette | 30 tablets | $19.635 | AB | Availability likely | +6189% |
| Amlodipine and Olmesartan Medoxomil 5 mg/1; 40 mg 42291-0002-30 | AvKARE | 30 tablets | — | AB | FDA listed | — |
| Amlodipine And Olmesartan Medoxomil 5 mg/1; 40 mg 42571-0237-05 | Micro | 500 tablets | — | AB | FDA listed | — |
| Amlodipine besylate and Olmesartran medoxomil 5 mg/1; 40 mg 46708-0213-30 | Alembic | 30 tablets | — | AB | FDA listed | — |
| Amlodipine and Olmesartan Medoxomil 5 mg/1; 40 mg 50228-0366-10 | ScieGen | 1000 tablets | — | AB | FDA listed | — |
| amlodipine besylate and olmesartan medoxomil 5 mg/1; 40 mg 51407-0859-30 | Golden | 30 tablets | — | AB | FDA listed | — |
| Amlodipine and Olmesartan Medoxomil 5 mg/1; 40 mg 68462-0568-14 | Glenmark | 10 tablets | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 69238-2676-01 You're viewing this | 1000 TABLET, FILM COATED in 1 BOTTLE (69238-2676-1) | 2018-12-03 | Active |
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: FETAL TOXICITY When pregnancy is detected, discontinue amlodipine and olmesartan medoxomil tablets as soon as possible ( 5.1 , 8.1 ). Drugs that act directly on the renin-angiotensin system (RAS) can cause injury and death to the developing fetus ( 5.1 , 8.1 ). WARNING: FETAL TOXICITY See full prescribing information for complete boxed warning.
When pregnancy is detected, discontinue amlodipine and olmesartan medoxomil tablets as soon as possible ( 5.1 , 8.1 ). Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus ( 5.1 , 8.1 ).
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Amlodipine and olmesartan medoxomil tablets are indicated for the treatment of hypertension, alone or with other antihypertensive agents, to lower blood pressure. Lowering blood pressure reduces the risk of fatal and nonfatal cardiovascular (CV) events, primarily strokes and myocardial infarctions. These benefits have been seen in controlled trials of antihypertensive drugs from a wide variety of pharmacologic classes including the class to which this drug principally belongs.
There are no controlled trials demonstrating risk reduction with amlodipine and olmesartan medoxomil tablets. Control of high blood pressure should be part of comprehensive cardiovascular risk management, including, as appropriate, lipid control, diabetes management, antithrombotic therapy, smoking cessation, exercise, and limited sodium intake. Many patients will require more than one drug to achieve blood pressure goals.
For specific advice on goals and management, see published guidelines, such as those of the National High Blood Pressure Education Program’s Joint National Committee on Prevention, Detection, Evaluation, and Treatment of High Blood Pressure (JNC). Numerous antihypertensive drugs, from a variety of pharmacologic classes and with different mechanisms of action, have been shown in randomized controlled trials to reduce cardiovascular morbidity and mortality, and it can be concluded that it is blood pressure reduction, and not some other pharmacologic property of the drugs, that is largely responsible for those benefits.
The largest and most consistent cardiovascular outcome benefit has been a reduction in the risk of stroke, but reductions in myocardial infarction and cardiovascular mortality also have been seen regularly. Elevated systolic or diastolic pressure causes increased cardiovascular risk, and the absolute risk increase per mmHg is greater at higher blood pressures, so that even modest reductions of severe hypertension can provide substantial benefit. Relative risk reduction from blood pressure reduction is similar across populations with varying absolute risk, so the absolute benefit is greater in patients who are at higher risk independent of their hypertension (for example, patients with diabetes or hyperlipidemia), and such patients would be expected to benefit from more aggressive treatment to a lower blood pressure goal.
Some antihypertensive drugs have smaller blood pressure effects (as monotherapy) in black patients, and many antihypertensive drugs have additional approved indications and effects (e.g., on angina, heart failure, or diabetic kidney disease). These considerations may guide selection of therapy. Amlodipine and olmesartan medoxomil tablets may also be used as initial therapy in patients who are likely to need multiple antihypertensive agents to achieve their blood pressure goals.
Patients with moderate or severe hypertension are at relatively high risk for cardiovascular events (such as strokes, heart attacks, and heart failure), kidney failure, and vision problems, so prompt treatment is clinically relevant. The decision to use a combination as initial therapy should be individualized and should be shaped by considerations such as baseline blood pressure, the target goal, and the incremental likelihood of achieving goal with a combination compared to monotherapy. Individual blood pressure goals may vary based upon the patient’s risk.
Data from an 8-week, placebo-controlled, parallel-group factorial study [ see Clinical Studies (14.1) ] provide estimates of the probability of reaching a blood pressure goal with amlodipine and olmesartan medoxomil tablets compared to amlodipine or olmesartan medoxomil monotherapy. The figures below provide estimates of the likelihood of achieving the targeted systolic or diastolic blood pressure goals with amlodipine and olmesartan medoxomil tablets 10/40 mg compared with amlodipine or olmesartan medoxomil monotherapy, based upon baseline systolic or d…
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION The usual starting dose of amlodipine and olmesartan medoxomil tablets is 5/20 mg once daily. The dosage can be increased after 1 to 2 weeks of therapy to a maximum dose of one 10/40 mg tablet once daily as needed to control blood pressure [ see Clinical Studies (14.1) ]. Recommended starting dose: 5/20 mg once daily ( 2 ). Titrate as needed in two-week intervals up to a maximum of 10/40 mg once daily ( 2 ).
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Amlodipine and olmesartan medoxomil tablets, USP are formulated for oral administration in the following strength combinations: 5/20 5/40 10/20 10/40 Amlodipine equivalent (mg) 5 5 10 10 Olmesartan medoxomil (mg) 20 40 20 40 Tablets: (amlodipine/olmesartan medoxomil content) 5/20 mg; 10/20 mg; 5/40 mg; and 10/40 mg (3) .
⛔ Contraindications ▾
4 CONTRAINDICATIONS Do not co-administer aliskiren with amlodipine and olmesartan medoxomil tablets in patients with diabetes [ See Drug Interactions (7.2) ]. Do not co-administer aliskiren with amlodipine and olmesartan medoxomil tablets in patients with diabetes (4) .
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Anticipate hypotension in volume-or salt-depleted patients with treatment initiation. Start treatment under close supervision ( 5.2 ). Increased angina or myocardial infarction may occur upon dosage initiation or increase ( 5.3 ).
Impaired renal function: changes in renal function may occur ( 5.4 ). Sprue-like enteropathy has been reported. Consider discontinuation of amlodipine and olmesartan medoxomil tablets in cases where no other etiology is found ( 5.6 ).
5.1Fetal Toxicity Amlodipine and olmesartan medoxomil tablets can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Resulting oligohydramnios can be associated with fetal lung hypoplasia and skeletal deformations.
Potential neonatal adverse effects include skull hypoplasia, anuria, hypotension, renal failure, and death. When pregnancy is detected, discontinue amlodipine and olmesartan medoxomil tablets as soon as possible [see Use in Specific Populations (8.1) ] .
5.2Hypotension in Volume- or Salt-Depleted Patients Olmesartan medoxomil. In patients with an activated renin-angiotensin system, such as volume- and/or salt-depleted patients (e.g., those being treated with high doses of diuretics) symptomatic hypotension may be anticipated after initiation of treatment with olmesartan medoxomil. Initiate treatment with amlodipine and olmesartan medoxomil tablets under close medical supervision.
If hypotension does occur, place the patient in the supine position and, if necessary, give an intravenous infusion of normal saline. A transient hypotensive response is not a contraindication to further treatment, which usually can be continued without difficulty once the blood pressure has stabilized. Amlodipine.
Symptomatic hypotension is possible, particularly in patients with severe aortic stenosis.Because of the gradual onset of action, acute hypotension is unlikely.
5.3Increased Angina or Myocardial Infarction Patients, particularly those with severe obstructive coronary artery disease, may develop increased frequency, duration, or severity of angina or acute myocardial infarction on starting calcium channel blocker therapy or at the time of dosage increase. The mechanism of this effect has not been elucidated.
5.4Impaired Renal Function Changes in renal function may be anticipated in susceptible individuals treated with olmesartan medoxomil as a consequence of inhibiting the renin-angiotensin-aldosterone system. In patients whose renal function may depend upon the activity of the renin-angiotensin-aldosterone system (e.g., patients with severe congestive heart failure), treatment with angiotensin converting enzyme inhibitors and angiotensin receptor antagonists has been associated with oliguria or progressive azotemia and (rarely) with acute renal failure and/or death.
Similar effects may occur in patients treated with amlodipine and olmesartan medoxomil tablets because of the olmesartan medoxomil component[ see Drug Interactions (7) and Clinical Pharmacology (12.3) ]. In studies of ACE inhibitors in patients with unilateral or bilateral renal artery stenosis, increases in serum creatinine or blood urea nitrogen (BUN) have been reported. There has been no long-term use of olmesartan medoxomil in patients with unilateral or bilateral renal artery stenosis, but similar effects would be expected with olmesartan medoxomil and amlodipine and olmesartan medoxomil tablets.
5.5Patients with Hepatic Impairment Patients with hepatic impairment have decreased clearance of amlodipine. Starting amlodipine or adding amlodipine at 2.5 mg in hepatically impaired patients is recommended. The lowest dose of amlodipine and olmesartan medoxomil tablets is 5/20 mg; therefore, initial therapy with amlodipine and olmesartan medoxomil tablets is not recommended in hepatically i…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Most common adverse reaction (incidence ≥ 3%) is edema (6.1) . To report SUSPECTED ADVERSE REACTIONS, contact ScieGen Pharmaceuticals Inc. at 1-855-724-3436 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical studies are conducted under widely varying conditions, adverse reaction rates observed in the clinical studies of a drug cannot be directly compared to rates in the clinical studies of another drug and may not reflect the rates observed in practice. Amlodipine and olmesartan medoxomil tablets The data described below reflect exposure to amlodipine and olmesartan medoxomil tablets in more than 1600 patients including more than 1,000 exposed for at least 6 months and more than 700 exposed for 1 year.
Amlodipine and olmesartan medoxomil tablets were studied in one placebo-controlled factorial trial [ see Clinical Trials (14.1) ]. The population had a mean age of 54 years and included approximately 55% males. Seventy-one percent were Caucasian and 25% were Black.
Patients received doses ranging from 5/20 mg to 10/40 mg orally once daily. The overall incidence of adverse reactions on therapy with amlodipine and olmesartan medoxomil tablets were similar to that seen with corresponding doses of the individual components of amlodipine and olmesartan medoxomil tablets, and to placebo. The reported adverse reactions were generally mild and seldom led to discontinuation of treatment (2.6% for amlodipine and olmesartan medoxomil tablets and 6.8% for placebo).
Edema Edema is a known, dose-dependent adverse effect of amlodipine but not of olmesartan medoxomil. The placebo-subtracted incidence of edema during the 8-week, randomized, double-blind treatment period was highest with amlodipine 10 mg monotherapy. The incidence was significantly reduced when 20 mg or 40 mg of olmesartan medoxomil was added to the 10 mg amlodipine dose.
Placebo-Subtracted Incidence of Edema During the Double-Blind Treatment Period *12.3% = actual placebo incidence Olmesartan Medoxomil Placebo 20 mg 40 mg Amlodipine Placebo - * -2.4% 6.2% 5 mg 0.7% 5.7% 6.2% 10 mg 24.5% 13.3% 11.2% Across all treatment groups, the frequency of edema was generally higher in women than men, as has been observed in previous studies of amlodipine. There was a greater decrease in hemoglobin and hematocrit in patients treated with amlodipine and olmesartan medoxomil tablets as compared to patients receiving either component.
Adverse reactions seen at lower rates during the double-blind period also occurred in the patients treated with amlodipine and olmesartan medoxomil tablets at about the same or greater incidence as in patients receiving placebo. These included hypotension, orthostatic hypotension, rash, pruritus, palpitation, urinary frequency, and nocturia. The adverse event profile obtained from 44 weeks of open-label combination therapy with amlodipine plus olmesartan medoxomil was similar to that observed during the 8-week, double-blind, placebo-controlled period.
Initial Therapy Analyzing the data described above specifically for initial therapy, it was observed that higher doses of amlodipine and olmesartan medoxomil tablets caused slightly more hypotension and orthostatic symptoms, but not at the recommended starting dose of amlodipine and olmesartan medoxomil tablets 5/20 mg. No increase in the incidence of syncope or near syncope was observed. The incidences of discontinuation because of any treatment emergent adverse events in the double-blind phase are summarized in the table below.
Discontinuation for any Treatment Emergent Adverse Event 1 1 Hypertension is counted as treatment failure and not as treatment emergent adverse event. N=160-163 subjects per treatment group. Olmesartan Medoxomil Placebo 10 mg 20 mg 40 mg Amlodipine Placebo 4.9% 4.3% 5.6% 3.1% 5 mg 3.7% 0.0% 1.2% 3.7% 10 mg 5.5% 6.8% 2.5% 5.6% Amlodipine.
Amlodipine has been evaluated for safety in more than 11,000 patients in U.S. and foreign…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Amlodipine ( 7.1 ): If simvastatin is co-administered with amlodipine, do not exceed 20 mg daily of simvastatin. Increased exposure of cyclosporine and tacrolimus. Increased exposure of amlodipine when coadministered with CYP3A inhibitors.
Olmesartan medoxomil ( 7.2 ): Nonsteroidal anti-inflammatory drugs (NSAIDS) may lead to increased risk of renal impairment and loss of antihypertensive effect. Dual inhibition of the renin-angiotensin system: Increased risk of renal impairment, hypotension, and hyperkalemia. Colesevelam hydrochloride: Consider administering olmesartan at least 4 hours before colesevelam hydrochloride dose.
Lithium: Increases in serum lithium concentrations and lithium toxicity.
7.1Drug Interactions with Amlodipine Simvastatin: Co-administration of simvastatin with amlodipine increases the systemic exposure of simvastatin. Limit the dose of simvastatin in patients on amlodipine to 20 mg daily [see Clinical Pharmacology (12.3) ]. Immunosuppressants: Amlodipine may increase the systemic exposure of cyclosporine or tacrolimus when co-administered.
Frequent monitoring of trough blood levels of cyclosporine and tacrolimus is recommended and adjust the dose when appropriate [see Clinical Pharmacology (12.3) ]. CYP3A Inhibitors : Co-administration of amlodipine with CYP3A inhibitors (moderate and strong) results in increased systemic exposure to amlodipine and may require dose reduction. Monitor for symptoms of hypotension and edema when amlodipine is co-administered with CYP3A inhibitors to determine the need for dose adjustment.
CYP3A Inducers: No information is available on the quantitative effects of CYP3A inducers on amlodipine. Blood pressure should be closely monitored when amlodipine is co-administered with CYP3A inducers.
7.2Drug Interactions with Olmesartan Medoxomil Non-Steroidal Anti-Inflammatory Agents including Selective Cyclooxygenase-2 Inhibitors (COX-2 Inhibitors): In patients who are elderly, volume-depleted (including those on diuretic therapy), or with compromised renal function, co-administration of NSAIDs, including selective COX-2 inhibitors, with angiotensin II receptor antagonists, including olmesartan medoxomil, may result in deterioration of renal function, including possible acute renal failure. These effects are usually reversible.
Monitor renal function periodically in patients receiving olmesartan medoxomil and NSAID therapy. The antihypertensive effect of angiotensin II receptor antagonists, including olmesartan medoxomil may be attenuated by NSAIDs including selective COX-2 inhibitors. Dual Blockade of the Renin-Angiotensin System (RAS): Dual blockade of the RAS with angiotensin receptor blockers, ACE inhibitors, or aliskiren is associated with increased risks of hypotension, hyperkalemia, and changes in renal function (including acute renal failure) compared to monotherapy.
Most patients receiving the combination of two RAS inhibitors do not obtain any additional benefit compared to monotherapy. In general, avoid combined use of RAS inhibitors. Closely monitor blood pressure, renal function and electrolytes in patients on amlodipine and olmesartan medoxomil tablets and other agents that affect the RAS.
Do not co-administer aliskiren with amlodipine and olmesartan medoxomil tablets in patients with diabetes [ see Contraindications (4) ]. Avoid use of aliskiren with amlodipine and olmesartan medoxomil tablets in patients with renal impairment (GFR <60 ml/min). Use with Colesevelam Hydrochloride: Concurrent administration of bile acid sequestering agent colesevelam hydrochloride reduces the systemic exposure and peak plasma concentration of olmesartan.
Administration of olmesartan at least 4 hours prior to colesevelam hydrochloride decreased the drug interaction effect. Consider administering olmesartan at least 4 hours before the colesevelam hydrochloride dose [see Clinical Pharmacology (12.3) ] . Lithium: Increases in serum lithium concentrations and lithium tox…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Breastfeeding is not recommended ( 8.2 ). Geriatric: Not recommended for initial therapy in patients ≥75 years old ( 8.5 ) Hepatic Impairment: Not recommended for initial therapy ( 8.6 )
8.1Pregnancy Risk Summary Amlodipine and olmesartan medoxomil tablets can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death [see Clinical Considerations] . Most epidemiologic studies examining fetal abnormalities after exposure to antihypertensive use in the first trimester have not distinguished drugs affecting the renin-angiotensin system from other antihypertensive agents.
When pregnancy is detected, discontinue amlodipine and olmesartan medoxomil tablets as soon as possible. Consider alternative antihypertensive therapy during pregnancy. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk Hypertension in pregnancy increases the maternal risk for pre-eclampsia, gestational diabetes, premature delivery, and delivery complications (e.g., need for cesarean section and post-partum hemorrhage).
Hypertension increases the fetal risk for intrauterine growth restriction and intrauterine death. Pregnant women with hypertension should be carefully monitored and managed accordingly. Fetal/Neonatal Adverse Reactions Olmesartan medoxomil Oligohydramnios in pregnant women who use drugs affecting the renin-angiotensin system in the second and third trimesters of pregnancy can result in the following: reduced fetal renal function leading to anuria and renal failure, fetal lung hypoplasia, skeletal deformations, including skull hypoplasia, hypotension, and death.
Perform serial ultrasound examinations to assess the intra-amniotic environment. Fetal testing may be appropriate, based on the week of gestation. Patients and physicians should be aware, however, that oligohydramnios may not appear until after the fetus has sustained irreversible injury.
Closely observe infants with histories of in utero exposure to olmesartan for hypotension, oliguria, and hyperkalemia. In neonates with a history of in utero exposure to olmesartan, if oliguria or hypotension occur, utilize measures to maintain adequate blood pressure and renal perfusion. Exchange transfusions or dialysis may be required as a means of reversing hypotension and supporting renal function [see Use in Specific Populations (8.4) ] .
Data Animal Data No reproductive studies have been conducted with the combination of olmesartan medoxomil, and amlodipine. However, these studies have been conducted for olmesartan medoxomil and amlodipine alone. Olmesartan medoxomil No teratogenic effects were observed when olmesartan medoxomil was administered to pregnant rats at oral doses up to 1000 mg/kg/day (240 times the maximum recommended human dose [MRHD] on a mg/m 2 basis) or pregnant rabbits at oral doses up to 1 mg/kg/day (half the MRHD on a mg/m 2 basis; higher doses could not be evaluated for effects on fetal development as they were lethal to the does).
In rats, significant decreases in pup birth weight and weight gain were observed at doses ≥ 1.6 mg/kg/day, and delays in developmental milestones (delayed separation of ear auricular, eruption of lower incisors, appearance of abdominal hair, descent of testes, and separation of eyelids) and dose-dependent increases in the incidence of dilation of the renal pelvis were observed at doses ≥ 8 mg/kg/day. The no observed effect dose for…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Amlodipine and olmesartan medoxomil tablets can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death [see Clinical Considerations] . Most epidemiologic studies examining fetal abnormalities after exposure to antihypertensive use in the first trimester have not distinguished drugs affecting the renin-angiotensin system from other antihypertensive agents.
When pregnancy is detected, discontinue amlodipine and olmesartan medoxomil tablets as soon as possible. Consider alternative antihypertensive therapy during pregnancy. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk Hypertension in pregnancy increases the maternal risk for pre-eclampsia, gestational diabetes, premature delivery, and delivery complications (e.g., need for cesarean section and post-partum hemorrhage).
Hypertension increases the fetal risk for intrauterine growth restriction and intrauterine death. Pregnant women with hypertension should be carefully monitored and managed accordingly. Fetal/Neonatal Adverse Reactions Olmesartan medoxomil Oligohydramnios in pregnant women who use drugs affecting the renin-angiotensin system in the second and third trimesters of pregnancy can result in the following: reduced fetal renal function leading to anuria and renal failure, fetal lung hypoplasia, skeletal deformations, including skull hypoplasia, hypotension, and death.
Perform serial ultrasound examinations to assess the intra-amniotic environment. Fetal testing may be appropriate, based on the week of gestation. Patients and physicians should be aware, however, that oligohydramnios may not appear until after the fetus has sustained irreversible injury.
Closely observe infants with histories of in utero exposure to olmesartan for hypotension, oliguria, and hyperkalemia. In neonates with a history of in utero exposure to olmesartan, if oliguria or hypotension occur, utilize measures to maintain adequate blood pressure and renal perfusion. Exchange transfusions or dialysis may be required as a means of reversing hypotension and supporting renal function [see Use in Specific Populations (8.4) ] .
Data Animal Data No reproductive studies have been conducted with the combination of olmesartan medoxomil, and amlodipine. However, these studies have been conducted for olmesartan medoxomil and amlodipine alone. Olmesartan medoxomil No teratogenic effects were observed when olmesartan medoxomil was administered to pregnant rats at oral doses up to 1000 mg/kg/day (240 times the maximum recommended human dose [MRHD] on a mg/m 2 basis) or pregnant rabbits at oral doses up to 1 mg/kg/day (half the MRHD on a mg/m 2 basis; higher doses could not be evaluated for effects on fetal development as they were lethal to the does).
In rats, significant decreases in pup birth weight and weight gain were observed at doses ≥ 1.6 mg/kg/day, and delays in developmental milestones (delayed separation of ear auricular, eruption of lower incisors, appearance of abdominal hair, descent of testes, and separation of eyelids) and dose-dependent increases in the incidence of dilation of the renal pelvis were observed at doses ≥ 8 mg/kg/day. The no observed effect dose for developmental toxicity in rats is 0.3 mg/kg/day, about one-tenth the MRHD of 40 mg/day.
Amlodipine No evidence of teratogenicity or other embryo/fetal toxicity was found when pregnant rats and rabbits were treated orally with am…
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of amlodipine and olmesartan medoxomil tablets in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the total number of subjects in the double-blind clinical study of amlodipine and olmesartan medoxomil tablets, 20% (384/1940) were 65 years of age or older and 3% (62/1940) were 75 years or older. No overall differences in safety or effectiveness were observed between subjects 65 years of age or older and younger subjects. Elderly patients have decreased clearance of amlodipine.
Starting amlodipine or adding amlodipine at 2.5 mg in patients ≥ 75 years old is recommended. The lowest dose of amlodipine and olmesartan medoxomil tablets is 5/20 mg; therefore, initial therapy with amlodipine and olmesartan medoxomil tablets is not recommended in patients ≥ 75 years old. Amlodipine.
Reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy. Elderly patients have decreased clearance of amlodipine with a resulting increase of AUC of approximately 40% to 60%, and a lower initial dose may be required.
Olmesartan medoxomil. Of the total number of hypertensive patients receiving olmesartan medoxomil in clinical studies, more than 20% were 65 years of age and over, while more than 5% were 75 years of age and older. No overall differences in effectiveness or safety were observed between elderly patients and younger patients.
Other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out.
🆘 Overdosage ▾
10 OVERDOSAGE There is no information on overdosage with amlodipine and olmesartan medoxomil tablets in humans. Amlodipine. Single oral doses of amlodipine maleate equivalent to 40 mg amlodipine/kg and 100 mg amlodipine/kg in mice and rats, respectively, caused deaths.
Single oral amlodipine maleate doses equivalent to 4 or more mg amlodipine/kg or higher in dogs (11 or more times the maximum recommended human dose on a mg/m 2 basis) caused a marked peripheral vasodilation and hypotension. Overdosage might be expected to cause excessive peripheral vasodilation with marked hypotension and possibly a reflex tachycardia. In humans, experience with intentional overdosage of amlodipine is limited.
If massive overdose should occur, active cardiac and respiratory monitoring should be instituted. Frequent blood pressure measurements are essential. Should hypotension occur, cardiovascular support including elevation of the extremities and the judicious administration of fluids should be initiated.
If hypotension remains unresponsive to these conservative measures, administration of vasopressors (such as phenylephrine) should be considered with attention to circulating volume and urine output. Intravenous calcium gluconate may help to reverse the effects of calcium entry blockade. As amlodipine is highly protein bound, hemodialysis is not likely to be of benefit.
Olmesartan medoxomil. Limited data are available related to overdosage in humans. The most likely manifestations of overdosage would be hypotension and tachycardia; bradycardia could be encountered if parasympathetic (vagal) stimulation occurs.
If symptomatic hypotension should occur, supportive treatment should be initiated. The dialyzability of olmesartan is unknown.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Amlodipine and olmesartan medoxomil tablets: Amlodipine and olmesartan medoxomil tablets are a combination of two antihypertensive drugs: a dihydropyridine calcium antagonist (calcium ion antagonist or slow-channel blocker), amlodipine besylate, and an angiotensin II receptor blocker, olmesartan medoxomil. The amlodipine component of amlodipine and olmesartan medoxomil tablets inhibits the transmembrane influx of calcium ions into vascular smooth muscle and cardiac muscle, and the olmesartan medoxomil component of amlodipine and olmesartan medoxomil tablets blocks the vasoconstrictor effects of angiotensin II.
Amlodipine. Experimental data suggests that amlodipine binds to both dihydropyridine and nonhydropyridine binding sites. The contractile processes of cardiac muscle and vascular smooth muscle are dependent upon the movement of extracellular calcium ions into these cells through specific ion channels.
Amlodipine inhibits calcium ion influx across cell membranes selectively, with a greater effect on vascular smooth muscle cells than on cardiac muscle cells. Negative inotropic effects can be detected in vitro but such effects have not been seen in intact animals at therapeutic doses. Serum calcium concentration is not affected by amlodipine.
Within the physiologic pH range, amlodipine is an ionized compound (pKa=8.6), and its kinetic interaction with the calcium channel receptor is characterized by a gradual rate of association and dissociation with the receptor binding site, resulting in a gradual onset of effect. Amlodipine is a peripheral arterial vasodilator that acts directly on vascular smooth muscle to cause a reduction in peripheral vascular resistance and reduction in blood pressure. Olmesartan medoxomil.
Angiotensin II is formed from angiotensin I in a reaction catalyzed by angiotensin converting enzyme (ACE, kininase II). Angiotensin II is the principal pressor agent of the renin-angiotensin system, with effects that include vasoconstriction, stimulation of synthesis and release of aldosterone, cardiac stimulation and renal reabsorption of sodium. Olmesartan blocks the vasoconstrictor effects of angiotensin II by selectively blocking the binding of angiotensin II to the AT 1 receptor in vascular smooth muscle.
Its action is, therefore, independent of the pathways for angiotensin II synthesis. An AT 2 receptor is found also in many tissues, but this receptor is not known to be associated with cardiovascular homeostasis. Olmesartan has more than a 12,500-fold greater affinity for the AT 1 receptor than for the AT 2 receptor.
Blockade of the renin-angiotensin system with ACE inhibitors, which inhibit the biosynthesis of angiotensin II from angiotensin I, is a mechanism of many drugs used to treat hypertension. ACE inhibitors also inhibit the degradation of bradykinin, a reaction also catalyzed by ACE. Because olmesartan does not inhibit ACE (kininase II), it does not affect the response to bradykinin.
Whether this difference has clinical relevance is not yet known. Blockade of the angiotensin II receptor inhibits the negative regulatory feedback of angiotensin II on renin secretion, but the resulting increased plasma renin activity and circulating angiotensin II levels do not overcome the effect of olmesartan on blood pressure.
12.2Pharmacodynamics Amlodipine. Following administration of therapeutic doses to patients with hypertension, amlodipine produces vasodilation resulting in a reduction of supine and standing blood pressures. These decreases in blood pressure are not accompanied by a significant change in heart rate or plasma catecholamine levels with chronic dosing.
With chronic once daily oral administration, antihypertensive effectiveness is maintained for at least 24 hours. Plasma concentrations correlate with effect in both young and elderly patients. The magnitude of reduction in blood pressure with amlodipine is also correlated with the height of pretre…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Amlodipine and olmesartan medoxomil tablets: Amlodipine and olmesartan medoxomil tablets are a combination of two antihypertensive drugs: a dihydropyridine calcium antagonist (calcium ion antagonist or slow-channel blocker), amlodipine besylate, and an angiotensin II receptor blocker, olmesartan medoxomil. The amlodipine component of amlodipine and olmesartan medoxomil tablets inhibits the transmembrane influx of calcium ions into vascular smooth muscle and cardiac muscle, and the olmesartan medoxomil component of amlodipine and olmesartan medoxomil tablets blocks the vasoconstrictor effects of angiotensin II.
Amlodipine. Experimental data suggests that amlodipine binds to both dihydropyridine and nonhydropyridine binding sites. The contractile processes of cardiac muscle and vascular smooth muscle are dependent upon the movement of extracellular calcium ions into these cells through specific ion channels.
Amlodipine inhibits calcium ion influx across cell membranes selectively, with a greater effect on vascular smooth muscle cells than on cardiac muscle cells. Negative inotropic effects can be detected in vitro but such effects have not been seen in intact animals at therapeutic doses. Serum calcium concentration is not affected by amlodipine.
Within the physiologic pH range, amlodipine is an ionized compound (pKa=8.6), and its kinetic interaction with the calcium channel receptor is characterized by a gradual rate of association and dissociation with the receptor binding site, resulting in a gradual onset of effect. Amlodipine is a peripheral arterial vasodilator that acts directly on vascular smooth muscle to cause a reduction in peripheral vascular resistance and reduction in blood pressure. Olmesartan medoxomil.
Angiotensin II is formed from angiotensin I in a reaction catalyzed by angiotensin converting enzyme (ACE, kininase II). Angiotensin II is the principal pressor agent of the renin-angiotensin system, with effects that include vasoconstriction, stimulation of synthesis and release of aldosterone, cardiac stimulation and renal reabsorption of sodium. Olmesartan blocks the vasoconstrictor effects of angiotensin II by selectively blocking the binding of angiotensin II to the AT 1 receptor in vascular smooth muscle.
Its action is, therefore, independent of the pathways for angiotensin II synthesis. An AT 2 receptor is found also in many tissues, but this receptor is not known to be associated with cardiovascular homeostasis. Olmesartan has more than a 12,500-fold greater affinity for the AT 1 receptor than for the AT 2 receptor.
Blockade of the renin-angiotensin system with ACE inhibitors, which inhibit the biosynthesis of angiotensin II from angiotensin I, is a mechanism of many drugs used to treat hypertension. ACE inhibitors also inhibit the degradation of bradykinin, a reaction also catalyzed by ACE. Because olmesartan does not inhibit ACE (kininase II), it does not affect the response to bradykinin.
Whether this difference has clinical relevance is not yet known. Blockade of the angiotensin II receptor inhibits the negative regulatory feedback of angiotensin II on renin secretion, but the resulting increased plasma renin activity and circulating angiotensin II levels do not overcome the effect of olmesartan on blood pressure.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Amlodipine and olmesartan medoxomil tablets, USP contain amlodipine besylate, USP at a dose equivalent to 5 or 10 mg amlodipine and olmesartan medoxomil, USP in the strengths described below. Amlodipine and olmesartan medoxomil tablets, USP are differentiated by tablet color/size and are debossed with an individual product tablet code on one side. Amlodipine and olmesartan medoxomil tablets, USP are supplied for oral administration in the following strength and package configurations: Tablet Strength (amlodipine equivalent/ olmesartan medoxomil) mg Package Configuration NDC# Product Code Tablet Color 5/20 mg Bottle of 1000 69238-2675-1 SG 365 White 10/20 mg Bottle of 1000 69238-2673-1 SG 367 Light Orange 5/40 mg Bottle of 1000 69238-2676-1 SG 366 Cream 10/40 mg Bottle of 1000 69238-2674-1 SG 368 Brownish Red Store at 25ºC (77ºF); excursions permitted to 15°C to 30ºC (59°F to 86ºF) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Amlodipine and olmesartan medoxomil provided as a tablet for oral administration, is a combination of the calcium channel blocker (CCB) amlodipine besylate, USP and the angiotensin II receptor blocker (ARB) olmesartan medoxomil, USP. The amlodipine besylate, USP component of amlodipine and olmesartan medoxomil tablets, USP is chemically described as 3-ethyl-5-methyl (±)-2-[(2-aminoethoxy)methyl]-4-(2-chlorophenyl)-1,4-dihydro-6-methyl-3,5-pyridinedicarboxylate,monobenzenesulphonate. Its empirical formula is C 20 H 25 ClN 2 O 5 •C 6 H 6 O 3 S.
Olmesartan medoxomil, USP a prodrug, is hydrolyzed to olmesartan during absorption from the gastrointestinal tract. The olmesartan medoxomil, USP component of amlodipine and olmesartan medoxomil tablets, USP is chemically described as 2,3-dihydroxy-2-butenyl 4-(1-hydroxy-1-methylethyl)-2-propyl-1-[ p -(o-1 H -tetrazol-5-ylphenyl)benzyl]imidazole-5-carboxylate, cyclic 2,3-carbonate. Its empirical formula is C 29 H 30 N 6 O 6 .
The structural formula for amlodipine besylate, USP is: The structural formula for olmesartan medoxomil, USP is: Amlodipine and olmesartan medoxomil tablets, USP contain amlodipine besylate, USP a white or almost white powder, and olmesartan medoxomil, USP a white to off-white crystalline powder. The molecular weights of amlodipine besylate, USP and olmesartan medoxomil, USP are 567.1 and 558.59, respectively. Amlodipine besylate, USP is slightly soluble in 2-propanol, water, freely soluble in methanol and sparingly soluble in ethanol.
Olmesartan medoxomil, USP is practically insoluble in water and sparingly soluble in methanol. Each tablet of amlodipine and olmesartan medoxomil also contains the following inactive ingredients: microcrystalline cellulose, pregelatinized starch, croscarmellose sodium, colloidal silicon dioxide and magnesium stearate. The color coatings contain polyvinyl alcohol, macrogol/ polyethylene glycol 3350, macrogol/ polyethylene glycol 8000, titanium dioxide, talc, iron oxide yellow (5/40 mg, 10/20 mg, 10/40 mg tablets), iron oxide red (10/20 mg and 10/40 mg tablets), and iron oxide black (10/40 mg tablets).
USP Dissolution Test is pending. Amlodipine Chemical Structure Olmesartan Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Pregnancy: Advise female patients of childbearing age about the consequences of exposure to amlodipine and olmesartan medoxomil tablets during pregnancy. Discuss treatment options with women planning to become pregnant. Tell patients to report pregnancies to their physicians as soon as possible [see Warnings and Precautions (5.1) and Use in Specific Populations (8.1) ] .
Lactation: Advise nursing women not to breastfeed during treatment with amlodipine and olmesartan medoxomil tablets [see Use in Specific Populations (8.2) ] . Potassium Supplements: Advise patients not to use potassium supplements or salt substitutes containing potassium without consulting their healthcare provider. Manufactured by: ScieGen Pharmaceuticals, Inc.
Hauppauge, NY 11788 Rev. 3/2024