
Esmolol Hydrochloride 20 mg/mL Injection
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the beta-Adrenergic Blocker class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Esmolol is an IV medication specifically designed for situations where your heart rate or blood pressure needs to be brought under control very quickly — like during or after surge...
- Why am I getting esmolol instead of a pill for my heart rate?
- Esmolol is intended for short-term use only. Your care team will run the infusion only as long as needed to control your heart rate or blood pressure in the current situation. Once...
- Some people feel a drop in blood pressure, which can cause dizziness or sweating. Nausea or drowsiness can also occur. The most common issue is low blood pressure — your care team...
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Brevibloc 20 mg/mL 10019-0075-87 | Baxter | 100 ml | — | AP | FDA listed | — |
| Brevibloc 20 mg/mL 10019-0666-10 | Baxter | 100 ml | — | AP | FDA listed | — |
| Brevibloc 20 mg/mL 10019-0668-10 | Baxter | 100 ml | — | AP | FDA listed | — |
| esmolol hydrochloride 20 mg/mL 25021-0309-82 | Sagent | 100 ml | — | AP | FDA listed | — |
| Esmolol Hydrochloride 20 mg/mL 44567-0451-10 | WG | 100 ml | — | AP | FDA listed | — |
| Esmolol Hydrochloride in Water 20 mg/mL 44567-0812-10 | WG | 100 ml | — | — | FDA listed | — |
| esmolol hydrochloride 20 mg/mL 55150-0421-10 | Eugia | 10 pouches | — | AP | FDA listed | — |
| esmolol hydrochloride in sodium chloride 20 mg/mL 67457-0658-10 | Mylan | 1 pouch | — | AP | FDA listed | — |
| Esmolol Hydrochloride 20 mg/mLthis 70121-1717-03 | Amneal | 12 pouches | — | AP | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 70121-1717-07 | 10 POUCH in 1 CARTON (70121-1717-7) / 1 BAG in 1 POUCH (70121-1717-1) / 100 mL in 1 BAG | 2022-12-16 | Active |
| 70121-1717-03 You're viewing this | 12 POUCH in 1 CARTON (70121-1717-3) / 1 BAG in 1 POUCH / 100 mL in 1 BAG | 2024-01-01 | Active |
Pack size FAQ
What quantity is in NDC 70121-1717-03?
What NDC number is used to bill for this package of Esmolol Hydrochloride 20 mg/mL Injection?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Esmolol hydrochloride in sodium chloride injection is a beta adrenergic blocker indicated for the short-term treatment of: Control of ventricular rate in supraventricular tachycardia including atrial fibrillation and atrial flutter and control of heart rate in non-compensatory sinus tachycardia. ( 1.1 ) Control of perioperative tachycardia and hypertension. ( 1.2 )
1.1Supraventricular Tachycardia or Non-compensatory Sinus Tachycardia Esmolol hydrochloride in sodium chloride injection is indicated for the rapid control of ventricular rate in patients with atrial fibrillation or atrial flutter in perioperative, postoperative, or other emergent circumstances where short term control of ventricular rate with a short-acting agent is desirable. Esmolol hydrochloride in sodium chloride injection is also indicated in non-compensatory sinus tachycardia where, in the physician’s judgment, the rapid heart rate requires specific intervention.
Esmolol hydrochloride in sodium chloride injection is intended for short-term use.
1.2Intra-operative and Post-operative Tachycardia and/or Hypertension Esmolol hydrochloride in sodium chloride injection is indicated for the short-term treatment of tachycardia and hypertension that occur during induction and tracheal intubation, during surgery, on emergence from anesthesia and in the post-operative period, when in the physician’s judgment such specific intervention is considered indicated. Use of esmolol hydrochloride in sodium chloride injection to prevent such events is not recommended.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Administer intravenously. ( 2.1 , 2.2 ) Titrate using ventricular rate or blood pressure at ≥ 4-minute intervals. ( 2.1 , 2.2 ) Supraventricular tachycardia (SVT) or non-compensatory sinus tachycardia.
( 2.1 ) Optional loading dose: 500 mcg per kg infused over one minute. Then 50 mcg per kg per minute for the next 4 minutes. Adjust dose as needed to a maximum of 200 mcg per kg per minute.
Additional loading doses may be administered. Perioperative tachycardia and hypertension. ( 2.2 ) Loading dose: 500 mcg per kg over 1 minute for gradual control (1 mg per kg over 30 seconds for immediate control).
Then 50 mcg per kg per minute for gradual control (150 mcg per kg per minute for immediate control) adjusted to a maximum of 200 (tachycardia) or 300 (hypertension) mcg per kg per minute. ( 2.2 )
2.1Dosing for the Treatment of Supraventricular Tachycardia or Non-compensatory Sinus Tachycardia Esmolol hydrochloride in sodium chloride injection is administered by continuous intravenous infusion with or without a loading dose. Additional loading doses and/or titration of the maintenance infusion (step-wise dosing) may be necessary based on desired ventricular response. Table 1: Step-Wise Dosing Step Action 1 Optional loading dose (500 mcg per kg over 1 minute), then 50 mcg per kg per min for 4 min 2 Optional loading dose if necessary, then 100 mcg per kg per min for 4 min 3 Optional loading dose if necessary, then 150 mcg per kg per min for 4 min 4 If necessary, increase dose to 200 mcg per kg per min In the absence of loading doses, continuous infusion of a single concentration of esmolol reaches pharmacokinetic and pharmacodynamic steady-state in about 30 minutes.
The effective maintenance dose for continuous and step-wise dosing is 50 mcg per kg per minute to 200 mcg per kg per minute, although doses as low as 25 mcg per kg per minute have been adequate. Dosages greater than 200 mcg per kg per minute provide little added heart rate lowering effect, and the rate of adverse reactions increases. Maintenance infusions may be continued for up to 48 hours.
2.2Intra-operative and Post-operative Tachycardia and Hypertension In this setting it is not always advisable to slowly titrate to a therapeutic effect. Therefore, two dosing options are presented: immediate control and gradual control. Immediate Control Administer 1 mg per kg as a bolus dose over 30 seconds followed by an infusion of 150 mcg per kg per min if necessary.
Adjust the infusion rate as required to maintain desired heart rate and blood pressure. Refer to Maximum Recommended Doses below. Gradual Control Administer 500 mcg per kg as a bolus dose over 1 minute followed by a maintenance infusion of 50 mcg per kg per min for 4 minutes.
Depending on the response obtained, continue dosing as outlined for supraventricular tachycardia. Refer to Maximum Recommended Doses below. Maximum Recommended Doses For the treatment of tachycardia, maintenance infusion dosages greater than 200 mcg per kg per min are not recommended; dosages greater than 200 mcg per kg per min provide little additional heart rate-lowering effect, and the rate of adverse reactions increases.
For the treatment of hypertension, higher maintenance infusion dosages (250 mcg per kg per min to 300 mcg per kg per min) may be required. The safety of doses above 300 mcg per kg per minute has not been studied.
2.3Transition from Esmolol Hydrochloride in Sodium Chloride Injection Therapy to Alternative Drugs After patients achieve adequate control of the heart rate and a stable clinical status, transition to alternative antiarrhythmic drugs may be accomplished. When transitioning from esmolol hydrochloride in sodium chloride injection to alternative drugs, the physician should carefully consider the labeling instructions of the alternative drug selected and reduce the dosage of esmolol hydrochloride in sodium chloride injection as follows: Thirty minutes following the first dose of the alternati…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS All esmolol hydrochloride in sodium chloride injection dosage forms are iso-osmotic solutions of esmolol hydrochloride in sodium chloride. Table 2: Esmolol Hydrochloride in Sodium Chloride Injection Presentations Product Name Esmolol Hydrochloride in Sodium Chloride Injection Esmolol Hydrochloride in Sodium Chloride Injection [DOUBLE STRENGTH] Total Dose 2,500 mg/250 mL 2,000 mg/100 mL Esmolol Hydrochloride Concentration 10 mg/mL 20 mg/mL Packaging 250 mL Bag 100 mL Bag Injection: 2,500 mg/250 mL (10 mg/mL) in 250 mL Premixed Injection bag.
( 3 ) Injection: 2,000 mg/100 mL (20 mg/mL) in 100 mL Double Strength Premixed Injection bag. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Esmolol hydrochloride in sodium chloride injection is contraindicated in patients with: Severe sinus bradycardia: May precipitate or worsen bradycardia resulting in cardiogenic shock and cardiac arrest [see Warnings and Precautions (5.2) ]. Heart block greater than first degree: Second- or third-degree atrioventricular block may precipitate or worsen bradycardia resulting in cardiogenic shock and cardiac arrest [see Warnings and Precautions (5.2) ]. Sick sinus syndrome: May precipitate or worsen bradycardia resulting in cardiogenic shock and cardiac arrest [see Warnings and Precautions (5.2) ].
Decompensated heart failure: May worsen heart failure. Cardiogenic shock: May precipitate further cardiovascular collapse and cause cardiac arrest. Intravenous administration of cardiodepressant calcium-channel antagonists (e.g., verapamil) and esmolol hydrochloride in sodium chloride injection in close proximity (i.e. while cardiac effects from the other are still present); fatal cardiac arrests have occurred in patients receiving esmolol hydrochloride in sodium chloride injection and intravenous verapamil.
Pulmonary hypertension: May precipitate cardiorespiratory compromise. Hypersensitivity reactions, including anaphylaxis, to esmolol or any of the inactive ingredients of the product (cross-sensitivity between beta blockers is possible). Severe sinus bradycardia.
( 4 ) Heart block greater than first degree. ( 4 ) Sick sinus syndrome. ( 4 ) Decompensated heart failure.
( 4 ) Cardiogenic shock. ( 4 ) Co-administration of intravenous cardiodepressant calcium-channel antagonists (e.g., verapamil) in close proximity to esmolol hydrochloride in sodium chloride injection. ( 4 , 7 ) Pulmonary hypertension.
( 4 ) Known hypersensitivity to esmolol. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Risk of hypotension, bradycardia, and cardiac failure: Monitor for signs and symptoms of cardiovascular adverse effects. Reduce or discontinue use. ( 5.1 , 5.2 , 5.3 , 5.10 ) Risk of exacerbating reactive airway disease.
( 5.5 ) Diabetes: May mask symptoms of hypoglycemia and alter glucose levels; monitor ( 5.6 ) Risk of unopposed alpha-agonism and severe hypertension in untreated pheochromocytoma. ( 5.9 ) Risk of myocardial ischemia when abruptly discontinued in patients with coronary artery disease. ( 5.12 , 5.15 )
5.1Hypotension Hypotension can occur at any dose but is dose-related. Patients with hemodynamic compromise or on interacting medications are at particular risk. Severe reactions may include loss of consciousness, cardiac arrest, and death.
For control of ventricular heart rate, maintenance doses greater than 200 mcg per kg per min are not recommended. Monitor patients closely, especially if pre-treatment blood pressure is low. In case of an unacceptable drop in blood pressure, reduce or stop esmolol hydrochloride in sodium chloride injection.
Decrease of dose or termination of infusion reverses hypotension, usually within 30 minutes.
5.2Bradycardia Bradycardia, including sinus pause, heart block, severe bradycardia, and cardiac arrest have occurred with the use of esmolol hydrochloride in sodium chloride injection. Patients with first-degree atrioventricular block, sinus node dysfunction, or conduction disorders may be at increased risk. Monitor heart rate and rhythm in patients receiving esmolol hydrochloride in sodium chloride injection [see Contraindications (4) ].
If severe bradycardia develops, reduce or stop esmolol hydrochloride in sodium chloride injection.
5.3Cardiac Failure Beta blockers, like esmolol hydrochloride in sodium chloride injection, can cause depression of myocardial contractility and may precipitate heart failure and cardiogenic shock. At the first sign or symptom of impending cardiac failure, stop esmolol hydrochloride in sodium chloride injection and start supportive therapy [see Overdosage (10) ].
5.4Intra-operative and Post-operative Tachycardia and/or Hypertension Monitor vital signs closely and titrate esmolol hydrochloride in sodium chloride injection slowly in the treatment of patients whose blood pressure is primarily driven by vasoconstriction associated with hypothermia.
5.5Reactive Airways Disease Patients with reactive airways disease should, in general, not receive beta blockers. Because of its relative beta 1 selectivity and titratability, titrate esmolol hydrochloride in sodium chloride injection to the lowest possible effective dose. In the event of bronchospasm, stop the infusion immediately; a beta 2 stimulating agent may be administered with appropriate monitoring of ventricular rates.
5.6Hypoglycemia Beta-blockers may prevent early warning signs of hypoglycemia, such as tachycardia, and increase the risk for severe or prolonged hypoglycemia at any time during treatment, especially in patients with diabetes mellitus or children and patients who are fasting (i.e. surgery, not eating regularly, or are vomiting). If severe hypoglycemia occurs, patients should be instructed to seek emergency treatment.
5.7Infusion Site Reactions Infusion site reactions have occurred with the use of esmolol hydrochloride in sodium chloride injection. They include irritation, inflammation, and severe reactions (thrombophlebitis, necrosis and blistering), in particular when associated with extravasation [see Adverse Reactions (6) ]. Avoid infusions into small veins or through a butterfly catheter.
If a local infusion site reaction develops, use an alternative infusion site and avoid extravasation.
5.8Use in Patients with Prinzmetal’s Angina Beta blockers may exacerbate anginal attacks in patients with Prinzmetal’s angina because of unopposed alpha receptor–mediated coronary artery vasoconstriction. Do not use nonselective beta blockers.
5.9 Use in Patients with…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Most common adverse reactions (incidence > 10%) are symptomatic hypotension (hyperhidrosis, dizziness) and asymptomatic hypotension. ( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Amneal Pharmaceuticals at 1-877-835-5472 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. The following adverse reaction rates are based on use of esmolol hydrochloride in sodium chloride injection in clinical trials involving 369 patients with supraventricular tachycardia and over 600 intraoperative and postoperative patients enrolled in clinical trials.
Most adverse effects observed in controlled clinical trial settings have been mild and transient. The most important and common adverse effect has been hypotension [see Warnings and Precautions (5.1) ]. Deaths have been reported in post-marketing experience occurring during complex clinical states where esmolol hydrochloride in sodium chloride injection was presumably being used simply to control ventricular rate [see Warnings and Precautions (5.5) ].
Table 3: Clinical Trial Adverse Reactions (Frequency ≥ 3%) System Organ Class (SOC) Preferred MedDRA Term Frequency VASCULAR DISORDERS Hypotension * Asymptomatic hypotension Symptomatic hypotension (hyperhidrosis, dizziness) 25% 12% GENERAL DISORDERS AND ADMINISTRATION SITE CONDITIONS Infusion site reactions (inflammation and induration) 8% GASTROINTESTINAL DISORDERS Nausea 7% NERVOUS SYSTEM DISORDERS Dizziness 3% Somnolence 3% * Hypotension resolved during esmolol hydrochloride in sodium chloride injection infusion in 63% of patients.
In 80% of the remaining patients, hypotension resolved within 30 minutes following discontinuation of infusion. Clinical Trial Adverse Reactions (Frequency < 3%) Psychiatric Disorders Confusional state and agitation (~ 2%) Anxiety, depression and abnormal thinking (< 1%) Nervous System Disorders Headache (~ 2%) Paresthesia, syncope, speech disorder, and light-headedness (< 1%) Convulsions (< 1%), with one death Vascular Disorders Peripheral ischemia (~ 1%) Pallor and flushing (< 1%) Gastrointestinal Disorders Vomiting (~ 1%) Dyspepsia, constipation, dry mouth, and abdominal discomfort (< 1%) Renal and Urinary Disorders Urinary retention (< 1%)
6.2Post-Marketing Experience In addition to the adverse reactions reported in clinical trials, the following adverse reactions have been reported in the post-marketing experience. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to estimate reliably their frequency or to establish a causal relationship to drug exposure. Cardiac Disorders Cardiac arrest, Coronary arteriospasm Skin and Subcutaneous Tissue Disorders Angioedema, Urticaria, Psoriasis
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Concomitant use of esmolol hydrochloride in sodium chloride injection with other drugs that can lower blood pressure, reduce myocardial contractility, or interfere with sinus node function or electrical impulse propagation in the myocardium can exaggerate esmolol hydrochloride in sodium chloride injection’s effects on blood pressure, contractility and impulse propagation. Severe interactions with such drugs can result in, for example, severe hypotension, cardiac failure, severe bradycardia, sinus pause, sinoatrial block, atrioventricular block and/or cardiac arrest.
In addition, with some drugs, beta blockade may precipitate increased withdrawal effects (see clonidine, guanfacine and moxonidine below). Esmolol hydrochloride in sodium chloride injection should therefore be used only after careful individual assessment of the risks and expected benefits in patients receiving drugs that can cause these types of pharmacodynamic interactions, including but not limited to: Digitalis glycosides: Concomitant administration of digoxin and esmolol hydrochloride in sodium chloride injection leads to an approximate 10% to 20% increase of digoxin blood levels at some time points.
Digoxin does not affect esmolol hydrochloride in sodium chloride injection pharmacokinetics. Both digoxin and beta blockers slow atrioventricular conduction and decrease heart rate. Concomitant use increases the risk of bradycardia.
Anticholinesterases: Esmolol hydrochloride in sodium chloride injection prolonged the duration of succinylcholine-induced neuromuscular blockade and moderately prolonged clinical duration and recovery index of mivacurium. Antihypertensive agents clonidine, guanfacine, or moxonidine: Beta blockers also increase the risk of clonidine-, guanfacine-, or moxonidine-withdrawal rebound hypertension. If, during concomitant use of a beta blocker, antihypertensive therapy needs to be interrupted or discontinued, discontinue the beta blocker first, and the discontinuation should be gradual.
Calcium channel antagonists: In patients with depressed myocardial function, use of esmolol hydrochloride in sodium chloride injection with cardiodepressant calcium channel antagonists (e.g., verapamil) can lead to fatal cardiac arrests. Sympathomimetic drugs: Sympathomimetic drugs having beta-adrenergic agonist activity will counteract effects of esmolol hydrochloride in sodium chloride injection. Vasoconstrictive and positive inotropic agents: Because of the risk of reducing cardiac contractility in presence of high systemic vascular resistance, do not use esmolol hydrochloride in sodium chloride injection to control tachycardia in patients receiving drugs that are vasoconstrictive and have positive inotropic effects, such as epinephrine, norepinephrine, and dopamine.
Digitalis glycosides: Risk of bradycardia. ( 7 ) Anticholinesterases: Prolongs neuromuscular blockade. ( 7 ) Antihypertensive agents: Risk of rebound hypertension.
( 7 ) Sympathomimetic drugs: Dose adjustment needed. ( 7 ) Vasoconstrictive and positive inotropic effect substances: Avoid concomitant use. ( 7 )
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Esmolol hydrochloride has been shown to produce increased fetal resorptions with minimal maternal toxicity in rabbits when given in doses approximately 8 times the maximum human maintenance dose (300 mcg/kg/min). There are no adequate and well-controlled studies in pregnant women. Esmolol hydrochloride in sodium chloride injection should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
Teratogenicity studies in rats at intravenous dosages of esmolol hydrochloride up to 3,000 mcg/kg/min (10 times the maximum human maintenance dosage) for 30 minutes daily produced no evidence of maternal toxicity, embryotoxicity or teratogenicity, while a dosage of 10,000 mcg/kg/min produced maternal toxicity and lethality. In rabbits, intravenous dosages up to 1,000 mcg/kg/min for 30 minutes daily produced no evidence of maternal toxicity, embryotoxicity or teratogenicity, while 2,500 mcg/kg/min produced minimal maternal toxicity and increased fetal resorptions.
8.2Labor and Delivery Although there are no adequate and well-controlled studies in pregnant women, use of esmolol in the last trimester of pregnancy or during labor or delivery has been reported to cause fetal bradycardia, which continued after termination of drug infusion. Esmolol hydrochloride in sodium chloride injection should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
8.3Nursing Mothers It is not known whether this drug is excreted in human milk. Because many drugs are excreted in human milk and because of the potential for serious adverse reactions in nursing infants from esmolol hydrochloride in sodium chloride injection, a decision should be made whether to discontinue nursing or to discontinue the drug, taking into account the importance of the drug to the mother.
8.4Pediatric Use The safety and effectiveness of esmolol hydrochloride in sodium chloride injection in pediatric patients have not been established.
8.5Geriatric Use Clinical studies of esmolol hydrochloride in sodium chloride injection did not include sufficient numbers of subjects aged 65 and over to determine whether they responded differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should usually start at the low end of the dosing range, reflecting greater frequency of decreased renal or cardiac function and of concomitant disease or other drug therapy.
8.6Hepatic Impairment No special precautions are necessary in patients with hepatic impairment because esmolol hydrochloride in sodium chloride injection is metabolized by red-blood cell esterases [see Clinical Pharmacology (12) ].
8.7Renal Impairment No dosage adjustment is required for esmolol in patients with renal impairment receiving a maintenance infusion of esmolol 150 mcg/kg for 4 hours. There is no information on the tolerability of maintenance infusions of esmolol using rates in excess of 150 mcg/kg or maintained longer than 4 hours [see Clinical Pharmacology (12) ].
🤰 Pregnancy ▾
8.1Pregnancy Esmolol hydrochloride has been shown to produce increased fetal resorptions with minimal maternal toxicity in rabbits when given in doses approximately 8 times the maximum human maintenance dose (300 mcg/kg/min). There are no adequate and well-controlled studies in pregnant women. Esmolol hydrochloride in sodium chloride injection should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
Teratogenicity studies in rats at intravenous dosages of esmolol hydrochloride up to 3,000 mcg/kg/min (10 times the maximum human maintenance dosage) for 30 minutes daily produced no evidence of maternal toxicity, embryotoxicity or teratogenicity, while a dosage of 10,000 mcg/kg/min produced maternal toxicity and lethality. In rabbits, intravenous dosages up to 1,000 mcg/kg/min for 30 minutes daily produced no evidence of maternal toxicity, embryotoxicity or teratogenicity, while 2,500 mcg/kg/min produced minimal maternal toxicity and increased fetal resorptions.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of esmolol hydrochloride in sodium chloride injection in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of esmolol hydrochloride in sodium chloride injection did not include sufficient numbers of subjects aged 65 and over to determine whether they responded differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should usually start at the low end of the dosing range, reflecting greater frequency of decreased renal or cardiac function and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
10 OVERDOSAGE
10.1Signs and Symptoms of Overdose Overdoses of esmolol hydrochloride in sodium chloride injection can cause cardiac and central nervous system effects. These effects may precipitate severe signs, symptoms, sequelae, and complications (for example, severe cardiac and respiratory failure, including shock and coma), and may be fatal. Continuous monitoring of the patient is required.
Cardiac effects include bradycardia, atrioventricular block (1 st -, 2 nd -, 3 rd degree), junctional rhythms, intraventricular conduction delays, decreased cardiac contractility, hypotension, cardiac failure (including cardiogenic shock), cardiac arrest/asystole, and pulseless electrical activity. Central nervous system effects include respiratory depression, seizures, sleep and mood disturbances, fatigue, lethargy, and coma. In addition, bronchospasm, mesenteric ischemia, peripheral cyanosis, hyperkalemia, and hypoglycemia (especially in children) may occur.
10.2Treatment Recommendations Because of its approximately 9-minute elimination half-life, the first step in the management of toxicity should be to discontinue the esmolol hydrochloride infusion. Then, based on the observed clinical effects, consider the following general measures . Bradycardia Consider intravenous administration of atropine or another anticholinergic drug or cardiac pacing.
Cardiac Failure Consider intravenous administration of a diuretic or digitalis glycoside. In shock resulting from inadequate cardiac contractility, consider intravenous administration of dopamine, dobutamine, isoproterenol, or inamrinone. Glucagon has been reported to be useful.
Symptomatic hypotension Consider intravenous administration of fluids or vasopressor agents such as dopamine or norepinephrine. Bronchospasm Consider intravenous administration of a beta 2 stimulating agent or a theophylline derivative.
10.3Dilution Errors Massive accidental overdoses of esmolol hydrochloride in sodium chloride injection have resulted from dilution errors. Use of esmolol hydrochloride in sodium chloride injection and esmolol hydrochloride in sodium chloride injection [DOUBLE STRENGTH] may reduce the potential for dilution errors. Some of these overdoses have been fatal while others resulted in permanent disability.
Bolus doses in the range of 625 mg to 2.5 g (12.5 mg/kg to 50 mg/kg) have been fatal. Patients have recovered completely from overdoses as high as 1.75 g given over one minute or doses of 7.5 g given over one hour for cardiovascular surgery. The patients who survived appear to be those whose circulation could be supported until the effects of esmolol hydrochloride in sodium chloride injection resolved.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Esmolol hydrochloride in sodium chloride injection is a beta 1 -selective (cardioselective) adrenergic receptor blocking agent with rapid onset, a very short duration of action, and no significant intrinsic sympathomimetic or membrane stabilizing activity at therapeutic dosages. Its elimination half-life after intravenous infusion is approximately 9 minutes. Esmolol hydrochloride in sodium chloride injection inhibits the beta 1 receptors located chiefly in cardiac muscle, but this preferential effect is not absolute and at higher doses it begins to inhibit beta 2 receptors located chiefly in the bronchial and vascular musculature.
12.2Pharmacodynamics Clinical pharmacology studies in normal volunteers have confirmed the beta blocking activity of esmolol hydrochloride in sodium chloride injection, showing reduction in heart rate at rest and during exercise, and attenuation of isoproterenol-induced increases in heart rate. Blood levels of esmolol hydrochloride in sodium chloride injection have been shown to correlate with extent of beta blockade. After termination of infusion, substantial recovery from beta blockade is observed in 10 to 20 minutes.
The acid metabolite of esmolol exhibits negligible pharmacological activity. In human electrophysiology studies, esmolol hydrochloride in sodium chloride injection produced effects typical of a beta blocker: a decrease in the heart rate, increase in sinus cycle length, prolongation of the sinus node recovery time, prolongation of the AH interval during normal sinus rhythm and during atrial pacing, and an increase in antegrade Wenckebach cycle length. In patients undergoing radionuclide angiography, esmolol hydrochloride in sodium chloride injection, at dosages of 200 mcg/kg/min, produced reductions in heart rate, systolic blood pressure, rate pressure product, left and right ventricular ejection fraction and cardiac index at rest, which were similar in magnitude to those produced by intravenous propranolol (4 mg).
During exercise, esmolol hydrochloride in sodium chloride injection produced reductions in heart rate, rate pressure product and cardiac index which were also similar to those produced by propranolol, but esmolol hydrochloride in sodium chloride injection produced a significantly larger fall in systolic blood pressure. In patients undergoing cardiac catheterization, the maximum therapeutic dose of 300 mcg/kg/min of esmolol hydrochloride in sodium chloride injection produced similar effects and, in addition, there were small, clinically insignificant increases in the left ventricular end diastolic pressure and pulmonary capillary wedge pressure.
At 30 minutes after the discontinuation of esmolol hydrochloride infusion, all of the hemodynamic parameters had returned to pre-treatment levels. The relative cardioselectivity of esmolol hydrochloride in sodium chloride injection was demonstrated in 10 mildly asthmatic patients. Infusions of esmolol hydrochloride in sodium chloride injection 100 mcg/kg/min, 200 mcg/kg/min and 300 mcg/kg/min produced no significant increases in specific airway resistance compared to placebo.
At 300 mcg/kg/min, esmolol hydrochloride in sodium chloride injection produced slightly enhanced bronchomotor sensitivity to dry air stimulus. These effects were not clinically significant, and esmolol hydrochloride in sodium chloride injection was well tolerated by all patients. Six of the patients also received intravenous propranolol, and at a dosage of 1 mg, two experienced significant, symptomatic bronchospasm requiring bronchodilator treatment.
One other propranolol-treated patient also experienced dry air-induced bronchospasm. No adverse pulmonary effects were observed in patients with COPD who received therapeutic dosages of esmolol hydrochloride in sodium chloride injection for treatment of supraventricular tachycardia (51 patients) or in perioperative settings (32 patients).
12.3 Pharmacokinetics Esmolo…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Esmolol hydrochloride in sodium chloride injection is a beta 1 -selective (cardioselective) adrenergic receptor blocking agent with rapid onset, a very short duration of action, and no significant intrinsic sympathomimetic or membrane stabilizing activity at therapeutic dosages. Its elimination half-life after intravenous infusion is approximately 9 minutes. Esmolol hydrochloride in sodium chloride injection inhibits the beta 1 receptors located chiefly in cardiac muscle, but this preferential effect is not absolute and at higher doses it begins to inhibit beta 2 receptors located chiefly in the bronchial and vascular musculature.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
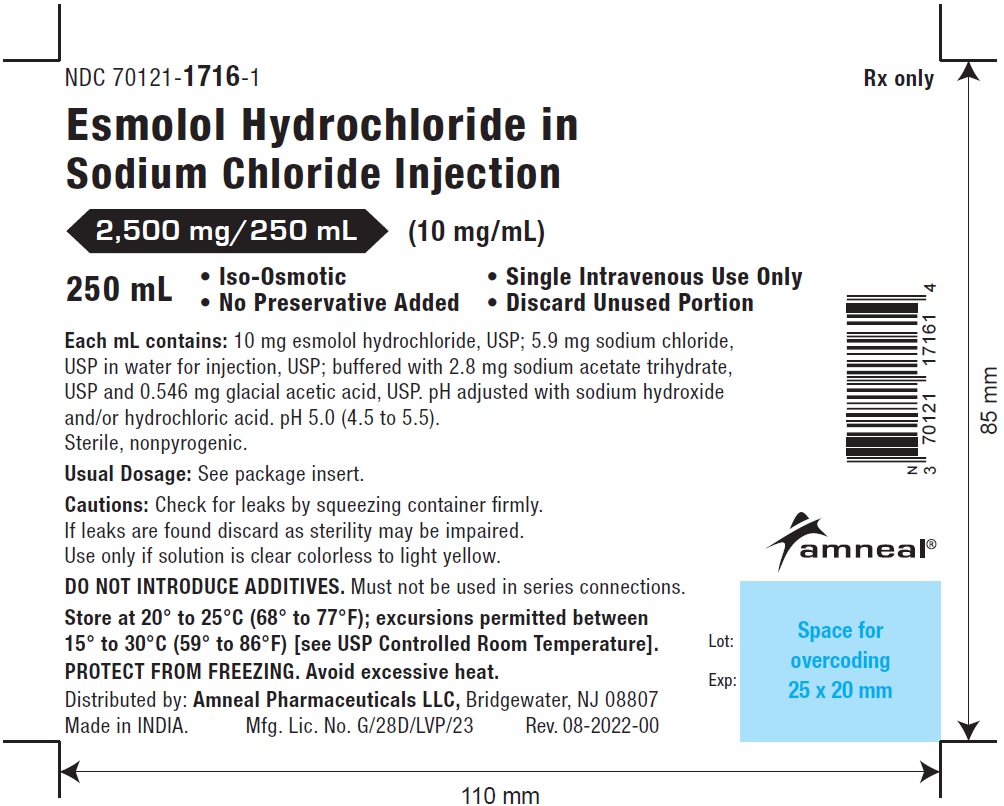
16.1How Supplied Esmolol Hydrochloride in Sodium Chloride Injection, 2,500 mg/250 mL (10 mg/mL) is supplied as clear, colorless to light yellow color solution filled in intravenous bags. Each mL contains 10 mg of esmolol hydrochloride, USP. They are available as follows: Strength Each Unit of Sale 2,500 mg/250 mL (10 mg/mL) NDC 70121-1716-1 1 Single-dose Intravenous Bag in an Overwrap NDC 70121-1716-7 Unit of 10 NDC 70121-1716-3 Unit of 12 Esmolol Hydrochloride in Sodium Chloride Injection [DOUBLE STRENGTH], 2,000 mg/100 mL (20 mg/mL) is supplied as clear, colorless to light yellow color solution filled in intravenous bags.
Each mL contains 20 mg of esmolol hydrochloride, USP. They are available as follows: Strength Each Unit of Sale 2,000 mg/100 mL (20 mg/mL) NDC 70121-1717-1 1 Single-dose Intravenous Bag in an Overwrap NDC 70121-1717-7 Unit of 10 NDC 70121-1717-3 Unit of 12
16.2Storage Store at 20° to 25˚C (68° to 77˚F); excursions permitted between 15˚ to 30˚C (59˚ to 86˚F) [see USP Controlled Room Temperature]. Protect from freezing. Avoid excessive heat.
Visually inspect the container. If the administration port protector is damaged, detached, or not present, discard container as solution path sterility may be impaired. Each intravenous bag contains no preservative.
Once drug has been withdrawn from ready-to-use bag, the bag should be used within 24 hours, with any unused portion discarded. Do not use plastic containers in series connections. Such use could result in an embolism due to residual air being drawn from the primary container before administration of the fluid from the secondary container is completed.
Do not remove unit from overwrap until ready to use. Do not use if overwrap has been previously opened or damaged. The overwrap is a moisture barrier.
The inner bag maintains sterility of the solution. Tear overwrap at notch and remove premixed bag. Some opacity of the plastic due to moisture absorption during the sterilization process may be observed.
This is normal and does not affect the solution quality or safety. The opacity will diminish gradually. Check for minute leaks by squeezing the inner bag firmly.
If leaks are found, discard solution, as sterility may be impaired. Do not use unless the solution is clear (colorless to light yellow) and the seal is intact. Preparation for intravenous administration: Use aseptic technique.
Suspend premixed bag from eyelet support. Twist-off from the centre of delivery port at bottom of bag. Attach administration set.
Refer to complete directions accompanying set [see Directions for Use (2.4) ] .
📋 Description ▾
11 DESCRIPTION Esmolol hydrochloride in sodium chloride injection is a beta adrenergic receptor blocker with a very short duration of action (elimination half-life is approximately 9 minutes). Esmolol hydrochloride, USP is: 4-[2-Hydroxy –3-[(1-methylethyl)amino]-propoxy]benzenepropanoic acid methyl ester hydrochloride and has the following structure: Esmolol hydrochloride, USP has the molecular formula C 16 H 25 NO 4 .HCl and a molecular weight of 331.83 g/mol. It has one asymmetric center and exists as an enantiomeric pair.
Esmolol hydrochloride, USP is a white to off-white crystalline powder. It is a relatively hydrophilic compound which is very soluble in water and freely soluble in alcohol. Its partition coefficient (octanol/water) at pH 3.0 to 5.0 is 1.7.
12
11.1Esmolol Hydrochloride in Sodium Chloride Injection Dosage Form Esmolol hydrochloride in sodium chloride injection is clear, colorless to light yellow, sterile, nonpyrogenic, iso-osmotic solution. The formulations for esmolol hydrochloride in sodium chloride injection, 2,500 mg/250 mL (10 mg/mL) and esmolol hydrochloride in sodium chloride injection [DOUBLE STRENGTH], 2,000 mg/100 mL (20 mg/mL) are described in the table below: Table 4: Esmolol Hydrochloride in Sodium Chloride Injection Formulations Esmolol Hydrochloride in Sodium Chloride Injection Esmolol Hydrochloride in Sodium Chloride Injection [DOUBLE STRENGTH] Esmolol Hydrochloride, USP 10 mg/mL 20 mg/mL Sodium Chloride, USP 5.9 mg/mL 4.1 mg/mL Water for Injection, USP Q.S. to volume of 250 mL Q.S. to volume of 100 mL Sodium Acetate Trihydrate, USP 2.8 mg/mL 2.8 mg/mL Glacial Acetic Acid, USP 0.546 mg/mL 0.546 mg/mL Sodium Hydroxide Q.S. to adjust pH to 5.0 (4.5 to 5.5) Hydrochloric Acid Q.S. to adjust pH to 5.0 (4.5 to 5.5) Q.S. = Quantity sufficient The calculated osmolarity of esmolol hydrochloride in sodium chloride injection, 2,500 mg/250 mL (10 mg/mL) and esmolol hydrochloride in sodium chloride injection [DOUBLE STRENGTH] 2,000 mg/100 mL (20 mg/mL) is 312 mOsmol/L.
The 250 mL and 100 mL Magiflex bags are non-latex, non-PVC with dual PP ports. Solutions in contact with the plastic container leach out certain chemical compounds from the plastic in very small amounts; however, biological testing was supportive of the safety of the plastic container materials.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Physicians should inform patients of the risks associated with esmolol hydrochloride in sodium chloride injection: The most common adverse reactions are symptomatic hypotension (hyperhidrosis, dizziness) and asymptomatic hypotension. Inform patients or caregivers that there is a risk of hypoglycemia when esmolol is given to patients who are fasting or who are vomiting. Monitor for symptoms of hypoglycemia. [see Warnings and Precautions (5.6) ] .
For additional information go to www.amneal.com or call 1-877-835-5472. Manufactured by: Amneal Pharmaceuticals Pvt. Ltd.
Mehsana 382165, INDIA Distributed by: Amneal Pharmaceuticals LLC Bridgewater, NJ 08807 Rev. 04-2024-05 1