
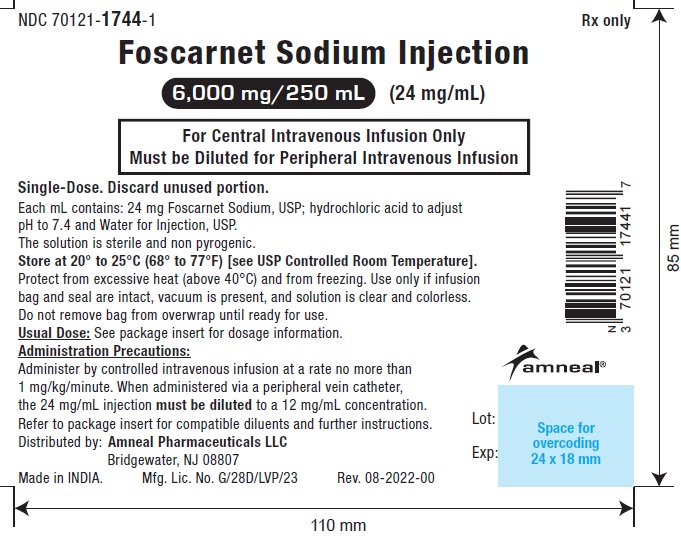
Foscarnet Sodium 24 mg/mL Injection — NDC 70121-1744-7 (Billing 70121-1744-07)
This is a package of Foscarnet Sodium 24 mg/mL Injection from Amneal Pharmaceuticals LLC, marketed since Mar 2024 and currently FDA-listed.
NDC database record
One package, one record: these facts belong to NDC 70121-1744-7 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 70121 labeler · 1744 product · 7 package
- Package marketed since
- Mar 4, 2024
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Barcode (UPC-A, from the NDC)
- 3 7012117447 9
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 082018
- GCN: 49315
- GPI-14 (Medi-Span): 12200020102030
- HICL (First Databank): 013221
- AHFS class code: 08:18.92.00
- RxCUI (RxNorm): 1734377
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Pyrophosphate Analog DNA Polymerase Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It treats CMV retinitis, an eye infection, in people with AIDS. It also treats herpes simplex infections of the skin and mucous membranes that no longer respond to acyclovir, in pe...
- It is given as a slow IV infusion with a pump, along with fluids to protect your kidneys. It should never be pushed in quickly. Your team sets the schedule based on your weight and...
- Foscarnet can harm the kidneys and change levels of calcium, magnesium, potassium and phosphate. Regular tests let your team adjust the dose and treat problems early.
- Tell your nurse about tingling around the mouth, numbness in your hands or feet, muscle spasms or a seizure. Also report hives, swelling, trouble breathing, a racing or irregular h...
Patient education
Supplement & herbal interactions
Foscarnet may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 8, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 70121-1744-02 70121-1744-2 Main listing | 12 POUCH in 1 CARTON / 1 BAG in 1 POUCH / 250 mL in 1 BAG | 2024-03-04 | — | Active |
| 70121-1744-07 You're viewing this | 10 POUCH in 1 CARTON / 1 BAG in 1 POUCH / 250 mL in 1 BAG | 2024-03-04 | — | Active |
Pack size FAQ
What quantity is in this package?
What NDC number is used to bill for this package of Foscarnet Sodium 24 mg/mL Injection?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Foscarnet Sodium 24 mg/mL 00143-9192-01 | Hikma | 1 bottle | — | AP | FDA listed | — |
| foscarnet sodium 24 mg/mL 23155-0771-41 | Heritage | 1 bottle | — | AP | Discontinued | — |
| Foscarnet Sodium 24 mg/mL 25021-0189-84 | Sagent | 250 ml | — | AP | FDA listed | — |
| Foscarnet Sodium 6000 mg/250mL 43066-0089-10 | Baxter | 250 ml | — | AP | FDA listed | — |
| Foscarnet 24 mg/mL 63323-0875-50 | Fresenius | 1 bottle | — | AP | FDA listed | — |
| Foscarnet Sodium 24 mg/mL 65145-0191-10 | Caplin | 10 pouches | — | AP | FDA listed | — |
| Foscarnet Sodium 24 mg/mL 68083-0389-01 | Gland | 250 ml | — | AP | FDA listed | — |
| Foscarnet Sodium 24 mg/mLthis 70121-1744-07 | Amneal | 10 pouches | — | AP | FDA listed | — |
| Foscavir 24 mg/mL 76310-0024-45 | Clinigen | 10 pouches | — | AP | Discontinued | — |
| Foscarnet Sodium 24 mg/mL 70069-0864-10 | Somerset | 10 pouches | — | AP | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Foscarnet Injection inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
2 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 8, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Amneal Pharmaceuticals LLC labeler code 70121
- POTASSIUM PHOSPHATES 4.48 mg/mL; 4.72 mg/mL Injection NDC 70121-1722-9
- Ropivacaine Hydrochloride 2 mg/mL Injection NDC 70121-1732-3
- Ropivacaine Hydrochloride 2 mg/mL Injection NDC 70121-1733-3
- Ropivacaine Hydrochloride 5 mg/mL Injection NDC 70121-1734-3
- Ropivacaine Hydrochloride 5 mg/mL Injection NDC 70121-1735-3
- Nelarabine 5 mg/mL Injection NDC 70121-1743-1
- ALYMSYS bevacizumab-maly 100 mg/4mL Injection, Solution NDC 70121-1754-1
- ALYMSYS bevacizumab-maly 400 mg/16mL Injection, Solution NDC 70121-1755-1
- ROMIDEPSIN 5 mg/mL Injection, Solution, Concentrate NDC 70121-2250-1
- calcium chloride 100 mg/mL Injection, Solution NDC 70121-2308-4
- calcium chloride 100 mg/mL Injection, Solution NDC 70121-2309-7
- LABETALOL HYDROCHLORIDE 5 mg/mL Injection, Solution NDC 70121-2428-3
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING RENAL IMPAIRMENT IS THE MAJOR TOXICITY OF FOSCARNET SODIUM INJECTION. FREQUENT MONITORING OF SERUM CREATININE, WITH DOSE ADJUSTMENT FOR CHANGES IN RENAL FUNCTION, AND ADEQUATE HYDRATION WITH ADMINISTRATION OF FOSCARNET SODIUM INJECTION IS IMPERATIVE (see ADMINISTRATION section ; Hydration). SEIZURES, RELATED TO ALTERATIONS IN PLASMA MINERALS AND ELECTROLYTES, HAVE BEEN ASSOCIATED WITH FOSCARNET SODIUM INJECTION TREATMENT.
THEREFORE, PATIENTS MUST BE CAREFULLY MONITORED FOR SUCH CHANGES AND THEIR POTENTIAL SEQUELAE. MINERAL AND ELECTROLYTE SUPPLEMENTATION MAY BE REQUIRED. FOSCARNET SODIUM INJECTION IS INDICATED FOR USE ONLY IN IMMUNOCOMPROMISED PATIENTS WITH CMV RETINITIS AND MUCOCUTANEOUS ACYCLOVIR-RESISTANT HSV INFECTIONS (see INDICATIONS section ).
🎯 Indications and Usage ▾
INDICATIONS CMV Retinitis Foscarnet sodium injection is indicated for the treatment of CMV retinitis in patients with acquired immunodeficiency syndrome (AIDS). Combination therapy with foscarnet sodium injection and ganciclovir is indicated for patients who have relapsed after monotherapy with either drug. SAFETY AND EFFICACY OF FOSCARNET SODIUM INJECTION HAVE NOT BEEN ESTABLISHED FOR TREATMENT OF OTHER CMV INFECTIONS (e.g., PNEUMONITIS, GASTROENTERITIS); CONGENITAL OR NEONATAL CMV DISEASE; OR NONIMMUNOCOMPROMISED INDIVIDUALS.
Mucocutaneous Acyclovir Resistant HSV Infections Foscarnet sodium injection is indicated for the treatment of acyclovir-resistant mucocutaneous HSV infections in immunocompromised patients. SAFETY AND EFFICACY OF FOSCARNET SODIUM INJECTION HAVE NOT BEEN ESTABLISHED FOR TREATMENT OF OTHER HSV INFECTIONS (e.g., RETINITIS, ENCEPHALITIS); CONGENITAL OR NEONATAL HSV DISEASE; OR HSV IN NONIMMUNOCOMPROMISED INDIVIDUALS.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION CAUTION - DO NOT ADMINISTER FOSCARNET SODIUM INJECTION BY RAPID OR BOLUS INTRAVENOUS INJECTION. THE TOXICITY OF FOSCARNET SODIUM INJECTION MAY BE INCREASED AS A RESULT OF EXCESSIVE PLASMA LEVELS. CARE SHOULD BE TAKEN TO AVOID UNINTENTIONAL OVERDOSE BY CAREFULLY CONTROLLING THE RATE OF INFUSION.
THEREFORE, AN INFUSION PUMP MUST BE USED. IN SPITE OF THE USE OF AN INFUSION PUMP, OVERDOSES HAVE OCCURRED. ADMINISTRATION Instructions for Administration and Preparation Foscarnet sodium injection is administered by controlled intravenous infusion, either by using a central venous line or with dilution by using a peripheral vein.
The rate of controlled intravenous infusion must be no more than 1 mg/kg/minute. An individualized dose of foscarnet sodium injection should be calculated on the basis of body weight (mg/kg), renal function, indication of use and dosing frequency (refer to DOSAGE subsection). To reduce the risk of nephrotoxicity, creatinine clearance (mL/min/kg) should be calculated even if serum creatinine is within the normal range, and doses should be adjusted accordingly.
An individualized dose at the required concentration (24 mg/mL or 12 mg/mL) for the route of administration (central line or peripheral line) needs to be aseptically prepared prior to dispensing. The standard 24 mg/mL solution may be used with or without dilution when using a central venous catheter for infusion. When a peripheral vein catheter is used, the 24 mg/mL injection must be diluted to a 12 mg/mL concentration with 5% dextrose in water or with a normal saline solution prior to administration to avoid local irritation of peripheral veins.
Dilutions and/or removals of excess quantities should be accomplished under aseptic conditions. Solutions thus prepared should be used within 24 hours of first entry into a sealed bottle or infusion bag. Hydration Hydration may reduce the risk of nephrotoxicity.
Clinically dehydrated patients should have their condition corrected before initiating foscarnet sodium injection therapy. It is recommended that 750 to 1,000 mL of normal saline or 5% dextrose solution should be given prior to the first infusion of foscarnet sodium injection to establish diuresis. With subsequent infusions, 750 to 1,000 mL of hydration fluid should be given with 90 mg/kg to 120 mg/kg of foscarnet sodium injection, and 500 mL with 40 mg/kg to 60 mg/kg of foscarnet sodium injection.
Hydration fluid may need to be decreased if clinically warranted. Oral rehydration with similar regimens may be considered in certain patients. After the first dose, the hydration fluid should be administered concurrently with each infusion of foscarnet sodium injection.
Compatibility With Other Solutions/Drugs Other drugs and supplements can be administered to a patient receiving foscarnet sodium injection. However, care must be taken to ensure that foscarnet sodium injection is only administered with normal saline or 5% dextrose solution and that no other drug or supplement is administered concurrently via the same catheter. Foscarnet has been reported to be chemically incompatible with 30% dextrose, amphotericin B, and solutions containing calcium such as Ringer’s lactate and TPN.
Physical incompatibility with other intravenous drugs has also been reported including acyclovir sodium, ganciclovir, trimetrexate glucuronate, pentamidine isethionate, vancomycin, trimethoprim/sulfamethoxazole, diazepam, midazolam, digoxin, phenytoin, leucovorin, and proclorperazine. Because of foscarnet’s chelating properties, a precipitate can potentially occur when divalent cations are administered concurrently in the same catheter. Parenteral drug products must be inspected visually for particulate matter and discoloration prior to administration whenever the solution and container permit.
Solutions that are discolored or contain particulate matter should not be used. Accidental Exposure Accidental skin and eye contact with foscarnet sodium solution m… [Excerpted — this section continues on DailyMed.]
⛔ Contraindications ▾
CONTRAINDICATIONS Foscarnet sodium injection is contraindicated in patients with clinically significant hypersensitivity to foscarnet sodium.
⚠️ Warnings ▾
WARNINGS Renal Impairment THE MAJOR TOXICITY OF FOSCARNET SODIUM IS RENAL IMPAIRMENT (see ADVERSE REACTIONS section ). Renal impairment is most likely to become clinically evident during the second week of induction therapy, but may occur at any time during foscarnet sodium treatment. Renal function should be monitored carefully during both induction and maintenance therapy (see PATIENT MONITORING section ).
Elevations in serum creatinine are usually, but not always, reversible following discontinuation or dose adjustment of foscarnet sodium. Safety and efficacy data for patients with baseline serum creatinine levels greater than 2.8 mg/dL or measured 24-hour creatinine clearances < 50 mL/min are limited. SINCE FOSCARNET SODIUM HAS THE POTENTIAL TO CAUSE RENAL IMPAIRMENT, DOSE ADJUSTMENT BASED ON SERUM CREATININE IS NECESSARY.
Hydration may reduce the risk of nephrotoxicity. It is recommended that 750 mL to 1,000 mL of normal saline or 5% dextrose solution should be given prior to the first infusion of foscarnet sodium to establish diuresis. With subsequent infusions, 750 mL to 1,000 mL of hydration fluid should be given with 90 mg/kg to 120 mg/kg of foscarnet sodium, and 500 mL with 40 mg/kg to 60 mg/kg of foscarnet sodium.
Hydration fluid may need to be decreased if clinically warranted. After the first dose, the hydration fluid should be administered concurrently with each infusion of foscarnet sodium. Mineral and Electrolyte Abnormalities Foscarnet sodium has been associated with changes in serum electrolytes including hypocalcemia, hypophosphatemia, hyperphosphatemia, hypomagnesemia, and hypokalemia (see ADVERSE REACTIONS section ).
Foscarnet sodium may also be associated with a dose-related decrease in ionized serum calcium which may not be reflected in total serum calcium. This effect is likely to be related to chelation of divalent metal ions such as calcium by foscarnet. Patients should be advised to report symptoms of low ionized calcium such as perioral tingling, numbness in the extremities and paresthesias.
Particular caution and careful management of serum electrolytes is advised in patients with altered calcium or other electrolyte levels before treatment and especially in those with neurologic or cardiac abnormalities and those receiving other drugs known to influence minerals and electrolytes (see PATIENT MONITORING and Drug Interactions sections ). Physicians should be prepared to treat these abnormalities and their sequelae such as tetany, seizures or cardiac disturbances. The rate of foscarnet sodium infusion may also affect the decrease in ionized calcium.
Therefore, an infusion pump must be used for administration to prevent rapid intravenous infusion (see DOSAGE AND ADMINISTRATION section ). Slowing the infusion rate may decrease or prevent symptoms. Seizures Seizures related to mineral and electrolyte abnormalities have been associated with foscarnet sodium treatment (see WARNING section; Mineral and Electrolyte Abnormalities ).
Several cases of seizures were associated with death. Cases of status epilepticus have been reported. Risk factors associated with seizures included impaired baseline renal function, low total serum calcium, and underlying CNS conditions.
Hypersensitivity Serious acute hypersensitivity reactions (e.g., anaphylactic shock, urticaria, angioedema) have been reported post-marketing in patients receiving foscarnet sodium (see ADVERSE REACTIONS section ). If such an acute reaction occurs, therapy should be discontinued and appropriate medical therapy immediately instituted. QT prolongation and torsade de pointes Foscarnet sodium has been associated with prolongation of the QT interval, an ECG abnormality that has been associated with torsades de pointes, which has been reported during post-marketing surveillance for foscarnet sodium (see ADVERSE REACTIONS section ).
Some of these patients had confounding risk factors such as underlying cardiac disease, electrolyte abnormalities and oth… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
ADVERSE REACTIONS THE MAJOR TOXICITY OF FOSCARNET SODIUM IS RENAL IMPAIRMENT (see WARNINGS section ). Approximately 33% of 189 patients with AIDS and CMV retinitis who received foscarnet sodium (60 mg/kg TID), without adequate hydration, developed significant impairment of renal function (serum creatinine ≥ 2.0 mg/dL). The incidence of renal impairment in subsequent clinical trials in which 1,000 mL of normal saline or 5% dextrose solution was given with each infusion of foscarnet sodium was 12% (34/280).
Foscarnet sodium has been associated with changes in serum electrolytes including hypocalcemia (15% to 30%), hypophosphatemia (8% to 26%) and hyperphosphatemia (6%), hypomagnesemia (15% to 30%), and hypokalemia (16% to 48%) (see WARNINGS section ). The higher percentages were derived from those patients receiving hydration. Foscarnet sodium treatment was associated with seizures in 18/189 (10%) AIDS patients in the initial five controlled studies (see WARNINGS section ).
Risk factors associated with seizures included impaired baseline renal function, low total serum calcium, and underlying CNS conditions predisposing the patient to seizures. The rate of seizures did not increase with duration of treatment. Three cases were associated with overdoses of foscarnet sodium (see OVERDOSAGE section ).
In five controlled U.S. clinical trials the most frequently reported adverse events in patients with AIDS and CMV retinitis are shown in Table 9. These figures were calculated without reference to drug relationship or severity. TABLE 9: Adverse Events Reported in Five Controlled US Clinical Trials n = 189 n = 189 Fever 65% Abnormal Renal Function 27% Nausea 47% Vomiting 26% Anemia 33% Headache 26% Diarrhea 30% Seizures 10% From the same controlled studies, adverse events categorized by investigator as “severe” are shown in Table 10.
Although death was specifically attributed to foscarnet sodium in only one case, other complications of foscarnet sodium (i.e. renal impairment, electrolyte abnormalities, and seizures) may have contributed to patient deaths (see WARNINGS section ). TABLE 10: Severe Adverse Events n = 189 Death 14% Abnormal Renal Function 14% Marrow Suppression 10% Anemia 9% Seizures 7% From the five initial U.S. controlled trials of foscarnet sodium, the following list of adverse events has been compiled regardless of causal relationship to foscarnet sodium.
Evaluation of these reports was difficult because of the diverse manifestations of the underlying disease and because most patients received numerous concomitant medications. Incidence of 5% or Greater Body as a Whole: fever, fatigue, rigors, asthenia, malaise, pain, infection, sepsis, death Central and Peripheral Nervous System : headache, paresthesia, dizziness, involuntary muscle contractions, hypoesthesia, neuropathy, seizures including grand mal seizures (see WARNINGS ) Gastrointestinal System: anorexia, nausea, diarrhea, vomiting, abdominal pain Hematologic: anemia, granulocytopenia, leukopenia, neutropenia (see PRECAUTIONS ) Metabolic and Nutritional: mineral and electrolyte imbalances (see WARNINGS ) including hypokalemia, hypocalcemia, hypomagnesemia, hypophosphatemia, hyperphosphatemia Psychiatric: depression, confusion, anxiety Respiratory System: coughing, dyspnea Skin and Appendages: rash, increased sweating Urinary System: alterations in renal function including increased serum creatinine, decreased creatinine clearance, and abnormal renal function (see WARNINGS ) Special Senses: vision abnormalities Incidence between 1% and 5% Application Site: injection site pain, injection site inflammation Body as a Whole: back pain, chest pain (including reports of transient chest pain as part of infusion reactions), edema, influenza-like symptoms, bacterial infections, moniliasis, fungal infections, abscess Cardiovascular: hypertension, palpitations, ECG abnormalities including sinus tachycardia, first degree AV block and non-specific ST-T segment changes, hypotensi… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
Drug Interactions A possible drug interaction of foscarnet sodium and intravenous pentamidine has been described. Concomitant treatment of four patients in the United Kingdom with foscarnet sodium and intravenous pentamidine may have caused hypocalcemia; one patient died with severe hypocalcemia. Toxicity associated with concomitant use of aerosolized pentamidine has not been reported.
Because foscarnet sodium can reduce serum levels of ionized calcium, extreme caution is advised when used concurrently with other drugs known to influence serum calcium levels (e.g., intravenous pentamidine). Renal impairment and symptomatic hypocalcemia have been observed during concurrent treatment with foscarnet sodium and intravenous pentamidine. Because of foscarnet’s tendency to cause renal impairment, the use of foscarnet sodium should be avoided in combination with potentially nephrotoxic drugs such as aminoglycosides, amphotericin B, cyclosporine, acyclovir, methotrexate, tacrolimus and intravenous pentamidine (see above) unless the potential benefits outweigh the risks to the patient.
When diuretics are indicated, thiazides are recommended over loop diuretics because the latter inhibit renal tubular secretion, and may impair elimination of foscarnet sodium, potentially leading to toxicity. Abnormal renal function has been observed in clinical practice during the use of foscarnet sodium and ritonavir, or foscarnet sodium, ritonavir, and saquinavir (see DOSAGE and ADMINISTRATION ). Because of the risk of QT prolongation and the potential for torsades de pointes, the use of foscarnet sodium should be avoided in combination with agents known to prolong the QT interval including Class IA (e.g., quinidine or procainamide) or Class III (e.g., dofetilide, amiodarone, sotalol) antiarrhythmic agents, phenothiazines, tricyclic antidepressants, and certain macrolides and fluoroquinolones.
🤰 Pregnancy ▾
Pregnancy There are no adequate and well-controlled studies of foscarnet sodium in pregnant women. Because animal reproduction studies are not always predictive of human response, this drug should be used during pregnancy only if clearly needed. Animal Data: Foscarnet sodium did not adversely affect fertility and general reproductive performance in rats.
The results of peri- and post-natal studies in rats were also negative. However, these studies used exposures that are inadequate to define the potential for impairment of fertility at human drug exposure levels. Daily subcutaneous doses up to 75 mg/kg administered to female rats prior to and during mating, during gestation, and 21 days post-partum caused a slight increase (< 5%) in the number of skeletal anomalies compared with the control group.
Daily subcutaneous doses up to 75 mg/kg administered to rabbits and 150 mg/kg administered to rats during gestation caused an increase in the frequency of skeletal anomalies/variations. On the basis of estimated drug exposure (as measured by AUC), the 150 mg/kg dose in rats and 75 mg/kg dose in rabbits were approximately one-eighth (rat) and one-third (rabbit) the estimated maximal daily human exposure. These studies are inadequate to define the potential teratogenicity at levels to which women will be exposed.
🧒 Pediatric Use ▾
Pediatric Use The safety and effectiveness of foscarnet sodium in pediatric patients have not been established. Foscarnet sodium is deposited in teeth and bone and deposition is greater in young and growing animals. Foscarnet sodium has been demonstrated to adversely affect development of tooth enamel in mice and rats.
The effects of this deposition on skeletal development have not been studied. Since deposition in human bone has also been shown to occur, it is likely that it does so to a greater degree in developing bone in pediatric patients. Administration to pediatric patients should be undertaken only after careful evaluation and only if the potential benefits for treatment outweigh the risks.
🆘 Overdosage ▾
OVERDOSAGE In controlled clinical trials performed in the United States, overdosage with foscarnet sodium was reported in 10 out of 189 patients. All 10 patients experienced adverse events and all except one made a complete recovery. One patient died after receiving a total daily dose of 12.5 g for three days instead of the intended 10.9 g.
The patient suffered a grand mal seizure and became comatose. Three days later the patient expired with the cause of death listed as respiratory/cardiac arrest. The other nine patients received doses ranging from 1.14 times to 8 times their recommended doses with an average of 4 times their recommended doses.
Overall, three patients had seizures, three patients had renal function impairment, four patients had paresthesias either in limbs or periorally, and five patients had documented electrolyte disturbances primarily involving calcium and phosphate. Overdose (up to 20 times the recommended dose) has been reported in post-marketing use of foscarnet sodium. Some of these post-marketing reports were relative overdoses in that the dose of foscarnet sodium had not been adjusted in patients with a reduced renal function.
The pattern of adverse events associated with a foscarnet sodium overdose is consistent with the known adverse event profile of the drug. There is no specific antidote for foscarnet sodium overdose. Hemodialysis and hydration may be of benefit in reducing drug plasma levels in patients who receive an overdosage of foscarnet sodium, but the effectiveness of these interventions has not been evaluated.
The patient should be observed for signs and symptoms of renal impairment and electrolyte imbalance. Medical treatment should be instituted if clinically warranted.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Pharmacokinetics The pharmacokinetics of foscarnet has been determined after administration as an intermittent intravenous infusion during induction therapy in AIDS patients with CMV retinitis. Observed plasma foscarnet concentrations in four studies (FOS-01, ACTG-015, FP48PK, FP49PK) are summarized in Table 7: TABLE 7: Foscarnet Pharmacokinetic Characteristics * Parameter 60 mg/kg Q8h 90 mg/kg Q12h C max at steady-state (μM) 589 ± 192 (24) 623 ± 132 (19) C trough at steady-state (μM) 114 ± 91 (24) 63 ± 57 (17) Volume of distribution (L/kg) 0.41 ± 0.13 (12) 0.52 ± 0.20 (18) Plasma half-life (hr) 4.0 ± 2.0 (24) 3.3 ± 1.4 (18) Systemic clearance (L/hr) 6.2 ± 2.1 (24) 7.1 ± 2.7 (18) Renal clearance (L/hr) 5.6 ± 1.9 (5) 6.4 ± 2.5 (13) CSF: plasma ratio 0.69 ± 0.19 (9) † 0.66 ± 0.11 (5) ‡ * Values expressed as mean S.D.
(number of subjects studied) for each parameter. † 50 mg/kg Q8h for 28 days, samples taken 3 hrs after end of 1 hr infusion (Astra Report 815-04 AC025-1). ‡ 90 mg/kg Q12hr for 28 days, samples taken 1 hr after end of 2 hr infusion (Hengge et al., 1993). Distribution In vitro studies have shown that 14% to 17% of foscarnet is protein bound at plasma drug concentrations of 1 μM to 1,000 μM. The foscarnet terminal half-life determined by urinary excretion was 87.5 ± 41.8 hours, possibly due to release of foscarnet from bone.
Postmortem data on several patients in European clinical trials provide evidence that foscarnet does accumulate in bone in humans; however, the extent to which this occurs has not been determined. Special Populations Adults with Impaired Renal Function: The pharmacokinetic properties of foscarnet have been determined in a small group of adult subjects with normal and impaired renal function, as summarized in Table 8: TABLE 8: Pharmacokinetic Parameters (mean ± S.D.) After a Single 60 mg/kg Dose of Foscarnet Sodium in 4 Groups * of Adults with Varying Degrees of Renal Function Parameter Group 1 (N=6) Group 2 (N=6) Group 3 (N=6) Group 4 (N=4) Creatinine clearance (mL/min) 108 ± 16 68 ± 8 34 ± 9 20 ± 4 Foscarnet CL (mL/min/kg) 2.13 ± 0.71 1.33 ± 0.43 0.46 ± 0.14 0.43 ±
0.26Foscarnet half-life (hr) 1.93 ± 0.12 3.35 ± 0.87 13.0 ± 4.05 25.3 ± 18.7 * Group 1 patients had normal renal function defined as a creatinine clearance (CrCl) of > 80 mL/min, Group 2 CrCl was 50 mL/min to 80 mL/min, Group 3 CrCl was 25 mL/min to 49 mL/min and Group 4 CrCl was 10 mL/min to 24 mL/min. Total systemic clearance (CL) of foscarnet decreased and half-life increased with diminishing renal function (as expressed by creatinine clearance). Based on these observations, it is necessary to modify the dosage of foscarnet in patients with renal impairment (see DOSAGE AND ADMINISTRATION ).
Drug Interaction The pharmacokinetics of foscarnet and ganciclovir were not altered in 13 patients receiving either concomitant therapy or daily alternating therapy for maintenance of CMV disease. There is no clinically significant interaction with zidovudine (AZT), or probenecid.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Foscarnet Sodium Injection, 6000 mg/250 mL (24 mg/mL) is clear, colorless solution. It is available as follows: Strength Each Unit of Sale 6,000 mg/250 mL (24 mg/mL) NDC 70121-1744-1 1 Single-dose Intravenous Bag in an Overwrap NDC 70121-1744-7 Unit of 10 NDC 70121-1744-2 Unit of 12 Store at 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature]. Single-dose.
Discard unused portion. Protect from excessive heat (above 40°C) and from freezing. If refrigerated or exposed to temperatures below the freezing point, precipitation may occur.
By keeping the infusion bag at room temperature with repeated shaking, the precipitate can be brought into solution again. Foscarnet sodium injection should be used only if the infusion bag and its seal(s) are intact, a vacuum is present, and the solution is clear and colorless. Do not remove the infusion bag from the overwrap until ready for use.
To report SUSPECTED ADVERSE REACTIONS, contact Amneal Pharmaceuticals LLC at 1-877-835-5472 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch. Manufactured by: Amneal Pharmaceuticals Pvt. Ltd.
Mehsana 382165, INDIA Distributed by: Amneal Pharmaceuticals LLC Bridgewater, NJ 08807 Rev. 05-2026-04 1
📋 Description ▾
DESCRIPTION The chemical name of foscarnet sodium is phosphonoformic acid, trisodium salt. Foscarnet sodium, USP is a white to almost white, crystalline powder containing 6 equivalents of water of hydration with an empirical formula of Na 3 CO 5 P.6H 2 O and a molecular weight of 300.04. The structural formula is: Foscarnet sodium injection has the potential to chelate divalent metal ions, such as calcium and magnesium, to form stable coordination compounds.
Foscarnet sodium injection is a sterile, isotonic aqueous, clear, colorless solution for intravenous administration only. Each milliliter of foscarnet sodium injection contains 24 mg of foscarnet sodium hexahydrate in water for injection, USP. Hydrochloric acid may have been added to adjust the pH of the solution to 7.4.
Foscarnet sodium injection contains no preservatives. 1
⚠️ Precautions ▾
PRECAUTIONS General Care must be taken to infuse solutions containing foscarnet sodium only into veins with adequate blood flow to permit rapid dilution and distribution to avoid local irritation (see DOSAGE AND ADMINISTRATION ). Local irritation and ulcerations of penile epithelium have been reported in male patients receiving foscarnet sodium, possibly related to the presence of drug in the urine. Cases of male and female genital irritation/ulceration have been reported in patients receiving foscarnet sodium.
Adequate hydration with close attention to personal hygiene may minimize the occurrence of such events. Due to the sodium content of foscarnet sodium (240 micromoles (5.5 mg) of sodium per mL), avoid foscarnet sodium use when intravenous infusion of a large amount of sodium or water may not be tolerated (e.g., in patients with cardiomyopathy). Foscarnet sodium should also be avoided in patients on a controlled sodium diet.
Hematopoietic System Anemia has been reported in 33% of patients receiving foscarnet sodium in controlled studies. Granulocytopenia has been reported in 17% of patients receiving foscarnet sodium in controlled studies; however, only 1% (2/189) were terminated from these studies because of neutropenia. Information for Patients CMV Retinitis: Patients should be advised that foscarnet sodium is not a cure for CMV retinitis, and that they may continue to experience progression of retinitis during or following treatment.
They should be advised to have regular ophthalmologic examinations. Mucocutaneous Acyclovir-Resistant HSV Infections: Patients should be advised that foscarnet sodium is not a cure for HSV infections. While complete healing is possible, relapse occurs in most patients.
Because relapse may be due to acyclovir-sensitive HSV, sensitivity testing of the viral isolate is advised. In addition, repeated treatment with foscarnet sodium has led to the development of resistance associated with poorer response. In the case of poor therapeutic response, sensitivity testing of the viral isolate also is advised.
Effects on Ability to Drive and Use Machines: Adverse effects such as dizziness and convulsions may occur during foscarnet sodium therapy. Patients who experience seizures, dizziness, somnolence or other adverse reactions that could result in impairment, should be advised to avoid driving or operating machinery. General: Patients should be informed that the major toxicities of foscarnet are renal impairment, electrolyte disturbances, and seizures, and that dose modifications and possibly discontinuation may be required.
The importance of close monitoring while on therapy must be emphasized. Patients should be advised of the importance of reporting to their physicians symptoms of perioral tingling, numbness in the extremities or paresthesias during or after infusion as possible symptoms of electrolyte abnormalities. Patients should also be advised to promptly report any cardiac symptoms.
Should such symptoms occur, the infusion of foscarnet sodium should be stopped, appropriate laboratory samples for assessment of electrolyte concentrations obtained, and a physician consulted before resuming treatment. The rate of infusion must be no more than 1 mg/kg/minute. The potential for renal impairment may be minimized by accompanying foscarnet sodium administration with hydration adequate to establish and maintain a diuresis during dosing.
Drug Interactions A possible drug interaction of foscarnet sodium and intravenous pentamidine has been described. Concomitant treatment of four patients in the United Kingdom with foscarnet sodium and intravenous pentamidine may have caused hypocalcemia; one patient died with severe hypocalcemia. Toxicity associated with concomitant use of aerosolized pentamidine has not been reported.
Because foscarnet sodium can reduce serum levels of ionized calcium, extreme caution is advised when used concurrently with other drugs known to influence serum calcium levels (e.g., int… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers It is not known whether foscarnet sodium is excreted in human milk; however, in lactating rats administered 75 mg/kg, foscarnet sodium was excreted in maternal milk at concentrations three times higher than peak maternal blood concentrations. Because of the potential for serious adverse events in nursing infants, a decision should be made whether to discontinue nursing or discontinue drug, taking into consideration the importance of the drug to the mother. The Centers for Disease Control and Prevention recommend that HIV-infected mothers not breast-feed their infants to avoid risking postnatal transmission of HIV.
🔬 Clinical Studies ▾
CLINICAL TRIALS CMV Retinitis A prospective, randomized, controlled clinical trial (FOS-03) was conducted in 24 patients with AIDS and CMV retinitis comparing treatment with foscarnet sodium to no treatment. Patients received induction treatment of foscarnet sodium, 60 mg/kg every 8 hours for 3 weeks, followed by maintenance treatment with 90 mg/kg/day until retinitis progression (appearance of a new lesion or advancement of the border of a posterior lesion greater than 750 microns in diameter). All diagnoses and determinations of retinitis progression were made from masked reading of retinal photographs.
The 13 patients randomized to treatment with foscarnet sodium had a significant delay in progression of CMV retinitis compared to untreated controls. Median times to retinitis progression from study entry were 93 days (range 21 to > 364) and 22 days (range 7 to 42), respectively. In another prospective clinical trial of CMV retinitis in patients with AIDS (ACTG-915), 33 patients were treated with two to three weeks of foscarnet sodium induction (60 mg/kg TID) and then randomized to either 90 mg/kg/day or 120 mg/kg/day maintenance therapy.
The median times from study entry to retinitis progression were not significantly different between the treatment groups, 96 (range 14 to > 176) days and 140 (range 16 to > 233) days, respectively. In study ACTG 129/FGCRT SOCA study 107 patients with newly diagnosed CMV retinitis were randomized to treatment with foscarnet sodium (induction: 60 mg/kg TID for 2 weeks; maintenance: 90 mg/kg QD) and 127 were randomized to treatment with ganciclovir (induction: 5 mg/kg BID; maintenance: 5 mg/kg QD). The median time to progression on the two drugs was similar (Fos=59 and Gcv=56 days).
Relapsed CMV Retinitis The CMV Retinitis Retreatment Trial (ACTG 228/SOCA CRRT) was a randomized, open-label comparison of foscarnet sodium or ganciclovir monotherapy to the combination of both drugs for the treatment of persistently active or relapsed CMV retinitis in patients with AIDS. Subjects were randomized to one of the three treatments: foscarnet sodium 90 mg/kg BID induction followed by 120 mg/kg QD maintenance (Fos); ganciclovir 5 mg/kg BID induction followed by 10 mg/kg QD maintenance (Gcv); or the combination of the two drugs, consisting of continuation of the subject’s current therapy and induction dosing of the other drug (as above), followed by maintenance with foscarnet sodium 90 mg/kg QD plus ganciclovir 5 mg/kg QD (Cmb).
Assessment of retinitis progression was performed by masked evaluation of retinal photographs. The median times to retinitis progression or death were 39 days for the foscarnet sodium group, 61 days for the ganciclovir group and 105 days for the combination group. For the alternative endpoint of retinitis progression (censoring on death), the median times were 39 days for the foscarnet sodium group, 61 days for the ganciclovir group and 132 days for the combination group.
Due to censoring on death, the latter analysis may overestimate the treatment effect. Treatment modifications due to toxicity were more common in the combination group than in the foscarnet sodium or ganciclovir monotherapy groups (see ADVERSE REACTIONS section ). Mucocutaneous Acyclovir Resistant HSV Infections In a controlled trial, patients with AIDS and mucocutaneous, acyclovir-resistant HSV infection were randomized to either foscarnet sodium (N=8) at a dose of 40 mg/kg TID or vidarabine (N=6) at a dose of 15 mg/kg per day.
Eleven patients were non-randomly assigned to receive treatment with foscarnet sodium because of prior intolerance to vidarabine. Lesions in the eight patients randomized to foscarnet sodium healed after 11 to 25 days; seven of the 11 patients non-randomly treated with foscarnet sodium healed their lesions in 10 to 30 days. Vidarabine was discontinued because of intolerance (N=4) or poor therapeutic response (N=2).
In a second trial, forty AIDS patients and three bone marrow transplant rec… [Excerpted — this section continues on DailyMed.]
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity studies were conducted in rats and mice at oral doses of 500 mg/kg/day and 250 mg/kg/day. Oral bioavailability in unfasted rodents is < 20%. No evidence of oncogenicity was reported at plasma drug levels equal to 1/3 and 1/5, respectively, of those in humans (at the maximum recommended human daily dose) as measured by the area-under-the-time/concentration curve (AUC).
Foscarnet sodium showed genotoxic effects in the BALB/3T3 in vitro transformation assay at concentrations greater than 0.5 mcg/mL and an increased frequency of chromosome aberrations in the sister chromatid exchange assay at 1,000 mcg/mL. A high dose of foscarnet (350 mg/kg) caused an increase in micronucleated polychromatic erythrocytes in vivo in mice at doses that produced exposures (area under curve) comparable to that anticipated clinically.
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL NDC 70121-1744-1 Foscarnet Sodium Injection, 6000 mg/250 mL (24 mg/mL) Intravenous Bag Label Amneal Pharmaceuticals LLC NDC 70121-1744-1 Foscarnet Sodium Injection, 6000 mg/250 mL (24 mg/mL) Pouch Label Amneal Pharmaceuticals LLC NDC 70121-1744-7 Foscarnet Sodium Injection, 6000 mg/250 mL (24 mg/mL) Rx only 10 x 250 mL Carton Label Amneal Pharmaceuticals LLC NDC 70121-1744-2 Foscarnet Sodium Injection, 6000 mg/250 mL (24 mg/mL) Rx only 12 x 250 mL Carton Label Amneal Pharmaceuticals LLC 250ml 1 1 1
Medicare Part D spend CMS · PART D · 2025 (Q1-Q4)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |