
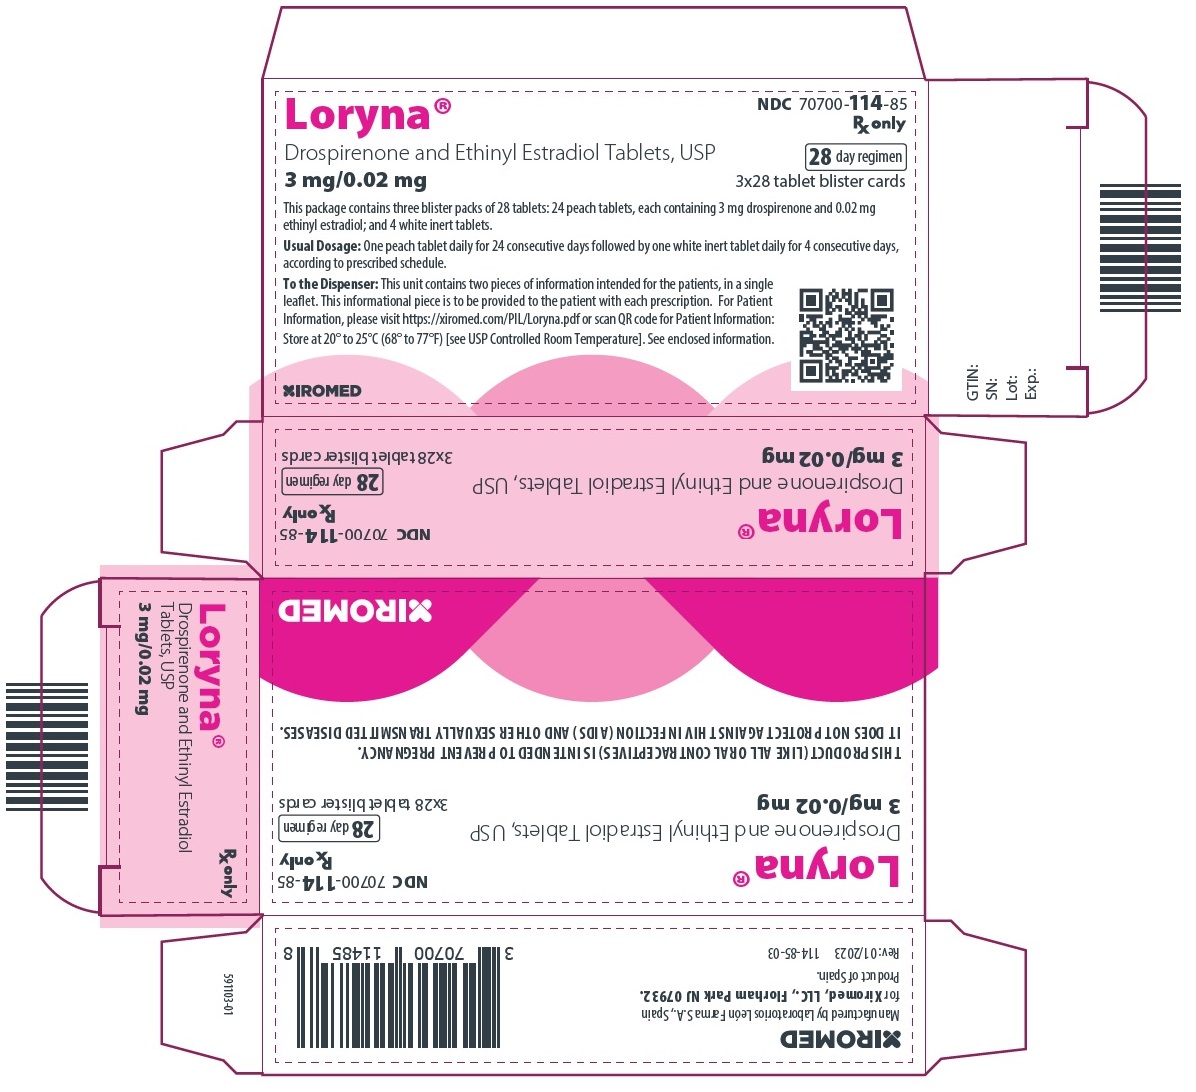
LORYNA Drospirenone and Ethinyl Estradiol Tablets Kit — NDC 70700-114-85 (Billing 70700-0114-85)
This is a package of LORYNA Drospirenone and Ethinyl Estradiol Tablets Kit from Xiromed, LLC., marketed since Jun 2022 and currently FDA-listed; retail pharmacies pay about $0.1909 per unit (NADAC). It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 70700-114-85 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 70700 labeler · 114 product · 85 package
- Package marketed since
- Feb 10, 2023
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC-A, from the NDC)
- 3 7070011485 8
- Medicaid fills, this package
- 130,799 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 060548
- GCN: 26737
- GPI-14 (Medi-Span): 25990002150316
- HICL (First Databank): 022026
- AHFS class code: 68:12.00.00
- RxCUI (RxNorm): 630734
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Progestin class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Oral contraceptives (birth-control pills) containing ethinyl estradiol (an estrogen) and drospirenone (a progestin) are used to prevent pregnancy, treat certain types of acne, and to relieve the symptoms of premenstrual dysphoric disorder (symptoms that occur before the menstrual period each month). Your doctor will select the best medication for your needs. Estrogen and progestin are two female sex hormones. Combinations of estrogen and progestin work by preventing ovulation (the release of eggs from the ovaries). Oral contraceptives treat acne by decreasing the amounts of certain natural sub...
Read the full MedlinePlus article ↗- It's primarily a birth control pill, but it can do more than that. Depending on which brand you have, it may also be approved to treat moderate acne or the emotional and physical s...
- What is this pill actually used for — is it just birth control?
- Take one tablet every day at the same time, following the order printed on your blister pack — the order really matters. If you miss a pill, take it as soon as you remember and kee...
- How do I take this pill and what happens if I miss one?
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.191 | $0.57 / 3 kit |
| Medicaid paysCMS SDUD · 12 mo | $0.3587 | $1.08 / 3 kit |
| Medicare drug plans payPart D · Q2 2026 | $0.3317 | $1.00 / 3 kit |
Where does this data come from?
- CMS NADAC weekly file · file of Oct 7, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q4 2025
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 70700-0114-85 You're viewing this Main listing | 3 BLISTER PACK in 1 CARTON / 1 KIT in 1 BLISTER PACK | 2023-02-10 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Lorynathis 70700-0114-85 | Xiromed, | 1 kit | $0.191 | AB | Availability likely | — |
| Loryna 63629-2336-01 | Bryant | 1 kit | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Oct 7, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Drospirenone / Ethinyl Estradiol inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 8, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Xiromed, LLC. labeler code 70700
- Norethindrone Acetate and Ethinyl Estradiol Kit NDC 70700-101-85
- Clobetasol Propionate .5 mg/g Ointment NDC 70700-106-15
- Acyclovir 50 mg/g Ointment NDC 70700-107-15
- Clobetasol Propionate .5 mg/g Cream NDC 70700-109-15
- Testosterone 20.25 mg/1.25g Gel, Metered NDC 70700-112-21
- Isibloom desogestrel and ethinyl estradiol Kit NDC 70700-113-85
- Syeda Drospirenone and Ethinyl Estradiol Kit NDC 70700-115-85
- ALTAVERA Levonorgestrel and Ethinyl Estradiol Kit NDC 70700-116-85
- Introvale Levonorgestrel and Ethinyl Estradiol Kit NDC 70700-117-87
- Vienva Levonorgestrel and Ethinyl Estradiol Kit NDC 70700-118-85
- Estarylla Norgestimate and ethinyl estradiol Kit NDC 70700-119-85
- Tri-Lo- Estarylla norgestimate and ethinyl estradiol Kit NDC 70700-120-85
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: CIGARETTE SMOKING AND SERIOUS CARDIOVASCULAR EVENTS Cigarette smoking increases the risk of serious cardiovascular events from combination oral contraceptives (COC) use. This risk increases with age, particularly in women over 35 years of age, and with the number of cigarettes smoked. For this reason, COCs should not be used by women who are over 35 years of age and smoke. [See CONTRAINDICATIONS ( 4 )] WARNING: CIGARETTE SMOKING AND SERIOUS CARDIOVASCULAR EVENTS See full prescribing information for complete boxed warning. • Women over 35 years old who smoke should not use d rospirenone and ethinyl estradiol ( 4 ). • Cigarette smoking increases the risk of serious cardiovascular events from combination oral contraceptive (COC) use.
( 4 )
Boxed Warning Section WARNING TO WOMEN WHO SMOKE Do not use drospirenone and ethinyl estradiol tablets if you smoke cigarettes and are over 35 years old. Smoking increases your risk of serious cardiovascular side effects (heart and blood vessel problems) from birth control pills, including death from heart attack, blood clots or stroke. This risk increases with age and the number of cigarettes you smoke.
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Loryna (drospirenone and ethinyl estradiol tablets) is an estrogen/progestin COC, indicated for use by women to: Prevent pregnancy. ( 1.1 ) Treat symptoms of premenstrual dysphoric disorder (PMDD) for women who choose to use an oral contraceptive for contraception. ( 1.2 ) Treat moderate acne for women at least 14 years old only if the patient desires an oral contraceptive for birth control. ( 1.3 )
1.1Oral Contraceptive Loryna (drospirenone and ethinyl estradiol tablets) are indicated for use by women to prevent pregnancy.
1.2Premenstrual Dysphoric Disorder (PMDD) Loryna is also indicated for the treatment of symptoms of premenstrual dysphoric disorder (PMDD) in women who choose to use an oral contraceptive as their method of contraception. The effectiveness of Loryna for PMDD when used for more than three menstrual cycles has not been evaluated. The essential features of PMDD according to the Diagnostic and Statistical Manual-4th edition (DSM-IV) include markedly depressed mood, anxiety or tension, affective lability, and persistent anger or irritability.
Other features include decreased interest in usual activities, difficulty concentrating, lack of energy, change in appetite or sleep, and feeling out of control. Physical symptoms associated with PMDD include breast tenderness, headache, joint and muscle pain, bloating and weight gain. In this disorder, these symptoms occur regularly during the luteal phase and remit within a few days following onset of menses; the disturbance markedly interferes with work or school, or with usual social activities and relationships with others.
Diagnosis is made by healthcare providers according to DSM-IV criteria, with symptomatology assessed prospectively over at least two menstrual cycles. In making the diagnosis, care should be taken to rule out other cyclical mood disorders. Loryna has not been evaluated for the treatment of premenstrual syndrome (PMS).
1.3Acne Loryna tablets are indicated for the treatment of moderate acne vulgaris in women at least 14 years of age, who have no known contraindications to oral contraceptive therapy and have achieved menarche. Drospirenone and ethinyl estradiol tablets should be used for the treatment of acne only if the patient desires an oral contraceptive for birth control.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Take one tablet daily by mouth at the same time every day. ( 2.1 ) • Tablets must be taken in the order directed on the blister pack. ( 2.1 )
2.1How to Take Loryna (drospirenone and ethinyl estradiol tablets) Take one tablet by mouth at the same time every day. The failure rate may increase when pills are missed or taken incorrectly. To achieve maximum contraceptive and PMDD effectiveness, drospirenone and ethinyl estradiol tablets must be taken exactly as directed, in the order directed on the blister pack. Single missed pills should be taken as soon as remembered.
2.2How to Start Loryna (drospirenone and ethinyl estradiol tablets) Instruct the patient to begin taking Loryna tablets either on the first day of her menstrual period (Day 1 Start) or on the first Sunday after the onset of her menstrual period (Sunday Start). Day 1 Start During the first cycle of Loryna tablets use, instruct the patient to take one peach drospirenone and ethinyl estradiol tablet daily, beginning on Day 1 of her menstrual cycle. (The first day of menstruation is Day 1.) She should take one peach Loryna tablet daily for 24 consecutive days, followed by one white inert tablet daily on Days 25 through 28.
Loryna tablets should be taken in the order directed on the package at the same time each day, preferably after the evening meal or at bedtime with some liquid, as needed. Loryna tablets can be taken without regard to meals. If drospirenone and ethinyl estradiol tablets are first taken later than the first day of the menstrual cycle, Loryna tablets should not be considered effective as a contraceptive until after the first 7 consecutive days of product administration.
Instruct the patient to use a non-hormonal contraceptive as back-up during the first 7 days. The possibility of ovulation and conception prior to initiation of medication should be considered. Sunday Start During the first cycle of Loryna tablets use, instruct the patient to take one peach Loryna tablet daily, beginning on the first Sunday after the onset of her menstrual period.
She should take one peach Loryna tablet daily for 24 consecutive days, followed by one white inert tablet daily on Days 25 through 28. Loryna tablets should be taken in the order directed on the package at the same time each day, preferably after the evening meal or at bedtime with some liquid, as needed. Loryna tablets can be taken without regard to meals.
Loryna tablets should not be considered effective as a contraceptive until after the first 7 consecutive days of product administration. Instruct the patient to use a non-hormonal contraceptive as back-up during the first 7 days. The possibility of ovulation and conception prior to initiation of medication should be considered.
The patient should begin her next and all subsequent 28-day regimens of Loryna tablets on the same day of the week that she began her first regimen, following the same schedule. She should begin taking her peach tablets on the next day after ingestion of the last white tablet, regardless of whether or not a menstrual period has occurred or is still in progress. Anytime a subsequent cycle of Loryna tablets are started later than the day following administration of the last white tablet, the patient should use another method of contraception until she has taken a peach Loryna tablets daily for seven consecutive days.
When switching from a different birth control pill When switching from another birth control pill, Loryna tablets should be started on the same day that a new pack of the previous oral contraceptive would have been started. When switching from a method other than a birth control pill When switching from a transdermal patch or vaginal ring, Loryna tablets should be started when the next application would have been due. When switching from an injection, Loryna tablets should be started when the next dose would have been due.
When switching from an intrauterine contraceptive or an implant, Loryn… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Loryna (drospirenone and ethinyl estradiol tablets, USP) is available in blister packs. Each blister pack (28 film-coated tablets) contains in the following order: • 24 peach tablets each containing 3 mg drospirenone (DRSP) and 0.02 mg ethinyl estradiol (EE) • 4 white inert tablets Loryna (drospirenone and ethinyl estradiol tablets) consists of 28 film-coated tablets in the following order ( 3 ): •24 peach tablets, each containing 3 mg drospirenone (DRSP) and 0.02 mg ethinyl estradiol (EE) •4 white inert tablets
⛔ Contraindications ▾
4 CONTRAINDICATIONS Loryna is contraindicated in females who are known to have or develop the following conditions: Renal impairment Adrenal insufficiency A high risk of arterial or venous thrombotic diseases. Examples include women who are known to: - Smoke, if over age 35 [see BOXED WARNING and WARNINGS AND PRECAUTIONS ( 5.1 ) ] - Have deep vein thrombosis or pulmonary embolism, now or in the past [see WARNINGS AND PRECAUTIONS ( 5.1 ) ] - Have cerebrovascular disease [see WARNINGS AND PRECAUTIONS ( 5.1 ) ] - Have coronary artery disease [see WARNINGS AND PRECAUTIONS ( 5.1 ) ] - Have thrombogenic valvular or thrombogenic rhythm diseases of the heart (for example, subacute bacterial endocarditis with valvular disease, or atrial fibrillation) [see WARNINGS AND PRECAUTIONS ( 5.1 ) ] - Have inherited or acquired hypercoagulopathies [see WARNINGS AND PRECAUTIONS ( 5.1 ) ] - Have uncontrolled hypertension [see WARNINGS AND PRECAUTIONS ( 5.6 ) ] - Have diabetes mellitus with vascular disease [see WARNINGS AND PRECAUTIONS ( 5.8 ) ] - Have headaches with focal neurological symptoms or have migraine headaches with or without aura if over age 35 [see WARNINGS AND PRECAUTIONS ( 5.9 ) ] Undiagnosed abnormal uterine bleeding [see WARNINGS AND PRECAUTIONS ( 5.10 )] Current diagnosis of, or history of, breast cancer, which may be hormone-sensitive [ see WARNINGS AND PRECAUTIONS ( 5.3 )] Liver tumors, benign or malignant, or liver disease [ see WARNINGS AND PRECAUTIONS ( 5.4 ) and USE IN SPECIFIC POPULATIONS ( 8.7 )] Pregnancy, because there is no reason to use COCs during pregnancy [ see WARNINGS AND PRECAUTIONS ( 5.11 ) and USE IN SPECIFIC POPULATIONS ( 8.1 )] Use of Hepatitis C drug combinations containing ombitasvir, paritaprevir/ritonavir, with or without dasabuvir due to the potential for ALT elevations [ see WARNINGS AND PRECAUTIONS ( 5.5 ) and DRUG INTERACTIONS ( 7.3 )].
Renal impairment ( 4 ) Adrenal insufficiency ( 4 ) A high risk of arterial or venous thrombotic diseases ( 4 ) Undiagnosed abnormal uterine bleeding ( 4 ) Breast cancer or other estrogen- or progestin-sensitive cancer ( 4 ) Liver tumors or liver disease ( 4 ) Pregnancy ( 4 ) Co-administration with Hepatitis C drug combinations containing ombitasvir, paritaprevir/ritonavir, with or without dasabuvir ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Vascular risks : Stop drospirenone and ethinyl estradiol if a thrombotic event occurs. Stop at least 4 weeks before and through 2 weeks after major surgery. Start no earlier than 4 weeks after delivery, in women who are not breastfeeding.
( 5.1 ) COCs containing DRSP may be associated with a higher risk of venous thromboembolism (VTE) than COCs containing levonorgestrel or some other progestins. Before initiating drospirenone and ethinyl estradiol in a new COC user or a woman who is switching from a contraceptive that does not contain DRSP, consider the risks and benefits of a DRSP-containing COC in light of her risk of a VTE. ( 5.1 ) • Hyperkalemia : DRSP has anti-mineralocorticoid activity.
Do not use in patients predisposed to hyperkalemia. Check serum potassium concentration during the first treatment cycle in women on long-term treatment with medications that may increase serum potassium concentration. ( 5.2 , 7.1 , 7.2 ) • Liver disease : Discontinue drospirenone and ethinyl estradiol if jaundice occurs.
( 5.4 ) • High blood pressure : Do not prescribe drospirenone and ethinyl estradiol for women with uncontrolled hypertension or hypertension with vascular disease. ( 5.5 ) • Carbohydrate and lipid metabolic effects : Monitor prediabetic and diabetic women taking drospirenone and ethinyl estradiol. Consider an alternate contraceptive method for women with uncontrolled dyslipidemia.
( 5.7 ) • Headache : Evaluate significant change in headaches and discontinue drospirenone and ethinyl estradiol if indicated. ( 5.8 ) • Uterine bleeding : Evaluate irregular bleeding or amenorrhea. ( 5.9 )
5.1Thromboembolic Disorders and Other Vascular Problems Stop Drospirenone and ethinyl estradiol if an arterial or venous thrombotic (VTE) event occurs. Based on presently available information on DRSP-containing COCs with 0.03 mg ethinyl estradiol (that is, Yasmin), DRSP-containing COCs may be associated with a higher risk of venous thromboembolism (VTE) than COCs containing the progestin levonorgestrel or some other progestins. Epidemiologic studies that compared the risk of VTE reported that the risk ranged from no increase to a three-fold increase.
Before initiating use of drospirenone and ethinyl estradiol in a new COC user or a woman who is switching from a contraceptive that does not contain DRSP, consider the risks and benefits of a DRSP-containing COC in light of her risk of a VTE. Known risk factors for VTE include smoking, obesity, and family history of VTE, in addition to other factors that contraindicate use of COCs [see CONTRAINDICATIONS ( 4 )]. A number of studies have compared the risk of VTE for users of Yasmin (which contains 0.03 mg of EE and 3 mg of DRSP) to the risk for users of other COCs, including COCs containing levonorgestrel.
Those that were required or sponsored by regulatory agencies are summarized in Table 1 . Table 1: Estimates (Hazard Ratios) of Venous Thromboembolism Risk in Current Users of Yasmin Compared to Users of Oral Contraceptives that Contain Other Progestins Epidemiologic Study (Author, Year of Publication) Population Studied Comparator Product (all are low-dose COCs; with ≤0.04 mg of EE) Hazard Ratio (HR) (95% CI) i3 Ingenix (Seeger 2007) Initiators, including new users a All COCs available in the US during the conduct of the study b HR: 0.9 (0.5-1.6) EURAS (Dinger 2007) Initiators, including new users a All COCS available in Europe during the conduct of the study c Levonorgestrel/EE HR: 0.9 (0.6-1.4) HR: 1 (0.6-1.8) “FDA-funded study” (2011) New users a All users (i.e., initiation and continuing use of study combination hormonal contraception) Other COCs available during the course of the study d Levonorgestrel/0.03 mg EE Other COCs available during the course of the study d Levonorgestrel/0.03 mg EE HR: 1.8 (1.3-2.4) HR: 1.6 (1.1-2.2) HR: 1.7 (1.4-2.1) HR: 1.5 (1.2-1.8) a) “New users” - no use of combination hormonal contraception for at least the prior 6 months b) In… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions with the use of COCs are discussed elsewhere in the labeling: •Serious cardiovascular events and stroke [see BOXED WARNING and WARNINGS AND PRECAUTIONS ( 5.1 ) ] •Vascular events [see WARNINGS AND PRECAUTIONS ( 5.1 ) ] •Liver disease [see WARNINGS AND PRECAUTIONS ( 5.4 ) ] Adverse reactions commonly reported by COC users are: •Irregular uterine bleeding •Nausea •Breast tenderness •Headache The most frequent adverse reactions (≥ 2%) in contraception and acne clinical trials were: headache/migraine (6.7%), menstrual irregularities (4.7%), nausea/vomiting (4.2%), breast pain/tenderness (4.0%) and mood changes (2.2%).
( 6.1 ) The most frequent adverse reactions (≥ 2%) in PMDD clinical trials were: menstrual irregularities (24.9%), nausea (15.8%), headache (13.0%), breast tenderness (10.5%), fatigue (4.2%), irritability (2.8%), decreased libido (2.8%), increased weight (2.5%), and affect lability (2.1%). ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Xiromed, LLC. At 1-844-XIROMED (844-947-6633) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Contraception and Acne Clinical Trials The data provided reflect the experience with the use of drospirenone and ethinyl estradiol in the adequate and well-controlled studies for contraception (N=1,056) and for moderate acne vulgaris (N=536).
For contraception, a Phase 3, multicenter, multinational, open-label study was conducted to evaluate safety and efficacy up to one year in 1,027 women aged 17 to 36 who took at least one dose of drospirenone and ethinyl estradiol. A second Phase 3 study was a single center, open-label, active-controlled study to evaluate the effect of 7 28-day cycles of drospirenone and ethinyl estradiol on carbohydrate metabolism, lipids and hemostasis in 29 women aged 18 to 35. For acne, two multicenter, double-blind, randomized, placebo-controlled studies, in 536 women aged 14 to 45 with moderate acne vulgaris who took at least one dose of drospirenone and ethinyl estradiol, evaluated the safety and efficacy during up to 6 cycles.
The adverse reactions seen across the 2 indications overlapped, and are reported using the frequencies from the pooled dataset. The most common adverse reactions (≥ 2% of users) were: headache/migraine (6.7%), menstrual irregularities (including vaginal hemorrhage [primarily spotting] and metrorrhagia (4.7%), nausea/vomiting (4.2%), breast pain/tenderness (4%) and mood changes (mood swings, depression, depressed mood and affect lability) (2.2%). PMDD Clinical Trials Safety data from trials for the indication of PMDD are reported separately due to differences in study design and setting in the Contraception and Acne studies as compared to the PMDD clinical program.
Two (one parallel and one crossover designed) multicenter, double-blind, randomized, placebo-controlled trials for the secondary indication of treating the symptoms of PMDD evaluated safety and efficacy of drospirenone and ethinyl estradiol during up to 3 cycles among 285 women aged 18–42, diagnosed with PMDD and who took at least one dose of drospirenone and ethinyl estradiol. Common adverse reactions (≥ 2% of users) were: menstrual irregularities (including vaginal hemorrhage [primarily spotting] and metrorrhagia) (24.9%), nausea (15.8%), headache (13.0%), breast tenderness (10.5%), fatigue (4.2%), irritability (2.8%), decreased libido (2.8%), increased weight (2.5%), and affect lability (2.1%).
Adverse Reactions (≥1%) Leading to Study Discontinuation: Contraception Clinical Trials Of 1,056 women, 6.6% discontinued from the clinical trials due to an adverse reaction; the most frequent adverse reactions leading to discontinu… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Consult the labeling of all concurrently-used drugs to obtain further information about interactions with hormonal contraceptives or the potential for enzyme alterations. Drugs or herbal products that induce certain enzymes (for example, CYP3A4) may decrease the effectiveness of COCs or increase breakthrough bleeding. Counsel patients to use a back-up or alternative method of contraception when enzyme inducers are used with COCs.
( 7.1 )
7.1Effects of Other Drugs on Combined Oral Contraceptives Substances diminishing the efficacy of COCs: Drugs or herbal products that induce certain enzymes, including cytochrome P450 3A4 (CYP3A4), may decrease the effectiveness of COCs or increase breakthrough bleeding. Some drugs or herbal products that may decrease the effectiveness of hormonal contraceptives include phenytoin, barbiturates, carbamazepine, bosentan, felbamate, griseofulvin, oxcarbazepine, rifampin, topiramate and products containing St. John’s wort.
Interactions between oral contraceptives and other drugs may lead to breakthrough bleeding and/or contraceptive failure. Counsel women to use an alternative method of contraception or a back-up method when enzyme inducers are used with COCs, and to continue back-up contraception for 28 days after discontinuing the enzyme inducer to ensure contraceptive reliability. Substances increasing the plasma concentrations of COCs: Co-administration of atorvastatin and certain COCs containing EE increase AUC values for EE by approximately 20%.
Ascorbic acid and acetaminophen may increase plasma EE concentrations, possibly by inhibition of conjugation. Concomitant administration of moderate or strong CYP3A4 inhibitors such as azole antifungals (e.g., ketoconazole, itraconazole, voriconazole, fluconazole), verapamil, macrolides (e.g., clarithromycin, erythromycin), diltiazem, and grapefruit juice can increase the plasma concentrations of the estrogen or the progestin or both. In a clinical drug-drug interaction study conducted in premenopausal women, once daily co-administration of DRSP 3 mg/EE 0.02 mg containing tablets with strong CYP3A4 inhibitor, ketoconazole 200 mg twice daily for 10 days resulted in a moderate increase of DRSP systemic exposure.
The exposure of EE was increased mildly [see WARNINGS AND PRECAUTIONS ( 5.2 ) and CLINICAL PHARMACOLOGY ( 12.3 )]. Human immunodeficiency virus (HIV)/Hepatitis C virus (HCV) protease inhibitors and non-nucleoside reverse transcriptase inhibitors: Significant changes (increase or decrease) in the plasma concentrations of estrogen and progestin have been noted in some cases of co-administration with HIV/HCV protease inhibitors or with non-nucleoside reverse transcriptase inhibitors. Antibiotics: There have been reports of pregnancy while taking hormonal contraceptives and antibiotics, but clinical pharmacokinetic studies have not shown consistent effects of antibiotics on plasma concentrations of synthetic steroids.
7.2Effects of Combined Oral Contraceptives on Other Drugs COCs containing EE may inhibit the metabolism of other compounds. COCs have been shown to significantly decrease plasma concentrations of lamotrigine, likely due to induction of lamotrigine glucuronidation. This may reduce seizure control; therefore, dosage adjustments of lamotrigine may be necessary.
Consult the labeling of the concurrently-used drug to obtain further information about interactions with COCs or the potential for enzyme alterations. COCs Increasing the Plasma Concentrations of CYP450 Enzymes: In clinical studies, administration of a hormonal contraceptive containing EE did not lead to any increase or only to a weak increase in plasma concentrations of CYP3A4 substrates (e.g., midazolam) while plasma concentrations of CYP2C19 substrates (e.g., omeprazole and voriconazole) and CYP1A2 substrates (e.g., theophylline and tizanidine) can have a weak or moderate increase.
Clinical studies did not indicate an inhibitory potential of DRSP towards hu… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Nursing Mothers: Not recommended; can decrease milk production. ( 8.3 )
8.1Pregnancy Risk Summary There is no use for contraception in pregnancy; therefore, Loryna should be discontinued during pregnancy. Epidemiologic studies and meta-analyses have not found an increased risk of genital or non-genital birth defects (including cardiac anomalies and limb-reduction defects) following exposure to CHCs before conception or during early pregnancy. In the U.S.
General population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4 percent and 15 to 20 percent, respectively. Data Human Data A retrospective database study of women in Norway, that included 44,734 pregnancies of which 368 were women who inadvertently too DRSP/EE during the first trimester of a pregnancy, found there were no adverse effects on pre-term birth, small for gestational age, or birth weight Z-scores. Post-marketing adverse event data on the use of Loryna in pregnant women suggest that frequencies of miscarriage and congenical anomalies were not higher than the estimated background risk in the general population.
8.2Lactation Risk Summary DRSP is present in human milk. After a single oral administration of 3 mg DRSP/0.03 mg EE tablets, DRSP concentration in breast milk over the 24-h period ranged from 1.4 to 7.0 ng/mL, with a mean ± standard deviation value of 3.7 ± 1.9 ng/mL. The estimated mean infant dose was 0.003 mg/day, which is about 0.1% of maternal dose (see Data).
There is limited information on the effects of Loryna on the breast-fed infant. CHCs can reduce milk production in breast- feeding females. This reduction can occur at any time but is less likely to occur once breast-feeding is well-established.
When possible, advise the nursing female to use other methods of contraception until she discontinues breast-feeding [See also DOSAGE AND ADMINISTRATION ( 2.2 ) ]. The developmental and health benefits of breast-feeding should be considered along with the mother’s clinical need for Loryna and any potential adverse effects on the breast-fed child from Loryna or from the underlying maternal condition. Data Human Data An open-label study evaluated the degree of DRSP transfer into milk within 72 hours following a single oral administration of 3 mg DRSP/0.03 mg EE tablets to 6 healthy lactating women who were 1 week to 3 months post- partum.
DRSP was present in breast milk with a mean Cmax of 13.5 ng/mL, while the mean Cmax in serum of lactating women was 30.8 ng/mL. The DRSP concentration in breast milk over the 24-hour period following dosing ranged from 1.4 to 7.0 ng/mL, with a mean ± standard deviation value of 3.7 ± 1.9 ng/mL. Based on single dose data, the maximal daily infant dose of DRSP was calculated to be 0.003 mg/day, which represented a mean of 0.1% of the maternal dose.
8.3Nursing Mothers When possible, advise the nursing mother to use other forms of contraception until she has weaned her child. Estrogen-containing COCs can reduce milk production in breastfeeding mothers. This is less likely to occur once breastfeeding is well-established; however, it can occur at any time in some women.
Small amounts of oral contraceptive steroids and/or metabolites are present in breast milk. After oral administration of 3 mg DRSP/0.03 mg EE (Yasmin) tablets, about 0.02% of the DRSP dose was excreted into the breast milk of postpartum women within 24 hours. This results in a maximal daily dose of about 0.003 mg DRSP in an infant.
8.4Pediatric Use Safety and efficacy of drospirenone and ethinyl estradiol have been established in women of reproductive age. Efficacy is expected to be the same for postpubertal adolescents under the age of 18 and for users 18 years and older. Use of this product before menarche is not indicated.
8.5Geriatric Use Drospirenone and ethinyl estradiol have not been studied in postmenopausal women and is not indicated in this population.… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There is no use for contraception in pregnancy; therefore, Loryna should be discontinued during pregnancy. Epidemiologic studies and meta-analyses have not found an increased risk of genital or non-genital birth defects (including cardiac anomalies and limb-reduction defects) following exposure to CHCs before conception or during early pregnancy. In the U.S.
General population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4 percent and 15 to 20 percent, respectively. Data Human Data A retrospective database study of women in Norway, that included 44,734 pregnancies of which 368 were women who inadvertently too DRSP/EE during the first trimester of a pregnancy, found there were no adverse effects on pre-term birth, small for gestational age, or birth weight Z-scores. Post-marketing adverse event data on the use of Loryna in pregnant women suggest that frequencies of miscarriage and congenical anomalies were not higher than the estimated background risk in the general population.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and efficacy of drospirenone and ethinyl estradiol have been established in women of reproductive age. Efficacy is expected to be the same for postpubertal adolescents under the age of 18 and for users 18 years and older. Use of this product before menarche is not indicated.
🧓 Geriatric Use ▾
8.5Geriatric Use Drospirenone and ethinyl estradiol have not been studied in postmenopausal women and is not indicated in this population.
🆘 Overdosage ▾
10 OVERDOSAGE There have been no reports of serious ill effects from overdose, including ingestion by children. Overdosage may cause withdrawal bleeding in females and nausea. DRSP is a spironolactone analogue which has anti-mineralocorticoid properties. Serum concentration of potassium and sodium, and evidence of metabolic acidosis, should be monitored in cases of overdose.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action COCs lower the risk of becoming pregnant primarily by suppressing ovulation. Other possible mechanisms may include cervical mucus changes that inhibit sperm penetration and the endometrial changes that reduce the likelihood of implantation.
12.2Pharmacodynamics Drospirenone is a spironolactone analogue with anti-mineralocorticoid and antiandrogenic activity. The estrogen in drospirenone and ethinyl estradiol is ethinyl estradiol. Contraception Two studies evaluated the effect of 3 mg DRSP / 0.02 mg EE combinations on the suppression of ovarian activity as assessed by measurement of follicle size via transvaginal ultrasound and serum hormone (progesterone and estradiol) analyses during two treatment cycles (21-day active tablet period plus 7-day pill-free period).
More than 90% of subjects in these studies demonstrated ovulation inhibition. One study compared the effect of 3 mg DRSP/0.02 mg EE combinations with two different regimens (24-day active tablet period plus 4-day pill-free period vs. 21-day active tablet period plus 7-day pill-free period) on the suppression of ovarian activity during two treatment cycles.
During the first treatment cycle, there were no subjects (0/49, 0%) taking the 24-day regimen who ovulated compared to 1 subject (1/50, 2%) using the 21-day regimen. After intentionally introduced dosing errors (3 missed active tablets on Days 1 to 3) during the second treatment cycle, there was 1 subject (1/49, 2%) taking the 24-day regimen who ovulated compared to 4 subjects (4/50, 8%) using the 21-day regimen. Acne Acne vulgaris is a skin condition with a multifactorial etiology including androgen stimulation of sebum production.
While the combination of EE and DRSP increases sex hormone binding globulin (SHBG) and decreases free testosterone, the relationship between these changes and a decrease in the severity of facial acne in otherwise healthy women with this skin condition has not been established. The impact of the antiandrogenic activity of DRSP on acne is not known.
12.3Pharmacokinetics Absorption The absolute bioavailability of DRSP from a single entity tablet is about 76%. The absolute bioavailability of EE is approximately 40% as a result of presystemic conjugation and first-pass metabolism. The absolute bioavailability of drospirenone and ethinyl estradiol, which is a combination tablet of DRSP and EE stabilized by betadex as a clathrate (molecular inclusion complex), has not been evaluated.
The bioavailability of EE is similar when dosed via a betadex clathrate formulation compared to when it is dosed as a free steroid. Serum concentrations of DRSP and EE reached peak levels within 1 to 2 hours after administration of drospirenone and ethinyl estradiol. The pharmacokinetics of DRSP are dose proportional following single doses ranging from 1 to 10 mg.
Following daily dosing of drospirenone and ethinyl estradiol, steady state DRSP concentrations were observed after 8 days. There was about 2 to 3 fold accumulation in serum C max and AUC (0–24h) values of DRSP following multiple dose administration of drospirenone and ethinyl estradiol (see Table 2 ). For EE, steady-state conditions are reported during the second half of a treatment cycle.
Following daily administration of drospirenone and ethinyl estradiol, serum C max and AUC (0–24h) values of EE accumulate by a factor of about 1.5 to 2 (see Table 2 ). TABLE 2: Pharmacokinetic Parameters of Drospirenone and Ethinyl Estradiol (DRSP 3 mg and EE 0.02 mg) DRSP Cycle / Day No. of Subjects C max a (ng/mL) T max b (h) AUC(0–24h) a (ng•h/mL) t 1/2 a (h) 1/1 23 38.4 (25) 1.5 (1–2) 268 (19) NA c 1/21 23 70.3 (15) 1.5 (1–2) 763 (17) 30.8 (22) EE Cycle / Day No. of Subjects C max a (pg/mL) T max b (h) AUC(0–24h) a (pg•h/mL) t 1/2 a (h) 1/1 23 32.8 (45) 1.5 (1–2) 108 (52) NA c 1/21 23 45.1 (35) 1.5 (1–2) 220 (57) NA c a) geometric mean (geometric coefficient of variation) b) median (range) c) NA = Not available Fo… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action COCs lower the risk of becoming pregnant primarily by suppressing ovulation. Other possible mechanisms may include cervical mucus changes that inhibit sperm penetration and the endometrial changes that reduce the likelihood of implantation.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied Loryna (drospirenone and ethinyl estradiol tablets, USP) 3 mg/0.02 mg are available as follows: Each blister card contains 24 active tablets and 4 inactive tablets. The 24 active tablets are peach, round, film-coated, debossed with SZ on one side and U2 on the other side. The 4 inert tablets are white, round, film-coated, debossed with SZ on one side and J1 on the other side. NDC 70700-114-85, one carton containing 3 blister cards
16.2Storage Store at 20° to 25º C (68° to 77º F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Loryna (drospirenone and ethinyl estradiol tablets, USP) provides an oral contraceptive regimen consisting of 24 peach active film-coated tablets each containing 3 mg of drospirenone and 0.02 mg of ethinyl estradiol and 4 white inert film coated tablets. Each active tablet consists of black iron oxide, croscarmellose sodium, lactose fast flo, polyethylene glycol, magnesium stearate, polysorbate 80, polyvinyl alcohol, povidone K-30, pregelatinized starch, talc, titanium dioxide, red iron oxide, yellow iron oxide.
The inert tablet consists of andydrous lactose, magnesium stearate, povidone K-30, polyethylene glycol, polyvinyl alcohol-part hydrolyzed, talc and titanium dioxide. Drospirenone (6R,7R,8R,9S,10R,13S,14S,15S,16S,17S)-1,3’,4’,6,6a,7,8,9,10,11,12,13,14,15,15a,16-hexadecahydro-10,13-dimethylspiro-[17H-dicyclopropa- [6,7:15,16] cyclopenta[a]phenanthrene-17,2’(5H)-furan]-3,5’(2H)-dione) is a synthetic progestational compound and has a molecular weight of 366.5 and a molecular formula of C 24 H 30 O 3 . Ethinyl estradiol (19-nor-17α-pregna 1,3,5(10)-triene-20-yne-3, 17-diol) is a synthetic estrogenic compound and has a molecular weight of 296.4 and a molecular formula of C 20 H 24 O 2 .
The structural formulas are as follows: Structure formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling. (Patient Information) •Counsel patients that cigarette smoking increases the risk of serious cardiovascular events from COC use, and that women who are over 35 years old and smoke should not use COCs. •Counsel patients that the increased risk of VTE compared to non-users of COCs is greatest after initially starting a COC or restarting (following a 4-week or greater pill-free interval) the same or a different COC. •Counsel patients about the information regarding the risk of VTE with DRSP-containing COCs compared to COCs that contain levonorgestrel or some other progestins. •Counsel patients that Loryna tablets do not protect against HIV-infection (AIDS) and other sexually transmitted diseases. •Counsel patients on Warnings and Precautions associated with COCs. •Counsel patients that Loryna tablets contain DRSP.
Drospirenone may increase potassium. Patients should be advised to inform their healthcare provider if they have kidney, liver or adrenal disease because the use of Loryna tablets in the presence of these conditions could cause serious heart and health problems. They should also inform their healthcare provider if they are currently on daily, long-term treatment (NSAIDs, potassium-sparing diuretics, potassium supplementation, ACE inhibitors, angiotensin-II receptor antagonists, heparin or aldosterone antagonists) for a chronic condition or taking strong CYP3A4 inhibitors. •Inform patients that Loryna tablets are not indicated during pregnancy.
If pregnancy occurs during treatment with Loryna tablets, instruct the patient to stop further intake . •Counsel patients to take one tablet daily by mouth at the same time every day. Instruct patients what to do in the event pills are missed. See “WHAT TO DO IF YOU MISS PILLS” section in FDA-APPROVED PATIENT LABELING . •Counsel patients to use a back-up or alternative method of contraception when enzyme inducers are used with COCs. •Counsel patients who are breastfeeding or who desire to breastfeed that COCs may reduce breast milk production.
This is less likely to occur if breastfeeding is well established. •Counsel any patient who starts COCs postpartum, and who has not yet had a period, to use an additional method of contraception until she has taken a peach tablet for 7 consecutive days. •Counsel patients that amenorrhea may occur. Rule out pregnancy in the event of amenorrhea in two or more consecutive cycles. LORYNA® is a registered trademark of Xiromed Pharma España, S.L.
Manufactured by Laboratorios Leon Farma S.A., Spain For Xiromed, LLC., Florham Park, NJ 07932 Product of Spain PI-114-04 Rev. 07/2023
🍼 Nursing Mothers ▾
8.3Nursing Mothers When possible, advise the nursing mother to use other forms of contraception until she has weaned her child. Estrogen-containing COCs can reduce milk production in breastfeeding mothers. This is less likely to occur once breastfeeding is well-established; however, it can occur at any time in some women.
Small amounts of oral contraceptive steroids and/or metabolites are present in breast milk. After oral administration of 3 mg DRSP/0.03 mg EE (Yasmin) tablets, about 0.02% of the DRSP dose was excreted into the breast milk of postpartum women within 24 hours. This results in a maximal daily dose of about 0.003 mg DRSP in an infant.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption The absolute bioavailability of DRSP from a single entity tablet is about 76%. The absolute bioavailability of EE is approximately 40% as a result of presystemic conjugation and first-pass metabolism. The absolute bioavailability of drospirenone and ethinyl estradiol, which is a combination tablet of DRSP and EE stabilized by betadex as a clathrate (molecular inclusion complex), has not been evaluated.
The bioavailability of EE is similar when dosed via a betadex clathrate formulation compared to when it is dosed as a free steroid. Serum concentrations of DRSP and EE reached peak levels within 1 to 2 hours after administration of drospirenone and ethinyl estradiol. The pharmacokinetics of DRSP are dose proportional following single doses ranging from 1 to 10 mg.
Following daily dosing of drospirenone and ethinyl estradiol, steady state DRSP concentrations were observed after 8 days. There was about 2 to 3 fold accumulation in serum C max and AUC (0–24h) values of DRSP following multiple dose administration of drospirenone and ethinyl estradiol (see Table 2 ). For EE, steady-state conditions are reported during the second half of a treatment cycle.
Following daily administration of drospirenone and ethinyl estradiol, serum C max and AUC (0–24h) values of EE accumulate by a factor of about 1.5 to 2 (see Table 2 ). TABLE 2: Pharmacokinetic Parameters of Drospirenone and Ethinyl Estradiol (DRSP 3 mg and EE 0.02 mg) DRSP Cycle / Day No. of Subjects C max a (ng/mL) T max b (h) AUC(0–24h) a (ng•h/mL) t 1/2 a (h) 1/1 23 38.4 (25) 1.5 (1–2) 268 (19) NA c 1/21 23 70.3 (15) 1.5 (1–2) 763 (17) 30.8 (22) EE Cycle / Day No. of Subjects C max a (pg/mL) T max b (h) AUC(0–24h) a (pg•h/mL) t 1/2 a (h) 1/1 23 32.8 (45) 1.5 (1–2) 108 (52) NA c 1/21 23 45.1 (35) 1.5 (1–2) 220 (57) NA c a) geometric mean (geometric coefficient of variation) b) median (range) c) NA = Not available Food Effect The rate of absorption of DRSP and EE following single administration of a formulation similar to drospirenone and ethinyl estradiol was slower under fed (high fat meal) conditions with the serum C max being reduced about 40% for both components.
The extent of absorption of DRSP, however, remained unchanged. In contrast, the extent of absorption of EE was reduced by about 20% under fed conditions. Distribution DRSP and EE serum concentrations decline in two phases.
The apparent volume of distribution of DRSP is approximately 4 L/kg and that of EE is reported to be approximately 4 to 5 L/kg. DRSP does not bind to SHBG or corticosteroid binding globulin (CBG) but binds about 97% to other serum proteins. Multiple dosing over 3 cycles resulted in no change in the free fraction (as measured at trough concentrations).
EE is reported to be highly but non-specifically bound to serum albumin (approximately 98.5 %) and induces an increase in the serum concentrations of both SHBG and CBG. EE induced effects on SHBG and CBG were not affected by variation of the DRSP dosage in the range of 2 to 3 mg. Metabolism The two main metabolites of DRSP found in human plasma were identified to be the acid form of DRSP generated by opening of the lactone ring and the 4,5-dihydrodrospirenone-3-sulfate, formed by reduction and subsequent sulfation.
These metabolites were shown not to be pharmacologically active. Drospirenone is also subject to oxidative metabolism catalyzed by CYP3A4. EE has been reported to be subject to significant gut and hepatic first-pass metabolism.
Metabolism of EE and its oxidative metabolites occur primarily by conjugation with glucuronide or sulfate. CYP3A4 in the liver is responsible for the 2-hydroxylation which is the major oxidative reaction. The 2-hydroxy metabolite is further transformed by methylation and glucuronidation prior to urinary and fecal excretion.
Excretion DRSP serum concentrations are characterized by a terminal disposition phase half-life of approximately 30 hours after both single and multiple dose regimen… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Drospirenone is a spironolactone analogue with anti-mineralocorticoid and antiandrogenic activity. The estrogen in drospirenone and ethinyl estradiol is ethinyl estradiol. Contraception Two studies evaluated the effect of 3 mg DRSP / 0.02 mg EE combinations on the suppression of ovarian activity as assessed by measurement of follicle size via transvaginal ultrasound and serum hormone (progesterone and estradiol) analyses during two treatment cycles (21-day active tablet period plus 7-day pill-free period).
More than 90% of subjects in these studies demonstrated ovulation inhibition. One study compared the effect of 3 mg DRSP/0.02 mg EE combinations with two different regimens (24-day active tablet period plus 4-day pill-free period vs. 21-day active tablet period plus 7-day pill-free period) on the suppression of ovarian activity during two treatment cycles.
During the first treatment cycle, there were no subjects (0/49, 0%) taking the 24-day regimen who ovulated compared to 1 subject (1/50, 2%) using the 21-day regimen. After intentionally introduced dosing errors (3 missed active tablets on Days 1 to 3) during the second treatment cycle, there was 1 subject (1/49, 2%) taking the 24-day regimen who ovulated compared to 4 subjects (4/50, 8%) using the 21-day regimen. Acne Acne vulgaris is a skin condition with a multifactorial etiology including androgen stimulation of sebum production.
While the combination of EE and DRSP increases sex hormone binding globulin (SHBG) and decreases free testosterone, the relationship between these changes and a decrease in the severity of facial acne in otherwise healthy women with this skin condition has not been established. The impact of the antiandrogenic activity of DRSP on acne is not known.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Oral Contraceptive Clinical Trial In the primary contraceptive efficacy study of drospirenone and ethinyl estradiol (3 mg DRSP/0.02 mg EE) of up to 1 year duration, 1,027 subjects were enrolled and completed 11,480 28-day cycles of use. The age range was 17 to 36 years. The racial demographic was: 87.8% Caucasian, 4.6% Hispanic, 4.3% Black, 1.2% Asian, and 2.1% other.
Women with a BMI greater than 35 were excluded from the trial. The pregnancy rate (Pearl Index) was 1.41 (95% CI [0.73, 2.47]) per 100 woman-years of use based on 12 pregnancies that occurred after the onset of treatment and within 14 days after the last dose of drospirenone and ethinyl estradiol in women 35 years of age or younger during cycles in which no other form of contraception was used.
14.2Premenstrual Dysphoric Disorder Clinical Trials Two multicenter, double-blind, randomized, placebo-controlled studies were conducted to evaluate the effectiveness of drospirenone and ethinyl estradiol in treating the symptoms of PMDD. Women aged 18 to 42 who met DSM-IV criteria for PMDD, confirmed by prospective daily ratings of their symptoms, were enrolled. Both studies measured the treatment effect of drospirenone and ethinyl estradiol using the Daily Record of Severity of Problems scale, a patient-rated instrument that assesses the symptoms that constitute the DSM-IV diagnostic criteria.
The primary study was a parallel group design that included 384 evaluable reproductive-aged women with PMDD who were randomly assigned to receive drospirenone and ethinyl estradiol or placebo treatment for 3 menstrual cycles. The supportive study, a crossover design, was terminated prematurely prior to achieving recruitment goals due to enrollment difficulties. A total of 64 women of reproductive age with PMDD were treated initially with drospirenone and ethinyl estradiol or placebo for up to 3 cycles followed by a washout cycle and then crossed over to the alternate medication for 3 cycles.
Efficacy was assessed in both studies by the change from baseline during treatment using a scoring system based on the first 21 items of the Daily Record of Severity of Problems. Each of the 21 items was rated on a scale from 1 (not at all) to 6 (extreme); thus a maximum score of 126 was possible. In both trials, women who received drospirenone and ethinyl estradiol had statistically significantly greater improvement in their Daily Record of Severity of Problems scores.
In the primary study, the average decrease (improvement) from baseline was 37.5 points in women taking drospirenone and ethinyl estradiol, compared to 30.0 points in women taking placebo.
14.3Acne Clinical Trials In two multicenter, double-blind, randomized, placebo-controlled studies, 889 subjects, ages 14 to 45 years, with moderate acne received drospirenone and ethinyl estradiol or placebo for six 28-day cycles. The primary efficacy endpoints were the percent change in inflammatory lesions, non-inflammatory lesions, total lesions, and the percentage of subjects with a "clear" or "almost clear" rating on the Investigator's Static Global Assessment (ISGA) scale on day 15 of cycle 6, as presented in Table 3 : Table 3: Efficacy Results for Acne Trials Evaluated at day 15 of cycle 6, last observation carried forward for the Intent to treat population Study 1 Study 2 Drospirenone and Ethinyl Estradiol N=228 Placebo N=230 Drospirenone and Ethinyl Estradiol N=218 Placebo N=213 ISGA Success Rate 35 (15%) 10 (4%) 46 (21%) 19 (9%) Inflammatory Lesions Mean Baseline Count Mean Absolute (%) Reduction 33 15 (48%) 33 11 (32%) 32 16 (51%) 32 11 (34%) Non-inflammatory Lesions Mean Baseline Count Mean Absolute (%) Reduction 47 18 (39%) 47 10 (18%) 44 17 (42%) 44 11 (26%) Total lesions Mean Baseline Count Mean Absolute (%) reduction 80 33 (42%) 80 21 (25%) 76 33 (46%) 76 22 (31%)
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility In a 24 month oral carcinogenicity study in mice dosed with 10 mg/kg/day DRSP alone or 1 + 0.01, 3 + 0.03 and 10 + 0.1 mg/kg/day of DRSP and EE, 0.1 to 2 times the exposure (AUC of DRSP) of women taking a contraceptive dose, there was an increase in carcinomas of the harderian gland in the group that received the high dose of DRSP alone. In a similar study in rats given 10 mg/kg/day DRSP alone or 0.3 + 0.003, 3 + 0.03 and 10 + 0.1 mg/kg/day DRSP and EE, 0.8 to 10 times the exposure of women taking a contraceptive dose, there was an increased incidence of benign and total (benign and malignant) adrenal gland pheochromocytomas in the group receiving the high dose of DRSP.
Mutagenesis studies for DRSP were conducted in vivo and in vitro and no evidence of mutagenic activity was observed.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility In a 24 month oral carcinogenicity study in mice dosed with 10 mg/kg/day DRSP alone or 1 + 0.01, 3 + 0.03 and 10 + 0.1 mg/kg/day of DRSP and EE, 0.1 to 2 times the exposure (AUC of DRSP) of women taking a contraceptive dose, there was an increase in carcinomas of the harderian gland in the group that received the high dose of DRSP alone. In a similar study in rats given 10 mg/kg/day DRSP alone or 0.3 + 0.003, 3 + 0.03 and 10 + 0.1 mg/kg/day DRSP and EE, 0.8 to 10 times the exposure of women taking a contraceptive dose, there was an increased incidence of benign and total (benign and malignant) adrenal gland pheochromocytomas in the group receiving the high dose of DRSP.
Mutagenesis studies for DRSP were conducted in vivo and in vitro and no evidence of mutagenic activity was observed.
📚 References ▾
15 REFERENCES 1. Seeger, J.D., Loughlin, J., Eng, P.M., Clifford, C.R., Cutone, J., and Walker, A.M. (2007).
Risk of thromboembolism in women taking ethinylestradiol/drospirenone and other oral contraceptives. Obstet Gynecol 110 , 587-593. 2.
Dinger, J.C., Heinemann, L.A., and Kuhl-Habich, D. (2007). The safety of a drospirenone-containing oral contraceptive: final results from the European Active Surveillance Study on oral contraceptives based on 142,475 women-years of observation.
Contraception 75 , 344-354. 3. Combined hormonal contraceptives (CHCs) and the risk of cardiovascular endpoints.
Sidney, S. (primary author), http://www.fda.gov/downloads/Drugs/DrugSafety/UCM277384.pdf, accessed Oct 27, 2011. 4.
Lidegaard, O., Lokkegaard, E., Svendsen, A.L., and Agger, C. (2009). Hormonal contraception and risk of venous thromboembolism: national follow-up study.
BMJ 339 , b2890. 5. Lidegaard, O., Nielsen, L.H., Skovlund, C.W., Skjeldestad, F.E., and Lokkegaard, E.
(2011). Risk of venous thromboembolism from use of oral contraceptives containing different progestogens and oestrogen doses: Danish cohort study, 2001-9. BMJ 343 , d6423.
6. van Hylckama Vlieg, A., Helmerhorst, F.M., Vandenbroucke, J.P., Doggen, C.J., and Rosendaal, F.R. (2009). The venous thrombotic risk of oral contraceptives, effects of oestrogen dose and progestogen type: results of the MEGA case-control study.
BMJ 339 , b2921. 7. Dinger, J., Assmann, A., Mohner, S., and Minh, T.D.
(2010). Risk of venous thromboembolism and the use of dienogest- and drospirenone-containing oral contraceptives: results from a German case-control study. J Fam Plann Reprod Health Care 36 , 123-129.
8. Jick, S.S., and Hernandez, R.K. (2011).
Risk of non-fatal venous thromboembolism in women using oral contraceptives containing drospirenone compared with women using oral contraceptives containing levonorgestrel: case-control study using United States claims data. BMJ 342 , d2151. 9.
Parkin, L., Sharples, K., Hernandez, R.K., and Jick, S.S. (2011). Risk of venous thromboembolism in users of oral contraceptives containing drospirenone or levonorgestrel: nested case-control study based on UK General Practice Research Database.
BMJ 342 , d2139.
📄 Patient Package Insert ▾
FDA Approved Patient Labeling Guide for Using Loryna ® (drospirenone and ethinyl estradiol tablets) 3 mg/0.02 mg Boxed Warning Section WARNING TO WOMEN WHO SMOKE Do not use drospirenone and ethinyl estradiol tablets if you smoke cigarettes and are over 35 years old. Smoking increases your risk of serious cardiovascular side effects (heart and blood vessel problems) from birth control pills, including death from heart attack, blood clots or stroke. This risk increases with age and the number of cigarettes you smoke.
FDA Approved Patient Labeling Guide Birth control pills help to lower the chances of becoming pregnant when taken as directed. They do not protect against HIV infection (AIDS) and other sexually transmitted diseases. What is Loryna?
Loryna is a birth control pill. It contains two female hormones, a synthetic estrogen called ethinyl estradiol and a progestin called drospirenone. The progestin drospirenone may increase potassium.
Therefore, you should not take Loryna if you have kidney, liver or adrenal disease because this could cause serious heart and health problems. Other drugs may also increase potassium. If you are currently on daily, long-term treatment for a chronic condition with any of the medications below, you should consult your healthcare provider about whether Loryna is right for you, and during the first month that you take Loryna, you should have a blood test to check your potassium level. •NSAIDs (ibuprofen [Motrin, Advil], naproxen [Aleve and others] when taken long-term and daily for treatment of arthritis or other problems) •Potassium-sparing diuretics (spironolactone and others) •Potassium supplementation •ACE inhibitors (Capoten, Vasotec, Zestril and others) •Angiotensin-II receptor antagonists (Cozaar, Diovan, Avapro and others) •Heparin •Aldosterone antagonists Loryna may also be taken to treat premenstrual dysphoric disorder (PMDD) if you choose to use the Pill for birth control.
Unless you have already decided to use the Pill for birth control, you should not start Loryna to treat your PMDD because there are other medical therapies for PMDD that do not have the same risks as the Pill. PMDD is a mood disorder related to the menstrual cycle. PMDD significantly interferes with work or school, or with usual social activities and relationships with others.
Symptoms include markedly depressed mood, anxiety or tension, mood swings, and persistent anger or irritability. Other features include decreased interest in usual activities, difficulty concentrating, lack of energy, change in appetite or sleep, and feeling out of control. Physical symptoms associated with PMDD may include breast tenderness, headache, joint and muscle pain, bloating and weight gain.
These symptoms occur regularly before menstruation starts and go away within a few days following the start of the period. Diagnosis of PMDD should be made by healthcare providers. You should only use Loryna for treatment of PMDD if you: • Have already decided to use oral contraceptives for birth control, and • Have been diagnosed with PMDD by your healthcare provider.
Loryna has not been shown to be effective for the treatment of premenstrual syndrome (PMS), a less serious set of symptoms occurring before menstruation. If you or your healthcare provider believe you have PMS, you should take Loryna only if you want to prevent pregnancy; and not for the treatment of PMS. Loryna may also be taken to treat moderate acne if all of the following are true: •Your healthcare provider says it is safe for you to use Loryna. •You are at least 14 years old. •You have started having menstrual periods. •You want to use a birth control pill to prevent pregnancy.
How Well Does Loryna Work? Your chance of getting pregnant depends on how well you follow the directions for taking your birth control pills. The better you follow the directions, the less chance you have of getting pregnant.
Based on the results of one clinical study, 1 to 2 women out of 100 women, may g… [Excerpted — this section continues on DailyMed.]
📄 Recent Major Changes ▾
RECENT MAJOR CHANGES Warnings and Precautions ( 5.3 ) 4/2022
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL PRINCIPAL DISPLAY PACKAGE LABEL - Carton NDC 70700-114-85 Loryna (Drospirenone and Ethinyl Estradiol Tablets, USP) 3 mg/0.02 mg Rx Only
Medicaid utilization & spend
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | ✓ Available |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |