
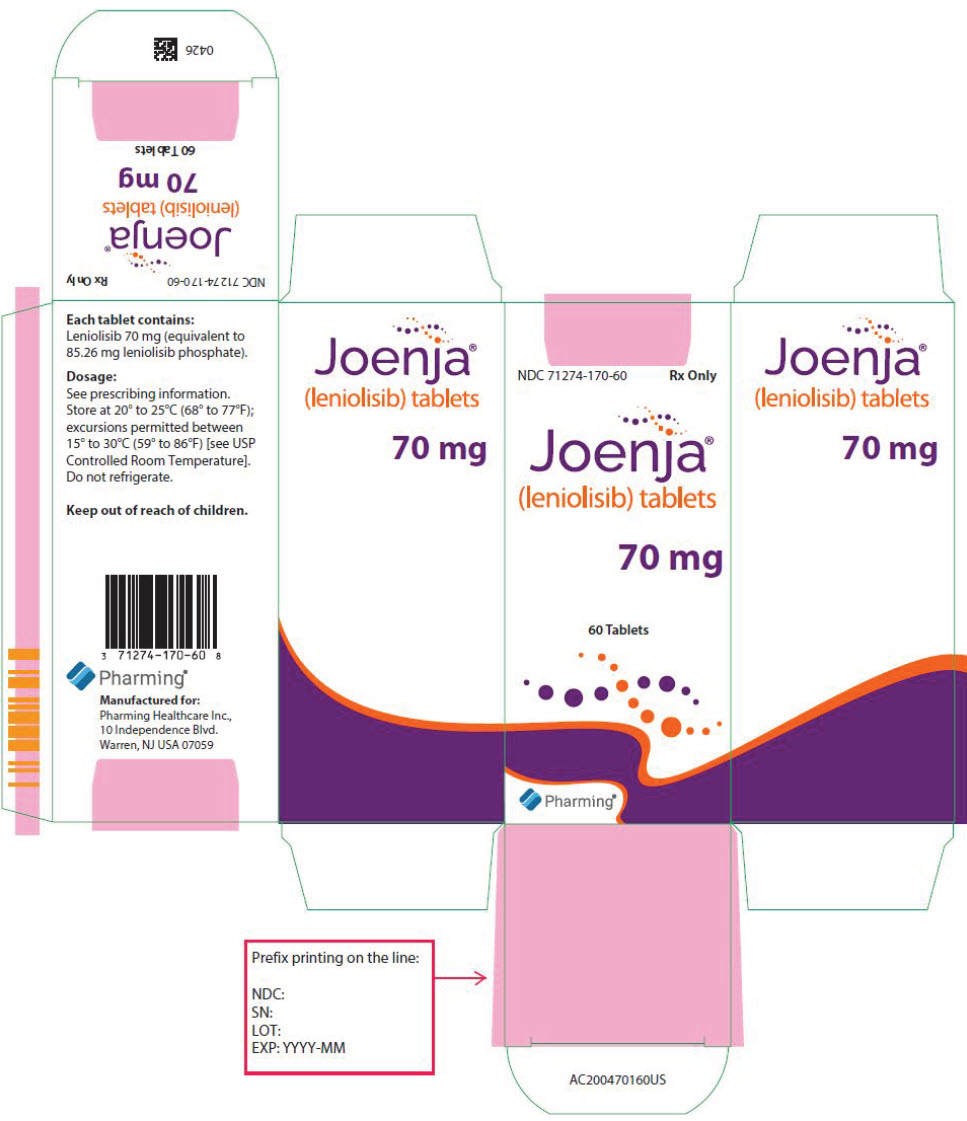
Joenja Leniolisib 70 mg Tablet, Film Coated, 60-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Kinase Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Leniolisib is used to treat adults and children 12 years of age and older who have activated phosphoinositide 3-kinase delta syndrome (APDS; an genetic condition that decreases the activity of the immune system and can result in recurrent infections, swollen lymph nodes and spleen, and a certain type of lymphoma [a type of blood cancer]). Leniolisib is in a class of medications called kinase inhibitors. It works by blocking the signals that cause abnormalities in the immune system, which improves the functions of the immune system.
Read the full MedlinePlus article ↗- APDS is a rare inherited immune disorder caused by a gene change that makes a specific enzyme — called PI3K-delta — work in overdrive. That throws your immune cells out of balance...
- What exactly is APDS, and how does Joenja help?
- Timing does matter in the sense that you should take your two daily doses about 12 hours apart — for example, morning and evening — to keep steady levels in your body. The good new...
- Does it matter what time of day I take Joenja, or whether I eat first?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Leniolisib — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $887.58 | $53,255.09 / 60 tablets |
| Medicare drug plans payPart D · Q2 2026 | $810.76 | $48,645.43 / 60 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Joenja 70 mgthis 71274-0170-60 | Pharming | 60 tablets | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 8653092 ↗ | Drug substance | — | Feb 19, 2032 |
| Code | What it grants | Expires |
|---|---|---|
| NCE | New Chemical Entity (5-year) | Mar 24, 2028 |
| ODE-430 | Orphan Drug Exclusivity (7-year) | Mar 24, 2030 |
Is there a generic version of JOENJA 70 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 71274-0170-60 You're viewing this | 1 BOTTLE, PLASTIC in 1 CARTON (71274-170-60) / 60 TABLET, FILM COATED in 1 BOTTLE, PLASTIC | 2023-03-29 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE JOENJA is indicated for the treatment of activated phosphoinositide 3-kinase delta (PI3Kδ) syndrome (APDS) in adult and pediatric patients 12 years of age and older. JOENJA is a kinase inhibitor indicated for the treatment of activated phosphoinositide 3-kinase delta (PI3Kδ) syndrome (APDS) in adult and pediatric patients 12 years of age and older. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Verify pregnancy status in females of reproductive potential prior to initiating treatment. ( 2.1 , 5.1 ) Recommended dosage: 70 mg administered orally twice daily approximately 12 hours apart, with or without food, in adult and pediatric patients 12 years of age and older and weighing ≥ 45kg. ( 2.2 )
2.1Testing Prior to Treatment with JOENJA Verify pregnancy status in females of reproductive potential prior to initiating treatment with JOENJA [see Warnings and Precautions ( 5.1 ), and Use in Specific Populations ( 8.1 , 8.3 )] .
2.2Recommended Dosage and Administration The recommended dosage of JOENJA in adult and pediatric patients 12 years of age and older weighing 45 kg or greater is 70 mg administered orally twice daily approximately 12 hours apart, with or without food. There is no recommended dosage for patients weighing less than 45 kg. Advise patients that if a dose is missed by more than 6 hours, wait and take the next dose at the usual time.
Advise patients that if vomiting occurs within 1 hour after taking JOENJA, take JOENJA as soon as possible. If vomiting occurs more than 1 hour after dosing, wait and take the next dose at the usual time.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets: 70 mg (leniolisib), yellow, oval-shaped, biconvex, bevelled edge film-coated tablet debossed with "70" on one side and "LNB" on the other side. Tablets: 70 mg leniolisib ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Embryo-Fetal Toxicity: JOENJA may cause fetal harm. Advise patients of the potential risk to a fetus and to use effective contraception. ( 5.1 , 8.1 , 8.3 ) Vaccinations: Live, attenuated vaccinations may be less effective if administered during JOENJA treatment.
( 5.2 ) Risk of Hypersensitivty Reactions Including Anaphylaxis: Hypersensitivity reactions including anaphlyaxis have been reported in the postmarketing setting. If hypersensitivity reactions occur, discontinue JOENJA and institute appropriate therapy. ( 5.3 )
5.1Embryo-Fetal Toxicity Based on findings in animals, JOENJA may cause fetal harm when administered to a pregnant woman. Administration of leniolisib to rats and rabbits during the period of organogenesis caused embryo-fetal toxicity including malformations at exposures that were 2-6 times higher than the maximum recommended human dose (MRHD) in APDS patients based on AUC comparisons. Verify the pregnancy status of patients of reproductive potential prior to starting treatment.
Advise pregnant women of the potential risk to a fetus. Advise females of reproductive potential to use highly effective methods of contraception during treatment and for 1 week after the last dose [see Dosage and Administration ( 2.1 ), Use in Specific Populations ( 8.1 , 8.3 )] .
5.2Vaccinations Live, attenuated vaccinations may be less effective if administered during JOENJA treatment.
5.3Risk of Hypersensitivity Reactions, Including Anaphylaxis Hypersensitivity reaction(s), including anaphylaxis, have been reported in postmarketing setting. If a clinically significant hypersensitivity reaction occurs, discontinue JOENJA and institute appropriate therapy [see Adverse Reactions (6.2) ].
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: Risk of Hypersensitivity Reactions, Including Anaphylaxis [see Warnings and Precautions (5.3) ] Most common adverse reactions (incidence > 10%) were headache, sinusitis, and atopic dermatitis. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Pharming Healthcare Inc. at 1-800-930-5221 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The safety of JOENJA reflects exposure based on 38 adult and pediatric patients 12 years of age and older with activated phosphoinositide 3-kinase delta (PI3Kδ) syndrome (APDS) from the placebo-controlled portion of Study 2201 [see Clinical Studies ( 14 )] and additional open-label clinical safety data.
Thirty-seven of 38 patients received JOENJA 70 mg orally twice daily for at least 25 weeks and 66% were exposed for 96 weeks or longer. Median duration of JOENJA treatment was approximately 2 years, and 4 patients had more than 5 years of JOENJA exposure. The data below are based on the 12-week, placebo-controlled portion of Study 2201 in which either JOENJA 70 mg (N=21) or placebo (N=10) was administered twice daily to patients with APDS.
Demographics of the patients who participated in this study are summarized in Clinical Studies [see Clinical Studies ( 14 )] . Table 1 presents the number of patients and incidence, rounded to the nearest percent, of adverse reactions that occurred in 2 or more patients treated with JOENJA and for which the incidence in patients treated with JOENJA was greater than the incidence in patients treated with placebo. The most common adverse reactions (> 10%) were headache, sinusitis, and atopic dermatitis.
Table 1 Adverse Reactions Reported by 2 or More JOENJA-Treated Patients and More Frequently than Placebo Adverse Reactions JOENJA N=21 n (%) Placebo N=10 n (%) 1 Dermatitis atopic: including dermatitis atopic and eczema 2 Tachycardia: including tachycardia and sinus tachycardia Headache 5 (24) 2 (20) Sinusitis 4 (19) 0 Dermatitis atopic 1 3 (14) 0 Tachycardia 2 2 (10) 0 Diarrhea 2 (10) 0 Fatigue 2 (10) 1 (10) Pyrexia 2 (10) 0 Back pain 2 (10) 0 Neck pain 2 (10) 0 Alopecia 2 (10) 0 Specific Adverse Reactions Laboratory Abnormalities Seven (33%) patients receiving JOENJA developed an absolute neutrophil count (ANC) between 500 and 1500 cells/microL.
No patients developed an ANC < 500 cells/microL and there were no reports of infection associated with neutropenia. Weight Increase In the open-label clinical trial (n=37), five patients (14%) experienced weight gain. Some patients became overweight or obese.
6.2Postmarketing Experience The following adverse reactions have been identified during postapproval use of JOENJA. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Immune System Disorders : hypersensitivity (anaphylaxis)
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Strong CYP3A4 Inhibitors: Avoid concomitant use. ( 7.1 ) Strong and Moderate CYP3A4 Inducers: Avoid concomitant use. ( 7.1 ) BCRP, OATP1B1, and OATP1B3 Substrates: Avoid concomitant use. ( 7.2 )
7.1Effects of Other Drugs on JOENJA Strong CYP3A4 Inhibitors Concomitant use of JOENJA with strong CYP3A4 inhibitors should be avoided. JOENJA is a substrate of CYP3A4. Leniolisib exposure was increased 2-fold when co-administered with itraconazole, a strong CYP3A4 inhibitor [see Clinical Pharmacology ( 12.3 )] .
Strong and Moderate CYP3A4 Inducers Concomitant use of JOENJA with strong and moderate CYP3A4 inducers should be avoided. JOENJA is a substrate of CYP3A4. Concomitant use of strong and moderate CYP3A4 inducers may result in reduced leniolisib exposure and thus reduced leniolisib efficacy [see Clinical Pharmacology ( 12.3 )] .
7.2Effects of JOENJA on Other Drugs BCRP, OATP1B1, and OATP1B3 Substrates Concomitant use of JOENJA with BCRP, OATP1B1, and OATP1B3 substrates should be avoided. JOENJA is an inhibitor of BCRP, OATP1B1, and OATP1B3 transporters. Administration of JOENJA increases exposure of BCRP, OATP1B1, and OATP1B3 substrates [see Clinical Pharmacology (12.3) ] , which may increase the risk of adverse reactions related to these substrates.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Advise women not to breastfeed. ( 8.2 ) Hepatic impairment: Use in patients with moderate to severe hepatic impairment is not recommended. ( 8.6 )
8.1Pregnancy Risk Summary JOENJA can cause fetal harm based on findings from animal studies. There are no available data on JOENJA use in pregnant women to inform a drug-associated risk of major birth defects, miscarriage, or other adverse maternal or fetal outcomes. In animal reproduction studies, oral administration of leniolisib to pregnant rats and rabbits during the period of organogenesis at exposures approximately 2-6 times the MRHD on an AUC basis, produced embryofetal toxicity including malformations ( see Data ).
Advise pregnant women of the potential risk to a fetus. The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage of clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data Leniolisib was administered orally to pregnant rats at doses of 10, 30, and 120 mg/kg/day during the period of organogenesis from gestation Day 6 to Day 17. Leniolisib at a dose of 120 mg/kg/day was associated with decreased fetal body weight, visceral and skeletal variations, and external, visceral, and skeletal malformations (eye bulge, microphthalmia, anophthalmia, and reduction in orbital socket size) in the presence of maternal toxicity (decrease in body weight gain) at exposures approximately 6 times the MRHD on an AUC basis.
No developmental toxicity was observed in rats at an exposure approximately 2 times the MRHD (on an AUC basis at a maternal oral dose of 30 mg/kg/day). Leniolisib was administered orally to pregnant rabbits at doses of 10, 30, and 100 mg/kg/day during the period of organogenesis from gestation Day 7 to Day 20. Leniolisib at a dose of 100 mg/kg/day was associated with skeletal variations as well as visceral and skeletal malformations (microphthalmia and reduction in orbital socket size) in the presence of maternal toxicity (decrease in body weight gain) at exposures approximately 2 times the MRHD on an AUC basis.
No developmental toxicity was observed in rabbits at an exposure approximately 0.3 times the MRHD (on an AUC basis at a maternal oral dose of 30 mg/kg/day). In a pre- and postnatal developmental toxicity study, leniolisib was administered orally to pregnant rats at oral doses of 10, 30, and 90 mg/kg/day from gestation day 7 through postnatal day 21. Leniolisib at a dose of 90 mg/kg/day (approximately 5 times the exposure at the MRHD on an AUC basis) was associated with a slight decrease in the percentage of pups born that survived 21 days postpartum (lactation index) and decreased pup body weights were observed prior to weaning.
8.2Lactation Risk Summary There are no data on the presence of leniolisib or its metabolites in human milk or the effects on the breastfed infant or milk production. Leniolisib is present in rat milk ( see Data ). When a drug is present in animal milk, it is likely that the drug will be present in human milk.
Because of the potential for serious adverse reactions from leniolisib in the breastfed child, advise women not to breastfeed during treatment with JOENJA and for 1 week after the last dose. Data Animal Data Leniolisib was present in the milk of lactating rats administered oral doses of 10, 30, and 90 mg/kg/day from gestation day 7 through postnatal day 21. Leniolisib concentrations were approximately 2- to 3-fold higher in milk than in maternal plasma.
The concentration of leniolisib in animal milk does not necessarily predict the concentration of drug in human milk.
8.3Females and Males of Reproductive Potential Based on findings from animal studies, JOENJA may cause fetal harm when administered to a pregnant woman [see…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary JOENJA can cause fetal harm based on findings from animal studies. There are no available data on JOENJA use in pregnant women to inform a drug-associated risk of major birth defects, miscarriage, or other adverse maternal or fetal outcomes. In animal reproduction studies, oral administration of leniolisib to pregnant rats and rabbits during the period of organogenesis at exposures approximately 2-6 times the MRHD on an AUC basis, produced embryofetal toxicity including malformations ( see Data ).
Advise pregnant women of the potential risk to a fetus. The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage of clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data Leniolisib was administered orally to pregnant rats at doses of 10, 30, and 120 mg/kg/day during the period of organogenesis from gestation Day 6 to Day 17. Leniolisib at a dose of 120 mg/kg/day was associated with decreased fetal body weight, visceral and skeletal variations, and external, visceral, and skeletal malformations (eye bulge, microphthalmia, anophthalmia, and reduction in orbital socket size) in the presence of maternal toxicity (decrease in body weight gain) at exposures approximately 6 times the MRHD on an AUC basis.
No developmental toxicity was observed in rats at an exposure approximately 2 times the MRHD (on an AUC basis at a maternal oral dose of 30 mg/kg/day). Leniolisib was administered orally to pregnant rabbits at doses of 10, 30, and 100 mg/kg/day during the period of organogenesis from gestation Day 7 to Day 20. Leniolisib at a dose of 100 mg/kg/day was associated with skeletal variations as well as visceral and skeletal malformations (microphthalmia and reduction in orbital socket size) in the presence of maternal toxicity (decrease in body weight gain) at exposures approximately 2 times the MRHD on an AUC basis.
No developmental toxicity was observed in rabbits at an exposure approximately 0.3 times the MRHD (on an AUC basis at a maternal oral dose of 30 mg/kg/day). In a pre- and postnatal developmental toxicity study, leniolisib was administered orally to pregnant rats at oral doses of 10, 30, and 90 mg/kg/day from gestation day 7 through postnatal day 21. Leniolisib at a dose of 90 mg/kg/day (approximately 5 times the exposure at the MRHD on an AUC basis) was associated with a slight decrease in the percentage of pups born that survived 21 days postpartum (lactation index) and decreased pup body weights were observed prior to weaning.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of JOENJA for the treatment of activated phosphoinositide 3-kinase delta syndrome have been established in pediatric patients 12 years of age and older. Use of JOENJA for this indication is supported by evidence from an adequate and well-controlled study in adult and pediatric patients 12 years of age and older [see Clinical Studies ( 14 )] . There is no recommended dosage for pediatric patients 12 years of age and older who weigh less than 45 kg [see Dosage and Administration ( 2.2 )] .
The safety and effectiveness of JOENJA have not been established in pediatric patients below the age of 12 years. Juvenile Animal Toxicity Data Studies were conducted with leniolisib in juvenile rats starting at postnatal day (PND) 7 (the equivalent of a human newborn) to PND 77 (the equivalent of a human adult). Death was observed in juvenile rats that received 90 mg/kg/day, approximately 2-4 times the MRHD on an AUC basis and occurred primarily during the pre-weaning period (PND 9 to PND 15).
Changes in the onset of puberty (delays in males and accelerations in females) were observed in juvenile rats at equal to or greater than 30 mg/kg/day leniolisib, which is one half to equivalent to, the MRHD on an AUC basis. A no effect dose level was identified at an exposure approximately 0.2 times the MRHD on an AUC basis.
🧓 Geriatric Use ▾
8.5Geriatric Use Because clinical studies of JOENJA did not include any patients 65 years of age and older, it cannot be determined whether they respond differently from younger adult patients.
🆘 Overdosage ▾
10 OVERDOSAGE If overdosage occurs, monitor the patient for any signs or symptoms of adverse reactions. Treatment of overdose with JOENJA consists of general supportive measures including monitoring of vital signs as well as observation of the clinical status of the patient.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Leniolisib inhibits PI3K-delta by blocking the active binding site of PI3K-delta. In cell-free isolated enzyme assays, leniolisib was selective for PI3K-delta over PI3K-alpha (28-fold), PI3K-beta (43-fold), and PI3K-gamma (257-fold), as well as the broader kinome. In cell-based assays, leniolisib reduced pAkt pathway activity and inhibited proliferation and activation of B and T cell subsets.
Gain-of-function variants in the gene encoding the p110-delta catalytic subunit or loss of function variants in the gene encoding the p85-alpha regulatory subunit each cause hyperactivity of PI3K-delta. Leniolisib inhibits the signalling pathways that lead to increased production of PIP3, hyperactivity of the downstream mTOR/Akt pathway, and to the dysregulation of B and T cells.
12.2Pharmacodynamics Ex vivo pharmacodynamics of leniolisib [proportion of phosphorylated Akt (pAkt)-positive B cells] were assessed intra-individually at 10, 30, and 70 mg twice daily for 4 weeks at each dose level in patients with APDS. Within the explored dose range, higher leniolisib plasma concentrations were generally associated with higher reduction of pAkt-positive B cells and higher doses were associated with a slightly higher peak reduction as well as more sustained reduction. Treatment with JOENJA 70 mg twice a day at steady state is estimated to produce time-averaged reduction of pAkt-positive B cells by approximately 80%.
12.3Pharmacokinetics The systemic drug exposure (AUC and C max ) of leniolisib increased dose proportionally within the studied range of doses (20 to 140 mg twice a day dosing and single doses of 10 to 400 mg). During twice daily dosing approximately 12 hours apart, leniolisib accumulates approximately 1.4-fold (range of 1.0 to 2.2) in achieving steady-state, consistent with an effective half-life (t 1/2 ) of approximately 7 hours. Steady state drug concentrations can be expected to be reached after approximately 2 to 3 days of JOENJA treatment.
The pharmacokinetics of leniolisib are similar between healthy participants and APDS patients. Absorption In a placebo controlled, single and multiple ascending dose study in healthy participants, leniolisib median time to maximum plasma concentration (T max ) occurred at about 1 hour postdose. T max appeared independent of dose and was not altered after multiple oral doses.
Food is unlikely to have a clinically meaningful effect on the systemic exposure of leniolisib during JOENJA treatment. Distribution The systemic decay in leniolisib plasma concentration over time is bi-exponential, indicating a distribution delay towards peripheral tissues. The apparent terminal elimination t 1/2 is approximately 10 hours.
The volume of distribution of leniolisib is estimated to be
28.5L in patients with APDS. Leniolisib was highly bound (94.5%) to plasma proteins. Elimination The mean recovery of total 14C-radioactivity following a single oral dose of 70 mg 14C-leniolisib was 92.5% (67.0% and 25.5% recovered via feces and urine, respectively) 168 hours postdose.
Unchanged leniolisib (6.32%) was the predominant drug-related material recovered in urine. Metabolism Leniolisib was 60% metabolized by the liver, with CYP3A4 being the most predominant enzyme involved (95.4%) in the primary oxidative metabolism of leniolisib with minor contribution from other enzymes (3.5% CYP3A5, 0.7% CYP1A2 and 0.4% CYP2D6). Intestinal secretion by BCRP as well as extrahepatic CYP1A1 cannot be excluded as excretion routes.
Specific Populations Pediatric Patients Following a single 70 mg oral dose of leniolisib in APDS patients, leniolisib systemic exposures were comparable between pediatric patients (12 to 17 years of age) and adults (≥ 18 years of age), with median T max (ranging from 1 to 5 hours) reached approximately 3 hours post-dose in patients 12 to 17 years of age. The observed difference in the median T max between pediatric patients (12 to 17 years of age) and ad…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Leniolisib inhibits PI3K-delta by blocking the active binding site of PI3K-delta. In cell-free isolated enzyme assays, leniolisib was selective for PI3K-delta over PI3K-alpha (28-fold), PI3K-beta (43-fold), and PI3K-gamma (257-fold), as well as the broader kinome. In cell-based assays, leniolisib reduced pAkt pathway activity and inhibited proliferation and activation of B and T cell subsets.
Gain-of-function variants in the gene encoding the p110-delta catalytic subunit or loss of function variants in the gene encoding the p85-alpha regulatory subunit each cause hyperactivity of PI3K-delta. Leniolisib inhibits the signalling pathways that lead to increased production of PIP3, hyperactivity of the downstream mTOR/Akt pathway, and to the dysregulation of B and T cells.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING JOENJA is available in 70 mg tablet: yellow, oval-shaped, biconvex, bevelled edge film-coated tablet debossed with "70" on one side and "LNB" on the other side. It is supplied in bottles with a child-resistant cap of 60 tablets (NDC 71274-170-60). Store at 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature]. Do not refrigerate.
📋 Description ▾
11 DESCRIPTION Leniolisib is a kinase inhibitor. The chemical name for leniolisib phosphate is 1-[(3 S )-3-[[5,6,7,8-Tetrahydro-6-[6-methoxy-5-(trifluoromethyl)-3-pyridinyl]pyrido[4,3- d ]pyrimidin-4-yl]amino]-1-pyrrolidinyl]-1-propanone phosphate (1:1). Leniolisib phosphate has the following structural formula: The molecular formula is C 21 H 25 F 3 N 6 O 2 •H 3 PO 4 and the molecular weight is 450.47 g/mol for the free base, 548.46 g/mol for the phosphate salt.
Leniolisib phosphate is a white to yellowish to yellowish-greenish powder. The aqueous solubility of leniolisib phosphate is pH dependent with decreasing solubility observed with increasing pH. JOENJA film-coated tablets are for oral administration.
Each tablet contains 70 mg of leniolisib (equivalent to 85.26 mg leniolisib phosphate) with the following inactive ingredients: colloidal silicon dioxide, hydroxypropyl methylcellulose, lactose monohydrate, magnesium stearate, microcrystalline cellulose, and sodium starch glycolate. The tablet filmcoating contains hydroxypropyl methylcellulose, iron oxide red, iron oxide yellow, polyethylene glycol, talc, and titanium dioxide. Structural Formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Embryo-Fetal Toxicity Advise pregnant women of the potential risk to a fetus. Advise females of reproductive potential to inform their healthcare provider of a known or suspected pregnancy. [see Warnings and Precautions ( 5.1 ) and Use in Specific Populations ( 8.1 , 8.3 )] . Advise females of reproductive potential to use highly effective contraceptive during treatment with JOENJA and for 1 week after the last dose [see Warnings and Precautions ( 5.1 ) and Use in Specific Populations ( 8.3 )] .
Vaccinations Instruct patients to inform the healthcare providers that they are taking JOENJA prior to a potential vaccination [see Warnings and Precautions (5.2) ]. Risk of Hypersensitivity Reactions, Including Anaphylaxis Advise patients to discontinue JOENJA and to seek immediate medical attention if they develop any signs and symptoms of serious allergic reactions [see Warnings and Precautions (5.3) ]. Lactation Advise women not to breastfeed during treatment with JOENJA and for 1 week after the last dose [see Use in Specific Populations ( 8.2 )] .
Administration Advise patients JOENJA may be taken with or without food [see Dosage and Administration ( 2.2 )] . Instruct patients that if they miss a dose by more than 6 hours, skip the missed dose. Advise patients to take the next dose as scheduled [see Dosage and Administration ( 2.2 )] .
Instruct patients that if vomiting occurs within 1 hour after taking JOENJA, take a dose as soon as possible [see Dosage and Administration ( 2.2 )] . Manufactured for: Pharming Healthcare Inc., 10 Independence Blvd. Warren, NJ USA 07059 JOENJA is a trademark of Pharming Intellectual Property B.V. ©2025 Pharming Technologies B.V.
All rights reserved. AC2004703US-0850