
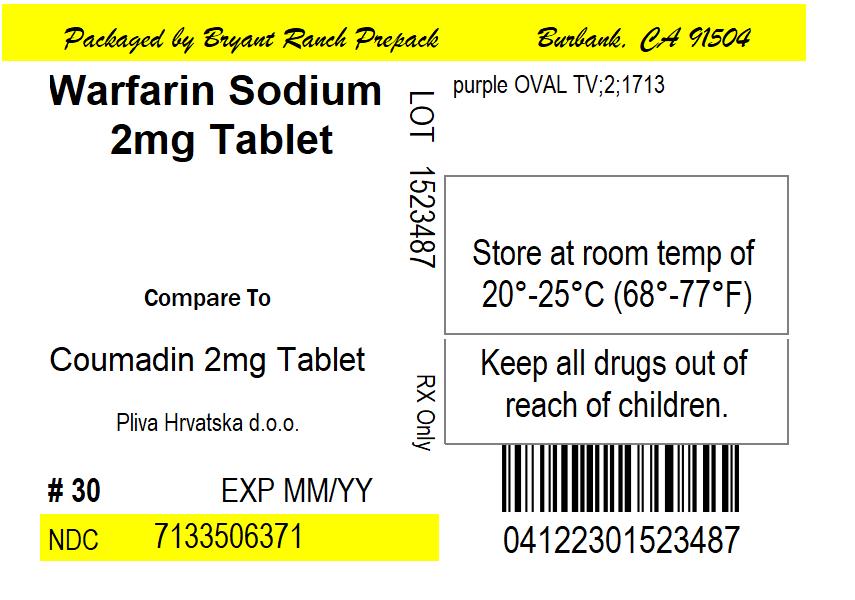
Warfarin Sodium 2 mg Tablet, 50-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Vitamin K Antagonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Warfarin's effect on your blood varies a lot depending on your diet, other medications, your health, and even genetics. The INR blood test measures how long it takes your blood to...
- Why do I need to get blood tests so often while taking warfarin?
- The big one is vitamin K, which is found mostly in leafy green vegetables like spinach, kale, and broccoli. Vitamin K works against warfarin, so if you suddenly eat a lot more or a...
- What foods do I need to watch out for on warfarin?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Warfarin Sodium — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 4AQJ3LG584
A synthetic blue dye combined with aluminum to create a stable colorant. It's used in medicines and supplements to add blue color or create specific shades for product identification and appearance.
-
UNII WZB9127XOA
A synthetic red dye used to color medications and make them easier to identify. It serves as a colorant in tablets, capsules, and liquid formulations.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
7 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.1286 | $6.43 / 50 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Warfarin Sodium 2 mg 00093-1713-01 | Teva | 100 tablets | $0.087 | AB | Discontinued | — |
| Jantoven 2 mg 00832-1212-00 | Upsher-Smith | 100 tablets | $0.087 | AB | Availability likely | — |
| Warfarin Sodium 2 mg 62584-0984-01 | American | 100 tablets | $0.087 | AB | Availability likely | — |
| Warfarin Sodium 2 mg 65162-0762-10 | Amneal | 100 tablets | $0.087 | AB | Availability likely | — |
| Warfarin Sodium 2 mg 76282-0328-01 | Exelan | 100 tablets | $0.087 | AB | Availability likely | — |
| Warfarin Sodium 2 mg 43353-0021-30 | Aphena | 30 tablets | — | AB | FDA listed | — |
| Warfarin Sodium 2 mg 50090-1211-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Warfarin Sodium 2 mg 50090-2654-00 | A-S | 30 tablets | — | AB | Discontinued | — |
| Warfarin Sodium 2 mg 50090-7464-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Warfarin Sodium 2 mg 51407-0342-10 | Golden | 1000 tablets | — | AB | FDA listed | — |
| Warfarin Sodium 2 mg 51407-0785-01 | Golden | 100 tablets | — | AB | FDA listed | — |
| Warfarin Sodium 2 mg 51655-0993-52 | Northwind | 30 tablets | — | AB | FDA listed | — |
| Warfarin Sodium 2 mg 51672-4028-00 | Sun | 100 tablets | — | AB | Discontinued | — |
| Warfarin Sodium 2 mg 55154-4695-00 | Cardinal | 10 tablets | — | AB | FDA listed | — |
| Warfarin Sodium 2 mg 67046-1067-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| Warfarin Sodium 2 mg 70518-0255-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Warfarin Sodium 2 mg 70518-2381-00 | REMEDYREPACK | 100 tablets | — | AB | FDA listed | — |
| Warfarin Sodium 2 mgthis 71335-0637-05 | Bryant | 50 tablets | — | AB | Discontinued | — |
| Warfarin Sodium 2 mg 71335-2309-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Warfarin Sodium 2 mg 71610-0462-30 | Aphena | 30 tablets | — | AB | FDA listed | — |
| Warfarin Sodium 2 mg 71610-0574-30 | Aphena | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 71335-0637-01 | 30 TABLET in 1 BOTTLE (71335-0637-1) | 2022-02-09 | Discontinued by firm |
| 71335-0637-02 | 14 TABLET in 1 BOTTLE (71335-0637-2) | 2022-02-09 | Discontinued by firm |
| 71335-0637-03 | 90 TABLET in 1 BOTTLE (71335-0637-3) | 2022-02-09 | Discontinued by firm |
| 71335-0637-04 | 45 TABLET in 1 BOTTLE (71335-0637-4) | 2022-02-09 | Discontinued by firm |
| 71335-0637-05 You're viewing this | 50 TABLET in 1 BOTTLE (71335-0637-5) | 2022-02-09 | Discontinued by firm |
| 71335-0637-06 | 21 TABLET in 1 BOTTLE (71335-0637-6) | 2022-02-09 | Discontinued by firm |
| 71335-0637-07 | 60 TABLET in 1 BOTTLE (71335-0637-7) | 2022-02-09 | Discontinued by firm |
| 71335-0637-08 | 20 TABLET in 1 BOTTLE (71335-0637-8) | 2022-02-09 | Discontinued by firm |
You're viewing one of 8 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 71335-0637-05?
What is the difference between NDC 71335-0637-05 and NDC 71335-0637-02?
What NDC number is used to bill for this package of Warfarin Sodium 2 mg Tablet?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
What does the discontinued status mean for this NDC?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: BLEEDING RISK Warfarin sodium can cause major or fatal bleeding [see Warnings and Precautions ( 5.1 )] . Perform regular monitoring of INR in all treated patients [see Dosage and Administration ( 2.1 )] . Drugs, dietary changes, and other factors affect INR levels achieved with warfarin sodium therapy [see Drug Interactions ( 7 )] .
Instruct patients about prevention measures to minimize risk of bleeding and to report signs and symptoms of bleeding [see Patient Counseling Information ( 17 )] . WARNING: BLEEDING RISK See full prescribing information for complete boxed warning. Warfarin sodium can cause major or fatal bleeding.
( 5.1 ) Perform regular monitoring of INR in all treated patients. ( 2.1 ) Drugs, dietary changes, and other factors affect INR levels achieved with warfarin sodium therapy. ( 7 ) Instruct patients about prevention measures to minimize risk of bleeding and to report signs and symptoms of bleeding.
( 17 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Warfarin sodium tablets are indicated for: Prophylaxis and treatment of venous thrombosis and its extension, pulmonary embolism (PE). Prophylaxis and treatment of thromboembolic complications associated with atrial fibrillation (AF) and/or cardiac valve replacement. Reduction in the risk of death, recurrent myocardial infarction (MI), and thromboembolic events such as stroke or systemic embolization after myocardial infarction.
Limitations of Use Warfarin sodium tablets have no direct effect on an established thrombus, nor does it reverse ischemic tissue damage. Once a thrombus has occurred, however, the goals of anticoagulant treatment are to prevent further extension of the formed clot and to prevent secondary thromboembolic complications that may result in serious and possibly fatal sequelae. Warfarin sodium tablets are a vitamin K antagonist indicated for: Prophylaxis and treatment of venous thrombosis and its extension, pulmonary embolism ( 1 ) Prophylaxis and treatment of thromboembolic complications associated with atrial fibrillation and/or cardiac valve replacement ( 1 ) Reduction in the risk of death, recurrent myocardial infarction, and thromboembolic events such as stroke or systemic embolization after myocardial infarction ( 1 ) Limitations of Use Warfarin sodium tablets have no direct effect on an established thrombus, nor does it reverse ischemic tissue damage.
( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Individualize dosing regimen for each patient, and adjust based on INR response. ( 2.1 , 2.2 ) Knowledge of genotype can inform initial dose selection. ( 2.3 ) Monitoring: Obtain daily INR determinations upon initiation until stable in the therapeutic range. Obtain subsequent INR determinations every 1 to 4 weeks. ( 2.4 ) Review conversion instructions from other anticoagulants. ( 2.8 )
2.1Individualized Dosing The dosage and administration of warfarin sodium tablets must be individualized for each patient according to the patient’s International Normalized Ratio (INR) response to the drug. Adjust the dose based on the patient’s INR and the condition being treated. Consult the latest evidence-based clinical practice guidelines regarding the duration and intensity of anticoagulation for the indicated conditions.
2.2Recommended Target INR Ranges and Durations for Individual Indications An INR of greater than 4 appears to provide no additional therapeutic benefit in most patients and is associated with a higher risk of bleeding. Venous Thromboembolism (including deep venous thrombosis [DVT] and PE) Adjust the warfarin dose to maintain a target INR of 2.5 (INR range, 2 to 3) for all treatment durations. The duration of treatment is based on the indication as follows: For patients with a DVT or PE secondary to a transient (reversible) risk factor, treatment with warfarin for 3 months is recommended.
For patients with an unprovoked DVT or PE, treatment with warfarin is recommended for at least 3 months. After 3 months of therapy, evaluate the risk-benefit ratio of long-term treatment for the individual patient. For patients with two episodes of unprovoked DVT or PE, long-term treatment with warfarin is recommended.
For a patient receiving long-term anticoagulant treatment, periodically reassess the risk-benefit ratio of continuing such treatment in the individual patient. Atrial Fibrillation In patients with non-valvular AF, anticoagulate with warfarin to target INR of 2.5 (range, 2 to 3). In patients with non-valvular AF that is persistent or paroxysmal and at high risk of stroke (i.e., having any of the following features: prior ischemic stroke, transient ischemic attack, or systemic embolism, or 2 of the following risk factors: age greater than 75 years, moderately or severely impaired left ventricular systolic function and/or heart failure, history of hypertension, or diabetes mellitus), long-term anticoagulation with warfarin is recommended.
In patients with non-valvular AF that is persistent or paroxysmal and at an intermediate risk of ischemic stroke (i.e., having 1 of the following risk factors: age greater than 75 years, moderately or severely impaired left ventricular systolic function and/or heart failure, history of hypertension, or diabetes mellitus), long-term anticoagulation with warfarin is recommended. For patients with AF and mitral stenosis, long-term anticoagulation with warfarin is recommended. For patients with AF and prosthetic heart valves, long-term anticoagulation with warfarin is recommended; the target INR may be increased and aspirin added depending on valve type and position, and on patient factors.
Mechanical and Bioprosthetic Heart Valves For patients with a bileaflet mechanical valve or a Medtronic Hall (Minneapolis, MN) tilting disk valve in the aortic position who are in sinus rhythm and without left atrial enlargement, therapy with warfarin to a target INR of 2.5 (range, 2 to 3) is recommended. For patients with tilting disk valves and bileaflet mechanical valves in the mitral position, therapy with warfarin to a target INR of 3 (range, 2.5 to 3.5) is recommended. For patients with caged ball or caged disk valves, therapy with warfarin to a target INR of 3 (range, 2.5 to 3.5) is recommended.
For patients with a bioprosthetic valve in the mitral position, therapy with warfarin to a target INR of 2.5 (range, 2 to 3) for the first 3 months after valve insertion is recomm…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Warfarin sodium tablets USP, 1 mg are available as pink, capsule-shaped, biconvex scored tablets, debossed with TV/1 on the scored side and 1712 on the other side. Warfarin sodium tablets USP, 2 mg are available as lavender, capsule-shaped, biconvex scored tablets, debossed with TV/2 on the scored side and 1713 on the other side. Warfarin sodium tablets USP, 2.5 mg are available as green, capsule-shaped, biconvex scored tablets, debossed with TV/2 1 / 2 on the scored side and 1714 on the other side.
Warfarin sodium tablets USP, 3 mg are available as tan, capsule-shaped, biconvex scored tablets, debossed with TV/3 on the scored side and 1715 on the other side. Warfarin sodium tablets USP, 4 mg are available as blue, capsule-shaped, biconvex scored tablets, debossed with TV/4 on the scored side and 1716 on the other side. Warfarin sodium tablets USP, 5 mg are available as peach, capsule-shaped, biconvex scored tablets, debossed with TV/5 on the scored side and 1721 on the other side.
Warfarin sodium tablets USP, 6 mg are available as teal, capsule-shaped, biconvex scored tablets, debossed with TV/6 on the scored side and 1718 on the other side. Warfarin sodium tablets USP, 7.5 mg are available as yellow, capsule-shaped, biconvex scored tablets, debossed with TV/7 1 / 2 on the scored side and 1719 on the other side. Warfarin sodium tablets USP, 10 mg are available as white, capsule-shaped, biconvex scored tablets, debossed with TV/10 on the scored side and 1720 on the other side.
Scored tablets: 1, 2, 2.5, 3, 4, 5, 6, 7.5, or 10 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Warfarin sodium is contraindicated in: Pregnancy Warfarin sodium is contraindicated in women who are pregnant except in pregnant women with mechanical heart valves, who are at high risk of thromboembolism [see Warnings and Precautions ( 5.7 ) and Use in Specific Populations ( 8.1 )] . Warfarin sodium can cause fetal harm when administered to a pregnant woman. Warfarin sodium exposure during pregnancy causes a recognized pattern of major congenital malformations (warfarin embryopathy and fetotoxicity), fatal fetal hemorrhage, and an increased risk of spontaneous abortion and fetal mortality.
If warfarin sodium is used during pregnancy or if the patient becomes pregnant while taking this drug, the patient should be apprised of the potential hazard to a fetus [see Use in Specific Populations ( 8.1 )] . Warfarin sodium is contraindicated in patients with: Hemorrhagic tendencies or blood dyscrasias Recent or contemplated surgery of the central nervous system or eye, or traumatic surgery resulting in large open surfaces [see Warnings and Precautions ( 5.8 )] Bleeding tendencies associated with: − Active ulceration or overt bleeding of the gastrointestinal, genitourinary, or respiratory tract − Central nervous system hemorrhage − Cerebral aneurysms, dissecting aorta − Pericarditis and pericardial effusions − Bacterial endocarditis Threatened abortion, eclampsia, and preeclampsia Unsupervised patients with conditions associated with potential high level of non-compliance Spinal puncture and other diagnostic or therapeutic procedures with potential for uncontrollable bleeding Hypersensitivity to warfarin or to any other components of this product (e.g., anaphylaxis) [see Adverse Reactions ( 6 )] Major regional or lumbar block anesthesia Malignant hypertension Pregnancy, except in women with mechanical heart valves ( 4 , 5.7 , 8.1 ) Hemorrhagic tendencies or blood dyscrasias ( 4 ) Recent or contemplated surgery of the central nervous system (CNS) or eye, or traumatic surgery resulting in large open surfaces ( 4 , 5.8 ) Bleeding tendencies associated with certain conditions ( 4 ) Threatened abortion, eclampsia, and preeclampsia ( 4 ) Unsupervised patients with potential high levels of non-compliance ( 4 ) Spinal puncture and other diagnostic or therapeutic procedures with potential for uncontrollable bleeding ( 4 ) Hypersensitivity to warfarin or any component of the product ( 4 ) Major regional or lumbar block anesthesia ( 4 ) Malignant hypertension ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Tissue necrosis: Necrosis or gangrene of skin or other tissues can occur, with severe cases requiring debridement or amputation. Discontinue warfarin sodium and consider alternative anticoagulants if necessary. ( 5.2 ) Calciphylaxis: Fatal and serious cases have occurred.
Discontinue warfarin sodium and consider alternative anticoagulation therapy. ( 5.3 ) Acute kidney injury may occur during episodes of excessive anticoagulation and hematuria. ( 5.4 ) Systemic atheroemboli and cholesterol microemboli: Some cases have progressed to necrosis or death.
Discontinue warfarin sodium if such emboli occur. ( 5.5 ) Heparin-induced thrombocytopenia (HIT): Initial therapy with warfarin sodium in HIT has resulted in cases of amputation and death. Warfarin sodium may be considered after platelet count has normalized.
( 5.6 ) Pregnant women with mechanical heart valves: Warfarin sodium may cause fetal harm; however, the benefits may outweigh the risks. ( 5.7 )
5.1Hemorrhage Warfarin sodium can cause major or fatal bleeding. Bleeding is more likely to occur within the first month. Risk factors for bleeding include high intensity of anticoagulation (INR > 4), age greater than or equal to 65, history of highly variable INRs, history of gastrointestinal bleeding, hypertension, cerebrovascular disease, anemia, malignancy, trauma, renal impairment, certain genetic factors [see Clinical Pharmacology ( 12.5 )] , certain concomitant drugs [see Drug Interactions ( 7 )] , and long duration of warfarin therapy.
Perform regular monitoring of INR in all treated patients. Those at high risk of bleeding may benefit from more frequent INR monitoring, careful dose adjustment to desired INR, and a shortest duration of therapy appropriate for the clinical condition. However, maintenance of INR in the therapeutic range does not eliminate the risk of bleeding.
Drugs, dietary changes, and other factors affect INR levels achieved with warfarin sodium therapy. Perform more frequent INR monitoring when starting or stopping other drugs, including botanicals, or when changing dosages of other drugs [see Drug Interactions ( 7 )] . Instruct patients about prevention measures to minimize risk of bleeding and to report signs and symptoms of bleeding [see Patient Counseling Information ( 17 )] .
5.2Tissue Necrosis Warfarin sodium can cause necrosis and/or gangrene of skin and other tissues, which is an uncommon but serious risk (<0.1%). Necrosis may be associated with local thrombosis and usually appears within a few days of the start of warfarin sodium therapy. In severe cases of necrosis, treatment through debridement or amputation of the affected tissue, limb, breast, or penis has been reported.
Careful clinical evaluation is required to determine whether necrosis is caused by an underlying disease. Although various treatments have been attempted, no treatment for necrosis has been considered uniformly effective. Discontinue warfarin sodium therapy if necrosis occurs.
Consider alternative drugs if continued anticoagulation therapy is necessary.
5.3Calciphylaxis Warfarin sodium can cause fatal and serious calciphylaxis or calcium uremic arteriolopathy, which has been reported in patients with and without end-stage renal disease. When calciphylaxis is diagnosed in these patients, discontinue warfarin sodium and treat calciphylaxis as appropriate. Consider alternative anticoagulation therapy.
5.4Acute Kidney Injury In patients with altered glomerular integrity or with a history of kidney disease, acute kidney injury may occur with warfarin sodium, possibly in relation to episodes of excessive anticoagulation and hematuria [see Use in Specific Populations ( 8.6 )] . More frequent monitoring of anticoagulation is advised in patients with compromised renal function.
5.5Systemic Atheroemboli and Cholesterol Microemboli Anticoagulation therapy with warfarin sodium may enhance the release of atheromatous plaque emboli. Systemic atheroemboli and c…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions to warfarin sodium are discussed in greater detail in other sections of the labeling: Hemorrhage [see Boxed Warning, Warnings and Precautions (5.1), and Overdosage ( 10 )] Tissue Necrosis [see Warnings and Precautions ( 5.2 )] Calciphylaxis [see Warnings and Precautions ( 5.3 )] Acute Kidney Injury [see Warnings and Precautions ( 5.4 )] Systemic Atheroemboli and Cholesterol Microemboli [see Warnings and Precautions ( 5.5 )] Limb Ischemia, Necrosis, and Gangrene in Patients with HIT and HITTS [see Warnings and Precautions ( 5.6 )] Other Clinical Settings with Increased Risks [see Warnings and Precautions ( 5.8 )] Other adverse reactions to warfarin sodium include: Immune system disorders: hypersensitivity/allergic reactions (including urticaria and anaphylactic reactions) Vascular disorders: vasculitis Hepatobiliary disorders: hepatitis, elevated liver enzymes.
Cholestatic hepatitis has been associated with concomitant administration of warfarin sodium and ticlopidine. Gastrointestinal disorders: nausea, vomiting, diarrhea, taste perversion, abdominal pain, flatulence, bloating Skin disorders: rash, dermatitis (including bullous eruptions), pruritus, alopecia Respiratory disorders: tracheal or tracheobronchial calcification General disorders: chills Most common adverse reactions to warfarin sodium are fatal and nonfatal hemorrhage from any tissue or organ. ( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Teva at 1-888-838-2872 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Concomitant use of drugs that increase bleeding risk, antibiotics, antifungals, botanical (herbal) products, and inhibitors and inducers of CYP2C9, 1A2, or 3A4. ( 7 ) Consult labeling of all concurrently used drugs for complete information about interactions with warfarin sodium or increased risks for bleeding. ( 7 )
7.1General Information Drugs may interact with warfarin sodium through pharmacodynamic or pharmacokinetic mechanisms. Pharmacodynamic mechanisms for drug interactions with warfarin sodium are synergism (impaired hemostasis, reduced clotting factor synthesis), competitive antagonism (vitamin K), and alteration of the physiologic control loop for vitamin K metabolism (hereditary resistance). Pharmacokinetic mechanisms for drug interactions with warfarin sodium are mainly enzyme induction, enzyme inhibition, and reduced plasma protein binding.
It is important to note that some drugs may interact by more than one mechanism. More frequent INR monitoring should be performed when starting or stopping other drugs, including botanicals, or when changing dosages of other drugs, including drugs intended for short-term use (e.g., antibiotics, antifungals, corticosteroids) [ see Boxed Warning ]. Consult the labeling of all concurrently used drugs to obtain further information about interactions with warfarin sodium or adverse reactions pertaining to bleeding.
7.2CYP450 Interactions CYP450 isozymes involved in the metabolism of warfarin include CYP2C9, 2C19, 2C8, 2C18, 1A2, and 3A4. The more potent warfarin S -enantiomer is metabolized by CYP2C9 while the R -enantiomer is metabolized by CYP1A2 and 3A4. Inhibitors of CYP2C9, 1A2, and/or 3A4 have the potential to increase the effect (increase INR) of warfarin by increasing the exposure of warfarin.
Inducers of CYP2C9, 1A2, and/or 3A4 have the potential to decrease the effect (decrease INR) of warfarin by decreasing the exposure of warfarin. Examples of inhibitors and inducers of CYP2C9, 1A2, and 3A4 are below in Table 2 ; however, this list should not be considered all-inclusive. Consult the labeling of all concurrently used drugs to obtain further information about CYP450 interaction potential.
The CYP450 inhibition and induction potential should be considered when starting, stopping, or changing dose of concomitant medications. Closely monitor INR if a concomitant drug is a CYP2C9, 1A2, and/or 3A4 inhibitor or inducer. Table 2: Examples of CYP450 Interactions with Warfarin Enzyme Inhibitors Inducers CYP2C9 amiodarone, capecitabine, cotrimoxazole, etravirine, fluconazole, fluvastatin, fluvoxamine, metronidazole, miconazole, oxandrolone, sulfinpyrazone, tigecycline, voriconazole, zafirlukast aprepitant, bosentan, carbamazepine, phenobarbital, rifampin CYP1A2 acyclovir, allopurinol, caffeine, cimetidine, ciprofloxacin, disulfiram, enoxacin, famotidine, fluvoxamine, methoxsalen, mexiletine, norfloxacin, oral contraceptives, phenylpropanolamine, propafenone, propranolol, terbinafine, thiabendazole, ticlopidine, verapamil, zileuton montelukast, moricizine, omeprazole, phenobarbital, phenytoin, cigarette smoking CYP3A4 alprazolam, amiodarone, amlodipine, amprenavir, aprepitant, atorvastatin, atazanavir, bicalutamide, cilostazol, cimetidine, ciprofloxacin, clarithromycin, conivaptan, cyclosporine, darunavir/ritonavir, diltiazem, erythromycin, fluconazole, fluoxetine, fluvoxamine, fosamprenavir, imatinib, indinavir, isoniazid, itraconazole, ketoconazole, lopinavir/ritonavir, nefazodone, nelfinavir, nilotinib, oral contraceptives, posaconazole, ranitidine, ranolazine, ritonavir, saquinavir, telithromycin, tipranavir, voriconazole, zileuton armodafinil, amprenavir, aprepitant, bosentan, carbamazepine, efavirenz, etravirine, modafinil, nafcillin, phenytoin, pioglitazone, prednisone, rifampin, rufinamide
7.3Drugs that Increase Bleeding Risk Examples of drugs known to increase the risk of bleeding are presented in Table 3 . Because bleeding risk is increased when these…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnant women with mechanical heart valves: Warfarin sodium may cause fetal harm; however, the benefits may outweigh the risks. ( 8.1 ) Lactation: Monitor breastfeeding infants for bruising or bleeding. ( 8.2 ) Renal Impairment: Instruct patients with renal impairment to frequently monitor their INR. ( 8.6 )
8.1Pregnancy Risk Summary Warfarin sodium is contraindicated in women who are pregnant except in pregnant women with mechanical heart valves, who are at high risk of thromboembolism, and for whom the benefits of warfarin sodium may outweigh the risks [see Warnings and Precautions ( 5.7 )] . Warfarin sodium can cause fetal harm. Exposure to warfarin during the first trimester of pregnancy caused a pattern of congenital malformations in about 5% of exposed offspring.
Because these data were not collected in adequate and well-controlled studies, this incidence of major birth defects is not an adequate basis for comparison to the estimated incidences in the control group or the U.S. general population and may not reflect the incidences observed in practice. Consider the benefits and risks of warfarin sodium and possible risks to the fetus when prescribing warfarin sodium to a pregnant woman. Adverse outcomes in pregnancy occur regardless of the health of the mother or the use of medications.
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Fetal/Neonatal Adverse Reactions In humans, warfarin crosses the placenta, and concentrations in fetal plasma approach the maternal values.
Exposure to warfarin during the first trimester of pregnancy caused a pattern of congenital malformations in about 5% of exposed offspring. Warfarin embryopathy is characterized by nasal hypoplasia with or without stippled epiphyses (chondrodysplasia punctata) and growth retardation (including low birth weight). Central nervous system and eye abnormalities have also been reported, including dorsal midline dysplasia characterized by agenesis of the corpus callosum, Dandy-Walker malformation, midline cerebellar atrophy, and ventral midline dysplasia characterized by optic atrophy.
Mental retardation, blindness, schizencephaly, microcephaly, hydrocephalus, and other adverse pregnancy outcomes have been reported following warfarin exposure during the second and third trimesters of pregnancy [see Contraindications ( 4 )] .
8.2Lactation Risk Summary Warfarin was not present in human milk from mothers treated with warfarin from a limited published study. Because of the potential for serious adverse reactions, including bleeding in a breastfed infant, consider the developmental and health benefits of breastfeeding along with the mother’s clinical need for warfarin sodium and any potential adverse effects on the breastfed infant from warfarin sodium or from the underlying maternal condition before prescribing warfarin sodium to a lactating woman.
Clinical Considerations Monitor breastfeeding infants for bruising or bleeding. Data Human Data Based on published data in 15 nursing mothers, warfarin was not detected in human milk. Among the 15 full-term newborns, 6 nursing infants had documented prothrombin times within the expected range.
Prothrombin times were not obtained for the other 9 nursing infants. Effects in premature infants have not been evaluated.
8.3Females and Males of Reproductive Potential Pregnancy Testing Warfarin sodium can cause fetal harm [see Use in Specific Populations ( 8.1 )] . Verify the pregnancy status of females of reproductive potential prior to initiating warfarin sodium therapy. Contraception Females Advise females of reproductive potential to use effective contraception during treatment and for at least 1 month after the final dose of warfa…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Warfarin sodium is contraindicated in women who are pregnant except in pregnant women with mechanical heart valves, who are at high risk of thromboembolism, and for whom the benefits of warfarin sodium may outweigh the risks [see Warnings and Precautions ( 5.7 )] . Warfarin sodium can cause fetal harm. Exposure to warfarin during the first trimester of pregnancy caused a pattern of congenital malformations in about 5% of exposed offspring.
Because these data were not collected in adequate and well-controlled studies, this incidence of major birth defects is not an adequate basis for comparison to the estimated incidences in the control group or the U.S. general population and may not reflect the incidences observed in practice. Consider the benefits and risks of warfarin sodium and possible risks to the fetus when prescribing warfarin sodium to a pregnant woman. Adverse outcomes in pregnancy occur regardless of the health of the mother or the use of medications.
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Fetal/Neonatal Adverse Reactions In humans, warfarin crosses the placenta, and concentrations in fetal plasma approach the maternal values.
Exposure to warfarin during the first trimester of pregnancy caused a pattern of congenital malformations in about 5% of exposed offspring. Warfarin embryopathy is characterized by nasal hypoplasia with or without stippled epiphyses (chondrodysplasia punctata) and growth retardation (including low birth weight). Central nervous system and eye abnormalities have also been reported, including dorsal midline dysplasia characterized by agenesis of the corpus callosum, Dandy-Walker malformation, midline cerebellar atrophy, and ventral midline dysplasia characterized by optic atrophy.
Mental retardation, blindness, schizencephaly, microcephaly, hydrocephalus, and other adverse pregnancy outcomes have been reported following warfarin exposure during the second and third trimesters of pregnancy [see Contraindications ( 4 )] .
🧒 Pediatric Use ▾
8.4Pediatric Use Adequate and well-controlled studies with warfarin sodium have not been conducted in any pediatric population, and the optimum dosing, safety, and efficacy in pediatric patients is unknown. Pediatric use of warfarin sodium is based on adult data and recommendations, and available limited pediatric data from observational studies and patient registries. Pediatric patients administered warfarin sodium should avoid any activity or sport that may result in traumatic injury.
The developing hemostatic system in infants and children results in a changing physiology of thrombosis and response to anticoagulants. Dosing of warfarin in the pediatric population varies by patient age, with infants generally having the highest, and adolescents having the lowest milligram per kilogram dose requirements to maintain target INRs. Because of changing warfarin requirements due to age, concomitant medications, diet, and existing medical condition, target INR ranges may be difficult to achieve and maintain in pediatric patients, and more frequent INR determinations are recommended.
Bleeding rates varied by patient population and clinical care center in pediatric observational studies and patient registries. Infants and children receiving vitamin K-supplemented nutrition, including infant formulas, may be resistant to warfarin therapy, while human milk-fed infants may be sensitive to warfarin therapy.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the total number of patients receiving warfarin sodium in controlled clinical trials for which data were available for analysis, 1885 patients (24.4%) were 65 years and older, while 185 patients (2.4%) were 75 years and older. No overall differences in effectiveness or safety were observed between these patients and younger patients, but greater sensitivity of some older individuals cannot be ruled out. Patients 60 years or older appear to exhibit greater than expected INR response to the anticoagulant effects of warfarin [see Clinical Pharmacology ( 12.3 )] .
Warfarin sodium is contraindicated in any unsupervised patient with senility. Conduct more frequent monitoring for bleeding with administration of warfarin sodium to elderly patients in any situation or with any physical condition where added risk of hemorrhage is present. Consider lower initiation and maintenance doses of warfarin sodium in elderly patients [see Dosage and Administration ( 2.2 , 2.3 )] .
🆘 Overdosage ▾
10 OVERDOSAGE
10.1Signs and Symptoms Bleeding (e.g., appearance of blood in stools or urine, hematuria, excessive menstrual bleeding, melena, petechiae, excessive bruising or persistent oozing from superficial injuries, unexplained fall in hemoglobin) is a manifestation of excessive anticoagulation.
10.2Treatment The treatment of excessive anticoagulation is based on the level of the INR, the presence or absence of bleeding, and clinical circumstances. Reversal of warfarin sodium anticoagulation may be obtained by discontinuing warfarin sodium therapy and, if necessary, by administration of oral or parenteral vitamin K 1 . The use of vitamin K 1 reduces response to subsequent warfarin sodium therapy and patients may return to a pretreatment thrombotic status following the rapid reversal of a prolonged INR.
Resumption of warfarin sodium administration reverses the effect of vitamin K, and a therapeutic INR can again be obtained by careful dosage adjustment. If rapid re-anticoagulation is indicated, heparin may be preferable for initial therapy. Prothrombin complex concentrate (PCC), fresh frozen plasma, or activated Factor VII treatment may be considered if the requirement to reverse the effects of warfarin sodium is urgent.
A risk of hepatitis and other viral diseases is associated with the use of blood products; PCC and activated Factor VII are also associated with an increased risk of thrombosis. Therefore, these preparations should be used only in exceptional or life-threatening bleeding episodes secondary to warfarin sodium overdosage.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Warfarin acts by inhibiting the synthesis of vitamin K-dependent clotting factors, which include Factors II, VII, IX, and X, and the anticoagulant proteins C and S. Vitamin K is an essential cofactor for the post ribosomal synthesis of the vitamin K-dependent clotting factors. Vitamin K promotes the biosynthesis of γ-carboxyglutamic acid residues in the proteins that are essential for biological activity.
Warfarin is thought to interfere with clotting factor synthesis by inhibition of the C1 subunit of vitamin K epoxide reductase (VKORC1) enzyme complex, thereby reducing the regeneration of vitamin K 1 epoxide [see Clinical Pharmacology ( 12.5 )] .
12.2Pharmacodynamics An anticoagulation effect generally occurs within 24 hours after warfarin administration. However, peak anticoagulant effect may be delayed 72 to 96 hours. The duration of action of a single dose of racemic warfarin is 2 to 5 days.
The effects of warfarin sodium may become more pronounced as effects of daily maintenance doses overlap. This is consistent with the half-lives of the affected vitamin K-dependent clotting factors and anticoagulation proteins: Factor II - 60 hours, VII - 4 to 6 hours, IX - 24 hours, X - 48 to 72 hours, and proteins C and S are approximately 8 hours and 30 hours, respectively.
12.3Pharmacokinetics Warfarin sodium is a racemic mixture of the R - and S -enantiomers of warfarin. The S -enantiomer exhibits 2 to 5 times more anticoagulant activity than the R -enantiomer in humans, but generally has a more rapid clearance. Absorption Warfarin is essentially completely absorbed after oral administration, with peak concentration generally attained within the first 4 hours. Distribution Warfarin shows a volume of distribution of about
0.14L/kg. Approximately 99% of the drug is bound to plasma proteins. Metabolism The elimination of warfarin is almost entirely by metabolism.
Warfarin is stereoselectively metabolized by hepatic cytochrome P-450 (CYP450) microsomal enzymes to inactive hydroxylated metabolites (predominant route) and by reductases to reduced metabolites (warfarin alcohols) with minimal anticoagulant activity. Identified metabolites of warfarin include dehydrowarfarin, two diastereoisomer alcohols, and 4′-, 6-, 7-, 8-, and 10- hydroxywarfarin. The CYP450 isozymes involved in the metabolism of warfarin include CYP2C9, 2C19, 2C8, 2C18, 1A2, and 3A4.
CYP2C9, a polymorphic enzyme, is likely to be the principal form of human liver CYP450 that modulates the in vivo anticoagulant activity of warfarin. Patients with one or more variant CYP2C9 alleles have decreased S-warfarin clearance [see Clinical Pharmacology ( 12.5 )] . Excretion The terminal half-life of warfarin after a single dose is approximately 1 week; however, the effective half-life ranges from 20 to 60 hours, with a mean of about 40 hours.
The clearance of R-warfarin is generally half that of S-warfarin, thus as the volumes of distribution are similar, the half-life of R-warfarin is longer than that of S-warfarin. The half-life of R-warfarin ranges from 37 to 89 hours, while that of S-warfarin ranges from 21 to 43 hours. Studies with radiolabeled drug have demonstrated that up to 92% of the orally administered dose is recovered in urine.
Very little warfarin is excreted unchanged in urine. Urinary excretion is in the form of metabolites. Geriatric Patients Patients 60 years or older appear to exhibit greater than expected INR response to the anticoagulant effects of warfarin.
The cause of the increased sensitivity to the anticoagulant effects of warfarin in this age group is unknown but may be due to a combination of pharmacokinetic and pharmacodynamic factors. Limited information suggests there is no difference in the clearance of S-warfarin; however, there may be a slight decrease in the clearance of R-warfarin in the elderly as compared to the young. Therefore, as patient age increases, a lower dose of warfarin is usually…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Warfarin acts by inhibiting the synthesis of vitamin K-dependent clotting factors, which include Factors II, VII, IX, and X, and the anticoagulant proteins C and S. Vitamin K is an essential cofactor for the post ribosomal synthesis of the vitamin K-dependent clotting factors. Vitamin K promotes the biosynthesis of γ-carboxyglutamic acid residues in the proteins that are essential for biological activity.
Warfarin is thought to interfere with clotting factor synthesis by inhibition of the C1 subunit of vitamin K epoxide reductase (VKORC1) enzyme complex, thereby reducing the regeneration of vitamin K 1 epoxide [see Clinical Pharmacology ( 12.5 )] .
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Warfarin sodium tablets USP, 2 mg are available as lavender, capsule-shaped, biconvex scored tablets, debossed with TV/2 on the scored side and 1713 on the other side containing 2 mg warfarin sodium, USP. NDC: 71335-0637-1: 30 Tablets in a BOTTLE NDC: 71335-0637-2: 14 Tablets in a BOTTLE NDC: 71335-0637-3: 90 Tablets in a BOTTLE NDC: 71335-0637-4: 45 Tablets in a BOTTLE NDC: 71335-0637-5: 50 Tablets in a BOTTLE NDC: 71335-0637-6: 21 Tablets in a BOTTLE NDC: 71335-0637-7: 60 Tablets in a BOTTLE NDC: 71335-0637-8: 20 Tablets in a BOTTLE Dispense in a tight, light-resistant container as defined in the USP, with a child-resistant closure (as required).
Protect from light. Keep tightly closed. Store at 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature].
Special Handling Procedures for proper handling and disposal of potentially hazardous drugs should be considered. Guidelines on this subject have been published [see References (15)]. Pharmacy and clinical personnel who are pregnant should avoid exposure to crushed or broken tablets [see Use in Specific Populations (8.1)].
Keep this and all medications out of the reach of children. Repackaged/Relabeled by: Bryant Ranch Prepack, Inc. Burbank, CA 91504
📋 Description ▾
11 DESCRIPTION Warfarin sodium tablets, USP contain warfarin sodium, an anticoagulant that acts by inhibiting vitamin K-dependent coagulation factors. The chemical name of warfarin sodium is 3-(α-acetonylbenzyl)-4-hydroxycoumarin sodium salt, which is a racemic mixture of the R - and S -enantiomers. Crystalline warfarin sodium is an isopropanol clathrate.
Its structural formula may be represented as follows: C 19 H 15 NaO 4 M.W. 330.31 Crystalline warfarin sodium occurs as a white, odorless, crystalline powder that is discolored by light. It is very soluble in water, freely soluble in alcohol, and very slightly soluble in chloroform and ether.
Each tablet, for oral administration, contains 1 mg, 2 mg, 2.5 mg, 3 mg, 4 mg, 5 mg, 6 mg, 7.5 mg or 10 mg warfarin sodium, USP. In addition, each tablet contains the following inactive ingredients: colloidal silicon dioxide, croscarmellose sodium, lactose monohydrate, magnesium stearate, and microcrystalline cellulose. The 1 mg also contains FD&C red no.
40. The 2 mg also contains FD&C blue no. 2 aluminum lake and FD&C red no.
40 aluminum lake. The 2.5 mg also contains D&C yellow no. 10 aluminum lake and FD&C blue no.
1 aluminum lake. The 3 mg also contains FD&C yellow no. 6 aluminum lake, FD&C blue no.
2 aluminum lake, FD&C red no. 40 aluminum lake, and D&C yellow no. 10 aluminum lake.
The 4 mg also contains FD&C blue no. 1 aluminum lake and FD&C blue no. 2 aluminum lake.
The 5 mg also contains FD&C yellow no. 6 aluminum lake, FD&C red no. 40 aluminum lake and D&C yellow no.
10 aluminum lake. The 6 mg also contains D&C yellow no. 10 aluminum lake and FD&C blue no.
1 aluminum lake. The 7.5 mg also contains D&C yellow no. 10 aluminum lake and FD&C yellow no.
6 aluminum lake.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Instructions for Patients Advise patients to: Strictly adhere to the prescribed dosage schedule [see Dosage and Administration ( 2.1 )] . If the prescribed dose of warfarin sodium is missed, take the dose as soon as possible on the same day but do not take a double dose of warfarin sodium the next day to make up for missed doses [see Dosage and Administration ( 2.6 )] .
Obtain prothrombin time tests and make regular visits to their physician or clinic to monitor therapy [see Dosage and Administration ( 2.1 )] . Be aware that if therapy with warfarin sodium is discontinued, the anticoagulant effects of warfarin sodium may persist for about 2 to 5 days [see Clinical Pharmacology ( 12.2 )] . Avoid any activity or sport that may result in traumatic injury [see Use in Specific Populations ( 8.4 )] .
And to tell their physician if they fall often as this may increase their risk for complications. Eat a normal, balanced diet to maintain a consistent intake of vitamin K. Avoid drastic changes in dietary habits, such as eating large amounts of leafy, green vegetables [see Drug Interactions ( 7.5 )] .
Contact their physician to report any serious illness, such as severe diarrhea, infection, or fever [see Warnings and Precautions ( 5 ) and Adverse Reactions ( 6 )] . Immediately contact their physician when experiencing pain and discoloration of the skin (a purple bruise like rash) mostly on areas of the body with a high fat content, such as breasts, thighs, buttocks, hips and abdomen [ see Warnings and Precautions ( 5.2 ) ]. Immediately contact their physician when experiencing any unusual symptom or pain since warfarin sodium may cause small cholesterol or athero emboli.
On feet it may appear as a sudden cool, painful, purple discoloration of toe(s) or forefoot [ see Warnings and Precautions ( 5.5 ) ]. Immediately contact their physician when taking warfarin sodium after any heparin formulation therapy and experiencing bloody or black stools or appearence of bruises, or bleeding [ see Warnings and Precautions ( 5.6 ) ]. To tell all of their healthcare professionals and dentists that they are taking warfarin sodium.
This should be done before they have any surgery or dental procedure [ see Dosage and Administration ( 2.7 ) ]. Carry identification stating that they are taking warfarin sodium. Bleeding Risks Advise patients to: Notify their physician immediately if any unusual bleeding or symptoms occur.
Signs and symptoms of bleeding include: pain, swelling or discomfort, prolonged bleeding from cuts, increased menstrual flow or vaginal bleeding, nosebleeds, bleeding of gums from brushing, unusual bleeding or bruising, red or dark brown urine, red or tar black stools, headache, dizziness, or weakness [see Box Warning and Warnings and Precautions ( 5.1 )] . Concomitant Medications and Botanicals (Herbals) Advise patients to: Not take or discontinue any other drug, including salicylates (e.g., aspirin and topical analgesics), other over-the-counter drugs, and botanical (herbal) products except on advice of your physician [see Drug Interactions ( 7 )] .
Pregnancy and Nursing Advise patients to: Notify their physician if they are pregnant or planning to become pregnant or considering breast feeding [ see Use in Specific Populations ( 8.1 , 8.2 , 8.3 ) ]. Avoid warfarin sodium during pregnancy except in pregnant women with mechanical heart valves, who are at risk of thromboembolism [ see Contraindications ( 4 ) ]. Use effective measures to avoid pregnancy while taking warfarin sodium.
This is very important because their unborn baby could be seriously harmed if they take warfarin sodium while they are pregnant [ see Use in Specific Populations ( 8.1 , 8.3 ) ]. Dispense with Medication Guide available at: www.tevausa.com/medguides Manufactured In Croatia By: Pliva Hrvatska d.o.o. Zagreb, Croatia Manufactured For: Teva Pharmaceutica…
💬 Medication Guide ▾
MEDICATION GUIDE Dispense with Medication Guide available at: www.tevausa.com/medguides Warfarin (war' far in) Sodium (soe' dee um) Tablets What is the most important information I should know about warfarin sodium tablets? Warfarin sodium tablets can cause bleeding which can be serious and sometimes lead to death. This is because warfarin sodium tablets are a blood thinner medicine that lowers the chance of blood clots forming in your body.
You may have a higher risk of bleeding if you take warfarin sodium tablets and: are 65 years of age or older have a history of stomach or intestinal bleeding have high blood pressure (hypertension) have a history of stroke, or “mini-stroke” (transient ischemic attack or TIA) have serious heart disease have a low blood count or cancer have had trauma, such as an accident or surgery have kidney problems take other medicines that increase your risk of bleeding, including: a medicine that contains heparin other medicines to prevent or treat blood clots non-steroidal anti-inflammatory drugs (NSAIDs) take warfarin sodium for a long time.
Warfarin sodium is the active ingredient in warfarin sodium tablets. Tell your healthcare provider if you take any of these medicines. Ask your healthcare provider if you are not sure if your medicine is one listed above.
Many other medicines can interact with warfarin sodium tablets and affect the dose you need or increase warfarin sodium tablets side effects. Do not change or stop any of your medicines or start any new medicines before you talk to your healthcare provider. Do not take other medicines that contain warfarin sodium while taking warfarin sodium tablets.
Get your regular blood test to check for your response to warfarin sodium tablets. This blood test is called an INR test. The INR test checks to see how fast your blood clots.
Your healthcare provider will decide what INR numbers are best for you. Your dose of warfarin sodium tablets will be adjusted to keep your INR in a target range for you. Call your healthcare provider right away if you get any of the following signs or symptoms of bleeding problems: pain, swelling, or discomfort headaches, dizziness, or weakness unusual bruising (bruises that develop without known cause or grow in size) nosebleeds bleeding gums bleeding from cuts takes a long time to stop menstrual bleeding or vaginal bleeding that is heavier than normal pink or brown urine red or black stools coughing up blood vomiting blood or material that looks like coffee grounds Some foods and beverages can interact with warfarin sodium tablets and affect your treatment and dose.
Eat a normal, balanced diet. Talk to your healthcare provider before you make any diet changes. Do not eat large amounts of leafy, green vegetables.
Leafy, green vegetables contain vitamin K. Certain vegetable oils also contain large amounts of vitamin K. Too much vitamin K can lower the effect of warfarin sodium tablets.
Always tell all of your healthcare providers that you take warfarin sodium tablets. Wear or carry information that you take warfarin sodium tablets. See “What are the possible side effects of warfarin sodium tablets?” for more information about side effects.
What are warfarin sodium tablets? Warfarin sodium tablets are prescription medicine used to treat blood clots and to lower the chance of blood clots forming in your body. Blood clots can cause a stroke, heart attack, or other serious conditions if they form in the legs or lungs.
Who should not take warfarin sodium tablets? Do not take warfarin sodium tablets if: your risk of having bleeding problems is higher than the possible benefit of treatment. Your healthcare provider will decide if warfarin sodium tablets are right for you. you are pregnant unless you have a mechanical heart valve.
Warfarin sodium tablets may cause birth defects, miscarriage, or death of your unborn baby. you are allergic to warfarin or any of the other ingredients in warfarin sodium tablets. See the end of this leafl…