
Dextroamphetamine Saccharate, Amphetamine Aspartate Monohydrate, Dextroamphetamine Sulfate and 2.5 mg; 2.5 mg; 2.5 mg; 2.5 mg Tablet, 90-count — NDC 71335-1249-3 (Billing 71335-1249-03)
This is a package of 90 tablets of Dextroamphetamine Saccharate, Amphetamine Aspartate Monohydrate, Dextroamphetamine Sulfate and 2.5 mg; 2.5 mg; 2.5 mg; 2.5 mg Tablet from Bryant Ranch Prepack, no longer marketed (first marketed Jun 2002), no longer in the FDA NDC Directory.
NDC database record
One package, one record: these facts belong to NDC 71335-1249-3 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 71335 labeler · 1249 product · 3 package
- Package marketed since
- May 17, 2024
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC-A, from the NDC)
- 3 7133512493 9
- FDA record last changed
- Oct 1, 2026
Other active recalls for Dextroamphetamine Saccharate, Amphetamine Aspartate Monohydrate, Dextroamphetamine Sulfate And Amphetamine Sulfate (different manufacturers) — 5 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
- RxCUI (RxNorm): 541892
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Central Nervous System Stimulant class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
The combination of dextroamphetamine and amphetamine (Adderall®, Adderall® XR, Mydayis®) is used as part of a treatment program to control symptoms of attention deficit hyperactivity disorder (ADHD; more difficulty focusing, controlling actions, and remaining still or quiet than other people who are the same age). Adderall® is used to treat ADHD in adults and children 3 years of age and older. Adderall® XR is used to treat ADHD in adults and children 6 years of age and older. Mydayis® is used to treat ADHD in adults and children 13 years of age and older. Dextroamphetamine and amphetamine (Add...
Read the full MedlinePlus article ↗- It treats ADHD. Some tablet products, including Adderall tablets, are also used for narcolepsy. Which product you have determines the approved ages and uses.
- Extended-release capsules are usually taken once a day in the morning, because they can last up to 16 hours and may disturb sleep. Take it the same way each day, with or without fo...
- Loss of appetite, trouble sleeping, stomach pain, nervousness and weight loss are common. Adults may also get dry mouth and headache. Call your doctor if these are bothersome or se...
- It has a high potential for abuse and misuse, which can lead to addiction and overdose. Take only as prescribed, never share it, store it locked up, and dispose of leftovers safely...
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.5376 | $48.38 / 90 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 4, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 71335-1249-01 71335-1249-1 Main listing | 60 TABLET in 1 BOTTLE | 2022-03-16 | — | Discontinued by firm |
| 71335-1249-02 71335-1249-2 | 30 TABLET in 1 BOTTLE | 2022-03-16 | — | Discontinued by firm |
| 71335-1249-03 You're viewing this | 90 TABLET in 1 BOTTLE | 2022-03-16 | — | Discontinued by firm |
| 71335-1249-04 71335-1249-4 | 120 TABLET in 1 BOTTLE | 2022-03-16 | — | Discontinued by firm |
| 71335-1249-05 71335-1249-5 | 18 TABLET in 1 BOTTLE | 2022-03-16 | — | Discontinued by firm |
You're viewing one of 5 pack sizes for this product.
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 71335-1249-05?
What NDC number is used to bill for this package of Dextroamphetamine Saccharate, Amphetamine Aspartate Monohydrate, Dextroamphetamine Sulfate and 2.5 mg; 2.5 mg; 2.5 mg; 2.5 mg Tablet?
Therapeutic equivalents
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII H3R47K3TBD
FD&C Blue No. 1 is a synthetic blue dye approved for use in foods and medicines. It serves as a colorant to give the medication its distinctive appearance and help with product identification.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 3, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Bryant Ranch Prepack labeler code 71335
- Diclofenac Sodium 100 mg Tablet, Extended Release NDC 71335-1238-1
- Escitalopram 5 mg Tablet, Film Coated NDC 71335-1241-1
- Labetalol Hydrochloride 200 mg Tablet, Film Coated NDC 71335-1242-1
- Pravastatin Sodium 10 mg Tablet NDC 71335-1243-1
- Irbesartan 150 mg Tablet NDC 71335-1244-1
- Oxycodone Hydrochloride 30 mg Tablet NDC 71335-1245-1
- Amitriptyline Hydrochloride 25 mg Tablet, Film Coated NDC 71335-1254-0
- Tadalafil 20 mg Tablet, Film Coated NDC 71335-1255-1
- Amitriptyline Hydrochloride 50 mg Tablet, Film Coated NDC 71335-1256-1
- Verapamil Hydrochloride 180 mg Tablet NDC 71335-1258-1
- Metoclopramide 5 mg Tablet NDC 71335-1259-1
- Irbesartan 150 mg Tablet NDC 71335-1263-1
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: ABUSE, MISUSE, AND ADDICTION Dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate has a high potential for abuse and misuse, which can lead to the development of a substance use disorder, including addiction. Misuse and abuse of CNS stimulants, including dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate, can result in overdose and death (see OVERDOSAGE ), and this risk is increased with higher doses or unapproved methods of administration, such as snorting or injection.
Before prescribing dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate, assess each patient’s risk for abuse, misuse, and addiction. Educate patients and their families about these risks, proper storage of the drug, and proper disposal of any unused drug. Throughout dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate treatment, reassess each patient’s risk of abuse, misuse, and addiction and frequently monitor for signs and symptoms of abuse, misuse, and addiction (see WARNINGS and DRUG ABUSE AND DEPENDENCE ).
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets (Mixed salts of a single entity amphetamine product) is indicated for the treatment of Attention Deficit Hyperactivity Disorder (ADHD) and Narcolepsy. Attention Deficit Hyperactivity Disorder (ADHD) A diagnosis of Attention Deficit Hyperactivity Disorder (ADHD; DSM-IV ® ) implies the presence of hyperactive-impulsive or inattentive symptoms that caused impairment and were present before age 7 years.
The symptoms must cause clinically significant impairment, e.g., in social, academic, or occupational functioning, and be present in two or more settings, e.g., school (or work) and at home. The symptoms must not be better accounted for by another mental disorder. For the Inattentive Type, at least six of the following symptoms must have persisted for at least 6 months: lack of attention to details/careless mistakes; lack of sustained attention; poor listener; failure to follow through on tasks; poor organization; avoids tasks requiring sustained mental effort; loses things; easily distracted; forgetful.
For the Hyperactive-Impulsive Type, at least six of the following symptoms must have persisted for at least 6 months: fidgeting/squirming; leaving seat; inappropriate running/climbing; difficulty with quiet activities; "on the go;" excessive talking; blurting answers; can't wait turn; intrusive. The Combined Type requires both inattentive and hyperactive-impulsive criteria to be met.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Regardless of indication, amphetamines should be administered at the lowest effective dosage, and dosage should be individually adjusted according to the therapeutic needs and response of the patient. Late evening doses should be avoided because of the resulting insomnia. Attention Deficit Hyperactivity Disorder Not recommended for children under 3 years of age.
In children from 3 to 5 years of age, start with 2.5 mg daily; daily dosage may be raised in increments of 2.5 mg at weekly intervals until optimal response is obtained. In children 6 years of age and older, start with 5 mg once or twice daily; daily dosage may be raised in increments of 5 mg at weekly intervals until optimal response is obtained. Only in rare cases will it be necessary to exceed a total of 40 mg per day.
Give first dose on awakening; additional doses (1 or 2) at intervals of 4 to 6 hours. Prior to treating patients with dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate assess: • for the presence of cardiac disease (i.e., perform a careful history, family history of sudden death or ventricular arrhythmia, and physical exam) (see WARNINGS ). • the family history and clinically evaluate patients for motor or verbal tics or Tourette’s syndrome before initiating dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate (see WARNINGS ).
Narcolepsy Usual dose 5 mg to 60 mg per day in divided doses, depending on the individual patient response. Narcolepsy seldom occurs in children under 12 years of age; however, when it does, dextroamphetamine sulfate may be used. The suggested initial dose for patients aged 6 to 12 is 5 mg daily; daily dose may be raised in increments of 5 mg at weekly intervals until optimal response is obtained.
In patients 12 years of age and older, start with 10 mg daily; daily dosage may be raised in increments of 10 mg at weekly intervals until optimal response is obtained. If bothersome adverse reactions appear (e.g., insomnia or anorexia), dosage should be reduced. Give first dose on awakening; additional doses (1 or 2) at intervals of 4 to 6 hours.
⛔ Contraindications ▾
CONTRAINDICATIONS In patients known to be hypersensitive to amphetamine, or other components of mixed salts of a single entity amphetamine product. Hypersensitivity reactions such as angioedema and anaphylactic reactions have been reported in patients treated with other amphetamine products (see ADVERSE REACTIONS ). Patients taking monoamine oxidase inhibitors (MAOIs), or within 14 days of stopping MAOIs (including MAOIs such as linezolid or intravenous methylene blue), because of an increased risk of hypertensive crisis (see WARNINGS and Drug Interactions ).
⚠️ Warnings ▾
WARNINGS Abuse, Misuse, and Addiction Dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate has a high potential for abuse and misuse. The use of dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate exposes individuals to the risks of abuse and misuse, which can lead to the development of a substance use disorder, including addiction. Dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate can be diverted for non-medical use into illicit channels or distribution (see DRUG ABUSE and DEPENDENCE: Abuse ).
Misuse and abuse of CNS stimulants, including dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate, can result in overdose and death (see OVERDOSAGE ), and this risk is increased with higher doses or unapproved methods of administration, such as snorting or injection. Before prescribing dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate, assess each patient’s risk for abuse, misuse, and addiction. Educate patients and their families about these risks and proper disposal of any unused drug.
Advise patients to store amphetamine sulfate in a safe place, preferably locked, and instruct patients to not give dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate to anyone else. Throughout dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate treatment, reassess each patient’s risk of abuse, misuse, and addiction and frequently monitor for signs and symptoms of abuse, misuse, and addiction. Risks to Patients with Serious Cardiac Disease Sudden death has been reported in patients with structural cardiac abnormalities or other serious cardiac disease who were treated with CNS stimulant treatment at the recommended ADHD dosages.
Avoid dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate use in patients with known structural cardiac abnormalities, cardiomyopathy, serious cardiac arrhythmia, coronary artery disease, or other serious cardiac disease. Increased Blood Pressure and Heart Rate CNS stimulants cause an increase in blood pressure (mean increase about 2 to 4 mm Hg) and heart rate (mean increase about 3 to 6 bpm). Some patients may have larger increases.
Monitor all dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate-treated patients for potential tachycardia and hypertension. Psychiatric Adverse Reactions Exacerbation of Preexisting Psychosis CNS stimulants may exacerbate symptoms of behavior disturbance and thought disorder in patients with a pre-existing psychotic disorder. Induction of a Manic Episode in Patients with Bipolar Disorder CNS stimulants may induce a manic or mixed episode in patients.
Prior to initiating treatment, screen patients for risk factors for developing a manic episode (e.g., comorbid or history of depressive symptoms or a family history of suicide, bipolar disorder, or depression). New Psychotic or Manic Symptoms CNS stimulants, at recommended doses, may cause psychotic or manic symptoms (e.g., hallucinations, delusional thinking, or mania) in patients without a prior history of psychotic illness or mania. In a pooled analysis of multiple short-term, placebo-controlled studies of CNS stimulants, psychotic or manic symptoms occurred in approximately 0.1% of CNS stimulant-treated patients, compared with 0% of placebo-treated patients.
If such symptoms occur, consider discontinuing dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate. Long-Term Suppression of Growth in Pediatric Patients CNS stimulants have been associated with weight loss and slowing of growth rate in pediatric patients. Closely monitor growth (weight and… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Cardiovascular Palpitations, tachycardia, elevation of blood pressure, sudden death, myocardial infarction. There have been isolated reports of cardiomyopathy associated with chronic amphetamine use. Central Nervous System Psychotic episodes at recommended doses, overstimulation, restlessness, irritability, euphoria, dyskinesia, dysphoria, depression, tremor, motor and verbal tics, aggression, anger, logorrhea, dermatillomania.
Eye Disorders Vision blurred, mydriasis. Gastrointestinal Dryness of the mouth, unpleasant taste, diarrhea, constipation, intestinal ischemia and other gastrointestinal disturbances. Anorexia and weight loss may occur as undesirable effects.
Allergic Urticaria, rash, hypersensitivity reactions including angioedema and anaphylaxis. Serious skin rashes, including Stevens-Johnson syndrome and toxic epidermal necrolysis have been reported. Endocrine Impotence, changes in libido, frequent or prolonged erections.
Skin Alopecia. Musculoskeletal Rhabdomyolysis. To report SUSPECTED ADVERSE REACTIONS, contact Sandoz Inc. at 1-800-525-8747 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
🤰 Pregnancy ▾
Pregnancy Teratogenic Effects Amphetamine, in the enantiomer ratio present in mixed salts of a single entity amphetamine product (d- to l- ratio of 3:1), had no apparent effects on embryofetal morphological development or survival when orally administered to pregnant rats and rabbits throughout the period of organogenesis at doses of up to 6 mg/kg/day and 16 mg/kg/day, respectively. These doses are approximately 1.5 and 8 times, respectively, the maximum recommended human dose of 30 mg/day (child) on a mg/m 2 body surface area basis.
Fetal malformations and death have been reported in mice following parenteral administration of d-amphetamine doses of 50 mg/kg/day (approximately 6 times that of a human dose of 30 mg/day (child) on a mg/m 2 basis) or greater to pregnant animals. Administration of these doses was also associated with severe maternal toxicity. A number of studies in rodents indicate that prenatal or early postnatal exposure to amphetamine (d- or d,l-), at doses similar to those used clinically, can result in long-term neurochemical and behavioral alterations.
Reported behavioral effects include learning and memory deficits, altered locomotor activity, and changes in sexual function. There are no adequate and well-controlled studies in pregnant women. There has been one report of severe congenital bony deformity, tracheo-esophageal fistula, and anal atresia (vater association) in a baby born to a woman who took dextroamphetamine sulfate with lovastatin during the first trimester of pregnancy.
Amphetamines should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus. Nonteratogenic Effects Infants born to mothers dependent on amphetamines have an increased risk of premature delivery and low birth weight. Also, these infants may experience symptoms of withdrawal as demonstrated by dysphoria, including agitation, and significant lassitude.
🧒 Pediatric Use ▾
Pediatric Use Long-term effects of amphetamines in children have not been well established. Amphetamines are not recommended for use in children under 3 years of age with Attention Deficit Hyperactivity Disorder described under INDICATIONS AND USAGE .
🆘 Overdosage ▾
OVERDOSAGE Clinical Effects of Overdose Overdose of CNS stimulants is characterized by the following sympathomimetic effects: • Cardiovascular effects including tachyarrhythmias, and hypertension or hypotension. Vasospasm, myocardial infarction, or aortic dissection may precipitate sudden cardiac death. Takotsubo cardiomyopathy may develop. • CNS effects including psychomotor agitation, confusion, and hallucinations.
Serotonin syndrome, seizures, cerebral vascular accidents, and coma may occur. • Life-threatening hyperthermia (temperatures greater than 104°F) and rhabdomyolysis may develop. Overdose Management Consider the possibility of multiple drug ingestion. D-amphetamine is not dialyzable.
Consider contacting the Poison Help line (1-800-222-1222) or a medical toxicologist for additional overdose management recommendations.
Overdose Management Consider the possibility of multiple drug ingestion. D-amphetamine is not dialyzable. Consider contacting the Poison Help line (1-800-222-1222) or a medical toxicologist for additional overdose management recommendations.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Pharmacodynamics Amphetamines are non-catecholamine sympathomimetic amines with CNS stimulant activity. The mode of therapeutic action in Attention Deficit Hyperactivity Disorder (ADHD) is not known. Amphetamines are thought to block the reuptake of norepinephrine and dopamine into the presynaptic neuron and increase the release of these monoamines into the extraneuronal space.
Pharmacokinetics Mixed salts of a single entity amphetamine product contain d-amphetamine and l-amphetamine salts in the ratio of 3:1. Following administration of a single dose 10 mg or 30 mg of mixed salts of a single entity amphetamine product to healthy volunteers under fasted conditions, peak plasma concentrations occurred approximately 3 hours post-dose for both d-amphetamine and l-amphetamine. The mean elimination half‑life (t ½ ) for d-amphetamine was shorter than the t ½ of the l-isomer (9.77 to 11 hours vs.
11.5to 13.8 hours). The PK parameters (C max , AUC 0-inf ) of d-and l-amphetamine increased approximately three-fold from 10 mg to 30 mg indicating dose-proportional pharmacokinetics. The effect of food on the bioavailability of mixed salts of a single entity amphetamine product has not been studied.
Metabolism and Excretion Amphetamine is reported to be oxidized at the 4 position of the benzene ring to form 4‑hydroxyamphetamine, or on the side chain α or β carbons to form alpha-hydroxy-amphetamine or norephedrine, respectively. Norephedrine and 4-hydroxy-amphetamine are both active and each is subsequently oxidized to form 4-hydroxy-norephedrine. Alpha-hydroxy-amphetamine undergoes deamination to form phenylacetone, which ultimately forms benzoic acid and its glucuronide and the glycine conjugate hippuric acid.
Although the enzymes involved in amphetamine metabolism have not been clearly defined, CYP2D6 is known to be involved with formation of 4-hydroxy-amphetamine. Since CYP2D6 is genetically polymorphic, population variations in amphetamine metabolism are a possibility. Amphetamine is known to inhibit monoamine oxidase, whereas the ability of amphetamine and its metabolites to inhibit various P450 isozymes and other enzymes has not been adequately elucidated.
In vitro experiments with human microsomes indicate minor inhibition of CYP2D6 by amphetamine and minor inhibition of CYP1A2, 2D6, and 3A4 by one or more metabolites. However, due to the probability of auto-inhibition and the lack of information on the concentration of these metabolites relative to in vivo concentrations, no predications regarding the potential for amphetamine or its metabolites to inhibit the metabolism of other drugs by CYP isozymes in vivo can be made. With normal urine pHs approximately half of an administered dose of amphetamine is recoverable in urine as derivatives of alpha-hydroxy-amphetamine and approximately another 30% to 40% of the dose is recoverable in urine as amphetamine itself.
Since amphetamine has a pKa of 9.9, urinary recovery of amphetamine is highly dependent on pH and urine flow rates. Alkaline urine pHs result in less ionization and reduced renal elimination, and acidic pHs and high flow rates result in increased renal elimination with clearances greater than glomerular filtration rates, indicating the involvement of active secretion. Urinary recovery of amphetamine has been reported to range from 1% to 75%, depending on urinary pH, with the remaining fraction of the dose hepatically metabolized.
Consequently, both hepatic and renal dysfunction have the potential to inhibit the elimination of amphetamine and result in prolonged exposures. In addition, drugs that affect urinary pH are known to alter the elimination of amphetamine, and any decrease in amphetamine’s metabolism that might occur due to drug interactions or genetic polymorphisms is more likely to be clinically significant when renal elimination is decreased (see PRECAUTIONS ).
📦 How Supplied / Storage and Handling ▾
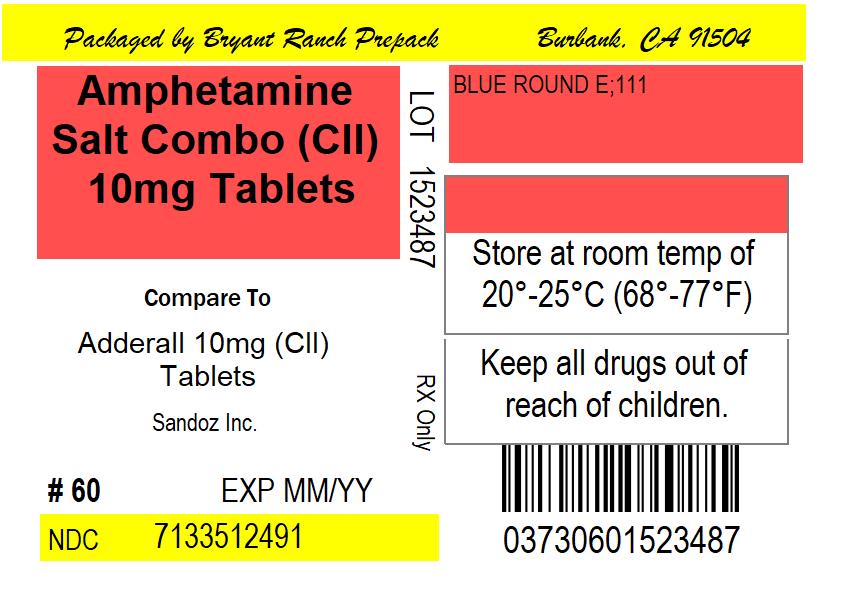
HOW SUPPLIED Dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets (Mixed salts of a single entity amphetamine product), for oral administration, are available as: 10 mg Dark blue, round, biconvex tablets, debossed “E” over “111” on one side and double-bisected on the other side and supplied as: NDC: 71335-1249-1: 60 Tablets in a BOTTLE NDC: 71335-1249-2: 30 Tablets in a BOTTLE NDC: 71335-1249-3: 90 Tablets in a BOTTLE NDC: 71335-1249-4: 120 Tablets in a BOTTLE NDC: 71335-1249-5: 18 Tablets in a BOTTLE Dispense contents in a tight, light-resistant container as defined in the USP with a child-resistant closure, as required.
Protect from light and moisture. Keep tightly closed. Store at 20°C to 25°C (68°F to 77°F) (See USP Controlled Room Temperature).
KEEP OUT OF THE REACH OF CHILDREN. Repackaged/Relabeled by: Bryant Ranch Prepack, Inc. Burbank, CA 91504
📋 Description ▾
DESCRIPTION A single-entity amphetamine product combining the neutral sulfate salts of dextroamphetamine and amphetamine, with the dextro isomer of amphetamine saccharate and d, l-amphetamine aspartate monohydrate. Each Tablet Contains 5 mg 10 mg 20 mg 30 mg Dextroamphetamine Saccharate 1.25 mg 2.5 mg 5 mg 7.5 mg Amphetamine Aspartate Monohydrate 1.25 mg 2.5 mg 5 mg 7.5 mg Dextroamphetamine Sulfate, USP 1.25 mg 2.5 mg 5 mg 7.5 mg Amphetamine Sulfate, USP 1.25 mg 2.5 mg 5 mg 7.5 mg Total Amphetamine Base Equivalence 3.13 mg 6.3 mg 12.6 mg 18.8 mg Inactive Ingredients: lactose monohydrate, pregelatinized starch (corn) and magnesium stearate.
Color Additives: FD&C blue No. 1 aluminum lake (for 5 mg and 10 mg strengths) and FD&C yellow No. 6 aluminum lake (for 20 mg and 30 mg strengths).
💬 Information for Patients ▾
Information for Patients Advise the patient to read the FDA-approved patient labeling (Medication Guide). Abuse, Misuse, and Addiction Educate patients and their families about the risks of abuse, misuse, and addiction of dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate, which can lead to overdose and death, and proper disposal of any unused drug (see WARNINGS , DRUG ABUSE AND DEPENDENCE , OVERDOSAGE ). Advise patients to store dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate in a safe place, preferably locked, and instruct patients to not give dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate to anyone else.
Risks to Patients with Serious Cardiac Disease Advise patients that there are potential risks to patients with serious cardiac disease, including sudden death, with dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate use. Instruct patients to contact a healthcare provider immediately if they develop symptoms such as exertional chest pain, unexplained syncope, or other symptoms suggestive of cardiac disease (see WARNINGS ). Increased Blood Pressure and Heart Rate Advise patients that dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate can elevate blood pressure and heart rate (see WARNINGS ).
Psychiatric Adverse Reactions Advise patients that dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate, at recommended doses, can cause psychotic or manic symptoms, even in patients without prior history of psychotic symptoms or mania (see WARNINGS ). Long-Term Suppression of Growth in Pediatric Patients Advise patients that dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate may cause slowing of growth including weight loss (see WARNINGS ) .
Circulation Problems in Fingers and Toes (Peripheral Vasculopathy, Including Raynaud’s Phenomenon) • Instruct patients beginning treatment with dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate about the risk of peripheral vasculopathy, including Raynaud’s phenomenon, and associated signs and symptoms: fingers or toes may feel numb, cool, painful, and/or may change color from pale, to blue, to red. • Instruct patients to report to their physician any new numbness, pain, skin color change, or sensitivity to temperature in fingers or toes. • Instruct patients to call their physician immediately with any signs of unexplained wounds appearing on fingers or toes while taking dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate. • Further clinical evaluation (e.g., rheumatology referral) may be appropriate for certain patients.
Serotonin Syndrome Caution patients about the risk of serotonin syndrome with concomitant use of dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate and other serotonergic drugs including SSRIs, SNRIs, triptans, tricyclic antidepressants, fentanyl, lithium, tramadol, tryptophan, buspirone, St. John's Wort, and with drugs that impair metabolism of serotonin (in particular MAOIs, both those intended to treat psychiatric disorders and also others such as linezolid (see CONTRAINDICATIONS , WARNINGS , and DRUG INTERACTIONS ) .
Advise patients to contact their healthcare provider or report to the emergency room if they experience signs or symptoms of serotonin syndrome. Motor and Verbal Tics, and Worsening of Tourette’s Syndrome Advise patients that motor and verbal tics and worsening of Tourette’s Syndrome may occur during treatment with dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate. Instruct the patients to notify the… [Excerpted — this section continues on DailyMed.]
💬 Medication Guide ▾
Medication Guide Dextroamphetamine Saccharate, Amphetamine Aspartate, Dextroamphetamine Sulfate and Amphetamine Sulfate Tablets, CII (dex-troe-am-FET-ah-meen) What is the most important information I should know about mixed salts of a single entity amphetamine product? Mixed salts of a single entity amphetamine product may cause serious side effects, including: • Abuse, misuse, and addiction. Mixed salts of a single entity amphetamine product has a high chance for abuse and misuse and may lead to substance use problems, including addiction.
Misuse and abuse of mixed salts of a single entity amphetamine product, other amphetamine containing medicines, and methylphenidate containing medicines, can lead to overdose and death. The risk of overdose and death is increased with higher doses of mixed salts of a single entity amphetamine product or when it is used in ways that are not approved, such as snorting or injection. o Your healthcare provider should check you or your child’s risk for abuse, misuse, and addiction before starting treatment with mixed salts of a single entity amphetamine product and will monitor you or your child during treatment. o Mixed salts of a single entity amphetamine product may lead to physical dependence after prolonged use, even if taken as directed by your healthcare provider. o Do not give mixed salts of a single entity amphetamine product to anyone else.
See “What is mixed salts of a single entity amphetamine product?” for more information. o Keep mixed salts of a single entity amphetamine product in a safe place and properly dispose of any unused medicine. See “How should I store mixed salts of a single entity amphetamine product?” for more information. o Tell your healthcare provider if you or your child have ever abused or been dependent on alcohol, prescription medicines, or street drugs. o Risks for people with serious heart disease: Sudden death has happened in people who have heart defects or other serious heart disease.
Your healthcare provider should check you or your child carefully for heart problems before starting treatment with mixed salts of a single entity amphetamine product. Tell your healthcare provider if you or your child have any heart problems, heart disease, or heart defects. Call your healthcare provider right away or go to the nearest hospital emergency room right away if you or your child have any signs of heart problems such as chest pain, shortness of breath, or fainting during treatment with mixed salts of a single entity amphetamine product. • Increased blood pressure and heart rate.
Your healthcare provider should check you or your child’s blood pressure and heart rate regularly during treatment with mixed salts of a single entity amphetamine product. • Mental (psychiatric) problems, including: o new or worse behavior and thought problems o new or worse bipolar illness o new psychotic symptoms (such as hearing voices, or seeing or believing things that are not real) or new manic symptoms Tell your healthcare provider about any mental problems you or your child have, or about a family history of suicide, bipolar illness, or depression.
Call your healthcare provider right away if you or your child have any new or worsening mental symptoms or problems during treatment with mixed salts of a single entity amphetamine product, especially hearing voices, seeing or believing things that are not real, or new manic symptoms. What is mixed salts of a single entity amphetamine product? Mixed salts of a single entity amphetamine product is a central nervous system (CNS) stimulant prescription medicine used for the treatment of: • Attention-Deficit Hyperactivity Disorder (ADHD) in children 3 to 17 years of age.
Mixed salts of a single entity amphetamine product may help increase attention and decrease impulsiveness and hyperactivity in people with ADHD. • a sleep disorder called narcolepsy in people 6 years and older. It is not known if mixed salts of a single entity amphetamine pr… [Excerpted — this section continues on DailyMed.]
⚠️ Precautions ▾
PRECAUTIONS Information for Patients Advise the patient to read the FDA-approved patient labeling (Medication Guide). Abuse, Misuse, and Addiction Educate patients and their families about the risks of abuse, misuse, and addiction of dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate, which can lead to overdose and death, and proper disposal of any unused drug (see WARNINGS , DRUG ABUSE AND DEPENDENCE , OVERDOSAGE ). Advise patients to store dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate in a safe place, preferably locked, and instruct patients to not give dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate to anyone else.
Risks to Patients with Serious Cardiac Disease Advise patients that there are potential risks to patients with serious cardiac disease, including sudden death, with dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate use. Instruct patients to contact a healthcare provider immediately if they develop symptoms such as exertional chest pain, unexplained syncope, or other symptoms suggestive of cardiac disease (see WARNINGS ). Increased Blood Pressure and Heart Rate Advise patients that dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate can elevate blood pressure and heart rate (see WARNINGS ).
Psychiatric Adverse Reactions Advise patients that dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate, at recommended doses, can cause psychotic or manic symptoms, even in patients without prior history of psychotic symptoms or mania (see WARNINGS ). Long-Term Suppression of Growth in Pediatric Patients Advise patients that dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate may cause slowing of growth including weight loss (see WARNINGS ) .
Circulation Problems in Fingers and Toes (Peripheral Vasculopathy, Including Raynaud’s Phenomenon) • Instruct patients beginning treatment with dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate about the risk of peripheral vasculopathy, including Raynaud’s phenomenon, and associated signs and symptoms: fingers or toes may feel numb, cool, painful, and/or may change color from pale, to blue, to red. • Instruct patients to report to their physician any new numbness, pain, skin color change, or sensitivity to temperature in fingers or toes. • Instruct patients to call their physician immediately with any signs of unexplained wounds appearing on fingers or toes while taking dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate. • Further clinical evaluation (e.g., rheumatology referral) may be appropriate for certain patients.
Serotonin Syndrome Caution patients about the risk of serotonin syndrome with concomitant use of dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate and other serotonergic drugs including SSRIs, SNRIs, triptans, tricyclic antidepressants, fentanyl, lithium, tramadol, tryptophan, buspirone, St. John's Wort, and with drugs that impair metabolism of serotonin (in particular MAOIs, both those intended to treat psychiatric disorders and also others such as linezolid (see CONTRAINDICATIONS , WARNINGS , and DRUG INTERACTIONS ) .
Advise patients to contact their healthcare provider or report to the emergency room if they experience signs or symptoms of serotonin syndrome. Motor and Verbal Tics, and Worsening of Tourette’s Syndrome Advise patients that motor and verbal tics and worsening of Tourette’s Syndrome may occur during treatment with dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate. Instruct the patients t… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
Pharmacokinetics Mixed salts of a single entity amphetamine product contain d-amphetamine and l-amphetamine salts in the ratio of 3:1. Following administration of a single dose 10 mg or 30 mg of mixed salts of a single entity amphetamine product to healthy volunteers under fasted conditions, peak plasma concentrations occurred approximately 3 hours post-dose for both d-amphetamine and l-amphetamine. The mean elimination half‑life (t ½ ) for d-amphetamine was shorter than the t ½ of the l-isomer (9.77 to 11 hours vs.
11.5to 13.8 hours). The PK parameters (C max , AUC 0-inf ) of d-and l-amphetamine increased approximately three-fold from 10 mg to 30 mg indicating dose-proportional pharmacokinetics. The effect of food on the bioavailability of mixed salts of a single entity amphetamine product has not been studied.
🧬 Pharmacodynamics ▾
Pharmacodynamics Amphetamines are non-catecholamine sympathomimetic amines with CNS stimulant activity. The mode of therapeutic action in Attention Deficit Hyperactivity Disorder (ADHD) is not known. Amphetamines are thought to block the reuptake of norepinephrine and dopamine into the presynaptic neuron and increase the release of these monoamines into the extraneuronal space.
🔒 Drug Abuse and Dependence ▾
DRUG ABUSE AND DEPENDENCE Controlled Substance Mixed salts of a single entity amphetamine product contains amphetamine, a Schedule II controlled substance. Abuse Dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate has a high potential for abuse and misuse which can lead to the development of a substance use disorder, including addiction (see WARNINGS and PRECAUTIONS ). Dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate can be diverted for non‑medical use into illicit channels or distribution.
Abuse is the intentional non-therapeutic use of a drug, even once, to achieve a desired psychological or physiological effect. Misuse is the intentional use, for therapeutic purposes, of a drug by an individual in a way other than prescribed by a health care provider or for whom it was not prescribed. Drug addiction is a cluster of behavioral, cognitive, and physiological phenomena that may include a strong desire to take the drug, difficulties in controlling drug use (e.g., continuing drug use despite harmful consequences, giving a higher priority to drug use than other activities and obligations), and possible tolerance or physical dependence.
Misuse and abuse of amphetamines may cause increased heart rate, respiratory rate, or blood pressure; sweating; dilated pupils; hyperactivity; restlessness; insomnia; decreased appetite; loss of coordination; tremors; flushed skin; vomiting; and/or abdominal pain. Anxiety, psychosis, hostility, aggression, and suicidal or homicidal ideation have also been observed with CNS stimulants abuse and/or misuse. Misuse and abuse of CNS stimulants, including dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate, can result in overdose and death (see OVERDOSAGE ), and this risk is increased with higher doses or unapproved methods of administration, such as snorting or injection.
Dependence Physical Dependence Dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate may produce physical dependence. Physical dependence is a state that develops as a result of physiological adaptation in response to repeated drug use, manifested by withdrawal signs and symptoms after abrupt discontinuation or a significant dose reduction of a drug. Withdrawal signs and symptoms after abrupt discontinuation or dose reduction following prolonged use of CNS stimulants including dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate include dysphoric mood; depression; fatigue; vivid, unpleasant dreams; insomnia or hypersomnia; increased appetite; and psychomotor retardation or agitation.
Tolerance Dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate may produce tolerance. Tolerance is a physiological state characterized by a reduced response to a drug after repeated administration (i.e., a higher dose of a drug is required to produce the same effect that was once obtained at a lower dose).
🔒 Controlled Substance ▾
Controlled Substance Mixed salts of a single entity amphetamine product contains amphetamine, a Schedule II controlled substance. Abuse Dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate has a high potential for abuse and misuse which can lead to the development of a substance use disorder, including addiction (see WARNINGS and PRECAUTIONS ). Dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate can be diverted for non‑medical use into illicit channels or distribution.
Abuse is the intentional non-therapeutic use of a drug, even once, to achieve a desired psychological or physiological effect. Misuse is the intentional use, for therapeutic purposes, of a drug by an individual in a way other than prescribed by a health care provider or for whom it was not prescribed. Drug addiction is a cluster of behavioral, cognitive, and physiological phenomena that may include a strong desire to take the drug, difficulties in controlling drug use (e.g., continuing drug use despite harmful consequences, giving a higher priority to drug use than other activities and obligations), and possible tolerance or physical dependence.
Misuse and abuse of amphetamines may cause increased heart rate, respiratory rate, or blood pressure; sweating; dilated pupils; hyperactivity; restlessness; insomnia; decreased appetite; loss of coordination; tremors; flushed skin; vomiting; and/or abdominal pain. Anxiety, psychosis, hostility, aggression, and suicidal or homicidal ideation have also been observed with CNS stimulants abuse and/or misuse. Misuse and abuse of CNS stimulants, including dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate, can result in overdose and death (see OVERDOSAGE ), and this risk is increased with higher doses or unapproved methods of administration, such as snorting or injection.
📄 Package Label / Principal Display Panel ▾
Dextroamphetamine Saccharate, Amphetamine Aspartate, Dextroamphetamine Sulfate and Amphetamine Sulfate Tablets (CII) 10 mg Label
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |