
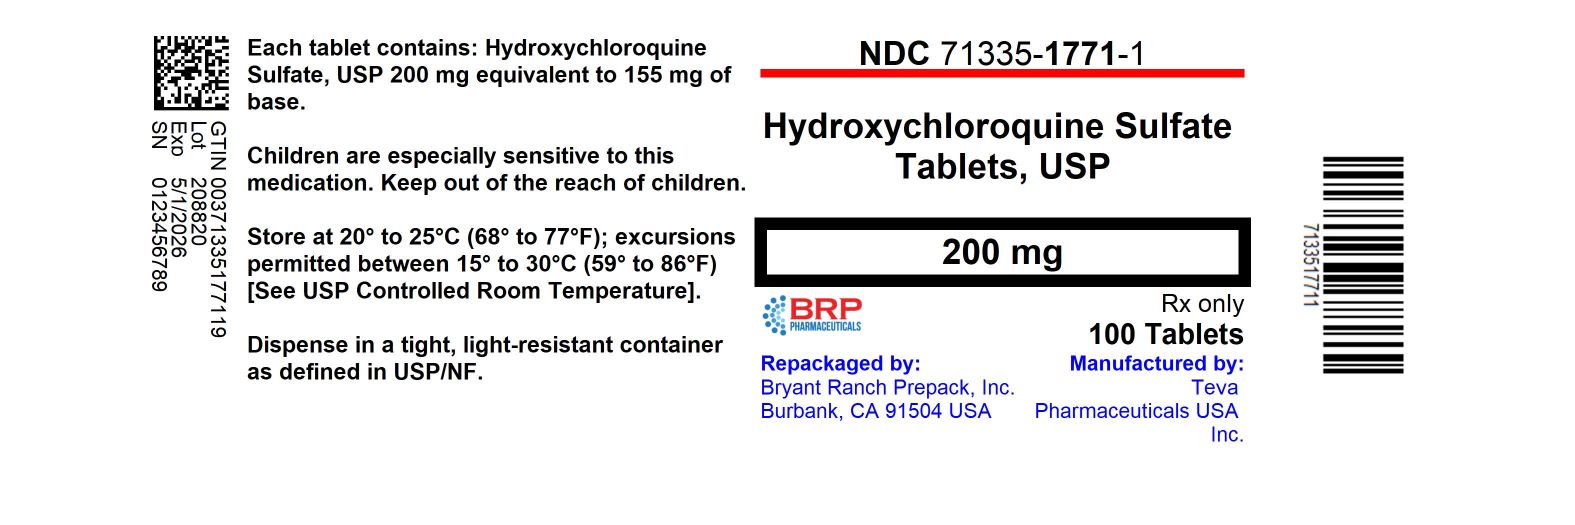
Hydroxychloroquine Sulfate 200 mg Tablet, Film Coated, 14-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Antimalarial class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- It has two main uses. First, it treats and helps prevent malaria — a parasitic infection spread by mosquitoes — in both adults and children. Second, it helps manage autoimmune cond...
- What exactly is hydroxychloroquine used for?
- Always take it by mouth with food or milk — this helps protect your stomach and reduces nausea. Don't crush or split the tablet unless your specific product allows it; check your l...
- How should I take my hydroxychloroquine tablet?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII O7TSZ97GEP
A mineral compound that serves as a filler and binding agent in tablets and capsules. It adds bulk to the medicine and helps hold ingredients together during manufacturing.
-
UNII 0VUT3PMY82
Hypromellose 2910 is a plant-derived thickening agent made from cellulose. In medicines, it forms protective coatings on tablets or capsules, controls how fast the drug releases, and thickens liquid formulations.
-
UNII 1IVH67816N
Hypromellose 2910 is a plant-derived cellulose compound used as a thickener and film-former in medicines. It helps control how quickly the medication dissolves and creates protective coatings on tablets or capsules.
-
UNII 0WZ8WG20P6
Hypromellose 2910 is a plant-based cellulose derivative that acts as a thickener, binder, and film-coating agent. It helps control how quickly the medicine dissolves and protects the tablet or capsule from moisture and light.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII VH2XOU12IE
Polydextrose is a synthetic polymer made from dextrose (sugar) that acts as a bulking agent and filler in medicines. It helps give tablets and capsules proper volume and texture while often adding slight sweetness.
-
UNII Q662QK8M3B
Polyethylene glycol 8000 is a synthetic polymer made from ethylene oxide. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and add bulk to the medicine.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII XHX3C3X673
Triacetin is a clear, oily liquid made from glycerin and acetic acid. It works as a plasticizer and solvent in medicines, helping soften coatings and improve how liquids mix together in formulations.
10 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.3275 | $4.59 / 14 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Hydroxychloroquine Sulfate 200 mg 00093-2401-01 | Teva | 100 tablets | $0.149 | AB | Availability likely | — |
| Hydroxychloroquine Sulfate 200 mg 00904-7046-06 | Major | 50 tablets | $0.149 | AB | Availability likely | — |
| Hydroxychloroquine Sulfate 200 mg 16571-0112-01 | Rising | 100 tablets | $0.149 | AB | Availability likely | — |
| Hydroxychloroquine sulfate 200 mg 16714-0110-01 | Northstar | 100 tablets | $0.149 | AB | Availability likely | — |
| Hydroxychloroquine Sulfate 200 mg 16729-0485-01 | Accord | 100 tablets | $0.149 | AB | Availability likely | — |
| Hydroxychloroquine Sulfate 200 mg 43598-0721-01 | Dr. | 100 tablets | $0.149 | AB | Availability likely | — |
| Hydroxychloroquine Sulfate 200 mg 50268-0412-15 | AvPAK | 50 tablets | $0.149 | AB | Availability likely | — |
| Hydroxychloroquine Sulfate 200 mg 59651-0889-01 | Aurobindo | 100 tablets | $0.149 | AB | Availability likely | — |
| Hydroxychloroquine 200 mg 62135-0752-90 | Chartwell | 90 tablets | $0.149 | AB | Availability likely | — |
| Hydroxychloroquine Sulfate 200 mg 68084-0269-01 | American | 1 tablet | $0.149 | AB | Availability likely | — |
| Hydroxychloroquine sulfate 200 mg 68382-0096-01 | Zydus | 100 tablets | $0.149 | AB | Availability likely | — |
| Hydroxychloroquine Sulfate 200 mg 69238-1544-01 | Amneal | 100 tablets | $0.149 | AB | Availability likely | — |
| Hydroxychloroquine sulfate 200 mg 82009-0045-05 | Quallent | 500 tablets | $0.149 | AB | Availability likely | — |
| Hydroxychloroquine Sulfate 200 mg 83980-0001-01 | Ipca | 100 tablets | $0.149 | AB | Availability likely | — |
| Hydroxychloroquine sulfate 200 mg 57664-0761-13 | Sun | 500 tablets | $0.176 | AB | FDA listed | — |
| Hydroxychloroquine sulfate 200 mg 00615-8459-39 | NCS | 30 tablets | — | AB | FDA listed | — |
| Hydroxychloroquine Sulfate 200 mg 42385-0971-01 | Laurus | 100 tablets | — | AB | FDA listed | — |
| Hydroxychloroquine Sulfate 200 mg 50090-4659-01 | A-S | 60 tablets | — | AB | Discontinued | — |
| Hydroxychloroquine sulfate 200 mg 50090-5573-00 | A-S | 30 tablets | — | AB | Discontinued | — |
| Hydroxychloroquine Sulfate 200 mg 50090-6280-01 | A-S | 60 tablets | — | AB | FDA listed | — |
| Hydroxychloroquine sulfate 200 mg 50090-6629-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Hydroxychloroquine sulfate 200 mg 50090-7306-01 | A-S | 60 tablets | — | AB | FDA listed | — |
| Hydroxychloroquine sulfate 200 mg 50090-7307-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Hydroxychloroquine sulfate 200 mg 55154-2074-00 | Cardinal | 1 tablet | — | AB | FDA listed | — |
| Hydroxychloroquine Sulfate 200 mg 55154-3567-00 | Cardinal | 10 tablets | — | AB | FDA listed | — |
| Plaquenil 200 mg 59212-0562-10 | Advanz | 100 tablets | — | AB | FDA listed | — |
| Hydroxychloroquine Sulfate 200 mg 60219-1544-01 | Amneal | 100 tablets | — | AB | FDA listed | — |
| Hydroxychloroquine sulfate 200 mg 65841-0633-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
| Hydroxychloroquine Sulfate 200 mg 67046-1523-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| Hydroxychloroquine sulfate 200 mg 68071-2332-01 | NuCare | 100 tablets | — | AB | FDA listed | — |
| Hydroxychloroquine sulfate 200 mg 68071-3955-06 | NuCare | 60 tablets | — | AB | FDA listed | — |
| Hydroxychloroquine sulfate 200 mg 68788-7747-02 | Preferred | 20 tablets | — | AB | FDA listed | — |
| Sovuna 200 mg 70954-0804-10 | ANI | 30 tablets | — | — | FDA listed | — |
| Plaquenil 200 mg 71205-0448-12 | Proficient | 12 tablets | — | AB | FDA listed | — |
| Hydroxychloroquine sulfate 200 mg 71335-0897-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Hydroxychloroquine Sulfate 200 mg 71335-1523-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Hydroxychloroquine Sulfate 200 mgthis 71335-1771-08 | Bryant | 14 tablets | — | AB | FDA listed | — |
| Hydroxychloroquine Sulfate 200 mg 71335-2813-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Hydroxychloroquine Sulfate 200 mg 71335-2814-01 | Bryant | 500 tablets | — | AB | FDA listed | — |
| Hydroxychloroquine Sulfate 200 mg 71335-3079-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Hydroxychloroquine Sulfate 200 mg 71335-3113-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Hydroxychloroquine Sulfate 200 mg 71335-3142-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Plaquenil 200 mg 71610-0473-30 | Aphena | 30 tablets | — | AB | FDA listed | — |
| Hydroxychloroquine sulfate 200 mg 71610-0506-30 | Aphena | 30 tablets | — | AB | FDA listed | — |
| Hydroxychloroquine Sulfate 200 mg 71610-0701-53 | Aphena | 60 tablets | — | AB | FDA listed | — |
| Hydroxychloroquine Sulfate 200 mg 71610-0961-30 | Aphena | 30 tablets | — | AB | FDA listed | — |
| Hydroxychloroquine Sulfate 200 mg 72162-2467-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Hydroxychloroquine sulfate 200 mg 76420-0850-01 | Asclemed | 100 tablets | — | AB | FDA listed | — |
| Hydroxychloroquine Sulfate 200 mg 82619-0131-01 | Creekwood | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 71335-1771-01 | 100 TABLET, FILM COATED in 1 BOTTLE (71335-1771-1) | 2021-09-02 | Active |
| 71335-1771-02 | 30 TABLET, FILM COATED in 1 BOTTLE (71335-1771-2) | 2021-08-19 | Active |
| 71335-1771-03 | 60 TABLET, FILM COATED in 1 BOTTLE (71335-1771-3) | 2021-12-29 | Active |
| 71335-1771-04 | 180 TABLET, FILM COATED in 1 BOTTLE (71335-1771-4) | 2021-01-21 | Active |
| 71335-1771-05 | 90 TABLET, FILM COATED in 1 BOTTLE (71335-1771-5) | 2021-12-29 | Active |
| 71335-1771-06 | 120 TABLET, FILM COATED in 1 BOTTLE (71335-1771-6) | 2021-12-29 | Active |
| 71335-1771-07 | 10 TABLET, FILM COATED in 1 BOTTLE (71335-1771-7) | 2021-08-16 | Active |
| 71335-1771-08 You're viewing this | 14 TABLET, FILM COATED in 1 BOTTLE (71335-1771-8) | 2021-12-29 | Active |
| 71335-1771-09 | 20 TABLET, FILM COATED in 1 BOTTLE (71335-1771-9) | 2021-08-18 | Active |
You're viewing one of 9 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 71335-1771-08?
What is the difference between NDC 71335-1771-08 and NDC 71335-1771-07?
What NDC number is used to bill for this package of Hydroxychloroquine Sulfate 200 mg Tablet, Film Coated?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Hydroxychloroquine sulfate tablets are an antimalarial and antirheumatic indicated for the: Treatment of uncomplicated malaria due to Plasmodium falciparum, Plasmodium malariae, Plasmodium ovale, and Plasmodium vivax in adult and pediatric patients. ( 1.1 ) Prophylaxis of malaria in geographic areas where chloroquine resistance is not reported in adult and pediatric patients. ( 1.1 ) Treatment of rheumatoid arthritis in adults.
( 1.2 ) Treatment of systemic lupus erythematosus in adults. ( 1.3 ) Treatment of chronic discoid lupus erythematosus in adults. ( 1.4 ) Limitations of Use ( 1.1 ) : Hydroxychloroquine sulfate tablets are not recommended for the: Treatment of complicated malaria.
Treatment of chloroquine or hydroxychloroquine-resistant strains of Plasmodium species. Treatment of malaria acquired in geographic areas where chloroquine resistance occurs or when the Plasmodium species has not been identified. Prophylaxis of malaria in geographic areas where chloroquine resistance occurs.
Prevention of relapses of P. vivax or P. ovale because it is not active against the hypnozoite liver stage forms of these parasites. For radical cure of P. vivax and P. ovale infections, concomitant therapy with an 8-aminoquinoline drug is necessary.
1.1Malaria Hydroxychloroquine sulfate tablets are indicated in adult and pediatric patients for the: Treatment of uncomplicated malaria due to Plasmodium falciparum, Plasmodium malariae, Plasmodium vivax, and Plasmodium ovale. Prophylaxis of malaria in geographic areas where chloroquine resistance is not reported. Limitations of Use: Hydroxychloroquine sulfate tablets are not recommended for: Treatment of complicated malaria.
Treatment of malaria by chloroquine or hydroxychloroquine-resistant strains of Plasmodium species [see Microbiology ( 12.4 )]. Treatment of malaria acquired in geographic areas where chloroquine resistance occurs or when the Plasmodium species has not been identified. Prophylaxis of malaria in geographic areas where chloroquine resistance occurs.
Prevention of relapses of P. vivax or P. ovale because it is not active against the hypnozoite liver stage forms of these parasites. For radical cure of P. vivax and P. ovale infections, concomitant therapy with an 8-aminoquinoline drug is necessary [see Microbiology ( 12.4 )]. For the most current information about drug resistance, refer to the latest recommendations from the Center for Disease Control and Prevention 1 .
1.2Rheumatoid Arthritis Hydroxychloroquine sulfate tablets are indicated for the treatment of acute and chronic rheumatoid arthritis in adults.
1.3Systemic Lupus Erythematosus Hydroxychloroquine sulfate tablets are indicated for the treatment of systemic lupus erythematosus in adults.
1.4Chronic Discoid Lupus Erythematosus Hydroxychloroquine sulfate tablets are indicated for the treatment of chronic discoid lupus erythematosus in adults.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Malaria in Adult and Pediatric Patients ( 2.2 ): Prophylaxis: Begin weekly doses 2 weeks prior to travel to the endemic area, continue weekly doses while in the endemic area, and continue the weekly doses for 4 weeks after leaving the endemic area: - Adults: 400 mg once a week - Pediatric patients ≥ 31 kg: 6.5 mg/kg up to 400 mg, once a week Treatment of Uncomplicated Malaria: See Full Prescribing Information (FPI) for complete dosing information. Rheumatoid Arthritis in Adults ( 2.3 ): Initial dosage: 400 mg to 600 mg daily Chronic dosage: 200 mg once daily or 400 mg once daily (or in two divided doses) Systemic Lupus Erythematosus in Adults ( 2.4 ): 200 mg once daily or 400 mg once daily (or in two divided doses) Chronic Discoid Lupus Erythematosus in Adults ( 2.5 ): 200 mg once daily or 400 mg once daily (or in two divided doses)
2.1Important Administration Instructions Administer hydroxychloroquine sulfate tablets orally with food or milk. Do not crush or divide the tablets.
2.2Dosage for Malaria in Adult and Pediatric Patients Hydroxychloroquine sulfate tablets are not recommended in pediatric patients less than 31 kg because the lowest available strength (200 mg) exceeds the recommended dose for these patients and it cannot be divided. Prophylaxis Treatment must start 2 weeks before travel to an endemic area. Advise the patient to take the prophylaxis dosage once a week, staring 2 weeks prior to travel to the endemic area, on the same day every week, continuing the same weekly dose while in the endemic area, and for 4 weeks after leaving the endemic area.
The recommended prophylaxis dosage is: Adult patients: 400 mg once a week Pediatric patients ≥ 31kg: 6.5 mg/kg actual body weight (up to 400 mg) once a week Treatment of Uncomplicated Malaria The dosages for the treatment of uncomplicated malaria are: Adult patients: Administer 800 mg initially; subsequently administer 400 mg at 6 hours, 24 hours, and 48 hours after the initial dose (total dosage = 2000 mg). Pediatric patients ≥ 31 kg: Administer 13 mg/kg (up to 800 mg) initially; subsequently administer 6.5 mg/kg (up to 400 mg) at 6 hours, 24 hours, and 48 hours after the initial dose (total dosage = 31 mg/kg - up to 2000 mg).
For radical cure of P. vivax and P. ovale infections, concomitant therapy with an 8-aminoquinoline drug is necessary [see Microbiology ( 12.4 )].
2.3Dosage for Rheumatoid Arthritis in Adults The recommended dosage is: Initial dosage: 400 mg to 600 mg daily as a single daily dose or two divided doses. The action of hydroxychloroquine is cumulative and may require weeks to months for maximum therapeutic effect. Daily doses exceeding 5 mg/kg (actual weight) of hydroxychloroquine sulfate increase the incidence of retinopathy [see Warnings and Precautions ( 5.2 )].
Chronic dosage: 200 mg once daily to 400 mg daily, as a single dose or two divided doses. Corticosteroids, salicylates, and other antirheumatic agents may be used concomitantly with hydroxychloroquine sulfate tablets.
2.4Dosage for Systemic Lupus Erythematosus in Adults The recommended dosage is 200 mg given once daily, or 400 mg given once daily or in two divided doses.
2.5Dosage for Chronic Discoid Lupus Erythematosus in Adults The recommended dosage is 200 mg given once daily, or 400 mg given once daily or in two divided doses.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets: 200 mg of hydroxychloroquine sulfate, white, unscored, film-coated, capsule-shaped tablets debossed “TV” and “2401” on one side and plain on the other side. Tablets: 200 mg of hydroxychloroquine sulfate ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Hydroxychloroquine sulfate tablets are contraindicated in patients with known hypersensitivity to 4-aminoquinoline compounds. Patients with hypersensitivity to 4-aminoquinoline compounds ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Cardiomyopathy and Ventricular Arrhythmias : Fatal or life-threatening cardiomyopathy and ventricular arrhythmias were reported. ( 5.1 ) Retinal Toxicity : Irreversible retinal damage is related to cumulative dosage and treatment duration. Baseline retinal exam and exams during treatment are recommended.
( 5.2 ) Serious Skin Reactions : Stevens Johnson syndrome, toxic epidermal necrolysis, drug reaction with eosinophilia and systemic symptoms, acute generalized exanthematous pustulosis have been reported. ( 5.3 ) Worsening of Psoriasis : Avoid in patients with psoriasis. ( 5.4 ) Risks Associated with Use in Porphyria: Avoid in patients with porphyria.
Hepatotoxicity was reported in patients with porphyria cutanea tarda ( 5.5 ). Hematologic Toxicity : Discontinue if myelosuppression occurs. ( 5.6 ) Renal Toxicity : Consider phospholipidosis as a possible cause of renal injury in patients with underlying connective tissue disorders.
Discontinue hydroxychloroquine sulfate if renal toxicity is suspected or demonstrated by tissue biopsy in any organ system. ( 5.1 , 5.8 , 5.11 )
5.1Cardiomyopathy and Ventricular Arrhythmias Fatal and life-threatening cases of cardiotoxicity, including cardiomyopathy, have been reported in patients treated with hydroxychloroquine sulfate tablets. Signs and symptoms of cardiac compromise have occurred during acute and chronic hydroxychloroquine sulfate tablets treatment. In multiple cases, endomyocardial biopsy showed association of the cardiomyopathy with phospholipidosis in the absence of inflammation, infiltration, or necrosis.
Drug-induced phospholipidosis may occur in other organ systems [see Warnings and Precautions ( 5.8 , 5.11 )] . Patients may present with ventricular hypertrophy, pulmonary hypertension and conduction disorders including sick sinus syndrome. ECG findings include atrioventricular, right or left bundle branch block.
Hydroxychloroquine sulfate has a potential to prolong the QT interval. Ventricular arrhythmias (including torsades de pointes) have been reported in hydroxychloroquine sulfate tablets-treated patients. The magnitude of QT prolongation may increase with increasing concentrations of the drug.
Therefore, the recommended dose should not be exceeded [see Adverse Reactions ( 6 ) , Overdosage ( 10 )]. Avoid hydroxychloroquine sulfate tablets administration in patients with congenital or documented acquired QT prolongation and/or known risk factors for prolongation of the QT interval such as: Cardiac disease, e.g., heart failure, myocardial infarction. Proarrhythmic conditions, e.g., bradycardia (< 50 bpm).
History of ventricular dysrhythmias. Uncorrected hypokalemia and/or hypomagnesemia. Concomitant administration with QT interval prolonging agents as this may lead to an increased risk for ventricular arrhythmias [see Drug Interactions ( 7.1 )] .
Therefore, hydroxychloroquine sulfate tablets are not recommended in patients taking other drugs that have the potential to prolong the QT interval. Correct electrolyte imbalances prior to use. Monitor cardiac function as clinically indicated during hydroxychloroquine sulfate tablets therapy.
Discontinue hydroxychloroquine sulfate tablets if cardiotoxicity is suspected or demonstrated by tissue biopsy.
5.2Retinal Toxicity Irreversible retinal damage was observed in some patients treated with hydroxychloroquine sulfate and it is related to cumulative dosage and treatment duration. In patients of Asian descent, retinal toxicity may first be noticed outside the macula. Risk factors for retinal damage include daily hydroxychloroquine sulfate dosages ≥5 mg/kg of actual body weight, durations of use greater than five years, renal impairment, use of concomitant drug products such as tamoxifen citrate, and concurrent macular disease.
Within the first year of starting hydroxychloroquine sulfate tablets, a baseline ocular examination is recommended including best corrected distance visual acuity (BCVA), an auto…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are described in greater detail in other sections: Cardiomyopathy and Ventricular Arrhythmias [see Warnings and Precautions ( 5.1 )] Retinal Toxicity [see Warnings and Precautions ( 5.2 )] Serious Skin Reactions [see Warnings and Precautions ( 5.3 )] Worsening of Psoriasis [see Warnings and Precautions ( 5.4 )] Risks Associated with Use in Porphyria [see Warnings and Precautions ( 5.5 )] Hematologic Toxicity [see Warnings and Precautions ( 5.6 )] Hemolytic Anemia Associated with G6PD [see Warnings and Precautions ( 5.7 )] Skeletal Muscle Myopathy or Neuropathy [see Warnings and Precautions ( 5.8 )] Neuropsychiatric Reactions Including Suicidality [see Warnings and Precautions ( 5.9 )] Hypoglycemia [see Warnings and Precautions ( 5.10 )] Renal Toxicity [see Warnings and Precautions ( 5.11 )] The following adverse reactions have been identified during post-approval use of 4-aminoquinoline drugs, including hydroxychloroquine sulfate tablets.
Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure: - Blood and lymphatic system disorders : Bone marrow depression, anemia, aplastic anemia, agranulocytosis, leukopenia, thrombocytopenia - Cardiac disorders: Cardiomyopathy, cardiac failure, QT-interval prolongation, ventricular tachycardia, torsades de pointes, atrioventricular block, bundle branch block, sick sinus syndrome, pulmonary hypertension - Ear and labyrinth disorders : Vertigo, tinnitus, nystagmus, sensorineural hearing loss - Eye disorders: Retinopathy, retinal pigmentation changes (typically bull’s eye appearance), visual field defects (paracentral scotomas), macular degeneration, corneal edema, corneal opacities, decreased dark adaptation - Gastrointestinal disorders: Nausea, vomiting, diarrhea, abdominal pain - General disorders : Fatigue - Hepatobiliary disorders : Abnormal liver function tests, fulminant hepatic failure - Immune system disorders : Urticaria, angioedema, bronchospasm - Metabolism and nutrition disorders : Anorexia, hypoglycemia, weight loss - Musculoskeletal and connective tissue disorders: Proximal myopathy, depressed tendon reflexes, abnormal nerve conduction - Nervous system disorders: Ataxia, dizziness, headache, seizure, extrapyramidal disorders (dystonia, dyskinesia, tremor) - Neuropsychiatric disorders: Affect/emotional lability, irritability, nervousness, psychosis, suicidal ideation, suicidal behavior, depression, hallucinations, anxiety, agitation, confusion, delusions, paranoia, mania and sleep disorders (insomnia, night terrors, nightmares) - Skin and subcutaneous tissue disorders: Alopecia, hair color changes, rash, pruritus, photosensitivity, psoriasis exacerbation, hyperpigmentation, exfoliative dermatitis, erythema multiforme, acute generalized exanthematous pustulosis, Drug Rash with Eosinophilia and Systemic Symptoms (DRESS syndrome), Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN) The most common adverse reactions reported are: nausea, vomiting, diarrhea, and abdominal pain.
( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Teva at 1-888-838-2872 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Drugs Prolonging QT Interval and Other Arrhythmogenic Drugs. ( 7.1 ) See FPI for more important drug interactions. ( 7 )
7.1Drugs Prolonging QT Interval and Other Arrhythmogenic Drugs Hydroxychloroquine sulfate tablets prolongs the QT interval. There may be an increased risk of inducing ventricular arrhythmias if hydroxychloroquine sulfate tablets are used concomitantly with other arrhythmogenic drugs. Therefore, hydroxychloroquine sulfate tablets are not recommended in patients taking other drugs that have the potential to prolong the QT interval or are arrhythmogenic [see Warnings and Precautions ( 5.1 )].
7.2Insulin or Other Antidiabetic Drugs Hydroxychloroquine sulfate tablets may enhance the effects of insulin and antidiabetic drugs, and consequently increase the hypoglycemic risk. Therefore, a decrease in dosage of insulin and other antidiabetic drugs may be necessary [see Warnings and Precautions ( 5.10 ) ] .
7.3Drugs that Lower the Seizure Threshold Hydroxychloroquine sulfate tablets can lower the seizure threshold. Coadministration of hydroxychloroquine sulfate tablets with other antimalarials known to lower the seizure threshold (e.g., mefloquine) may increase the risk of seizures.
7.4Antiepileptics The activity of antiepileptic drugs might be impaired if coadministered with hydroxychloroquine sulfate tablets.
7.5Methotrexate Concomitant use of hydroxychloroquine sulfate tablets and methotrexate may increase the incidence of adverse reactions.
7.6Cyclosporine An increased plasma cyclosporin level was reported when cyclosporin and hydroxychloroquine sulfate tablets were coadministered. Monitor serum cyclosporine levels closely in patients receiving combined therapy.
7.7Digoxin Concomitant hydroxychloroquine sulfate tablets and digoxin therapy may result in increased serum digoxin levels. Monitor serum digoxin levels closely in patients receiving combined therapy.
7.8Cimetidine Concomitant use of cimetidine resulted in a 2-fold increase of exposure of chloroquine, which is structurally related to hydroxychloroquine. Interaction of cimetidine with hydroxychloroquine cannot be ruled out. Avoid concomitant use of cimetidine.
7.9Rifampicin Lack of efficacy of hydroxychloroquine was reported when rifampicin was concomitantly administered. Avoid concomitant use of rifampicin.
7.10Praziquantel Chloroquine has been reported to reduce the bioavailability of praziquantel. Interaction of praziquantel with hydroxychloroquine cannot be ruled out.
7.11Antacids and kaolin Antacids and kaolin can reduce absorption of chloroquine; an interval of at least 4 hours between intake of these agents and chloroquine should be observed. Interaction of antacids and kaolin with hydroxychloroquine cannot be ruled out.
7.12Ampicillin In a study of healthy volunteers, chloroquine significantly reduced the bioavailability of ampicillin. Interaction of ampicillin with hydroxychloroquine cannot be ruled out.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Prolonged clinical experience over decades of use and available data from published epidemiologic and clinical studies with hydroxychloroquine sulfate tablets use in pregnant women have not identified a drug-associated risk of major birth defects, miscarriage, or adverse maternal, or fetal outcomes ( see Data ) . There are risks to the mother and fetus associated with untreated or increased disease activity from malaria, rheumatoid arthritis, and systemic lupus erythematosus in pregnancy (see Clinical Considerations ).
Animal reproduction studies were not conducted with hydroxychloroquine. The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the US general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo-Fetal Risk Malaria : Malaria during pregnancy increases the risk for adverse pregnancy outcomes, including maternal anemia, prematurity, spontaneous abortion, and stillbirth. Rheumatoid Arthritis: Published data suggest that increased disease activity is associated with the risk of developing adverse pregnancy outcomes in women with rheumatoid arthritis Adverse pregnancy outcomes include preterm delivery (before 37 weeks of gestation), low birth weight (less than 2500 g) infants, and small for gestational age at birth.
Systemic Lupus Erythematosus : Pregnant women with systemic lupus erythematosus, especially those with increased disease activity, are at increased risk of adverse pregnancy outcomes, including spontaneous abortion, fetal death, preeclampsia, preterm birth, and intrauterine growth restriction. Passage of maternal auto-antibodies across the placenta may result in neonatal illness, including neonatal lupus and congenital heart block. Data Human Data Data from published epidemiologic and clinical studies have not established an association with hydroxychloroquine sulfate tablets use during pregnancy and major birth defects, miscarriage, or adverse maternal or fetal outcomes.
Hydroxychloroquine readily crosses the placenta with cord blood levels corresponding to maternal plasma levels. No retinal toxicity, ototoxicity, cardiotoxicity, or growth and developmental abnormalities have been observed in children who were exposed to hydroxychloroquine in utero . Available epidemiologic and clinical studies have methodological limitations including small sample size and study design.
8.2Lactation Risk Summary Published lactation data report that hydroxychloroquine is present in human milk at low levels. No adverse reactions have been reported in breastfed infants. No retinal toxicity, ototoxicity, cardiotoxicity, or growth and developmental abnormalities have been observed in children who were exposed to hydroxychloroquine through breastmilk.
There is no information on the effect of hydroxychloroquine on milk production. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for hydroxychloroquine sulfate tablets and any potential adverse effects on the breastfed child from hydroxychloroquine sulfate tablets or from the underlying maternal condition.
8.4Pediatric Use The safety and effectiveness of hydroxychloroquine sulfate tablets have been established in pediatric patients for the treatment of uncomplicated malaria due to P. falciparum, P. malariae, P. vivax , and P. ovale, as well as for the prophylaxis of malaria in geographic areas where chloroquine resistance is not reported. However, this product cannot be directly administered to pediatric patients weighing less than 31 kg because the film-coated tablets cannot be crushed or divided [see Dosage and Administration ( 2.1 , 2.2 )]…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Prolonged clinical experience over decades of use and available data from published epidemiologic and clinical studies with hydroxychloroquine sulfate tablets use in pregnant women have not identified a drug-associated risk of major birth defects, miscarriage, or adverse maternal, or fetal outcomes ( see Data ) . There are risks to the mother and fetus associated with untreated or increased disease activity from malaria, rheumatoid arthritis, and systemic lupus erythematosus in pregnancy (see Clinical Considerations ).
Animal reproduction studies were not conducted with hydroxychloroquine. The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the US general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo-Fetal Risk Malaria : Malaria during pregnancy increases the risk for adverse pregnancy outcomes, including maternal anemia, prematurity, spontaneous abortion, and stillbirth. Rheumatoid Arthritis: Published data suggest that increased disease activity is associated with the risk of developing adverse pregnancy outcomes in women with rheumatoid arthritis Adverse pregnancy outcomes include preterm delivery (before 37 weeks of gestation), low birth weight (less than 2500 g) infants, and small for gestational age at birth.
Systemic Lupus Erythematosus : Pregnant women with systemic lupus erythematosus, especially those with increased disease activity, are at increased risk of adverse pregnancy outcomes, including spontaneous abortion, fetal death, preeclampsia, preterm birth, and intrauterine growth restriction. Passage of maternal auto-antibodies across the placenta may result in neonatal illness, including neonatal lupus and congenital heart block. Data Human Data Data from published epidemiologic and clinical studies have not established an association with hydroxychloroquine sulfate tablets use during pregnancy and major birth defects, miscarriage, or adverse maternal or fetal outcomes.
Hydroxychloroquine readily crosses the placenta with cord blood levels corresponding to maternal plasma levels. No retinal toxicity, ototoxicity, cardiotoxicity, or growth and developmental abnormalities have been observed in children who were exposed to hydroxychloroquine in utero . Available epidemiologic and clinical studies have methodological limitations including small sample size and study design.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of hydroxychloroquine sulfate tablets have been established in pediatric patients for the treatment of uncomplicated malaria due to P. falciparum, P. malariae, P. vivax , and P. ovale, as well as for the prophylaxis of malaria in geographic areas where chloroquine resistance is not reported. However, this product cannot be directly administered to pediatric patients weighing less than 31 kg because the film-coated tablets cannot be crushed or divided [see Dosage and Administration ( 2.1 , 2.2 )] .
The safety and effectiveness of hydroxychloroquine sulfate tablets have not been established in pediatric patients for the treatment of rheumatoid arthritis, chronic discoid lupus erythematosus, or systemic lupus erythematosus.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical trials of hydroxychloroquine sulfate tablets did not include sufficient numbers of patients 65 years of age and older to determine whether they respond differently from younger adult patients. Nevertheless, this drug is known to be substantially excreted by the kidney, and the risk of toxic reactions to this drug may be greater in patients with impaired renal function. In general, dose selection in geriatric patients should start with the lowest recommended dose, taking into consideration the greater frequency of decreased hepatic, renal or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
10 OVERDOSAGE Hydroxychloroquine sulfate tablets overdosage symptoms have an onset within 1 to 3 hours of ingestion. The following have been reported with hydroxychloroquine sulfate tablets overdosage: Cardiovascular toxicity, including QRS or QTc prolongation, ventricular tachycardia, ventricular fibrillation, torsade de pointes, atrioventricular block, cardiac arrest and death. Life-threatening hypotension is common.
Severe hypokalemia secondary to an intracellular shift is common in severe toxicity. Central nervous system (CNS) depression, seizures, visual disturbances, transient blindness, and coma may occur. Gastrointestinal decontamination procedures warrant consideration in patients that present within the first hour post-ingestion.
If the level of consciousness rapidly deteriorates in severe poisoning, consider intubation before gastrointestinal decontamination procedures. Monitor plasma potassium levels and manage accordingly. Hemofiltration, hemodialysis, and hemoperfusion are not of benefit.
Consider contacting a poison center (1-800-221-2222) or a medical toxicologist for overdosage management recommendations.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Malaria Hydroxychloroquine is a 4-aminoquinoline antimalarial [see Microbiology ( 12.4 )] and antirheumatic agent. Rheumatoid Arthritis, Systemic Lupus Erythematosus and Chronic Discoid Lupus Erythematosus The mechanisms underlying the anti-inflammatory and immunomodulatory effects of hydroxychloroquine sulfate tablets in the treatment of rheumatoid arthritis, chronic discoid lupus erythematosus and systemic lupus erythematosus are not fully known.
12.2Pharmacodynamics The exposure-response relationship and time course of pharmacodynamic response for the safety and effectiveness of hydroxychloroquine have not been fully characterized.
12.3Pharmacokinetics Following oral administration, the whole blood concentration of hydroxychloroquine at steady state is dose proportional over a dose range from 200 mg daily to 400 mg daily of hydroxychloroquine sulfate tablet in rheumatoid arthritis and lupus patients. Absorption Following a single 200 mg oral dose of hydroxychloroquine sulfate tablet to healthy male volunteers, whole blood hydroxychloroquine C max was 129.6 ng/mL (plasma C max was 50.3 ng/mL) with T max of 3.3 hours (plasma T max 3.7 hours). Peak blood concentrations of metabolites were observed at the same time as peak levels of hydroxychloroquine.
Mean absolute oral bioavailability is 79% (SD: 12%) in fasting conditions. Peak blood concentrations ranged from 1161 ng/mL to 2436 ng/mL (mean 1918 ng/mL) following a single dose of 155 mg intravenous infusion and from 2290 ng/mL to 4211 ng/mL (mean 3312 ng/mL) following a single dose of 310 mg intravenous infusion in healthy subjects. Pharmacokinetic parameters were not significantly different over the therapeutic dose range of 155 mg and 310 mg, indicating linear kinetics.
In patients with rheumatoid arthritis, there was large variability as to the fraction of the dose absorbed (i.e. 30 to 100%), and mean hydroxychloroquine levels were significantly higher in patients with less disease activity. Distribution Hydroxychloroquine sulfate is extensively distributed to tissues and has a large volume of distribution.
Approximately 50% of hydroxychloroquine is bound to plasma proteins. Metabolism Significant levels of three metabolites, desethylhydroxychloroquine (DHCQ), desethylchloroquine (DCQ), and bidesethylhydroxychloroquine (BDCQ) were found in plasma and blood, with DHCQ being the major metabolite. In vitro, hydroxychloroquine is metabolized mainly by CYP2C8, CYP3A4 and CYP2D6 as well as by FMO-1 and MAO-A.
Elimination / Excretion Renal clearance in patients with rheumatoid arthritis treated with hydroxychloroquine sulfate tablets for at least 6 months was similar to that in single dose studies in healthy volunteers, suggesting that no change in clearance occurred with chronic dosing. Renal clearance of unchanged hydroxychloroquine was approximately 16% to 30% of the dose after oral and IV administration. Results following a single oral dose of a 200 mg tablet demonstrated a half-life of hydroxychloroquine about 40 days in whole blood.
Following chronic oral administration of hydroxychloroquine, the absorption half-life of hydroxychloroquine was approximately 3 to 4 hours and the terminal half-life ranged from 40 to 50 days in whole blood. The effective half-life of hydroxychloroquine is likely to be shorter and steady state is achieved by 6 weeks following 400 mg daily oral administration in rheumatoid arthritis patients. Drug Interaction Studies In vitro study suggested that hydroxychloroquine has a potential to inhibit CYP2D6, CYP3A4, P-glycoproteins (P-gp), MATE1 and MATE2-K.
In vitro study suggested that hydroxychloroquine has no significant potential to inhibit CYP1A2, CYP2B6, CYP2C8, CYP2C9, CYP2C19, and the main transporters OATP1B1, OATP1B3, OAT1, OAT3, OCT1, and OCT2. In vitro, hydroxychloroquine has no significant potential to induce CYP1A2, CYP2B6 and CYP3A4.
12.4 Microbiology Mechanism of Action in Malaria The pr…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Malaria Hydroxychloroquine is a 4-aminoquinoline antimalarial [see Microbiology ( 12.4 )] and antirheumatic agent. Rheumatoid Arthritis, Systemic Lupus Erythematosus and Chronic Discoid Lupus Erythematosus The mechanisms underlying the anti-inflammatory and immunomodulatory effects of hydroxychloroquine sulfate tablets in the treatment of rheumatoid arthritis, chronic discoid lupus erythematosus and systemic lupus erythematosus are not fully known.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied Hydroxychloroquine sulfate tablets USP, 200 mg (equivalent to 155 mg of base), are white, unscored, film-coated, capsule-shaped tablets debossed “TV” and “2401” on one side and plain on the other side NDC: 71335-1771-9: 20 Tablets in a BOTTLE NDC: 71335-1771-7: 10 Tablets in a BOTTLE NDC: 71335-1771-8: 14 Tablets in a BOTTLE NDC: 71335-1771-1: 100 Tablets in a BOTTLE NDC: 71335-1771-2: 30 Tablets in a BOTTLE NDC: 71335-1771-3: 60 Tablets in a BOTTLE NDC: 71335-1771-4: 180 Tablets in a BOTTLE NDC: 71335-1771-5: 90 Tablets in a BOTTLE NDC: 71335-1771-6: 120 Tablets in a BOTTLE
16.2Storage Dispense in a tight, light-resistant container as defined in the USP, with a child-resistant closure (as required). Store at 20° to 25°C (68° to 77°F) [See USP Controlled Room Temperature]. Do not crush or divide hydroxychloroquine sulfate film-coated tablets. Keep out of the reach of children. Repackaged/Relabeled by: Bryant Ranch Prepack, Inc. Burbank, CA 91504
📋 Description ▾
11 DESCRIPTION Hydroxychloroquine sulfate, USP is an antimalarial and antirheumatic drug, chemically described as (±)-2-[[4-[(7-Chloro-4-quinolyl) amino]pentyl] ethylamino] ethanol sulfate (1:1) (salt). Its structural formula is: C 18 H 26 ClN 3 O•H 2 SO 4 Molecular Weight: 433.95 Hydroxychloroquine sulfate, USP is a white to almost white, crystalline powder, freely soluble in water; practically insoluble in alcohol, chloroform, and ether. Hydroxychloroquine sulfate tablets, USP for oral administration contain 200 mg hydroxychloroquine sulfate, USP (equivalent to 155 mg of hydroxychloroquine) and the following inactive ingredients: dibasic calcium phosphate dihydrate, hypromellose, magnesium stearate, polydextrose, polyethylene glycol, starch 1500 partially pregelatinized maize starch, titanium dioxide, and triacetin.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Important Administration Instructions Advise the patient to take hydroxychloroquine sulfate tablets with food or milk and not to crush or divide the tablet. Cardiomyopathy and Ventricular Arrhythmias Inform the patient that serious cardiac effects, life-threatening and fatal cases have been reported with use of hydroxychloroquine sulfate tablets Advise patients to seek medical attention immediately if they experience any symptoms of heart rhythm changes including fast or irregular heartbeat, lightheadedness, dizziness, or syncope [see Warnings and Precautions ( 5.1 )].
Retinal Toxicity Inform the patient that irreversible retinal damage has been observed in some patients with the use of hydroxychloroquine sulfate tablets. Advise patients of the importance of the ophthalmology visits for monitoring their eyes. Instruct patients to seek medical attention promptly if they experience decreased vision or decreased dark adaptation [see Warnings and Precautions ( 5.2 )].
Serious Skin Reactions Inform the patient that severe, life-threatening skin reactions have been reported with the use of hydroxychloroquine sulfate tablets. Advise the patient to seek medical attention immediately if experiencing any of the following signs and symptoms: blisters on the skin, eyes, lips or in the mouth, itching or burning, with or without fever [see Warnings and Precautions ( 5.3 )]. Hepatotoxicity Associated with Porphyria Cutanea Tarda Inform the patient that liver toxicity has been reported in when hydroxychloroquine sulfate tablets was used in patients with porphyria cutanea tarda.
In some cases, PCT was diagnosed only after the occurrence of liver injury, when hydroxychloroquine sulfate tablets was prescribed for an approved indication. Advise the patient to seek medical attention if experiencing fatigue, rash, nausea, dark urine, or jaundice [see Warnings and Precautions ( 5.5 )] . Skeletal Muscle Myopathy or Neuropathy Inform the patient that muscle weakness and atrophy has been reported with hydroxychloroquine sulfate tablets use Advise patients to report to the physician symptoms of muscle weakness [see Warnings and Precautions ( 5.8 )] .
Neuropsychiatric Reactions Including Suicidality Alert patients to seek medical attention immediately if they experience new or worsening depression, suicidal thoughts, or other mood changes [see Warnings and Precautions ( 5.9 )]. Hypoglycemia Inform the patient that hydroxychloroquine sulfate tablets have been associated with severe hypoglycemia. Advise the patient to monitor blood sugar levels if possible and to seek medical attention if experiencing any of the signs and symptoms of hypoglycemia such as sweating, shakiness, weakness, dizziness, tachycardia, nausea, blurred vision, confusion, fainting, or loss of consciousness [see Warnings and Precautions ( 5.10 )].
Distributed By: Teva Pharmaceuticals Parsippany, NJ 07054 Rev. I 2/2024