
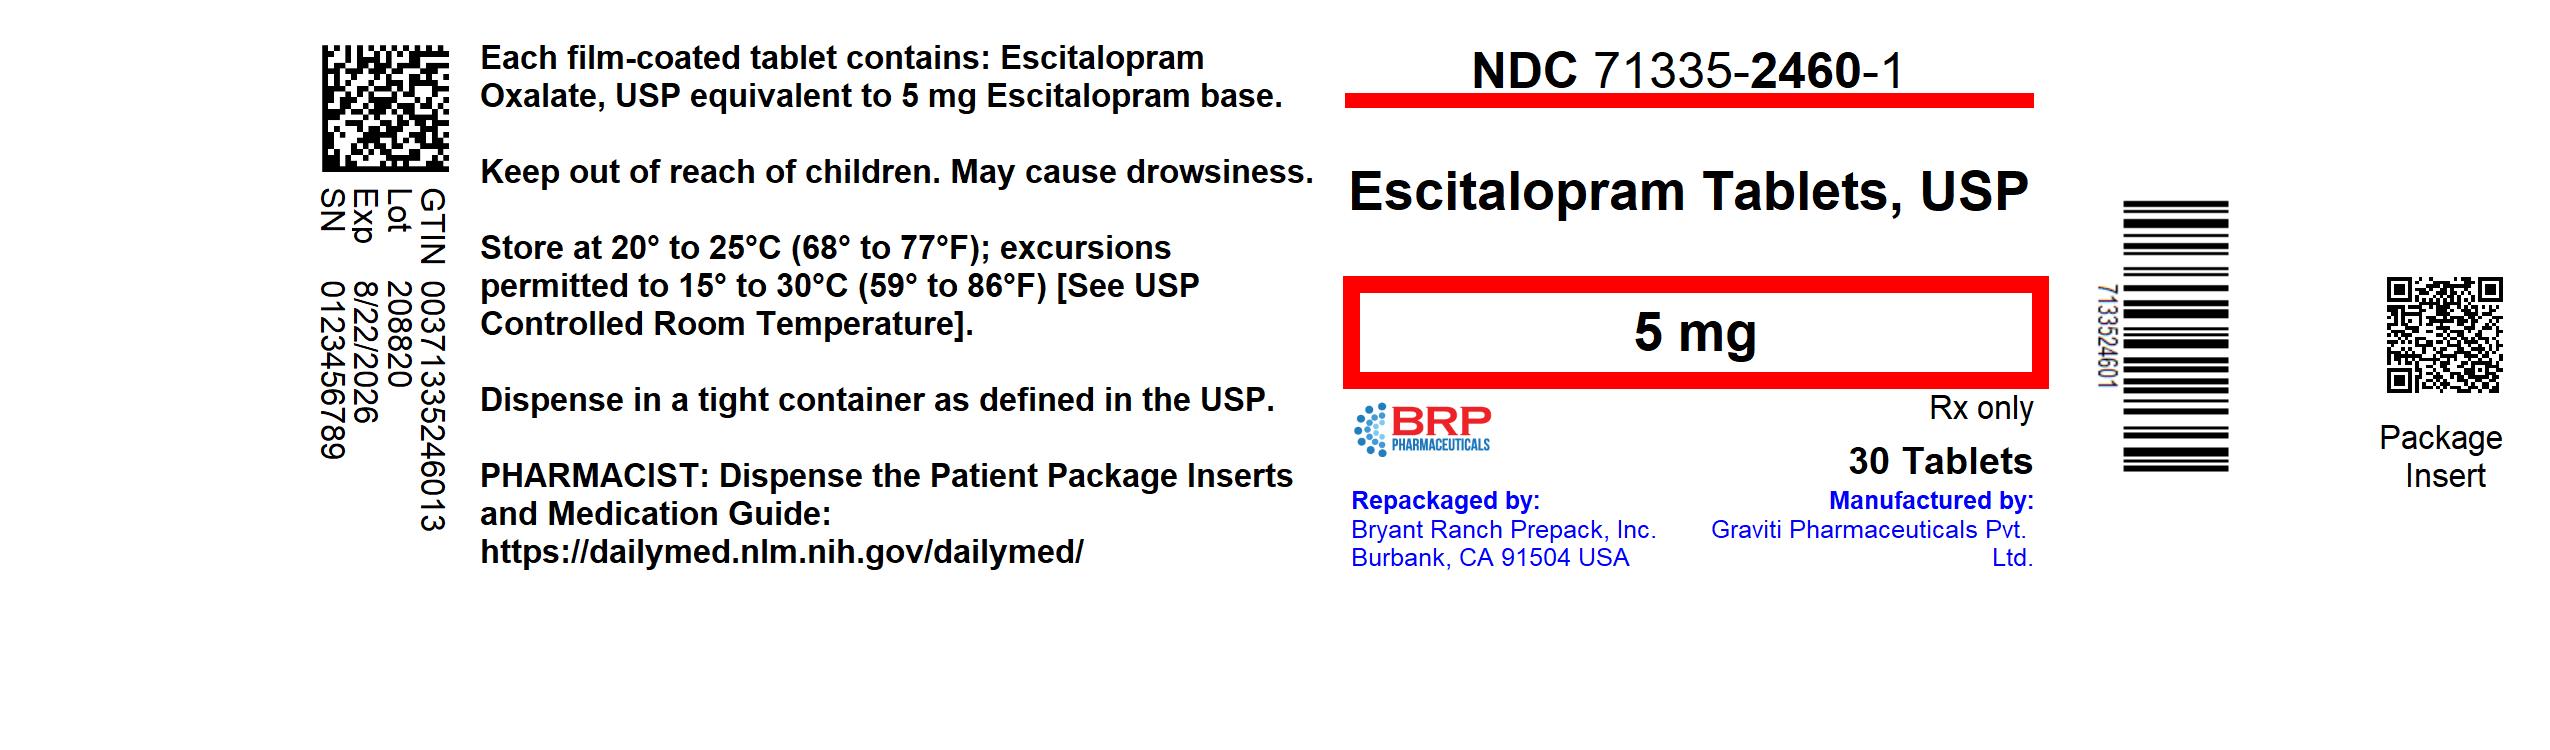
escitalopram 5 mg Tablet, Film Coated, 60-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Serotonin Reuptake Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Escitalopram is used to treat depression and generalized anxiety disorder (GAD; excessive worry and tension that disrupts daily life and lasts for 6 months or longer). Escitalopram is in a class of antidepressants called selective serotonin reuptake inhibitors (SSRIs). It works by increasing the amount of serotonin, a natural substance in the brain that helps maintain mental balance.
Read the full MedlinePlus article ↗- That's one of the most common questions — and honestly, antidepressants do take time. Most people don't notice a full effect in the first week or two. It often takes several weeks...
- How long will it take before I start feeling better on escitalopram?
- It's great that you're feeling better — but please don't stop on your own. Stopping escitalopram abruptly can cause withdrawal-like symptoms like dizziness, irritability, and a flu...
- Can I stop taking escitalopram once I feel better?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Escitalopram — tap one for details:
Escitalopram may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII REK4960K2U
Butylated hydroxyanisole is a synthetic preservative that prevents oils and fats in medicines from spoiling or becoming rancid. It keeps the medicine stable and extends its shelf life.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII RFW2ET671P
Hydroxypropyl cellulose is a plant-derived thickening agent made from cellulose. It acts as a binder to hold tablet ingredients together and as a film-former to coat tablets or control how fast the medicine releases.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
9 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.1381 | $8.29 / 60 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Escitalopram 5 mg 16729-0168-01 | Accord | 100 tablets | $0.042 | AB | Availability likely | — |
| escitalopram 5 mg 13668-0135-01 | Torrent | 100 tablets | $0.042 | AB | Availability likely | — |
| escitalopram 5 mg 16571-0755-01 | Rising | 100 tablets | $0.042 | AB | Availability likely | — |
| Escitalopram 5 mg 43547-0280-10 | SOLCO | 100 tablets | $0.042 | AB | Availability likely | — |
| Escitalopram 5 mg 60687-0865-01 | American | 1 tablet | $0.042 | AB | Availability likely | — |
| Escitalopram 5 mg 65862-0373-01 | Aurobindo | 100 tablets | $0.042 | AB | Availability likely | — |
| Escitalopram 5 mg 68001-0591-00 | BluePoint | 100 tablets | $0.042 | AB | Availability likely | — |
| Escitalopram Oxalate 5 mg 72603-0149-01 | NorthStar | 1000 tablets | $0.042 | AB | Availability likely | — |
| escitalopram oxalate 5 mg 82009-0035-10 | Quallent | 1000 tablets | $0.042 | AB | Availability likely | — |
| Escitalopram 5 mg 59746-0279-01 | Jubilant | 100 tablets | $0.045 | AB | FDA listed | — |
| Escitalopram Oxalate 5 mg 33342-0036-11 | Macleods | 100 tablets | $0.046 | AB | FDA listed | — |
| Lexapro 5 mg 00456-2005-01 | Allergan, | 100 tablets | $14.743 | AB | Availability likely | — |
| Escitalopram 5 mg 00615-8475-05 | NCS | 15 tablets | — | AB | FDA listed | — |
| Escitalopram Oxalate 5 mg 43602-0473-10 | Ascent | 1000 tablets | — | AB | FDA listed | — |
| Escitalopram 5 mg 50090-5312-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| escitalopram 5 mg 50090-7177-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Escitalopram 5 mg 51655-0116-26 | Northwind | 90 tablets | — | AB | FDA listed | — |
| Escitalopram 5 mg 51655-0766-52 | Northwind | 30 tablets | — | AB | FDA listed | — |
| Escitalopram Oxalate 5 mg 53746-0019-05 | Amneal | 500 tablets | — | AB | FDA listed | — |
| escitalopram 5 mg 60760-0894-30 | ST. | 30 tablets | — | AB | FDA listed | — |
| Escitalopram Oxalate 5 mg 65162-0019-03 | Amneal | 30 tablets | — | AB | FDA listed | — |
| escitalopram 5 mg 67046-1472-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| Escitalopram Oxalate 5 mg 69097-0847-02 | Cipla | 30 tablets | — | AB | FDA listed | — |
| Escitalopram 5 mg 70518-2597-00 | REMEDYREPACK | 1 tablet | — | AB | Discontinued | — |
| escitalopram 5 mg 70518-4300-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| escitalopram oxalate 5 mg 71205-0313-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Escitalopram 5 mg 71335-1241-01 | Bryant | 30 tablets | — | AB | Discontinued | — |
| Escitalopram 5 mg 71335-2058-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| escitalopram 5 mgthis 71335-2460-02 | Bryant | 60 tablets | — | AB | FDA listed | — |
| Escitalopram 5 mg 71335-9687-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| escitalopram 5 mg 72162-2242-00 | Bryant | 1000 tablets | — | AB | FDA listed | — |
| Escitalopram 5 mg 72189-0449-30 | Direct_Rx | 30 tablets | — | AB | FDA listed | — |
| Escitalopram oxalate 5 mg 76282-0249-01 | Exelan | 100 tablets | — | AB | FDA listed | — |
| Escitalopram 5 mg 76420-0721-01 | Asclemed | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 71335-2460-01 | 30 TABLET, FILM COATED in 1 BOTTLE (71335-2460-1) | 2024-09-27 | Active |
| 71335-2460-02 You're viewing this | 60 TABLET, FILM COATED in 1 BOTTLE (71335-2460-2) | 2024-12-12 | Active |
| 71335-2460-03 | 90 TABLET, FILM COATED in 1 BOTTLE (71335-2460-3) | 2024-07-29 | Active |
| 71335-2460-04 | 100 TABLET, FILM COATED in 1 BOTTLE (71335-2460-4) | 2024-12-12 | Active |
You're viewing one of 4 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 71335-2460-02?
What is the difference between NDC 71335-2460-02 and NDC 71335-2460-01?
What NDC number is used to bill for this package of escitalopram 5 mg Tablet, Film Coated?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: SUICIDAL THOUGHTS AND BEHAVIORS Antidepressants increased the risk of suicidal thoughts and behaviors in pediatric and young adult patients in short-term studies. Closely monitor all antidepressant-treated patients for clinical worsening, and for emergence of suicidal thoughts and behaviors [ see Warnings and Precautions ( 5.1 ) ]. Escitalopram tablets are not approved for use in pediatric patients less than 12 years of age [ see Use in Specific Populations ( 8.4 ) ].
WARNING: SUICIDAL THOUGHTS AND BEHAVIORS See full prescribing information for complete boxed warning. Increased risk of suicidal thoughts and behavior in pediatric and young adult patients taking antidepressants. Closely monitor all antidepressant-treated patients for clinical worsening and emergence of suicidal thoughts and behaviors ( 5.1 ).
Escitalopram tablets is not approved for use in pediatric patients less than 7 years of age ( 8.4 ).
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Escitalopram tablets are indicated for the treatment of: major depressive disorder (MDD) in adults and pediatric patients 12 years of age and older. generalized anxiety disorder (GAD) in adults. Additional pediatric use information is approved for AbbVie Inc.'s LEXAPRO (escitalopram) tablets. However, due to AbbVie Inc.'s marketing exclusivity rights, this drug product is not labeled with that information.
Escitalopram tablets are a selective serotonin reuptake inhibitor (SSRI) indicated for: treatment of major depressive disorder (MDD) in adults and pediatric patients 12 years of age and older ( 1 ) treatment of generalized anxiety disorder (GAD) in adults ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Indication and Population Recommended Dose MDD in Adolescents ( 2.1 ) Initial: 10 mg once daily Recommended: 10 mg once daily Maximum: 20 mg once daily MDD in Pediatric Patients 12 years and older ( 2.1 ) Initial: 10 mg once daily Recommended: 10 mg once daily Maximum: 20 mg once daily GAD in Adults ( 2.2 ) Initial: 10 mg once daily Recommended: 10 mg once daily Maximum: 20 mg once daily No additional benefits were seen at 20 mg once daily ( 2.1 ) Administer once daily, morning or evening, with or without food ( 2.3 ) Elderly patients: recommended dosage is 10 mg once daily ( 2.4 ) Hepatic impairment: recommended dosage is 10 mg once daily ( 2.4 , 8.6 ) When discontinuing Escitalopram tablets, reduce dose gradually whenever possible ( 2.5 )
2.1Major Depressive Disorder Adults The recommended dose of escitalopram tablets is 10 mg once daily. A fixed-dose trial of escitalopram tablets demonstrated the effectiveness of both 10 mg and 20 mg of escitalopram tablets, but failed to demonstrate a greater benefit of 20 mg over 10 mg [ see Clinical Studies ( 14.1 ) ]. Depending on clinical response and tolerability, dosage may be increased to the maximum recommended dosage of 20 mg once daily at an interval of no less than 1 week.
Pediatric Patients 12 years of age and older The recommended dosage of escitalopram tablet in pediatric patients 12 years of age and older is 10 mg once daily. Depending on clinical response and tolerability, dosage may be increased to the maximum recommended dosage of 20 mg once daily at an interval of no less than 3 weeks.
2.2Generalized Anxiety Disorder Adults The recommended starting dose of escitalopram tablets is 10 mg once daily. If the dose is increased to 20 mg, this should occur after a minimum of one week. Depending on clinical response and tolerability, dosage may be increased to the maximum recommended dosage of 20 mg once daily at an interval of no less than 1 week.
Additional pediatric use information is approved for AbbVie Inc.'s LEXAPRO (escitalopram) tablets. However, due to AbbVie Inc.'s marketing exclusivity rights, this drug product is not labeled with that information.
2.3Administration Information Administer Escitalopram tablets orally once daily, in the morning or evening, with or without food.
2.4Screen for Bipolar Disorder Prior to Starting Escitalopram Tablets Prior to initiating treatment with escitalopram tablets or another antidepressant, screen patients for a personal family history of bipolar disorder, mania, or hypomania [ see Warnings and Precautions ( 5.5 ) ].
2.5Recommended Dosage for Specific Populations The recommended dosage for most elderly patients and patients with hepatic impairment is 10 mg once daily [see Use in Specific Populations ( 8.5 , 8.6 )]. The recommended dosage for Escitalopram tablets in adults with a creatinine clearance less than 20 mL/minute has not been determined. No dosage adjustment is necessary for patients with mild or moderate renal impairment [see Use in Specific Populations ( 8.7 )].
2.6Discontinuation of Treatment with Escitalopram Tablets Symptoms associated with discontinuation of escitalopram tablets and other SSRIs and SNRIs have been reported [see Warnings and Precautions ( 5.3 )]. Patients should be monitored for these symptoms when discontinuing treatment. A gradual reduction in the dose rather than abrupt cessation is recommended whenever possible.
If intolerable symptoms occur following a decrease in the dose or upon discontinuation of treatment, then resuming the previously prescribed dose may be considered. Subsequently, the physician may continue decreasing the dose but at a more gradual rate.
2.7Switching a Patient to or from a Monoamine Oxidase Inhibitor (MAOI) Antidepressant At least 14 days should elapse between discontinuation of an MAOI intended to treat psychiatric disorders and initiation of therapy with escitalopram tablets. Conversely, at least 14 days should be allowed after stopping e…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets Escitalopram Tablets, USP 5 mg are available as White, round, biconvex, film coated tablets, engraved "77" on one side and plain on the other side. Escitalopram Tablets, USP 10 mg are available as White, round, biconvex, film coated tablets, engraved "74" over score on one side and plain on the other side. Escitalopram Tablets, USP 20 mg are available as White, round, biconvex, film coated tablets, engraved "71" over score on one side and plain on the other side.
Tablets: 5 mg, 10 mg (scored) and 20 mg (scored)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Escitalopram tablets is contraindicated in patients: taking MAOIs with Escitalopram tablets or within 14 days of stopping treatment with Escitalopram tablets because of an increased risk of serotonin syndrome. The use of Escitalopram tablets within 14 days of stopping an MAOI intended to treat psychiatric disorders is also contraindicated [see Dosage and Administration ( 2.7 ) and Warnings and Precautions ( 5.2 )]. Starting Escitalopram tablets in a patient who is being treated with MAOIs such as linezolid or intravenous methylene blue is also contraindicated because of an increased risk of serotonin syndrome [see Dosage and Administration ( 2.6 ) and Warnings and Precautions ( 5.2 )]. taking pimozide [see Drug Interactions ( 7 )]. with a hypersensitivity to escitalopram or citalopram or any of the inactive ingredients in Escitalopram tablets.
Do not use MAOIs intended to treat psychiatric disorders with Escitalopram tablets or within 14 days of stopping treatment with Escitalopram tablets. Do not use Escitalopram tablets within 14 days of stopping an MAOI intended to treat psychiatric disorders. In addition, do not start Escitalopram tablets in a patient who is being treated with linezolid or intravenous methylene blue ( 4 ) Known hypersensitivity to escitalopram or citalopram or any of the inactive ingredients ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Serotonin Syndrome: Increased risk when co-administered with other serotonergic agents (e.g., SSRI, SNRI, triptans), but also when taken alone. If it occurs, discontinue Escitalopram tablets and initiate supportive treatment ( 4 , 5.2 ) Discontinuation syndrome: When discontinuing Escitalopram tablets, reduce dosage gradually whenever possible, and monitor for discontinuation symptoms ( 5.3 ) Seizures: Use with care in patients with a history of seizure ( 5.4 ). Activation of Mania/Hypomania: Screen patients for bipolar disorder.
( 5.5 ). Hyponatremia: Can occur in association with syndrome of inappropriate antidiuretic hormone secretion ( 5.6 ). Increased Risk of Bleeding: Concomitant use of nonsteroidal anti-inflammatory drugs, aspirin, other antiplatelet drugs, warfarin and other drugs that affect coagulation may increase risk ( 5.7 ).
Interference with Cognitive and Motor Performance: Use caution when operating machinery ( 5.8 ). Angle Closure Glaucoma: Angle closure glaucoma has occurred in patients with untreated anatomically narrow angles treated with antidepressants. ( 5.9 ) Use in Patients with Concomitant Illness: Use caution in patients with diseases or conditions that produce altered metabolism or hemodynamic responses ( 5.10 ).
Sexual Dysfunction: Escitalopram tablets may cause symptoms of sexual dysfunction ( 5.11 ).
5.1Suicidal Thoughts and Behaviors in Adolescents and Young Adults In pooled analyses of placebo-controlled trials of antidepressant drugs (SSRIs and other antidepressant classes) that included approximately 77,000 adult patients and 4,500 pediatric patients, the incidence of suicidal thoughts and behaviors in the antidepressant-treated patients age 24 years and younger was greater than in placebo-treated patients. There was considerable variation in risk of suicidal thoughts and behaviors among drugs, but there was an increased risk identified in young patients for most drugs studied.
There were differences in absolute risk of suicidal thoughts and behaviors across the different indications, with the highest incidence in patients with MDD. The drug-placebo differences in the number of cases of suicidal thoughts and behaviors per 1,000 patients treated are provided in Table 1. Table 1: Risk Differences of the Number of Patients of Suicidal Thoughts and Behaviors in the Pooled Placebo-Controlled Trials of Antidepressants in Pediatric and Adult Patients Age Range Drug-Placebo Difference in Number of Patients of Suicidal Thoughts and Behaviors per 1,000 Patients Treated <18 years old 14 additional patients 18 to 24 years old 5 additional patients Decreases Compared to Placebo 25 to 64 years old 1 fewer patient ≥65 years old 6 fewer patients It is unknown whether the risk of suicidal thoughts and behaviors in children, adolescents, and young adults extends to longer-term use, i.e., beyond four months.
However, there is substantial evidence from placebo-controlled maintenance trials in adults with MDD that antidepressants delay the recurrence of depression and that depression itself is a risk factor for suicidal thoughts and behaviors. Monitor all antidepressant-treated patients for any indication for clinical worsening and emergence of suicidal thoughts and behaviors, especially during the initial few months of drug therapy, and at times of dosage changes. Counsel family members or caregivers of patients to monitor for changes in behavior and to alert the healthcare provider.
Consider changing the therapeutic regimen, including possibly discontinuing escitalopram tablets, in patients whose depression is persistently worse, or who are experiencing emergent suicidal thoughts or behaviors.
5.2Serotonin Syndrome SSRIs, including Escitalopram tablets, can precipitate serotonin syndrome, a potentially life-threatening condition. The risk is increased with concomitant use of other serotonergic drugs (including triptans, tricyclic antidepressants, fentanyl, lithium, tramadol, tryptop…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in greater detail in other sections of the labeling: Suicidal thoughts and behaviors in adolescents and young adults [see Warnings and Precautions ( 5.1 )] Serotonin syndrome [see Warnings and Precautions ( 5.2 )] Discontinuation syndrome [see Warnings and Precautions ( 5.3 )] Seizures [see Warnings and Precautions ( 5.4 )] Activation of mania or hypomania [see Warnings and Precautions ( 5.5 )] Hyponatremia [see Warnings and Precautions ( 5.6 )] Increased Risk of Bleeding [see Warnings and Precautions ( 5.7 )] Interference with Cognitive and Motor Performance [see Warnings and Precautions ( 5.8 )] Angle-closure glaucoma [see Warnings and Precautions ( 5.9 )] Use in Patients with Concomitant Illness [see Warnings and Precautions ( 5.10 )] Sexual Dysfunction [see Warnings and Precautions ( 5.11 )] Most commonly observed adverse reactions (incidence ≥ 5% and at least twice the incidence of placebo patients) are: insomnia, ejaculation disorder (primarily ejaculatory delay), nausea, sweating increased, fatigue and somnolence, decreased libido, and anorgasmia ( 6.1 ).
To report SUSPECTED ADVERSE REACTIONS, contact Rising Pharma Holdings, Inc. at 1-844-874-7464 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical studies are conducted under widely varying conditions, adverse reaction rates observed in the clinical studies of a drug cannot be directly compared to rates in the clinical studies of another drug and may not reflect the rates observed in practice. Clinical Trial Data Sources Adults Adverse reactions information for escitalopram was collected from 715 patients with major depressive disorder who were exposed to escitalopram and from 592 patients who were exposed to placebo in double-blind, placebo-controlled trials.
An additional 284 patients with major depressive disorder were newly exposed to escitalopram in open-label trials. The adverse event information for escitalopram in patients with GAD was collected from 429 patients exposed to escitalopram and from 427 patients exposed to placebo in double-blind, placebo-controlled trials. Adverse reactions during exposure were obtained primarily by general inquiry and recorded by clinical investigators using terminology of their own choosing.
Consequently, it is not possible to provide a meaningful estimate of the proportion of individuals experiencing adverse reactions without first grouping similar types of reactions into a smaller number of standardized event categories. In the tables and tabulations that follow, standard World Health Organization (WHO) terminology has been used to classify reported adverse reactions. The stated frequencies of adverse reactions represent the proportion of individuals who experienced, at least once, a treatment emergent adverse event of the type listed.
An event was considered treatment-emergent if it occurred for the first time or worsened while receiving therapy following baseline evaluation. Pediatric Patients Adverse reaction information for pediatric patients was collected in double-blind placebo-controlled studies in 576 pediatric patients 6 to 17 years of age, (286 escitalopram tablets, 290 placebo) with major depressive disorder and in 273 pediatric patients 7 to 17 years of age (137 escitalopram tablets, 136 placebo) with generalized anxiety disorder. The safety and effectiveness of escitalopram tablets have not been established in pediatric patients less than 12 years of age with MDD or less than 7 years of age with GAD.
Adverse Reactions Associated with Discontinuation of Treatment Major Depressive Disorder Adults Among the 715 depressed patients who received escitalopram in placebo-controlled trials, 6% discontinued treatment due to an adverse event, as compared to 2% of 592 patients receiving placebo. In two fixed-dose studies, the rate of discontinuation for adverse reactions in patients receiving 10 mg/day escitalopram w…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Table 6 presents clinically important drug interactions with Escitalopram tablets. TABLE 6 Clinically Important Drug Interactions with Escitalopram tablets Monoamine Oxidase Inhibitors (MAOIs) Clinical Impact: Concomitant use of SSRIs, including Escitalopram tablets, and MAOIs increases the risk of serotonin syndrome. Intervention: Escitalopram tablets is contraindicated in patients taking MAOIs, including MAOIs such as linezolid or intravenous methylene blue [see Dosage and Administration ( 2.7 ), Contraindications ( 4 ), and Warnings and Precautions ( 5.2 )].
Pimozide Clinical Impact: Concomitant use of racemic citalopram with pimozide increases plasma concentrations of pimozide, a drug with a narrow therapeutic index, and may increase the risk of QT prolongation and/or ventricular arrhythmias compared to use of racemic citalopram alone [see Clinical Pharmacology ( 12.3 )]. Intervention: Escitalopram tablets is contraindicated in patients taking pimozide [see Contraindications ( 4 )]. Serotonergic Drugs Clinical Impact: Concomitant use of Escitalopram tablets and other serotonergic drugs (including other SSRIs, SNRIs, triptans, tricyclic antidepressants, opoids, lithium, buspirone, amphetamines, tryptophan, and St.
John's Wot) increases the risk of serotonin syndrome. Intervention: Monitor patients for signs and symptoms of serotonin syndrome, particularly during Escitalopram tablets initiation and dosage increases. If serotonin syndrome occurs, consider discontinuation of Escitalopram tablets and/or concomitant serotonergic drugs [see Warning and Precautions ( 5.2 )].
Drugs That Interfere With Hemostasis (NSAIDs, Aspirin, Warfarin, etc.) Clinical Impact: Concomitant use of Escitalopram tablets and an antiplatelet or anticoagulant may potentiate the risk of bleeding. Intervention: Inform patients of the increased risk of bleeding associated with the concomitant use of Escitalopram tablets and antiplatelet agents and anticoagulants. For patients taking warfarin, carefully monitor the international normalized ratio [see Warning and Precautions ( 5.7 )].
Sumatriptan Clinical Impact: There have been postmarketing reports describing patients with weakness, hyperreflexia, and incoordination following the use of an SSRI and sumatriptan. Intervention: If concomitant treatment with sumatriptan and an SSRI is clinically warranted, appropriate observation of the patient is advised [see Warning and Precautions ( 5.2 )]. Carbamazepine Clinical Impact: Combined administration of racemic citalopram (40 mg/day for 14 days) and carbamazepine (titrated to 400 mg/day for 35 days) did not significantly affect the pharmacokinetics of carbamazepine, a CYP3A4 substrate.
Intervention: Although trough citalopram plasma levels were unaffected, given the enzyme-inducing properties of carbamazepine, the possibility that carbamazepine might increase the clearance of escitalopram should be considered if the two drugs are coadministered. Drugs Metabolized by CYP2D6 Clinical Impact: Coadministration of escitalopram (20 mg/day for 21 days) with the tricyclic antidepressant desipramine (single dose of 50 mg), a substrate for CYP2D6, resulted in a 40% increase in C max and a 100% increase in AUC of desipramine.
Intervention: The clinical significance of this finding is unknown. Exercise caution during coadministration of escitalopram and drugs metabolized by CYP2D6. Concomitant use with SSRIs, SNRIs or Tryptophan is not recommended ( 7 ).
Use caution when concomitant use with drugs that affect Hemostasis (NSAIDs, Aspirin, Warfarin) ( 7 ).
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS ● Pregnancy: SSRI use, particularly later in pregnancy, may increase the risk for persistent pulmonary hypertension and symptoms of poor adaptation (respiratory distress, temperature instability, feeding difficulties, hypotonia, tremor, irritability) in the neonate. ( 8.1 ). Additional pediatric use information is approved for AbbVie Inc.'s LEXAPRO (escitalopram) tablets.
However, due to AbbVie Inc.'s marketing exclusivity rights, this drug product is not labeled with that information.
8.1Pregnancy Risk Summary Based on data from published observational studies, exposure to SSRIs, particularly in the month before delivery, has been associated with a less than 2-fold increase in the risk of postpartum hemorrhage [see Warnings and Precautions (5.7) and Clinical Considerations] . Available data from published epidemiologic studies and postmarketing reports have not established an increased risk of major birth defects or miscarriage. There are risks of persistent pulmonary hypertension of the newborn (PPHN) (see Data) and poor neonatal adaptation (see Clinical Considerations) with exposure to selective serotonin reuptake inhibitors (SSRIs), including escitalopram tablets, during pregnancy.
There are risks associated with untreated depression in pregnancy (see Clinical Considerations). In animal reproduction studies, both escitalopram and racemic citalopram have been shown to have adverse effects on embryo/fetal and postnatal development, including fetal structural abnormalities, when administered at doses greater than human therapeutic doses (see Data) . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in the clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Disease-associated maternal risk and/or embryo/fetal risk Women who discontinue antidepressants are more likely to experience a relapse of major depression than women who continue antidepressants.
This finding is from a prospective longitudinal study of 201 pregnant women with a history of major depression, who were euthymic and taking antidepressants at the beginning of pregnancy. Consider the risk of untreated depression when discontinuing or changing treatment with antidepressant medication during pregnancy and postpartum. Maternal Adverse Reactions Use of Lexapro in the month before delivery may be associated with an increased risk of postpartum hemorrhage [see Warnings and Precautions (5.7)] .
Fetal/Neonatal adverse reactions Neonates exposed to SSRIs or SNRIs, including escitalopram tablets, late in third trimester have developed complications requiring prolonged hospitalization, respiratory support, and tube feeding. Such complications can arise immediately upon delivery. Reported clinical findings have included respiratory distress, cyanosis, apnea, seizures, temperature instability, feeding difficulty, vomiting, hypoglycemia, hypotonia, hypertonia, hyperreflexia, tremor, jitteriness, irritability, and constant crying.
These features are consistent with either a direct toxic effect of SSRIs and SNRIs or, possibly, a drug discontinuation syndrome. It should be noted that, in some cases, the clinical picture is consistent with serotonin syndrome [ see Warnings and Precautions ( 5.2 ) ]. Data Human Data Exposure to SSRIs, particularly later in pregnancy, may increase the risk for PPHN.
PPHN occurs in 1 to 2 per 1,000 live births in the general populations and is associated with substantial neonatal morbidity and mortality. Animal Data In a rat embryo/fetal development study, oral administration of escitalopram (56, 112, or 150 mg/kg/day) to pregnant animals during the period of organogenesis resulted in decreased fetal body weight and associated de…
🆘 Overdosage ▾
10 OVERDOSAGE The following have been reported with escitalopram tablet overdosage: Seizures, which may be delayed, and altered mental status including coma. Cardiovascular toxicity, which may be delayed, including QRS and QTc interval prolongation, wide complex tachyarrhythmias, and torsade de pointes. Hypertension most commonly seen, but rarely can see hypotension alone or with co-ingestants including alcohol.
Serotonin syndrome (patients with a multiple drug overdosage with other proserotonergic drugs may have a higher risk). Prolonged cardiac monitoring is recommended in escitalopram overdosage ingestions due to the arrhythmia risk. Gastrointestinal decontamination with activated charcoal should be considered in patients who present early after a escitalopram overdose.
Consider contacting a poison center (1-800-221-2222) or a medical toxicologist for overdosage management recommendations.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The mechanism of antidepressant action of escitalopram, the S-enantiomer of racemic citalopram, is presumed to be linked to potentiation of serotonergic activity in the central nervous system (CNS) resulting from its inhibition of CNS neuronal reuptake of serotonin (5-HT).
12.2Pharmacodynamics In vitro and in vivo studies in animals suggest that escitalopram is a highly selective serotonin reuptake inhibitor (SSRI) with minimal effects on norepinephrine and dopamine neuronal reuptake. Escitalopram is at least 100-fold more potent than the R-enantiomer with respect to inhibition of 5-HT reuptake and inhibition of 5-HT neuronal firing rate. Tolerance to a model of antidepressant effect in rats was not induced by long-term (up to 5 weeks) treatment with escitalopram.
Escitalopram has no or very low affinity for serotonergic (5-HT 1-7 ) or other receptors including alpha- and beta-adrenergic, dopamine (D 1-5 ), histamine (H 1-3 ), muscarinic (M 1-5 ), and benzodiazepine receptors. Escitalopram also does not bind to, or has low affinity for, various ion channels including Na + , K + , Cl - , and Ca ++ channels. Antagonism of muscarinic, histaminergic, and adrenergic receptors has been hypothesized to be associated with various anticholinergic, sedative, and cardiovascular side effects of other psychotropic drugs.
12.3Pharmacokinetics The single- and multiple-dose pharmacokinetics of escitalopram are linear and dose-proportional in a dose range of 10 to 30 mg/day. With once-daily dosing, steady state plasma concentrations are achieved within approximately one week. At steady state, the extent of accumulation of escitalopram in plasma in young healthy subjects was 2.2-2.5 times the plasma concentrations observed after a single dose.
Absorption The absolute bioavailability of citalopram is about 80% relative to an intravenous dose. The tablet and the oral solution dosage forms of escitalopram oxalate are bioequivalent. Following a single oral dose (20 mg tablet or solution) of escitalopram, peak blood levels occur at about 5 hours.
Absorption of escitalopram is not affected by food. Distribution The binding of escitalopram to human plasma proteins is approximately 56%. The volume of distribution of citalopram is about 12 L/kg.
Data specific on escitalopram are unavailable. Elimination Biotransformation of escitalopram is mainly hepatic, with a mean terminal half-life of about 27-32 hours. The oral clearance of escitalopram is 600 mL/min, with approximately 7% of that due to renal clearance.
Metabolism Escitalopram is metabolized to S-DCT and S-didemethylcitalopram (S-DDCT). In humans, unchanged escitalopram is the predominant compound in plasma. At steady state, the concentration of the escitalopram metabolite S-DCT in plasma is approximately one-third that of escitalopram.
The level of S-DDCT was not detectable in most subjects. In vitro studies show that escitalopram is at least 7 and 27 times more potent than S-DCT and S-DDCT, respectively, in the inhibition of serotonin reuptake, suggesting that the metabolites of escitalopram do not contribute significantly to the antidepressant actions of escitalopram. S-DCT and S-DDCT also have no or very low affinity for serotonergic (5-HT1-7) or other receptors including alpha- and beta-adrenergic, dopamine (D1-5), histamine (H1-3), muscarinic (M1-5), and benzodiazepine receptors.
S-DCT and S-DDCT also do not bind to various ion channels including Na+, K+, Cl-, and Ca++ channels. In vitro studies using human liver microsomes indicated that CYP3A4 and CYP2C19 are the primary isozymes involved in the N-demethylation of escitalopram. Excretion Following oral administrations of escitalopram, the fraction of drug recovered in the urine as escitalopram and Sdemethylcitalopram (S-DCT) is about 8% and 10%, respectively.
Specific Populations Pediatric Patients Pediatric patients 12 to 17 years of age: In a single dose study of 10 mg escitalopram, AUC…
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Escitalopram Tablets, USP 5 mg are available as White, round, biconvex, film coated tablets, engraved "77" on one side and plain on the other side. NDC: 71335-2460-1: 30 Tablets in a BOTTLE NDC: 71335-2460-2: 60 Tablets in a BOTTLE NDC: 71335-2460-3: 90 Tablets in a BOTTLE NDC: 71335-2460-4: 100 Tablets in a BOTTLE Store at 20ºC to 25ºC (68ºF to 77ºF); excursions permitted from 15ºC to 30ºC (59ºF to 86ºF) [see USP Controlled Room Temperature]. Dispense in a tight container [see USP].
Repackaged/Relabeled by: Bryant Ranch Prepack, Inc. Burbank, CA 91504
📋 Description ▾
11 DESCRIPTION Escitalopram Tablets, USP are an orally administered selective serotonin reuptake inhibitor (SSRI). Escitalopram is the pure S-enantiomer (single isomer) of the racemic bicyclic phthalane derivative citalopram. Escitalopram oxalate is designated S-(+)-1-[3-(dimethyl-amino)propyl]-1-(p-fluorophenyl)-5-phthalancarbonitrile oxalate with the following structural formula: The molecular formula is C 20 H 21 FN 2 O • C 2 H 2 O 4 and the molecular weight is 414.40.
Escitalopram oxalate, USP occurs as a fine, white to off-white powder and is freely soluble in methanol and dimethyl sulfoxide (DMSO), soluble in isotonic saline solution, sparingly soluble in water and ethanol, slightly soluble in ethyl acetate, and insoluble in heptane. Escitalopram oxalate is available as tablets. Escitalopram Tablets, USP are film-coated, round tablets containing escitalopram oxalate in strengths equivalent to 5 mg, 10 mg, and 20 mg escitalopram base.
The 10 and 20 mg tablets are scored. The tablets also contain the following inactive ingredients: butylated hydroxyanisole, croscarmellose sodium, lactose monohydrate, magnesium stearate and microcrystalline cellulose. The film coating contains hydroxypropyl cellulose, hypromellose, polyethylene glycol, and titanium dioxide.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Suicidal Thoughts and Behaviors Advise patients, their families and caregivers to look for the emergence of suicidal ideation and behavior, especially during treatment and when the dose is adjusted up or down, and instruct them to report such symptoms to their healthcare provider [see Boxed Warning and Warnings and Precautions ( 5.1 )]. Serotonin Syndrome Caution patients about the risk of serotonin syndrome, particularly with the with the concomitant use of Escitalopram tablets with other serotonergic drugs including triptans, tricyclic antidepressants, fentanyl, lithium, tramadol, tryptophan, buspirone, amphetamines and St.
John's Wort, and with drugs that impair metabolism of serotonin (in particular, MAOIs, both those intended to treat psychiatric disorders and also others, such as linezolid). Instruct patients to contact their health care provider or report to the emergency room if they experience signs or symptoms of serotonin syndrome [see Warnings and Precautions ( 5.2 ), Drug Interactions (7.1)]. Discontinuation Syndrome Advise patients not to abruptly discontinue Escitalopram tablets and to discuss any tapering regimen with their healthcare provider.
Inform patients that adverse reactions can occur when Escitalopram tablets is discontinued [see Warnings and Precautions ( 5.3 )]. Activation of Mania or Hypomania Advise patients and their caregivers to observe for signs of activation of mania/hypomania and instruct them to report such symptoms to the healthcare provider [see Warnings and Precautions ( 5.5 )]. Increased Risk of Bleeding Inform patients about the concomitant use of Escitalopram tablets with NSAIDs, aspirin, warfarin, other antiplatelet drugs, or other anticoagulants because the combined use has been associated with an increased risk of bleeding.
Advise patients to inform their healthcare providers if they are taking or planning to take any prescription or over-the-counter medications that increase the risk of bleeding [see Warnings and Precautions ( 5.7 )]. Angle Closure Glaucoma Advise patients that taking Escitalopram tablets can cause mild pupillary dilation, which in susceptible individuals, can lead to an episode of angle closure glaucoma. Pre-existing glaucoma is almost always open-angle glaucoma because angle closure glaucoma, when diagnosed, can be treated definitively with iridectomy.
Open-angle glaucoma is not a risk factor for angle closure glaucoma. Patients may wish to be examined to determine whether they are susceptible to angle closure, and have a prophylactic procedure (e.g., iridectomy), if they are susceptible [see Warnings and Precautions ( 5.9 )]. Sexual Dysfunction Advise patients that use of escitalopram tablets may cause symptoms of sexual dysfunction in both male and female patients.
Inform patients that they should discuss any changes in sexual function and potential management strategies with their healthcare provider [see Warnings and Precautions ( 5.11 )]. Concomitant Medications Since escitalopram is the active isomer of racemic citalopram (Celexa), the two agents should not be coadministered. Patients should be advised to inform their physician if they are taking, or plan to take, any prescription or over-the-counter drugs, as there is a potential for interactions.
Interference with Psychomotor Performance Because psychoactive drugs may impair judgment, thinking, or motor skills, patients should be cautioned about operating hazardous machinery, including automobiles, until they are reasonably certain that escitalopram tablets therapy does not affect their ability to engage in such activities. Alcohol Patients should be told that, although escitalopram tablets has not been shown in experiments with normal subjects to increase the mental and motor skill impairments caused by alcohol, the concomitant use of escitalopram tablets and alcohol in depressed patients is…
💬 Medication Guide ▾
MEDICATION GUIDE Escitalopram (es'' sye tal' oh pram) Tablets, USP Dispense with Medication Guide available at: https://www.risingpharma.com/Medguides/EscitalopramTabletsUSPMG.pdf What is the most important information I should know about escitalopram tablets? Escitalopram tablets may cause serious side effects, including: ● Increased risk of suicidal thoughts or actions. Escitalopram tablets and other antidepressant medicines increase the risk of suicidal thoughts and actions in people 24 years of age and younger, especially within the first few months of treatment or when the dose is changed.
Depression or other mental illnesses are the most important causes of suicidal thoughts or actions. How can I watch for and try to prevent suicidal thoughts and actions? Pay close attention to any changes, especially sudden changes in mood, behavior, thoughts, or feelings, or if you or your child develop suicidal thoughts or actions.
This is very important when an antidepressant medicine is started or when the dose is changed. Call your healthcare provider right away to report new or sudden changes in mood, behavior, thoughts, or feelings or if you or your child develop suicidal thoughts or actions. Keep all follow-up visits with your healthcare provider as scheduled and call your healthcare provider between visits if you are worried about symptoms.
Call your healthcare provider or get emergency medical help right away if you or your child have any of the following symptoms, especially if they are new, worse, or worry you: attempts to commit suicide acting on dangerous impulses acting aggressive, being angry or violent thoughts about suicide or dying new or worse depression new or worsening anxiety panic attacks feeling very agitated or restless new or worse irritability trouble sleeping an extreme increase in activity or talking (mania) other unusual changes in behavior or mood What are escitalopram tablets?
Escitalopram tablets are a prescription medicine used to treat: a certain type of depression called Major Depressive Disorder (MDD) in adults and children 12 years of age and older Generalized Anxiety Disorder (GAD) in adults It is not known if Escitalopram tablets is safe and effective for use in children under 12 years of age with MDD or children under 7 years of age with GAD. Do not take escitalopram tablets if you or your child: are taking, or have stopped taking within the last 14 days, a medicine called a monoamine oxidase inhibitor (MAOI), including the antibiotic linezolid or intravenous methylene blue are taking the antipsychotic medicine pimozide are allergic to escitalopram or citalopram or any of the ingredients in escitalopram tablets.
See the end of this Medication Guide for a complete list of ingredients in escitalopram tablets. Ask your healthcare provider or pharmacist if you are not sure if you or your child take an MAOI, including the antibiotic linezolid or intravenous methylene blue. Do not start taking an MAOI for at least 14 days after you or your child have stopped treatment with escitalopram tablets.
Before taking escitalopram tablets, tell your healthcare provider about all your medical conditions, including if you or your child: have or had seizures or convulsions have, or have a family history of bipolar disorder, mania, or hypomania have low blood sodium levels have or had bleeding problems have high pressure in the eye (glaucoma) have heart, liver, or kidney problems are pregnant or plan to become pregnant. escitalopram tablets may harm the unborn baby. Taking escitalopram tablets during the third trimester of pregnancy may cause the baby to have withdrawal symptoms, or breathing, temperature control, feeding, or other problems after birth.
Talk to your healthcare provider about the risks to the baby if you or your child take escitalopram tablets during pregnancy. Tell your healthcare provider right away if you or your child become pregnant or think you may be pregnant during treatment with escitalopra…