
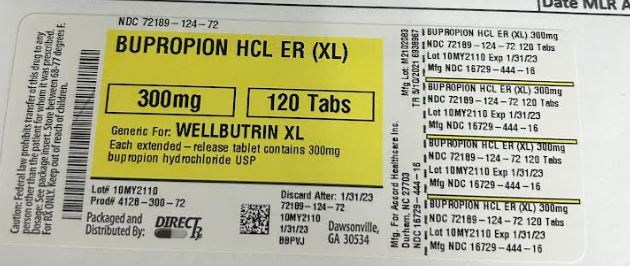
BUPROPION HYDROCHLORIDE 300 mg Tablet, Extended Release, 120-count
Other active recalls for Bupropion Hydrochloride (different manufacturers) — 3 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Aminoketone class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Bupropion is used to treat depression. and seasonal affective disorder (SAD; episodes of depression that occur at the same time each year [usually in the fall and winter but rarely may occur in the spring or summer months]). Bupropion is also used to help people stop smoking. Bupropion is in a class of medications called antidepressants. It works by increasing certain types of activity in the brain.
Read the full MedlinePlus article ↗- Bupropion is an antidepressant primarily used to treat major depressive disorder — that's clinical depression. Depending on which formulation you're prescribed, it may also be used...
- Most people don't notice a full effect immediately — antidepressant treatment for depression typically requires several months or longer. Your dose may also be increased gradually...
- Will bupropion make me feel better right away?
- The most common ones are dry mouth, nausea, trouble sleeping, dizziness, headache, and feeling anxious or agitated — especially early on. Many of these improve as your body adjusts...
Patient education
Supplement & herbal interactions
Bupropion may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII ZT934N0X4W
A naturally occurring amino acid salt used as a reducing agent and antioxidant in medications. It helps prevent ingredient breakdown and may improve product stability during storage.
-
UNII 7Z8S9VYZ4B
Ethylcellulose is a plant-derived thickener and film-former made by chemically modifying cellulose. It's used as a binder to hold tablet ingredients together, a coating to control how quickly medicine is released, or a thickener in liquid formulations.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII R8WTH25YS2
Glyceryl dibehenate is a wax-like substance made from behenate fatty acids and glycerol. It functions as a binder and release-control agent in tablets and capsules, helping hold ingredients together and regulate how quickly the medicine dissolves and releases in your body.
-
UNII Y6O7T4G8P9
Hydrated silica is a fine powder form of silicon dioxide with absorbed water. It works as an anti-caking agent and absorbent in medicines, helping powders stay free-flowing and preventing clumping.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII NX76LV5T8J
A synthetic plastic polymer made from methacrylic acid and ethyl acrylate. It's used as a coating or binder to control how and where the medicine dissolves in your digestive system.
-
UNII OJ4Z5Z32L4
A synthetic polymer made by linking ethylene glycol units together. It serves as a solvent, humectant to retain moisture, and film-forming agent in tablets and coatings to improve texture and drug delivery.
-
UNII RDH86HJV5Z
Povidone K90 is a synthetic polymer made from a chemical called vinyl pyrrolidone. It acts as a binder to hold pill ingredients together and as a dispersant to help the medicine break down and dissolve properly in your body.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 46N107B71O
Shellac is a natural resin secreted by the lac beetle. It's used as a coating on tablets and capsules to control how quickly the medicine dissolves and to improve appearance and stability.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 8Z96QXD6UM
Triethyl citrate is a clear liquid derived from citric acid. It acts as a plasticizer and solvent in tablet coatings and film formulations, helping the coating remain flexible and adhere properly to the medicine.
13 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.3192 | $38.30 / 120 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Bupropion Hydrochloride XL 300 mg 00904-7469-04 | Major | 1 tablet | $0.101 | AB3 | Availability likely | — |
| bupropion hydrochloride 300 mg 16571-0863-03 | Rising | 30 tablets | $0.101 | AB3 | Availability likely | — |
| Bupropion Hydrochloride 300 mg 16729-0444-10 | Accord | 30 tablets | $0.101 | AB3 | Availability likely | — |
| Bupropion Hydrochloride 300 mg 31722-0488-05 | Camber | 500 tablets | $0.101 | AB3 | Availability likely | — |
| Bupropion Hydrochloride XL 300 mg 42806-0349-05 | Epic | 500 tablets | $0.101 | AB3 | Availability likely | — |
| Bupropion Hydrochloride XL 300 mg 42806-0416-05 | Epic | 500 tablets | $0.101 | AB3 | Availability likely | — |
| Bupropion Hydrochloride (XL) 300 mg 43598-0656-05 | Dr | 500 tablets | $0.101 | AB3 | Availability likely | — |
| Bupropion Hydrochloride 300 mg 45963-0142-05 | Actavis | 500 tablets | $0.101 | AB3 | Availability likely | — |
| Bupropion Hydrochloride (XL) 300 mg 50228-0145-05 | ScieGen | 500 tablets | $0.101 | AB3 | Availability likely | — |
| Bupropion Hydrochloride 300 mg 50268-0134-13 | AvPAK | 1 tablet | $0.101 | AB3 | Availability likely | — |
| Bupropion Hydrochloride 300 mg 60687-0793-21 | American | 1 tablet | $0.101 | AB3 | Availability likely | — |
| Bupropion hydrochloride 300 mg 68001-0614-03 | BluePoint | 500 tablets | $0.101 | AB3 | Availability likely | — |
| Bupropion Hydrochloride XL 300 mg 68180-0320-02 | Lupin | 500 tablets | $0.101 | AB3 | Availability likely | — |
| Bupropion Hydrochloride 300 mg 69097-0072-12 | Cipla | 500 tablets | $0.101 | AB3 | Availability likely | — |
| Bupropion Hydrochloride (XL) 300 mg 69097-0876-02 | CIPLA | 30 tablets | $0.101 | — | Availability likely | — |
| Bupropion Hydrochloride XL 300 mg 69367-0289-05 | Westminster | 500 tablets | $0.101 | AB3 | Discontinued | — |
| Bupropion hydrochloride 300 mg 70010-0785-03 | Granules | 30 tablets | $0.101 | AB3 | Availability likely | — |
| Bupropion Hydrochloride XL 300 mg 82009-0052-05 | Quallent | 500 tablets | $0.101 | AB3 | Availability likely | — |
| Bupropion Hydrochloride (XL) 300 mg 83301-0025-01 | Mullan | 30 tablets | $0.101 | AB3 | Availability likely | — |
| Bupropion hydrochloride 300 mg 63304-0724-05 | Sun | 500 tablets | $0.103 | — | Discontinued | — |
| Bupropion Hydrochloride 300 mg 68001-0520-03 | BluePoint | 500 tablets | $0.107 | AB3 | Availability likely | — |
| Bupropion Hydrochloride (XL) 300 mg 24979-0102-02 | Upsher-Smith | 500 tablets | $0.112 | — | Discontinued | — |
| Bupropion Hydrochloride XL 300 mg 70436-0011-02 | Slate | 500 tablets | $0.115 | AB3 | Availability likely | — |
| Bupropion hydrochloride (XL) 300 mg 00527-2430-32 | Lannett | 30 tablets | $0.144 | AB3 | FDA listed | — |
| Wellbutrin Xl 300 mg 00187-0731-07 | Bausch | 7 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride 300 mg 00615-8505-05 | NCS | 15 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride 300 mg 50090-4749-00 | A-S | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride 300 mg 50090-5245-00 | A-S | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride (XL) 300 mg 50090-5334-00 | A-S | 30 tablets | — | — | FDA listed | — |
| Bupropion Hydrochloride XL 300 mg 50090-6961-00 | A-S | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride XL 300 mg 50090-6962-00 | A-S | 90 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride (XL) 300 mg 50090-7334-00 | A-S | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride (XL) 300 mg 50090-7335-00 | A-S | 90 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride XL 300 mg 50090-7602-00 | A-S | 90 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride 300 mg 55700-0820-30 | Quality | 30 tablets | — | AB3 | Discontinued | — |
| Bupropion Hydrochloride (Xl) 300 mg 62135-0876-30 | Chartwell | 30 tablets | — | AB3 | FDA listed | — |
| bupropion 300 mg 63187-0521-30 | Proficient | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride 300 mg 63187-0819-30 | Proficient | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride (XL) 300 mg 63629-8475-01 | Bryant | 500 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride (XL) 300 mg 63629-8476-01 | Bryant | 30 tablets | — | AB3 | FDA listed | — |
| bupropion 300 mg 65841-0780-05 | Zydus | 500 tablets | — | AB3 | FDA listed | — |
| Bupropion hydrochloride 300 mg 67046-1497-03 | Coupler | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion hydrochloride 300 mg 67046-1648-03 | Coupler | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride XL 300 mg 68071-3928-09 | NuCare | 90 tablets | — | AB3 | FDA listed | — |
| bupropion 300 mg 68382-0354-05 | Zydus | 500 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride 300 mg 68788-7992-01 | Preferred | 100 tablets | — | AB3 | FDA listed | — |
| Bupropion hydrochloride 300 mg 68788-8815-01 | Preferred | 100 tablets | — | AB3 | FDA listed | — |
| Bupropion hydrochloride (XL) 300 mg 69680-0158-30 | Vitruvias | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride (XL) 300 mg 70518-3790-00 | REMEDYREPACK | 30 tablets | — | AB3 | Discontinued | — |
| Bupropion Hydrochloride XL 300 mg 70518-4014-00 | REMEDYREPACK | 90 tablets | — | AB3 | FDA listed | — |
| bupropion hydrochloride 300 mg 70518-4343-00 | REMEDYREPACK | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion hydrochloride 300 mg 70518-4415-00 | REMEDYREPACK | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride XL 300 mg 70518-4446-00 | REMEDYREPACK | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride XL 300 mg 70518-4551-00 | REMEDYREPACK | 90 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride 300 mg 71205-0465-30 | Proficient | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride (XL) 300 mg 71205-0968-30 | Proficient | 30 tablets | — | — | FDA listed | — |
| Bupropion Hydrochloride (XL) 300 mg 71335-1114-01 | Bryant | 30 tablets | — | — | Discontinued | — |
| Bupropion Hydrochloride 300 mg 71335-1214-01 | Bryant | 30 tablets | — | AB3 | Discontinued | — |
| Bupropion Hydrochloride (XL) 300 mg 71335-2312-01 | Bryant | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion hydrochloride 300 mg 71335-2499-01 | Bryant | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride (XL) 300 mg 72162-1278-09 | Bryant | 90 tablets | — | — | Discontinued | — |
| Bupropion Hydrochloride (XL) 300 mg 72162-1527-03 | Bryant | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride 300 mgthis 72189-0124-72 | DIRECT | 120 tablets | — | AB3 | FDA listed | — |
| Bupropion HCL ER (XL) 300 mg 72189-0539-30 | Direct_RX | 30 tablets | — | AB3 | FDA listed | — |
| buPropion Hydrochloride XL 300 mg 72516-0036-03 | Oryza | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride (XL) 300 mg 72789-0112-90 | PD-Rx | 90 tablets | — | — | Discontinued | — |
| Bupropion Hydrochloride (XL) 300 mg 76282-0481-05 | Exelan | 500 tablets | — | — | FDA listed | — |
| Bupropion Hydrochloride 300 mg 76420-0812-01 | Asclemed | 100 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride (XL) 300 mg 77771-0145-05 | RADHA | 500 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride XL 300 mg 80425-0468-01 | Advanced | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride (XL) 300 mg 80425-0539-01 | Advanced | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride (XL) 300 mg 82804-0013-30 | Proficient | 30 tablets | — | — | FDA listed | — |
| Bupropion Hydrochloride 300 mg 85534-0006-01 | HAWAII | 100 tablets | — | AB3 | FDA listed | — |
| Bupropion hydrochloride 300 mg 87441-0014-01 | Unit | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride (XL) 300 mg 68788-4172-01 | Preferred | 100 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride 300 mg 59651-0512-05 | Aurobindo | 500 tablets | — | AB3 | FDA listed | — |
| Bupropion hydrochloride 300 mg 70518-4739-00 | REMEDYREPACK | 90 tablets | — | AB3 | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 72189-0124-30 | 30 TABLET, EXTENDED RELEASE in 1 BOTTLE (72189-124-30) | 2020-08-14 | Active |
| 72189-0124-72 You're viewing this | 120 TABLET, EXTENDED RELEASE in 1 BOTTLE (72189-124-72) | 2020-08-14 | Active |
You're viewing the largest of 2 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 72189-0124-72?
What is the difference between NDC 72189-0124-72 and NDC 72189-0124-30?
What NDC number is used to bill for this package of BUPROPION HYDROCHLORIDE 300 mg Tablet, Extended Release?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
Bupropion Hydrochloride Extended-release (SR) tablets are indicated for the treatment of major depressive disorder (MDD), as defined by the Diagnostic and Statistical Manual (DSM). The efficacy of bupropion in the treatment of a major depressive episode was established in two 4-week controlled inpatient trials and one 6-week controlled outpatient trial of adult subjects with MDD [see CLINICAL STUDIES (14)]. The efficacy of Bupropion Hydrochloride Extended-release (SR) tablets in maintaining an antidepressant response for up to 44 weeks following 8 weeks of acute treatment was demonstrated in a placebo-controlled trial [see CLINICAL STUDIES (14)].
⏱️ Dosage and Administration ▾
2.1General Instructions for Use To minimize the risk of seizure, increase the dose gradually [see WARNINGS AND PRECAUTIONS (5.3)]. Bupropion Hydrochloride Extended-release (SR) tablets should be swallowed whole and not crushed, divided, or chewed. Bupropion Hydrochloride Extended-release (SR) tablets may be taken with or without food.
The usual adult target dose for Bupropion Hydrochloride Extended-release (SR) tablets is 300 mg per day, given as 150 mg twice daily. Initiate dosing with 150 mg per day given as a single daily dose in the morning. After 3 days of dosing, the dose may be increased to the 300-mg-per-day target dose, given as 150 mg twice daily.
There should be an interval of at least 8 hours between successive doses. A maximum of 400 mg per day, given as 200 mg twice daily, may be considered for patients in whom no clinical improvement is noted after several weeks of treatment at 300 mg per day. To avoid high peak concentrations of bupropion and/or its metabolites, do not exceed 200 mg in any single dose.
It is generally agreed that acute episodes of depression require several months or longer of antidepressant drug treatment beyond the response in the acute episode. It is unknown whether the dose of Bupropion Hydrochloride Extended-release (SR) tablets needed for maintenance treatment is identical to the dose that provided an initial response. Periodically reassess the need for maintenance treatment and the appropriate dose for such treatment.
2.2Dose Adjustment in Patients with Hepatic Impairment In patients with moderate to severe hepatic impairment (Child-Pugh score: 7 to 15), the maximum dose of Bupropion Hydrochloride Extended-release (SR) tablets is 100 mg per day or 150 mg every other day. In patients with mild hepatic impairment (Child-Pugh score: 5 to 6), consider reducing the dose and/or frequency of dosing [see USE IN SPECIFIC POPULATIONS (8.7), CLINICAL PHARMACOLOGY (12.3)].
2.3Dose Adjustment in Patients with Renal Impairment Consider reducing the dose and/or frequency of Bupropion Hydrochloride Extended-release (SR) tablets in patients with renal impairment (Glomerular Filtration Rate less than 90 mL per min) [see USE IN SPECIFIC POPULATIONS (8.6), CLINICAL PHARMACOLOGY (12.3)].
2.4Switching a Patient to or from a Monoamine Oxidase Inhibitor (MAOI) Antidepressant At least 14 days should elapse between discontinuation of an MAOI intended to treat depression and initiation of therapy with Bupropion Hydrochloride Extended-release (SR) tablets. Conversely, at least 14 days should be allowed after stopping Bupropion Hydrochloride Extended-release (SR) tablets before starting an MAOI antidepressant [see CONTRAINDICATIONS (4), DRUG INTERACTIONS (7.6)].
2.5Use of Bupropion Hydrochloride Extended-release (SR) Tablets with Reversible MAOIs Such as Linezolid or Methylene Blue Do not start Bupropion hydrochloride Extended-release (SR) tablets in a patient who is being treated with a reversible MAOI such as linezolid or intravenous methylene blue. Drug interactions can increase the risk of hypertensive reactions. In a patient who requires more urgent treatment of a psychiatric condition, non-pharmacological interventions, including hospitalization, should be considered [see CONTRAINDICATIONS (4), DRUG INTERACTIONS (7.6)].
In some cases, a patient already receiving therapy with Bupropion Hydrochloride Extended-release (SR) tablets may require urgent treatment with linezolid or intravenous methylene blue. If acceptable alternatives to linezolid or intravenous methylene blue treatment are not available and the potential benefits of linezolid or intravenous methylene blue treatment are judged to outweigh the risks of hypertensive reactions in a particular patient, Bupropion Hydrochloride Extended-release (SR) tablets should be stopped promptly, and linezolid or intravenous methylene blue can be administered.
The patient should be monitored for 2 weeks or until 24 hours after the last dose of linezolid or intrav…
💊 Dosage Forms and Strengths ▾
100 mg – blue, round, biconvex, film-coated, extended-release (SR) tablets debossed with “S” on one side and “522” on the other. • 150 mg – purple, round, biconvex, film-coated, extended-release (SR) tablets debossed with “S” on one side and “525” on the other. • 200 mg –pink, round, biconvex, film-coated, extended-release (SR) tablets debossed with “S” on one side and “527” on the other.
⛔ Contraindications ▾
Bupropion Hydrochloride Extended-release (SR) tablets are contraindicated in patients with a seizure disorder. • Bupropion Hydrochloride Extended-release (SR) tablets are contraindicated in patients with a current or prior diagnosis of bulimia or anorexia nervosa as a higher incidence of seizures was observed in such patients treated with the immediate-release formulation of bupropion [see WARNINGS AND PRECAUTIONS (5.3)]. • Bupropion Hydrochloride Extended-release (SR) tablets are contraindicated in patients undergoing abrupt discontinuation of alcohol, benzodiazepines, barbiturates, and antiepileptic drugs [see WARNINGS AND PRECAUTIONS (5.3), DRUG INTERACTIONS (7.3)]. • The use of MAOIs (intended to treat psychiatric disorders) concomitantly with Bupropion Hydrochloride Extended-release (SR) tablets or within 14 days of discontinuing treatment with Bupropion Hydrochloride Extended-release (SR) tablets is contraindicated.
There is an increased risk of hypertensive reactions when Bupropion Hydrochloride Extended-release (SR) tablets are used concomitantly with MAOIs. The use of Bupropion Hydrochloride Extended-release (SR) tablets within 14 days of discontinuing treatment with an MAOI is also contraindicated. Starting Bupropion Hydrochloride Extended-release (SR) tablets in a patient treated with reversible MAOIs such as linezolid or intravenous methylene blue is contraindicated [see DOSAGE AND ADMINISTRATION (2.4, 2.5), WARNING AND PRECAUTIONS (5.4), DRUG INTERACTIONS (7.6)]. • Bupropion Hydrochloride Extended-release (SR) tablets are contraindicated in patients with known hypersensitivity to bupropion or other ingredients of Bupropion Hydrochloride Extended-release (SR) tablets.
Anaphylactoid/anaphylactic reactions and Stevens-Johnson syndrome have been reported [see WARNINGS AND PRECAUTIONS (5.8)].
⚠️ Warnings and Cautions ▾
5.1Suicidal Thoughts and Behaviors in Children, Adolescents, and Young Adults Patients with MDD, both adult and pediatric, may experience worsening of their depression and/or the emergence of suicidal ideation and behavior (suicidality) or unusual changes in behavior, whether or not they are taking antidepressant medications, and this risk may persist until significant remission occurs. Suicide is a known risk of depression and certain other psychiatric disorders, and these disorders themselves are the strongest predictors of suicide.
There has been a long-standing concern that antidepressants may have a role in inducing worsening of depression and the emergence of suicidality in certain patients during the early phases of treatment. Pooled analyses of short-term placebo-controlled trials of antidepressant drugs (selective serotonin reuptake inhibitors [SSRIs] and others) show that these drugs increase the risk of suicidal thinking and behavior (suicidality) in children, adolescents, and young adults (ages 18 to 24) with MDD and other psychiatric disorders.
Short-term clinical trials did not show an increase in the risk of suicidality with antidepressants compared with placebo in adults beyond age 24; there was a reduction with antidepressants compared with placebo in adults aged 65 and older. The pooled analyses of placebo-controlled trials in children and adolescents with MDD, obsessive compulsive disorder (OCD), or other psychiatric disorders included a total of 24 short-term trials of 9 antidepressant drugs in over 4,400 subjects. The pooled analyses of placebo-controlled trials in adults with MDD or other psychiatric disorders included a total of 295 short-term trials (median duration of 2 months) of 11 antidepressant drugs in over 77,000 subjects.
There was considerable variation in risk of suicidality among drugs, but a tendency toward an increase in the younger subjects for almost all drugs studied. There were differences in absolute risk of suicidality across the different indications, with the highest incidence in MDD. The risk differences (drug vs. placebo), however, were relatively stable within age strata and across indications.
These risk differences (drug-placebo difference in the number of cases of suicidality per 1,000 subjects treated) are provided in Table 1. Table 1. Risk Differences in the Number of Suicidality Cases by Age Group in the Pooled Placebo-Controlled Trials of Antidepressants in Pediatric and Adult Subjects Age Range Drug-Placebo Difference in Number of Cases of Suicidality per 1,000 Subjects Treated Increases Compared With Placebo <18 14 additional cases 18-24 5 additional cases Decreases Compared With Placebo 25-64 1 fewer case ≥65 6 fewer cases No suicides occurred in any of the pediatric trials.
There were suicides in the adult trials, but the number was not sufficient to reach any conclusion about drug effect on suicide. It is unknown whether the suicidality risk extends to longer-term use, i.e., beyond several months. However, there is substantial evidence from placebo-controlled maintenance trials in adults with depression that the use of antidepressants can delay the recurrence of depression.
All patients being treated with antidepressants for any indication should be monitored appropriately and observed closely for clinical worsening, suicidality, and unusual changes in behavior, especially during the initial few months of a course of drug therapy, or at times of dose changes, either increases or decreases [see BOXED WARNING]. The following symptoms, anxiety, agitation, panic attacks, insomnia, irritability, hostility, aggressiveness, impulsivity, akathisia (psychomotor restlessness), hypomania, and mania, have been reported in adult and pediatric patients being treated with antidepressants for major depressive disorder as well as for other indications, both psychiatric and nonpsychiatric.
Although a causal link between the emergence of such symptoms and either the worsening of depres…
⚠️ Warnings ▾
WARNING: SUICIDALITY AND ANTIDEPRESSANT DRUGS Antidepressants increased the risk of suicidal thoughts and behavior in children, adolescents, and young adults in short-term trials. These trials did not show an increase in the risk of suicidal thoughts and behavior with antidepressant use in subjects over age 24; there was a reduction in risk with antidepressant use in subjects aged 65 and older [see WARNINGS AND PRECAUTIONS (5.1)]. In patients of all ages who are started on antidepressant therapy, monitor closely for worsening, and for emergence of suicidal thoughts and behaviors.
Advise families and caregivers of the need for close observation and communication with the prescriber [see WARNINGS AND PRECAUTIONS (5.1)].
🤒 Adverse Reactions ▾
The following adverse reactions are discussed in greater detail in other sections of the labeling: • Suicidal thoughts and behaviors in adolescents and young adults [see BOXED WARNING, WARNINGS AND PRECAUTIONS (5.1)] • Neuropsychiatric symptoms and suicide risk in smoking cessation treatment [see BOXED WARNING, WARNINGS AND PRECAUTIONS (5.2)] • Seizure [see WARNINGS AND PRECAUTIONS (5.3)] • Hypertension [see WARNINGS AND PRECAUTIONS (5.4)] • Activation of mania or hypomania [see WARNINGS AND PRECAUTIONS (5.5)] • Psychosis and other neuropsychiatric reactions [see WARNINGS AND PRECAUTIONS (5.6)] • Angle-closure glaucoma [see WARNINGS AND PRECAUTIONS (5.7)] • Hypersensitivity reactions [see WARNINGS AND PRECAUTIONS (5.8)]
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared with rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. Adverse Reactions Leading to Discontinuation of Treatment: In placebo-controlled clinical trials, 4%, 9%, and 11% of the placebo, 300-mg-per-day, and 400-mg-per-day groups, respectively, discontinued treatment due to adverse reactions.
The specific adverse reactions leading to discontinuation in at least 1% of the 300-mg-per-day or 400-mg-per-day groups and at a rate at least twice the placebo rate are listed in Table 2. Table 2. Treatment Discontinuations Due to Adverse Reactions in Placebo-Controlled Trials Adverse Reaction Placebo (n=385) Bupropion Hydrochloride Extended-release (SR) tablets 300 mg/day (n=376) Bupropion Hydrochloride Extended-release (SR) tablets 400 mg/day (n=114) Rash 0.0% 2.4% 0.9% Nausea 0.3% 0.8% 1.8% Agitation 0.3% 0.3% 1.8% Migraine 0.3% 0.0% 1.8% Commonly Observed Adverse Reactions: Adverse reactions from Table 3 occurring in at least 5% of subjects treated with Bupropion Hydrochloride Extended-release (SR) tablets and at a rate at least twice the placebo rate are listed below for the 300- and 400-mg-per-day dose groups.
Bupropion Hydrochloride Extended-release (SR) tablets 300 mg per day: Anorexia, dry mouth, rash, sweating, tinnitus, and tremor. Bupropion Hydrochloride Extended-release (SR) tablets 400 mg per day: Abdominal pain, agitation, anxiety, dizziness, dry mouth, insomnia, myalgia, nausea, palpitation, pharyngitis, sweating, tinnitus, and urinary frequency. Adverse reactions reported in placebo-controlled trials are presented in Table 3.
Reported adverse reactions were classified using a COSTART-based Dictionary. Table 3. Adverse Reactions Reported by at Least 1% of Subjects and at a Greater Frequency than Placebo in Controlled Clinical Trials * Incidence based on the number of female subjects. — Hyphen denotes adverse events occurring in greater than 0 but less than 0.5% of subjects.
Body System/Adverse Reaction Bupropion Hydrochloride Extended-release (SR) tablets 300 mg/day (n = 376) Bupropion Hydrochloride Extended-release (SR) tablets 400 mg/day (n = 114) Placebo (n = 385) Body (General) Headache 26% 25% 23% Infection 8% 9% 6% Abdominal pain 3% 9% 2% Asthenia 2% 4% 2% Chest pain 3% 4% 1% Pain 2% 3% 2% Fever 1% 2% — Cardiovascular Palpitation 2% 6% 2% Flushing 1% 4% — Migraine 1% 4% 1% Hot flashes 1% 3% 1% Digestive Dry mouth 17% 24% 7% Nausea 13% 18% 8% Constipation 10% 5% 7% Diarrhea 5% 7% 6% Anorexia 5% 3% 2% Vomiting 4% 2% 2% Dysphagia 0% 2% 0% Musculoskeletal Myalgia 2% 6% 3% Arthralgia 1% 4% 1% Arthritis 0% 2% 0% Twitch 1% 2% — Nervous system Insomnia 11% 16% 6% Dizziness 7% 11% 5% Agitation 3% 9% 2% Anxiety 5% 6% 3% Tremor 6% 3% 1% Nervousness 5% 3% 3% Somnolence 2% 3% 2% Irritability 3% 2% 2% Memory decreased — 3% 1% Paresthesia 1% 2% 1% Central nervous system stimulation 2% 1% 1% Respiratory Pharyngitis 3% 11% 2% Sinusitis 3% 1% 2% Increased cough 1% 2% 1% Skin Sweating 6% 5% 2% Rash 5% 4% 1% Pruritus 2% 4% 2% Urticaria 2% 1% 0% Special senses Tinnitus 6% 6% 2%…
🔄 Drug Interactions ▾
7.1Potential for Other Drugs to Affect Bupropion Hydrochloride Extended-release (SR) Tablets Bupropion is primarily metabolized to hydroxybupropion by CYP2B6. Therefore, the potential exists for drug interactions between Bupropion Hydrochloride Extended-release (SR) tablets and drugs that are inhibitors or inducers of CYP2B6. Inhibitors of CYP2B6: Ticlopidine and Clopidogrel: Concomitant treatment with these drugs can increase bupropion exposure but decrease hydroxybupropion exposure.
Based on clinical response, dosage adjustment of Bupropion Hydrochloride Extended-release (SR) tablets may be necessary when coadministered with CYP2B6 inhibitors (e.g., ticlopidine or clopidogrel) [see CLINICAL PHARMACOLOGY (12.3)]. Inducers of CYP2B6: Ritonavir, Lopinavir, and Efavirenz: Concomitant treatment with these drugs can decrease bupropion and hydroxybupropion exposure. Dosage increase of Bupropion Hydrochloride Extended-release (SR) tablets may be necessary when coadministered with ritonavir, lopinavir, or efavirenz [see CLINICAL PHARMACOLOGY (12.3)] but should not exceed the maximum recommended dose.
Carbamazepine, Phenobarbital, Phenytoin: While not systematically studied, these drugs may induce the metabolism of bupropion and may decrease bupropion exposure [see CLINICAL PHARMACOLOGY (12.3)]. If bupropion is used concomitantly with a CYP inducer, it may be necessary to increase the dose of bupropion, but the maximum recommended dose should not be exceeded.
7.2Potential for Bupropion Hydrochloride Extended-release (SR) Tablets to Affect Other Drugs Drugs Metabolized by CYP2D6: Bupropion and its metabolites (erythrohydrobupropion, threohydrobupropion, hydroxybupropion) are CYP2D6 inhibitors. Therefore, coadministration of Bupropion Hydrochloride Extended-release (SR) tablets with drugs that are metabolized by CYP2D6 can increase the exposures of drugs that are substrates of CYP2D6. Such drugs include certain antidepressants (e.g., venlafaxine, nortriptyline, imipramine, desipramine, paroxetine, fluoxetine, and sertraline), antipsychotics (e.g., haloperidol, risperidone, thioridazine), beta-blockers (e.g., metoprolol), and Type 1C antiarrhythmics (e.g., propafenone and flecainide).
When used concomitantly with Bupropion Hydrochloride Extended-release (SR) tablets, it may be necessary to decrease the dose of these CYP2D6 substrates, particularly for drugs with a narrow therapeutic index. Drugs that require metabolic activation by CYP2D6 to be effective (e.g., tamoxifen) theoretically could have reduced efficacy when administered concomitantly with inhibitors of CYP2D6 such as bupropion. Patients treated concomitantly with Bupropion Hydrochloride Extended-release (SR) tablets and such drugs may require increased doses of the drug [see CLINICAL PHARMACOLOGY (12.3)].
Digoxin Coadministration of Bupropion Hydrochloride Extended-release (SR) tablets with digoxin may decrease plasma digoxin levels. Monitor plasma digoxin levels in patients treated concomitantly with WELLBUTRIN SR and digoxin [see Clinical Pharmacology (12.3)].
7.3Drugs that Lower Seizure Threshold Use extreme caution when coadministering Bupropion Hydrochloride Extended-release (SR) tablets with other drugs that lower seizure threshold (e.g., other bupropion products, antipsychotics, antidepressants, theophylline, or systemic corticosteroids). Use low initial doses and increase the dose gradually [see CONTRAINDICATIONS (4), WARNINGS AND PRECAUTIONS (5.3)].
7.4Dopaminergic Drugs (Levodopa and Amantadine) Bupropion, levodopa, and amantadine have dopamine agonist effects. CNS toxicity has been reported when bupropion was coadministered with levodopa or amantadine. Adverse reactions have included restlessness, agitation, tremor, ataxia, gait disturbance, vertigo, and dizziness.
It is presumed that the toxicity results from cumulative dopamine agonist effects. Use caution when administering Bupropion Hydrochloride Extended-release (SR) tablets concomitantly with these drugs.…
👥 Use in Specific Populations ▾
8.1Pregnancy Pregnancy Category C Risk Summary: Data from epidemiological studies of pregnant women exposed to bupropion in the first trimester indicate no increased risk of congenital malformations overall. All pregnancies, regardless of drug exposure, have a background rate of 2% to 4% for major malformations, and 15% to 20% for pregnancy loss. No clear evidence of teratogenic activity was found in reproductive developmental studies conducted in rats and rabbits; however, in rabbits, slightly increased incidences of fetal malformations and skeletal variations were observed at doses approximately equal to the maximum recommended human dose (MRHD) and greater and decreased fetal weights were seen at doses twice the MRHD and greater.
Bupropion Hydrochloride Extended-release (SR) tablets should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus. Clinical Considerations: Consider the risks of untreated depression when discontinuing or changing treatment with antidepressant medications during pregnancy and postpartum. Human Data: Data from the international bupropion Pregnancy Registry (675 first trimester exposures) and a retrospective cohort study using the United Healthcare database (1,213 first trimester exposures) did not show an increased risk for malformations overall.
No increased risk for cardiovascular malformations overall has been observed after bupropion exposure during the first trimester. The prospectively observed rate of cardiovascular malformations in pregnancies with exposure to bupropion in the first trimester from the international Pregnancy Registry was 1.3% (9 cardiovascular malformations/675 first-trimester maternal bupropion exposures), which is similar to the background rate of cardiovascular malformations (approximately 1%). Data from the United Healthcare database and a case-control study (6,853 infants with cardiovascular malformations and 5,763 with non-cardiovascular malformations) from the National Birth Defects Prevention Study (NBDPS) did not show an increased risk for cardiovascular malformations overall after bupropion exposure during the first trimester.
Study findings on bupropion exposure during the first trimester and risk for left ventricular outflow tract obstruction (LVOTO) are inconsistent and do not allow conclusions regarding a possible association. The United Healthcare database lacked sufficient power to evaluate this association; the NBDPS found increased risk for LVOTO (n = 10; adjusted OR = 2.6; 95% CI: 1.2, 5.7), and the Slone Epidemiology case control study did not find increased risk for LVOTO. Study findings on bupropion exposure during the first trimester and risk for ventricular septal defect (VSD) are inconsistent and do not allow conclusions regarding a possible association.
The Slone Epidemiology Study found an increased risk for VSD following first trimester maternal bupropion exposure (n = 17; adjusted OR = 2.5; 95% CI: 1.3, 5.0) but did not find increased risk for any other cardiovascular malformations studied (including LVOTO as above). The NBDPS and United Healthcare database study did not find an association between first trimester maternal bupropion exposure and VSD. For the findings of LVOTO and VSD, the studies were limited by the small number of exposed cases, inconsistent findings among studies, and the potential for chance findings from multiple comparisons in case control studies.
Animal Data: In studies conducted in rats and rabbits, bupropion was administered orally during the period of organogenesis at doses of up to 450 and 150 mg per kg per day, respectively (approximately 11 and 7 times the MRHD, respectively, on a mg per m2 basis). No clear evidence of teratogenic activity was found in either species; however, in rabbits, slightly increased incidences of fetal malformations and skeletal variations were observed at the lowest dose tested (25 mg per kg per day, approximately equal to the MRHD on a mg per m2…
🆘 Overdosage ▾
10.1Human Overdose Experience Overdoses of up to 30 grams or more of bupropion have been reported. Seizure was reported in approximately one-third of all cases. Other serious reactions reported with overdoses of bupropion alone included hallucinations, loss of consciousness, sinus tachycardia, and ECG changes such as conduction disturbances (including QRS prolongation) or arrhythmias.
Fever, muscle rigidity, rhabdomyolysis, hypotension, stupor, coma, and respiratory failure have been reported mainly when bupropion was part of multiple drug overdoses. Although most patients recovered without sequelae, deaths associated with overdoses of bupropion alone have been reported in patients ingesting large doses of the drug. Multiple uncontrolled seizures, bradycardia, cardiac failure, and cardiac arrest prior to death were reported in these patients.
10.2Overdosage Management Consult a Certified Poison Control Center for up-to-date guidance and advice. Telephone numbers for certified poison control centers are listed in the Physicians' Desk Reference (PDR). Call 1-800-222-1222 or refer to www.poison.org.
There are no known antidotes for bupropion. In case of an overdose, provide supportive care, including close medical supervision and monitoring. Consider the possibility of multiple drug overdose.
Ensure an adequate airway, oxygenation, and ventilation. Monitor cardiac rhythm and vital signs. Induction of emesis is not recommended.
🧬 Clinical Pharmacology ▾
12.1Mechanism of Action The exact mechanism of the antidepressant action of bupropion is not known, but is presumed to be related to noradrenergic and/or dopaminergic mechanisms. Bupropion is a relatively weak inhibitor of the neuronal reuptake of norepinephrine and dopamine, and does not inhibit the reuptake of serotonin. Bupropion does not inhibit monoamine oxidase.
12.3Pharmacokinetics Bupropion is a racemic mixture. The pharmacological activity and pharmacokinetics of the individual enantiomers have not been studied. The mean elimination half-life (±SD) of bupropion after chronic dosing is 21 (±9) hours, and steady-state plasma concentrations of bupropion are reached within 8 days.
Absorption: The absolute bioavailability of Bupropion Hydrochloride Extended-release (SR) tablets in humans has not been determined because an intravenous formulation for human use is not available. However, it appears likely that only a small proportion of any orally administered dose reaches the systemic circulation intact. In rat and dog studies, the bioavailability of bupropion ranged from 5% to 20%.
In humans, following oral administration of Bupropion Hydrochloride Extended-release (SR) tablets, peak plasma concentration (Cmax) of bupropion is usually achieved within 3 hours. In a trial comparing chronic dosing with Bupropion Hydrochloride Extended-release (SR) tablets 150 mg twice daily to bupropion immediate-release formulation 100 mg 3 times daily, the steady state Cmax for bupropion after Bupropion Hydrochloride Extended-release (SR) tablets administration was approximately 85% of those achieved after bupropion immediate-release formulation administration.
Exposure (AUC) to bupropion was equivalent for both formulations. Bioequivalence was also demonstrated for all three major active metabolites (i.e., hydroxybupropion, threohydrobupropion and erythrohydrobupropion) for both Cmax and AUC. Thus, at steady state, Bupropion Hydrochloride Extended-release (SR) tablets given twice daily, and the immediate-release formulation of bupropion given 3 times daily, are essentially bioequivalent for both bupropion and the 3 quantitatively important metabolites.
Bupropion Hydrochloride Extended-release (SR) tablets can be taken with or without food. Bupropion Cmax and AUC were increased by 11% to 35% and 16% to 19%, respectively, when Bupropion Hydrochloride Extended-release (SR) tablets were administered with food to healthy volunteers in three trials. The food effect is not considered clinically significant.
Distribution: In vitro tests show that bupropion is 84% bound to human plasma proteins at concentrations up to 200 mcg per mL.. The extent of protein binding of the hydroxybupropion metabolite is similar to that for bupropion; whereas, the extent of protein binding of the threohydrobupropion metabolite is about half that seen with bupropion. Metabolism: Bupropion is extensively metabolized in humans.
Three metabolites are active: hydroxybupropion, which is formed via hydroxylation of the tert-butyl group of bupropion, and the amino-alcohol isomers, threohydrobupropion and erythrohydrobupropion, which are formed via reduction of the carbonyl group. In vitro findings suggest that CYP2B6 is the principal isoenzyme involved in the formation of hydroxybupropion, while cytochrome P450 enzymes are not involved in the formation of threohydrobupropion. Oxidation of the bupropion side chain results in the formation of a glycine conjugate of meta-chlorobenzoic acid, which is then excreted as the major urinary metabolite.
The potency and toxicity of the metabolites relative to bupropion have not been fully characterized. However, it has been demonstrated in an antidepressant screening test in mice that hydroxybupropion is one-half as potent as bupropion, while threohydrobupropion and erythrohydrobupropion are 5-fold less potent than bupropion. This may be of clinical importance because the plasma concentrations of the metabolites are as high as or highe…
📦 How Supplied / Storage and Handling ▾
Bupropion hydrochloride extended-release tablets, USP (XL) are supplied as: NDC Strength Quantity Description 16729-443-10 150 mg bottle of 30 tablets creamy-white to pale yellow, round tablets printed with “GS1” on one side and plain on the other side 16729-443-15 150 mg bottle of 90 tablets creamy-white to pale yellow, round tablets printed with “GS1” on one side and plain on the other side 16729-443-16 150 mg bottle of 500 tablets creamy-white to pale yellow, round tablets printed with “GS1” on one side and plain on the other side 16729-444-10 300 mg bottle of 30 tablets creamy-white to pale yellow, round tablets printed with “GS2” on one side and plain on the other side 16729-444-15 300 mg bottle of 90 tablets creamy-white to pale yellow, round tablets printed with “GS2” on one side and plain on the other side 16729-444-16 300 mg bottle of 500 tablets creamy-white to pale yellow, round tablets printed with “GS2” on one side and plain on the other side Store at 25°C (77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature].Protect from light.
Bupropion hydrochloride extended-release tablets, USP (XL) may have an odor.
📋 Description ▾
Bupropion Hydrochloride Extended-release Tablets USP (SR), an antidepressant of the aminoketone class, is chemically unrelated to tricyclic, tetracyclic, selective serotonin re-uptake inhibitor, or other known antidepressant agents. Its structure closely resembles that of diethylpropion; it is related to phenylethylamines. It is designated as (±)-1-(3-chlorophenyl)-2-[(1,1-dimethylethyl)amino]-1-propanone hydrochloride.
The molecular weight is 276.2. The molecular formula is C13H18ClNO∙HCl. Bupropion hydrochloride powder is white, crystalline, and highly soluble in water.
It has a bitter taste and produces the sensation of local anesthesia on the oral mucosa. The structural formula is: [Chemical Structure] Bupropion Hydrochloride Extended-release Tablets USP (SR) is supplied for oral administration as 100-mg (blue), 150-mg (purple), and 200-mg (pink), film-coated, sustained-release tablets. Each tablet contains the labeled amount of bupropion hydrochloride and the inactive ingredients: copovidone, glyceryl behenate, hydroxypropyl cellulose, magnesium stearate, microcrystalline cellulose, polyethylene glycol, polyvinyl alcohol, talc and titanium dioxide.
In addition, the 100-mg tablet contains FD&C Blue No. 2 Lake, the 150-mg tablet contains FD&C Blue No. 2 Lake and FD&C Red No.
40 Lake, and the 200-mg tablet contains Iron Oxide Red. Meet USP Dissolution Test 19.
💬 Medication Guide ▾
Bupropion Hydrochloride Extended-release (SR) Tablets, USP (bue-PROE-pee-on HYE-droe-KLOR-ide) IMPORTANT: Be sure to read the three sections of this Medication Guide. The first section is about the risk of suicidal thoughts and actions with antidepressant medicines; the second section is about the risk of changes in thinking and behavior, depression and suicidal thoughts or actions with medicines used to quit smoking; and the third section is entitled What Other Important Information Should I Know About Bupropion Hydrochloride Extended-release (SR) Tablets?
Antidepressant Medicines, Depression and Other Serious Mental Illnesses, and Suicidal Thoughts or Actions This section of the Medication Guide is only about the risk of suicidal thoughts and actions with antidepressant medicines. What is the most important information I should know about antidepressant medicines, depression and other serious mental illnesses, and suicidal thoughts or actions? What is the most important information I should know about antidepressant medicines, depression and other serious mental illnesses, and suicidal thoughts or actions?
1. Antidepressant medicines may increase suicidal thoughts or actions in some children, teenagers, or young adults within the first few months of treatment. 2.
Depression or other serious mental illnesses are the most important causes of suicidal thoughts and actions. Some people may have a particularly high risk of having suicidal thoughts or actions. These include people who have (or have a family history of) bipolar illness (also called manic-depressive illness) or suicidal thoughts or actions.
3. How can I watch for and try to prevent suicidal thoughts and actions in myself or a family member? • Pay close attention to any changes, especially sudden changes, in mood, behaviors, thoughts, or feelings. This is very important when an antidepressant medicine is started or when the dose is changed. • Call your healthcare provider right away to report new or sudden changes in mood, behavior, thoughts, or feelings. • Keep all follow-up visits with your healthcare provider as scheduled.
Call the healthcare provider between visits as needed, especially if you have concerns about symptoms. Call your healthcare provider right away if you or your family member has any of the following symptoms, especially if they are new, worse, or worry you: • thoughts about suicide or dying • attempts to commit suicide • new or worse depression • new or worse anxiety • feeling very agitated or restless • panic attacks • trouble sleeping (insomnia) • new or worse irritability • acting aggressive, being angry, or violent • acting on dangerous impulses • an extreme increase in activity and talking (mania) • other unusual changes in behavior or mood What else do I need to know about antidepressant medicines? • Never stop an antidepressant medicine without first talking to a healthcare provider.
Stopping an antidepressant medicine suddenly can cause other symptoms. • Antidepressants are medicines used to treat depression and other illnesses. It is important to discuss all the risks of treating depression and also the risks of not treating it. Patients and their families or other caregivers should discuss all treatment choices with the healthcare provider, not just the use of antidepressants. • Antidepressant medicines have other side effects.
Talk to the healthcare provider about the side effects of the medicine prescribed for you or your family member. • Antidepressant medicines can interact with other medicines. Know all of the medicines that you or your family member takes. Keep a list of all medicines to show the healthcare provider.
Do not start new medicines without first checking with your healthcare provider. It is not known if Bupropion Hydrochloride Extended-release (SR) tablets are safe and effective in children under the age of 18. Quitting Smoking, Quit-Smoking Medications, Changes in Thinking and Behavior, Depression, and Suicidal Though…