
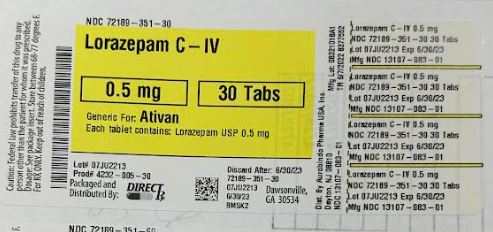
Lorazepam .5 mg Tablet, 2-count — NDC 72189-351-02 (Billing 72189-0351-02)
This is a package of 2 tablets of Lorazepam .5 mg Tablet from DirectRx, marketed since Apr 2022 and currently FDA-listed. It is the main listing for this product, which comes in 3 package sizes.
NDC database record
One package, one record: these facts belong to NDC 72189-351-02 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 72189 labeler · 351 product · 02 package
- Package marketed since
- Apr 29, 2022
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Billing quantity
- 2 EA per package
- Barcode (UPC-A, from the NDC)
- 3 7218935102 1
- FDA record last changed
- Jul 24, 2026
Other active recalls for Lorazepam (different manufacturers) — 1 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 003757
- GCN: 14160
- GPI-14 (Medi-Span): 57100060000305
- HICL (First Databank): 004846
- AHFS class code: 28:12.08.00
- RxCUI (RxNorm): 197900
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Benzodiazepine class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Lorazepam is used to relieve anxiety and treat insomnia. Lorazepam is in a class of medications called benzodiazepines. It works by slowing activity in the brain to allow for relaxation.
Read the full MedlinePlus article ↗- It depends on the form. Tablets and the oral liquid are for anxiety disorders or short-term anxiety relief. The injection is used in the hospital for status epilepticus and for sed...
- Take it exactly as your prescriber directs. If you use the liquid concentrate, mix it into water, juice, applesauce or pudding with the supplied dropper, then use it all right away...
- No, avoid alcohol. Opioids with lorazepam can cause extreme sleepiness, slowed breathing, coma and death. Tell me about every medicine you take so we can check for problems.
- Can I drink alcohol or take opioids with it?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Lorazepam — tap one for details:
Lorazepam may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.1178 | $0.24 / 2 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 4, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 72189-0351-02 You're viewing this Main listing | 2 TABLET in 1 BOTTLE | 2022-04-29 | — | Active |
| 72189-0351-30 72189-351-30 | 30 TABLET in 1 BOTTLE | 2022-04-29 | — | Active |
| 72189-0351-60 72189-351-60 | 60 TABLET in 1 BOTTLE | 2022-04-29 | — | Active |
You're viewing the smallest of 3 pack sizes for this product.
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 72189-0351-30?
What NDC number is used to bill for this package of Lorazepam .5 mg Tablet?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Lorazepam .5 mg 00093-3425-01 | Teva | 100 tablets | $0.034 | AB | Availability likely | — |
| Lorazepam .5 mg 13107-0083-01 | Aurolife | 100 tablets | $0.034 | AB | Availability likely | — |
| Lorazepam .5 mg 60687-0820-01 | American | 100 tablets | $0.034 | AB | Availability likely | — |
| Lorazepam .5 mg 62135-0861-01 | Chartwell | 100 tablets | $0.034 | — | Availability likely | — |
| Lorazepam .5 mg 63304-0772-01 | SUN | 100 tablets | $0.034 | AB | Availability likely | — |
| Lorazepam .5 mg 64980-0627-01 | Rising | 100 tablets | $0.034 | AB | Availability likely | — |
| Lorazepam .5 mg 69315-0904-01 | Leading | 100 tablets | $0.034 | AB | Availability likely | — |
| Lorazepam .5 mg 00904-6007-60 | Major | 100 tablets | $0.046 | AB | Discontinued | — |
| Ativan .5 mg 00187-0063-01 | Bausch | 100 tablets | $32.865 | AB | FDA listed | — |
| Lorazepam .5 mg 51407-0996-01 | Golden | 100 tablets | — | AB | FDA listed | — |
| Lorazepam .5 mg 58118-0904-08 | Clinical | 30 tablets | — | AB | FDA listed | — |
| Lorazepam .5 mg 61919-0062-02 | DIRECT | 2 tablets | — | AB | FDA listed | — |
| Lorazepam .5 mg 62559-0195-01 | ANI | 100 tablets | — | AB | FDA listed | — |
| Lorazepam .5 mg 67046-0786-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| Lorazepam .5 mg 67296-1478-01 | Redpharm | 10 tablets | — | AB | Discontinued | — |
| Lorazepam .5 mg 67296-1629-01 | RedPharm | 10 tablets | — | AB | FDA listed | — |
| Lorazepam .5 mg 68071-3096-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Lorazepam .5 mg 68071-3121-06 | NuCare | 6 tablets | — | AB | FDA listed | — |
| Lorazepam .5 mg 68071-3751-06 | NuCare | 60 tablets | — | AB | FDA listed | — |
| Lorazepam .5 mg 68071-4916-04 | NuCare | 45 tablets | — | AB | FDA listed | — |
| Lorazepam .5 mg 68071-5068-06 | NuCare | 6 tablets | — | AB | FDA listed | — |
| Lorazepam .5 mg 68788-7355-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Lorazepam .5 mg 70518-1520-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Lorazepam .5 mg 70518-3806-00 | REMEDYREPACK | 30 tablets | — | AB | Discontinued | — |
| Lorazepam .5 mg 71205-0166-02 | Proficient | 2 tablets | — | AB | FDA listed | — |
| Lorazepam .5 mg 71205-0228-02 | Proficient | 2 tablets | — | AB | FDA listed | — |
| Lorazepam .5 mg 71205-0756-10 | Proficient | 10 tablets | — | AB | FDA listed | — |
| Lorazepam .5 mg 71335-0329-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Lorazepam .5 mg 71335-1455-01 | Bryant | 30 tablets | — | AB | Discontinued | — |
| Lorazepam .5 mg 71610-0008-10 | Aphena | 10 tablets | — | AB | FDA listed | — |
| Lorazepam .5 mg 71610-0199-10 | Aphena | 10 tablets | — | AB | FDA listed | — |
| Lorazepam .5 mg 71610-0225-15 | Aphena | 15 tablets | — | AB | FDA listed | — |
| Lorazepam .5 mg 71610-0654-10 | Aphena | 10 tablets | — | AB | FDA listed | — |
| Lorazepam .5 mg 71610-0764-10 | Aphena | 10 tablets | — | AB | FDA listed | — |
| Lorazepam .5 mg 71610-0827-10 | Aphena | 10 tablets | — | AB | FDA listed | — |
| Lorazepam .5 mgthis 72189-0351-02 | DirectRx | 2 tablets | — | AB | FDA listed | — |
| Lorazepam .5 mg 72789-0236-30 | PD-Rx | 30 tablets | — | AB | FDA listed | — |
| Lorazepam .5 mg 72789-0355-30 | PD-Rx | 30 tablets | — | AB | FDA listed | — |
| Lorazepam .5 mg 76420-0647-01 | Asclemed | 100 tablets | — | AB | FDA listed | — |
| Lorazepam .5 mg 76420-0872-00 | Asclemed | 1000 tablets | — | AB | FDA listed | — |
| Lorazepam .5 mg 87441-0050-01 | Unit | 30 tablets | — | AB | FDA listed | — |
| Lorazepam .5 mg 60760-0947-02 | St. | 2 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3SY5LH9PMK
Anhydrous lactose is a milk sugar with no water content. It acts as a filler and binder in tablets and capsules, adding bulk and helping ingredients stick together.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 0BZ5A00FQU
Polacrilin potassium is a synthetic polymer that absorbs water and swells. It acts as a disintegrant, helping tablets or capsules break apart quickly so the active ingredient can be absorbed in your body.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 3, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from DirectRx labeler code 72189
- Cartia Xt diltiazem hydrochloride 300 mg Capsule, Extended Release NDC 72189-344-90
- Levothyroxine Sodium 200 ug Tablet NDC 72189-346-90
- Progesterone 200 mg Capsule NDC 72189-347-90
- Hydrocodone Bitartrate and Acetaminophen 325 mg; 10 mg Tablet NDC 72189-348-20
- Bupropion Hydrochloride SR 150 mg Tablet, Film Coated, Extended Release NDC 72189-349-30
- Piroxicam 20 mg Capsule NDC 72189-350-60
- Hydrocodone APAP 7.5 mg; 325 mg Tablet NDC 72189-352-30
- Armodafinil 200 mg Tablet NDC 72189-353-30
- Doxepin HCL 10 mg Capsule NDC 72189-355-30
- Chlorthalidone 25 mg Tablet NDC 72189-356-60
- Doxycycline Monohydrate 100 mg Capsule NDC 72189-358-20
- Gentamicin Sulfate Opth Solution 3 mg/mL Solution/ Drops NDC 72189-359-05
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
Lorazepam tablets are indicated for the management of anxiety disorders or for the short-term relief of the symptoms of anxiety or anxiety associated with depressive symptoms. Anxiety or tension associated with the stress of everyday life usually does not require treatment with an anxiolytic. The effectiveness of lo razepam tablets in long-term use, that is, more than 4 months, has not been assessed by systematic clinical studies.
The physician should periodically reassess the usefulness of the drug for the individual patient.
⏱️ Dosage and Administration ▾
Lorazepam tablets are administered orally. For optimal results, dose, frequency of administration, and duration of therapy should be individualized according to patient response. To facilitate this, 0.5 mg, 1 mg, and 2 mg tablets are available.
The usual range is 2 to 6 mg/day given in divided doses, the largest dose being taken before bedtime, but the daily dosage may vary from 1 to 10 mg/day. For anxiety, most patients require an initial dose of 2 to 3 mg/day given two times a day or three times a day. For insomnia due to anxiety or transient situational stress, a single daily dose of 2 to 4 mg may be given, usually at bedtime.
For elderly or debilitated patients, an initial dosage of 1 to 2 mg/day in divided doses is recommended, to be adjusted as needed and tolerated. The dosage of l orazepam tablets should be increased gradually when needed to help avoid adverse effects. When higher dosage is indicated, the evening dose should be increased before the daytime doses.
Discontinuation or Dosage Reduction of Lorazepam Tablets To reduce the risk of withdrawal reactions, use a gradual taper to discontinue lorazepam tablets or reduce the dosage. If a patient develops withdrawal reactions, consider pausing the taper or increasing the dosage to the previous tapered dosage level. Subsequently decrease the dosage more slowly (see WARNINGS: Dependence and Withdrawal Reactions and DRUG ABUSE AND DEPENDENCE: Dependence).
⛔ Contraindications ▾
Lorazepam is contraindicated in patients with: • hypersensitivity to benzodiazepines or to any components of the formulation • acute narrow-angle glaucoma.
⚠️ Warnings ▾
Risks from Concomitant Use with Opioids Concomitant use of benzodiazepines, including lorazepam, and opioids may result in profound sedation, respiratory depression, coma, and death. Because of these risks, reserve concomitant prescribing of these drugs in patients for whom alternative treatment options are inadequate. Observational studies have demonstrated that concomitant use of opioid analgesics and benzodiazepines increases the risk of drug-related mortality compared to use of opioids alone.
If a decision is made to prescribe lorazepam concomitantly with opioids, prescribe the lowest effective dosages and minimum durations of concomitant use, and follow patients closely for signs and symptoms of respiratory depression and sedation. In patients already receiving an opioid analgesic, prescribe a lower initial dose of lorazepam than indicated in the absence of an opioid and titrate based on clinical response. If an opioid is initiated in a patient already taking lorazepam, prescribe a lower initial dose of the opioid and titrate based upon clinical response.
Advise both patients and caregivers about the risks of respiratory depression and sedation when lorazepam is used with opioids. Advise patients not to drive or operate heavy machinery until the effects of concomitant use with the opioid have been determined (seePRECAUTIONS: Drug Interactions). Abuse, Misuse, and Addiction The use of benzodiazepines, including lorazepam, exposes users to the risks of abuse, misuse, and addiction, which can lead to overdose or death.
Abuse and misuse of benzodiazepines often (but not always) involve the use of doses greater than the maximum recommended dosage and commonly involve concomitant use of other medications, alcohol, and/or illicit substances, which is associated with an increased frequency of serious adverse outcomes, including respiratory depression, overdose, or death (seeDRUG ABUSE AND DEPENDENCE: Abuse). Before prescribing lorazepam and throughout treatment, assess each patient’s risk for abuse, misuse, and addiction (e.g., using a standardized screening tool).
Use of lorazepam, particularly in patients at elevated risk, necessitates counseling about the risks and proper use of lorazepam along with monitoring for signs and symptoms of abuse, misuse, and addiction. Prescribe the lowest effective dosage; avoid or minimize concomitant use of CNS depressants and other substances associated with abuse, misuse, and addiction (e.g., opioid analgesics, stimulants); and advise patients on the proper disposal of unused drug. If a substance use disorder is suspected, evaluate the patient and institute (or refer them for) early treatment, as appropriate.
Dependence and Withdrawal Reactions To reduce the risk of withdrawal reactions, use a gradual taper to discontinue lorazepam or reduce the dosage (a patient-specific plan should be used to taper the dose)(SEE DOSAGE AND ADMINSTRATION: Discontinuation or Dosage Reduction of lorazepam). Patients at an increased risk of withdrawal adverse reactions after benzodiazepine discontinuation or rapid dosage reduction include those who take higher dosages, and those who have had longer durations of use. Acute Withdrawal Reactions The continued use of benzodiazepines, including lorazepam, may lead to clinically significant physical dependence.
Abrupt discontinuation or rapid dosage reduction of lorazepam after continued use, or administration of flumazenil (a benzodiazepine antagonist) may precipitate acute withdrawal reactions, which can be life-threatening (e.g., seizures)(SEE DRUG ABUSE AND DEPENDENCE: Dependence). Protracted Withdrawal Syndrome In some cases, benzodiazepine users have developed a protracted withdrawal syndrome with withdrawal symptoms lasting weeks to more than 12 months (SEE DRUG ABUSE AND DEPENDENCE: Dependence ). Pre-existing depression may emerge or worsen during use of benzodiazepines including lorazepam.
Lorazepam is not recommended for use in patients with a primary depre… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
Most adverse reactions to benzodiazepines, including CNS effects and respiratory depression, are dose dependent, with more severe effects occurring with high doses. In a sample of about 3500 patients treated for anxiety, the most frequent adverse reaction to l orazepam was sedation (15.9%), followed by dizziness (6.9%), weakness (4.2%), and unsteadiness (3.4%). The incidence of sedation and unsteadiness increased with age.
Other adverse reactions to benzodiazepines, including l orazepam are fatigue, drowsiness, amnesia, memory impairment, confusion, disorientation, depression, unmasking of depression, disinhibition, euphoria, suicidal ideation/attempt, ataxia, asthenia, extrapyramidal symptoms, convulsions/seizures, tremor, vertigo, eye function/visual disturbance (including diplopia and blurred vision), dysarthria/slurred speech, change in libido, impotence, decreased orgasm; headache, coma; respiratory depression, apnea, worsening of sleep apnea, worsening of obstructive pulmonary disease; gastrointestinal symptoms including nausea, change in appetite, constipation, jaundice, increase in bilirubin, increase in liver transaminases, increase in alkaline phosphatase; hypersensitivity reactions, anaphylactoid reactions; dermatological symptoms, allergic skin reactions, alopecia; syndrome of inappropriate antidiuretic hormone (SIADH), hyponatremia; thrombocytopenia, agranulocytosis, pancytopenia; hypothermia; and autonomic manifestations.
Paradoxical reactions, including anxiety, excitation, agitation, hostility, aggression, rage, sleep disturbances/insomnia, sexual arousal, and hallucinations may occur. Small decreases in blood pressure and hypotension may occur but are usually not clinically significant, probably being related to the relief of anxiety produced by l orazepam. To report SUSPECTED ADVERSE REACTIONS, contact Aurobindo Pharma USA, Inc. at 1-866-850-2876 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
🆘 Overdosage ▾
In postmarketing experience, overdose with lorazepam has occurred predominantly in combination with alcohol and/or other drugs. Therefore, in the management of overdosage, it should be borne in mind that multiple agents may have been taken. Symptoms Overdosage of benzodiazepines is usually manifested by varying degrees of CNS depression ranging from drowsiness to coma.
In mild cases, symptoms include drowsiness, mental confusion, paradoxical reactions, dysarthria, and lethargy. In more serious cases, and especially when other drugs or alcohol were ingested, symptoms may include ataxia, hypotonia, hypotension, cardiovascular depression, respiratory depression, hypnotic state, coma, and death. Management General supportive and symptomatic measures are recommended; vital signs must be monitored, and the patient closely observed.
When there is a risk of aspiration, induction of emesis is not recommended. Gastric lavage may be indicated if performed soon after ingestion or in symptomatic patients. Administration of activated charcoal may also limit drug absorption.
Hypotension, though unlikely, usually may be controlled with norepinephrine bitartrate injection. Lorazepam is poorly dialyzable. Lorazepam glucuronide, the inactive metabolite, may be highly dialyzable.
The benzodiazepine antagonist flumazenil may be used in hospitalized patients as an adjunct to, not as a substitute for, proper management of benzodiazepine overdose. The prescriber should be aware of a risk of seizure in association with flumazenil treatment, particularly in long-term benzodiazepine users and in cyclic antidepressant overdose. The complete flumazenil package insert including CONTRAINDICATIONS, WARNINGS, and PRECAUTIONS sections should be consulted prior to use.
🧬 Clinical Pharmacology ▾
Studies in healthy volunteers show that in single high doses lorazepam has a tranquilizing action on the central nervous system with no appreciable effect on the respiratory or cardiovascular systems. Lorazepam is readily absorbed with an absolute bioavailability of 90%. Peak concentrations in plasma occur approximately 2 hours following administration.
The peak plasma level of lorazepam from a 2 mg dose is approximately 20 ng/mL. The mean half-life of unconjugated lorazepam in human plasma is about 12 hours and for its major metabolite, lorazepam glucuronide, about 18 hours. At clinically relevant concentrations, lorazepam is approximately 85% bound to plasma proteins. lorazepam is rapidly conjugated at its 3-hydroxy group into lorazepam glucuronide which is then excreted in the urine.
Lorazepam glucuronide has no demonstrable central nervous system (CNS) activity in animals. The plasma levels of lorazepam are proportional to the dose given. There is no evidence of accumulation of lorazepam on administration up to 6 months.
Studies comparing young and elderly subjects have shown that advancing age does not have a significant effect on the pharmacokinetics of lorazepam. However, in one study involving single intravenous doses of 1.5 to 3 mg of Lorazepam injection, mean total body clearance of lorazepam decreased by 20% in 15 elderly subjects of 60 to 84 years of age compared to that in 15 younger subjects of 19 to 38 years of age.
📦 How Supplied / Storage and Handling ▾
Lorazepam Tablets, USP are available in the following dosage strengths: 0.5 mg, white to off-while, round, flat-faced beveled edge tablets debossed with “U32” on one side and plain on the other side. NDC 13107-083-11 Bottles of 10 tablets NDC 13107-083-01 Bottles of 100 tablets NDC 13107-083-05 Bottles of 500 tablets NDC 13107-083-99 Bottles of 1000 tablets 1 mg, white to off-white, round, flat-faced beveled edge tablets debossed with “U33” on one side and bisect on the other side. NDC 13107-084-11 Bottles of 10 tablets NDC 13107-084-01 Bottles of 100 tablets NDC 13107-084-05 Bottles of 500 tablets NDC 13107-084-99 Bottles of 1000 tablets 2 mg, while to off-white, round, flat-faced beveled edge tablets debossed with a bisect separating “U” and “34” on one side and “2” on the other side.
NDC 13107-085-11 Bottles of 10 tablets NDC 13107-085-01 Bottles of 100 tablets NDC 13107-085-05 Bottles of 500 tablets NDC 13107-085-99 Bottles of 1000 tablets Keep bottles tightly closed. Keep out of reach of children. STORE AT 20°C to 25°C (68° to 77°F) [SEE USP CONTROLLED ROOM TEMPERATURE].
DISPENSE IN A TIGHT, LIGHT-RESISTANT CONTAINER AS DESCRIBED IN THE USP. Dispense with Medication Guide available at www.aurobindousa.com/medication-guides Distributed by: Aurobindo Pharma USA, Inc. 279 Princeton-Hightstown Road East Windsor, NJ 08520 Revised: 01/2022
📋 Description ▾
Lorazepam USP, an antianxiety agent, has the chemical formula, 7-chloro-5-(o-chlorophenyl)-1,3-dihydro-3-hydroxy-2H-1,4-benzodiazepin-2-one: Chemical-Structure It is a nearly white powder almost insoluble in water. Each lorazepam tablet USP, to be taken orally, contains 0.5 mg, 1 mg, or 2 mg of lorazepam USP. The inactive ingredients present are anhydrous lactose, magnesium stearate, microcrystalline cellulose, and polacriline potassium.
💬 Medication Guide ▾
MEDICATION GUIDE LORAZEPAM Tablets, USP CIV What is the most important information I should know about LORAZEPAM? · LORAZEPAM isa benzodiazepine medicine. Taking benzodiazepines with opioid medicines, alcohol, or other central nervous system depressants (including street drugs) can cause severe drowsiness, breathing problems (respiratory depression), coma and death. Getemergencyhelpright away if any of the following happens: shallow or slowedbreathing breathingstops(whichmaylead to the heartstopping) excessivesleepiness(sedation) Do not drive or operate heavy machinery until you know how taking LORAZEPAM with opioids affects you.
Risk of abuse,misuse, and addiction.There is a risk of abuse,misuse,andaddictionwithbenzodiazepinesincludingLORAZEPAM whichcanlead to overdoseandserioussideeffects including comaanddeath. Serioussideeffects including comaanddeathhavehappened in peoplewho have abused or misusedbenzodiazepines,includingLORAZEPAM.Theseserioussideeffectsmayalsoincludedelirium,paranoia,suicidalthoughts or actions,seizures,anddifficultybreathing.Call your healthcareprovider or go to thenearest hospital emergencyroomrightaway if you getany of theseserioussideeffects.
Youcandevelop an addictioneven if you take LORAZEPAM exactly as prescribed by your healthcareprovider. TakeLORAZEPAM exactly as your healthcareproviderprescribed. Do not share your LORAZEPAM withotherpeople.
Keep LORAZEPAM in a safeplaceandaway from children. Physicaldependence and withdrawalreactions.LORAZEPAM cancausephysicaldependenceandwithdrawalreactions. Do not suddenlystoptakingLORAZEPAM.
StoppingLORAZEPAM suddenlycancauseseriousandlife-threateningsideeffects,including,unusualmovements,responses or expressions,seizures,suddenandseveremental or nervoussystemchanges,depression,seeing or hearingthingsthatothersdo not see or hear,anextremeincrease in activity or talking,losingtouchwithreality,andsuicidalthoughts or actions.Callyourhealthcareprovider or go to the nearest hospital emergencyroomrightaway if youget any of thesesymptoms. Somepeoplewhosuddenlystopbenzodiazepines have symptoms that canlast for severalweeks to more than 12 months,includinganxiety,troubleremembering,learning, or concentrating,depression,problemssleeping,feelinglikeinsectsarecrawlingunder your skin,weakness,shaking,muscletwitching,burning or pricklingfeeling in your hands,arms,legs or feet, and ringing in your ears.
Physicaldependence is not the sameas drug addiction.Yourhealthcareprovidercantell you moreabout the differencesbetweenphysicaldependenceand drug addiction. Do not takemore LORAZEPAM than prescribed or takeLORAZEPAM for longerthanprescribed. What is LORAZEPAM?
LORAZEPAM is a prescriptionmedicineused: to treatanxietydisorders for the short-termrelief of the symptoms of anxiety or anxietythatcanhappenwith symptoms of depression LORAZEPAM is a federalcontrolledsubstance(CIV)because it contains Lorazepam thatcan be abused or lead to dependence.KeepLORAZEPAM in a safeplace to preventmisuseandabuse.Selling or givingawayLORAZEPAM may harm others, and is againstthelaw.Tell your healthcareprovider if youhaveabused or beendependent on alcohol,prescriptionmedicines or streetdrugs. It is not known if LORAZEPAM issafeandeffective for use in childrenlessthan 12 years of age.
It is not known if LORAZEPAM issafeandeffective for use for longerthan 4 months. Donot take LORAZEPAM if you: areallergic to Lorazepam, other benzodiazepines, or any of the ingredients in LORAZEPAM. See the end of this MedicationGuidefor a completelist of ingredients in LORAZEPAM.
Beforeyou take LORAZEPAM, tell your healthcare provider about all of your medical conditions, including if you: have or havehaddepression,moodproblems, or suicidalthoughts or behavior have a history of drug or alcoholabuse or addiction have lung disease or breathingproblems(suchasCOPD,sleepapneasyndrome) haveliver or kidneyproblems have or havehadseizures arepregnant or plan to becomepregnant.LORAZEPAM mayharm your unbornbaby.Youand your hea… [Excerpted — this section continues on DailyMed.]
⚠️ Precautions ▾
In patients with depression, a possibility for suicide should be borne in mind; benzodiazepines should not be used in such patients without adequate antidepressant therapy. Lorazepam should be used with caution in patients with compromised respiratory function (e.g., COPD, sleep apnea syndrome). Elderly or debilitated patients may be more susceptible to the sedative effects of l orazepam.
Therefore, these patients should be monitored frequently and have their dosage adjusted carefully according to patient response; the initial dosage should not exceed 2 mg. Paradoxical reactions have been occasionally reported during benzodiazepine use. Such reactions may be more likely to occur in children and the elderly.
Should these occur, use of the drug should be discontinued. The usual precautions for treating patients with impaired renal or hepatic function should be observed. As with all benzodiazepines, the use of l orazepam may worsen hepatic encephalopathy; therefore, l orazepam should be used with caution in patients with severe hepatic insufficiency and/or encephalopathy.
Dosage for patients with severe hepatic insufficiency should be adjusted carefully according to patient response; lower doses may be sufficient in such patients. In patients where gastrointestinal or cardiovascular disorders coexist with anxiety, it should be noted that l orazepam has not been shown to be of significant benefit in treating the gastrointestinal or cardiovascular component. Esophageal dilation occurred in rats treated with l orazepam for more than 1 year at 6 mg/kg/day.
The no- effect dose was 1.25 mg/kg/day (approximately 6 times the maximum human therapeutic dose of 10 mg/day). The effect was reversible only when the treatment was withdrawn within 2 months of first observation of the phenomenon. The clinical significance of this is unknown.
However, use of l orazepam for prolonged periods and in geriatric patients requires caution, and there should be frequent monitoring for symptoms of upper GI disease. Safety and effectiveness of l orazepam in children of less than 12 years have not been established. Information for Patients Advise the patient to read the FDA-approved patient labeling (Medication Guide).
Risks from Concomitant Use with Opioids Advise both patients and caregivers about the risks of potentially fatal respiratory depression and sedation when lorazepam is used with opioids and not to use such drugs concomitantly unless supervised by a health care provider. Advise patients not to drive or operate heavy machinery until the effects of concomitant use with the opioid have been determined (SEE WARNINGS: Risks from Concomitant Use of Opioids and PRECAUTIONS: Drug Interactions). Abuse, Misuse, and Addiction Inform patients that the use of lorazepam even at recommended doses, exposes users to risks of abuse, misuse, and addiction, which can lead to overdose and death, especially when used in combination with other medications (e.g., opioid analgesics), alcohol, and/or illicit substances.
Inform patients about the signs and symptoms of benzodiazepine abuse, misuse, and addiction; to seek medical help if they develop these signs and/or symptoms; and on the proper disposal of unused drug (SEE WARNINGS: Abuse Misuse, and Addiction and DRUG ABUSE AND DEPENDENCE). Withdrawal Reactions Inform patients that the continued use of lorazepam may lead to clinically significant physical dependence and that abrupt discontinuation or rapid dosage reduction of lorazepam may precipitate acute withdrawal reactions, which can be life-threatening.
Inform patients that in some cases, patients taking benzodiazepines have developed a protracted withdrawal syndrome with withdrawal symptoms lasting weeks to more than 12 months. Instruct patients that discontinuation or dosage reduction of lorazepam may require a slow taper (see WARNINGS:Dependence and Withdrawal Reactions and DRUG ABUSE AND DEPENDENCE). Essential Laboratory Tests Some patients on l orazepam have d… [Excerpted — this section continues on DailyMed.]
🔒 Drug Abuse and Dependence ▾
Controlled Substance Lorazepam tablets contains l orazepam, a Schedule IV controlled substance. Abuse Lorazepam is a benzodiazepine and a CNS depressant with a potential for abuse and addiction. Abuse is the intentional, non-therapeutic use of a drug, even once, for its desirable psychological or physiological effects.
Misuse is the intentional use, for therapeutic purposes, of a drug by an individual in a way other than prescribed by a health care provider or for whom it was not prescribed. Drug addiction is a cluster of behavioral, cognitive, and physiological phenomena that may include a strong desire to take the drug, difficulties in controlling drug use (e.g., continuing drug use despite harmful consequences, giving a higher priority to drug use than other activities and obligations), and possible tolerance or physical dependence.
Even taking benzodiazepines as prescribed may put patients at risk for abuse and misuse of their medication. Abuse and misuse of benzodiazepines may lead to addiction. Abuse and misuse of benzodiazepines often (but not always) involve the use of doses greater than the maximum recommended dosage and commonly involve concomitant use of other medications, alcohol, and/or illicit substances, which is associated with an increased frequency of serious adverse outcomes, including respiratory depression, overdose, or death.
Benzodiazepines are often sought by individuals who abuse drugs and other substances, and by individuals with addictive disorders (SEE WARNINGS: Abuse, Misuse, and Addiction). The following adverse reactions have occurred with benzodiazepine abuse and/or misuse: abdominal pain, amnesia, anorexia, anxiety, aggression, ataxia, blurred vision, confusion, depression, disinhibition, disorientation, dizziness, euphoria, impaired concentration and memory, indigestion, irritability, muscle pain, slurred speech, tremors, and vertigo.
The following severe adverse reactions have occurred with benzodiazepine abuse and/or misuse: delirium, paranoia, suicidal ideation and behavior, seizures, coma, breathing difficulty, and death. Death is more often associated with polysubstance use (especially benzodiazepines with other CNS depressants such as opioids and alcohol). Dependence Physical Dependence Lorazepam may produce physical dependence from continued therapy.
Physical dependence is a state that develops as a result of physiological adaptation in response to repeated drug use, manifested by withdrawal signs and symptoms after abrupt discontinuation or a significant dose reduction of a drug. Abrupt discontinuation or rapid dosage reduction of benzodiazepines or administration of flumazenil, a benzodiazepine antagonist, may precipitate acute withdrawal reactions, including seizures, which can be life-threatening. Patients at an increased risk of withdrawal adverse reactions after benzodiazepine discontinuation or rapid dosage reduction include those who take higher dosages (i.e., higher and/or more frequent doses) and those who have had longer durations of use (SEE WARNINGS: Dependence and Withdrawal Reactions).
To reduce the risk of withdrawal reactions, use a gradual taper to discontinue lorazepam or reduce the dosage (see DOSAGE AND ADMINISTRATION: Discontinuation or Dosage Reduction of Lorazepam and WARNINGS). Acute Withdrawal Signs and Symptoms Acute withdrawal signs and symptoms associated with benzodiazepines have included abnormal involuntary movements, anxiety, blurred vision, depersonalization, depression, derealization, dizziness, fatigue, gastrointestinal adverse reactions (e.g., nausea, vomiting, diarrhea, weight loss, decreased appetite), headache, hyperacusis, hypertension, irritability, insomnia, memory impairment,muscle pain and stiffness, panic attacks, photophobia, restlessness, tachycardia, and tremor.
More severe acute withdrawal signs and symptoms, including life-threatening reactions, have included catatonia, convulsions, delirium tremens, depression, hallucinations, mania, p… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
hjhgjghj
72189-351-30
72189-351-60
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |