
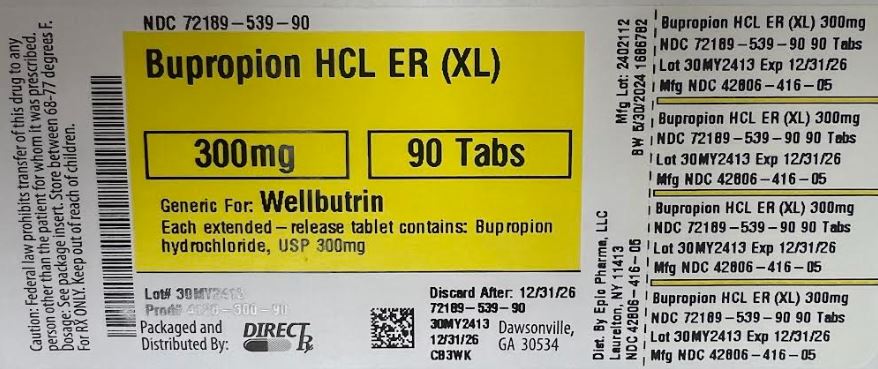
Bupropion HCL ER (XL) 300 mg Tablet, Extended Release, 90-count — NDC 72189-539-90 (Billing 72189-0539-90)
This is a package of 90 tablets of Bupropion HCL ER (XL) 300 mg Tablet, Extended Release from Direct_RX, marketed since Mar 2024 and currently FDA-listed.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 053007
- GCN: 20318
- HICL (First Databank): 001653
- AHFS class code: 28:16.04.92
- RxCUI (RxNorm): 993557
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Aminoketone class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- Bupropion treats major depressive disorder. Some extended-release products, like Aplenzin and bupropion XL, can also prevent seasonal affective disorder, the depression that return...
- Take it by mouth exactly as prescribed. XL tablets are taken once in the morning, with or without food, and must be swallowed whole. Your doctor will usually raise the dose gradual...
- The most common ones are dry mouth, nausea, trouble sleeping, dizziness, headache, anxiety and tremor. Call your doctor right away if you have a seizure, new suicidal thoughts, sev...
- It's best to limit or avoid alcohol. Rare neuropsychiatric events and lower alcohol tolerance have been reported. Never suddenly stop heavy drinking while on bupropion without talk...
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.3192 | $28.73 / 90 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 72189-0539-30 72189-539-30 Main listing | 30 TABLET, EXTENDED RELEASE in 1 BOTTLE | 2024-03-01 | — | Active |
| 72189-0539-90 You're viewing this | 90 TABLET, EXTENDED RELEASE in 1 BOTTLE | 2024-03-01 | — | Active |
You're viewing the largest of 2 pack sizes for this product.
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 72189-0539-30?
What NDC number is used to bill for this package of Bupropion HCL ER (XL) 300 mg Tablet, Extended Release?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Bupropion Hydrochloride XL 300 mg 00904-7469-04 | Major | 1 tablet | $0.100 | AB3 | Availability likely | — |
| bupropion hydrochloride 300 mg 16571-0863-03 | Rising | 30 tablets | $0.100 | AB3 | Availability likely | — |
| Bupropion Hydrochloride 300 mg 16729-0444-10 | Accord | 30 tablets | $0.100 | AB3 | Availability likely | — |
| Bupropion Hydrochloride 300 mg 31722-0488-05 | Camber | 500 tablets | $0.100 | AB3 | Availability likely | — |
| Bupropion Hydrochloride XL 300 mg 42806-0416-05 | Epic | 500 tablets | $0.100 | AB3 | Availability likely | — |
| Bupropion Hydrochloride (XL) 300 mg 43598-0656-05 | Dr | 500 tablets | $0.100 | AB3 | Availability likely | — |
| Bupropion Hydrochloride 300 mg 45963-0142-05 | Actavis | 500 tablets | $0.100 | AB3 | Availability likely | — |
| Bupropion Hydrochloride (XL) 300 mg 50228-0145-05 | ScieGen | 500 tablets | $0.100 | AB3 | Availability likely | — |
| Bupropion Hydrochloride 300 mg 50268-0134-13 | AvPAK | 1 tablet | $0.100 | AB3 | Availability likely | — |
| Bupropion Hydrochloride 300 mg 60687-0793-21 | American | 1 tablet | $0.100 | AB3 | Availability likely | — |
| Bupropion hydrochloride 300 mg 68001-0614-03 | BluePoint | 500 tablets | $0.100 | AB3 | Availability likely | — |
| Bupropion Hydrochloride XL 300 mg 68180-0320-02 | Lupin | 500 tablets | $0.100 | AB3 | Availability likely | — |
| Bupropion Hydrochloride 300 mg 69097-0072-12 | Cipla | 500 tablets | $0.100 | AB3 | Availability likely | — |
| Bupropion Hydrochloride (XL) 300 mg 69097-0876-02 | CIPLA | 30 tablets | $0.100 | — | Availability likely | — |
| Bupropion Hydrochloride XL 300 mg 69367-0289-05 | Westminster | 500 tablets | $0.100 | AB3 | Discontinued | — |
| Bupropion hydrochloride 300 mg 70010-0785-03 | Granules | 30 tablets | $0.100 | AB3 | Availability likely | — |
| Bupropion Hydrochloride XL 300 mg 82009-0052-05 | Quallent | 500 tablets | $0.100 | AB3 | Availability likely | — |
| Bupropion Hydrochloride (XL) 300 mg 83301-0025-01 | Mullan | 30 tablets | $0.100 | AB3 | Availability likely | — |
| Bupropion Hydrochloride XL 300 mg 42806-0349-05 | Epic | 500 tablets | $0.101 | AB3 | Availability likely | — |
| Bupropion hydrochloride 300 mg 63304-0724-05 | Sun | 500 tablets | $0.103 | — | Discontinued | — |
| Bupropion Hydrochloride 300 mg 68001-0520-03 | BluePoint | 500 tablets | $0.107 | AB3 | FDA listed | — |
| Bupropion Hydrochloride (XL) 300 mg 24979-0102-02 | Upsher-Smith | 500 tablets | $0.112 | — | Discontinued | — |
| Bupropion Hydrochloride XL 300 mg 70436-0011-02 | Slate | 500 tablets | $0.115 | AB3 | Availability likely | — |
| Bupropion hydrochloride (XL) 300 mg 00527-2430-32 | Lannett | 30 tablets | $0.144 | AB3 | FDA listed | — |
| Wellbutrin Xl 300 mg 00187-0731-07 | Bausch | 7 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride 300 mg 00615-8505-05 | NCS | 15 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride 300 mg 50090-4749-00 | A-S | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride 300 mg 50090-5245-00 | A-S | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride (XL) 300 mg 50090-5334-00 | A-S | 30 tablets | — | — | FDA listed | — |
| Bupropion Hydrochloride XL 300 mg 50090-6961-00 | A-S | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride XL 300 mg 50090-6962-00 | A-S | 90 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride (XL) 300 mg 50090-7334-00 | A-S | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride (XL) 300 mg 50090-7335-00 | A-S | 90 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride XL 300 mg 50090-7602-00 | A-S | 90 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride 300 mg 55700-0820-30 | Quality | 30 tablets | — | AB3 | Discontinued | — |
| Bupropion Hydrochloride (Xl) 300 mg 62135-0876-30 | Chartwell | 30 tablets | — | AB3 | FDA listed | — |
| bupropion 300 mg 63187-0521-30 | Proficient | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride 300 mg 63187-0819-30 | Proficient | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride (XL) 300 mg 63629-8475-01 | Bryant | 500 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride (XL) 300 mg 63629-8476-01 | Bryant | 30 tablets | — | AB3 | FDA listed | — |
| bupropion 300 mg 65841-0780-05 | Zydus | 500 tablets | — | AB3 | FDA listed | — |
| Bupropion hydrochloride 300 mg 67046-1497-03 | Coupler | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion hydrochloride 300 mg 67046-1648-03 | Coupler | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride XL 300 mg 68071-3928-09 | NuCare | 90 tablets | — | AB3 | FDA listed | — |
| bupropion 300 mg 68382-0354-05 | Zydus | 500 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride 300 mg 68788-7992-01 | Preferred | 100 tablets | — | AB3 | FDA listed | — |
| Bupropion hydrochloride 300 mg 68788-8815-01 | Preferred | 100 tablets | — | AB3 | FDA listed | — |
| Bupropion hydrochloride (XL) 300 mg 69680-0158-30 | Vitruvias | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride (XL) 300 mg 70518-3790-00 | REMEDYREPACK | 30 tablets | — | AB3 | Discontinued | — |
| Bupropion Hydrochloride XL 300 mg 70518-4014-00 | REMEDYREPACK | 90 tablets | — | AB3 | FDA listed | — |
| bupropion hydrochloride 300 mg 70518-4343-00 | REMEDYREPACK | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion hydrochloride 300 mg 70518-4415-00 | REMEDYREPACK | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride XL 300 mg 70518-4446-00 | REMEDYREPACK | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride XL 300 mg 70518-4551-00 | REMEDYREPACK | 90 tablets | — | AB3 | Discontinued | — |
| Bupropion Hydrochloride 300 mg 71205-0465-30 | Proficient | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride (XL) 300 mg 71205-0968-30 | Proficient | 30 tablets | — | — | FDA listed | — |
| Bupropion Hydrochloride (XL) 300 mg 71335-1114-01 | Bryant | 30 tablets | — | — | Discontinued | — |
| Bupropion Hydrochloride 300 mg 71335-1214-01 | Bryant | 30 tablets | — | AB3 | Discontinued | — |
| Bupropion Hydrochloride (XL) 300 mg 71335-2312-01 | Bryant | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion hydrochloride 300 mg 71335-2499-01 | Bryant | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride (XL) 300 mg 72162-1278-09 | Bryant | 90 tablets | — | — | Discontinued | — |
| Bupropion Hydrochloride (XL) 300 mg 72162-1527-03 | Bryant | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride 300 mg 72189-0124-30 | DIRECT | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion HCL ER (XL) 300 mgthis 72189-0539-90 | Direct_RX | 90 tablets | — | AB3 | FDA listed | — |
| buPropion Hydrochloride XL 300 mg 72516-0036-03 | Oryza | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride (XL) 300 mg 72789-0112-90 | PD-Rx | 90 tablets | — | — | Discontinued | — |
| Bupropion Hydrochloride (XL) 300 mg 76282-0481-05 | Exelan | 500 tablets | — | — | FDA listed | — |
| Bupropion Hydrochloride 300 mg 76420-0812-01 | Asclemed | 100 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride (XL) 300 mg 77771-0145-05 | RADHA | 500 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride XL 300 mg 80425-0468-01 | Advanced | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride (XL) 300 mg 80425-0539-01 | Advanced | 30 tablets | — | AB3 | FDA listed | — |
| Bupropion Hydrochloride (XL) 300 mg 82804-0013-30 | Proficient | 30 tablets | — | — | FDA listed | — |
| Bupropion Hydrochloride 300 mg 85534-0006-01 | HAWAII | 100 tablets | — | AB3 | FDA listed | — |
| Bupropion hydrochloride 300 mg 87441-0014-01 | Unit | 30 tablets | — | AB3 | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: SUICIDAL THOUGHTS AND BEHAVIORS SUICIDALITY AND ANTIDEPRESSANT DRUGS Antidepressants increased the risk of suicidal thoughts and behavior in children, adolescents, and young adults in short-term trials. These trials did not show an increase in the risk of suicidal thoughts and behavior with antidepressant use in subjects aged 65 and older [see Warnings and Precautions ( 5.1)] . In patients of all ages who are started on antidepressant therapy, monitor closely for worsening, and for emergence of suicidal thoughts and behaviors.
Advise families and caregivers of the need for close observation and communication with the prescriber [see Warnings and Precautions ( 5.1)] .
🎯 Indications and Usage ▾
1.1Major Depressive Disorder (MDD) Bupropion hydrochloride extended-release tablets (XL) are indicated for the treatment of major depressive disorder (MDD), as defined by the Diagnostic and Statistical Manual (DSM). The efficacy of the immediate-release formulation of bupropion was established in two 4-week controlled inpatient trials and one 6-week controlled outpatient trial of adult patients with MDD. The efficacy of the sustained-release formulation of bupropion in the maintenance treatment of MDD was established in a long-term (up to 44 weeks), placebo-controlled trial in patients who had responded to bupropion in an 8-week study of acute treatment [see CLINICAL STUDIES (14.1)].
1.2Seasonal Affective Disorde (SAD) Bupropion hydrochloride extended-release tablets (XL) are indicated for the prevention of seasonal major depressive episodes in patients with a diagnosis of seasonal affective disorder (SAD). The efficacy of bupropion hydrochloride extended-release tablets (XL) in the prevention of seasonal major depressive episodes was established in 3 placebo-controlled trials in adult outpatients with a history of MDD with an autumn-winter seasonal pattern as defined in the DSM [see CLINICAL STUDIES (14.2)].
⏱️ Dosage and Administration ▾
2.1General Instructions for Use To minimize the risk of seizure, increase the dose gradually [see WARNINGS AND PRECAUTIONS (5.3)]. Bupropion hydrochloride extended-release tablets (XL) should be swallowed whole and not crushed, divided, or chewed. Bupropion hydrochloride extended-release tablets (XL) should be administered in the morning and may be taken with or without food.
2.2Dosage for Major Depressive Disorder (MDD) The recommended starting dose for MDD is 150 mg once daily in the morning. After 4 days of dosing, the dose may be increased to the target dose of 300 mg once daily in the morning. It is generally agreed that acute episodes of depression require several months or longer of antidepressant treatment beyond the response in the acute episode.
It is unknown whether the bupropion hydrochloride extended-release tablets (XL) dose needed for maintenance treatment is identical to the dose that provided an initial response. Periodically reassess the need for maintenance treatment and the appropriate dose for such treatment.
2.3Dosage for Seasonal Affective Disorder (SAD) The recommended starting dose for SAD is 150 mg once daily. After 7 days of dosing, the dose may be increased to the target dose of 300 mg once daily in the morning. Doses above 300 mg of bupropion hydrochloride extended-release were not assessed in the SAD trials.
For the prevention of seasonal MDD episodes associated with SAD, initiate bupropion hydrochloride extended-release tablets (XL) in the autumn, prior to the onset of depressive symptoms. Continue treatment through the winter season. Taper and discontinue bupropion hydrochloride extended-release tablets (XL) in early spring.
For patients treated with 300 mg per day, decrease the dose to 150 mg once daily before discontinuing bupropion hydrochloride extended-release tablets (XL). Individualize the timing of initiation, and duration of treatment should be individualized, based on the patient’s historical pattern of seasonal MDD episodes.
2.4Switching Patients from WELLBUTRIN Tablets or from WELLBUTRIN SR Sustained-Release Tablets When switching patients from WELLBUTRIN Tablets to bupropion hydrochloride extended-release tablets (XL) or from WELLBUTRIN SR (bupropion hydrochloride extended-release tablets (SR)) to bupropion hydrochloride extended-release tablets (XL), give the same total daily dose when possible.
2.5To Discontinue Bupropion Hydrochloride Extended-Release Tablets (XL), Taper the Dose When discontinuing treatment in patients treated with bupropion hydrochloride extended-release tablets (XL) 300 mg once daily, decrease the dose to 150 mg once daily prior to discontinuation.
2.6Dosage Adjustment in Patients with Hepatic Impairment In patients with moderate to severe hepatic impairment (Child-Pugh score: 7 to 15), the maximum dose is 150 mg every other day. In patients with mild hepatic impairment (Child-Pugh score: 5 to 6), consider reducing the dose and/or frequency of dosing [see USE IN SPECIFIC POPULATIONS (8.7) and CLINICAL PHARMACOLOGY (12.3)].
2.7Dose Adjustment in Patients with Renal Impairment Consider reducing the dose and/or frequency of bupropion hydrochloride extended-release tablets (XL) in patients with renal impairment (glomerular filtration rate less than 90 mL/min) [see USE IN SPECIFIC POPULATIONS (8.6) and CLINICAL PHARMACOLOGY (12.3)].
2.8Switching a Patient to or from a Monoamine Oxidase Inhibitor (MAOI) Antidepressant At least 14 days should elapse between discontinuation of an MAOI intended to treat depression and initiation of therapy with bupropion hydrochloride extended-release tablets (XL). Conversely, at least 14 days should be allowed after stopping bupropion hydrochloride extended-release tablets (XL) before starting an MAOI antidepressant [see CONTRAINDICATIONS (4) and DRUG INTERACTIONS (7.6)].
2.9Use of Bupropion Hydrochloride Extended-Release Tablets (XL) with Reversible MAOIs such as Linezolid or Methylene Blue Do not start bupropion hydrochlori… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
Bupropion Hydrochloride Extended-Release Tablets USP (XL), 150 mg of bupropion hydrochloride, are white to pale yellow, round biconvex tablet with imprinting “YH 102” on one side and plain on the other side. Bupropion Hydrochloride Extended-Release Tablets USP (XL), 300 mg of bupropion hydrochloride, are white to pale yellow, round biconvex tablet with imprinting “YH 101” on one side and plain on the other side.
⛔ Contraindications ▾
Bupropion hydrochloride extended-release tablets (XL) are contraindicated in patients with seizure disorder. Bupropion hydrochloride extended-release tablets (XL) are contraindicated in patients with a current or prior diagnosis of bulimia or anorexia nervosa as a higher incidence of seizures was observed in such patients treated with bupropion hydrochloride extended-release tablets (XL) [see WARNINGS AND PRECAUTIONS (5.3)]. Bupropion hydrochloride extended-release tablets (XL) are contraindicated in patients undergoing abrupt discontinuation of alcohol, benzodiazepines, barbiturates, and antiepileptic drugs [see WARNINGS AND PRECAUTIONS (5.3) and DRUG INTERACTIONS (7.3)].
The use of MAOIs (intended to treat psychiatric disorders) concomitantly with bupropion hydrochloride extended-release tablets (XL) or within 14 days of discontinuing treatment with bupropion hydrochloride extended-release tablets (XL) is contraindicated. There is an increased risk of hypertensive reactions when bupropion hydrochloride extended-release tablets (XL) is used concomitantly with MAOIs. The use of bupropion hydrochloride extended-release tablets (XL) within 14 days of discontinuing treatment with an MAOI is also contraindicated.
Starting bupropion hydrochloride extended-release tablets (XL) in a patient treated with reversible MAOIs such as linezolid or intravenous methylene blue is contraindicated [see DOSAGE AND ADMINISTRATION (2.9), WARNINGS AND PRECAUTIONS (5.4) and DRUG INTERACTIONS (7.6)]. Bupropion hydrochloride extended-release tablets (XL) are contraindicated in patients with known hypersensitivity to bupropion or other ingredients of bupropion hydrochloride extended-release tablets (XL). Anaphylactoid/anaphylactic reactions and Stevens-Johnson syndrome have been reported [see WARNINGS AND PRECAUTIONS (5.8)].
⚠️ Warnings and Cautions ▾
5.1Suicidal Thoughts and Behaviors in Children, Adolescents, and Young Adults Patients with major depressive disorder (MDD), both adult and pediatric, may experience worsening of their depression and/or the emergence of suicidal ideation and behavior (suicidality) or unusual changes in behavior, whether or not they are taking antidepressant medications, and this risk may persist until significant remission occurs. Suicide is a known risk of depression and certain other psychiatric disorders, and these disorders themselves are the strongest predictors of suicide.
There has been a long-standing concern that antidepressants may have a role in inducing worsening of depression and the emergence of suicidality in certain patients during the early phases of treatment. Pooled analyses of short-term placebo-controlled trials of antidepressant drugs (Selective Serotonin Reuptake Inhibitors [SSRIs] and others) show that these drugs increase the risk of suicidal thinking and behavior (suicidality) in children, adolescents, and young adults (ages 18 to 24) with major depressive disorder (MDD) and other psychiatric disorders.
Short-term studies did not show an increase in the risk of suicidality with antidepressants compared to placebo in adults beyond age 24; there was a reduction with antidepressants compared to placebo in adults aged 65 and older. The pooled analyses of placebo-controlled trials in children and adolescents with MDD, obsessive compulsive disorder (OCD), or other psychiatric disorders included a total of 24 short-term trials of 9 antidepressant drugs in over 4,400 patients. The pooled analyses of placebo-controlled trials in adults with MDD or other psychiatric disorders included a total of 295 short-term trials (median duration of 2 months) of 11 antidepressant drugs in over 77,000 patients.
There was considerable variation in risk of suicidality among drugs, but a tendency toward an increase in the younger patients for almost all drugs studied. There were differences in absolute risk of suicidality across the different indications, with the highest incidence in MDD. The risk differences (drug vs. placebo), however, were relatively stable within age strata and across indications.
These risk differences (drug-placebo difference in the number of cases of suicidality per 1,000 patients treated) are provided in Table 1. Table 1: Risk Differences in the Number of Suicidality Cases by Age Group in the Pooled Placebo-Controlled Trials of Antidepressants in Pediatric and Adult Patients Age Range Drug-Placebo Difference in Number of Cases of Suicidality per 1,000 Patients Treated Increases Compared to Placebo <18 years 14 additional cases 18-24 years 5 additional cases Decreases Compared to Placebo 25-64 years 1 fewer case ≥65 years 6 fewer cases No suicides occurred in any of the pediatric trials.
There were suicides in the adult trials, but the number was not sufficient to reach any conclusion about drug effect on suicide. It is unknown whether the suicidality risk extends to longer-term use, i.e., beyond several months. However, there is substantial evidence from placebo-controlled maintenance trials in adults with depression that the use of antidepressants can delay the recurrence of depression.
All patients being treated with antidepressants for any indication should be monitored appropriately and observed closely for clinical worsening, suicidality, and unusual changes in behavior, especially during the initial few months of a course of drug therapy, or at times of dose changes, either increases or decreases [see BOXED WARNING and USE IN SPECIFIC POPULATIONS (8.4)]. The following symptoms, anxiety, agitation, panic attacks, insomnia, irritability, hostility, aggressiveness, impulsivity, akathisia (psychomotor restlessness), hypomania, and mania, have been reported in adult and pediatric patients being treated with antidepressants for major depressive disorder as well as for other indications, both psychiatric and nonpsychia… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
The following adverse reactions are discussed in greater detail in other sections of the labeling: Suicidal thoughts and behaviors in children, adolescents, and young adults [see WARNINGS AND PRECAUTIONS (5.1)] Neuropsychiatric adverse events and suicide risk in smoking cessation treatment [see WARNINGS AND PRECAUTIONS (5.2)] Seizure [see WARNINGS AND PRECAUTIONS (5.3)] Hypertension [see WARNINGS AND PRECAUTIONS (5.4)] Activation of mania or hypomania [see WARNINGS AND PRECAUTIONS (5.5)] Psychosis and other neuropsychiatric events [see WARNINGS AND PRECAUTIONS (5.6)] Angle-Closure Glaucoma [see WARNINGS AND PRECAUTIONS (5.7)] Hypersensitivity reactions [see WARNINGS AND PRECAUTIONS (5.8)]
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Commonly Observed Adverse Reactions in Controlled Clinical Trials of Sustained-Release Bupropion Hydrochloride Adverse reactions that occurred in at least 5% of patients treated with bupropion HCl sustained-release (300 mg and 400 mg per day) and at a rate at least twice the placebo rate are listed below.
300 mg/day of bupropion HCl sustained-release: anorexia, dry mouth, rash, sweating, tinnitus, and tremor. 400 mg/day of bupropion HCl sustained-release: abdominal pain, agitation, anxiety, dizziness, dry mouth, insomnia, myalgia, nausea, palpitation, pharyngitis, sweating, tinnitus, and urinary frequency. Bupropion hydrochloride extended-release tablets (XL) have been demonstrated to have similar bioavailability both to the immediate-release and sustained-release formulations of bupropion.
The information included under this subsection and under subsection 6.2 is based primarily on data from controlled clinical trials with the sustained-release and extended-release formulations of bupropion hydrochloride. Major Depressive Disorder Adverse Reactions Leading to Discontinuation of Treatment with Bupropion HCl Immediate-Release, Bupropion HCl Sustained-Release, and Bupropion HCl Extended-Release in Major Depressive Disorder Trials. In placebo-controlled clinical trials with bupropion HCl sustained-release, 4%, 9%, and 11% of the placebo, 300 mg/day and 400 mg/day groups, respectively, discontinued treatment because of adverse reactions.
The specific adverse reactions leading to discontinuation in at least 1% of the 300 mg/day or 400 mg/day groups and at a rate at least twice the placebo rate are listed in Table 2. Table 2: Treatment Discontinuation Due to Adverse Reactions in Placebo-Controlled Trials in MDD Adverse Reaction Term Placebo (n=385) Bupropion HCl Sustained- Release 300 mg/day (n=376) Bupropion HCl Sustained- Release 400 mg/day (n=114) Rash 0.0% 2.4% 0.9% Nausea 0.3% 0.8% 1.8% Agitation 0.3% 0.3% 1.8% Migraine 0.3% 0.0% 1.8% In clinical trials with bupropion HCl immediate-release, 10% of patients and volunteers discontinued due to an adverse reaction.
Reactions resulting in discontinuation (in addition to those listed above for the sustained-release formulation) included vomiting, seizures, and sleep disturbances. Adverse Reactions Occurring at an Incidence of >1% in Patients Treated with Bupropion HCl Immediate-Release or Bupropion HCl Sustained-Release in MDD Table 3 summarizes the adverse reactions that occurred in placebo-controlled trials in patients treated with bupropion HCl sustained-release 300 mg/day and 400 mg/day. These include reactions that occurred in either the 300 mg or 400 mg group at an incidence of 1% or more and were more frequent than in the placebo group.
Table 3: Adverse Reactions in Placebo-Controlled Trials in Patients with MDD Body System/Adverse Reaction Placebo (n=385) Bupropion HCl Sustained-Release 300 mg/day (n=376) Bupropion HCl Sustained-Release 400 mg/day (n=114) Body (General) Headache 23% 26% 25% Infection 6… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7.1Potential for Other Drugs to Affect Bupropion Hydrochloride Extended-Release Tablets (XL) Bupropion is primarily metabolized to hydroxybupropion by CYP2B6. Therefore, the potential exists for drug interactions between bupropion hydrochloride extended-release tablets (XL) and drugs that are inhibitors or inducers of CYP2B6. Inhibitors of CYP2B6 Ticlopidine and Clopidogrel: Concomitant treatment with these drugs can increase bupropion exposures but decrease hydroxybupropion exposure.
Based on clinical response, dosage adjustment of bupropion hydrochloride extended-release tablets (XL) may be necessary when coadministered with CYP2B6 inhibitors (e.g., ticlopidine or clopidogrel) [see CLINICAL PHARMACOLOGY (12.3)]. Inducers of CYP2B6 Ritonavir, Lopinavir, and Efavirenz: Concomitant treatment with these drugs can decrease bupropion and hydroxybupropion exposure. Dosage increase of bupropion hydrochloride extended-release tablets (XL) may be necessary when coadministered with ritonavir, lopinavir, or efavirenz but should not exceed the maximum recommended dose [see CLINICAL PHARMACOLOGY (12.3)].
Carbamazepine, Phenobarbital, Phenytoin: While not systemically studied, these drugs may induce metabolism of bupropion and may decrease bupropion exposure [see CLINICAL PHARMACOLOGY (12.3)] . If bupropion is used concomitantly with a CYP inducer, it may be necessary to increase the dose of bupropion, but the maximum recommended dose should not be exceeded.
7.2Potential for Bupropion Hydrochloride Extended-Release Tablets (XL) to Affect Other Drugs Drugs Metabolized by CYP2D6 Bupropion and its metabolites (erythrohydrobupropion, threohydrobupropion, hydroxybupropion) are CYP2D6 inhibitors. Therefore, coadministration of bupropion hydrochloride extended-release tablets (XL) with drugs that are metabolized by CYP2D6 can increase the exposures of drugs that are substrates of CYP2D6. Such drugs include certain antidepressants (e.g., venlafaxine, nortriptyline, imipramine, desipramine, paroxetine, fluoxetine, and sertraline), antipsychotics (e.g., haloperidol, risperidone, and thioridazine), beta-blockers (e.g., metoprolol), and Type 1C antiarrhythmics (e.g., propafenone, and flecainide).
When used concomitantly with bupropion hydrochloride extended-release tablets (XL), it may be necessary to decrease the dose of these CYP2D6 substrates, particularly for drugs with a narrow therapeutic index. Drugs that require metabolic activation by CYP2D6 to be effective (e.g., tamoxifen), theoretically could have reduced efficacy when administered concomitantly with inhibitors of CYP2D6 such as bupropion. Patients treated concomitantly with bupropion hydrochloride extended-release tablets (XL) and such drugs may require increased doses of the drug [see CLINICAL PHARMACOLOGY (12.3)].
7.3Drugs That Lower Seizure Threshold Use extreme caution when coadministering bupropion hydrochloride extended-release tablets (XL) with other drugs that lower the seizure threshold (e.g., other bupropion products, antipsychotics, antidepressants, theophylline, or systemic corticosteroids). Use low initial doses of bupropion hydrochloride extended-release tablets (XL) and increase the dose gradually [see WARNINGS AND PRECAUTIONS (5.3)].
7.4Dopaminergic Drugs (Levodopa and Amantadine) Bupropion, levodopa, and amantadine have dopamine agonist effects. CNS toxicity has been reported when bupropion was coadministered with levodopa or amantadine. Adverse reactions have included restlessness, agitation, tremor, ataxia, gait disturbance, vertigo, and dizziness.
It is presumed that the toxicity results from cumulative dopamine agonist effects. Use caution when administering bupropion hydrochloride extended-release tablets (XL) concomitantly with these drugs.
7.5Use with Alcohol In postmarketing experience, there have been rare reports of adverse neuropsychiatric events or reduced alcohol tolerance in patients who were drinking alcohol during treatment with bupropion hydrochlorid… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to antidepressants during pregnancy. Healthcare providers are encouraged to register patients by calling the National Pregnancy Registry for Antidepressants at 1-844-405-6185 or visiting online at https://womensmentalhealth.org/clinical-and-research-programs/pregnancyregistry/antidepressants/. Risk Summary Data from epidemiological studies of pregnant women exposed to bupropion in the first trimester have not identified an increased risk of congenital malformations overall ( see Data).
There are risks to the mother associated with untreated depression ( see Clinical Considerations). When bupropion was administered to pregnant rats during organogenesis, there was no evidence of fetal malformations at doses up to approximately 10 times the maximum recommended human dose (MRHD) of 450 mg/day. When given to pregnant rabbits during organogenesis, non-dose-related increases in incidence of fetal malformations and skeletal variations were observed at doses approximately equal to the MRHD and greater.
Decreased fetal weights were seen at doses twice the MRHD and greater ( see Animal Data). The estimated background risk for major birth defects and miscarriage are unknown for the indicated population. All pregnancies have a background rate of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Disease-associated maternal and/or embryo/fetal risk A prospective, longitudinal study followed 201 pregnant women with a history of major depressive disorder who were euthymic and taking antidepressants during pregnancy at the beginning of pregnancy. The women who discontinued antidepressants during pregnancy were more likely to experience a relapse of major depression than women who continued antidepressants.
Consider the risks to the mother of untreated depression and potential effects on the fetus when discontinuing or changing treatment with antidepressant medications during pregnancy and postpartum. Data Human Data Data from the international bupropion Pregnancy Registry (675 first trimester exposures) and a retrospective cohort study using the United Healthcare database (1,213 first trimester exposures) did not show an increased risk for malformations overall. The Registry was not designed or powered to evaluate specific defects but suggested a possible increase in cardiac malformations.
No increased risk for cardiovascular malformations overall has been observed after bupropion exposure during the first trimester. The prospectively observed rate of cardiovascular malformations in pregnancies with exposure to bupropion in the first trimester from the international Pregnancy Registry was 1.3% (9 cardiovascular malformations/675 first-trimester maternal bupropion exposures), which is similar to the background rate of cardiovascular malformations (approximately 1%). Data from the United Healthcare database, which has a limited number of exposed cases with cardiovascular malformations, and a case-controlled study (6,853 infants with cardiovascular malformations and 5,753 with non- cardiovascular malformations) from the National Birth Defects Prevention Study (NBDPS) did not show an increased risk for cardiovascular malformations overall after bupropion exposure during the first trimester.
Study findings on bupropion exposure during the first trimester and risk left ventricular outflow tract obstruction (LVOTO) are inconsistent and do not allow conclusions regarding possible association. The United Healthcare database lacked sufficient power to evaluate this association; the NBDPS found increased risk for LVOTO (n=10; adjusted odds ratio (OR)=2.6; 95% CI: 1.2, 5.7), and the Slone Epidemiology case control study did not fi… [Excerpted — this section continues on DailyMed.]
🆘 Overdosage ▾
10.1Human Overdose Experience Overdoses of up to 30 grams or more of bupropion have been reported. Seizure was reported in approximately one third of all cases. Other serious reactions reported with overdoses of bupropion alone included hallucinations, loss of consciousness, mental status changes, sinus tachycardia, ECG changes such as conduction disturbances or arrhythmias, clonus, myoclonus, and hyperreflexia.
Fever, muscle rigidity, rhabdomyolysis, hypotension, stupor, coma, and respiratory failure have been reported mainly when bupropion was part of multiple drug overdoses. Although most patients recovered without sequelae, deaths associated with overdoses of bupropion alone have been reported in patients ingesting large doses of the drug. Multiple uncontrolled seizures, bradycardia, cardiac failure, and cardiac arrest prior to death were reported in these patients.
10.2Overdosage Management Consult a Certified Poison Control Center for up-to-date guidance and advice. Call 1-800-222-1222 or refer to www.poison.org. There are no known antidotes for bupropion. In case of an overdose, provide supportive care, including close medical supervision and monitoring. Consider the possibility of multiple drug overdose.
🧬 Clinical Pharmacology ▾
12.1Mechanism of Action The mechanism of action of bupropion is unknown, as is the case with other antidepressants. However, it is presumed that this action is mediated by noradrenergic and/or dopaminergic mechanisms. Bupropion is a relatively weak inhibitor of the neuronal uptake of norepinephrine and dopamine and does not inhibit monoamine oxidase or the reuptake of serotonin.
12.3Pharmacokinetics Bupropion is a racemic mixture. The pharmacologic activity and pharmacokinetics of the individual enantiomers have not been studied. Following chronic dosing, the mean steady-state plasma concentration of bupropion was reached within 8 days.
The mean elimination half-life (±SD) of bupropion is 21 (±9) hours. In a study comparing 14-day dosing with bupropion hydrochloride extended-release tablets (XL), 300 mg once-daily to the immediate-release formulation of bupropion at 100 mg 3 times daily, equivalence was demonstrated for peak plasma concentration and area under the curve for bupropion and the three metabolites (hydroxybupropion, threohydrobupropion, and erythrohydrobupropion). Additionally, in a study comparing 14-day dosing with bupropion hydrochloride extended-release tablets (XL) 300 mg once daily to the sustained-release formulation of bupropion at 150 mg 2 times daily, equivalence was demonstrated for peak plasma concentration and area under the curve for bupropion and the three metabolites.
Absorption Following single oral administration of bupropion hydrochloride extended-release tablets (XL) to healthy volunteers, the median time to peak plasma concentrations for bupropion was approximately 5 hours. The presence of food did not affect the peak concentration or area under the curve of bupropion. Distribution In vitro tests show that bupropion is 84% bound to human plasma proteins at concentrations up to 200 mcg/mL.
The extent of protein binding of the hydroxybupropion metabolite is similar to that for bupropion, whereas the extent of protein binding of the threohydrobupropion metabolite is about half that of bupropion. Metabolism Bupropion is extensively metabolized in humans. Three metabolites are active: hydroxybupropion, which is formed via hydroxylation of the tert-butyl group of bupropion, and the amino-alcohol isomers threohydrobupropion and erythrohydrobupropion, which are formed via reduction of the carbonyl group.
In vitro findings suggest that CYP2B6 is the principal isoenzyme involved in the formation of hydroxybupropion, while cytochrome P450 enzymes are not involved in the formation of threohydrobupropion. Oxidation of the bupropion side chain results in the formation of a glycine conjugate of meta-chlorobenzoic acid, which is then excreted as the major urinary metabolite. The potency and toxicity of the metabolites relative to bupropion have not been fully characterized.
However, it has been demonstrated in an antidepressant screening test in mice that hydroxybupropion is one half as potent as bupropion, while threohydrobupropion and erythrohydrobupropion are 5-fold less potent than bupropion. This may be of clinical importance, because the plasma concentrations of the metabolites are as high or higher than those of bupropion. At steady state, peak plasma concentration of hydroxybupropion occurred approximately 7 hours after administration of bupropion hydrochloride extended-release tablets (XL), and it was approximately 7 times the peak level of the parent drug.
The elimination half-life of hydroxybupropion is approximately 20 (±5) hours, and its AUC at steady state is about 13 times that of bupropion. The times to peak concentrations for the erythrohydrobupropion and threohydrobupropion metabolites are similar to that of hydroxybupropion. However, the elimination half-lives of erythrohydrobupropion and threohydrobupropion are longer, approximately 33 (±10) and 37 (±13) hours, respectively, and steady-state AUCs were 1.4 and 7 times that of bupropion, respectively.
Bupropion and its metabolites exhibit l… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
Bupropion Hydrochloride Extended-Release Tablets USP (XL), 150 mg of bupropion hydrochloride, are white to pale yellow, round biconvex tablet with imprinting “YH 102” in bottles of 30 tablets (NDC 42806-414-30), 90 tablets (NDC 42806-414-09) and 500 tablets (NDC 42806-414-05). Bupropion Hydrochloride Extended-Release Tablets USP (XL), 300 mg of bupropion hydrochloride, are white to pale yellow, round biconvex tablet with imprinting “YH 101” in bottles of 30 tablets (NDC 72189-539-30), 90 tablets (NDC 42806-416-09) and 500 tablets (NDC 42806-416-05).
📦 Storage and Handling ▾
Store at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [See USP Controlled Room Temperature]. Dispense in a tight, light-resistant container as defined in the USP with a child-resistant closure. Keep out of reach of children. Bupropion Hydrochloride Extended-Release Tablets USP (XL) may have an odor.
📋 Description ▾
Bupropion Hydrochloride USP, an antidepressant of the aminoketone class, is chemically unrelated to tricyclic, tetracyclic, selective serotonin reuptake inhibitor, or other known antidepressant agents. Its structure closely resembles that of diethylpropion; it is related to phenylethylamines. It is designated as (±)-1-(3-chorophenyl)-2-[(1,1-dimethylethyl)amino]-1-propanone hydrochloride.
The molecular weight is 276.2. The molecular formula is C 13H 18ClNO•HCl. Bupropion hydrochloride powder is white, crystalline, and highly soluble in water.
It has a bitter taste and produces the sensation of local anesthesia on the oral mucosa. The structural formula is: [bupropion-structure] Bupropion Hydrochloride Extended-Release Tablets USP (XL) are supplied for oral administration as 150 mg and 300 mg white to pale yellow extended-release tablets. Each tablet contains the labeled amount of bupropion hydrochloride and the inactive ingredients: cysteine hydrochloride, ethylcellulose, methacrylic acid copolymer dispersion, lecithin, magnesium stearate, polyvinyl alcohol, polyethylene glycol, povidone, silicon dioxide, talc, triethyl citrate and titanium dioxide.
The tablets are printed with black ink containing ammonium hydroxide, ferrosoferric oxide, propylene glycol, shellac glaze. The insoluble shell of the extended-release tablet may remain intact during gastrointestinal transit and is eliminated in the feces. USP dissolution test 22 is used.
🔬 Clinical Studies ▾
14.1Major Depressive Disorder The efficacy of bupropion in the treatment of major depressive disorder was established with the immediate-release formulation of bupropion hydrochloride in two 4-week, placebo-controlled trials in adult inpatients with MDD and in one 6-week, placebo-controlled trial in adult outpatients with MDD. In the first study, the bupropion dose range was 300 mg to 600 mg per day administered in 3 divided doses; 78% of patients were treated with doses of 300 mg to 450 mg per day. The trial demonstrated the efficacy of bupropion as measured by the Hamilton Depression Rating Scale (HAMD) total score, the HAMD depressed mood item (item 1), and the Clinical Global Impressions-Severity Scale (CGI-S).
The second study included 2 fixed doses of bupropion (300 mg and 450 mg per day) and placebo. This trial demonstrated the efficacy of bupropion for only the 450 mg dose. The efficacy results were significant for the HAMD total score and the CGI-S severity score, but not for HAMD item 1.
In the third study, outpatients were treated with bupropion 300 mg per day. This study demonstrated the efficacy of bupropion as measured by the HAMD total score, the HAMD item 1, the Montgomery-Asberg Depression Rating Scale (MADRS), the CGI-S score, and the CGI-Improvement Scale (CGI-I) score. A longer-term, placebo-controlled, randomized withdrawal trial demonstrated the efficacy of bupropion HCl sustained-release in the maintenance treatment of MDD.
The trial included adult outpatients meeting DSM-IV criteria for MDD, recurrent type, who had responded during an 8-week open-label trial of bupropion 300 mg per day. Responders were randomized to continuation of bupropion 300 mg per day or placebo for up to 44 weeks of observation for relapse. Response during the open-label phase was defined as a CGI-Improvement Scale score of 1 (very much improved) or 2 (much improved) for each of the final 3 weeks.
Relapse during the double-blind phase was defined as the investigator’s judgment that drug treatment was needed for worsening depressive symptoms. Patients in the bupropion group experienced significantly lower relapse rates over the subsequent 44 weeks compared to those in the placebo group. Although there are no independent trials demonstrating the efficacy of bupropion hydrochloride extended-release tablets (XL) in the acute treatment of MDD, studies have demonstrated similar bioavailability between the immediate-, sustained-, and extended-release formulations of bupropion HCl under steady-state conditions (i.e., the exposures [C max and AUC] for bupropion and its metabolites are similar among the 3 formulations).
14.2Seasonal Affective Disorder The efficacy of bupropion hydrochloride extended-release tablets (XL) in the prevention of seasonal major depressive episodes associated with SAD was established in 3 randomized, double-blind, placebo-controlled trials in adult outpatients with a history of MDD with an autumn-winter seasonal pattern (as defined by DSM-IV criteria). Bupropion treatment was initiated prior to the onset of symptoms in the autumn (September to November). Treatment was discontinued following a 2-week taper that began during the first week of spring (fourth week of March), resulting in a treatment duration of approximately 4 to 6 months for the majority of patients.
Patients were randomized to treatment with bupropion hydrochloride extended-release tablets (XL) or placebo. The initial bupropion dose was 150 mg once daily for 1 week, followed by up-titration to 300 mg once daily. Patients who were deemed by the investigator to be unlikely or unable to tolerate 300 mg once daily were allowed to remain on, or had their dose reduced to, 150 mg once daily.
The mean bupropion doses in the 3 trials ranged from 257 mg to 280 mg per day. Approximately 59% of patients continued in the study for 3 to 6 months; 26% continued for <3 months, 15% continued for >6 months. To enter the trials, patients must have had a low level of… [Excerpted — this section continues on DailyMed.]
🔒 Drug Abuse and Dependence ▾
9.1Controlled Substance Bupropion is not a controlled substance.
9.2Abuse Humans Controlled clinical studies of bupropion HCl immediate-release conducted in normal volunteers, in subjects with a history of multiple drug abuse, and in depressed patients demonstrated an increase in motor activity and agitation/excitement. In a population of individuals experienced with drugs of abuse, a single dose of 400 mg bupropion produced mild amphetamine-like activity as compared to placebo on the Morphine-Benzedrine Subscale of the Addiction Research Center Inventories (ARCI), and a score intermediate between placebo and amphetamine on the Liking Scale of the ARCI.
These scales measure general feelings of euphoria and drug desirability. Findings in clinical trials, however, are not known to reliably predict the abuse potential of drugs. Nonetheless, evidence from single-dose studies does suggest that the recommended daily dosage of bupropion when administered in divided doses is not likely to be significantly reinforcing to amphetamine or CNS stimulant abusers.
However, higher doses (that could not be tested because of the risk of seizure) might be modestly attractive to those who abuse CNS stimulant drugs. Bupropion hydrochloride extended-release tablets (XL) are intended for oral use only. The inhalation of crushed tablets or injection of dissolved bupropion has been reported.
Seizures and/or cases of death have been reported when bupropion has been administered intranasally or by parenteral injection. Animals Studies in rodents and primates demonstrated that bupropion exhibits some pharmacologic actions common to psychostimulants. In rodents, it has been shown to increase locomotor activity, elicit a mild stereotyped behavioral response, and increase rates of responding in several schedule-controlled behavior paradigms.
In primate models assessing the positive reinforcing effects of psychoactive drugs, bupropion was self-administered intravenously. In rats, bupropion produced amphetamine-like and cocaine-like discriminative stimulus effects in drug discrimination paradigms used to characterize the subjective effects of psychoactive drugs.
🧪 Nonclinical Toxicology ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Lifetime carcinogenicity studies were performed in rats and mice at doses up to 300 and 150 mg/kg/day bupropion hydrochloride, respectively. These doses are approximately 7 and 2 times the maximum recommended human dose (MRHD), respectively, on a mg/m 2 basis. In the rat study there was an increase in nodular proliferative lesions of the liver at doses of 100 to 300 mg/kg/day of bupropion hydrochloride (approximately 2 to 7 times the MRHD on a mg/m 2 basis); lower doses were not tested.
The question of whether or not such lesions may be precursors of neoplasms of the liver is currently unresolved. Similar liver lesions were not seen in the mouse study, and no increase in malignant tumors of the liver and other organs was seen in either study. Bupropion produced a positive response (2 to 3 times control mutation rate) in 2 of 5 strains in one Ames bacterial mutagenicity assay, but was negative in another.
Bupropion produced an increase in chromosomal aberrations in 1 of 3 in vivo rat bone marrow cytogenetic studies. A fertility study in rats at doses up to 300 mg/kg/day revealed no evidence of impaired fertility.
📄 Package Label / Principal Display Panel ▾
72189-0539-30
72189-539-90
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |