
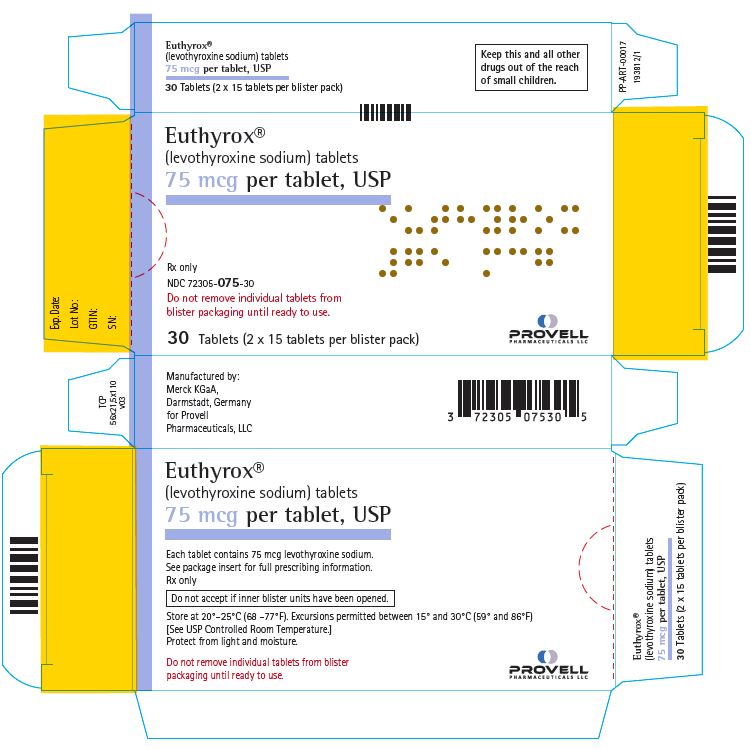
EUTHYROX levothyroxine sodium 75 ug Tablet, 30-count
Other active recalls for Levothyroxine Sodium (different manufacturers) — 6 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the l-Thyroxine class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Levothyroxine is used to treat hypothyroidism (condition where the thyroid gland does not produce enough thyroid hormone). It is also used with surgery and radioactive iodine therapy to treat thyroid cancer. Levothyroxine is in a class of medications called hormones. It works by replacing thyroid hormone that is normally produced by the body. Without thyroid hormone, your body cannot function properly, which may result in poor growth, slow speech, lack of energy, excessive tiredness, constipation, weight gain, hair loss, dry, thick skin, increased sensitivity to cold, joint and muscle pain, he...
Read the full MedlinePlus article ↗- Your thyroid gland isn't making enough of a hormone called T4, which your whole body depends on to regulate your energy, metabolism, heart rate, and more. Levothyroxine is a precis...
- What exactly is levothyroxine doing for me — why do I need to take it every day?
- Timing really does make a difference with this medication. Food — especially high-fiber foods or anything soy-based — can block your gut from absorbing it properly. Taking it 30 to...
- Why does it matter so much when I take it — can't I just take it with breakfast?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Levothyroxine Sodium — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII XF417D3PSL
Anhydrous citric acid is a sour, crystalline powder derived from citric acid with water removed. In medicines, it acts as a buffer to control pH, adds tartness to improve taste, and helps tablets disintegrate.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
6 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.222 | $6.67 / 30 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.2386 | $7.16 / 30 tablets |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Levothyroxine Sodium 75 ug 00378-1805-10 | Mylan | 1000 tablets | $0.046 | AB1,AB2,AB3,AB4 | Availability likely | save 79% |
| Levothyroxine Sodium 75 ug 00527-3282-43 | Lannett | 1000 tablets | $0.046 | AB1,AB2,AB3 | Availability likely | save 79% |
| Levothyroxine Sodium .075 mg 00904-6951-61 | Major | 100 tablets | $0.046 | AB1,AB2,AB3 | Availability likely | save 79% |
| Levothyroxine sodium 75 ug 16729-0449-15 | Accord | 90 tablets | $0.046 | AB1,AB2,AB3,AB4 | Availability likely | save 79% |
| Levothyroxine Sodium 75 ug 33342-0395-10 | Macleods | 90 tablets | $0.046 | AB1,AB2,AB3,AB4 | Availability likely | save 79% |
| levothyroxine sodium 75 ug 47781-0646-10 | Alvogen, | 1000 tablets | $0.046 | AB1,AB2,AB3,AB4 | Availability likely | save 79% |
| Levothyroxine Sodium 75 ug 51079-0441-20 | Mylan | 100 tablets | $0.046 | AB1,AB2,AB3,AB4 | Availability likely | save 79% |
| Levothyroxine Sodium .075 mg 60687-0475-01 | American | 100 tablets | $0.046 | AB1,AB2,AB3 | Availability likely | save 79% |
| Levothyroxine Sodium .075 mg 68180-0967-01 | Lupin | 100 tablets | $0.046 | AB1,AB2,AB3 | Availability likely | save 79% |
| Levothyroxine Sodium .075 mg 69238-1832-01 | Amneal | 100 tablets | $0.046 | AB1,AB2,AB3 | Availability likely | save 79% |
| Levothyroxine Sodium 75 ug 72603-0662-01 | NorthStar | 1000 tablets | $0.046 | AB1,AB2,AB3,AB4 | Availability likely | save 79% |
| Levo-T 75 ug 55466-0106-11 | Neolpharma, | 90 tablets | $0.046 | AB1,AB2,AB3 | Discontinued | save 79% |
| Euthyrox 75 ugthis 72305-0075-30 | Provell | 30 tablets | $0.222 | — | FDA listed | — |
| Levoxyl 75 ug 60793-0852-01 | Pfizer | 100 tablets | $0.944 | AB1,AB3 | Availability likely | +325% |
| Synthroid 75 ug 00074-5182-11 | AbbVie | 100 tablets | $1.662 | AB1,AB2 | Availability likely | +648% |
| Unithroid 75 ug 60846-0803-01 | Amneal | 100 tablets | $4.195 | AB1,AB2,AB3 | Availability likely | +1787% |
| Levothyroxine sodium 75 ug 00480-8690-01 | Teva | 100 tablets | — | AB1,AB2,AB3,AB4 | Discontinued | — |
| Levothyroxine Sodium .075 mg 00615-8597-05 | NCS | 15 tablets | — | AB1,AB2,AB3 | FDA listed | — |
| Levothyroxine Sodium .075 mg 31722-0286-01 | Camber | 100 tablets | — | AB4 | FDA listed | — |
| Levothyroxine sodium 75 ug 50090-6118-00 | A-S | 30 tablets | — | AB1,AB2,AB3,AB4 | FDA listed | — |
| Levothyroxine sodium 75 ug 50090-6119-00 | A-S | 90 tablets | — | AB1,AB2,AB3,AB4 | FDA listed | — |
| Levothyroxine Sodium .075 mg 50090-6824-00 | A-S | 30 tablets | — | AB1,AB2,AB3 | FDA listed | — |
| Levothyroxine Sodium .075 mg 50090-6825-00 | A-S | 90 tablets | — | AB1,AB2,AB3 | FDA listed | — |
| Levothyroxine Sodium 75 ug 51655-0576-52 | Northwind | 30 tablets | — | AB1,AB2,AB3 | FDA listed | — |
| Levothyroxine Sodium .075 mg 51655-0687-52 | Northwind | 30 tablets | — | AB1,AB2,AB3 | FDA listed | — |
| Levothyroxine Sodium .075 mg 51655-0989-52 | Northwind | 30 tablets | — | AB1,AB2,AB3 | FDA listed | — |
| Levothyroxine Sodium .075 mg 55154-3560-00 | Cardinal | 10 tablets | — | AB1,AB2,AB3 | FDA listed | — |
| Levothyroxine Sodium 75 ug 55154-5395-00 | Cardinal | 10 tablets | — | AB1,AB2,AB3,AB4 | FDA listed | — |
| Levothyroxine Sodium .075 mg 67046-0801-03 | Coupler | 30 tablets | — | AB1,AB2,AB3 | FDA listed | — |
| Levothyroxine Sodium 75 ug 67046-1635-03 | Coupler | 30 tablets | — | AB1,AB2,AB3 | FDA listed | — |
| Levothyroxine sodium 75 ug 67296-2046-03 | Redpharm | 30 tablets | — | AB1,AB2,AB3,AB4 | FDA listed | — |
| Levothyroxine Sodium 75 ug 68071-3887-03 | NuCare | 30 tablets | — | AB1,AB2,AB3,AB4 | FDA listed | — |
| levothyroxine sodium 75 ug 68071-5227-09 | NuCare | 90 tablets | — | AB1,AB2,AB3,AB4 | FDA listed | — |
| levothyroxine sodium 75 ug 68788-7725-03 | Preferred | 30 tablets | — | AB1,AB2,AB3,AB4 | FDA listed | — |
| Levothyroxine sodium 75 ug 68788-7954-03 | Preferred | 30 tablets | — | AB1,AB2,AB3,AB4 | FDA listed | — |
| Levothyroxine Sodium 75 ug 68788-8806-03 | Preferred | 30 tablets | — | AB1,AB2,AB3,AB4 | FDA listed | — |
| Levothyroxine Sodium .075 mg 68788-8896-03 | Preferred | 30 tablets | — | AB1,AB2,AB3 | FDA listed | — |
| Levothyroxine sodium 75 ug 70518-3274-00 | REMEDYREPACK | 90 tablets | — | AB1,AB2,AB3,AB4 | FDA listed | — |
| Levothyroxine Sodium 75 ug 70518-4435-00 | REMEDYREPACK | 90 tablets | — | AB1,AB2,AB3,AB4 | FDA listed | — |
| levothyroxine sodium 75 ug 71205-0353-30 | Proficient | 30 tablets | — | AB1,AB2,AB3,AB4 | FDA listed | — |
| Levothyroxine Sodium 75 ug 71205-0655-30 | Proficient | 30 tablets | — | AB1,AB2,AB3 | FDA listed | — |
| levothyroxine sodium 75 ug 71335-1423-01 | Bryant | 30 tablets | — | AB1,AB2,AB3,AB4 | FDA listed | — |
| Levothyroxine sodium 75 ug 71335-1827-01 | Bryant | 30 tablets | — | AB1,AB2,AB3,AB4 | FDA listed | — |
| Levothyroxine Sodium 75 ug 71335-2039-01 | Bryant | 30 tablets | — | AB1,AB2,AB3 | FDA listed | — |
| Levothyroxine Sodium 75 ug 71335-2289-01 | Bryant | 1000 tablets | — | AB1,AB2,AB3 | FDA listed | — |
| levothyroxine sodium 75 ug 71335-2967-01 | Bryant | 90 tablets | — | AB1,AB2,AB3,AB4 | FDA listed | — |
| levothyroxine sodium 75 ug 72162-1460-00 | Bryant | 1000 tablets | — | AB1,AB2,AB3,AB4 | FDA listed | — |
| Levothyroxine Sodium 75 ug 72189-0073-90 | DIRECT | 90 tablets | — | AB1,AB2,AB3,AB4 | FDA listed | — |
| Levothyroxine Sodium .075 mg 72189-0107-30 | DIRECT | 30 tablets | — | AB1,AB2,AB3 | FDA listed | — |
| Levothyroxine Sodium .075 mg 72865-0238-10 | XLCare | 1000 tablets | — | AB4 | FDA listed | — |
| Levothyroxine sodium 75 ug 82804-0053-30 | Proficient | 30 tablets | — | AB1,AB2,AB3,AB4 | FDA listed | — |
| Levothyroxine sodium 75 ug 87063-0085-00 | ASCLEMED | 1000 tablets | — | AB1,AB2,AB3,AB4 | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2025 (Q1-Q4)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 72305-0075-30 You're viewing this | 2 BLISTER PACK in 1 CARTON (72305-075-30) / 15 TABLET in 1 BLISTER PACK | $0.2223 / ea | $6.67 | 2018-10-17 | Active |
| 72305-0075-90 | 6 BLISTER PACK in 1 CARTON (72305-075-90) / 15 TABLET in 1 BLISTER PACK | — | — | 2023-01-01 | Discontinued by firm |
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 72305-0075-30?
What is the difference between NDC 72305-0075-30 and NDC 72305-0075-90?
What NDC number is used to bill for this package of EUTHYROX levothyroxine sodium 75 ug Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: NOT FOR TREATMENT OF OBESITY OR FOR WEIGHT LOSS Thyroid hormones, including EUTHYROX, either alone or with other therapeutic agents, should not be used for the treatment of obesity or for weight loss. In euthyroid patients, doses within the range of daily hormonal requirements are ineffective for weight reduction. Larger doses may produce serious or even life-threatening manifestations of toxicity, particularly when given in association with sympathomimetic amines such as those used for their anorectic effects [see Adverse Reactions (6) , Drug Interactions (7.7) , and Overdosage (10) ] .
WARNING: NOT FOR TREATMENT OF OBESITY OR FOR WEIGHT LOSS See full prescribing information for complete boxed warning. Thyroid hormones, including EUTHYROX, should not be used for the treatment of obesity or for weight loss. Doses beyond the range of daily hormonal requirements may produce serious or even life-threatening manifestations of toxicity ( 6 , 10 ).
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE EUTHYROX is L-thyroxine (T4) indicated in pediatric and adult patients for: Hypothyroidism: As replacement in primary (thyroidal), secondary (pituitary), and tertiary (hypothalamic) congenital or acquired hypothyroidism. ( 1 ) Pituitary Thyrotropin (Thyroid-Stimulating Hormone, TSH) suppression: As an adjunct to surgery and radioiodine therapy in the management of thyrotropin-dependent well-differentiated thyroid cancer. ( 1 ) Limitations of Use: - Not indicated for suppression of benign thyroid nodules and nontoxic diffuse goiter in iodine-sufficient patients.
( 1 ) - Not indicated for treatment of hypothyroidism during the recovery phase of subacute thyroiditis. ( 1 ) Hypothyroidism EUTHYROX is indicated in pediatric and adult patients as a replacement therapy in primary (thyroidal), secondary (pituitary), and tertiary (hypothalamic) congenital or acquired hypothyroidism. Pituitary Thyrotropin (Thyroid-Stimulating Hormone, TSH) Suppression EUTHYROX is indicated in pediatric and adult patients as an adjunct to surgery and radioiodine therapy in the management of thyrotropin-dependent well-differentiated thyroid cancer .
Limitations of Use: EUTHYROX is not indicated for suppression of benign thyroid nodules and nontoxic diffuse goiter in iodine-sufficient patients as there are no clinical benefits and overtreatment with EUTHYROX may induce hyperthyroidism [see Warnings and Precautions (5.4) ]. EUTHYROX is not indicated for treatment of hypothyroidism during the recovery phase of subacute thyroiditis.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Administer once daily, on an empty stomach, one-half to one hour before breakfast. ( 2.1 ) Administer at least 4 hours before or after drugs that are known to interfere with absorption. ( 2.1 ) Evaluate the need for dose adjustments when regularly administering within one hour of certain foods that may affect absorption.
( 2.1 ) Starting dose depends on a variety of factors, including age, body weight, cardiovascular status, concomitant medical conditions (including pregnancy), concomitant medications, co-administered food, and the specific nature of the condition being treated. Peak therapeutic effect may not be attained for 4 to 6 weeks. ( 2.2 ) See full prescribing information for dosing in specific patient populations.
( 2.3 ) Adequacy of therapy determined with periodic monitoring of TSH and/or T4 as well as clinical status. ( 2.4 )
2.1General Administration Information Administer EUTHYROX tablets orally as a single daily dose, on an empty stomach, one-half to one hour before breakfast. Administer EUTHYROX at least 4 hours before or after drugs known to interfere with EUTHYROX absorption [see Drug Interactions (7.1) ]. Evaluate the need for dose adjustments when regularly administering within one hour of certain foods that may affect EUTHYROX absorption [see Drug Interactions (7.9) , Clinical Pharmacology (12.3) ].
Administer EUTHYROX to infants and children who cannot swallow intact tablets by crushing the tablet, suspending the freshly crushed tablet in a small amount (5 mL to 10 mL or 1 teaspoon to 2 teaspoons) of water and immediately administering the suspension by spoon or dropper. Do not store the suspension. Do not administer in foods that decrease absorption of EUTHYROX, such as soybean-based infant formula [see Drug Interactions (7.9) ].
2.2General Principles of Dosing The dose of EUTHYROX for hypothyroidism or pituitary TSH suppression depends on a variety of factors including: the patient's age, body weight, cardiovascular status, concomitant medical conditions (including pregnancy), concomitant medications, co-administered food and the specific nature of the condition being treated [see Dosage and Administration (2.3) , Warnings and Precautions (5) , Drug Interactions (7) ]. Dosing must be individualized to account for these factors and dose adjustments made based on periodic assessment of the patient's clinical response and laboratory parameters [see Dosage and Administration (2.4) ].
The peak therapeutic effect of a given dose of EUTHYROX may not be attained for 4 to 6 weeks.
2.3Dosing in Specific Populations Primary Hypothyroidism in Adults and in Adolescents in Whom Growth and Puberty Are Complete Start EUTHYROX at the full replacement dose in otherwise healthy, non-elderly individuals who have been hypothyroid for only a short time (such as a few months). The average full replacement dose of EUTHYROX is approximately 1.6 mcg per kg per day (for example: 100 mcg per day to 125 mcg per day for a 70 kg adult). Adjust the dose by 12.5 mcg to 25 mcg increments every 4 to 6 weeks until the patient is clinically euthyroid and the serum TSH returns to normal.
Doses greater than 200 mcg per day are seldom required. An inadequate response to daily doses of greater than 300 mcg per day is rare and may indicate poor compliance, malabsorption, drug interactions, or a combination of these factors. For elderly patients or patients with underlying cardiac disease, start with a dose of 12.5 mcg per day to 25 mcg per day.
Increase the dose every 6 to 8 weeks, as needed until the patient is clinically euthyroid and the serum TSH returns to normal. The full replacement dose of EUTHYROX may be less than 1 mcg per kg per day in elderly patients. In patients with severe longstanding hypothyroidism, start with a dose of 12.5 mcg per day to 25 mcg per day.
Adjust the dose in 12.5 mcg to 25 mcg increments every 2 to 4 weeks until the patient is clinically euthyroid and the serum TSH level is normali…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS EUTHYROX tablets are uncoated, off-white, round and flat on both sides with a beveled edge, and a dividing score on both sides available as: Tablet Strength Tablet Markings 25 mcg "EM" and "25" 50 mcg "EM" and "50" 75 mcg "EM" and "75" 88 mcg "EM" and "88" 100 mcg "EM" and "100" 112 mcg "EM" and "112" 125 mcg "EM" and "125" 137 mcg "EM" and "137" 150 mcg "EM" and "150" 175 mcg "EM" and "175" 200 mcg "EM" and "200" Tablets: 25 mcg, 50 mcg, 75 mcg, 88 mcg, 100 mcg, 112 mcg, 125 mcg, 137 mcg, 150 mcg, 175 mcg, 200 mcg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS EUTHYROX is contraindicated in patients with uncorrected adrenal insufficiency [ see Warnings and Precautions (5.3) ]. Uncorrected adrenal insufficiency. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Cardiac adverse reactions in the elderly and in patients with underlying cardiovascular disease: Initiate EUTHYROX at less than the full replacement dose because of the increased risk of cardiac adverse reactions, including atrial fibrillation. ( 2.3 , 5.1 , 8.5 ) Myxedema coma: Do not use oral thyroid hormone drug products to treat myxedema coma. ( 5.2 ) Acute adrenal crisis in patients with concomitant adrenal insufficiency: Treat with replacement glucocorticoids prior to initiation of EUTHYROX treatment.
( 5.3 ) Prevention of hyperthyroidism or incomplete treatment of hypothyroidism: Proper dose titration and careful monitoring is critical to prevent the persistence of hypothyroidism or the development of hyperthyroidism. ( 5.4 ) Worsening of diabetic control: Therapy in patients with diabetes mellitus may worsen glycemic control and result in increased antidiabetic agent or insulin requirements. Carefully monitor glycemic control after starting, changing, or discontinuing thyroid hormone therapy.
( 5.5 ) Decreased bone mineral density associated with thyroid hormone over-replacement: Over-replacement can increase bone resorption and decrease bone mineral density. Give the lowest effective dose. ( 5.6 )
5.1Cardiac Adverse Reactions in the Elderly and in Patients with Underlying Cardiovascular Disease Overtreatment with levothyroxine may cause an increase in heart rate, cardiac wall thickness, and cardiac contractility and may precipitate angina or arrhythmias, particularly in patients with cardiovascular disease and in elderly patients. Initiate EUTHYROX therapy in this population at lower doses than those recommended in younger individuals or in patients without cardiac disease [see Dosage and Administration (2.3) , Use in Specific Populations (8.5) ].
Monitor for cardiac arrhythmias during surgical procedures in patients with coronary artery disease receiving suppressive EUTHYROX therapy. Monitor patients receiving concomitant EUTHYROX and sympathomimetic agents for signs and symptoms of coronary insufficiency. If cardiovascular symptoms develop or worsen, reduce or withhold the EUTHYROX dose for one week and restart at a lower dose.
5.2Myxedema Coma Myxedema coma is a life-threatening emergency characterized by poor circulation and hypometabolism, and may result in unpredictable absorption of levothyroxine sodium from the gastrointestinal tract. Use of oral thyroid hormone drug products is not recommended to treat myxedema coma. Administer thyroid hormone products formulated for intravenous administration to treat myxedema coma.
5.3Acute Adrenal Crisis in Patients with Concomitant Adrenal Insufficiency Thyroid hormone increases metabolic clearance of glucocorticoids. Initiation of thyroid hormone therapy prior to initiating glucocorticoid therapy may precipitate an acute adrenal crisis in patients with adrenal insufficiency. Treat patients with adrenal insufficiency with replacement glucocorticoids prior to initiating treatment with EUTHYROX [see Contraindications (4) ].
5.4Prevention of Hyperthyroidism or Incomplete Treatment of Hypothyroidism EUTHYROX has a narrow therapeutic index. Over- or under-treatment with EUTHYROX may have negative effects on growth and development, cardiovascular function, bone metabolism, reproductive function, cognitive function, emotional state, gastrointestinal function, and on glucose and lipid metabolism. Titrate the dose of EUTHYROX carefully and monitor response to titration to avoid these effects [see Dosage and Administration (2.4) ].
Monitor for the presence of drug or food interactions when using EUTHYROX and adjust the dose as necessary [see Drug Interactions (7) , Clinical Pharmacology (12.3) ].
5.5Worsening of Diabetic Control Addition of levothyroxine therapy in patients with diabetes mellitus may worsen glycemic control and result in increased antidiabetic agent or insulin requirements. Carefully monitor glycemic control after starting, changing,…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Adverse reactions associated with EUTHYROX therapy are primarily those of hyperthyroidism due to therapeutic overdosage [see Warnings and Precautions (5) , Overdosage (10) ]. They include the following: General: fatigue, increased appetite, weight loss, heat intolerance, fever, excessive sweating Central Nervous System: headache, hyperactivity, nervousness, anxiety, irritability, emotional lability, insomnia Musculoskeletal: tremors, muscular weakness and cramps Cardiovascular: palpitations, tachycardia, arrhythmias, increased pulse and blood pressure, heart failure, angina, myocardial infarction, cardiac arrest Respiratory: dyspnea Gastrointestinal: diarrhea, vomiting, abdominal cramps and elevations in liver function tests Dermatologic: hair loss, flushing, rash Endocrine: decreased bone mineral density Reproductive: menstrual irregularities, impaired fertility Seizures have been reported rarely with levothyroxine therapy.
Adverse reactions associated with EUTHYROX are primarily those of hyperthyroidism due to therapeutic overdosage: arrhythmias, myocardial infarction, dyspnea, muscle spasm, headache, nervousness, irritability, insomnia, tremors, muscle weakness, increased appetite, weight loss, diarrhea, heat intolerance, menstrual irregularities, and skin rash. ( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Provell Pharmaceuticals, LLC at 1-888-899-7041 or FDA at1-800-FDA-1088 or www.fda.gov/medwatch . Adverse Reactions in Pediatric Patients Pseudotumor cerebri and slipped capital femoral epiphysis have been reported in pediatric patients receiving levothyroxine therapy.
Overtreatment may result in craniosynostosis in infants and premature closure of the epiphyses in pediatric patients with resultant compromised adult height. Hypersensitivity Reactions Hypersensitivity reactions to inactive ingredients have occurred in patients treated with thyroid hormone products. These include urticaria, pruritus, skin rash, flushing, angioedema, various gastrointestinal symptoms (abdominal pain, nausea, vomiting and diarrhea), fever, arthralgia, serum sickness and wheezing.
Hypersensitivity to levothyroxine itself is not known to occur.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS See full prescribing information for drugs that affect thyroid hormone pharmacokinetics and metabolism (e.g., absorption, synthesis, secretion, catabolism, protein binding, and target tissue response) and may alter the therapeutic response to EUTHYROX. ( 7 )
7.1Drugs Known to Affect Thyroid Hormone Pharmacokinetics Many drugs can exert effects on thyroid hormone pharmacokinetics (e.g. absorption, synthesis, secretion, catabolism, protein binding, and target tissue response) and may alter the therapeutic response to EUTHYROX (see Tables 2 – 5). Table 2: Drugs That May Decrease T4 Absorption (Hypothyroidism) Potential impact: Concurrent use may reduce the efficacy of EUTHYROX by binding and delaying or preventing absorption, potentially resulting in hypothyroidism Drug or Drug Class Effect Calcium Carbonate Ferrous Sulfate Calcium carbonate may form an insoluble chelate with levothyroxine, and ferrous sulfate likely forms a ferric-thyroxine complex.
Administer EUTHYROX at least 4 hours apart from these agents. Orlistat Monitor patients treated concomitantly with orlistat and EUTHYROX for changes in thyroid function. Bile Acid Sequestrants -Colesevelam -Cholestyramine -Colestipol Ion Exchange Resins -Kayexalate -Sevelamer Bile acid sequestrants and ion exchange resins are known to decrease levothyroxine absorption.
Administer EUTHYROX at least 4 hours prior to these drugs or monitor thyrotropin (TSH) levels. Other drugs: Proton Pump Inhibitors Sucralfate Antacids - Aluminum & Magnesium Hydroxides - Simethicone Gastric acidity is an essential requirement for adequate absorption of levothyroxine. Sucralfate, antacids and proton pump inhibitors may cause hypochlorhydria, affect intragastric pH, and reduce levothyroxine absorption.
Monitor patients appropriately. Table 3: Drugs That May Alter T4 and Triiodothyronine (T3) Serum Transport Without Affecting Free-Thyroxine (FT4) Concentration (Euthyroidism) Drug or Drug Class Effect Clofibrate Estrogen-containing oral contraceptives Estrogens (oral) Heroin / Methadone 5-Fluorouracil Mitotane Tamoxifen These drugs may increase serum thyroxine-binding globulin (TBG) concentration. Androgens / Anabolic Steroids Asparaginase Glucocorticoids Slow-Release Nicotinic Acid These drugs may decrease serum TBG concentration.
Potential impact (below) : Administration of these agents with EUTHYROX results in an initial transient increase in FT4. Continued administration results in a decrease in serum T4 and normal FT4 and TSH concentrations. Salicylates (> 2 g/day) Salicylates inhibit binding of T4 and T3 to TBG and transthyretin.
An initial increase in serum FT4 is followed by return of FT4 to normal levels with sustained therapeutic serum salicylate concentrations, although total T4 levels may decrease by as much as 30%. Other drugs: Carbamazepine Furosemide (> 80 mg IV) Heparin Hydantoins Non-Steroidal Anti-inflammatory Drugs - Fenamates These drugs may cause protein-binding site displacement . Furosemide has been shown to inhibit the protein binding of T4 to TBG and albumin, causing an increased free-T4 fraction in serum.
Furosemide competes for T4-binding sites on TBG, prealbumin, and albumin, so that a single high dose can acutely lower the total T4 level. Phenytoin and carbamazepine reduce serum protein binding of levothyroxine, and total and free-T4 may be reduced by 20% to 40%, but most patients have normal serum TSH levels and are clinically euthyroid. Closely monitor thyroid hormone parameters.
Table 4: Drugs That May Alter Hepatic Metabolism of T4 (Hypothyroidism) Potential impact: Stimulation of hepatic microsomal drug-metabolizing enzyme activity may cause increased hepatic degradation of levothyroxine, resulting in increased EUTHYROX requirements. Drug or Drug Class Effect Phenobarbital Rifampin Phenobarbital has been shown to reduce the response to thyroxine. Phenobarbital increases L-thyroxine metabolism by inducing uridine 5'-diphospho-glucuronosyltransferase (UG…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy may require the use of higher doses of EUTHYROX. ( 2.3 , 8.1 )
8.1Pregnancy Risk Summary Experience with levothyroxine use in pregnant women, including data from post-marketing studies, have not reported increased rates of major birth defects or miscarriages (see Data ). There are risks to the mother and fetus associated with untreated hypothyroidism in pregnancy. Since thyroid-stimulating hormone (TSH) levels may increase during pregnancy, TSH should be monitored and EUTHYROX dosage adjusted during pregnancy (see Clinical Considerations ).
There are no animal studies conducted with levothyroxine during pregnancy. EUTHYROX should not be discontinued during pregnancy and hypothyroidism diagnosed during pregnancy should be promptly treated. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk Maternal hypothyroidism during pregnancy is associated with a higher rate of complications, including spontaneous abortion, gestational hypertension, pre-eclampsia, stillbirth, and premature delivery. Untreated maternal hypothyroidism may have an adverse effect on fetal neurocognitive development.
Dose Adjustments During Pregnancy and Postpartum Period Pregnancy may increase EUTHYROX requirements. Serum TSH level should be monitored and the EUTHYROX dosage adjusted during pregnancy. Since postpartum TSH levels are similar to preconception values, the EUTHYROX dosage should return to the pre-pregnancy dose immediately after delivery [see Dosage and Administration (2.3) ].
Data Human Data Levothyroxine is approved for use as a replacement therapy for hypothyroidism. There is a long experience of levothyroxine use in pregnant women, including data from post-marketing studies that have not reported increased rates of fetal malformations, miscarriages or other adverse maternal or fetal outcomes associated with levothyroxine use in pregnant women.
8.2Lactation Risk Summary Limited published studies report that levothyroxine is present in human milk. However, there is insufficient information to determine the effects of levothyroxine on the breastfed infant and no available information on the effects of levothyroxine on milk production. Adequate levothyroxine treatment during lactation may normalize milk production in hypothyroid lactating mothers.
The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for EUTHYROX and any potential adverse effects on the breastfed infant from EUTHYROX or from the underlying maternal condition.
8.4Pediatric Use The initial dose of EUTHYROX varies with age and body weight. Dosing adjustments are based on an assessment of the individual patient's clinical and laboratory parameters [see Dosage and Administration (2.3 , 2.4) ]. In children in whom a diagnosis of permanent hypothyroidism has not been established, discontinue EUTHYROX administration for a trial period, but only after the child is at least 3 years of age.
Obtain serum T4 and TSH levels at the end of the trial period, and use laboratory test results and clinical assessment to guide diagnosis and treatment, if warranted. Congenital Hypothyroidism [see Dosage and Administration (2.3 , 2.4) ] Rapid restoration of normal serum T 4 concentrations is essential for preventing the adverse effects of congenital hypothyroidism on intellectual development as well as on overall physical growth and maturation. Therefore, initiate EUTHYROX therapy immediately upon diagnosis.
Levothyroxine is generally continued for life in these patients. Closely monitor infants during the first 2 weeks of EUTHYROX therapy for cardiac overload, arrhythmias, and aspiration from av…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Experience with levothyroxine use in pregnant women, including data from post-marketing studies, have not reported increased rates of major birth defects or miscarriages (see Data ). There are risks to the mother and fetus associated with untreated hypothyroidism in pregnancy. Since thyroid-stimulating hormone (TSH) levels may increase during pregnancy, TSH should be monitored and EUTHYROX dosage adjusted during pregnancy (see Clinical Considerations ).
There are no animal studies conducted with levothyroxine during pregnancy. EUTHYROX should not be discontinued during pregnancy and hypothyroidism diagnosed during pregnancy should be promptly treated. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk Maternal hypothyroidism during pregnancy is associated with a higher rate of complications, including spontaneous abortion, gestational hypertension, pre-eclampsia, stillbirth, and premature delivery. Untreated maternal hypothyroidism may have an adverse effect on fetal neurocognitive development.
Dose Adjustments During Pregnancy and Postpartum Period Pregnancy may increase EUTHYROX requirements. Serum TSH level should be monitored and the EUTHYROX dosage adjusted during pregnancy. Since postpartum TSH levels are similar to preconception values, the EUTHYROX dosage should return to the pre-pregnancy dose immediately after delivery [see Dosage and Administration (2.3) ].
Data Human Data Levothyroxine is approved for use as a replacement therapy for hypothyroidism. There is a long experience of levothyroxine use in pregnant women, including data from post-marketing studies that have not reported increased rates of fetal malformations, miscarriages or other adverse maternal or fetal outcomes associated with levothyroxine use in pregnant women.
🧒 Pediatric Use ▾
8.4Pediatric Use The initial dose of EUTHYROX varies with age and body weight. Dosing adjustments are based on an assessment of the individual patient's clinical and laboratory parameters [see Dosage and Administration (2.3 , 2.4) ]. In children in whom a diagnosis of permanent hypothyroidism has not been established, discontinue EUTHYROX administration for a trial period, but only after the child is at least 3 years of age.
Obtain serum T4 and TSH levels at the end of the trial period, and use laboratory test results and clinical assessment to guide diagnosis and treatment, if warranted. Congenital Hypothyroidism [see Dosage and Administration (2.3 , 2.4) ] Rapid restoration of normal serum T 4 concentrations is essential for preventing the adverse effects of congenital hypothyroidism on intellectual development as well as on overall physical growth and maturation. Therefore, initiate EUTHYROX therapy immediately upon diagnosis.
Levothyroxine is generally continued for life in these patients. Closely monitor infants during the first 2 weeks of EUTHYROX therapy for cardiac overload, arrhythmias, and aspiration from avid suckling. Closely monitor patients to avoid undertreatment or overtreatment.
Undertreatment may have deleterious effects on intellectual development and linear growth. Overtreatment has been associated with craniosynostosis in infants, may adversely affect the tempo of brain maturation, and accelerate the bone age, with resultant premature closure of the epiphyses and compromised adult stature. Acquired Hypothyroidism in Pediatric Patients Closely monitor patients to avoid undertreatment and overtreatment.
Undertreatment may result in poor school performance due to impaired concentration and slowed mentation and in reduced adult height. Overtreatment may accelerate the bone age and result in premature epiphyseal closure and compromised adult stature. Treated children may manifest a period of catch-up growth, which may be adequate in some cases to normalize adult height.
In children with severe or prolonged hypothyroidism, catch-up growth may not be adequate to normalize adult height.
🧓 Geriatric Use ▾
8.5Geriatric Use Because of the increased prevalence of cardiovascular disease among the elderly, initiate EUTHYROX at less than the full replacement dose [see Warnings and Precautions (5.1) and Dosage and Administration (2.3) ] . Atrial arrhythmias can occur in elderly patients. Atrial fibrillation is the most common of the arrhythmias observed with levothyroxine overtreatment in the elderly.
🆘 Overdosage ▾
10 OVERDOSAGE The signs and symptoms of overdosage are those of hyperthyroidism [See Warnings and Precautions (5.4) and Adverse Reactions (6) ]. In addition, confusion and disorientation may occur. Cerebral embolism, shock, coma, and death have been reported.
Seizures occurred in a 3 year-old child ingesting 3.6 mg levothyroxine. Symptoms may not necessarily be evident or may not appear until several days after ingestion of levothyroxine sodium. Reduce the EUTHYROX dose or discontinue temporarily if signs or symptoms of overdosage occur.
Initiate appropriate supportive treatment as dictated by the patient's medical status. For current information on the management of poisoning or overdosage, contact the National Poison Control Center at 1-800-222-1222 or www.poison.org.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Thyroid hormones exert their physiologic actions through control of DNA transcription and protein synthesis. Triiodothyronine (T3) and L-thyroxine (T4) diffuse into the cell nucleus and bind to thyroid receptor proteins attached to DNA. This hormone nuclear receptor complex activates gene transcription and synthesis of messenger RNA and cytoplasmic proteins.
The physiological actions of thyroid hormones are produced predominantly by T3, the majority of which (approximately 80%) is derived from T4 by deiodination in peripheral tissues.
12.2Pharmacodynamics Oral levothyroxine sodium is a synthetic T4 hormone that exerts the same physiologic effect as endogenous T4, thereby maintaining normal T4 levels when a deficiency is present.
12.3Pharmacokinetics Absorption Absorption of orally administered T 4 from the gastrointestinal tract ranges from 40% to 80%. The majority of the levothyroxine dose is absorbed from the jejunum and upper ileum. The relative bioavailability of EUTHYROX tablets, compared to an equal nominal dose of oral levothyroxine sodium solution, is approximately 99%.
T 4 absorption is increased by fasting, and decreased in malabsorption syndromes and by certain foods such as soybeans. Dietary fiber decreases bioavailability of T 4 . Absorption may also decrease with age.
In addition, many drugs and foods affect T 4 absorption [see Drug Interactions (7) ]. Distribution Circulating thyroid hormones are greater than 99% bound to plasma proteins, including thyroxine-binding globulin (TBG), thyroxine-binding prealbumin (TBPA), and thyroxine-binding albumin (TBA), whose capacities and affinities vary for each hormone. The higher affinity of both TBG and TBPA for T 4 partially explains the higher serum levels, slower metabolic clearance, and longer half-life of T 4 compared to T 3 .
Protein-bound thyroid hormones exist in reverse equilibrium with small amounts of free hormone. Only unbound hormone is metabolically active. Many drugs and physiologic conditions affect the binding of thyroid hormones to serum proteins [see Drug Interactions (7) ].
Thyroid hormones do not readily cross the placental barrier [see Use in Specific Populations (8.1) ]. Elimination Metabolism T 4 is slowly eliminated (Table 6). The major pathway of thyroid hormone metabolism is through sequential deiodination.
Approximately 80% of circulating T 3 is derived from peripheral T 4 by monodeiodination. The liver is the major site of degradation for both T 4 and T 3 , with T 4 deiodination also occurring at a number of additional sites, including the kidney and other tissues. Approximately 80% of the daily dose of T 4 is deiodinated to yield equal amounts of T 3 and reverse T 3 (rT 3 ).
T 3 and rT 3 are further deiodinated to diiodothyronine. Thyroid hormones are also metabolized via conjugation with glucuronides and sulfates and excreted directly into the bile and gut where they undergo enterohepatic recirculation. Table 6: Pharmacokinetic Parameters of Thyroid Hormones in Euthyroid Patients Hormone Ratio in Thyroglobulin Biologic Potency t½ (days) Protein Binding (%) Includes TBG, TBPA, and TBA Levothyroxine (T 4 ) 10–20 1 6–7 3 to 4 days in hyperthyroidism, 9 to 10 days in hypothyroidism
99.96 Liothyronine (T 3 ) 1 4 ≤ 2
99.5Excretion Thyroid hormones are primarily eliminated by the kidneys. A portion of the conjugated hormone reaches the colon unchanged and is eliminated in the feces. Approximately 20% of T 4 is eliminated in the stool. Urinary excretion of T 4 decreases with age.
🧬 Mechanism of Action ▾
12.1Mechanism of Action Thyroid hormones exert their physiologic actions through control of DNA transcription and protein synthesis. Triiodothyronine (T3) and L-thyroxine (T4) diffuse into the cell nucleus and bind to thyroid receptor proteins attached to DNA. This hormone nuclear receptor complex activates gene transcription and synthesis of messenger RNA and cytoplasmic proteins.
The physiological actions of thyroid hormones are produced predominantly by T3, the majority of which (approximately 80%) is derived from T4 by deiodination in peripheral tissues.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING EUTHYROX (levothyroxine sodium) tablets are uncoated, off-white, round and flat on both sides with a beveled edge, and a dividing score on both sides available as: Tablet Strength Tablet Markings Carton Marking and Blister Packaging Color NDC 30-count carton NDC 90-count carton 25 mcg “EM” and “25” Orange NDC 72305-025-30 NDC 72305-025-90 50 mcg “EM” and “50” White NDC 72305-050-30 NDC 72305-050-90 75 mcg “EM” and “75” Purple NDC 72305-075-30 NDC 72305-075-90 88 mcg “EM” and “88” Olive NDC 72305-088-30 NDC 72305-088-90 100 mcg “EM” and “100” Yellow NDC 72305-100-30 NDC 72305-100-90 112 mcg “EM” and “112” Rose NDC 72305-112-30 NDC 72305-112-90 125 mcg “EM” and “125” Brown NDC 72305-125-30 NDC 72305-125-90 137 mcg “EM” and “137” Turquoise NDC 72305-137-30 NDC 72305-137-90 150 mcg “EM” and “150” Blue NDC 72305-150-30 NDC 72305-150-90 175 mcg “EM” and “175” Lilac NDC 72305-175-30 NDC 72305-175-90 200 mcg “EM” and “200” Pink NDC 72305-200-30 NDC 72305-200-90 Each 30-count carton contains 30 tablets with 2 blister packs.
Each 90-count carton contains 90 tablets with 6 blister packs. Each blister pack contains 15 tablets placed in individual cavities. Store between 20°C to 25°C (68°F to 77°F), with excursions permitted between 15°C to 30°C (59°F to 86°F).
Protect from light and moisture, avoid heat. Do not separate the individual cavities containing the tablet from the intact blister and do not remove the individual tablets from blister packaging until ready to use.
📦 Storage and Handling ▾
Store between 20°C to 25°C (68°F to 77°F), with excursions permitted between 15°C to 30°C (59°F to 86°F). Protect from light and moisture, avoid heat. Do not separate the individual cavities containing the tablet from the intact blister and do not remove the individual tablets from blister packaging until ready to use.
📋 Description ▾
11 DESCRIPTION EUTHYROX contains the active ingredient, levothyroxine, a synthetic crystalline levothyroxine (T 4 ) in sodium salt form. It is chemically designated as L-3,3',5,5'-tetraiodothyronine monosodium hydrate. Synthetic T 4 is identical in chemical structure to the T 4 produced in the human thyroid gland.
Levothyroxine sodium has the molecular formula C 15 H 10 I 4 NNaO 4 ∙ x H 2 O, molecular weight of 798.85 (anhydrous), and structural formula as shown: EUTHYROX tablets for oral administration are supplied in the following strengths: 25 mcg, 50 mcg, 75 mcg, 88 mcg, 100 mcg, 112 mcg, 125 mcg, 137 mcg, 150 mcg, 175 mcg, and 200 mcg. Inactive ingredients citric acid anhydrous, corn starch, gelatin, magnesium stearate, mannitol, sodium croscarmellose. chemical
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Inform the patient of the following information to aid in the safe and effective use of EUTHYROX: Dosing and Administration Instruct patients to take EUTHYROX only as directed by their healthcare provider. Instruct patients to take EUTHYROX as a single dose, preferably on an empty stomach, one-half to one hour before breakfast. Inform patients that agents such as iron and calcium supplements and antacids can decrease the absorption of levothyroxine.
Instruct patients not to take EUTHYROX tablets within 4 hours of these agents. Instruct patients to notify their healthcare provider if they are pregnant or breastfeeding or are thinking of becoming pregnant while taking EUTHYROX. Important Information Inform patients that it may take several weeks before they notice an improvement in symptoms.
Inform patients that the levothyroxine in EUTHYROX is intended to replace a hormone that is normally produced by the thyroid gland. Generally, replacement therapy is to be taken for life. Inform patients that EUTHYROX should not be used as a primary or adjunctive therapy in a weight control program.
Instruct patients to notify their healthcare provider if they are taking any other medications, including prescription and over-the-counter preparations. Instruct patients to notify their physician of any other medical conditions they may have, particularly heart disease, diabetes, clotting disorders, and adrenal or pituitary gland problems, as the dose of medications used to control these other conditions may need to be adjusted while they are taking EUTHYROX. If they have diabetes, instruct patients to monitor their blood and/or urinary glucose levels as directed by their physician and immediately report any changes to their physician.
If patients are taking anticoagulants, their clotting status should be checked frequently. Instruct patients to notify their physician or dentist that they are taking EUTHYROX prior to any surgery. Adverse Reactions Instruct patients to notify their healthcare provider if they experience any of the following symptoms: rapid or irregular heartbeat, chest pain, shortness of breath, leg cramps, headache, nervousness, irritability, sleeplessness, tremors, change in appetite, weight gain or loss, vomiting, diarrhea, excessive sweating, heat intolerance, fever, changes in menstrual periods, hives or skin rash, or any other unusual medical event.
Inform patients that partial hair loss may occur rarely during the first few months of EUTHYROX therapy, but this is usually temporary.