
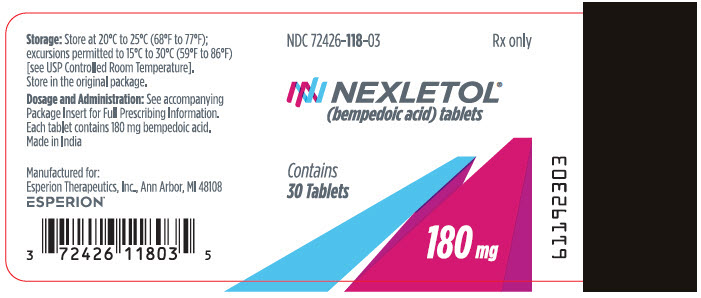
Nexletol Bempedoic Acid 180 mg Tablet, Film Coated, 90-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Adenosine Triphosphate-Citrate Lyase Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Nexletol does two things depending on why your doctor prescribed it. If you're at higher risk for heart disease and can't tolerate statins, it helps lower the chance of a serious e...
- What exactly is Nexletol supposed to do for me?
- Nexletol was specifically developed for people who can't tolerate recommended statin doses, so that situation is exactly what it's designed for. It works differently from statins a...
- Can I take Nexletol if statins made my muscles hurt?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Bempedoic Acid — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 9XZ8H6N6OH
A plant-based cellulose derivative used as a binder to hold tablet ingredients together, a thickener in liquids, and a coating agent to control how fast the medicine dissolves.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 7T9FYH5QMK
A plant-derived powder that serves as a binder and filler in tablets and capsules. It helps hold ingredients together, adds bulk, and aids in smooth tablet disintegration when swallowed.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII 532B59J990
Polyvinyl alcohol is a synthetic polymer made from plant-derived materials. It's used as a binder to hold ingredients together, a film-former in coatings, and a thickener in liquid formulations.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 5856J3G2A2
A starch-based powder made from potatoes and processed with sodium. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the medicine can be absorbed.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
10 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Nexletol 180 mgthis 72426-0118-09 | Esperion | 90 tablets | — | — | Discontinued | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 11744816 ↗ | Method of use | U-3883 | Mar 14, 2036 |
| US 11926584 ↗ | Method of use | U-3873 | Jun 19, 2040 |
| US 12404227 ↗ | Drug substance | U-4258 | Jun 19, 2040 |
| US 11760714 ↗ | Drug product | — | Jun 19, 2040 |
| US 7335799 ↗ | Drug substance | — | Dec 3, 2030 |
| US 12398087 ↗ | Drug substance | — | Jun 19, 2040 |
| US 11613511 ↗ | Drug substance | — | Jun 19, 2040 |
| Code | What it grants | Expires |
|---|---|---|
| I-943 | New indication (3-year) | Mar 22, 2027 |
| I-944 | New indication (3-year) | Mar 22, 2027 |
Is there a generic version of this drug?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 72426-0118-03 | 30 TABLET, FILM COATED in 1 BOTTLE, PLASTIC (72426-118-03) | $13.81 / ea | $414.17 | 2020-03-06 | Active |
| 72426-0118-09 You're viewing this | 90 TABLET, FILM COATED in 1 BOTTLE, PLASTIC (72426-118-09) | — | — | 2020-03-06 | Discontinued by firm |
| 72426-0118-99 | 7 TABLET, FILM COATED in 1 BLISTER PACK (72426-118-99) | — | — | 2020-03-06 | Active |
You're viewing the largest of 3 pack sizes for this product.
This pack shows little to no recent Medicaid volume — the 30 tablets pack carries most fills. See all packs ↓
Pack size FAQ
What quantity is in NDC 72426-0118-09?
What is the difference between NDC 72426-0118-09 and NDC 72426-0118-99?
What NDC number is used to bill for this package of Nexletol Bempedoic Acid 180 mg Tablet, Film Coated?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
What does the discontinued status mean for this NDC?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE NEXLETOL is indicated: to reduce the risk of major adverse cardiovascular events (cardiovascular death, myocardial infarction, stroke, or coronary revascularization) in adults at increased risk for these events who are unable to take recommended statin therapy (including those not taking a statin). as an adjunct to diet and exercise, in combination with other low-density lipoprotein cholesterol (LDL-C) lowering therapies, or alone when concomitant LDL-C lowering therapy is not possible, to reduce LDL-C in adults with hypercholesterolemia, including heterozygous familial hypercholesterolemia (HeFH).
NEXLETOL, an adenosine triphosphate-citrate lyase (ACL) inhibitor, is indicated: to reduce the risk of major adverse cardiovascular events (cardiovascular death, myocardial infarction, stroke, or coronary revascularization) in adults at increased risk for these events who are unable to take recommended statin therapy (including those not taking a statin). ( 1 ) as an adjunct to diet and exercise, in combination with other low-density lipoprotein cholesterol (LDL-C) lowering therapies, or alone when concomitant LDL-C lowering therapy is not possible, to reduce LDL-C in adults with hypercholesterolemia, including heterozygous familial hypercholesterolemia (HeFH).
( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Administer 180 mg orally once daily with or without food. ( 2.1 )
2.1Recommended Dosage The recommended dosage of NEXLETOL is 180 mg administered orally once daily. NEXLETOL can be taken with or without food. After initiation of NEXLETOL, analyze lipid levels within 8 to 12 weeks.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS NEXLETOL is available as: Tablets: 180 mg, white to off-white, oval shaped, debossed with "180" on one side and "ESP" on the other side. Tablets: 180 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS NEXLETOL is contraindicated in patients with a prior serious hypersensitivity reaction to bempedoic acid or any of the excipients in NEXLETOL. Serious hypersensitivity reactions, such as angioedema, have occurred [see Adverse Reactions (6.2) ]. History of a serious hypersensitivity reaction to bempedoic acid or any of the excipients in NEXLETOL. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hyperuricemia: Elevations in serum uric acid have occurred. Assess uric acid levels periodically as clinically indicated. Monitor for signs and symptoms of hyperuricemia, and initiate treatment with urate-lowering drugs as appropriate.
( 5.1 ) Tendon Rupture: Tendon rupture has occurred. Discontinue NEXLETOL at the first sign of tendon rupture. Avoid NEXLETOL in patients who have a history of tendon disorders or tendon rupture.
( 5.2 )
5.1Hyperuricemia NEXLETOL inhibits renal tubular OAT2 and may increase blood uric acid levels [see Clinical Pharmacology (12.3) ] . In the primary hypercholesterolemia trials [see Clinical Studies (14.2) ] , 26% of NEXLETOL-treated patients with normal baseline uric acid values (versus 9.5% placebo) experienced hyperuricemia one or more times, and 3.5% of patients experienced clinically significant hyperuricemia reported as an adverse reaction (versus 1.1% placebo). Increases in uric acid levels usually occurred within the first 4 weeks of treatment initiation, persisted throughout treatment, and returned to baseline following discontinuation of treatment.
After 12 weeks of treatment, the mean placebo-adjusted increase in uric acid compared to baseline was 0.8 mg/dL for patients treated with NEXLETOL. In the cardiovascular outcomes trial [see Clinical Studies (14.1) ], 16.4% of NEXLETOL-treated patients experienced clinically significant hyperuricemia reported as an adverse reaction (versus 8.2% placebo). Elevated blood uric acid may lead to the development of gout.
In the primary hypercholesterolemia trials, gout was reported in 1.5% of patients treated with NEXLETOL and 0.4% of patients treated with placebo. In the cardiovascular outcomes trial, gout was reported in 3.2% of patients treated with NEXLETOL and 2.2% treated with placebo. Advise patients to contact their healthcare provider if symptoms of hyperuricemia occur.
Assess serum uric acid when clinically indicated. Monitor patients for signs and symptoms of hyperuricemia, and initiate treatment with urate-lowering drugs as appropriate.
5.2Tendon Rupture NEXLETOL is associated with an increased risk of tendon rupture or injury. In the primary hypercholesterolemia trials [see Clinical Studies (14.2) ] , tendon rupture occurred in 0.5% of patients treated with NEXLETOL versus 0% of placebo-treated patients and involved the rotator cuff (the shoulder), biceps tendon, or Achilles tendon. Tendon rupture occurred within weeks to months of starting NEXLETOL.
In the cardiovascular outcomes trial [see Clinical Studies (14.1) ] , tendon rupture events occurred in 1.2% of NEXLETOL-treated patients versus 0.9% of placebo-treated patients. Tendon rupture may occur more frequently in patients over 60 years of age, in those taking corticosteroid or fluoroquinolone drugs, in patients with renal failure, and in patients with previous tendon disorders. Discontinue NEXLETOL immediately if the patient experiences rupture of a tendon.
Consider discontinuing NEXLETOL if the patient experiences joint pain, swelling, or inflammation. Advise patients to rest at the first sign of tendinitis or tendon rupture and to contact their healthcare provider if tendinitis or tendon rupture symptoms occur. Consider alternative therapy in patients with a history of tendon disorders or tendon rupture.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: Hyperuricemia [see Warnings and Precautions (5.1) ] Tendon Rupture [see Warnings and Precautions (5.2) ] Common adverse reactions in the ( 6.1 ): Primary hypercholesterolemia trials (incidence ≥ 2% and more frequent than placebo) were upper respiratory tract infection, muscle spasms, hyperuricemia, back pain, abdominal pain or discomfort, bronchitis, pain in extremity, anemia, and elevated liver enzymes.
Cardiovascular outcomes trial (incidence ≥ 2% and 0.5% greater than placebo) were hyperuricemia, renal impairment, anemia, elevated liver enzymes, muscle spasms, gout, and cholelithiasis. To report SUSPECTED ADVERSE REACTIONS, contact Esperion at 833-377-7633 (833 ESPRMED) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. The data in Table 1 reflect exposure to NEXLETOL in two placebo-controlled primary hypercholesterolemia trials that included 2,009 patients treated with NEXLETOL for 52 weeks (median treatment duration of 52 weeks) [see Clinical Studies (14.2) ] .
The mean age for NEXLETOL-treated patients was 65 years, 29% were female, 95% were White, 3% were Black or African American, 1% were Asian, and 1% were other races; 3% identified as Hispanic or Latino ethnicity. All patients received NEXLETOL 180 mg orally once daily plus maximally tolerated statin therapy alone or in combination with other lipid-lowering therapies. At baseline, 97% of patients had CVD and about 4% had a diagnosis of HeFH.
Patients on simvastatin 40 mg/day or higher were excluded from the trials. In the primary hypercholesterolemia trials, adverse reactions led to discontinuation of treatment in 11% of NEXLETOL-treated patients and 8% of placebo-treated patients. The most common reasons for NEXLETOL treatment discontinuation were muscle spasms (0.5% versus 0.3% placebo), diarrhea (0.4% versus 0.1% placebo), and pain in extremity (0.3% versus 0.0% placebo).
Adverse reactions reported in at least 2% of NEXLETOL-treated patients and more frequently than in placebo-treated patients are shown in Table 1. Table 1. Adverse Reactions (≥ 2% and greater than placebo) in NEXLETOL-Treated Patients with Primary Hypercholesterolemia and CVD or HeFH (Trials 2 and 3) Adverse Reaction Placebo Background therapy included statin and ± other lipid-lowering therapies (N = 999) % NEXLETOL (N = 2,009) % Upper respiratory tract infection 4.0
4.5Muscle spasms 2.3
3.6Hyperuricemia Grouped term that includes other related terms 1.1
3.5Back pain 2.2
3.3Abdominal pain or discomfort 2.2
3.1Bronchitis 2.5
3.0Pain in extremity 1.7
3.0Anemia 1.9
2.8Elevated liver enzymes 0.8
2.1In the cardiovascular outcomes trial, in which 7,001 patients were exposed to NEXLETOL and 6,964 patients were exposed to placebo for a median of 3.1 years [see Clinical Studies, (14.1) ] , adverse reactions led to discontinuation of treatment in 11% of NEXLETOL-treated patients and 10% of placebo-treated patients. Adverse reactions reported in at least 2% of NEXLETOL-treated patients and 0.5% greater than placebo are shown in Table 2. Table 2.
Adverse Reactions (≥ 2% and 0.5% greater than placebo) in NEXLETOL-Treated Patients with CVD or at High Risk for CVD (Trial 1) Adverse Reaction Placebo (N=6,964) % NEXLETOL (N=7,001) % Hyperuricemia Grouped term that includes other related terms 8 16 Renal impairment Renal impairment includes laboratory related terms including glomerular filtration rate decreased, blood creatinine increased and hematuria 9 11 Anemia 4 5 Elevated liver enzymes 3 4 Muscle spasms 3 4 Gout 2 3 Cholelithiasis 1 2 Other Adverse Reactions Tendon Rupture In the hyperchole…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Table 3 includes a list of drugs with clinically important drug interactions when administered concomitantly with NEXLETOL and instructions for preventing or managing them. Table 3. Clinically Important Drug Interactions with NEXLETOL Simvastatin Clinical Impact: Concomitant use of NEXLETOL with simvastatin causes an increase in simvastatin concentration and may increase the risk of simvastatin-related myopathy [see Clinical Pharmacology (12.3) ] .
Intervention : Avoid concomitant use of NEXLETOL with simvastatin greater than 20 mg. Pravastatin Clinical Impact: Concomitant use of NEXLETOL with pravastatin causes an increase in pravastatin concentration and may increase the risk of pravastatin-related myopathy [see Clinical Pharmacology (12.3) ] . Intervention: Avoid concomitant use of NEXLETOL with pravastatin greater than 40 mg.
Fibrates Clinical Impact: Concomitant administration of fibrates with NEXLETOL resulted in increased triglycerides and decreased high-density lipoprotein cholesterol (HDL-C) in some patients in clinical studies and post-marketing reports. Reversibility of both increased triglycerides and decreased HDL-C levels was observed when either NEXLETOL or fibrate therapy was discontinued. Intervention: Monitor triglycerides and HDL-C four weeks after initial concomitant use of NEXLETOL and a fibrate and periodically thereafter.
If increased triglycerides or decreased HDL-C levels are detected, discontinue NEXLETOL or fibrate therapy based on clinical judgment. Monitor triglycerides and HDL-C levels until levels return to baseline. Simvastatin: Avoid concomitant use of NEXLETOL with simvastatin greater than 20 mg.
( 7 ) Pravastatin: Avoid concomitant use of NEXLETOL with pravastatin greater than 40 mg. ( 7 ) Fibrates: Concomitant use of NEXLETOL with fibrates may increase triglycerides and decrease high-density lipoprotein cholesterol. ( 7 )
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Based on mechanism of action, may cause fetal harm. ( 8.1 )
8.1Pregnancy Risk Summary Discontinue NEXLETOL when pregnancy is recognized unless the benefits of therapy outweigh the potential risks to the fetus. There are insufficient data on NEXLETOL use in pregnant women to evaluate for a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. In animal reproduction studies, bempedoic acid was not teratogenic in rats and rabbits when administered at doses resulting in exposures up to 11 and 12 times, respectively, the human exposures at the maximum clinical dose, based on AUC (see Data ) .
NEXLETOL decreases cholesterol synthesis and possibly the synthesis of other biologically active substances derived from cholesterol; therefore, NEXLETOL may cause fetal harm when administered to pregnant women based on the mechanism of action [see Clinical Pharmacology (12.1) ] . In addition, treatment of hypercholesterolemia is not generally necessary during pregnancy. Atherosclerosis is a chronic process and the discontinuation of lipid-lowering drugs during pregnancy should have little impact on the outcome of long-term therapy of primary hypercholesterolemia for most patients.
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Report pregnancies to the Esperion Therapeutics, Inc.
Adverse Event reporting line at 1-833-377-7633. Data Animal Data Bempedoic acid was not teratogenic when given orally at doses of 60 and 80 mg/kg/day, resulting in 11 and 12 times the systemic exposure in humans at the maximum recommended human dose (MRHD) of 180 mg to pregnant rats and rabbits, respectively. In an embryofetal development study in rats, bempedoic acid was given orally to pregnant rats at 10, 30, and 60 mg/kg/day during the period of organogenesis from gestation day 6 to 17.
There were increases in the incidence of non-adverse fetal skeletal variations (bent long bones and bent scapula and incomplete ossification) at doses ≥ 10 mg/kg/day (less than the clinical exposure) in the absence of maternal toxicity. At maternally toxic doses, bempedoic acid caused decreases in the numbers of viable fetuses, increases in post-implantation loss, and increased total resorptions at 60 mg/kg/day (11 times MRHD) and reduced fetal body weight at ≥ 30 mg/kg/day (4 times the MRHD). No adverse development effects were observed when bempedoic acid was given to pregnant rabbits during the period of organogenesis (gestation day 6 to 18) at doses up to 80 mg/kg/day (12 times MRHD).
In a pre- and post-natal development study in pregnant rats given oral doses of bempedoic acid at 5, 10, 20, 30 and 60 mg/kg/day throughout pregnancy and lactation (gestation day 6 to lactation day 20), there were adverse effects on delivery in the presence of maternal toxicity, including: increases in stillborn pups, reductions in numbers of live pups, pup survival, pup growth and slight delays in learning and memory at ≥ 10 mg/kg/day (at exposures equivalent to the MRHD).
8.2Lactation Risk Summary Bempedoic acid was detected in breast milk of lactating women who received six consecutive daily doses of 180 mg bempedoic acid. The mean daily infant dose of bempedoic acid through breast milk was approximately 0.03 mg/day (95% CI: 0.02; 0.05) with a mean calculated daily infant oral dosage of 0.012 mg/kg/day based on a standard infant milk intake of 150 mL/kg/day. The mean (SD) relative infant dose (RID) was approximately 0.5 (0.2)% of the maternal weight-adjusted dosage (see Data ) .
Concentrations of ESP15228, the active metabolite, in breast milk were below the limit of quantitation (20 ng/mL) in 7 of 8 subjects studied. There is no information regarding the effects of NEXLETOL on…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Discontinue NEXLETOL when pregnancy is recognized unless the benefits of therapy outweigh the potential risks to the fetus. There are insufficient data on NEXLETOL use in pregnant women to evaluate for a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. In animal reproduction studies, bempedoic acid was not teratogenic in rats and rabbits when administered at doses resulting in exposures up to 11 and 12 times, respectively, the human exposures at the maximum clinical dose, based on AUC (see Data ) .
NEXLETOL decreases cholesterol synthesis and possibly the synthesis of other biologically active substances derived from cholesterol; therefore, NEXLETOL may cause fetal harm when administered to pregnant women based on the mechanism of action [see Clinical Pharmacology (12.1) ] . In addition, treatment of hypercholesterolemia is not generally necessary during pregnancy. Atherosclerosis is a chronic process and the discontinuation of lipid-lowering drugs during pregnancy should have little impact on the outcome of long-term therapy of primary hypercholesterolemia for most patients.
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Report pregnancies to the Esperion Therapeutics, Inc.
Adverse Event reporting line at 1-833-377-7633. Data Animal Data Bempedoic acid was not teratogenic when given orally at doses of 60 and 80 mg/kg/day, resulting in 11 and 12 times the systemic exposure in humans at the maximum recommended human dose (MRHD) of 180 mg to pregnant rats and rabbits, respectively. In an embryofetal development study in rats, bempedoic acid was given orally to pregnant rats at 10, 30, and 60 mg/kg/day during the period of organogenesis from gestation day 6 to 17.
There were increases in the incidence of non-adverse fetal skeletal variations (bent long bones and bent scapula and incomplete ossification) at doses ≥ 10 mg/kg/day (less than the clinical exposure) in the absence of maternal toxicity. At maternally toxic doses, bempedoic acid caused decreases in the numbers of viable fetuses, increases in post-implantation loss, and increased total resorptions at 60 mg/kg/day (11 times MRHD) and reduced fetal body weight at ≥ 30 mg/kg/day (4 times the MRHD). No adverse development effects were observed when bempedoic acid was given to pregnant rabbits during the period of organogenesis (gestation day 6 to 18) at doses up to 80 mg/kg/day (12 times MRHD).
In a pre- and post-natal development study in pregnant rats given oral doses of bempedoic acid at 5, 10, 20, 30 and 60 mg/kg/day throughout pregnancy and lactation (gestation day 6 to lactation day 20), there were adverse effects on delivery in the presence of maternal toxicity, including: increases in stillborn pups, reductions in numbers of live pups, pup survival, pup growth and slight delays in learning and memory at ≥ 10 mg/kg/day (at exposures equivalent to the MRHD).
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of NEXLETOL have not been established in pediatric patients.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the 3,009 adult patients in the primary hypercholesterolemia trials of NEXLETOL, 1,753 (58%) were 65 years of age and older, while 478 (16%) were 75 years of age and older. Of the 13,970 adult patients in the cardiovascular outcomes trial [see Clinical Studies (14.1) ] , 8,204 (59%) were 65 years of age and older, while 2,107 (15%) were 75 years of age and older. No overall differences in safety or effectiveness of NEXLETOL have been observed between patients 65 years of age and older and younger adult patients.
🆘 Overdosage ▾
10 OVERDOSAGE There is no clinical experience with NEXLETOL overdose. In the event of an overdosage, consider contacting the Poison Help line (1-800-222-1222) or a medical toxicologist for additional overdosage management recommendations.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Bempedoic acid is an adenosine triphosphate-citrate lyase (ACL) inhibitor that lowers LDL-C by inhibition of cholesterol synthesis in the liver. ACL is an enzyme upstream of 3-hydroxy-3-methyl-glutaryl-coenzyme A (HMG-CoA) reductase in the cholesterol biosynthesis pathway. Bempedoic acid and its active metabolite, ESP15228, require coenzyme A (CoA) activation by very long-chain acyl-CoA synthetase 1 (ACSVL1) to ETC-1002-CoA and ESP15228-CoA, respectively.
ACSVL1 is expressed primarily in the liver. Inhibition of ACL by ETC-1002-CoA results in decreased cholesterol synthesis in the liver and lowers LDL-C in blood via upregulation of low-density lipoprotein receptors.
12.2Pharmacodynamics Administration of bempedoic acid alone, or in combination with other lipid modifying agents, decreases LDL-C, non-high density lipoprotein cholesterol (non-HDL-C), apolipoprotein B (apo B), and total cholesterol (TC) in patients with hypercholesterolemia. Cardiac Electrophysiology At a dose of 240 mg (1.3 times the approved recommended dose), bempedoic acid does not prolong the QT interval to any clinically relevant extent.
12.3Pharmacokinetics Bempedoic acid pharmacokinetic parameters are presented as the mean [± standard deviation (SD)] unless otherwise specified. The steady-state maximum plasma concentration (C max ) and area under the curve (AUC) following multiple-dose administration of bempedoic acid at 180 mg/day were 20.6 ± 6.1 µg/mL and 289.0 ± 96.4 µg∙h/mL, respectively. Bempedoic acid steady-state pharmacokinetics were generally linear over a range of > 60 mg to 220 mg (approximately 33% to 122% of the recommended dosage of 180 mg daily).
There were no time-dependent changes in bempedoic acid pharmacokinetics following repeat administration at the recommended dosage, and bempedoic acid steady-state was achieved after 7 days. The mean accumulation ratio was approximately 2.3-fold. The steady-state C max and AUC of the active metabolite (ESP15228) of bempedoic acid were 2.8 ± 0.9 µg/mL and 51.2 ± 17.2 µg∙h/mL, respectively.
ESP15228 likely made a minor contribution to the overall clinical activity of bempedoic acid based on systemic exposure, relative potency, and pharmacokinetic properties. Absorption Pharmacokinetic data indicate that bempedoic acid is absorbed with a median time to maximum concentration of 3.5 hours when administered as NEXLETOL 180 mg tablets. Effect of Food Concomitant food administration had no effect on the oral bioavailability of bempedoic acid.
Distribution The bempedoic acid apparent volume of distribution (V/F) was 18 L. Plasma protein binding of bempedoic acid, its glucuronide and its active metabolite, ESP15228, were 99.3%, 98.8% and 99.2%, respectively. Bempedoic acid does not partition into blood cells.
Elimination The steady-state clearance (CL/F) of bempedoic acid was 11.2 mL/min after once-daily dosing; renal clearance of unchanged bempedoic acid represented less than 2% of total clearance. The mean ± SD half-life for bempedoic acid in humans was 21 ± 11 hours at steady-state. Metabolism The primary route of elimination for bempedoic acid is through metabolism of the acyl glucuronide.
Bempedoic acid is also reversibly converted to an active metabolite (ESP15228) based on aldo-keto reductase activity observed in vitro from human liver. Mean plasma AUC metabolite/parent drug ratio for ESP15228 following repeat-dose administration was 18% and remained constant over time. Both compounds are converted to inactive glucuronide conjugates in vitro by UGT2B7.
Bempedoic acid, ESP15228 and their respective conjugated forms were detected in plasma with bempedoic acid accounting for the majority (46%) of the AUC 0-48h and its glucuronide being the next most prevalent (30%). ESP15228 and its glucuronide represented 10% and 11% of the plasma AUC 0-48h , respectively. Excretion Following single oral administration of 240 mg of bempedoic acid (1.3 times the approved…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Bempedoic acid is an adenosine triphosphate-citrate lyase (ACL) inhibitor that lowers LDL-C by inhibition of cholesterol synthesis in the liver. ACL is an enzyme upstream of 3-hydroxy-3-methyl-glutaryl-coenzyme A (HMG-CoA) reductase in the cholesterol biosynthesis pathway. Bempedoic acid and its active metabolite, ESP15228, require coenzyme A (CoA) activation by very long-chain acyl-CoA synthetase 1 (ACSVL1) to ETC-1002-CoA and ESP15228-CoA, respectively.
ACSVL1 is expressed primarily in the liver. Inhibition of ACL by ETC-1002-CoA results in decreased cholesterol synthesis in the liver and lowers LDL-C in blood via upregulation of low-density lipoprotein receptors.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING How Supplied NEXLETOL tablets are supplied as follows: Tablet Strength Description Package Configuration NDC No. 180 mg White to off white and oval, debossed with "180" on one side and "ESP" on the other side Bottle of 30 tablets with child-resistant cap 72426-118-03 Storage and Handling Store at 68°F to 77°F (20°C to 25°C); excursions permitted to 59°F to 86°F (15°C to 30°C) [see USP Controlled Room Temperature] . Store and dispense in the original package.
📦 Storage and Handling ▾
Storage and Handling Store at 68°F to 77°F (20°C to 25°C); excursions permitted to 59°F to 86°F (15°C to 30°C) [see USP Controlled Room Temperature] . Store and dispense in the original package.
📋 Description ▾
11 DESCRIPTION NEXLETOL tablets, for oral use, contain bempedoic acid, an adenosine triphosphate-citrate lyase (ACL) inhibitor. The chemical name for bempedoic acid is 8-hydroxy-2,2,14,14-tetramethyl-pentadecanedioic acid. The molecular formula is C 19 H 36 O 5 , and the molecular weight is 344.5 grams per mole.
Bempedoic acid is a white to off-white crystalline powder that is highly soluble in ethanol, isopropanol and pH 8 phosphate buffer, and insoluble in water and aqueous solutions below pH 5. Structural formula: Each film-coated tablet of NEXLETOL contains 180 mg of bempedoic acid and the following inactive ingredients: colloidal silicon dioxide, hydroxyl propyl cellulose, lactose monohydrate, magnesium stearate, microcrystalline cellulose, and sodium starch glycolate. The film coating comprises of partially hydrolyzed polyvinyl alcohol, polyethylene glycol, talc, and titanium dioxide.
Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise patients to read the FDA-approved patient labeling (Patient Information). Risk of Hyperuricemia Advise patients of the risk of elevated serum uric acid levels, including development of gout. Inform patients that serum uric acid levels may be monitored during treatment with NEXLETOL.
Patients with signs or symptoms of hyperuricemia should contact their healthcare provider if symptoms occur [See Warnings and Precautions (5.1) ] Risk of Tendon Rupture Inform patients of the risk of tendon rupture. Advise patients to rest at the first sign of tendinitis or tendon rupture and to immediately contact their healthcare provider if tendinitis or tendon rupture symptoms occur [see Warnings and Precautions (5.2) ]. Risk of Myopathy with Concomitant Use of Simvastatin or Pravastatin Advise patients to notify their healthcare provider(s) if they are taking, or plan to take simvastatin or pravastatin.
The risk of myopathy occurring with the use of simvastatin or pravastatin may be increased when taken with NEXLETOL [see Drug Interactions (7) ]. Pregnancy Advise pregnant women of the potential risk to a fetus based on NEXLETOL's mechanism of action. Advise females to inform their healthcare provider of a known or suspected pregnancy.
Advise patients that there is a pregnancy safety study that monitors pregnancy outcomes in patients exposed to NEXLETOL during pregnancy. Encourage these patients to report their pregnancy to Esperion at 1-833-377-7633 [see Use in Specific Populations (8.1) ].