
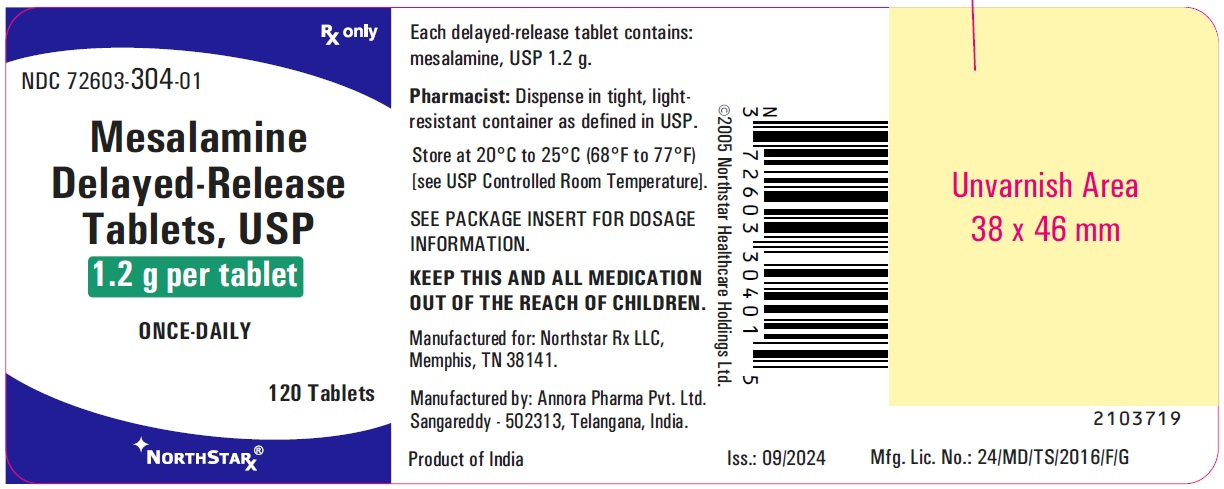
Mesalamine 1.2 g Tablet, Delayed Release, 120-count — NDC 72603-304-01 (Billing 72603-0304-01)
This is a package of 120 tablets of Mesalamine 1.2 g Tablet, Delayed Release from NorthStar RxLLC, marketed since Dec 2024 and currently FDA-listed; retail pharmacies pay about $0.7809 per tablet (NADAC). It is this product's only package size.
Other active recalls for Mesalamine (different manufacturers) — 1 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 062058
- GCN: 97842
- GPI-14 (Medi-Span): 52500030000670
- HICL (First Databank): 001848
- AHFS class code: 56:36.00.00
- RxCUI (RxNorm): 686429
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Aminosalicylate class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Mesalamine is used to treat ulcerative colitis (a condition which causes swelling and sores in the lining of the colon [large intestine] and rectum) and also to maintain improvement of ulcerative colitis symptoms. Mesalamine is in a class of medications called anti-inflammatory agents. It works by stopping the body from producing a certain substance that may cause inflammation.
Read the full MedlinePlus article ↗- It treats ulcerative colitis and, in rectal forms, inflammation in the lower bowel such as proctitis. Some products are for flares, some for keeping remission, and some for both. Y...
- It depends on your product. Tablets and most capsules are swallowed whole. Rectal forms are usually used at bedtime. Drink plenty of fluids, and follow your label for food and timi...
- Headache, gas, belly pain and diarrhea are the common ones. Call your doctor if you get severe cramping with bloody diarrhea, fever or rash, since that could be a reaction to the d...
- Yes. Your kidney function should be checked before starting and periodically after. If you take azathioprine or 6-mercaptopurine, or are 65 or older, blood counts should be monitor...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Mesalamine — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.781 | $93.71 / 120 tablets |
| Medicaid paysCMS SDUD · 12 mo | $1.29 | $155.39 / 120 tablets |
| Medicare drug plans payPart D · Q2 2026 | $1.71 | $205.00 / 120 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 72603-0304-01 You're viewing this Main listing | 120 TABLET, DELAYED RELEASE in 1 BOTTLE | 2024-12-01 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Mesalamine 1.2 g 00527-3012-48 | Lannett | 120 tablets | $0.781 | AB | Availability likely | — |
| Mesalamine 1.2 g 00591-2245-22 | Actavis | 120 tablets | $0.781 | AB | Availability likely | — |
| mesalamine 1.2 g 00904-6832-04 | Major | 1 tablet | $0.781 | AB | Availability likely | — |
| Mesalamine 1.2 g 60687-0397-25 | American | 1 tablet | $0.781 | AB | Availability likely | — |
| Mesalamine 1.2 g 62135-0714-12 | Chartwell | 120 tablets | $0.781 | AB | Availability likely | — |
| Mesalamine 1.2 g 63304-0175-13 | Sun | 120 tablets | $0.781 | AB | Availability likely | — |
| mesalamine 1.2 g 68382-0711-19 | Zydus | 120 tablets | $0.781 | AB | Availability likely | — |
| Mesalamine 1.2 gthis 72603-0304-01 | NorthStar | 120 tablets | $0.781 | AB | Availability likely | — |
| Mesalamine 1.2 g 54092-0100-01 | Takeda | 120 tablets | $0.795 | AB | Availability likely | +2% |
| Lialda 1.2 g 54092-0476-01 | Takeda | 120 tablets | $8.947 | AB | Availability likely | +1046% |
| Mesalamine 1.2 g 31722-0043-05 | Camber | 500 tablets | — | AB | FDA listed | — |
| mesalamine 1.2 g 51407-0900-12 | Golden | 120 tablets | — | AB | FDA listed | — |
| mesalamine 1.2 g 70771-1071-01 | Zydus | 120 tablets | — | AB | FDA listed | — |
| Mesalamine 1.2 g 72162-2213-02 | Bryant | 120 tablets | — | AB | FDA listed | — |
| Mesalamine 1.2 g 72162-2231-02 | Bryant | 120 tablets | — | AB | FDA listed | — |
| Mesalamine 1.2 g 84612-0175-13 | Nuvaila | 120 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 5138Q19F1X
Ammonia is a colorless gas made from nitrogen and hydrogen. It's used in medicines as a pH buffer to maintain the correct acidity level and help keep the product stable.
-
UNII 619G5K328Y
A yellow-to-reddish powder form of cerium, a rare earth element. Used as a polishing agent and anti-caking ingredient to keep powders free-flowing and prevent clumping in solid dosage forms.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII B1QE5P712K
Hypromellose 2208 is a plant-derived thickening agent that dissolves in water. It's used as a binder to help hold tablet ingredients together and as a coating on pills to control how quickly the medicine releases in your body.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 74G4R6TH13
A synthetic polymer made by combining two plastic-like chemicals. It forms a coating on tablets or capsules that dissolves at a specific point in the digestive tract, controlling where and when the medicine releases.
-
UNII 5KY68S2577
A synthetic plastic polymer made from two chemical compounds combined in a specific ratio. It forms a coating on tablets and capsules to control how and where the medication dissolves in the digestive tract.
-
UNII PNR0YF693Y
A plant-based powder made from purified wood cellulose. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in the stomach.
-
UNII 30IQX730WE
Polyethylene glycol 6000 is a synthetic polymer made from ethylene glycol units. It acts as a binder, filler, and solubilizer in medicines to help hold ingredients together, add bulk, and improve how well active drugs dissolve and absorb.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 46N107B71O
Shellac is a natural resin secreted by the lac beetle. It's used as a coating on tablets and capsules to control how quickly the medicine dissolves and to improve appearance and stability.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII H8AV0SQX4D
A modified starch derived from potato or corn starch. It absorbs water quickly and helps tablets or capsules break apart and dissolve in the stomach, acting as a disintegrant to ensure the medicine releases its active ingredients properly.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII 8Z96QXD6UM
Triethyl citrate is a clear liquid derived from citric acid. It acts as a plasticizer and solvent in tablet coatings and film formulations, helping the coating remain flexible and adhere properly to the medicine.
16 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Mesalamine delayed-release tablets are indicated for the: · induction and maintenance of remission in adult patients with mildly to moderately active ulcerative colitis. · treatment of mildly to moderately active ulcerative colitis in pediatric patients weighing at least 24 kg. Mesalamine delayed-release tablet is an aminosalicylate indicated for the: • induction and maintenance of remission in adult patients with mildly to moderately active ulcerative colitis. ( 1 ) • treatment of mildly to moderately active ulcerative colitis in pediatric patients weighing at least 24 kg.
( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Administration Instructions • Evaluate renal function prior to initiation of mesalamine delayed-release tablets and periodically while on therapy. • Swallow mesalamine delayed-release tablets whole; do not split or crush. • Administer mesalamine delayed-release tablets with food [see Clinical Pharmacology ( 12.3 )] . • Drink an adequate amount of fluids [see Warnings and Precautions ( 5.8 )] . Adults • The recommended dosage for the induction of remission in adult patients with mildly to moderately active ulcerative colitis is 2.4 g to 4.8 g (two to four 1.2 g tablets) taken once daily. • The recommended dosage for the maintenance of remission is 2.4 g (two 1.2 g tablets) taken once daily.
Pediatric Patients The recommended dosage for treatment of mildly to moderately active ulcerative colitis in pediatric patients weighing at least 24 kg who can swallow tablets whole is shown in Table 1: Table 1: Recommended Dosage of Mesalamine Delayed-release Tablets for the Treatment of Mildly to Moderately Active Ulcerative Colitis in Pediatric Patients Weighing at least 24 kg Weight of Pediatric Patient Once Daily Mesalamine Delayed-release Tablets Dosage Week 0 to Week 8 After Week 8 24 kg to 35 kg 2.4 g (two 1.2 g tablets) 1.2 g (one 1.2 g tablet) Greater than 35 kg to 50 kg 3.6 g (three 1.2 g tablets) 2.4 g (two 1.2 g tablets) Greater than 50 kg 4.8 g (four 1.2 g tablets) 2.4 g (two 1.2 g tablets) Administration Instructions • Evaluate renal function prior to initiation of mesalamine delayed-release tablets and periodically while on therapy.
( 2 , 5.1 ) • Swallow mesalamine delayed-release tablets whole; do not split or crush. ( 2 ) • Administer mesalamine delayed-release tablets with food. ( 2 ) • Drink an adequate amount of fluids.
( 2 , 5.8 ) Recommended Dosage in Adults • For induction of remission : 2.4 g to 4.8 g (two to four 1.2 g tablets) once daily. ( 2 ) • For maintenance of remission : 2.4 g (two 1.2 g tablets) once daily. ( 2 ) Recommended Dosage in Pediatric Patients • The recommended dosage for treatment of mildly to moderately active ulcerative colitis in pediatric patients weighing at least 24 kg who can swallow tablets whole is shown below: ( 2 ) Weight of Pediatric Patient Once Daily Mesalamine Delayed-Release Tablets Dosage Week 0 to Week 8 After Week 8 24 kg to 35 kg 2.4 g (two 1.2 g tablets) 1.2 g (one 1.2 g tablet) Greater than 35 kg to 50 kg 3.6 g (three 1.2 g tablets) 2.4 g (two 1.2 g tablets) Greater than 50 kg 4.8 g (four 1.2 g tablets) 2.4 g (two 1.2 g tablets)
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS The reddish-brown, oval-shaped, enteric-coated tablets containing 1.2 g mesalamine is imprinted with “M19” in black color on one side and plain on other side. Delayed-Release Tablets: 1.2 g ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Mesalamine is contraindicated in patients with known or suspected hypersensitivity to salicylates, aminosalicylates, or to any of the ingredients of mesalamine [see Warnings and Precautions ( 5.3 ), Adverse Reactions ( 6.2 ), Description ( 11 )] . Known or suspected hypersensitivity to salicylates or aminosalicylates or to any of the ingredients of mesalamine. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Renal Impairment : Assess renal function at the beginning of treatment and periodically during treatment. Evaluate the risks and benefits of mesalamine in patients with known renal impairment or taking nephrotoxic drugs. Discontinue mesalamine if renal function deteriorates while on therapy.
( 5.1 , 7.1 , 8.6 ) • Mesalamine-Induced Acute Intolerance Syndrome : Symptoms may be difficult to distinguish from an ulcerative colitis exacerbation. Monitor for worsening symptoms while on treatment. Discontinue treatment if acute intolerance syndrome is suspected.
( 5.2 ) • Hypersensitivity Reactions, including myocarditis and pericarditis : Evaluate patients immediately and discontinue mesalamine if a hypersensitivity reaction is suspected. ( 5.3 ) • Hepatic Failure : Evaluate the risks and benefits of using mesalamine in patients with known liver impairment. ( 5.4 ) • Severe Cutaneous Adverse Reactions : Discontinue at the first signs or symptoms of severe cutaneous adverse reactions or other signs of hypersensitivity and consider further evaluation.
( 5.5 ) • Upper Gastrointestinal Tract Obstruction : Avoid in patients with pyloric stenosis or other organic or functional obstruction. ( 5.6 ) • Photosensitivity: Advise patients with pre-existing skin conditions to avoid sun exposure, wear protective clothing, and use a broad-spectrum sunscreen when outdoors. ( 5.7 ) • Nephrolithiasis : Cases of nephrolithiasis have been reported with the use of mesalamine.
Mesalamine-containing stones are undetectable by standard radiography or computed tomography (CT). Ensure adequate hydration during treatment. ( 5.8 ) • Interference With Laboratory Tests : Use of mesalamine may lead to spuriously elevated test results when measuring urinary normetanephrine by liquid chromatography with electrochemical detection.
( 5.9 )
5.1Renal Impairment Renal impairment, including minimal change disease, acute and chronic interstitial nephritis, and, rarely, renal failure, has been reported in patients given products such as mesalamine that contain mesalamine or are converted to mesalamine. In animal studies, the kidney was the principal organ of mesalamine toxicity [see Adverse Reactions ( 6.2 ), Nonclinical Toxicology ( 13.2 )] . Evaluate renal function prior to initiation of mesalamine therapy and periodically while on therapy.
Evaluate the risks and benefits of using mesalamine in patients with known renal impairment, history of renal disease, or taking concomitant nephrotoxic drugs. Discontinue mesalamine if renal function deteriorates while on therapy [see Drug Interactions ( 7.1 ), Use in Specific Populations ( 8.6 )] .
5.2Mesalamine-Induced Acute Intolerance Syndrome Mesalamine has been associated with an acute intolerance syndrome that may be difficult to distinguish from an exacerbation of ulcerative colitis. Although the exact frequency of occurrence has not been determined, it has occurred in 3% of patients in controlled clinical trials of mesalamine or sulfasalazine. Symptoms include cramping, acute abdominal pain, and bloody diarrhea, and sometimes fever, headache, and rash.
Monitor patients closely for worsening of these symptoms while on treatment. If acute intolerance syndrome is suspected, promptly discontinue treatment with mesalamine.
5.3Hypersensitivity Reactions Hypersensitivity reactions have been reported in patients taking sulfasalazine. Some of these patients may have a similar reaction to mesalamine delayed-release tablets or to other compounds that contain or are converted to mesalamine. As with sulfasalazine, mesalamine-induced hypersensitivity reactions may present as internal organ involvement, including myocarditis, pericarditis, nephritis, hepatitis, pneumonitis, and hematologic abnormalities.
Evaluate patients immediately if signs or symptoms of a hypersensitivity reaction are present. Discontinue mesalamine if an alternative etiology for the signs or symptoms cannot be established.
5.4Hepatic F… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in labeling: • Renal impairment, including renal failure [see Warnings and Precautions ( 5.1 )] • Mesalamine-induced acute intolerance syndrome [see Warnings and Precautions ( 5.2 )] • Hypersensitivity reactions [see Warnings and Precautions ( 5.3 )] • Hepatic failure [see Warnings and Precautions ( 5.4 )] • Severe cutaneous adverse reactions [see Warnings and Precautions ( 5.5 )] • Upper gastrointestinal tract obstruction [see Warnings and Precautions ( 5.6 )] • Photosensitivity [see Warnings and Precautions ( 5.7 )] • Nephrolithiasis [see Warnings and Precautions ( 5.8 )] Most common adverse reactions in: • adults (≥2%) are headache, flatulence, liver function test abnormal, abdominal pain, and diarrhea.
( 6.1 ) • pediatric patients (≥5%) are abdominal pain, upper respiratory tract infection, vomiting, anemia, headache, and viral infection. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact NorthStar Rx LLC at 1-800-206-7821 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adults Induction The most common adverse reactions occurring in at least 1% of mesalamine-or placebo-treated adult patients with mildly to moderately active ulcerative colitis in two eight-week, randomized, double-blind, placebo-controlled trials (Study 1 and Study 2) [see Clinical Studies ( 14.1 )] are listed in Table 2.
Table 2: Adverse Reactions* in Two Eight-Week, Placebo-Controlled Trials of Induction Therapy (Study 1 and Study 2) in Adults with Mildly to Moderately Active Ulcerative Colitis Adverse Reaction Mesalamine 2.4 g once daily (n=177) Mesalamine 4.8 g once daily (n=179) Placebo (n=179) Headache 6% 3% <1% Flatulence 4% 3% 3% Liver Function Test Abnormal <1% 2% 1% Alopecia 0 1% 0 Pruritus <1% 1% 1% *Reported in at least 1% of patients in at least one mesalamine group and greater than placebo Pancreatitis occurred in less than 1% of patients during induction in clinical trials and resulted in discontinuation of therapy with mesalamine in patients experiencing this event.
Maintenance of Remission A mesalamine dosage of 2.4 g/day, administered as either 1.2 g twice daily or 2.4 g once daily, was evaluated for safety in three maintenance trials in patients with mildly to moderately active ulcerative colitis: a 6-month double-blind, active-controlled study (Study 3) [see Clinical Studies ( 14.1 )] and two 12- to 14-month open-label studies. The most common adverse reactions with mesalamine in these maintenance trials are listed in Table 3. Table 3: Adverse Reactions* in Three Trials of Maintenance of Remission in Adults with Ulcerative Colitis Mesalamine 2.4 g/day † (n=1082) Adverse Reaction % Headache 3% Liver function test abnormal 2% Abdominal pain 2% Diarrhea 2% Abdominal distension 1% Abdominal pain upper 1% Dyspepsia 1% Back pain 1% Rash 1% Arthralgia 1% Fatigue 1% Hypertension 1% *Reported in at least 1% of patients † Administered either as 1.2 g twice daily or 2.4 g once daily The following adverse reactions, presented by body system, were reported in less than 1% of mesalamine -treated patients with ulcerative colitis in either induction or maintenance trials: Cardiac Disorder : tachycardia Ear and Labyrinth Disorders : ear pain Gastrointestinal Disorders : abdominal distention, colitis, diarrhea, flatulence, nausea, pancreatitis, rectal polyp, vomiting General Disorders and Administrative Site Disorders : asthenia, face edema, fatigue, pyrexia Investigations : decreased platelet count Musculoskeletal and Connective Tissue Disorders : arthralgia, back pain Nervous System Disorders : dizziness, somnolence, tremor Respiratory, Thoracic and Mediastinal… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Nephrotoxic Agents including NSAIDs : Increased risk of nephrotoxicity; monitor for changes in renal function and mesalamine-related adverse reactions. ( 7.1 ) • Azathioprine or 6-Mercaptopurine : Increased risk of blood dyscrasias; monitor complete blood cell counts and platelet counts. ( 7.2 )
7.1Nephrotoxic Agents, Including Non-Steroidal Anti-Inflammatory Drugs The concurrent use of mesalamine with known nephrotoxic agents, including non-steroidal anti-inflammatory drugs (NSAIDs), may increase the risk of nephrotoxicity. Monitor patients taking nephrotoxic drugs for changes in renal function and mesalamine-related adverse reactions [see Warnings and Precautions ( 5.1 )].
7.2Azathioprine and 6-Mercaptopurine The concurrent use of mesalamine with azathioprine or 6-mercaptopurine and/or any other drugs known to cause myelotoxicity may increase the risk for blood disorders, bone marrow failure, and associated complications. If concomitant use of mesalamine and azathioprine or 6-mercaptopurine cannot be avoided, monitor blood tests, including complete blood cell counts and platelet counts.
7.3Interference with Urinary Normetanephrine Measurements Use of mesalamine may lead to spuriously elevated test results when measuring urinary normetanephrine by liquid chromatography with electrochemical detection [see Warnings and Precautions ( 5.9 )]. Consider an alternative, selective assay for normetanephrine.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Geriatric Patients : Increased risk of blood dyscrasias; monitor complete blood cell counts and platelet counts. ( 8.5 )
8.1Pregnancy Risk Summary Published data from meta-analyses, cohort studies, and case series on the use of mesalamine during pregnancy have not reliably informed an association with mesalamine and major birth defects, miscarriage, or adverse maternal or fetal outcomes (see Data). There are adverse effects on maternal and fetal outcomes associated with ulcerative colitis in pregnancy (see Clinical Considerations). In animal reproduction studies, there were no adverse developmental outcomes with administration of oral mesalamine during organogenesis to pregnant rats and rabbits at doses 1.8 and 2.9 times, respectively, the maximum recommended human dose (see Data).
The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriages in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Disease-associated maternal and embryo/fetal risk Published data suggest that increased disease activity is associated with the risk of developing adverse pregnancy outcomes in women with ulcerative colitis. Adverse pregnancy outcomes include preterm delivery (before 37 weeks of gestation), low birth weight (less than 2500 g) infants, and small for gestational age at birth. Data Human Data Published data from meta-analyses, cohort studies, and case series on the use of mesalamine during early pregnancy (first trimester) and throughout pregnancy have not reliably informed an association of mesalamine and major birth defects, miscarriage, or adverse maternal or fetal outcomes.
There is no clear evidence that mesalamine exposure in early pregnancy is associated with an increased risk of major congenital malformations, including cardiac malformations. Published epidemiologic studies have important methodological limitations which hinder interpretation of the data, including inability to control for confounders, such as underlying maternal disease, maternal use of concomitant medications, and missing information on the dose and duration of use for mesalamine products. Animal Data Reproduction studies with mesalamine during organogenesis have been performed in rats at doses up to 1000 mg/kg/day (1.8 times the maximum recommended human dose based on a body surface area comparison) and rabbits at doses up to 800 mg/kg/day (2.9 times the maximum recommended human dose based on a body surface area comparison) and have revealed no evidence of harm to the fetus due to mesalamine.
8.2Lactation Risk Summary Data from published literature report the presence of mesalamine and its metabolite, N-acetyl-5-aminosalicylic acid in human milk in small amounts with relative infant doses (RID) of 0.1% or less for mesalamine (see Data). There are case reports of diarrhea in breastfed infants exposed to mesalamine (see Clinical Considerations). There is no information on the effects of the drug on milk production.
The lack of clinical data during lactation precludes a clear determination of the risk of mesalamine to an infant during lactation; therefore, the developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for mesalamine and any potential adverse effects on the breastfed child from mesalamine or from the underlying maternal condition. Clinical Considerations Advise the caregiver to monitor the breastfed infant for diarrhea. Data In published lactation studies, maternal mesalamine doses from various oral and rectal formulations and products ranged from 500 mg to 4.8 g daily.
The average concentration of mesalamine in milk ranged from non-detectable to 0.5 mg/L. The average concentration… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Published data from meta-analyses, cohort studies, and case series on the use of mesalamine during pregnancy have not reliably informed an association with mesalamine and major birth defects, miscarriage, or adverse maternal or fetal outcomes (see Data). There are adverse effects on maternal and fetal outcomes associated with ulcerative colitis in pregnancy (see Clinical Considerations). In animal reproduction studies, there were no adverse developmental outcomes with administration of oral mesalamine during organogenesis to pregnant rats and rabbits at doses 1.8 and 2.9 times, respectively, the maximum recommended human dose (see Data).
The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriages in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Disease-associated maternal and embryo/fetal risk Published data suggest that increased disease activity is associated with the risk of developing adverse pregnancy outcomes in women with ulcerative colitis. Adverse pregnancy outcomes include preterm delivery (before 37 weeks of gestation), low birth weight (less than 2500 g) infants, and small for gestational age at birth. Data Human Data Published data from meta-analyses, cohort studies, and case series on the use of mesalamine during early pregnancy (first trimester) and throughout pregnancy have not reliably informed an association of mesalamine and major birth defects, miscarriage, or adverse maternal or fetal outcomes.
There is no clear evidence that mesalamine exposure in early pregnancy is associated with an increased risk of major congenital malformations, including cardiac malformations. Published epidemiologic studies have important methodological limitations which hinder interpretation of the data, including inability to control for confounders, such as underlying maternal disease, maternal use of concomitant medications, and missing information on the dose and duration of use for mesalamine products. Animal Data Reproduction studies with mesalamine during organogenesis have been performed in rats at doses up to 1000 mg/kg/day (1.8 times the maximum recommended human dose based on a body surface area comparison) and rabbits at doses up to 800 mg/kg/day (2.9 times the maximum recommended human dose based on a body surface area comparison) and have revealed no evidence of harm to the fetus due to mesalamine.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of mesalamine have been established for the treatment of mildly to moderately active ulcerative colitis in pediatric patients weighing at least 24 kg. Use of mesalamine in this population is supported by evidence from adequate and well-controlled trials in adults, a multicenter, randomized, double-blind, parallel group trial in 105 pediatric patients 5 to 17 years of age, and additional pharmacokinetic analyses. The safety profile in pediatric patients was similar to that observed in adults [see Adverse Reactions ( 6.1 ), Clinical Pharmacology ( 12.3 ), Clinical Studies ( 14.2 )] .
The safety and effectiveness of mesalamine have not been established in patients weighing less than 24 kg.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical trials of mesalamine did not include sufficient numbers of patients aged 65 years and over to determine whether they respond differently from younger patients. Reports from uncontrolled clinical studies and postmarketing reporting systems suggested a higher incidence of blood dyscrasias (i.e., agranulocytosis, neutropenia, and pancytopenia) in patients who were 65 years or older who were taking mesalamine-containing products such as mesalamine compared to younger patients. Monitor complete blood cell counts and platelet counts in elderly patients during treatment with mesalamine.
Systemic exposures are increased in elderly subjects [see Clinical Pharmacology ( 12.3 )]. In general, consider the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy in elderly patients when prescribing mesalamine. Consider starting at the low end of the dosing range for induction in elderly patients [see Dosage and Administration ( 2 ), Use in Specific Populations ( 8.6 )].
🆘 Overdosage ▾
10 OVERDOSAGE Mesalamine is an aminosalicylate, and symptoms of salicylate toxicity may include nausea, vomiting, abdominal pain, tachypnea, hyperpnea, tinnitus, and neurologic symptoms (headache, dizziness, confusion, seizures). Severe intoxication with salicylates may lead to electrolyte and blood pH imbalance, and potentially end organ (e.g., renal and liver) damage. There is no specific known antidote for mesalamine overdose; however, conventional therapy for salicylate toxicity may be beneficial in the event of acute overdosage and may include gastrointestinal tract decontamination to prevent further absorption.
Correct fluid and electrolyte imbalance by the administration of appropriate intravenous therapy and maintain adequate renal function. Mesalamine is a pH-dependent, delayed-release product and this factor should be considered when treating a suspected overdose.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The mechanism of action of mesalamine is not fully understood, but it appears to have a topical anti-inflammatory effect on the colonic epithelial cells. Mucosal production of arachidonic acid metabolites, both through the cyclooxygenase and lipoxygenase pathways, is increased in patients with ulcerative colitis, and it is possible that mesalamine diminishes inflammation by blocking cyclooxygenase and inhibiting prostaglandin production in the colon.
12.3Pharmacokinetics Absorption The total absorption of mesalamine from mesalamine 2.4 g or 4.8 g given once daily for 14 days to healthy subjects was found to be approximately 21% to 22% of the administered dose. Gamma-scintigraphy studies have shown that a single dose of mesalamine 1.2 g (one tablet) passed intact through the upper gastrointestinal tract of fasted healthy subjects. Scintigraphic images showed a trail of radio-labeled tracer in the colon, suggesting that mesalamine had distributed through this region of the gastrointestinal tract.
In a single-dose study, mesalamine 1.2 g, 2.4 g, and 4.8 g were administered in the fasted state to healthy subjects. Plasma concentrations of mesalamine were detectable after 2 hours and reached a maximum by 9 to 12 hours on average for the doses studied. The pharmacokinetic parameters are highly variable among subjects (Table 4).
Mesalamine systemic exposure in terms of area under the plasma concentration-time curve (AUC) was slightly more than dose proportional between 1.2 g and 4.8 g mesalamine. Maximum plasma concentrations (C max ) of mesalamine increased approximately dose proportionately between 1.2 g and 2.4 g and sub-proportionately between 2.4 g and 4.8 g of mesalamine, with the dose normalized value at 4.8 g representing, on average, 74% of that at 2.4 g based on geometric means. Table 4: Mean (SD) Pharmacokinetic Parameters for Mesalamine Following Single-Dose Administration of Mesalamine Under Fasting Conditions Parameter* of Mesalamine Mesalamine 1.2 g (N=47) Mesalamine 2.4 g (N=48) Mesalamine 4.8 g (N=48) AUC 0-t (ng⋅h/mL) 9039 † (5054) 20538 (12980) 41434 (26640) AUC 0-∞ (ng⋅h/mL) 9578 ‡ (5214) 21084 (13185) 44775 § (30302) C max (ng/mL) 857 (638) 1595 (1484) 2154 (1140) T max ¶ (h) 9.0 # (4.0 to 32.1) 12.0 (4.0 to 34.1) 12.0 (4.0 to 34.0) T lag ¶ (h) 2.0 # (0 to 8.0) 2.0 (1.0 to 4.0) 2.0 (1.0 to 4.0) T 1/2 (h) (Terminal Phase) 8.56 ‡ (6.38) 7.05 Þ (5.54) 7.25 § (8.32) * Arithmetic mean of parameter values are presented except for T max and T lag . † N=43, ‡ N=27, § N=36, ¶ Median (min, max), # N=46, Þ N=33 Food Effects Administration of a single dose of mesalamine 4.8 g with a high-fat meal resulted in further delay in absorption, and plasma concentrations of mesalamine were detectable 4 hours following dosing.
However, a high-fat meal increased systemic exposure of mesalamine (mean C max : increased 91%; mean AUC: increased 16%) compared to results in the fasted state. mesalamine was administered with food in the controlled clinical trials [see Dosage and Administration ( 2 )]. In a single- and multiple-dose pharmacokinetic study of mesalamine, 2.4 g or 4.8 g was administered once daily with standard meals to 28 healthy subjects per dose group. Plasma concentrations of mesalamine were detectable after 4 hours and were maximal by 8 hours after the single dose.
Steady state was achieved generally by 2 days after dosing. Mean AUC at steady state was only modestly greater (1.1- to 1.4-fold) than predictable from single dose pharmacokinetics. Distribution Mesalamine is approximately 43% bound to plasma proteins at the concentration of 2.5 mcg/mL.
Elimination Metabolism The only major metabolite of mesalamine (5-aminosalicylic acid) is N-acetyl-5-aminosalicylic acid. Its formation is brought about by N-acetyltransferase (NAT) activity in the liver and intestinal mucosa cells, principally by NAT-1. Excretion Excretion of mesalamine is mainly via the renal route following met… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action The mechanism of action of mesalamine is not fully understood, but it appears to have a topical anti-inflammatory effect on the colonic epithelial cells. Mucosal production of arachidonic acid metabolites, both through the cyclooxygenase and lipoxygenase pathways, is increased in patients with ulcerative colitis, and it is possible that mesalamine diminishes inflammation by blocking cyclooxygenase and inhibiting prostaglandin production in the colon.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Mesalamine delayed-release tablets, USP are available as reddish-brown, oval-shaped, enteric-coated tablets containing 1.2 g mesalamine is imprinted with “M19” in black color on one side and plain on other side supplied in: HDPE Bottle with a child-resistant closure of 120 delayed-release tablets NDC 72603-304-01 Store at 20°C to 25°C (68°F to 77°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Each mesalamine delayed-release tablet, USP for oral administration contains 1.2 g 5-aminosalicylic acid (5-ASA; mesalamine), an anti-inflammatory agent. Mesalamine also has the chemical name 5-amino-2-hydroxybenzoic acid and its structural formula is: Molecular formula: C 7 H 7 NO 3 Molecular weight: 153.14 The tablet is coated with a pH-dependent polymer film, which breaks down at or above pH 6.8, normally in the terminal ileum where mesalamine then begins to be released from the tablet core. The tablet core contains mesalamine with hydrophilic and lipophilic excipients and provides for extended release of mesalamine.
The inactive ingredients of mesalamine delayed-release tablets, USP are colloidal silicon dioxide, ferric oxide, hypromellose, magnesium stearate, methacrylic acid and methyl methacrylate copolymer, microcrystalline cellulose, polyethylene glycol, sodium starch glycolate, talc, titanium dioxide, triethyl citrate, the imprinting ink contains ammonium hydroxide, black iron oxide, propylene glycol and shellac. FDA approved dissolution test specifications differ from USP. mesalaminedrtabsstructure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Renal Impairment Inform patients that mesalamine delayed-release tablets may decrease their renal function, especially if they have known renal impairment or are taking nephrotoxic drugs, and periodic monitoring of renal function will be performed while they are on therapy. Advise patients to complete all blood tests ordered by their healthcare provider [see Warnings and Precautions ( 5.1 )]. Mesalamine-Induced Acute Intolerance Syndrome and Other Hypersensitivity Reactions Instruct patients to stop taking mesalamine delayed-release tablets and report to their healthcare provider if they experience new or worsening symptoms of acute intolerance syndrome (cramping, abdominal pain, bloody diarrhea, fever, headache, and rash) or other symptoms suggestive of mesalamine-induced hypersensitivity [see Warnings and Precautions ( 5.2 , 5.3 )].
Hepatic Failure Advise patients with known liver disease to contact their healthcare provider if they experience signs or symptoms of worsening liver function [see Warnings and Precautions ( 5.4 )]. Severe Cutaneous Adverse Reactions Inform patients of the signs and symptoms of severe cutaneous adverse reactions. Instruct patients to stop taking mesalamine delayed-release tablets and report to their healthcare provider at first appearance of a severe cutaneous adverse reaction or other sign of hypersensitivity [see Warnings and Precautions ( 5.5 )].
Upper Gastrointestinal Tract Obstruction Advise patients to contact their healthcare provider if they experience signs and symptoms of upper gastrointestinal tract obstruction [see Warnings and Precautions ( 5.6 )]. Photosensitivity Advise patients with pre-existing skin conditions to avoid sun exposure, wear protective clothing, and use a broad-spectrum sunscreen when outdoors [see Warnings and Precautions ( 5.7 )]. Nephrolithiasis Instruct patients to drink an adequate amount of fluids during treatment in order to minimize the risk of kidney stone formation and to contact their healthcare provider if they experience signs or symptoms of a kidney stone (e.g., severe side or back pain, blood in the urine) [see Warnings and Precautions ( 5.8 )].
Blood Disorders Inform elderly patients and those taking azathioprine or 6-mercaptopurine of the risk for blood disorders and the need for periodic monitoring of complete blood cell counts and platelet counts while on therapy. Advise patients to complete all blood tests ordered by their healthcare provider [see Drug Interactions ( 7.2 ), Use in Specific Populations ( 8.5 )]. Administration Instruct patients: • Swallow mesalamine delayed-release tablets whole; do not split or crush. • Take mesalamine delayed-release tablets with food [see Clinical Pharmacology ( 12.3 )]. • Urine may become discolored reddish-brown while taking mesalamine delayed-release tablets when it comes in contact with surfaces or water treated with hypochlorite-containing bleach.
If discolored urine is observed, advise patients to observe their urine flow. Report to the healthcare provider only if urine is discolored on leaving the body, before contact with any surface or water (e.g., in the toilet). • Drink an adequate amount of fluids [see Warnings and Precautions ( 5.8 )]. Manufactured for: Northstar Rx LLC Memphis, TN 38141.
Manufactured by: Annora Pharma Pvt. Ltd. Sangareddy - 502313, Telangana, India.
Issued: 09/2024
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption The total absorption of mesalamine from mesalamine 2.4 g or 4.8 g given once daily for 14 days to healthy subjects was found to be approximately 21% to 22% of the administered dose. Gamma-scintigraphy studies have shown that a single dose of mesalamine 1.2 g (one tablet) passed intact through the upper gastrointestinal tract of fasted healthy subjects. Scintigraphic images showed a trail of radio-labeled tracer in the colon, suggesting that mesalamine had distributed through this region of the gastrointestinal tract.
In a single-dose study, mesalamine 1.2 g, 2.4 g, and 4.8 g were administered in the fasted state to healthy subjects. Plasma concentrations of mesalamine were detectable after 2 hours and reached a maximum by 9 to 12 hours on average for the doses studied. The pharmacokinetic parameters are highly variable among subjects (Table 4).
Mesalamine systemic exposure in terms of area under the plasma concentration-time curve (AUC) was slightly more than dose proportional between 1.2 g and 4.8 g mesalamine. Maximum plasma concentrations (C max ) of mesalamine increased approximately dose proportionately between 1.2 g and 2.4 g and sub-proportionately between 2.4 g and 4.8 g of mesalamine, with the dose normalized value at 4.8 g representing, on average, 74% of that at 2.4 g based on geometric means. Table 4: Mean (SD) Pharmacokinetic Parameters for Mesalamine Following Single-Dose Administration of Mesalamine Under Fasting Conditions Parameter* of Mesalamine Mesalamine 1.2 g (N=47) Mesalamine 2.4 g (N=48) Mesalamine 4.8 g (N=48) AUC 0-t (ng⋅h/mL) 9039 † (5054) 20538 (12980) 41434 (26640) AUC 0-∞ (ng⋅h/mL) 9578 ‡ (5214) 21084 (13185) 44775 § (30302) C max (ng/mL) 857 (638) 1595 (1484) 2154 (1140) T max ¶ (h) 9.0 # (4.0 to 32.1) 12.0 (4.0 to 34.1) 12.0 (4.0 to 34.0) T lag ¶ (h) 2.0 # (0 to 8.0) 2.0 (1.0 to 4.0) 2.0 (1.0 to 4.0) T 1/2 (h) (Terminal Phase) 8.56 ‡ (6.38) 7.05 Þ (5.54) 7.25 § (8.32) * Arithmetic mean of parameter values are presented except for T max and T lag . † N=43, ‡ N=27, § N=36, ¶ Median (min, max), # N=46, Þ N=33 Food Effects Administration of a single dose of mesalamine 4.8 g with a high-fat meal resulted in further delay in absorption, and plasma concentrations of mesalamine were detectable 4 hours following dosing.
However, a high-fat meal increased systemic exposure of mesalamine (mean C max : increased 91%; mean AUC: increased 16%) compared to results in the fasted state. mesalamine was administered with food in the controlled clinical trials [see Dosage and Administration ( 2 )]. In a single- and multiple-dose pharmacokinetic study of mesalamine, 2.4 g or 4.8 g was administered once daily with standard meals to 28 healthy subjects per dose group. Plasma concentrations of mesalamine were detectable after 4 hours and were maximal by 8 hours after the single dose.
Steady state was achieved generally by 2 days after dosing. Mean AUC at steady state was only modestly greater (1.1- to 1.4-fold) than predictable from single dose pharmacokinetics. Distribution Mesalamine is approximately 43% bound to plasma proteins at the concentration of 2.5 mcg/mL.
Elimination Metabolism The only major metabolite of mesalamine (5-aminosalicylic acid) is N-acetyl-5-aminosalicylic acid. Its formation is brought about by N-acetyltransferase (NAT) activity in the liver and intestinal mucosa cells, principally by NAT-1. Excretion Excretion of mesalamine is mainly via the renal route following metabolism to N-acetyl-5-aminosalicylic acid (acetylation); however, there is also limited excretion of the parent drug in urine.
Of the approximately 21% to 22% of the dose absorbed, less than 8% of the dose was excreted unchanged in the urine after 24 hours, compared with greater than 13% for N-acetyl-5-aminosalicylic acid. The mean renal clearance (CL R ) in adults ranged from
1.8 L/h to
2.9 L/h following single dose administration and ranged from
5.5 L/h to
6.4L/h after a multiple dosing for 14 day… [Excerpted — this section continues on DailyMed.]
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Adults with Mildly to Moderately Active Ulcerative Colitis Induction of Remission Two similarly designed, randomized, double-blind, placebo-controlled trials (Study 1, NCT00503243 and Study 2, NCT00548574) were conducted in 517 adult patients with mildly to moderately active ulcerative colitis. The study population was primarily Caucasian (80%), had a mean age of 42 years (6% age 65 years or older), and was approximately 50% male. Both studies used mesalamine dosages of 2.4 g and 4.8 g administered once daily for 8 weeks, except in Study 1 the 2.4 g dosage was administered as two divided doses (i.e., 1.2 g twice daily).
The primary efficacy endpoint in both trials was to compare the percentage of patients in remission after 8 weeks of treatment for the mesalamine treatment groups versus placebo. Remission was defined as an Ulcerative Colitis Disease Activity Index (UC-DAI) of ≤1, with scores of zero for rectal bleeding and for stool frequency, and a sigmoidoscopy score reduction of 1 point or more from baseline. In both studies, the mesalamine dosages of 2.4 g and 4.8 g once daily demonstrated superiority over placebo in the primary efficacy endpoint (Table 6).
Both mesalamine dosages also provided consistent benefit in secondary efficacy parameters, including clinical improvement, clinical remission, and sigmoidoscopic improvement. Both mesalamine dosages had similar efficacy profiles. Table 6: Proportion of Adult Patients with Mildly to Moderately Active Ulcerative Colitis in Remission at Week 8 in Two Double-Blind Placebo-Controlled Induction Trials Dose Study 1 (n=262) n/N (%) Study 2 (n=255) n/N (%) Mesalamine 2.4 g/day 30/88 (34) 34/84 (41) Mesalamine 4.8 g/day 26/89 (29) 35/85 (41) Placebo 11/85 (13) 19/86 (22) Maintenance of Remission A multicenter, randomized, double-blind, active comparator study (Study 3, NCT00151892) was conducted in a total of 826 adult patients in remission from ulcerative colitis.
Patients were randomized in a 1:1 ratio to receive either mesalamine 2.4 g administered once daily or another mesalamine delayed-release product administered as 0.8 g twice daily. The study population had a mean age of 45 years (8% age 65 years or older), were 52% male, and were primarily Caucasian (64%). Maintenance of remission was assessed using a modified UC-DAI.
For this trial, maintenance of remission was based on maintaining endoscopic remission defined as a modified UC-DAI endoscopy subscore of ≤1. An endoscopy subscore of 0 represented normal mucosal appearance with intact vascular pattern and no friability or granulation. For this trial the endoscopy score definition of 1 (mild disease) was modified such that it could include erythema, decreased vascular pattern, and minimal granularity; however, it could not include friability.
The proportion of patients who maintained remission at Month 6 in this study using mesalamine 2.4 g once daily (84%) was similar to the comparator (82%).
14.2Pediatric Patients with Mildly to Moderately Active Ulcerative Colitis Weighing at Least 24 kg A multicenter, randomized, double-blind, parallel-group study (NCT02093663) was conducted in pediatric patients aged 5 through 17 years with mildly to moderately active ulcerative colitis to determine the safety and effectiveness of mesalamine. The study consisted of two treatment phases, an initial 8-week phase and a 26-week phase. The overall population consisted of 105 patients, of whom 27 patients participated in both the 8-week and 26-week phases.
Each phase included two dosage arms and patients were randomized at the beginning of each phase in a 1:1 ratio, stratified by body weight group. Patients received a low or a high weight-based dosage of mesalamine in four weight groups. Because of the small number of patients in the lowest body weight group (0 in the 8-week phase and 3 in the 26-week phase), the safety and effectiveness of mesalamine in patients weighing less than 24 kg have not been established.… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis In a 104-week dietary carcinogenicity study in CD-1 mice, mesalamine at doses up to 2500 mg/kg/day was not tumorigenic. This dose is 2.2 times the maximum recommended human dose (based on a body surface area comparison) of mesalamine. Furthermore, in a 104-week dietary carcinogenicity study in Wistar rats, mesalamine up to a dose of 800 mg/kg/day was not tumorigenic.
This dose is 1.4 times the recommended human dose (based on a body surface area comparison) of mesalamine. Mutagenesis No evidence of mutagenicity was observed in an in vitro Ames test or an in vivo mouse micronucleus test. Impairment of Fertility No effects on fertility or reproductive performance were observed in male or female rats at oral doses of mesalamine up to 400 mg/kg/day (0.7 times the maximum recommended human dose based on a body surface area comparison).
13.2Animal Toxicology and/or Pharmacology In animal studies with mesalamine, a 13-week oral toxicity study in mice and 13-week and 52-week oral toxicity studies in rats and cynomolgus monkeys have shown the kidney to be the major target organ of mesalamine toxicity. Oral daily doses of 2400 mg/kg in mice and 1150 mg/kg in rats produced renal lesions including granular and hyaline casts, tubular degeneration, tubular dilation, renal infarct, papillary necrosis, tubular necrosis, and interstitial nephritis. In cynomolgus monkeys, oral daily doses of 250 mg/kg or higher produced nephrosis, papillary edema, and interstitial fibrosis.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis In a 104-week dietary carcinogenicity study in CD-1 mice, mesalamine at doses up to 2500 mg/kg/day was not tumorigenic. This dose is 2.2 times the maximum recommended human dose (based on a body surface area comparison) of mesalamine. Furthermore, in a 104-week dietary carcinogenicity study in Wistar rats, mesalamine up to a dose of 800 mg/kg/day was not tumorigenic.
This dose is 1.4 times the recommended human dose (based on a body surface area comparison) of mesalamine. Mutagenesis No evidence of mutagenicity was observed in an in vitro Ames test or an in vivo mouse micronucleus test. Impairment of Fertility No effects on fertility or reproductive performance were observed in male or female rats at oral doses of mesalamine up to 400 mg/kg/day (0.7 times the maximum recommended human dose based on a body surface area comparison).
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL Mesalamine Delayed-Release Tablets, USP 1.2 g - Container Label - 120's count 120scontainer