
buprenorphine hydrochloride 8 mg Tablet, 30-count — NDC 72888-183-30 (Billing 72888-0183-30)
This is a package of 30 tablets of buprenorphine hydrochloride 8 mg Tablet from Advagen Pharma Ltd, marketed since Jun 2015 and currently FDA-listed; retail pharmacies pay about $0.5714 per tablet (NADAC). It is the main listing for this product, which comes in 2 package sizes.
Other active recalls for Buprenorphine Hydrochloride (different manufacturers) — 3 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 029313
- GCN: 64673
- HICL (First Databank): 001762
- AHFS class code: 28:08.12.00
- RxCUI (RxNorm): 351264
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Partial Opioid Agonist class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It depends on the product. Sublingual tablets, Sublocade and Brixadi treat opioid dependence. Belbuca, Butrans, patches and the injection treat severe pain that needs an opioid.
- Follow your label exactly. Sublingual tablets dissolve under the tongue once daily and must not be chewed or swallowed. Patches stay on for 7 days, and injections are given by a pr...
- Nausea, headache, dizziness, constipation, sleepiness and dry mouth are common. With patches, you may get itching or redness at the site. Call for help if breathing slows or you ca...
- No, not without your prescriber's guidance. Alcohol, benzodiazepines and other sedatives can cause dangerous sedation, slowed breathing, coma and death.
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Buprenorphine Hydrochloride — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.571 | $17.14 / 30 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.8374 | $25.12 / 30 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.4294 | $12.88 / 30 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 72888-0183-30 You're viewing this Main listing | 30 TABLET in 1 BOTTLE | $0.5714 / ea | $17.14 | 2024-01-23 | — | Active |
| 72888-0183-90 72888-183-90 | 90 TABLET in 1 BOTTLE | — | — | 2024-01-23 | — | Active |
You're viewing the smallest of 2 pack sizes for this product.
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 72888-0183-90?
What NDC number is used to bill for this package of buprenorphine hydrochloride 8 mg Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Buprenorphine 8 mg 00054-0177-13 | Hikma | 30 tablets | $0.571 | AB | Availability likely | — |
| buprenorphine hydrochloride 8 mg 00121-2038-30 | PAI | 30 tablets | $0.571 | AB | Availability likely | — |
| Buprenorphine 8 mg 00228-3153-03 | Actavis | 30 tablets | $0.571 | AB | Availability likely | — |
| Buprenorphine HCl 8 mg 00406-7018-03 | SpecGx | 30 tablets | $0.571 | AB | Availability likely | — |
| Buprenorphine 8 mg 00904-7155-04 | Major | 30 tablets | $0.571 | AB | Availability likely | — |
| Buprenorphine HCl 8 mg 31722-0871-30 | Camber | 30 tablets | $0.571 | AB | Availability likely | — |
| Buprenorphine 8 mg 42858-0502-03 | Rhodes | 30 tablets | $0.571 | AB | Availability likely | — |
| Buprenorphine 8 mg 50268-0129-15 | AvPAK | 50 tablets | $0.571 | AB | Availability likely | — |
| Buprenorphine 8 mg 60687-0492-21 | American | 30 tablets | $0.571 | AB | Availability likely | — |
| buprenorphine hydrochloride 8 mgthis 72888-0183-30 | Advagen | 30 tablets | $0.571 | AB | Availability likely | — |
| Buprenorphine 8 mg 50090-5805-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| buprenorphine hydrochloride 8 mg 50090-7559-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Buprenorphine HCl 8 mg 58118-0177-08 | Clinical | 30 tablets | — | AB | FDA listed | — |
| Buprenorphine 8 mg 58118-0460-08 | Clinical | 30 tablets | — | AB | FDA listed | — |
| Buprenorphine 8 mg 58118-0502-08 | Clinical | 30 tablets | — | AB | FDA listed | — |
| Buprenorphine 8 mg 62756-0460-64 | Sun | 30 tablets | — | AB | FDA listed | — |
| Buprenorphine 8 mg 67296-2173-03 | Redpharm | 30 tablets | — | AB | FDA listed | — |
| Buprenorphine HCl 8 mg 70518-2014-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| buprenorphine hydrochloride 8 mg 70518-4571-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Buprenorphine 8 mg 71335-1154-00 | Bryant | 120 tablets | — | AB | FDA listed | — |
| Buprenorphine HCl 8 mg 71335-1163-00 | Bryant | 120 tablets | — | AB | FDA listed | — |
| Buprenorphine 8 mg 72162-1345-03 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Buprenorphine Sublingual C-III 8 mg 72189-0582-60 | Direct_Rx | 60 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Buprenorphine Sublingual Tablets are indicated for the treatment of opioid dependence and is preferred for induction. Buprenorphine Sublingual Tablets should be used as part of a complete treatment plan to include counseling and psychosocial support. Buprenorphine Sublingual Tablets contain buprenorphine, a partial opioid agonist, and is indicated for the treatment of opioid dependence and is preferred for induction.
( 1 ) Buprenorphine Sublingual Tablets should be used as part of a complete treatment plan that includes counseling and psychosocial support. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Administer Buprenorphine Sublingual Tablets sublingually as a single daily dose. ( 2.1 ) Strongly consider recommending or prescribing an opioid overdose reversal agent (e.g., naloxone, nalmefene) at the time buprenorphine sublingual tablets are initiated or renewed because patients being treated for opioid use disorder have the potential for relapse, putting them at risk for opioid overdose. ( 2.2 ) To avoid precipitating withdrawal, induction with Buprenorphine Sublingual Tablets should be undertaken when objective and clear signs of withdrawal are evident.
( 2.3 ) Buprenorphine and naloxone sublingual film or buprenorphine and naloxone sublingual tablets are generally initiated after two days of buprenorphine sublingual tablets titration. ( 2.4 ) Administer Buprenorphine Sublingual Tablets as directed in the Full Prescribing information. ( 2.3 , 2.4 , 2.5 ) Buprenorphine Sublingual Tablets must be administered whole.
Do not cut, chew, or swallow Buprenorphine Sublingual Tablets. ( 2.5 ) When discontinuing treatment, gradually taper to avoid signs and symptoms of withdrawal. ( 2.9 )
2.1Important Dosage and Administration Instructions Buprenorphine Sublingual Tablets are administered sublingually as a single daily dose. Buprenorphine Sublingual Tablets do not contain naloxone and is preferred for use only during induction. Following induction, buprenorphine and naloxone sublingual film or buprenorphine and naloxone sublingual tablets are preferred due to the presence of naloxone when clinical use includes unsupervised administration.
The use of Buprenorphine Sublingual Tablets for unsupervised administration should be limited to those patients who cannot tolerate buprenorphine and naloxone sublingual film or buprenorphine and naloxone sublingual tablet; for example, those patients who have been shown to be hypersensitive to naloxone. Medication should be prescribed in consideration of the frequency of visits. Provision of multiple refills is not advised early in treatment or without appropriate patient follow-up visits.
2.2Patient Access to an Opioid Overdose Reversal Agent for the Emergency Treatment of Opioid Overdose Inform patients and caregivers about opioid overdose reversal agents (e.g., naloxone, nalmefene) and discuss the importance of having access to an opioid overdose reversal agent. Because patients being treated for opioid use disorder have the potential for relapse, putting them at risk for opioid overdose, strongly consider recommending or prescribing an overdose reversal agent for the emergency treatment of opioid overdose, both when initiating and renewing treatment with Buprenorphine Sublingual Tablets.
Also consider recommending or prescribing such an agent if the patient has household members (including children) or other close contacts at risk for accidental ingestion or opioid overdose [see Warnings and Precautions ( 5.2 )]. Discuss the options for obtaining an opioid overdose reversal agent (e.g., prescription, over-the-counter, or as part of a community-based program) [see Warnings and Precautions ( 5.2 )]. There are important differences among the opioid overdose reversal agents, such as route of administration, product strength, approved patient age range, and pharmacokinetics.
Be familiar with these differences, as outlined in the approved labeling for those products, prior to recommending or prescribing such an agent. Advise patients and caregivers that opioid overdose reversal agents, such as naloxone or nalmefene, may also be administered for a known or suspected overdose with Buprenorphine Sublingual Tablets itself. Higher than normal doses and repeated administration of an opioid overdose reversal agent may be necessary due to the long duration of action of Buprenorphine Sublingual Tablets and its affinity for the mu receptor [see Overdosage ( 10 )] .
2.3Induction Prior to induction, consideration should be given to the type of opioid dependence (i.e., long- or s… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Buprenorphine Sublingual Tablets are supplied as a white to off white round convex tablet in four dosage strengths: buprenorphine 2 mg, buprenorphine 4 mg, buprenorphine 8 mg, and buprenorphine 12 mg Sublingual tablet: buprenorphine 2 mg, buprenorphine 4 mg, buprenorphine 8 mg and buprenorphine 12 mg. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Buprenorphine Sublingual Tablets are contraindicated in patients with a history of hypersensitivity to buprenorphine, as serious adverse reactions, including anaphylactic shock, have been reported [see Warnings and Precautions ( 5.9 )] . Hypersensitivity to buprenorphine. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Addiction, Abuse, and Misuse : Buprenorphine can be abused in a similar manner to other opioids. Monitor patients for conditions indicative of diversion or progression of opioid dependence and addictive behaviors. Multiple refills should not be prescribed early in treatment or without appropriate patient follow-up visits.
( 5.1 ) Respiratory Depression : Life-threatening respiratory depression and death have occurred in association with buprenorphine use. Warn patients of the potential danger of self-administration of benzodiazepines or other CNS depressants while under treatment with Buprenorphine Sublingual Tablets ( 5.2 , 5.3 ) Unintentional Pediatric Exposure : Store Buprenorphine Sublingual Tablets safely out of the sight and reach of children. Buprenorphine can cause severe, possibly fatal, respiratory depression in children.
( 5.4 ) Neonatal Opioid Withdrawal Syndrome : Neonatal opioid withdrawal syndrome (NOWS) is an expected and treatable outcome of prolonged use of opioids during pregnancy. ( 5.5 ) Adrenal Insufficiency : If diagnosed, treat with physiologic replacement of corticosteroids, and wean patient off of the opioid. ( 5.6 ) Risk of Opioid Withdrawal with Abrupt Discontinuation : If treatment is temporarily interrupted or discontinued, monitor patients for withdrawal and treat appropriately.
( 5.7 ) Risk of Hepatitis, Hepatic Events : Monitor liver function tests prior to initiation and during treatment and evaluate suspected hepatic events. ( 5.8 ) Precipitation of Opioid Withdrawal Signs and Symptoms : An opioid withdrawal syndrome is likely to occur with parenteral misuse of Buprenorphine Sublingual Tablets by individuals physically dependent on full opioid agonists, or by sublingual administration before the agonist effects of other opioids have subsided. ( 5.10 ) Risk of Overdose in Opioid-Naïve Patients : Buprenorphine Sublingual Tablets are NOT appropriate as an analgesic.
There have been reported deaths of opioid naïve individuals who received a 2 mg sublingual dose of buprenorphine. ( 5.11 )
5.1Addiction, Abuse, and Misuse Buprenorphine Sublingual Tablets contain buprenorphine, a Schedule III controlled substance that can be abused in a manner similar to other opioids, legal or illicit. Prescribe and dispense buprenorphine with appropriate precautions to minimize risk of misuse, abuse, or diversion, and ensure appropriate protection from theft, including in the home. Clinical monitoring appropriate to the patient’s level of stability is essential.
Multiple refills should not be prescribed early in treatment or without appropriate patient follow-up visits [see Drug Abuse and Dependence ( 9.2 )].
5.2Life-Threatening Respiratory Depression and Central Nervous System (CNS) Depression Buprenorphine has been associated with life-threatening respiratory depression and death. Many, but not all, post-marketing reports regarding coma and death involved misuses by self-injection or were associated with the concomitant use of benzodiazepines or other CNS depressants, including alcohol. Warn patients of the potential danger of self-administration of benzodiazepines or other CNS depressants while under treatment with Buprenorphine Sublingual Tablets. [see Warnings and Precautions ( 5.3 ), Drug Interactions ( 7 )].
Use Buprenorphine Sublingual Tablets with caution in patients with compromised respiratory function (e.g., chronic obstructive pulmonary disease, cor pulmonale, decreased respiratory reserve, hypoxia, hypercapnia, or pre-existing respiratory depression). Educate patients and caregivers on how to recognize respiratory depression and emphasize the importance of calling 911 or getting emergency medical help right away in the event of a known or suspected overdose [ see Patient Counseling Information ( 17 ) ]. Opioids can cause sleep-related breathing disorders including central sleep apnea (CSA) and sleep-related hypoxemia.
Opioid use increases the risk of CSA in a dose-dependen… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described elsewhere in the labeling: Addiction, Abuse, and Misuse [see Warnings and Precautions ( 5.1 )] Respiratory and CNS Depression [see Warnings and Precautions ( 5.2 , 5.3 )] Neonatal Opioid Withdrawal Syndrome [see Warnings and Precautions ( 5.5 )] Adrenal Insufficiency [see Warnings and Precautions ( 5.6 )] Opioid Withdrawal [see Warnings and Precautions ( 5.7 , 5.10 )] Hepatitis, Hepatic Events [see Warnings and Precautions ( 5.8 )] Hypersensitivity Reactions [see Warnings and Precautions ( 5.9 )] Orthostatic Hypotension [see Warnings and Precautions ( 5.16 )] Elevation of Cerebrospinal Fluid Pressure [see Warnings and Precautions ( 5.17 )] Elevation of Intracholedochal Pressure [see Warnings and Precautions ( 5.18 )] Adverse events commonly observed with administration of buprenorphine are oral hypoesthesia, glossodynia, oral mucosal erythema, headache, nausea, vomiting, hyperhidrosis, constipation, signs and symptoms of withdrawal, insomnia, pain, and peripheral edema.
( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Advagen Pharma Ltd, at 866-488-0312 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The safety of Buprenorphine Sublingual Tablets was supported by clinical trials using buprenorphine sublingual tablets, buprenorphine and naloxone sublingual tablets and other trials using buprenorphine sublingual solutions. In total, safety data were available from 3214 opioid-dependent subjects exposed to buprenorphine at doses in the range used in treatment of opioid addiction.
Few differences in adverse event profile were noted between buprenorphine sublingual tablets or buprenorphine administered as a sublingual solution. The following adverse events were reported to occur by at least 5% of patients in a 4-week study ( Table 1 ). Table 1.
Adverse Events ≥5% by Body System and Treatment Group in a 4-week Study N(%) N(%) Body System / Adverse Event (COSTART Terminology) Buprenorphine Sublingual Tablets 16 mg/day N=103 Placebo N=107 Body as a Whole Asthenia 5 (4.9%) 7 (6.5%) Chills 8 (7.8%) 8 (7.5%) Headache 30 (29.1%) 24 (22.4%) Infection 12 (11.7%) 7 (6.5%) Pain 19 (18.4%) 20 (18.7%) Pain Abdomen 12 (11.7%) 7 (6.5%) Pain Back 8 (7.8%) 12 (11.2%) Withdrawal Syndrome 19 (18.4%) 40 (37.4%) Cardiovascular System Vasodilation 4 (3.9%) 7 (6.5%) Digestive System Constipation 8 (7.8%) 3 (2.8%) Diarrhea 5 (4.9%) 16 (15.0%) Nausea 14 (13.6%) 12 (11.2%) Vomiting 8 (7.8%) 5 (4.7%) Nervous System Insomnia 22 (21.4%) 17 (15.9%) Respiratory System Rhinitis 10 (9.7%) 14 (13.1%) Skin and Appendages Sweating 13 (12.6%) 11 (10.3%) The adverse event profile of buprenorphine was also characterized in the dose-controlled study of buprenorphine solution, over a range of doses in four months of treatment.
Table 2 shows adverse events reported by at least 5% of subjects in any dose group in the dose-controlled study. Table 2. Adverse Events (≥5%) by Body System and Treatment Group in a 16-week Study Body System/ Adverse Event (COSTART Terminology) Buprenorphine Dose* Very Low* (N=184) Low* (N=180) Moderate* (N=186) High* (N=181) Total* (N=731) N (%) N (%) N (%) N (%) N (%) Body as a Whole Abscess 9 (5%) 2 (1%) 3 (2%) 2 (1%) 16 (2%) Asthenia 26 (14%) 28 (16%) 26 (14%) 24 (13%) 104 (14%) Chills 11 (6%) 12 (7%) 9 (5%) 10 (6%) 42 (6%) Fever 7 (4%) 2 (1%) 2 (1%) 10 (6%) 21 (3%) Flu Syndrome 4 (2%) 13 (7%) 19 (10%) 8 (4%) 44 (6%) Headache 51 (28%) 62 (34%) 54 (29%) 53 (29%) 220 (30%) Infection 32 (17%) 39 (22%) 38 (20%) 40 (22%) 149 (20%) Injury Accidental 5 (3%) 10 (6%) 5 (3%) 5 (3%) 25 (3%) Pain 47 (26%) 37 (21%) 49 (26%) 44 (24%) 177 (24%) Pain Back 18 (10%) 29 (16%) 28 (15%) 27 (15%)… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Table 3 includes clinically significant drug interactions with Buprenorphine Sublingual Tablets. Table 3. Clinically Significant Drug Interactions with Buprenorphine Sublingual Tablets Benzodiazepines or other Central Nervous System (CNS) Depressants Clinical Impact : Due to additive pharmacologic effects, the concomitant use of benzodiazepines or other CNS depressants, including alcohol, increases the risk of respiratory depression, profound sedation, coma, and death.
Intervention : Cessation of benzodiazepines or other CNS depressants is preferred in most cases of concomitant use. In some cases, monitoring in a higher level of care for taper may be appropriate. In others, gradually tapering a patient off of a prescribed benzodiazepine or CNS depressant or decreasing to the lowest effective dose may be appropriate.
Before co-prescribing benzodiazepines for anxiety or insomnia, ensure that patients are appropriately diagnosed and consider alternative medications and non-pharmacologic treatments [see Warnings and Precautions ( 5.2 , 5.3 )] . If concomitant use is warranted, strongly consider recommending or prescribing an opioid overdose reversal agent, as is recommended for all patients on buprenorphine treatment for opioid use disorder [see Warnings and Precautions ( 5.2 )] . Examples : Benzodiazepines and other sedatives/hypnotics, anxiolytics, tranquilizers, muscle relaxants, general anesthetics, antipsychotics, gabapentinoids (gabapentin or pregabalin), other opioids, alcohol.
Inhibitors of CYP3A4 Clinical Impact : The concomitant use of buprenorphine and CYP3A4 inhibitors can increase the plasma concentration of buprenorphine, resulting in increased or prolonged opioid effects, particularly when an inhibitor is added after a stable dose of buprenorphine sublingual tablets is achieved. After stopping a CYP3A4 inhibitor, as the effects of the inhibitor decline, the buprenorphine plasma concentration will decrease [see Clinical Pharmacology ( 12.3 )] , potentially resulting in decreased opioid efficacy or a withdrawal syndrome in patients who had developed physical dependence to buprenorphine.
Intervention : If concomitant use is necessary, consider dosage reduction of buprenorphine sublingual tablets until stable drug effects are achieved. Monitor patients for respiratory depression and sedation at frequent intervals. If a CYP3A4 inhibitor is discontinued, consider increasing the buprenorphine sublingual tablets dosage until stable drug effects are achieved.
Monitor for signs of opioid withdrawal. Examples : Macrolide antibiotics (e.g.,erythromycin), azole-antifungal agents (e.g. ketoconazole), protease inhibitors (e.g., ritonavir). CYP3A4 Inducers Clinical Impact: The concomitant use of buprenorphine and CYP3A4 inducers can decrease the plasma concentration of buprenorphine [see Clinical Pharmacology ( 12.3 )], potentially resulting in decreased efficacy or onset of a withdrawal syndrome in patients who have developed physical dependence to buprenorphine.
After stopping a CYP3A4 inducer, as the effects of the inducer decline, the buprenorphine plasma concentration will increase [see Clinical Pharmacology ( 12.3 )], which could increase or prolong both therapeutic effects and adverse reactions and may cause serious respiratory depression. Intervention : If concomitant use is necessary, consider increasing the buprenorphine sublingual tablets dosage until stable drug effects are achieved. Monitor for signs of opioid withdrawal.
If a CYP3A4 inducer is discontinued, consider buprenorphine sublingual tablets dosage reduction and monitor for signs of respiratory depression. Examples : Rifampin, carbamazepine, phenytoin Antiretrovirals: Non-nucleoside reverse transcriptase inhibitors (NNRTIs) Clinical Impact: Non-nucleoside reverse transcriptase inhibitors (NNRTIs) are metabolized principally by CYP3A4. Efavirenz, nevirapine, and etravirine are known CYP3A inducers, whereas delavirdine is a CYP3A inhibitor.
Si… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Buprenorphine passes into mother’s milk. ( 8.2 ) Geriatric Patients: Monitor for sedation or respiratory depression. ( 8.5 ) Severe Hepatic Impairment: Consider reducing the starting and titration incremental dose by half and monitor for signs and symptoms of toxicity or overdose. ( 8.6 )
8.1Pregnancy Risk Summary The data on use of buprenorphine, the active ingredient in Buprenorphine Sublingual Tablets, in pregnancy, are limited; however, these data do not indicate an increased risk of major malformations specifically due to buprenorphine exposure. There are limited data from randomized clinical trials in women maintained on buprenorphine that were not designed appropriately to assess the risk of major malformations [see Data ] . Observational studies have reported on congenital malformations among buprenorphine- exposed pregnancies, but were also not designed appropriately to assess the risk of congenital malformations specifically due to buprenorphine exposure [see Data ] .
Reproductive and developmental studies in rats and rabbits identified adverse events at clinically relevant and higher doses. Embryofetal death was observed in both rats and rabbits administered buprenorphine during the period of organogenesis at doses approximately 6 and 0.3 times, respectively, the human sublingual dose of 16 mg/day of buprenorphine. Pre-and post-natal development studies in rats demonstrated increased neonatal deaths at 0.3 times and above and dystocia at approximately 3 times the human sublingual dose of 16 mg/day of buprenorphine.
No clear teratogenic effects were seen when buprenorphine was administered during organogenesis with a range of doses equivalent to or greater than the human sublingual dose of 16 mg/day of buprenorphine. However, increases in skeletal abnormalities were noted in rats and rabbits administered buprenorphine daily during organogenesis at doses approximately 0.6 times and approximately equal to the human sublingual dose of 16 mg/day of buprenorphine, respectively. In a few studies, some events such as acephalus and omphalocele were also observed but these findings were not clearly treatment-related [see Data ] .
Based on animal data, advise pregnant women of the potential risk to a fetus. The estimated background risks of major birth defects and miscarriage for the indicated population are unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Disease-associated maternal and embryo-fetal risk Untreated opioid addiction in pregnancy is associated with adverse obstetrical outcomes such as low birth weight, preterm birth, and fetal death. In addition, untreated opioid addiction often results in continued or relapsing illicit opioid use.
Dose Adjustment during Pregnancy and the Postpartum Period Dosage adjustments of buprenorphine, such as a higher doses, may be required during pregnancy, even if the patient was maintained on a stable dose prior to pregnancy. Dosing should be based on individual response, and withdrawal signs and symptoms should be monitored closely and the dose adjusted as necessary. Fetal/neonatal adverse reactions Neonatal opioid withdrawal syndrome may occur in newborn infants of mothers who are receiving treatment with Buprenorphine Sublingual Tablets.
Neonatal opioid withdrawal syndrome presents as irritability, hyperactivity and abnormal sleep pattern, high pitched cry, tremor, vomiting, diarrhea, and/or failure to gain weight. Signs of neonatal withdrawal usually occur in the first days after birth. The duration and severity of neonatal opioid withdrawal syndrome may vary.
Observe newborns for signs of neonatal opioid withdrawal syndrome and manage accordingly. [see Warnings and Precautions ( 5.5 )] . Labo… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary The data on use of buprenorphine, the active ingredient in Buprenorphine Sublingual Tablets, in pregnancy, are limited; however, these data do not indicate an increased risk of major malformations specifically due to buprenorphine exposure. There are limited data from randomized clinical trials in women maintained on buprenorphine that were not designed appropriately to assess the risk of major malformations [see Data ] . Observational studies have reported on congenital malformations among buprenorphine- exposed pregnancies, but were also not designed appropriately to assess the risk of congenital malformations specifically due to buprenorphine exposure [see Data ] .
Reproductive and developmental studies in rats and rabbits identified adverse events at clinically relevant and higher doses. Embryofetal death was observed in both rats and rabbits administered buprenorphine during the period of organogenesis at doses approximately 6 and 0.3 times, respectively, the human sublingual dose of 16 mg/day of buprenorphine. Pre-and post-natal development studies in rats demonstrated increased neonatal deaths at 0.3 times and above and dystocia at approximately 3 times the human sublingual dose of 16 mg/day of buprenorphine.
No clear teratogenic effects were seen when buprenorphine was administered during organogenesis with a range of doses equivalent to or greater than the human sublingual dose of 16 mg/day of buprenorphine. However, increases in skeletal abnormalities were noted in rats and rabbits administered buprenorphine daily during organogenesis at doses approximately 0.6 times and approximately equal to the human sublingual dose of 16 mg/day of buprenorphine, respectively. In a few studies, some events such as acephalus and omphalocele were also observed but these findings were not clearly treatment-related [see Data ] .
Based on animal data, advise pregnant women of the potential risk to a fetus. The estimated background risks of major birth defects and miscarriage for the indicated population are unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Disease-associated maternal and embryo-fetal risk Untreated opioid addiction in pregnancy is associated with adverse obstetrical outcomes such as low birth weight, preterm birth, and fetal death. In addition, untreated opioid addiction often results in continued or relapsing illicit opioid use.
Dose Adjustment during Pregnancy and the Postpartum Period Dosage adjustments of buprenorphine, such as a higher doses, may be required during pregnancy, even if the patient was maintained on a stable dose prior to pregnancy. Dosing should be based on individual response, and withdrawal signs and symptoms should be monitored closely and the dose adjusted as necessary. Fetal/neonatal adverse reactions Neonatal opioid withdrawal syndrome may occur in newborn infants of mothers who are receiving treatment with Buprenorphine Sublingual Tablets.
Neonatal opioid withdrawal syndrome presents as irritability, hyperactivity and abnormal sleep pattern, high pitched cry, tremor, vomiting, diarrhea, and/or failure to gain weight. Signs of neonatal withdrawal usually occur in the first days after birth. The duration and severity of neonatal opioid withdrawal syndrome may vary.
Observe newborns for signs of neonatal opioid withdrawal syndrome and manage accordingly. [see Warnings and Precautions ( 5.5 )] . Labor or Delivery Opioid-dependent women on buprenorphine maintenance therapy may require additional analgesia during labor. Opioids cross the placenta and may produce respiratory depression and psycho-physiologic effects in neonates.
An opioid overdose reversal agent, such as naloxone or nalmefene, must be available for reversal of… [Excerpted — this section continues on DailyMed.]
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of Buprenorphine Sublingual Tablets has not been established in pediatric patients.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of buprenorphine sublingual tablets, buprenorphine and naloxone sublingual film, or buprenorphine and naloxone sublingual tablets did not include sufficient numbers of subjects aged 65 and over to determine whether they responded differently than younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. Due to possible decreased hepatic, renal, or cardiac function and of concomitant disease or other drug therapy in geriatric patients, the decision to prescribe Buprenorphine Sublingual Tablets should be made cautiously in individuals 65 years of age or older and these patients should be monitored for signs and symptoms of toxicity or overdose.
🆘 Overdosage ▾
10 OVERDOSAGE Clinical Presentation The manifestations of acute overdose include pinpoint pupils, sedation, hypotension, hypoglycemia, respiratory depression, and death. Toxic leukoencephalopathy has been reported after opioid overdose and can present hours, days, or weeks after apparent recovery from the initial intoxication. Treatment of Overdose In the event of overdose, the respiratory and cardiac status of the patient should be monitored carefully.
When respiratory or cardiac functions are depressed, primary attention should be given to the re-establishment of adequate respiratory exchange through provision of a patent airway and institution of assisted or controlled ventilation. Oxygen, IV fluids, vasopressors, and other supportive measures should be employed as indicated. In the case of overdose, the primary management should be the re-establishment of adequate ventilation with mechanical assistance of respiration, if required.
An opioid overdose reversal agent may be of value for the management of buprenorphine overdose. Higher than normal doses and repeated administration may be necessary. The long duration of action of buprenorphine sublingual tablets should be taken into consideration when determining the length of treatment and medical surveillance needed to reverse the effects of an overdose.
Insufficient duration of monitoring may put patients at risk.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Buprenorphine Sublingual Tablets contain buprenorphine, a partial agonist at the mu-opioid receptor and an antagonist at the kappa-opioid receptor.
12.2Pharmacodynamics Subjective Effects: Comparisons of buprenorphine to full opioid agonists such as methadone and hydromorphone suggest that sublingual buprenorphine produces typical opioid agonist effects which are limited by a ceiling effect. Opioid agonist ceiling-effects were also observed in a double-blind, parallel group, dose-ranging comparison of single doses of buprenorphine sublingual solution (1, 2, 4, 8, 16, or 32 mg), placebo and a full agonist control at various doses. The treatments were given in ascending dose order at intervals of at least one week to 16 opioid-experienced subjects who were not physically dependent.
Both active drugs produced typical opioid agonist effects. For all measures for which the drugs produced an effect, buprenorphine produced a dose-related response. However, in each case, there was a dose that produced no further effect.
In contrast, the highest dose of the full agonist control always produced the greatest effects. Agonist objective rating scores remained elevated for the higher doses of buprenorphine (8-32 mg) longer than for the lower doses and did not return to baseline until 48 hours after drug administration. The onset of effects appeared more rapidly with buprenorphine than with the full agonist control, with most doses nearing peak effect after 100 minutes for buprenorphine compared to 150 minutes for the full agonist control.
Physiologic Effects: Buprenorphine in IV (2, 4, 8, 12 and 16 mg) and sublingual (12 mg) doses has been administered to opioid- experienced subjects who were not physically dependent to examine cardiovascular, respiratory and subjective effects at doses comparable to those used for treatment of opioid dependence. Compared to placebo, there were no statistically significant differences among any of the treatment conditions for blood pressure, heart rate, respiratory rate, O 2 saturation, or skin temperature across time.
Systolic BP was higher in the 8 mg group than placebo (3-hour AUC values). Minimum and maximum effects were similar across all treatments. Subjects remained responsive to low voice and responded to computer prompts.
Some subjects showed irritability, but no other changes were observed. The respiratory effects of sublingual buprenorphine were compared with the effects of methadone in a double-blind, parallel group, dose ranging comparison of single doses of buprenorphine sublingual solution (1, 2, 4, 8, 16, or 32 mg) and oral methadone (15, 30, 45, or 60 mg) in non-dependent, opioid-experienced volunteers. In this study, hypoventilation not requiring medical intervention was reported more frequently after buprenorphine doses of 4 mg and higher than after methadone.
Both drugs decreased O 2 saturation to the same degree. Effects on the Endocrine System: Opioids inhibit the secretion of adrenocorticotropic hormone (ACTH), cortisol, and luteinizing hormone (LH) in humans [see Adverse reactions ( 6.2 )] . They also stimulate prolactin, growth hormone (GH) secretion, and pancreatic secretion of insulin and glucagon.
Chronic use of opioids may influence the hypothalamic-pituitary-gonadal axis, leading to androgen deficiency that may manifest as low libido, impotence, erectile dysfunction, amenorrhea, or infertility. The causal role of opioids in the clinical syndrome of hypogonadism is unknown because the various medical, physical, lifestyle, and psychological stressors that may influence gonadal hormone levels have not been adequately controlled for in studies conducted to date. Patients presenting with symptoms of androgen deficiency should undergo laboratory evaluation.
Cardiac Electrophysiology Thorough QT studies with buprenorphine products have demonstrated QT prolongation ≤15 msec.
12.3Pharmacokinetics Absorption Plasma levels of buprenorphi… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Buprenorphine Sublingual Tablets contain buprenorphine, a partial agonist at the mu-opioid receptor and an antagonist at the kappa-opioid receptor.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED / STORAGE AND HANDLING Buprenorphine sublingual tablets containing 2 mg buprenorphine (as the free base, equivalent to 2.16 mg buprenorphine hydrochloride, USP) are white to off white round convex, tablet debossed with ‘˄’ on one side and plain on the other side and are supplied as: B9 Bottles of 30 with child resistant cap……………..NDC 72888-182-30 Bottles of 90 with child resistant cap……………..NDC 72888-182-90 Buprenorphine sublingual tablets containing 4 mg buprenorphine (as the free base, equivalent to 4.32 mg buprenorphine hydrochloride, USP) are white to off white round convex, tablet debossed with ‘24’ on one side and ‘˄’ on other side and are supplied as: Bottles of 30 with child resistant cap……………..NDC 72888-509-01 Bottles of 90 with child resistant cap……………..NDC 72888-509-02 Buprenorphine sublingual tablets containing 8 mg buprenorphine (as the free base, equivalent to 8.64 mg buprenorphine hydrochloride, USP) are white to off white round convex, tablet debossed with ‘˄’ on one side and plain on the other side and are supplied as: B10 Bottles of 30 with child resistant cap……………..NDC 72888-183-30 Bottles of 90 with child resistant cap……………..NDC 72888-183-90 Buprenorphine sublingual tablets containing 12 mg buprenorphine (as the free base, equivalent to 12.96 mg buprenorphine hydrochloride, USP) are white to off white round convex, tablet debossed with ‘L52’ on one side and ‘˄’ on other side and are supplied as: Bottles of 30 with child resistant cap……………..NDC 72888-510-01 Bottles of 90 with child resistant cap……………..NDC 72888-510-02 Store at 20°C to 25°C (68°F to 77°F); excursion permitted to 15° to 30°C (59° to 86°F) [See USP Controlled Room Temperature.].
Protect from moisture. Dispense in a tight, light-resistant container as defined in USP. Store Buprenorphine Sublingual Tablets securely and dispose of properly [see Patient Counseling Information ( 17 )].
📦 Storage and Handling ▾
Storage and Disposal Because of the risks associated with accidental ingestion, misuse, and abuse, advise patients to store Buprenorphine Sublingual Tablets securely, out of sight and reach of children, and in a location not accessible by others, including visitors to the home [see Warnings and Precautions ( 5.1 , 5.4 ), Drug Abuse and Dependance ( 9.2 )]. Inform patients that leaving Buprenorphine Sublingual Tablets unsecured can pose a deadly risk to others in the home. Advise patients and caregivers that when medicines are no longer needed, they should be disposed of promptly.
Expired, unwanted, or unused Buprenorphine Sublingual Tablets should be disposed of by flushing the unused medication down the toilet, if a drug take-back option is not readily available. Inform patients that they can visit www.fda.gov/drugdisposal for a complete list of medicines recommended for disposal by flushing, as well as additional information on disposal of unused medicines.
📋 Description ▾
11 DESCRIPTION Buprenorphine Sublingual Tablets are a white to off white round convex, tablet debossed with ˄ on 2 mg, ˄ on 8 mg on one side and plain on the B9 B10 other side, debossed with 24 on one side and ˄ on other side of 4 mg, debossed with L52 on one side and ˄ on other side of 12 mg. It contains buprenorphine HCl, a partial agonist at the mu-opioid receptor, and is available in four dosage strengths, buprenorphine 2 mg, buprenorphine 4 mg, buprenorphine 8 mg and buprenorphine 12 mg (as the free base, equivalent to 2.16 mg buprenorphine hydrochloride USP, 4.3 mg buprenorphine hydrochloride USP, 8.64 mg buprenorphine hydrochloride USP and 12.96 mg buprenorphine hydrochloride USP).
Each tablet also contains lactose monohydrate, mannitol, corn starch, citric acid anhydrous, sodium citrate dihydrate and magnesium stearate. Chemically, buprenorphine HCl is (2S)-2-[17-Cyclopropylmethyl-4,5α-epoxy-3-hydroxy-6-methoxy-6α,14-ethano-14α-morphinan-7α-yl]-3,3-dimethylbutan -2-ol hydrochloride. It has the following chemical structure: Buprenorphine HCl has the molecular formula C 29 H 41 NO 4 ∙HCl and the molecular weight is 504.10.
It is a white or off-white crystalline powder, sparingly soluble in water, freely soluble in methanol, soluble in alcohol and practically insoluble in cyclohexane. "Image Description"
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise patients to read the FDA-approved patient labeling ( Medication Guide ) Storage and Disposal Because of the risks associated with accidental ingestion, misuse, and abuse, advise patients to store Buprenorphine Sublingual Tablets securely, out of sight and reach of children, and in a location not accessible by others, including visitors to the home [see Warnings and Precautions ( 5.1 , 5.4 ), Drug Abuse and Dependance ( 9.2 )]. Inform patients that leaving Buprenorphine Sublingual Tablets unsecured can pose a deadly risk to others in the home.
Advise patients and caregivers that when medicines are no longer needed, they should be disposed of promptly. Expired, unwanted, or unused Buprenorphine Sublingual Tablets should be disposed of by flushing the unused medication down the toilet, if a drug take-back option is not readily available. Inform patients that they can visit www.fda.gov/drugdisposal for a complete list of medicines recommended for disposal by flushing, as well as additional information on disposal of unused medicines.
Safe Use Before initiating treatment with Buprenorphine Sublingual Tablets, explain the points listed below to caregivers and patients. Instruct patients to read the Medication Guide each time Buprenorphine Sublingual Tablets are dispensed because new information may be available. Inform patients and caregivers that potentially fatal additive effects may occur if Buprenorphine Sublingual Tablets are used with benzodiazepines or other CNS depressants.
(e.g., alcohol, non-benzodiazepine sedatives/hypnotics, anxiolytics, tranquilizers, muscle relaxants, general anesthetics, antipsychotics, gabapentinoids [gabapentin or pregabalin], and other opioids), counsel patients that such medications should not be used concomitantly unless supervised by a health care provider [see Warnings and Precautions ( 5.2 , 5.3 ), Drug Interactions ( 7 )]. Educate patients and caregivers on how to recognize respiratory depression and emphasize the importance of calling 911 or getting emergency medical help right away in the event of a known or suspected overdose [see Warnings and Precautions ( 5.2 )] .
Patient Access to an Opioid Overdose Reversal Agent for the Emergency Treatment of Opioid Overdose Inform patients and caregivers about opioid overdose reversal agents (e.g., naloxone, nalmefene) and discuss the importance of having access to an opioid overdose reversal agent. Because patients being treated for opioid use disorder are at risk for relapse, discuss the importance of having access to an opioid overdose reversal agent. Also discuss the importance of having access to an opioid overdose reversal agent if there are household members (including children) or other close contacts at risk for accidental ingestion or opioid overdose.
Discuss with the patient the options for obtaining an opioid overdose reversal agent (e.g., prescription, over-the-counter (some products), or as part of a community-based program) [see Dosage and Administration ( 2.2 ), Warnings and Precautions ( 5.3 )]. There are important differences among the opioid overdose reversal agents. Be familiar with these differences, as outlined in the approved labeling for those products, prior to recommending or prescribing such an agent.
Educate patients and caregivers on how to recognize the signs and symptoms of an opioid overdose. Explain to patients and caregivers that effects of opioid overdose reversal agents like naloxone and nalmefene are temporary, and that they must call 911 or get emergency medical help right away in all cases of known or suspected opioid overdose, even if an opioid overdose reversal agent is administered. Repeat administration may be necessary, particularly for overdose involving buprenorphine sublingual tablets, [See Dosage and Administration ( 2.2 ), Warnings and Precautions ( 5.2 ), Overdosage ( 10 )] .
Advise patients and caregivers: how to treat with an opioid overdose reversal agent in… [Excerpted — this section continues on DailyMed.]
💬 Medication Guide ▾
Medication Guide Buprenorphine (bue” pre nor’ feen) Sublingual Tablets (CIII) Rx Only IMPORTANT: Keep buprenorphine sublingual tablets in a secure place away from children. Accidental use by a child is a medical emergency and can result in death. If a child accidentally uses buprenorphine sublingual tablets, get emergency help or call 911 right away.
Tell your healthcare provider if you are living in a household where there are small children. What is the most important information I should know about Buprenorphine Sublingual Tablets? Buprenorphine Sublingual Tablets contain a medicine called buprenorphine.
Buprenorphine is an opioid that can cause serious and life threatening breathing problems, especially if you take or use certain other medicines or drugs. Ask your healthcare provider about medicines like naloxone or nalmefene that can be used in an emergency to reverse opioid overdose. including accidental use of Buprenorphine Sublingual Tablets by a child. If naloxone or nalmefene is given, you must call 911 or get emergency medical help right away to treat an overdose or accidental use of an opioid.
Buprenorphine Sublingual Tablets may cause serious and life-threatening breathing problems. Get emergency help right away if you: feel faint feel dizzy are confused feel sleepy or uncoordinated have blurred vision have slurred speech are breathing slower than normal cannot think well or clearly Do not take Buprenorphine Sublingual Tablets with certain medicines. Taking Buprenorphine Sublingual Tablets with other opioid medicines, benzodiazepines, gabapentinoids (gabapentin or pregabalin), alcohol, or other central nervous system depressants (including street drugs) can cause severe drowsiness, decreased awareness, breathing problems, coma, and death.
Do not inject (“shoot-up”) Buprenorphine Sublingual Tablets . Injecting Buprenorphine Sublingual Tablets may cause life-threatening infections and other serious health problems. Do not switch from Buprenorphine Sublingual Tablets to other medicines that contain buprenorphine without talking with your healthcare provider. The amount of buprenorphine in a dose of Buprenorphine Sublingual Tablets is not the same as in other medicines that contain buprenorphine.
Your healthcare provider will prescribe a starting dose of Buprenorphine Sublingual Tablets that may be different than other buprenorphine containing medicines you may have been taking. Do not stop taking Buprenorphine Sublingual Tablets suddenly. You could become sick and have withdrawal symptoms because your body has become used to the medicine (physical dependence).
Physical dependence is not the same as drug addiction. In an emergency, have family members tell emergency department staff that you are physically dependent on an opioid and are being treated with Buprenorphine Sublingual Tablets. Never give anyone else your Buprenorphine Sublingual Tablets.
They could die from taking it. Selling or giving away Buprenorphine Sublingual Tablets is against the law. Store Buprenorphine Sublingual Tablets securely, out of sight and reach of children, and in a location not accessible by others, including visitors to the home.
What is Buprenorphine Sublingual Tablets? Buprenorphine Sublingual Tablets are a prescription medicine used to treat opioid addiction in adults and is part of a complete treatment program that also includes counseling and behavioral therapy. Who should not take Buprenorphine Sublingual Tablets?
Do not take Buprenorphine Sublingual Tablets if you are allergic to buprenorphine. Before taking Buprenorphine Sublingual Tablets, tell your healthcare provider about all of your medical conditions, including if you have: trouble breathing or lung problems a curve in your spine that affects your breathing Addison’s disease an enlarged prostate (men) problems urinating Liver, kidney, or gallbladder problems alcoholism a head injury or brain problem mental health problems adrenal gland or thyroid gland probl… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
8.3Females and Males of Reproductive Potential Infertility Chronic use of opioids may cause reduced fertility in females and males of reproductive potential. It is not known whether these effects on fertility are reversible [see Adverse Reactions ( 6.2 ), Clinical Pharmacology ( 12.2 ), Nonclinical Toxicology ( 13.1 )] .
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption Plasma levels of buprenorphine increased with the sublingual dose of Buprenorphine Sublingual Tablets ( Table 4 ). There was wide inter-patient variability in the sublingual absorption of buprenorphine, but within subjects the variability was low. Both C max and AUC of buprenorphine increased in a linear fashion with the increase in dose (in the range of 4 to 16 mg), although the increase was not directly dose-proportional.
Table 4 Pharmacokinetic Parameters of Buprenorphine and Norbuprenorphine after the sublingual administration of Buprenorphine Sublingual Tablets Dose Analyte Mean SD C max (ng/mL) T max (h ) AUC inf (h∙ng/mL) t 1/2 (h) 2 mg Buprenorphine Mean SD 1.25 0.584 1.84 0.62 10.93 3.945 31.66
12.66Norbuprenorphine Mean SD 0.301 0.127 2.36 2.75 12.39 4.526 39.28 20.85 8 mg Buprenorphine Mean SD 2.88 1.14 1.28 0.46 28.39 10.22 35.01
14.7Norbuprenorphine Mean SD 1.38 0.752 1.75 2.11 50.18 22.61 44.33 19.27 16 mg Buprenorphine Mean SD 4.70 2.16 1.42 0.50 47.09 20.03 36.51
13.99Norbuprenorphine Mean SD 2.65 1.62 1.52 1.34 92.31 34.74 40.35
12.07Distribution Buprenorphine is approximately 96% protein bound, primarily to alpha and beta globulin. Elimination Metabolism Buprenorphine undergoes both N-dealkylation to norbuprenorphine and glucuronidation. The N-dealkylation pathway is mediated primarily by CYP3A4.
Norbuprenorphine, the major metabolite, can further undergo glucuronidation. Norbuprenorphine has been found to bind opioid receptors in-vitro; however, it is not known whether norbuprenorphine contributes to the overall effect of Buprenorphine Sublingual Tablets. Excretion A mass balance study of buprenorphine showed complete recovery of radiolabel in urine (30%) and feces (69%) collected up to 11 days after dosing.
Almost all of the dose was accounted for in terms of buprenorphine, norbuprenorphine, and two unidentified buprenorphine metabolites. In urine, most of buprenorphine and norbuprenorphine was conjugated (buprenorphine, 1% free and 9.4% conjugated; norbuprenorphine, 2.7% free and 11% conjugated). In feces, almost all of the buprenorphine and norbuprenorphine were free (buprenorphine, 33% free and 5% conjugated; norbuprenorphine, 21% free and 2% conjugated).
When Buprenorphine Sublingual Tablets are administered sublingually, buprenorphine has a mean elimination half-life from plasma ranging from 31 to 35 hours. Drug Interactions Studies CYP3A4 Inhibitors and Inducers Buprenorphine has been found to be a CYP2D6 and CYP3A4 inhibitor and its major metabolite, norbuprenorphine has been found to be a moderate CYP2D6 inhibitor in in vitro studies employing human liver microsomes. However, the relatively low plasma concentrations of buprenorphine and norbuprenorphine resulting from therapeutic doses are not expected to raise significant drug-drug interaction concerns [see Drug Interactions ( 7 )].
Specific Populations Hepatic Impairment In a pharmacokinetic study, the disposition of buprenorphine was determined after administering a 2.0 mg/0.5 mg buprenorphine and naloxone sublingual tablets in subjects with varied degrees of hepatic impairment as indicated by Child-Pugh criteria. The disposition of buprenorphine in patients with hepatic impairment was compared to disposition in subjects with normal hepatic function. In subjects with mild hepatic impairment, the changes in mean C max , AUC 0-last , and half-life values of buprenorphine were not clinically significant.
For subjects with moderate and severe hepatic impairment, mean C max , AUC 0-last , and half-life values of buprenorphine were increased ( Table 5 ) [see Warnings and Precautions ( 5.12 ) and Use in Specific Populations ( 8.6 )] . Table 5 Changes in Buprenorphine Pharmacokinetic Parameters in Subjects with Moderate and Severe Hepatic Impairment Hepatic Impairment PK Parameters Increase in buprenorphine compared to healthy subjects Moderate C max 8% AUC 0-last 64% Half-life 35% Severe C max 72% AUC 0-last 181% Hal… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Subjective Effects: Comparisons of buprenorphine to full opioid agonists such as methadone and hydromorphone suggest that sublingual buprenorphine produces typical opioid agonist effects which are limited by a ceiling effect. Opioid agonist ceiling-effects were also observed in a double-blind, parallel group, dose-ranging comparison of single doses of buprenorphine sublingual solution (1, 2, 4, 8, 16, or 32 mg), placebo and a full agonist control at various doses. The treatments were given in ascending dose order at intervals of at least one week to 16 opioid-experienced subjects who were not physically dependent.
Both active drugs produced typical opioid agonist effects. For all measures for which the drugs produced an effect, buprenorphine produced a dose-related response. However, in each case, there was a dose that produced no further effect.
In contrast, the highest dose of the full agonist control always produced the greatest effects. Agonist objective rating scores remained elevated for the higher doses of buprenorphine (8-32 mg) longer than for the lower doses and did not return to baseline until 48 hours after drug administration. The onset of effects appeared more rapidly with buprenorphine than with the full agonist control, with most doses nearing peak effect after 100 minutes for buprenorphine compared to 150 minutes for the full agonist control.
Physiologic Effects: Buprenorphine in IV (2, 4, 8, 12 and 16 mg) and sublingual (12 mg) doses has been administered to opioid- experienced subjects who were not physically dependent to examine cardiovascular, respiratory and subjective effects at doses comparable to those used for treatment of opioid dependence. Compared to placebo, there were no statistically significant differences among any of the treatment conditions for blood pressure, heart rate, respiratory rate, O 2 saturation, or skin temperature across time.
Systolic BP was higher in the 8 mg group than placebo (3-hour AUC values). Minimum and maximum effects were similar across all treatments. Subjects remained responsive to low voice and responded to computer prompts.
Some subjects showed irritability, but no other changes were observed. The respiratory effects of sublingual buprenorphine were compared with the effects of methadone in a double-blind, parallel group, dose ranging comparison of single doses of buprenorphine sublingual solution (1, 2, 4, 8, 16, or 32 mg) and oral methadone (15, 30, 45, or 60 mg) in non-dependent, opioid-experienced volunteers. In this study, hypoventilation not requiring medical intervention was reported more frequently after buprenorphine doses of 4 mg and higher than after methadone.
Both drugs decreased O 2 saturation to the same degree. Effects on the Endocrine System: Opioids inhibit the secretion of adrenocorticotropic hormone (ACTH), cortisol, and luteinizing hormone (LH) in humans [see Adverse reactions ( 6.2 )] . They also stimulate prolactin, growth hormone (GH) secretion, and pancreatic secretion of insulin and glucagon.
Chronic use of opioids may influence the hypothalamic-pituitary-gonadal axis, leading to androgen deficiency that may manifest as low libido, impotence, erectile dysfunction, amenorrhea, or infertility. The causal role of opioids in the clinical syndrome of hypogonadism is unknown because the various medical, physical, lifestyle, and psychological stressors that may influence gonadal hormone levels have not been adequately controlled for in studies conducted to date. Patients presenting with symptoms of androgen deficiency should undergo laboratory evaluation.
Cardiac Electrophysiology Thorough QT studies with buprenorphine products have demonstrated QT prolongation ≤15 msec.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES Clinical data on the safety and efficacy of Buprenorphine Sublingual Tablets were derived from studies of buprenorphine sublingual tablets formulations, with and without naloxone, and from studies of sublingual administration of a more bioavailable ethanolic solution of buprenorphine. Buprenorphine sublingual tablets were studied in 1834 patients; buprenorphine and naloxone tablets in 575 patients, and buprenorphine sublingual solutions in 2470 patients. A total of 1270 women received buprenorphine in those clinical trials.
Dosing recommendations are based on data from one trial of both tablet formulations and two trials of the ethanolic solution. All trials used buprenorphine in conjunction with psychosocial counseling as part of a comprehensive addiction treatment program. There were no clinical studies conducted to assess the efficacy of buprenorphine as the only component of treatment.
In a double-blind placebo- and active-controlled study, 326 heroin-addicted subjects were randomly assigned to either buprenorphine and naloxone sublingual tablets, 16 /4 mg per day; buprenorphine sublingual tablets, 16 mg per day; or placebo sublingual tablets. For subjects randomized to either active treatment, dosing began with one 8 mg buprenorphine sublingual tablets on Day 1, followed by 16 mg (two 8 mg tablets) of buprenorphine sublingual tablets on Day 2. On Day 3, those randomized to receive buprenorphine and naloxone sublingual tablets were switched to the combination tablet.
Subjects randomized to placebo received one placebo tablet on Day 1 and two placebo tablets per day thereafter for four weeks. Subjects were seen daily in the clinic (Monday through Friday) for dosing and efficacy assessments. Take-home doses were provided for weekends.
Subjects were instructed to hold the medication under the tongue for approximately 5 to 10 minutes until completely dissolved. Subjects received counseling regarding HIV infection and up to one hour of individualized counseling per week. The primary study comparison was to assess the efficacy of buprenorphine and naloxone sublingual tablets and buprenorphine sublingual tablets individually against placebo sublingual tablets.
The percentage of thrice-weekly urine samples that were negative for non-study opioids was statistically higher for both buprenorphine and naloxone sublingual tablets and buprenorphine sublingual tablets than for placebo sublingual tablets. In a double-blind, double-dummy, parallel-group study comparing buprenorphine ethanolic solution to a full agonist active control, 162 subjects were randomized to receive the ethanolic sublingual solution of buprenorphine at 8 mg/day (a dose which is roughly comparable to a dose of 12 mg per day of buprenorphine sublingual tablets), or two relatively low doses of active control, one of which was low enough to serve as an alternative to placebo, during a 3-10 day induction phase, a 16-week maintenance phase and a 7-week detoxification phase.
Buprenorphine was titrated to maintenance dose by Day 3; active control doses were titrated more gradually. Maintenance dosing continued through Week 17, and then medications were tapered by approximately 20%-30% per week over Weeks 18-24, with placebo dosing for the last two weeks. Subjects received individual and/or group counseling weekly.
Based on retention in treatment and the percentage of thrice-weekly urine samples negative for non-study opioids, buprenorphine was more effective than the low dose of the control, in keeping heroin addicts in treatment and in reducing their use of opioids while in treatment. The effectiveness of buprenorphine, 8 mg per day was similar to that of the moderate active control dose, but equivalence was not demonstrated. In a dose-controlled, double-blind, parallel-group, 16-week study, 731 subjects were randomized to receive one of four doses of buprenorphine ethanolic solution: 1 mg, 4 mg, 8 mg, and 16 mg.
Buprenorphine was titrated to maintenan… [Excerpted — this section continues on DailyMed.]
🔒 Drug Abuse and Dependence ▾
9 DRUG ABUSE AND DEPENDENCE
9.1Controlled Substance Buprenorphine Sublingual Tablets contain buprenorphine, a Schedule III controlled substance under the Controlled Substances Act.
9.2Abuse Buprenorphine, like morphine and other opioids, has the potential for being abused and is subject to criminal diversion. This should be considered when prescribing or dispensing buprenorphine in situations when the clinician is concerned about an increased risk of misuse, abuse, or diversion. Healthcare professionals should contact their state professional licensing board or state controlled substances authority for information on how to prevent and detect abuse or diversion of this product.
Patients who continue to misuse, abuse, or divert, buprenorphine products or other opioids should be provided or referred for more intensive and structured treatment. Abuse of buprenorphine poses a risk of overdose and death. This risk is increased with the use of buprenorphine and alcohol and other substances, especially benzodiazepines.
The healthcare provider may be able to more easily detect misuse or diversion by maintaining records of medication prescribed including date, dose, quantity, frequency of refills, and renewal requests of medication prescribed. Proper assessment of the patient, proper prescribing practices, periodic re-evaluation of therapy, and proper handling and storage of the medication are appropriate measures that help to limit abuse of opioid drugs.
9.3Dependence Buprenorphine is a partial agonist at the mu-opioid receptor and chronic administration produces physical dependence of the opioid type, characterized by moderate withdrawal signs and symptoms upon abrupt discontinuation or rapid taper. The withdrawal syndrome is typically milder than seen with full agonists and may be delayed in onset [see Warnings and Precautions ( 5.7 )]. Neonatal opioid withdrawal syndrome (NOWS) is an expected and treatable outcome of prolonged use of opioids during pregnancy [see Warnings and Precautions ( 5.5 )].
🔒 Controlled Substance ▾
9.1Controlled Substance Buprenorphine Sublingual Tablets contain buprenorphine, a Schedule III controlled substance under the Controlled Substances Act.
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity Carcinogenicity studies of buprenorphine were conducted in Sprague-Dawley rats and CD-1 mice. Buprenorphine was administered in the diet to rats at doses of 0.6, 5.5, and 56 mg/kg/day (estimated exposure was approximately 0.4, 3 and 35 times the recommended human daily sublingual dose of 16 mg on a mg/m 2 basis) for 27 months. As in the buprenorphine/naloxone carcinogenicity study in rat, statistically significant dose-related increases in Leydig cell tumors occurred.
In an 86-week study in CD-1 mice, buprenorphine was not carcinogenic at dietary doses up to 100 mg/kg/day (estimated exposure was approximately 30 times the recommended human daily sublingual dose of 16 mg on a mg/m 2 basis). Mutagenicity Buprenorphine was studied in a series of tests utilizing gene, chromosome, and DNA interactions in both prokaryotic and eukaryotic systems. Results were negative in yeast ( S. cerevisiae) for recombinant, gene convertant, or forward mutations; negative in Bacillus subtilis "rec" assay, negative for clastogenicity in CHO cells, Chinese hamster bone marrow and spermatogonia cells, and negative in the mouse lymphoma L5178Y assay.
Results were equivocal in the Ames test: negative in studies in two laboratories, but positive for frame shift mutation at a high dose (5 mg/plate) in a third study. Results were positive in the Green-Tweets ( E. coli ) survival test, positive in a DNA synthesis inhibition (DSI) test with testicular tissue from mice, for both in vivo and in vitro incorporation of [ 3 H]thymidine, and positive in unscheduled DNA synthesis (UDS) test using testicular cells from mice. Impairment of Fertility Reproduction studies of buprenorphine in rats demonstrated no evidence of impaired fertility at daily oral doses up to 80 mg/kg/day (estimated exposure was approximately 50 times the recommended human daily sublingual dose of 16 mg on a mg/m 2 basis) or up to 5 mg/kg/day IM or SC (estimated exposure was approximately 3 times the recommended human daily sublingual dose of 16 mg on a mg/m 2 basis).
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity Carcinogenicity studies of buprenorphine were conducted in Sprague-Dawley rats and CD-1 mice. Buprenorphine was administered in the diet to rats at doses of 0.6, 5.5, and 56 mg/kg/day (estimated exposure was approximately 0.4, 3 and 35 times the recommended human daily sublingual dose of 16 mg on a mg/m 2 basis) for 27 months. As in the buprenorphine/naloxone carcinogenicity study in rat, statistically significant dose-related increases in Leydig cell tumors occurred.
In an 86-week study in CD-1 mice, buprenorphine was not carcinogenic at dietary doses up to 100 mg/kg/day (estimated exposure was approximately 30 times the recommended human daily sublingual dose of 16 mg on a mg/m 2 basis). Mutagenicity Buprenorphine was studied in a series of tests utilizing gene, chromosome, and DNA interactions in both prokaryotic and eukaryotic systems. Results were negative in yeast ( S. cerevisiae) for recombinant, gene convertant, or forward mutations; negative in Bacillus subtilis "rec" assay, negative for clastogenicity in CHO cells, Chinese hamster bone marrow and spermatogonia cells, and negative in the mouse lymphoma L5178Y assay.
Results were equivocal in the Ames test: negative in studies in two laboratories, but positive for frame shift mutation at a high dose (5 mg/plate) in a third study. Results were positive in the Green-Tweets ( E. coli ) survival test, positive in a DNA synthesis inhibition (DSI) test with testicular tissue from mice, for both in vivo and in vitro incorporation of [ 3 H]thymidine, and positive in unscheduled DNA synthesis (UDS) test using testicular cells from mice. Impairment of Fertility Reproduction studies of buprenorphine in rats demonstrated no evidence of impaired fertility at daily oral doses up to 80 mg/kg/day (estimated exposure was approximately 50 times the recommended human daily sublingual dose of 16 mg on a mg/m 2 basis) or up to 5 mg/kg/day IM or SC (estimated exposure was approximately 3 times the recommended human daily sublingual dose of 16 mg on a mg/m 2 basis).
📖 Instructions for Use ▾
INSTRUCTIONS FOR USE Buprenorphine (bue” pre nor’ feen) Sublingual Tablets, CIII Rx Only This “Instructions for Use” contains information on how to correctly take Buprenorphine Sublingual Tablets. Important Information You Need to Know Before Taking Buprenorphine Sublingual Tablets: Your healthcare provider should show you how to take Buprenorphine Sublingual Tablets the right way. Preparing to take Buprenorphine Sublingual Tablets: Put the tablets under your tongue.
Let them dissolve completely. While Buprenorphine Sublingual Tablet is dissolving, do not chew or swallow the tablet because the medicine will not work as well. Talking while the tablet is dissolving can affect how well the medicine in the Buprenorphine Sublingual Tablets is absorbed.
After Buprenorphine Sublingual Tablet is completely dissolved, rinse your mouth with water and swallow. Wait for at least one hour before brushing teeth. If you miss a dose of Buprenorphine Sublingual Tablets, take your medicine when you remember.
If it is almost time for your next dose, skip the missed dose and take the next dose at your regular time. Do not take 2 doses at the same time unless your healthcare provider tells you to. If you are not sure about your dosing, call your healthcare provider.
Do not stop taking Buprenorphine Sublingual Tablets suddenly. You could become sick and have withdrawal symptoms because your body has become used to the medicine. Physical dependence is not the same as drug addiction.
Your healthcare provider can tell you more about the differences between physical dependence and drug addiction. To have fewer withdrawal symptoms, ask your healthcare provider how to stop using Buprenorphine Sublingual Tablets the right way. If you take too many Buprenorphine Sublingual Tablets or overdose, call Poison Control or get emergency medical help right away.
Storing Buprenorphine Sublingual Tablets: Store Buprenorphine Sublingual Tablets at room temperature between 20°C to 25°C (68°F to 77°F); excursion permitted to 15° to 30°C (59° to 86°F) [See USP Controlled Room Temperature.] Protect from moisture. Keep Buprenorphine Sublingual Tablets in a safe place, out of the sight and reach of children. Disposing of Buprenorphine Sublingual Tablets: Dispose of unused Buprenorphine Sublingual Tablets as soon as you no longer need them.
Dispose of expired, unwanted or unused Buprenorphine Sublingual Tablets by promptly flushing down the toilet (if a drug take‐back option is not readily available). Visit www.fda.gov/drugdisposal for additional information on disposal of unused medicines. If you need help with disposal of Buprenorphine Sublingual Tablets, call Advagen Pharma Ltd, at 866-488-0312.
All registered trademarks are the property of their respective owners. This “Instructions for Use” has been approved by the U.S. Food and Drug Administration.
Rev. 07/2026 "Image Description"
📄 Recent Major Changes ▾
Dosage and Administration ( 2.2 ) 10/2025 Warnings and Precautions ( 5.2 , 5.3 ) 10/2025
📄 Package Label / Principal Display Panel ▾
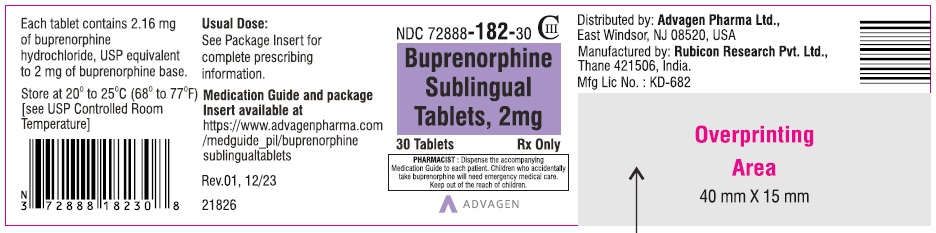
PACKAGE LABEL. PRINCIPAL DISPLAY PANEL Buprenorphine sublingual tablets 2 mg - NDC 72888-182-30 - 30 Tablets Label Buprenorphine sublingual tablets 2 mg - NDC 72888-182-90 - 90 Tablets Label Buprenorphine sublingual tablets 4 mg - NDC 72888-509-01 - 30 Tablets Label Buprenorphine sublingual tablets 4 mg - NDC 72888-509-02 - 90 Tablets Label Buprenorphine sublingual tablets 8 mg - NDC 72888-183-30 - 30 Tablets Label Buprenorphine sublingual tablets 8 mg - NDC 72888-183-90 - 90 Tablets Label Buprenorphine sublingual tablets 12 mg - NDC 72888-510-01 - 30 Tablets Label Buprenorphine sublingual tablets 12 mg - NDC 72888-510-02 - 90 Tablets Label "Image Description" "Image Description" "Image Description" "Image Description" "Image Description" "Image Description" "Image Description" "Image Description"