
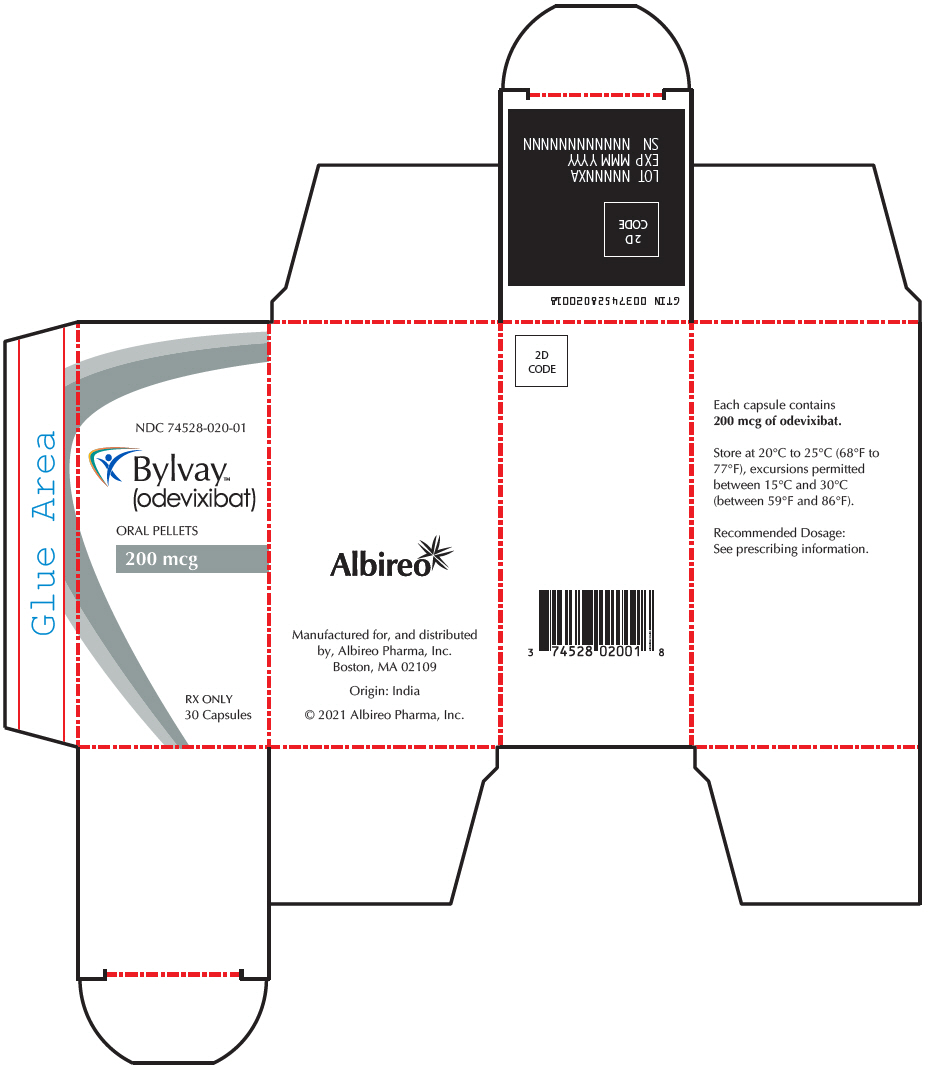
BYLVAY odevixibat 200 ug Capsule, Coated Pellets, 30-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Ileal Bile Acid Transporter Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Odevixibat is used to treat itching caused by familial intrahepatic cholestasis (PFIC; a liver disease in which the flow of bile from the liver is blocked) or Alagille syndrome (ALCS; an inherited condition in which bile builds up in the liver and causes liver damage). Odevixibat is in a class of medications called ileal bile acid transporter (IBAT) inhibitors. It works by decreasing the level of bile acids from the small intestine.
Read the full MedlinePlus article ↗- Bylvay works in the intestine to block the recycling of bile acids — substances produced by the liver — back into the bloodstream. In conditions like PFIC and Alagille syndrome, bi...
- What exactly does Bylvay do, and why does my child need it?
- Give Bylvay once every morning with the first meal of the day. Capsules should be swallowed whole — do not crush or chew them. The dose is based on your child's weight, so always f...
- How and when should we give Bylvay each day?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Odevixibat — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
0.8 mg
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
39 mg
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
2 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $528.63 | $15,858.95 / 30 capsules |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Bylvay 200 ug 15054-3301-01 | Ipsen | 30 capsules | — | — | FDA listed | — |
| Bylvay 200 ugthis 74528-0020-01 | Albireo | 30 capsules | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 12545705 ↗ | Method of use | U-3186 | Nov 8, 2031 |
| US 12545705 ↗ | Method of use | U-3186 | Nov 8, 2031 |
| US 12545705 ↗ | Method of use | U-3186 | Nov 8, 2031 |
| US 12545705 ↗ | Method of use | U-3186 | Nov 8, 2031 |
| US 12545705 ↗ | Method of use | U-3648 | Nov 8, 2031 |
| US 12545705 ↗ | Method of use | U-3648 | Nov 8, 2031 |
| US 12545705 ↗ | Method of use | U-3648 | Nov 8, 2031 |
| US 12545705 ↗ | Method of use | U-3648 | Nov 8, 2031 |
| US 12508234 ↗ | Method of use | U-3186 | Jun 20, 2039 |
| US 12508234 ↗ | Method of use | U-3648 | Jun 20, 2039 |
| US 12508234 ↗ | Method of use | U-3648 | Jun 20, 2039 |
| US 12508234 ↗ | Method of use | U-3648 | Jun 20, 2039 |
| US 12508234 ↗ | Method of use | U-3648 | Jun 20, 2039 |
| US 12508234 ↗ | Method of use | U-3186 | Jun 20, 2039 |
| US 12508234 ↗ | Method of use | U-3186 | Jun 20, 2039 |
| US 12508234 ↗ | Method of use | U-3186 | Jun 20, 2039 |
| US 10487111 ↗ | Method of use | U-3186 | Nov 8, 2031 |
| US 10981952 ↗ | Method of use | U-3187 | Nov 8, 2031 |
| US 10981952 ↗ | Method of use | U-3186 | Nov 8, 2031 |
| US 10981952 ↗ | Method of use | U-3186 | Nov 8, 2031 |
| US 10981952 ↗ | Method of use | U-3187 | Nov 8, 2031 |
| US 10487111 ↗ | Method of use | U-3186 | Nov 8, 2031 |
| US 10981952 ↗ | Method of use | U-3186 | Nov 8, 2031 |
| US 10981952 ↗ | Method of use | U-3187 | Nov 8, 2031 |
| US 10487111 ↗ | Method of use | U-3186 | Nov 8, 2031 |
| US 10487111 ↗ | Method of use | U-3186 | Nov 8, 2031 |
| US 10981952 ↗ | Method of use | U-3187 | Nov 8, 2031 |
| US 10981952 ↗ | Method of use | U-3186 | Nov 8, 2031 |
| US 9694018 ↗ | Method of use | U-3186 | Mar 18, 2034 |
| US 10011633 ↗ | Method of use | U-3186 | Nov 8, 2031 |
| US 10093697 ↗ | Method of use | U-3186 | Nov 8, 2031 |
| US 10093697 ↗ | Method of use | U-3186 | Nov 8, 2031 |
| US 10011633 ↗ | Method of use | U-3186 | Nov 8, 2031 |
| US 9694018 ↗ | Method of use | U-3186 | Mar 18, 2034 |
| US 10011633 ↗ | Method of use | U-3186 | Nov 8, 2031 |
| US 10093697 ↗ | Method of use | U-3186 | Nov 8, 2031 |
| US 9694018 ↗ | Method of use | U-3186 | Mar 18, 2034 |
| US 10011633 ↗ | Method of use | U-3186 | Nov 8, 2031 |
| US 10093697 ↗ | Method of use | U-3186 | Nov 8, 2031 |
| US 9694018 ↗ | Method of use | U-3186 | Mar 18, 2034 |
| US 12447156 ↗ | Method of use | U-3186 | Nov 12, 2041 |
| US 12447156 ↗ | Method of use | U-3186 | Nov 12, 2041 |
| US 12447156 ↗ | Method of use | U-3186 | Nov 12, 2041 |
| US 12447156 ↗ | Method of use | U-3186 | Nov 12, 2041 |
| US 11583539 ↗ | Method of use | U-3186 | Nov 12, 2041 |
| US 11583539 ↗ | Method of use | U-3186 | Nov 12, 2041 |
| US 11583539 ↗ | Method of use | U-3186 | Nov 12, 2041 |
| US 11583539 ↗ | Method of use | U-3186 | Nov 12, 2041 |
| US 10093697 ↗ | Method of use | U-3648 | Nov 8, 2031 |
| US 10093697 ↗ | Method of use | U-3648 | Nov 8, 2031 |
| US 10093697 ↗ | Method of use | U-3648 | Nov 8, 2031 |
| US 10093697 ↗ | Method of use | U-3648 | Nov 8, 2031 |
| US 10011633 ↗ | Method of use | U-3648 | Nov 8, 2031 |
| US 10011633 ↗ | Method of use | U-3648 | Nov 8, 2031 |
| US 10011633 ↗ | Method of use | U-3648 | Nov 8, 2031 |
| US 10011633 ↗ | Method of use | U-3648 | Nov 8, 2031 |
| US 9694018 ↗ | Method of use | U-3648 | Mar 18, 2034 |
| US 9694018 ↗ | Method of use | U-3648 | Mar 18, 2034 |
| US 9694018 ↗ | Method of use | U-3648 | Mar 18, 2034 |
| US 9694018 ↗ | Method of use | U-3648 | Mar 18, 2034 |
| US 11732006 ↗ | Method of use | U-3648 | Nov 8, 2031 |
| US 11732006 ↗ | Method of use | U-3648 | Nov 8, 2031 |
| US 11732006 ↗ | Method of use | U-3648 | Nov 8, 2031 |
| US 11732006 ↗ | Method of use | U-3648 | Nov 8, 2031 |
| US 11732006 ↗ | Method of use | U-3186 | Nov 8, 2031 |
| US 11732006 ↗ | Method of use | U-3186 | Nov 8, 2031 |
| US 11732006 ↗ | Method of use | U-3186 | Nov 8, 2031 |
| US 11732006 ↗ | Method of use | U-3186 | Nov 8, 2031 |
| US 12187812 ↗ | Method of use | U-3186 | Nov 8, 2031 |
| US 12187812 ↗ | Method of use | U-3186 | Nov 8, 2031 |
| US 12187812 ↗ | Method of use | U-3186 | Nov 8, 2031 |
| US 12187812 ↗ | Method of use | U-3186 | Nov 8, 2031 |
| US 12187812 ↗ | Method of use | U-3648 | Nov 8, 2031 |
| US 12187812 ↗ | Method of use | U-3648 | Nov 8, 2031 |
| US 12187812 ↗ | Method of use | U-3648 | Nov 8, 2031 |
| US 12187812 ↗ | Method of use | U-3648 | Nov 8, 2031 |
| US 11365182 ↗ | Method of use | U-3648 | Jun 20, 2039 |
| US 11365182 ↗ | Method of use | U-3648 | Jun 20, 2039 |
| US 11365182 ↗ | Method of use | U-3648 | Jun 20, 2039 |
| US 11365182 ↗ | Method of use | U-3648 | Jun 20, 2039 |
| US 10981952 ↗ | Method of use | U-3648 | Nov 8, 2031 |
| US 10981952 ↗ | Method of use | U-3649 | Nov 8, 2031 |
| US 10981952 ↗ | Method of use | U-3649 | Nov 8, 2031 |
| US 10981952 ↗ | Method of use | U-3648 | Nov 8, 2031 |
| US 10981952 ↗ | Method of use | U-3648 | Nov 8, 2031 |
| US 10981952 ↗ | Method of use | U-3649 | Nov 8, 2031 |
| US 10981952 ↗ | Method of use | U-3648 | Nov 8, 2031 |
| US 10981952 ↗ | Method of use | U-3649 | Nov 8, 2031 |
| US 10487111 ↗ | Method of use | U-3648 | Nov 8, 2031 |
| US 10487111 ↗ | Method of use | U-3648 | Nov 8, 2031 |
| US 10487111 ↗ | Method of use | U-3648 | Nov 8, 2031 |
| US 10487111 ↗ | Method of use | U-3648 | Nov 8, 2031 |
| US 11365182 ↗ | Method of use | U-3186 | Jun 20, 2039 |
| US 11365182 ↗ | Method of use | U-3186 | Jun 20, 2039 |
| US 11365182 ↗ | Method of use | U-3186 | Jun 20, 2039 |
| US 11365182 ↗ | Method of use | U-3186 | Jun 20, 2039 |
| US 11801226 ↗ | Drug product | — | Jun 20, 2039 |
| US 11801226 ↗ | Drug product | — | Jun 20, 2039 |
| US 11801226 ↗ | Drug product | — | Jun 20, 2039 |
| US 11802115 ↗ | Drug product | — | Jun 20, 2039 |
| US 12091394 ↗ | Drug substance | — | Jun 20, 2039 |
| US 11802115 ↗ | Drug product | — | Jun 20, 2039 |
| US 12091394 ↗ | Drug substance | — | Jun 20, 2039 |
| US 12091394 ↗ | Drug substance | — | Jun 20, 2039 |
| US 11802115 ↗ | Drug product | — | Jun 20, 2039 |
| US 10975046 ↗ | Drug substance | — | Jun 20, 2039 |
| US 10975046 ↗ | Drug substance | — | Jun 20, 2039 |
| US 10975046 ↗ | Drug substance | — | Jun 20, 2039 |
| US 12091394 ↗ | Drug substance | — | Jun 20, 2039 |
| US 10975046 ↗ | Drug substance | — | Jun 20, 2039 |
| US 11801226 ↗ | Drug product | — | Jun 20, 2039 |
| US 11802115 ↗ | Drug product | — | Jun 20, 2039 |
| Code | What it grants | Expires |
|---|---|---|
| I-918 | New indication (3-year) | Jun 13, 2026 |
| NCE | New Chemical Entity (5-year) | Jul 20, 2026 |
| ODE-363 | Orphan Drug Exclusivity (7-year) | Jul 20, 2028 |
| ODE-436 | Orphan Drug Exclusivity (7-year) | Jun 13, 2030 |
| I-918 | New indication (3-year) | Jun 13, 2026 |
| NCE | New Chemical Entity (5-year) | Jul 20, 2026 |
| ODE-363 | Orphan Drug Exclusivity (7-year) | Jul 20, 2028 |
| ODE-436 | Orphan Drug Exclusivity (7-year) | Jun 13, 2030 |
| I-918 | New indication (3-year) | Jun 13, 2026 |
| NCE | New Chemical Entity (5-year) | Jul 20, 2026 |
| ODE-363 | Orphan Drug Exclusivity (7-year) | Jul 20, 2028 |
| ODE-436 | Orphan Drug Exclusivity (7-year) | Jun 13, 2030 |
| I-918 | New indication (3-year) | Jun 13, 2026 |
| NCE | New Chemical Entity (5-year) | Jul 20, 2026 |
| ODE-363 | Orphan Drug Exclusivity (7-year) | Jul 20, 2028 |
| ODE-436 | Orphan Drug Exclusivity (7-year) | Jun 13, 2030 |
Is there a generic version of BYLVAY 200 MCG PELLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 74528-0020-01 You're viewing this | 1 BOTTLE in 1 CARTON (74528-020-01) / 30 CAPSULE, COATED PELLETS in 1 BOTTLE | 2021-07-20 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE BYLVAY is an ileal bile acid transporter (IBAT) inhibitor indicated for: Progressive Familial Intrahepatic Cholestasis (PFIC) the treatment of pruritus in patients 3 months of age and older with progressive familial intrahepatic cholestasis (PFIC). ( 1.1 ) Limitation of Use : BYLVAY is not recommended in a subgroup of PFIC type 2 patients with specific ABCB11 variants resulting in non-functional or complete absence of the bile salt export pump protein. ( 12.5 , 14.1 ) Alagille Syndrome (ALGS) the treatment of cholestatic pruritus in patients 12 months of age and older with Alagille syndrome (ALGS).
( 1.2 )
1.1Progressive Familial Intrahepatic Cholestasis (PFIC) BYLVAY is indicated for the treatment of pruritus in patients 3 months of age and older with PFIC. Limitations of Use BYLVAY is not recommended in a subgroup of PFIC type 2 patients with specific ABCB11 variants resulting in non-functional or complete absence of the bile salt export pump (BSEP) protein [see Clinical Pharmacology (12.5) and Clinical Studies (14.1) ].
1.2Alagille Syndrome (ALGS) BYLVAY is indicated for the treatment of cholestatic pruritus in patients 12 months of age and older with ALGS.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Recommended Dosage PFIC: Patients 3 months and older: 40 mcg/kg taken orally once daily. ( 2.1 ) If there is no improvement in pruritus after 3 months, the dosage may be increased in 40 mcg/kg increments up to 120 mcg/kg once daily, not to exceed a daily dosage of 6 mg/day. ( 2.1 ) ALGS: Patients 12 months and older: 120 mcg/kg taken orally once daily.
( 2.2 ) Preparation and Administration Instructions Administer BYLVAY in the morning with a meal. ( 2.4 ) Do not crush or chew capsules. ( 2.4 ) See full prescribing information for preparation and administration instructions.
( 2.4 )
2.1Recommended Dosage for Progressive Familial Intrahepatic Cholestasis (PFIC) in Patients Aged 3 Months and Older The recommended dosage of BYLVAY is 40 mcg/kg taken orally once daily in the morning with a meal. Table 1 below shows the recommended once daily dosage by body weight. If there is no improvement in pruritus after 3 months, the dosage may be increased in 40 mcg/kg increments up to 120 mcg/kg once daily not to exceed a daily dosage of 6 mg/day.
BYLVAY oral pellets are intended for use by patients weighing less than 19.5 kilograms. BYLVAY capsules are intended for use by patients weighing 19.5 kilograms or above. Table 1.
Recommended Dosage for PFIC in Patients aged 3 months and older (40 mcg/kg/day) Body Weight (kg) Once Daily Dosage (mcg) 7.4 and below 200 7.5 to 12.4 400 12.5 to 17.4 600 17.5 to 25.4 800 25.5 to 35.4 1,200 35.5 to 45.4 1,600 45.5 to 55.4 2,000 55.5 and above 2,400
2.2Recommended Dosage for Alagille Syndrome (ALGS) in Patients Aged 12 Months and Older The recommended dosage of BYLVAY is 120 mcg/kg taken orally once daily in the morning with a meal. Table 2 below shows the recommended once daily dosage by body weight. BYLVAY oral pellets are intended for use by patients weighing less than 19.5 kilograms.
BYLVAY capsules are intended for use by patients weighing 19.5 kilograms or above. Table 2. Recommended Dosage for ALGS in Patients aged 12 months and older (120 mcg/kg/day) Body Weight (kg) Once Daily Dosage (mcg) 7.4 and below 600 7.5 to 12.4 1,200 12.5 to 17.4 1,800 17.5 to 25.4 2,400 25.5 to 35.4 3,600 35.5 to 45.4 4,800 45.5 to 55.4 6,000 55.5 and above 7,200
2.3Dosage Modification for Management of Adverse Reactions Tolerability for Alagille Syndrome (ALGS) Dose reduction to 40 mcg/kg/day (Table 1) may be considered if tolerability issues occur in the absence of other causes. Once tolerability issues stabilize, increase to 120 mcg/kg/day. Liver Test Abnormalities Establish the baseline pattern of variability of liver tests prior to starting BYLVAY, so that potential signs of liver injury can be identified.
Monitor liver tests (e.g., ALT [alanine aminotransferase], AST [aspartate aminotransferase], TB [total bilirubin], DB [direct bilirubin] and International Normalized Ratio [INR]) during treatment with BYLVAY. Interrupt BYLVAY if new onset liver test abnormalities occur or symptoms consistent with clinical hepatitis are observed [see Warnings and Precautions (5.1) ]. Once the liver test abnormalities either return to baseline values or stabilize at a new baseline value, consider restarting BYLVAY at the recommended dosage [see Dosage and Administration (2.1 , 2.2) ] .
Consider discontinuing BYLVAY permanently if liver test abnormalities recur. Discontinue BYLVAY permanently if a patient experiences a hepatic decompensation event (e.g., variceal hemorrhage, ascites, hepatic encephalopathy).
2.4Preparation and Administration Instructions For patients taking bile acid binding resins, take BYLVAY at least 4 hours before or 4 hours after taking a bile acid binding resin [see Drug Interactions (7.1) ]. Do not crush or chew capsules. Oral Pellets: Mix the contents of the shell containing Oral Pellets into soft food or a liquid (as described below).
Discard the emptied shells. Do not let your child swallow the unopened shells containing the Oral Pellets. Administration Instructions for pati…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Oral Pellets: 200 mcg, 600 mcg ( 3 ) Capsules: 400 mcg, 1200 mcg ( 3 ) Oral Pellets: 200 mcg: capsule with ivory opaque cap and white opaque body; imprinted "A200" (black ink). 600 mcg: capsule with ivory opaque cap and body; imprinted "A600" (black ink). Capsules: 400 mcg: capsule with medium orange opaque cap and white opaque body; imprinted "A400" (black ink).
1200 mcg: capsule with medium orange opaque cap and body; imprinted "A1200" (black ink).
⛔ Contraindications ▾
4 CONTRAINDICATIONS IBAT inhibitors, including BYLVAY, are contraindicated in patients with prior or active hepatic decompensation events (e.g., variceal hemorrhage, ascites, hepatic encephalopathy) [see Warnings and Precautions (5.1) ] . Patients with prior or active hepatic decompensation events (e.g., variceal hemorrhage, ascites, hepatic encephalopathy). ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hepatoxicity : Obtain baseline liver tests and monitor patients frequently for the first 6 to 8 months after starting therapy, and as clinically indicated thereafter during treatment. If liver test abnormalities or signs of clinical hepatitis occur, consider dose reduction or treatment interruption. For persistent or recurrent liver test abnormalities relative to baseline, discontinue BYLVAY.
Monitor patients with compensated cirrhosis or portal hypertension more frequently. Permanently discontinue BYLVAY if hepatic decompensation occurs. ( 2.3 , 5.1 ) Diarrhea : Treat dehydration.
Treatment interruption or discontinuation may be required for persistent diarrhea. ( 5.2 ) Fat-Soluble Vitamin (FSV) Deficiency : Obtain baseline levels and monitor during treatment. Supplement with FSV if deficiency is observed.
If FSV deficiency persists or worsens despite FSV supplementation, consider discontinuing BYLVAY treatment. Fracture: Consider interrupting BYLVAY treatment. Supplement with FSV if indicated.
Bleeding: Interrupt treatment with BYLVAY. Optimize treatment of FSV deficiency and consider restarting BYLVAY once the patient is clinically stable. ( 5.3 )
5.1Hepatoxicity BYLVAY treatment is associated with a potential for drug-induced liver injury (DILI). In the PFIC and ALGS trials, treatment-emergent elevations of liver tests or worsening of liver tests occurred. Of the six patients who experienced DILI, two underwent liver transplant.
Obtain baseline liver tests because some ALGS and PFIC patients have abnormal liver tests at baseline. Monitor patients frequently for the first 6 to 8 months after starting therapy and as clinically indicated thereafter during treatment with BYLVAY. Monitor for elevation in liver tests, for the development of liver-related adverse reactions, and for physical signs of hepatic decompensation.
If liver test abnormalities or signs of clinical hepatitis occur in the absence of other causes, consider dose reduction or treatment interruption. Permanently discontinue BYLVAY if a patient experiences the following: persistent or recurrent liver test abnormalities, or upon rechallenge, signs and symptoms consistent with clinical hepatitis, or a hepatic decompensation event. The safety and effectiveness of BYLVAY have not been established in patients with decompensated cirrhosis.
Monitor patients with compensated cirrhosis or portal hypertension more frequently and discontinue BYLVAY if hepatic decompensation occurs. IBAT inhibitors, including BYLVAY, are contraindicated in patients with prior or active hepatic decompensation events [see Contraindications (4) ] .
5.2Diarrhea In Trial 1, diarrhea in PFIC patients was reported in 2 (10%) placebo-treated patients, 9 (39%) BYLVAY-treated 40 mcg/kg/day patients and 4 (21%) BYLVAY-treated 120 mcg/kg/day patients. Treatment interruption due to diarrhea occurred in 2 patients with 3 events during treatment with BYLVAY 120 mcg/kg/day. Treatment interruption due to diarrhea ranged between 3 to 7 days [see Adverse Reactions (6.1) ] .
One patient treated with BYLVAY 120 mcg/kg/day withdrew from Trial 1 due to persistent diarrhea. In Trial 3, diarrhea in ALGS patients was reported in 1 placebo-treated patient (6%) and in 10 (29%) BYLVAY-treated patients [see Adverse Reactions (6.1) ] . No patients interrupted or permanently discontinued BYLVAY due to diarrhea.
If diarrhea occurs, monitor for dehydration and treat promptly. Interrupt BYLVAY dosing if a patient experiences persistent diarrhea. Restart BYLVAY at 40 mcg/kg/day when diarrhea resolves, and increase the dose as tolerated if appropriate.
If diarrhea persists and no alternate etiology is identified, stop BYLVAY treatment.
5.3Fat-Soluble Vitamin Deficiency BYLVAY may adversely affect absorption of fat-soluble vitamins (FSV). FSV include vitamin A, D, E, and K (measured using INR levels). PFIC and ALGS patients can have FSV deficiency at baseline and are frequently supplemented with FSV…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in greater detail in other sections of the label: Hepatotoxicity [ see Warnings and Precautions (5.1) ] Diarrhea [see Warnings and Precautions (5.2) ] Fat-Soluble Vitamin Deficiency [see Warnings and Precautions (5.3) ] PFIC: Most common adverse reactions (>2%) are liver test abnormalities, diarrhea, abdominal pain, vomiting, and fat-soluble vitamin deficiency. ( 6.1 ) ALGS: Most common adverse reactions (>5%) are diarrhea, abdominal pain, hematoma, and decreased weight.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Albireo Pharma, Inc. at +1-855-252-4736, or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. PFIC Clinical Studies Trial 1 is a randomized, double-blind, placebo-controlled, 24-week study of two dose levels of BYLVAY (40 mcg/kg and 120 mcg/kg) administered once daily [see Clinical Studies (14.1) ] . Sixty-two patients were randomized (1:1:1) to receive one of the following: BYLVAY 40 mcg/kg/day (n=23), BYLVAY 120 mcg/kg/day (n=19), or Placebo (n=20).
Table 3 summarizes the frequency of adverse reactions reported in ≥2% and at a rate greater than placebo in patients treated with BYLVAY in Trial 1. The most common adverse reactions observed in Trial 1 included diarrhea, liver test abnormalities, vomiting, abdominal pain, and fat-soluble vitamin deficiency. Table 3.
Common Adverse Reactions Adverse reactions that occurred in ≥2% of BYLVAY-treated patients from a Clinical Study of BYLVAY in Patients with Progressive Familial Intrahepatic Cholestasis (Trial 1) Adverse Reaction Placebo N=20 n (%) BYLVAY 40 mcg/kg/day N=23 n (%) BYLVAY 120 mcg/kg/day N=19 n (%) Diarrhea 2 (10%) 9 (39%) 4 (21%) Transaminases increased (ALT, AST) 1 (5%) 3 (13%) 4 (21%) Vomiting 0 4 (17%) 3 (16%) Abdominal pain 0 3 (13%) 3 (16%) Blood bilirubin increased 2 (10%) 3 (13%) 2 (11%) Fat-soluble vitamin deficiency (A, D, E) 1 (5%) 0 3 (16%) Splenomegaly 0 0 2 (11%) Cholelithiasis 0 0 1 (5%) Dehydration 0 0 1 (5%) Fracture 0 1 (4%) 0 Trial 2 is an open-label, single-arm study in 116 patients with PFIC types 1, 2, 3, 4 and 6; four patients with benign recurrent intrahepatic cholestasis (BRIC) were also enrolled.
BYLVAY 40 or 120 mcg/kg/day was administered once daily for 72 weeks, with the option to continue treatment beyond 72 weeks. Adverse reactions were similar to those observed in Trial 1. However, fractures were reported in a total of 6 patients (5%) in Trial 2.
Adverse reactions observed in Trial 2 in addition to those described in Table 3 included increased INR (16%), epistaxis (9%), constipation (8%), coagulopathy (3%), headache (3%), nausea (3%), rash (3%), iron deficiency anemia (3%), gastroesophageal reflux disease (2%), prolonged prothrombin time (2%); and variceal hemorrhage, stoma hemorrhage, hematochezia, and rectal hemorrhage (<1% each). Adverse reactions leading to treatment discontinuation were increased bilirubin levels, diarrhea, progression of disease, increased INR, irritability, and decreased weight.
There was a total of 19 (16%) patients who underwent surgical intervention in Trial 2, with one patient who had surgical biliary diversion (SBD) followed by liver transplant, 15 patients who underwent liver transplant alone, and three patients who underwent SBD alone. Overall, 11 of the 19 patients had these surgical interventions prior to Week 72. ALGS Clinical Studies Trial 3 is a randomized, double-blind, placebo-controlled, 24-week study of a single dose level of BYLVAY (120 mcg/kg) administered once daily [see Clinical Studies (14.2) ] .
Fifty-two patients were randomized (2:1) to receive one of the following: BYLVAY 120 mcg/kg/day (n=35), or Placebo (n=17). Table…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS
7.1Bile Acid Binding Resins Administer bile acid binding resins (e.g., cholestyramine, colesevelam, or colestipol) at least 4 hours before or 4 hours after administration of BYLVAY [see Dosage and Administration (2.3) ] . Bile acid binding resins may bind odevixibat in the gut, which may reduce BYLVAY efficacy.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Based on animal data, may cause cardiac malformations ( 8.1 )
8.1Pregnancy Risk Summary Limited human data on the use of BYLVAY in pregnant women are insufficient to establish a drug-associated risk of major birth defects, miscarriage, or adverse developmental outcomes. Based on findings from animal reproduction studies, BYLVAY may cause cardiac malformations when a fetus is exposed during pregnancy. In pregnant rabbits treated orally with odevixibat during organogenesis, an increased incidence of malformations in fetal heart, great blood vessels, and other vascular sites occurred at all doses; maternal systemic exposure at the lowest dose was 2.1 times the maximum recommended dose (see Data ) .
Odevixibat may inhibit the absorption of fat-soluble vitamins. FSV are essential for normal fetal growth and development. Monitor pregnant patients for FSV deficiency and supplement as needed.
Increased supplementation of FSVs may be needed during pregnancy [see Warnings and Precautions (5.3) and Clinical Considerations ] . Consider the woman's need for BYLVAY, the potential drug-related risks to the fetus, and the potential adverse outcomes from untreated maternal PFIC and ALGS. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. There is a pregnancy safety study that monitors pregnancy outcomes in women exposed to BYLVAY during pregnancy. Pregnant women exposed to BYLVAY, or their healthcare providers, should report BYLVAY exposure by calling 1-855-252-4736.
Clinical Considerations Fetal/Neonatal Adverse Reactions Odevixibat may inhibit the absorption of fat-soluble vitamins (FSV). Monitor pregnant patients for FSV deficiency and supplement as needed. Increased supplementation of FSVs may be needed during pregnancy [see Warnings and Precautions (5.3) ] .
Data Animal Data In an embryo-fetal development study, pregnant rabbits received oral doses of 10, 30, or 100 mg/kg/day during the period of organogenesis. Fetuses from all maternal groups treated with odevixibat showed an increase in cardiovascular malformations, which included 5-chambered heart, small ventricle, large atrium, ventricular septum defect, misshapen aortic valve, dilated aortic arch, right sided and retroesophageal aortic arch, fusion of aortic arch and pulmonary trunk, ductus arteriosus atresia, and absence of subclavian artery.
These malformations occurred at 2.1 times the maximum recommended dose and higher, based on AUC (area under the plasma concentration-time curve). Odevixibat was shown to cross the placenta in pregnant rats. No adverse effects on embryo-fetal development were observed following oral administration of 100, 300, or 1,000 mg/kg/day in pregnant rats during organogenesis.
An increase in skeletal variations (delayed/incomplete ossification and thick ribs) was observed at 1,000 mg/kg/day. Maternal systemic exposure to odevixibat at the maximum dose tested was 272 times the maximum recommended dose, based on AUC. No adverse effects on postnatal development were observed in a pre- and postnatal development study, in which female rats were treated orally with up to 1,000 mg/kg/day during organogenesis through lactation.
The maternal AUC for odevixibat at 1,000 mg/kg/day was 434 times the maximum recommended dose, based on AUC.
8.2Lactation Risk Summary Odevixibat has low absorption following oral administration, and exposure of the infant to BYLVAY through breast milk is not expected at the recommended doses [see Clinical Pharmacology (12.3) ]. There are no data on the presence of odevixibat in human milk, the effects on the breastfed infant, or the effects on milk production. BYLVAY may reduce absorption of fat-soluble vitamins [see Warning and Precautions (5.3) ] .
Monitor FSV l…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Limited human data on the use of BYLVAY in pregnant women are insufficient to establish a drug-associated risk of major birth defects, miscarriage, or adverse developmental outcomes. Based on findings from animal reproduction studies, BYLVAY may cause cardiac malformations when a fetus is exposed during pregnancy. In pregnant rabbits treated orally with odevixibat during organogenesis, an increased incidence of malformations in fetal heart, great blood vessels, and other vascular sites occurred at all doses; maternal systemic exposure at the lowest dose was 2.1 times the maximum recommended dose (see Data ) .
Odevixibat may inhibit the absorption of fat-soluble vitamins. FSV are essential for normal fetal growth and development. Monitor pregnant patients for FSV deficiency and supplement as needed.
Increased supplementation of FSVs may be needed during pregnancy [see Warnings and Precautions (5.3) and Clinical Considerations ] . Consider the woman's need for BYLVAY, the potential drug-related risks to the fetus, and the potential adverse outcomes from untreated maternal PFIC and ALGS. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. There is a pregnancy safety study that monitors pregnancy outcomes in women exposed to BYLVAY during pregnancy. Pregnant women exposed to BYLVAY, or their healthcare providers, should report BYLVAY exposure by calling 1-855-252-4736.
Clinical Considerations Fetal/Neonatal Adverse Reactions Odevixibat may inhibit the absorption of fat-soluble vitamins (FSV). Monitor pregnant patients for FSV deficiency and supplement as needed. Increased supplementation of FSVs may be needed during pregnancy [see Warnings and Precautions (5.3) ] .
Data Animal Data In an embryo-fetal development study, pregnant rabbits received oral doses of 10, 30, or 100 mg/kg/day during the period of organogenesis. Fetuses from all maternal groups treated with odevixibat showed an increase in cardiovascular malformations, which included 5-chambered heart, small ventricle, large atrium, ventricular septum defect, misshapen aortic valve, dilated aortic arch, right sided and retroesophageal aortic arch, fusion of aortic arch and pulmonary trunk, ductus arteriosus atresia, and absence of subclavian artery.
These malformations occurred at 2.1 times the maximum recommended dose and higher, based on AUC (area under the plasma concentration-time curve). Odevixibat was shown to cross the placenta in pregnant rats. No adverse effects on embryo-fetal development were observed following oral administration of 100, 300, or 1,000 mg/kg/day in pregnant rats during organogenesis.
An increase in skeletal variations (delayed/incomplete ossification and thick ribs) was observed at 1,000 mg/kg/day. Maternal systemic exposure to odevixibat at the maximum dose tested was 272 times the maximum recommended dose, based on AUC. No adverse effects on postnatal development were observed in a pre- and postnatal development study, in which female rats were treated orally with up to 1,000 mg/kg/day during organogenesis through lactation.
The maternal AUC for odevixibat at 1,000 mg/kg/day was 434 times the maximum recommended dose, based on AUC.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of BYLVAY have been established in pediatric patients 3 months to 17 years of age for the treatment of pruritus in PFIC. Use of BYLVAY in this age group is supported by evidence from one randomized, double-blind, placebo-controlled trial conducted in 62 patients with a confirmed diagnosis of PFIC type 1 or type 2 (Trial 1), and an open-label extension trial in PFIC patients (Trial 2) [see Adverse Reactions (6.1) and Clinical Studies (14.1) ] . The safety and effectiveness of BYLVAY for the treatment of pruritus in PFIC in pediatric patients less than 3 months of age have not been established.
The safety and effectiveness of BYLVAY have been established in pediatric patients 12 months to 17 years of age for the treatment of pruritus in ALGS. Use of BYLVAY in this age group is supported by evidence from one randomized, double-blind, placebo-controlled trial conducted in 52 patients with a confirmed diagnosis of ALGS (Trial 3) and one open-label extension trial in ALGS patients (Trial 4) [see Adverse Reactions (6.1) and Clinical Studies (14.2) ] . The safety and effectiveness of BYLVAY for the treatment of pruritus in ALGS in pediatric patients less than 12 months of age have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use PFIC and ALGS are largely diseases of pediatric and young adult patients. Clinical studies in BYLVAY did not include patients 65 years of age and older.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Odevixibat is a reversible inhibitor of the ileal bile acid transporter (IBAT). It decreases the reabsorption of bile acids (primarily the salt forms) from the terminal ileum . Pruritus is a common symptom in patients with PFIC and ALGS; the pathophysiology of pruritus in patients with PFIC is not completely understood.
Although the complete mechanism by which odevixibat improves pruritus in both PFIC and ALGS patients is unknown, it may involve inhibition of the IBAT, which results in decreased reuptake of bile salts, as observed by a decrease in serum bile acids [see Clinical Pharmacology (12.2) ] .
12.2Pharmacodynamics Odevixibat reduces serum bile acids in patients with PFIC and ALGS . In Trial 1, a 24-week, randomized, double-blind, placebo-controlled trial conducted in 62 patients with a confirmed diagnosis of PFIC type 1 or type 2, the majority of patients (88.7%) had elevated serum bile acids above 100 mcmol/L at baseline [see Clinical Studies (14) ] . Serum bile acids concentrations were reduced from baseline within 4-8 weeks of odevixibat treatment compared to placebo treatment.
The decreased concentrations of serum bile acids fluctuated over time but generally were maintained during the treatment over 24 weeks. The extent of decrease in serum bile acids was similar between 40 and 120 mcg/kg. Trial 3 is a 24-week, randomized, double-blind, placebo-controlled trial conducted in 52 patients with a confirmed diagnosis of ALGS who were administered treatment with BYLVAY 120 mcg/kg once daily [see Clinical Studies (14.2) ].
At baseline, serum bile acids were variable ranging from 93 to 510 mcmol/L. Serum bile acid concentrations were reduced from baseline as early as Week 4 of odevixibat treatment and the reduction was generally maintained during treatment over 24 weeks.
12.3Pharmacokinetics In pediatric patients with PFIC, 6 months to 17 years of age who received BYLVAY 40 mcg/kg or 120 mcg/kg once daily with food in the morning, the measurable odevixibat concentrations ranged from 0.06 to 0.72 ng/mL, and odevixibat concentrations were below the limit of quantification (0.05 ng/mL) in the majority of plasma samples. In pediatric patients with ALGS who received BYLVAY 120 mcg/kg once daily with food in the morning, the measurable odevixibat concentrations ranged from 0.05 to 3.4 ng/mL.
Following single and repeated oral administration of odevixibat from 0.1 to 3 mg in healthy adults, plasma concentrations of odevixibat were mostly below the limit of quantification (0.05 ng/mL); therefore, AUC and peak plasma concentration (C max ) could not be calculated. Following a single administration of odevixibat 7.2 mg in healthy adults, the mean (%CV) C max and AUC 0-24h were 0.47 ng/mL (34.8) and 2.19 ng∙h/mL (36.2), respectively. No accumulation of odevixibat was observed following once-daily dosing.
Absorption Odevixibat is minimally absorbed following oral administration. Following a single administration of odevixibat 7.2 mg in healthy adults, odevixibat C max is reached between 1 to 5 hours. Sprinkle on Applesauce When odevixibat 9.6 mg was administered after sprinkling the pellets on applesauce, decreases of 39% and 35% in C max and AUC 0-24h , respectively, and delayed median T max from 3 hours to 4.5 hours were observed compared to administration of whole capsules (eight 1200 mcg capsules) under fasted conditions.
The effect of sprinkling on soft food on systemic exposure is not clinically significant [see Dosage and Administration (2.3) ]. Effect of Food Concomitant administration of a high-fat meal (800-1000 calories with approximately 50% of total caloric content of the meal from fat) with a single dose of odevixibat 9.6 mg delayed median T max from 3 hours to 4.5 hours and resulted in decreases of 72% and 62% in C max and AUC 0-24h , respectively, compared to administration under fasted conditions in healthy adults. The effect of food on the changes of systemic expos…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Odevixibat is a reversible inhibitor of the ileal bile acid transporter (IBAT). It decreases the reabsorption of bile acids (primarily the salt forms) from the terminal ileum . Pruritus is a common symptom in patients with PFIC and ALGS; the pathophysiology of pruritus in patients with PFIC is not completely understood.
Although the complete mechanism by which odevixibat improves pruritus in both PFIC and ALGS patients is unknown, it may involve inhibition of the IBAT, which results in decreased reuptake of bile salts, as observed by a decrease in serum bile acids [see Clinical Pharmacology (12.2) ] .
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Oral Pellets 200 mcg Oral Pellets: supplied as Size 0 capsule with ivory opaque cap and white opaque body; imprinted "A200" (black ink). Supplied in bottles of 30 with child-resistant closure (NDC 74528-020-01). 600 mcg Oral Pellets: supplied as Size 0 capsule with ivory opaque cap and body; imprinted "A600" (black ink).
Supplied in bottles of 30 with child-resistant closure (NDC 74528-060-01). Capsules 400 mcg Capsule: supplied as Size 3 capsule with medium orange opaque cap and white opaque body; imprinted "A400" (black ink). Supplied in bottles of 30 with child-resistant closure (NDC 74528-040-01).
1,200 mcg Capsule: supplied as Size 3 capsule with medium orange opaque cap and body; imprinted "A1200" (black ink). Supplied in bottles of 30 with child-resistant closure (NDC 74528-120-01). Storage and Handling: Store at 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C and 30°C (between 59°F and 86°F) [See USP Controlled Room Temperature].
📦 Storage and Handling ▾
Storage and Handling: Store at 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C and 30°C (between 59°F and 86°F) [See USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION The active ingredient in BYLVAY (odevixibat) capsules and BYLVAY (odevixibat) oral pellets, an ileal bile acid transporter (IBAT) inhibitor, is (2S)-2-{[(2R)-2-(2-{[3,3-dibutyl-7-(methylsulfanyl)-1,1-dioxo-5-phenyl-2,3,4,5-tetrahydro-1H-1λ 6 ,2,5-benzothiadiazepin-8yl]oxy}acetamido)-2-(4-hydroxyphenyl)acetly]amino}butanoic acid, which is formulated as the sesquihydrate having the following chemical structure: The molecular formula is C 37 H 48 N 4 O 8 S 2 ×
1.5H 2 O, with a molecular weight of 768.0 g/mol (anhydrous 740.9 g/mol). Odevixibat sesquihydrate is a white to off-white solid. Its solubility in aqueous solutions is pH-dependent and increases with increased pH.
BYLVAY is available for oral administration as oral pellets containing odevixibat sesquihydrate equivalent to 200 mcg or 600 mcg of odevixibat, and as capsules containing odevixibat sesquihydrate equivalent to 400 mcg or 1200 mcg of odevixibat, and the following excipients: hypromellose and microcrystalline cellulose. The capsule shells for the oral pellets contain hypromellose, titanium dioxide and yellow iron oxide. The capsule shells for the capsules contain hypromellose, red iron oxide, titanium dioxide and yellow iron oxide.
The imprinting ink contains ferrosoferric oxide/black iron oxide and shellac glaze. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Instructions for Use). Administration Instructions Advise patients or their caregivers(s) to: Take BYLVAY in the morning with a meal. Do not swallow the 200 mcg or 600 mcg capsule(s) containing Oral Pellets whole.
These are intended to be opened and the contents mixed into soft food or liquids [see Dosage and Administration (2.1 , 2.2 , 2.4) ] . Follow stepwise administration Instructions [see Dosage and Administration (2.4) ] for Oral Pellets and Capsules for patients unable to swallow the capsules whole. Take BYLVAY at least 4 hours before or 4 hours after taking a bile acid binding resin (e.g., cholestyramine, colesevelam, or colestipol) [see Drug Interactions (7.1) ].
Hepatotoxicity Advise patients or their caregiver(s) that liver tests should be obtained before starting BYLVAY and periodically during BYLVAY therapy. Inform patients or their caregiver(s) of the potential risk of hepatotoxicity, and that they will need to undergo monitoring for liver injury. Instruct patients or their caregiver(s) to immediately report any signs or symptoms of severe liver injury to their healthcare provider [see Dosage and Administration (2.3) and Warnings and Precautions (5.1) ].
Diarrhea Advise patients or their caregiver(s) to notify their healthcare provider if they experience new onset or worsening of diarrhea [see Warnings and Precautions (5.2) ]. Fat Soluble Vitamin (FSV) Deficiency Advise patients or their caregiver(s) that INR (for vitamin K) and serum levels of vitamins A, D, E will be obtained before starting and periodically during treatment to assess for FSV deficiency [see Warnings and Precautions (5.3) ]. Inform patients or their caregiver(s) that they may bleed more easily, may bleed longer, or have a bone fracture.
Advise patients or their caregiver(s) to call their healthcare provider for any signs or symptoms of bleeding or report any fractures. Pregnancy Advise patients or their caregiver(s) that there is a pregnancy safety study that collects pregnancy outcome data in women taking BYLVAY during pregnancy. Pregnant women exposed to BYLVAY, or their healthcare providers, should report BYLVAY exposure by calling 1-855-252-4736 [see Use in Specific Populations (8.1) ] .