
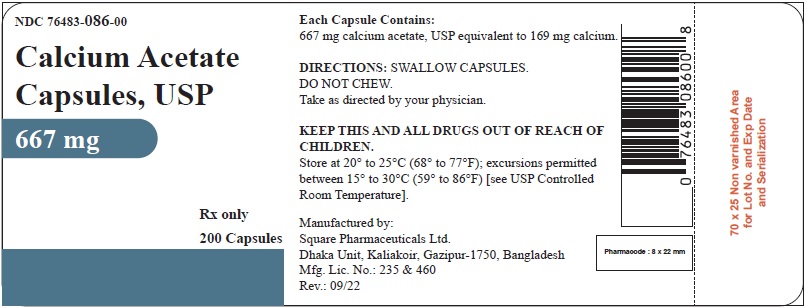
Calcium Acetate 667 mg Capsule, 200-count — NDC 76483-086-00 (Billing 76483-0086-00)
This is a package of 200 capsules of Calcium Acetate 667 mg Capsule from SQUARE PHARMACEUTICALS LIMITED, marketed since May 2023 and currently FDA-listed. It is this product's only package size.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
- RxCUI (RxNorm): 359296
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Drugs for treatment of hyperkalemia and hyperphosphatemia class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Calcium acetate is used to control high blood levels of phosphorus in people with kidney disease who are on dialysis (medical treatment to clean the blood when the kidneys are not working properly). Calcium acetate is in a class of medications called phosphate binders. It binds phosphorus that you get from foods in your diet and prevents it from being absorbed into your blood stream.
Read the full MedlinePlus article ↗- It lowers the phosphorus in your blood if you have end stage renal disease. Failing kidneys can't clear phosphorus well, so it builds up. Calcium acetate helps by binding phosphate...
- Take it by mouth with each meal. It needs to be in your stomach with your food to bind the phosphate. Your prescriber will adjust how many you take based on your blood tests, so fo...
- The most common are high blood calcium, nausea and vomiting. Some people also report dizziness, swelling or weakness. Call your doctor if you have ongoing nausea, constipation, poo...
- Avoid them unless your doctor says otherwise. Calcium supplements and calcium-based antacids add more calcium and raise the risk of high blood calcium. Check with me before taking...
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.2616 | $52.32 / 200 capsules |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 76483-0086-00 You're viewing this Main listing | 200 CAPSULE in 1 BOTTLE | 2023-05-31 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Calcium Acetate 667 mg 00054-0088-13 | Hikma | 30 capsules | $0.170 | AB | Availability likely | — |
| Calcium Acetate 667 mg 00904-7119-06 | Major | 50 capsules | $0.170 | AB | Availability likely | — |
| Calcium Acetate 667 mg 16571-0813-20 | Rising | 200 capsules | $0.170 | AB | Availability likely | — |
| calcium acetate 667 mg 23155-0531-02 | Heritage | 200 capsules | $0.170 | AB | Availability likely | — |
| Calcium Acetate 667 mg 62135-0191-22 | Chartwell | 200 capsules | $0.170 | AB | Availability likely | — |
| Calcium Acetate 667 mg 68084-0479-01 | American | 100 capsules | $0.170 | AB | Availability likely | — |
| Calcium Acetate 667 mg 69367-0411-02 | Westminster | 200 capsules | $0.170 | AB | Availability likely | — |
| Calcium Acetate 667 mg 75834-0323-02 | Nivagen | 200 capsules | $0.170 | AB | Availability likely | — |
| Calcium Acetate 667 mg 76282-0377-02 | EXELAN | 200 capsules | $0.170 | AB | Availability likely | — |
| Calcium Acetate 667 mg 00615-8632-39 | NCS | 30 capsules | — | AB | FDA listed | — |
| Calcium Acetate 667 mg 50268-0203-15 | AvPAK | 50 capsules | — | AB | FDA listed | — |
| Calcium Acetate 667 mg 53746-0590-01 | Amneal | 100 capsules | — | — | FDA listed | — |
| Calcium Acetate 667 mg 55154-4169-00 | Cardinal | 10 capsules | — | AB | FDA listed | — |
| Calcium Acetate 667 mg 60429-0491-02 | Golden | 200 capsules | — | AB | Discontinued | — |
| Calcium Acetate 667 mg 69097-0862-03 | Cipla | 60 capsules | — | AB | FDA listed | — |
| calcium acetate 667 mg 70518-4299-00 | REMEDYREPACK | 30 capsules | — | AB | FDA listed | — |
| Calcium Acetate 667 mg 72789-0422-97 | PD-Rx | 200 capsules | — | AB | FDA listed | — |
| calcium acetate 667 mg 73190-0031-20 | AvKARE | 200 capsules | — | AB | FDA listed | — |
| Calcium Acetate 667 mgthis 76483-0086-00 | SQUARE | 200 capsules | — | AB | FDA listed | — |
| Calcium Acetate 667 mg 82804-0968-00 | Proficient | 100 capsules | — | AB | FDA listed | — |
| Calcium Acetate 667 mg 60687-0589-01 | American | 100 capsules | — | AB | Discontinued | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 2S7830E561
Crospovidone is a synthetic polymer derived from povidone. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the active ingredient can be absorbed.
-
UNII 767IP0Y5NH
A synthetic red colorant used to give medicines their color. It helps patients identify their medication and makes the product visually appealing.
-
UNII H3R47K3TBD
FD&C Blue No. 1 is a synthetic blue dye approved for use in foods and medicines. It serves as a colorant to give the medication its distinctive appearance and help with product identification.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII WZH3C48M4T
Potassium hydroxide is a strong alkaline chemical used in medicines to adjust and maintain the pH level of liquid formulations, helping keep the product stable and the active ingredients effective.
-
UNII 46N107B71O
Shellac is a natural resin secreted by the lac beetle. It's used as a coating on tablets and capsules to control how quickly the medicine dissolves and to improve appearance and stability.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
10 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Calcium acetate capsules are a phosphate binder indicated to reduce serum phosphorus in patients with end stage renal disease (ESRD). Calcium acetate capsules are a phosphate binder indicated for the reduction of serum phosphorus in patients with end stage renal disease. (1)
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION The recommended initial dose of calcium acetate for the adult dialysis patient is 2 capsules with each meal. Increase the dose gradually to lower serum phosphorus levels to the target range, as long as hypercalcemia does not develop. Most patients require 3-4 capsules with each meal.
Starting dose is 2 capsules with each meal. (2) Titrate the dose every 2-3 weeks until acceptable serum phosphorus level is reached. Most patients require 3-4 capsules with each meal.
(2)
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Capsule: 667 mg calcium acetate per capsule. Capsule: 667 mg calcium acetate capsule. (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Patients with hypercalcemia. Hypercalcemia. (4)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Treat mild hypercalcemia by reducing or interrupting calcium acetate and Vitamin D. Severe hypercalcemia may require hemodialysis and discontinuation of calcium acetate. (5.1) Hypercalcemia may aggravate digitalis toxicity. (5.2)
5.1Hypercalcemia Patients with end stage renal disease may develop hypercalcemia when treated with calcium, including calcium acetate. Avoid the use of calcium supplements, including calcium-based nonprescription antacids, concurrently with calcium acetate. An overdose of calcium acetate may lead to progressive hypercalcemia, which may require emergency measures.
Therefore, early in the treatment phase during the dosage adjustment period, monitor serum calcium levels twice weekly. Should hypercalcemia develop, reduce the calcium acetate dosage, or discontinue the treatment, depending on the severity of hypercalcemia. More severe hypercalcemia (Ca >12 mg/dL) is associated with confusion, delirium, stupor and coma.
Severe hypercalcemia can be treated by acute hemodialysis and discontinuing calcium acetate therapy. Mild hypercalcemia (10.5 to 11.9 mg/dL) may be asymptomatic or manifest as constipation, anorexia, nausea, and vomiting. Mild hypercalcemia is usually controlled by reducing the calcium acetate dose or temporarily discontinuing therapy.
Decreasing or discontinuing Vitamin D therapy is recommended as well. Chronic hypercalcemia may lead to vascular calcification and other soft-tissue calcification. Radiographic evaluation of suspected anatomical regions may be helpful in early detection of soft tissue calcification.
The long term effect of calcium acetate on the progression of vascular or soft tissue calcification has not been determined. Hypercalcemia (>11 mg/dL) was reported in 16% of patients in a 3-month study of solid dose formulation of calcium acetate; all cases resolved upon lowering the dose or discontinuing treatment. Maintain the serum calcium-phosphorus (Ca x P) product below 55 mg 2 /dL 2 .
5.2Concomitant Use with Medications Hypercalcemia may aggravate digitalis toxicity.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Hypercalcemia is discussed elsewhere [see Warnings and Precautions (5.1)] . The most common (>10%) adverse reactions are hypercalcemia, nausea, and vomiting. (6.1) In clinical studies, patients have occasionally experienced nausea during calcium acetate therapy. (6) To report SUSPECTED ADVERSE REACTIONS, contact FDA at 1-800-FDA-1088 or www.fda.gov/medwatch
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. In clinical studies, calcium acetate has been generally well tolerated. Calcium acetate was studied in a 3-month, open-label, non-randomized study of 98 enrolled ESRD hemodialysis patients and an alternate liquid formulation of calcium acetate was studied in a two week double-blind, placebo-controlled, cross-over study with 69 enrolled ESRD hemodialysis patients.
Adverse reactions (>2% on treatment) from these trials are presented in Table 1. Table 1: Adverse Reactions in Patients with End-Stage Renal Disease Undergoing Hemodialysis Preferred Term Total adverse reactions reported for calcium acetate n=167 n (%) 3-mo, open-label study of calcium acetate n=98 n (%) Double blind, placebo-controlled, cross-over study of liquid calcium acetate n=69 Calcium acetate n (%) Placebo n (%) Nausea 6 (3.6) 6 (6.1) 0 (0.0) 0 (0.0) Vomiting 4 (2.4) 4 (4.1) 0 (0.0) 0 (0.0) Hypercalcemia 21 (12.6) 16 (16.3) 5 (7.2) 0 (0.0) Mild hypercalcemia may be asymptomatic or manifest itself as constipation, anorexia, nausea, and vomiting.
More severe hypercalcemia is associated with confusion, delirium, stupor, and coma. Decreasing dialysate calcium concentration could reduce the incidence and severity of calcium acetate-induced hypercalcemia. Isolated cases of pruritus have been reported, which may represent allergic reactions.
6.2Postmarketing Experience Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to estimate their frequency or to establish a causal relationship to drug exposure. The following additional adverse reactions have been identified during post-approval of calcium acetate: dizziness, edema, and weakness.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS The drug interaction of calcium acetate is characterized by the potential of calcium to bind to drugs with anionic functions (e.g., carboxyl, and hydroxyl groups). Calcium acetate may decrease the bioavailability of tetracyclines or fluoroquinolones via this mechanism. There are no empirical data on avoiding drug interactions between calcium acetate and most concomitant drugs.
When administering an oral medication with calcium acetate where a reduction in the bioavailability of that medication would have a clinically significant effect on its safety or efficacy, administer the drug one hour before or three hours after calcium acetate. Monitor blood levels of the concomitant drugs that have a narrow therapeutic range. Patients taking anti-arrhythmic medications for the control of arrhythmias and anti-seizure medications for the control of seizure disorders were excluded from the clinical trials with all forms of calcium acetate.
Calcium acetate may decrease the bioavailability of tetracyclines or fluoroquinolones. (7) When clinically significant drug interactions are expected, administer the drug at least one hour before or at least three hours after calcium acetate or consider monitoring blood levels of the drug. (7)
7.1Ciprofloxacin In a study of 15 healthy subjects, a co-administered single dose of 4 calcium acetate tablets, approximately 2.7 g, decreased the bioavailability of ciprofloxacin by approximately 50%.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Pregnancy Category C Calcium acetate capsules contains calcium acetate. Animal reproduction studies have not been conducted with calcium acetate, and there are no adequate and well controlled studies of calcium acetate use in pregnant women. Patients with end stage renal disease may develop hypercalcemia with calcium acetate treatment [see Warnings and Precautions (5.1)] .
Maintenance of normal serum calcium levels is important for maternal and fetal well being. Hypercalcemia during pregnancy may increase the risk for maternal and neonatal complications such as stillbirth, preterm delivery, and neonatal hypocalcemia and hypoparathyroidism. Calcium acetate treatment, as recommended, is not expected to harm a fetus if maternal calcium levels are properly monitored during and following treatment.
8.2Labor and Delivery The effects of calcium acetate on labor and delivery are unknown.
8.3Nursing Mothers Calcium acetate capsule contains calcium acetate and is excreted in human milk. Human milk feeding by a mother receiving calcium acetate is not expected to harm an infant, provided maternal serum calcium levels are appropriately monitored.
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established.
8.5Geriatric Use Clinical studies of calcium acetate did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other clinical experience has not identified differences in responses between elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Category C Calcium acetate capsules contains calcium acetate. Animal reproduction studies have not been conducted with calcium acetate, and there are no adequate and well controlled studies of calcium acetate use in pregnant women. Patients with end stage renal disease may develop hypercalcemia with calcium acetate treatment [see Warnings and Precautions (5.1)] .
Maintenance of normal serum calcium levels is important for maternal and fetal well being. Hypercalcemia during pregnancy may increase the risk for maternal and neonatal complications such as stillbirth, preterm delivery, and neonatal hypocalcemia and hypoparathyroidism. Calcium acetate treatment, as recommended, is not expected to harm a fetus if maternal calcium levels are properly monitored during and following treatment.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of calcium acetate did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other clinical experience has not identified differences in responses between elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
10 OVERDOSAGE Administration of calcium acetate in excess of the appropriate daily dosage may result in hypercalcemia [see Warnings and Precautions (5.1)] .
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY Patients with ESRD retain phosphorus and can develop hyperphosphatemia. High serum phosphorus can precipitate serum calcium resulting in ectopic calcification. Hyperphosphatemia also plays a role in the development of secondary hyperparathyroidism in patients with ESRD.
12.1Mechanism of Action Calcium acetate, when taken with meals, combines with dietary phosphate to form an insoluble calcium phosphate complex, which is excreted in the feces, resulting in decreased serum phosphorus concentration.
12.2Pharmacodynamics Orally administered calcium acetate from pharmaceutical dosage forms is systemically absorbed up to approximately 40% under fasting conditions and up to approximately 30% under non-fasting conditions. This range represents data from both healthy subjects and renal dialysis patients under various conditions.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Calcium acetate capsules, USP are available as hard gelatin capsule filled with white to off-white granular powder having a blue opaque cap and white opaque body imprinted "S086" on both parts. Each capsule contains 667 mg calcium acetate, USP (anhydrous; Ca(CH 3 COO) 2 ; MW=158.17 grams) equal to 169 mg (8.45 mEq) calcium. Supplied in Bottles of 200 (NDC 76483-086-00).
STORAGE: Store at 20° to 25°C (68° to 77°F); excursions permitted to 15°-30°C (59°-86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Calcium acetate acts as a phosphate binder. Its chemical name is calcium acetate. Its molecular formula is C 4 H 6 CaO 4 , and its molecular weight is 158.17.
Its structural formula is: Calcium Acetate Capsules are Hard Gelatin Capsules filled with white to off-white granular powder having a blue opaque cap and white opaque body imprinted "S086" on both parts. Each capsule contains 667 mg calcium acetate, USP (anhydrous; Ca(CH 3 COO) 2 ; MW=158.17 grams) equal to 169 mg (8.45 mEq) calcium. Each capsule contains the following inactive ingredients: Crospovidone NF, Sodium lauryl Sulfate NF, Magnesium Stearate NF.
The gelatin cap and body have the following inactive ingredients: FD&C blue #1, D&C red #28, titanium dioxide, USP and gelatin, USP. The Imprinting black ink contain shellac NF, black iron oxide NF and potassium hydroxide NF. Calcium acetate capsules are administered orally for the control of hyperphosphatemia in end-stage renal failure. "FDA approved dissolution test specifications differ from USP." image
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Inform patients to take calcium acetate with meals, adhere to their prescribed diets, and avoid the use of calcium supplements including nonprescription antacids. Inform the patients about the symptoms of hypercalcemia [ see Warnings and Precautions (5.1) and Adverse Reactions (6.1) ] . Advise patients who are taking an oral medication where reduction in the bioavailability of that medication would have clinically significant effect on its safety or efficacy to take the drug one hour before or three hours after calcium acetate.
Manufactured by: Square Pharmaceuticals Ltd. Dhaka Unit, Kaliakoir, Gazipur-1750, Bangladesh
🍼 Nursing Mothers ▾
8.3Nursing Mothers Calcium acetate capsule contains calcium acetate and is excreted in human milk. Human milk feeding by a mother receiving calcium acetate is not expected to harm an infant, provided maternal serum calcium levels are appropriately monitored.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES Effectiveness of calcium acetate in decreasing serum phosphorus has been demonstrated in two studies of the calcium acetate solid oral dosage form. Ninety-one patients with end-stage renal disease who were undergoing hemodialysis and were hyperphosphatemic (serum phosphorus >5.5 mg/dL) following a 1-week phosphate binder washout period contributed efficacy data to an open-label, non-randomized study. The patients received calcium acetate 667 mg tablets at each meal for a period of 12 weeks.
The initial starting dose was 2 tablets per meal for 3 meals a day, and the dose was adjusted as necessary to control serum phosphorus levels. The average final dose after 12 weeks of treatment was 3.4 tablets per meal. Although there was a decrease in serum phosphorus, in the absence of a control group the true magnitude of effect is uncertain.
The data presented in Table 2 demonstrate the efficacy of calcium acetate in the treatment of hyperphosphatemia in end-stage renal disease patients. The effects on serum calcium levels are also presented. Table 2: Average Serum Phosphorous and Calcium Levels at Pre-Study, Interim, and Study Completion Time points Parameter Pre-Study Week 4 b Week 8 Week 12 p-value c Phosphorus (mg/dL) a 7.4 ± 0.17 5.9 ± 0.16 5.6 ± 0.17 5.2 ± 0.17 ≤0.01 Calcium (mg/dL) a 8.9 ± 0.09 9.5 ± 0.10 9.7 ± 0.10 9.7 ± 0.10 ≤0.01 a Values expressed as mean ± SE. b Ninety-one patients completed at least 6 weeks of the study. c ANOVA of difference in values at pre-study and study completion.
There was a 30% decrease in serum phosphorus levels during the 12 week study period (p<0.01). Two-thirds of the decline occurred in the first month of the study. Serum calcium increased 9% during the study mostly in the first month of the study.
Treatment with the phosphate binder was discontinued for patients from the open-label study, and those patients whose serum phosphorus exceeded 5.5 mg/dL were eligible for entry into a double-blind, placebo-controlled, cross-over study. Patients were randomized to receive calcium acetate or placebo, and each continued to receive the same number of tablets as had been individually established during the previous study. Following 2 weeks of treatment, patients switched to the alternative therapy for an additional 2 weeks.
The phosphate binding effect of calcium acetate is shown in the Table 3. Table 3: Serum Phosphorous and Calcium Levels at Study Initiation and After Completion of Each Treatment Arm Parameter Pre-Study Post-Treatment p-value b Calcium Acetate Placebo Phosphorus (mg/dL) a 7.3 ± 0.18 5.9 ± 0.24 7.8 ± 0.22 <0.01 Calcium (mg/dL) a 8.9 ± 0.11 9.5 ± 0.13 8.8 ± 0.12 <0.01 a Values expressed as mean ± SEM b ANOVA of calcium acetate vs. placebo after 2 weeks of treatment. Overall, 2 weeks of treatment with calcium acetate statistically significantly (p<0.01) decreased serum phosphorus by a mean of 19% and increased serum calcium by a statistically significant (p<0.01) but clinically unimportant mean of 7%.
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment and Fertility No carcinogenicity, mutagenicity, or fertility studies have been conducted with calcium acetate.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment and Fertility No carcinogenicity, mutagenicity, or fertility studies have been conducted with calcium acetate.
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL NDC 76483-086-00 Calcium Acetate Capsules USP, 667 mg Rx Only 200 Capsules Calcium Acetate Capsules USP
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |