
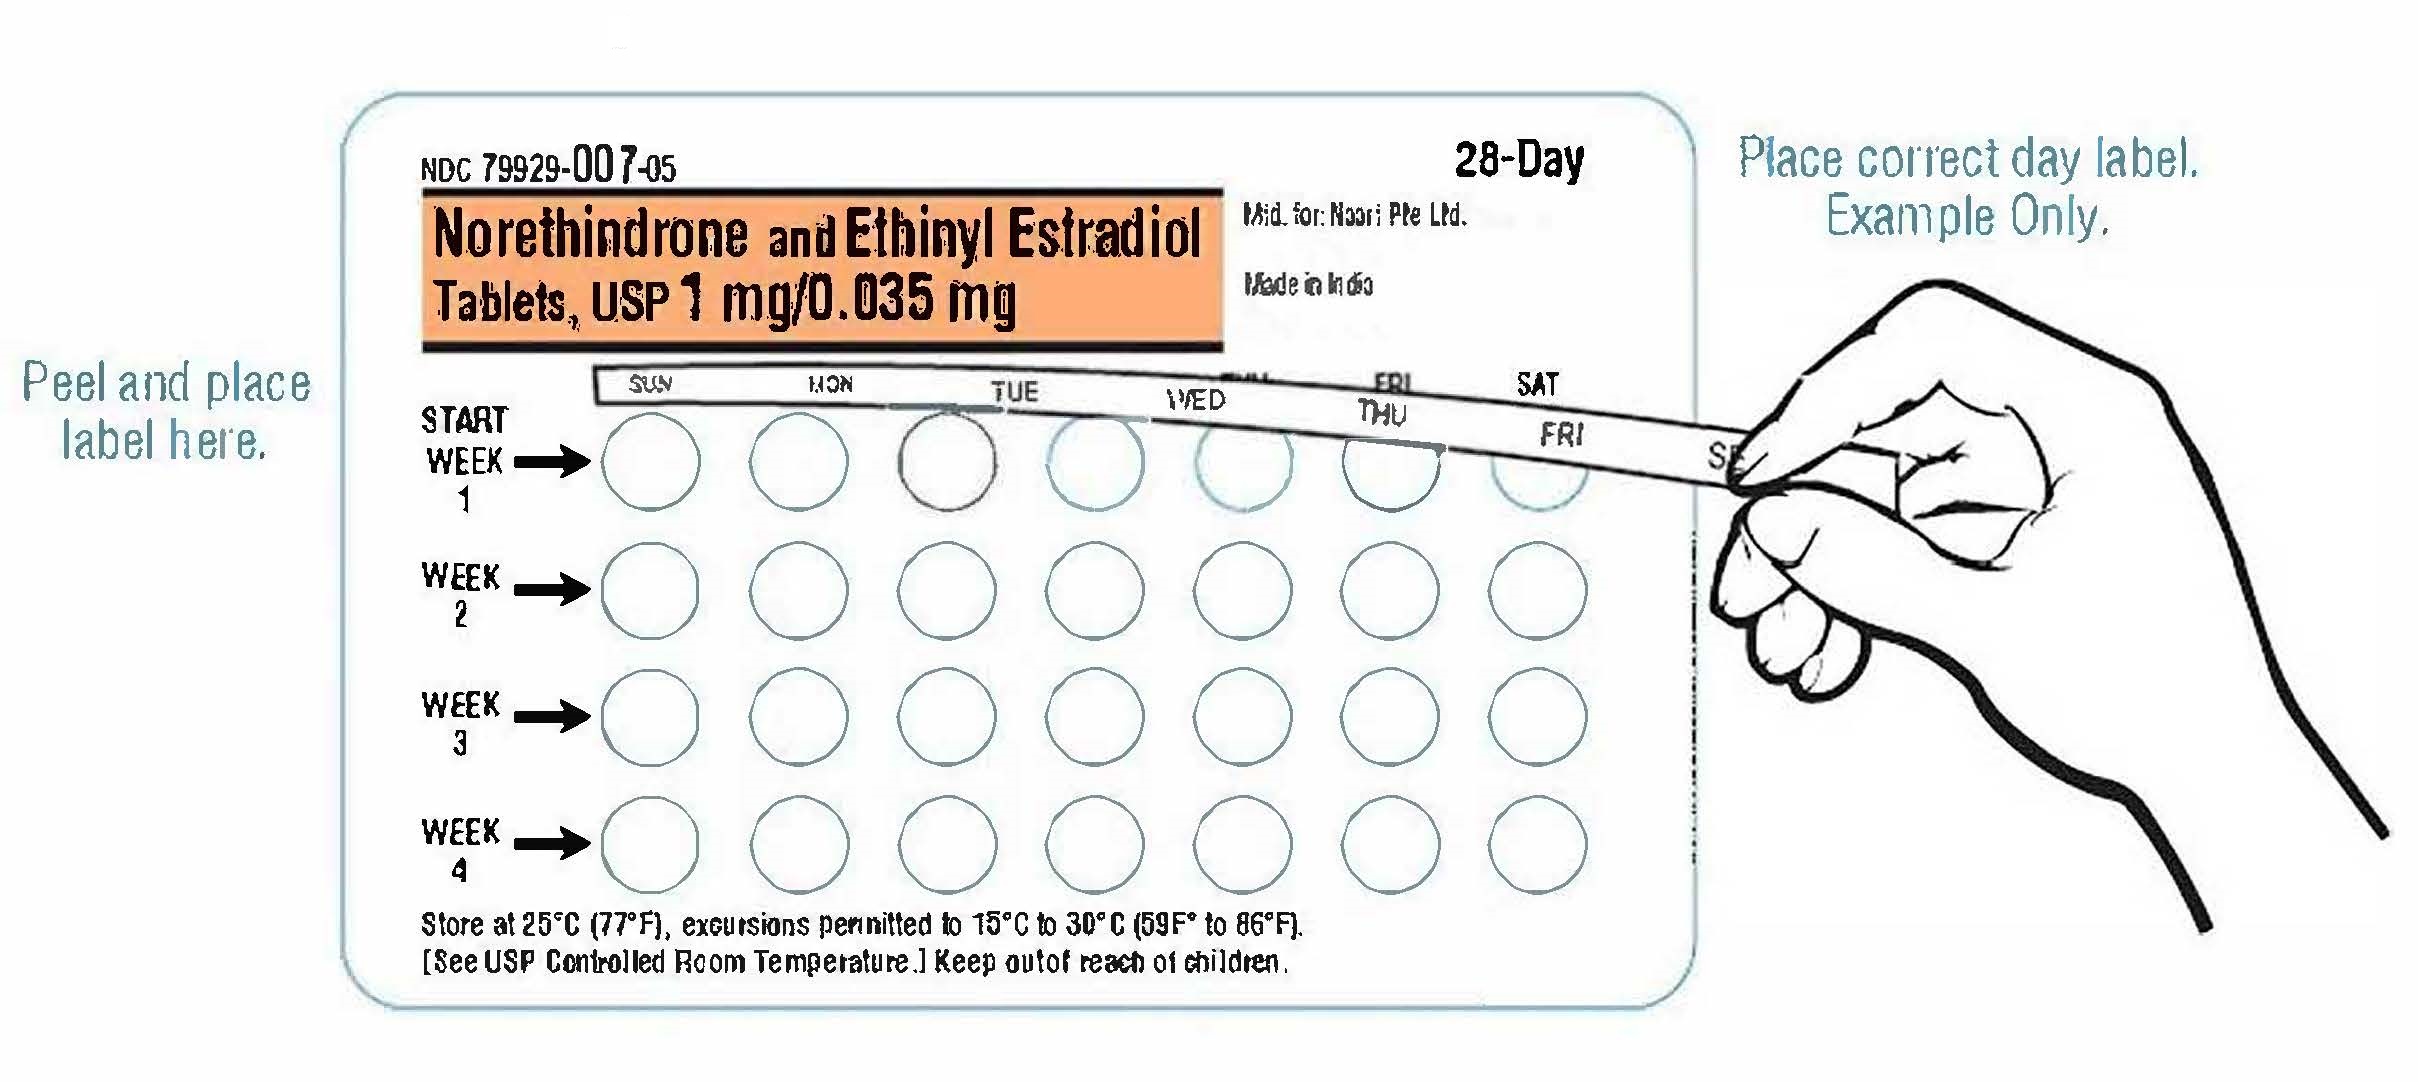
Norethindrone and ethinyl estradiol Kit
Other active recalls for Norethindrone And Ethinyl Estradiol (different manufacturers) — 3 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Estrogen class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Oral contraceptives (birth-control pills) containing ethinyl estradiol (an estrogen) and norethindrone (a progestin) are used to prevent pregnancy. Estrogen and progestin are two female sex hormones. Combinations of estrogen and progestin work mainly by preventing ovulation (the release of eggs from the ovaries). Oral contraceptives are an effective method of birth control, but they do not prevent the spread of human immunodeficiency virus (HIV, the virus that causes acquired immunodeficiency syndrome [AIDS]) and other sexually transmitted diseases.
Read the full MedlinePlus article ↗Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.2151 | $0.65 / 3 kit |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Nylia 1/35 65862-0898-88 | Aurobindo | 3 pouches | $0.212 | AB | Availability likely | — |
| Dasetta 1/35 16714-0348-01 | Northstar | 1 packet | $0.212 | AB | Availability likely | — |
| Alyacen 1/35 68462-0394-29 | Glenmark | 1 kit | $0.212 | AB | Availability likely | — |
| Nortrel 28 Day 00555-9010-58 | Teva | 6 pouches | $0.212 | AB | Availability likely | — |
| Nylia 7/7/7 65862-0897-88 | Aurobindo | 3 pouches | $0.235 | AB | Availability likely | — |
| Nortrel 7/7/7 (28 Day Regimen) 00555-9012-58 | Teva | 6 pouches | $0.235 | — | Availability likely | — |
| Dasetta 7/7/7 16714-0346-01 | Northstar | 1 packet | $0.235 | AB | Availability likely | — |
| Alyacen 7/7/7 68462-0556-29 | Glenmark | 1 kit | $0.235 | AB | Availability likely | — |
| Briellyn 68462-0316-29 | Glenmark | 1 kit | $0.347 | AB | Availability likely | — |
| Balziva 00555-9034-58 | Teva | 6 pouches | $0.347 | AB | Availability likely | — |
| Vyfemla 68180-0875-73 | Lupin | 63 tablets | $0.347 | AB | Availability likely | — |
| Necon 75907-0085-28 | Dr. | 1 packet | $0.485 | AB | Availability likely | — |
| Nortrel 28 Day 00555-9008-67 | Teva | 3 pouches | $0.485 | AB | Availability likely | — |
| Wera 16714-0370-01 | Northstar | 1 packet | $0.485 | AB | Availability likely | — |
| WYMZYA Fe 68180-0873-73 | Lupin | 21 tablets | $0.510 | AB | Availability likely | — |
| Necon 51862-0892-01 | Mayne | 1 packet | $0.617 | AB | FDA listed | — |
| Aranelle 00555-9066-67 | Teva | 3 pouches | $0.622 | AB | Availability likely | — |
| Kaitlib Fe 68180-0903-73 | Lupin | 24 tablets | $1.257 | AB | Availability likely | — |
| Cyonanz 65862-0899-88 | Aurobindo | 3 pouches | — | AB | FDA listed | — |
| Nortrel 7/7/7 (28 Day Regimen) 71205-0685-28 | Proficient | 1 pouch | — | — | FDA listed | — |
| Zenchent FE 69238-1581-03 | Amneal | 1 kit | — | AB | FDA listed | — |
| Alyacen 1/35 50090-1477-00 | A-S | 1 kit | — | AB | FDA listed | — |
| Nortrel 28 Day 50090-3229-00 | A-S | 1 kit | — | AB | FDA listed | — |
| Alyacen 1/35 71205-0547-28 | Proficient | 1 kit | — | AB | FDA listed | — |
| Norethindrone and ethinyl estradiolthis 79929-0007-07 | Naari | 1 kit | — | AB | FDA listed | — |
| Nylia 7/7/7 50090-6321-00 | A-S | 1 kit | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 79929-0007-07 You're viewing this | 3 BLISTER PACK in 1 CARTON (79929-007-07) / 1 KIT in 1 BLISTER PACK (79929-007-05) | 2022-12-31 | Active |
🧭 About this NDC listing & data coverage
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: CARDIOVASCULAR RISK ASSOCIATED WITH SMOKING Cigarette smoking increases the risk of serious cardiovascular events from combination oral contraceptive use. This risk increases with age, particularly in women over 35 years of age, and with the number of cigarettes smoked. For this reason, combination oral contraceptives, including norethindrone and ethinyl estradiol tablets 1 mg/0.035 mg, should not be used by women who are over 35 years of age and smoke.
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Norethindrone and ethinyl estradiol tablets, USP 1 mg/0.035 mg are indicated for the prevention of pregnancy in women who elect to use this product as a method of contraception. Oral contraceptives are highly effective. Table 1 lists the typical accidental pregnancy rates for users of combined oral contraceptives and other methods of contraception.
The efficacy of these contraceptive methods, except sterilization, the IUD, and the NORPLANT ® System depends upon the reliability with which they are used. Correct and consistent use of methods can result in lower failure rates. Table 1: Percentage of Women Experiencing an Unintended Pregnancy During the First Year of Typical Use and the First Year of Perfect Use of Contraception and the Percentage Continuing Use at the End of the First Year.
United States. % of Women Experiencing an Unintended Pregnancy within the First Year of Use % of Women Continuing Use at One Year Among couples attempting to avoid pregnancy, the percentage who continue to use a method for one year. Method (1) Typical Use Among typical couples who initiate use of a method (not necessarily for the first time), the percentage who experience an accidental pregnancy during the first year if they do not stop use for any other reason. (2) Perfect Use Among couples who initiate use of a method (not necessarily for the first time) and who use it perfectly (both consistently and correctly), the percentage who experience an accidental pregnancy during the first year if they do not stop use for any other reason.
(3) (4) Adapted from Hatcher et al., 1998, Ref. # 1. Emergency Contraceptive Pills: Treatment initiated within 72 hours after unprotected intercourse reduces the risk of pregnancy by at least 75%. The treatment schedule is one dose within 72 hours after unprotected intercourse, and a second dose 12 hours after the first dose.
The Food and Drug Administration has declared the following brands of oral contraceptives to be safe and effective for emergency contraception: Ovral ® (1 dose is 2 white pills), Alesse ® (1 dose is 5 pink pills), Nordette ® or Levlen ® (1 dose is 2 light-orange pills), Lo/Ovral ® (1 dose is 4 white pills), Triphasil ® or Tri-Levlen ® (1 dose is 4 yellow pills). Lactational Amenorrhea Method: LAM is a highly effective, temporary method of contraception. However, to maintain effective protection against pregnancy, another method of contraception must be used as soon as menstruation resumes, the frequency or duration of breastfeeds is reduced, bottle feeds are introduced, or the baby reaches six months of age.
Source: Trussell J, Contraceptive efficacy. In Hatcher RA, Trussell J, Stewart F, Cates W, Stewart GK, Kowal D, Guest F, Contraceptive Technology: Seventeenth Revised Edition. New York, NY: Irvington Publishers, 1998.
Chance The percents becoming pregnant in columns (2) and (3) are based on data from populations where contraception is not used and from women who cease using contraception in order to become pregnant. Among such populations, about 89% become pregnant within one year. This estimate was lowered slightly (to 85%) to represent the percent who would become pregnant within one year among women now relying on reversible methods of contraception if they abandoned contraception altogether.
85 85 Spermicides Foams, creams, gels, vaginal suppositories, and vaginal film. 26 6 40 Periodic abstinence 25 63 Calendar 9 Ovulation Method 3 Sympto-Thermal Cervical mucus (ovulation) method supplemented by calendar in the pre-ovulatory and basal body temperature in the post-ovulatory phases. 2 Post-Ovulation 1 Cap With spermicidal cream or jelly.
Parous Women 40 26 42 Nulliparous Women 20 9 56 Sponge Parous Women 40 20 42 Nulliparous Women 20 9 56 Diaphragm 20 6 56 Withdrawal 19 4 Condom Without spermicides. Female (Reality ® ) 21 5 56 Male 14 3 61 Pill 5 71 Progestin Only
0.5 Combined
0.1IUD Progesterone T 2.0 1.5 81 Copper T380A 0.8 0.6 78 LNg 20 0.1 0.1 81 Depo-Prover…
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION To achieve maximum contraceptive effectiveness, norethindrone and ethinyl estradiol tablets must be taken exactly as directed and at intervals not exceeding 24 hours. Norethindrone and ethinyl estradiol tablets are available in a blister pack which is preset for a Sunday Start. Day 1 Start is also available.
Sunday Start When taking norethindrone and ethinyl estradiol tablets, the first "active" tablet should be taken on the first Sunday after menstruation begins. If the period begins on Sunday, the first "active" tablet should be taken that day. Take one active tablet daily for 21 days followed by one green "reminder" tablet daily for 7 days.
After 28 tablets have been taken, a new course is started the next day (Sunday). For the first cycle of a Sunday Start regimen, another method of contraception, such as a condom or spermicide, should be used until after the first 7 consecutive days of administration. If the patient misses one (1) "active" tablet in Weeks 1, 2, or 3, the tablet should be taken as soon as she remembers.
If the patient misses two (2) "active" tablets in Week 1 or Week 2, the patient should take two (2) tablets the day she remembers and two (2) tablets the next day; and then continue taking one (1) tablet a day until she finishes the pack. The patient should be instructed to use a back-up method of birth control, such as a condom or spermicide, if she has sex in the seven (7) days after missing pills. If the patient misses two (2) "active" tablets in the third week or misses three (3) or more "active" tablets in a row, the patient should continue taking one tablet every day until Sunday.
On Sunday the patient should throw out the rest of the pack and start a new pack that same day. The patient should be instructed to use a back-up method of birth control if she has sex in the seven (7) days after missing pills. Complete instructions to facilitate patient counseling on proper pill usage may be found in the Detailed Patient Labeling ("How to Take the Pill" section).
Day 1 Start The dosage of norethindrone and ethinyl estradiol tablets, for the initial cycle of therapy, is one "active" tablet administered daily from the 1st through the 21st day of the menstrual cycle, counting the first day of menstrual flow as "Day 1" followed by one green "reminder" tablet daily for 7 days. Tablets are taken without interruption for 28 days. After 28 tablets have been taken, a new course is started the next day.
If the patient misses one (1) "active" tablet in Weeks 1, 2, or 3, the tablet should be taken as soon as she remembers. If the patient misses two (2) "active" tablets in Week 1 or Week 2, the patient should take two (2) tablets the day she remembers and two (2) tablets the next day; and then continue taking one (1) tablet a day until she finishes the pack. The patient should be instructed to use a back-up method of birth control, such as a condom or spermicide, if she has sex in the seven (7) days after missing pills.
If the patient misses two (2) "active" tablets in the third week or misses three (3) or more "active" tablets in a row, the patient should throw out the rest of the pack and start a new pack that same day. The patient should be instructed to use a back-up method of birth control if she has sex in the seven (7) days after missing pills. Complete instructions to facilitate patient counseling on proper pill usage may be found in the Detailed Patient Labeling ("How to Take the Pill" section).
The use of norethindrone and ethinyl estradiol tablets for contraception may be initiated 4 weeks postpartum in women who elect not to breastfeed. When the tablets are administered during the postpartum period, the increased risk of thromboembolic disease associated with the postpartum period must be considered. (See CONTRAINDICATIONS and WARNINGS concerning thromboembolic disease.
See also PRECAUTIONS: Nursing Mothers .) The possibility of ovulation and conception prior to initiation of medica…
⛔ Contraindications ▾
CONTRAINDICATIONS Oral contraceptives should not be used in women who currently have the following conditions: Thrombophlebitis or thromboembolic disorders A past history of deep vein thrombophlebitis or thromboembolic disorders Known thrombophilic conditions Cerebral vascular or coronary artery disease (current or history) Valvular heart disease with complications Persistent blood pressure values of ≥ 160 mm Hg systolic or ≥ 100 mg Hg diastolic 96 Diabetes with vascular involvement Headaches with focal neurological symptoms Major surgery with prolonged immobilization Current diagnosis of, or history of, breast cancer, which may be hormonesensitive Carcinoma of the endometrium or other known or suspected estrogen-dependent neoplasia Undiagnosed abnormal genital bleeding Cholestatic jaundice of pregnancy or jaundice with prior pill use Acute or chronic hepatocellular disease with abnormal liver function Hepatic adenomas or carcinomas Known or suspected pregnancy Hypersensitivity to any component of this product Are receiving Hepatitis C drug combinations containing ombitasvir/paritaprevir/ritonavir, with or without dasabuvir, due to the potential for ALT elevations (see WARNINGS, Risk of Liver Enzyme Elevations with Concomitant Hepatitis C Treatment).
⚠️ Warnings ▾
WARNINGS Cigarette smoking increases the risk of serious cardiovascular events from combination oral contraceptive use. This risk increases with age, particularly in women over 35 years of age, and with the number of cigarettes smoked. For this reason, combination oral contraceptives, including norethindrone and ethinyl estradiol tablets 1 mg/0.035 mg, should not be used by women who are over 35 years of age and smoke.
The use of oral contraceptives is associated with increased risks of several serious conditions including myocardial infarction, thromboembolism, stroke, hepatic neoplasia, and gallbladder disease, although the risk of serious morbidity or mortality is very small in healthy women without underlying risk factors. The risk of morbidity and mortality increases significantly in the presence of other underlying risk factors such as hypertension, hyperlipidemias, obesity and diabetes. Practitioners prescribing oral contraceptives should be familiar with the following information relating to these risks.
The information contained in this package insert is principally based on studies carried out in patients who used oral contraceptives with higher formulations of estrogens and progestogens than those in common use today. The effect of long-term use of the oral contraceptives with lower formulations of both estrogens and progestogens remains to be determined. Throughout this labeling, epidemiological studies reported are of two types: retrospective or case control studies and prospective or cohort studies.
Case control studies provide a measure of the relative risk of a disease, namely, a ratio of the incidence of a disease among oral contraceptive users to that among nonusers. The relative risk does not provide information on the actual clinical occurrence of a disease. Cohort studies provide a measure of attributable risk, which is the difference in the incidence of disease between oral contraceptive users and nonusers.
The attributable risk does provide information about the actual occurrence of a disease in the population (adapted from refs. 2 and 3 with the author's permission). For further information, the reader is referred to a text on epidemiological methods.
1. Thromboembolic Disorders and Other Vascular Problems a. Myocardial Infarction An increased risk of myocardial infarction has been attributed to oral contraceptive use.
This risk is primarily in smokers or women with other underlying risk factors for coronary artery disease such as hypertension, hypercholesterolemia, morbid obesity, and diabetes. The relative risk of heart attack for current oral contraceptive users has been estimated to be two to six. 4 to 10 The risk is very low under the age of 30.
Smoking in combination with oral contraceptive use has been shown to contribute substantially to the incidence of myocardial infarctions in women in their mid-thirties or older with smoking accounting for the majority of excess cases. 11 Mortality rates associated with circulatory disease have been shown to increase substantially in smokers, especially in those 35 years of age and older, and in nonsmokers over the age of 40 among women who use oral contraceptives. (See Figure 1 ).
Figure 1. Circulatory Disease Mortality Rates per 100,000 Women-Years by Age, Smoking Status and Oral Contraceptive Use (Adapted from P.M. Layde and V.
Beral, ref. #12.) Oral contraceptives may compound the effects of well-known risk factors, such as hypertension, diabetes, hyperlipidemias, age and obesity. 13 In particular, some progestogens are known to decrease HDL cholesterol and cause glucose intolerance, while estrogens may create a state of hyperinsulinism. 14 to 18 Oral contraceptives have been shown to increase blood pressure among users (see Section 10 in WARNINGS).
Similar effects on risk factors have been associated with an increased risk of heart disease. Oral contraceptives must be used with caution in women with cardiovascular disease risk factors. Figure 1 b.
Throm…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Post Marketing Experience Five studies that compared breast cancer risk between ever-users (current or past use) of COCs and never-users of COCs reported no association between ever use of COCs and breast cancer risk, with effect estimates ranging from 0.90 - 1.12 (Figure X2). Three studies compared breast cancer risk between current or recent COC users (<6 months since last use) and never users of COCs (Figure X2). One of these studies reported no association between breast cancer risk and COC use.
The other two studies found an increased relative risk of 1.19 - 1.33 with current or recent use. Both of these studies found an increased risk of breast cancer with current use of longer duration, with relative risks ranging from 1.03 with less than one year of COC use to approximately 1.4 with more than 8-10 years of COC use. RR = relative risk; OR = odds ratio; HR = hazard ratio. “ever COC” are females with current or past COC use; “never COC use” are females that never used COCs.
An increased risk of the following serious adverse reactions has been associated with the use of oral contraceptives (See WARNINGS ). Thrombophlebitis and venous thrombosis with or without embolism Arterial thromboembolism Pulmonary embolism Myocardial infarction Cerebral hemorrhage Cerebral thrombosis Hypertension Gallbladder disease Hepatic adenomas or benign liver tumors There is evidence of an association between the following conditions and the use of oral contraceptives: Mesenteric thrombosis Retinal thrombosis The following adverse reactions have been reported in patients receiving oral contraceptives and are believed to be drug-related: Nausea Vomiting Gastrointestinal symptoms (such as abdominal cramps and bloating) Breakthrough bleeding Spotting Change in menstrual flow Amenorrhea Temporary infertility after discontinuation of treatment Edema Melasma which may persist Breast changes: tenderness, enlargement, secretion Change in weight (increase or decrease) Change in cervical erosion and secretion Diminution in lactation when given immediately postpartum Cholestatic jaundice Migraine Allergic reaction, including rash, urticaria, angioedema Mental depression Reduced tolerance to carbohydrates Vaginal candidiasis Change in corneal curvature (steepening) Intolerance to contact lenses The following adverse reactions have been reported in users of oral contraceptives and a causal association has been neither confirmed nor refuted: Pre-menstrual syndrome Cataracts Changes in appetite Cystitis-like syndrome Headache Nervousness Dizziness Hirsutism Loss of scalp hair Erythema multiforme Erythema nodosum Hemorrhagic eruption Vaginitis Porphyria Impaired renal function Hemolytic uremic syndrome Acne Changes in libido Colitis Budd-Chiari Syndrome The following adverse reactions were also reported in clinical trials or during post-marketing experience: Gastrointestinal Disorders: diarrhea, pancreatitis; Musculoskeletal and Connective Tissue Disorders: muscle spasms, back pain; Reproductive System and Breast Disorders vulvovaginal pruritus , pelvic pain, dysmenorrhea, vulvovaginal dryness; Psychiatric Disorders: anxiety, mood swings, mood altered; Skin and Subcutaneous Tissue Disorders: pruritus, photosensitivity reaction; General Disorders and Administration Site Conditions: edema peripheral, fatigue, irritability, asthenia, malaise; Neoplasms Benign, Malignant, and Unspecified (Including Cysts and Polyps): breast cancer, breast mass, breast neoplasm, cervix carcinoma; Immune System Disorders: anaphylactic/anaphylactoid reaction ; Hepatobiliary Disorders: hepatitis, cholelithiasis. figure-2
🔄 Drug Interactions ▾
8. Drug Interactions Consult the labeling of concurrently-used drugs to obtain further information about interactions with hormonal contraceptives or the potential for enzyme alterations. Effects of Other Drugs on Combined Hormonal Contraceptives Substances decreasing the plasma concentrations of COCs and potentially diminishing the efficacy of COCs Drugs or herbal products that induce certain enzymes, including cytochrome P450 3A4 (CYP3A4), may decrease the plasma concentrations of COCs and potentially diminish the effectiveness of CHCs or increase breakthrough bleeding.
Some drugs or herbal products that may decrease the effectiveness of hormonal contraceptives include phenytoin, barbiturates, carbamazepine, bosentan, felbamate, griseofulvin, oxcarbazepine, rifampicin, topiramate, rifabutin, rufinamide, aprepitant, and products containing St. John's wort. Interactions between hormonal contraceptives and other drugs may lead to breakthrough bleeding and/or contraceptive failure.
Counsel women to use an alternative method of contraception or a back-up method when enzyme inducers are used with CHCs, and to continue back-up contraception for 28 days after discontinuing the enzyme inducer to ensure contraceptive reliability. Substances increasing the plasma concentrations of COCs Co-administration of atorvastatin or rosuvastatin and certain COCs containing EE increase AUC values for EE by approximately 20 to 25%. Ascorbic acid and acetaminophen may increase plasma EE concentrations, possibly by inhibition of conjugation.
CYP3A4 inhibitors such as itraconazole, voriconazole, fluconazole, grapefruit juice, or ketoconazole may increase plasma hormone concentrations. Human immunodeficiency virus (HIV)/ Hepatitis C virus (HCV) protease inhibitors and non-nucleoside reverse transcriptase inhibitors Significant changes (increase or decrease) in the plasma concentrations of estrogen and/or progestin have been noted in some cases of co-administration with HIV protease inhibitors (decrease [e.g., nelfinavir, ritonavir, darunavir/ritonavir, (fos) amprenavir/ritonavir, lopinavir/ritonavir, and tipranavir/ritonavir] or increase [e.g., indinavir and atazanavir/ritonavir]) /HCV protease inhibitors (decrease [e.g., boceprevir and telaprevir]) or with non-nucleoside reverse transcriptase inhibitors (decrease [e.g., nevirapine] or increase [e.g., etravirine]).
Concomitant Use with HCV Combination Therapy – Liver Enzyme Elevation Do not co-administer norethindrone and ethinyl estradiol tablets with HCV drug combinations containing ombitasvir/ paritaprevir/ritonavir, with or without dasabuvir, due to potential for ALT elevations (see WARNINGS, Risk of Liver Enzyme Elevations with Concomitant Hepatitis C Treatment). Colesevelam : Colesevelam, a bile acid sequestrant, given together with a combination oral hormonal contraceptive, has been shown to significantly decrease the AUC of EE.
A drug interaction between the contraceptive and colesevelam was decreased when the two drug products were given 4 hours apart. Effects of Combined Hormonal Contraceptives on Other Drugs COCs containing EE may inhibit the metabolism of other compounds (e.g., cyclosporine, prednisolone, theophylline, tizanidine, and voriconazole) and increase their plasma concentrations. COCs have been shown to decrease plasma concentrations of acetaminophen, clofibric acid, morphine, salicylic acid, temazepam and lamotrigine.
Significant decrease in plasma concentration of lamotrigine has been shown, likely due to induction of lamotrigine glucuronidation. This may reduce seizure control; therefore, dosage adjustments of lamotrigine may be necessary. Women on thyroid hormone replacement therapy may need increased doses of thyroid hormone because serum concentrations of thyroid-binding globulin increases with use of COCs.
🤰 Pregnancy ▾
11. Pregnancy Pregnancy Category X See CONTRAINDICATIONS and WARNINGS .
🧒 Pediatric Use ▾
13. Pediatric Use Safety and efficacy of norethindrone and ethinyl estradiol tablets has been established in women of reproductive age. Safety and efficacy are expected to be the same for postpubertal adolescents under the age of 16 and for users 16 years and older. Use of this product before menarche is not indicated.
🧓 Geriatric Use ▾
14. Geriatric Use This product has not been studied in women over 65 years of age and is not indicated in this population.
🆘 Overdosage ▾
OVERDOSAGE Serious ill effects have not been reported following acute ingestion of large doses of oral contraceptives by young children. Overdosage may cause nausea, and withdrawal bleeding may occur in females.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Combined Oral Contraceptives Combined oral contraceptives act by suppression of gonadotropins. Although the primary mechanism of this action is inhibition of ovulation, other alterations include changes in the cervical mucus (which increase the difficulty of sperm entry into the uterus) and the endometrium (which reduce the likelihood of implantation).
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Norethindrone and ethinyl estradiol tablets, USP 1 mg/0.035 mg are available in a blister pack (NDC 79929-007-05) containing 28 tablets, as follows: 21 Peach color, round, flat faced beveled edge, uncoated tablets debossed with "EL1" on one side and plain on other side, tablets may have mottled appearance on either of the surface (1 mg norethindrone USP and 0.035 mg ethinyl estradiol USP) and 7 green color, round, flat faced beveled edge, uncoated tablets debossed with "EL2" on one side and plain on other side, tablets may have mottled appearance on either of the surface containing inert ingredients.
The blister packs are available in boxes of 3 Store at 25°C (77°F); excursions permitted to 15°C to 30°C (59°F to 86°F). [See USP Controlled Room Temperature] Keep out of reach of children. ® The brands listed are trademarks of their respective owners. Manufactured For: Naari Pte Limited 36 Robinson Road, #13-01 City House, Singapore 068877 Issued December 2021
📦 Storage and Handling ▾
Store at 25°C (77°F); excursions permitted to 15°C to 30°C (59°F to 86°F). [See USP Controlled Room Temperature] Keep out of reach of children. ® The brands listed are trademarks of their respective owners. Manufactured For: Naari Pte Limited 36 Robinson Road, #13-01 City House, Singapore 068877 Issued December 2021
📋 Description ▾
COMBINED ORAL CONTRACEPTIVES Norethindrone and ethinyl estradiol tablets, USP are a combined oral contraceptive containing the progestational compound norethindrone USP and the estrogenic compound ethinyl estradiol USP. Norethindrone and ethinyl estradiol tablets, USP 1 mg/0.035 mg Each peach uncoated tablet contains 1 mg of norethindrone USP and 0.035 mg of ethinyl estradiol USP. Inactive ingredients include FD&C Yellow No.
6, lactose monohydrate, magnesium stearate and pregelatinized starch (maize). Each green tablet contains only inert ingredients, as follows: D&C Yellow No. 10 Lake, FD&C Blue No.
2 Lake, lactose monohydrate, magnesium stearate and pregelatinized starch (maize). The chemical name for norethindrone is 17-Hydroxy-19-nor-17α-pregn-4-en-20-yn-3-one, and for ethinyl estradiol is 19-Nor-17α-pregna-1,3,5(10)-trien-20-yne-3,17-diol. Their structural formulas are as follows: Chemical Structure
💬 Information for Patients ▾
INFORMATION FOR THE PATIENT See Patient Labeling printed below.