
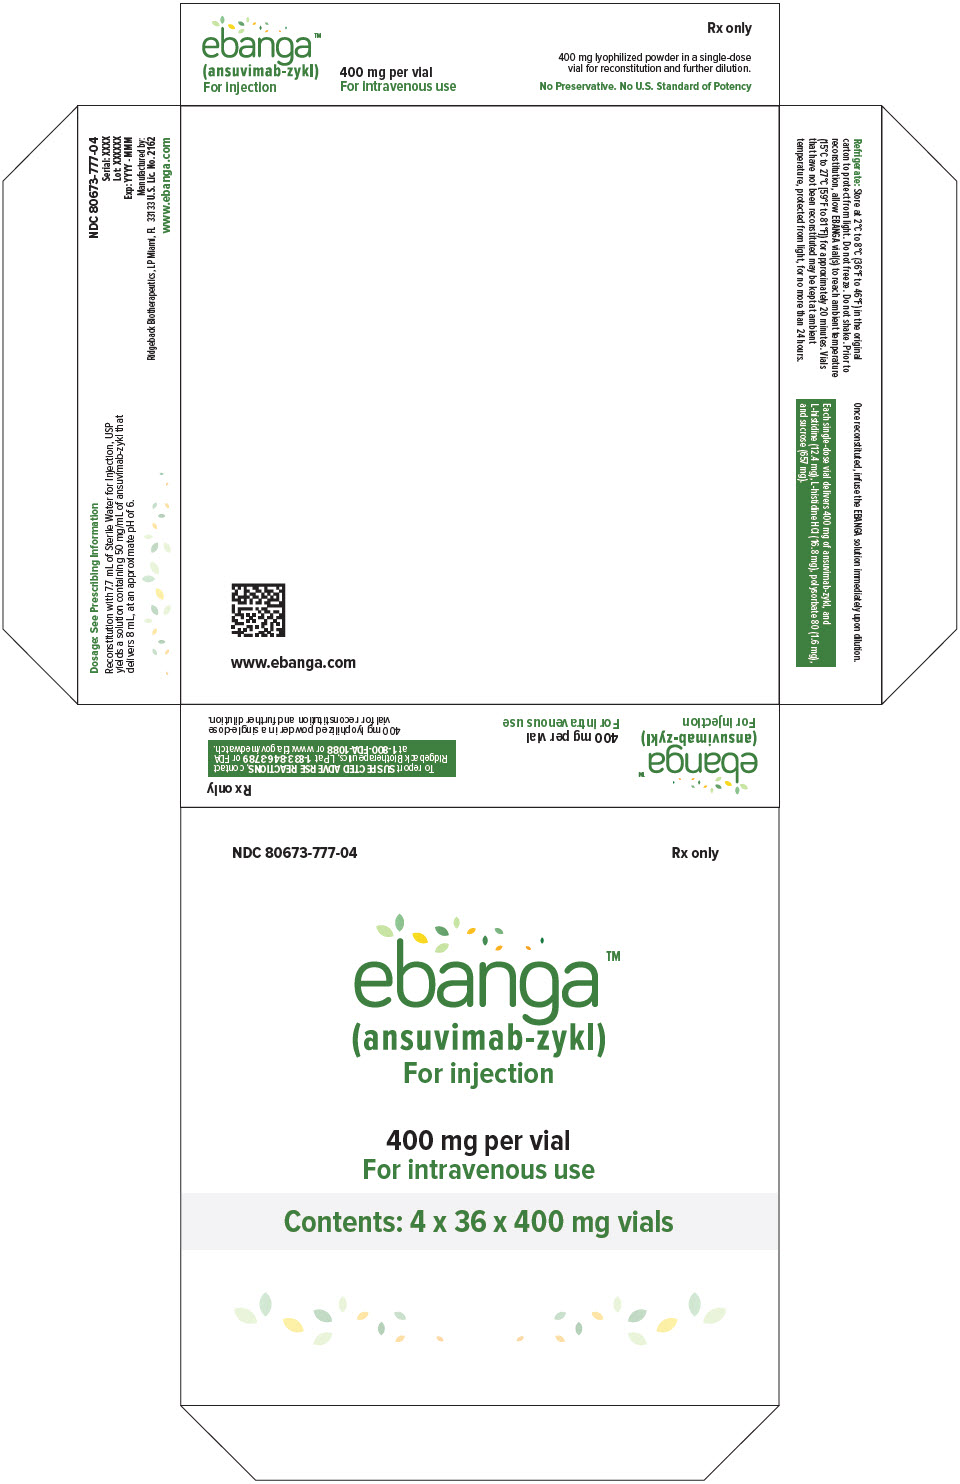
EBANGA ANSUVIMAB Kit
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Zaire Ebolavirus Glycoprotein-directed Antibody class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Ebanga is the brand name for ansuvimab — a lab-made antibody designed specifically to fight Ebola virus disease caused by the Zaire strain of Ebola. It's approved for adults, child...
- What exactly is Ebanga and what is it used for?
- Neither — it's given as an IV infusion directly into a vein, over about 60 minutes, once. You won't be preparing or taking anything at home. A healthcare team handles everything: d...
- How is Ebanga given — do I take a pill or get a shot?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Ebanga 400 mg/8mL 71655-0578-03 | Emergent | 36 vials | — | — | FDA listed | — |
| Ebangathis 80673-0777-04 | Ridgeback | 1 kit | — | — | Discontinued | — |
Where does this data come from?
⏳ Availability & biosimilar status
Biologics have no small-molecule generics; biosimilar competition is tracked in the FDA Purple Book.
Why the date isn’t exact: Biosimilar timing can change because patents may be challenged, settled, licensed, added or removed, and litigation can move the real date earlier or later.
🛈 What do these terms mean?
- Biologic patent
- A patent the reference product’s maker has publicly listed. A biosimilar generally can’t launch until these expire — unless they’re invalidated or resolved in a settlement.
- Reference-product exclusivity
- A flat 12 years of FDA market protection from the biologic’s first licensure (the BPCIA). No biosimilar can be licensed before it ends, regardless of patents.
- Interchangeable exclusivity
- The first interchangeable biosimilar can earn a period as the only interchangeable version (pharmacists can substitute it without the prescriber).
- Earliest biosimilar (LOE)
- The latest of all the dates above — the soonest a biosimilar can realistically reach the market. Litigation and settlements can move it earlier.
Biologics have no small-molecule “generics” — competition comes from FDA-licensed biosimilars, tracked in the FDA Purple Book.
| Code | What it grants | Expires |
|---|---|---|
| RefProduct | Reference-product exclusivity (12-year, BPCIA) — no biosimilar can be licensed before this date | Dec 21, 2032 |
Is there a biosimilar for this drug?
Why do different websites show different biosimilar dates?
Can a biosimilar launch before the last patent expires?
What does “current Purple Book estimate” mean?
What does “FDA listed” mean?
What does a patent or protection date mean here?
Where does this data come from?
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 80673-0777-01 | 1 CARTON in 1 BOX (80673-777-01) / 1 KIT in 1 CARTON * 36 VIAL, SINGLE-DOSE in 1 CARTON (80673-001-36) / 8 mL in 1 VIAL, SINGLE-DOSE (80673-001-01) | 2020-12-21 | Inactivated by FDA |
| 80673-0777-04 You're viewing this | 4 CARTON in 1 BOX (80673-777-04) / 1 KIT in 1 CARTON * 36 VIAL, SINGLE-DOSE in 1 CARTON (80673-001-36) / 8 mL in 1 VIAL, SINGLE-DOSE (80673-001-01) | 2020-12-21 | Inactivated by FDA |
| 80673-0777-08 | 8 CARTON in 1 BOX (80673-777-08) / 1 KIT in 1 CARTON * 36 VIAL, SINGLE-DOSE in 1 CARTON (80673-001-36) / 8 mL in 1 VIAL, SINGLE-DOSE (80673-001-01) | 2020-12-21 | Inactivated by FDA |
Pack size FAQ
What quantity is in NDC 80673-0777-04?
What NDC number is used to bill for this package of EBANGA ANSUVIMAB Kit?
🧭 About this NDC listing & data coverage
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
What does the discontinued status mean for this NDC?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE EBANGA is indicated for the treatment of infection caused by Zaire ebolavirus in adult and pediatric patients, including neonates born to a mother who is RT-PCR positive for Zaire ebolavirus infection [see Dosage and Administration (2.2) and Clinical Studies (14) ] . EBANGA™ (ansuvimab-zykl) is a Zaire ebolavirus glycoprotein (EBOV GP)-directed human monoclonal antibody indicated for the treatment of infection caused by Zaire ebolavirus in adult and pediatric patients, including neonates born to a mother who is RT-PCR positive for Zaire ebolavirus infection.
( 1 ) Limitation of Use The efficacy of EBANGA has not been established for other species of the Ebolavirus and Marburgvirus genera . Zaire ebolavirus can change over time, and factors such as emergence of resistance or changes in viral virulence could diminish the clinical benefit of antiviral drugs. Consider available information on drug susceptibility patterns for circulating Zaire ebolavirus strains when deciding whether to use EBANGA.
Limitations of Use: The efficacy of EBANGA has not been established for other species of the Ebolavirus and Marburgvirus genera. Zaire ebolavirus can change over time, and factors such as emergence of resistance, or changes in viral virulence could diminish the clinical benefit of antiviral drugs. Consider available information on drug susceptibility patterns for circulating Zaire ebolavirus strains when deciding whether to use EBANGA.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION The recommended dose of EBANGA for adult and pediatric patients is 50 mg/kg reconstituted, further diluted, and administered as a single intravenous infusion over 60 minutes. ( 2.1 , 2.2 ) See Full Prescribing Information for instructions on preparation, dilution and administration of EBANGA injection. ( 2.2 )
2.1Recommended Dosage for Adult and Pediatric Patients The recommended dosage of EBANGA is 50 mg/kg administered as a single intravenous (IV) infusion over 60 minutes. EBANGA must be reconstituted with Sterile Water for Injection, USP then further diluted in 0.9% Sodium Chloride Injection, USP or 5% Dextrose Injection, USP prior to IV infusion [see Dosage and Administration (2.2) ] . 2.2.
Preparation, Administration, and Storage Instructions EBANGA must be prepared and administered under the supervision of a health care professional. Reconstitution Instructions Aseptically reconstitute and further dilute EBANGA prior to IV infusion. Do not administer as an IV push or bolus.
More than one vial may be needed for a full dose. Calculate the dose (mg) based on the patient's actual weight in kg and the number of EBANGA vials required [see Dosage and Administration (2.1) ] . Prior to reconstitution, allow EBANGA vial(s) to reach ambient temperature (15°C to 27°C [59°F to 81°F]) for approximately 20 minutes.
If for any reason reconstitution cannot proceed immediately upon reaching ambient temperature, vials that have NOT been reconstituted may be kept at ambient temperature, protected from light, for no more than 24 hours. Immediately upon reaching ambient temperature, use a sterile 10 mL syringe and an 18-gauge needle to withdraw 7.7 mL of Sterile Water for Injection, USP. Insert the needle tip into the EBANGA vial.
Holding horizontally, angle the needle down at an approximate 45° angle, above the lyophilized powder, which has a cake-like appearance. Slowly inject the diluent along the wall of the vial and without any air to avoid foaming and bubbles. Gently swirl (do NOT shake) for approximately 10 seconds; then set the vial down to rest for at least 10 seconds.
Repeat until the cake is dissolved. This may take up to 20 minutes. Upon reconstitution, one vial delivers 8 mL of solution that is clear to slightly opalescent and colorless to slightly yellow containing 50 mg/mL of ansuvimab-zykl.
Do NOT administer and discard the vial if the reconstituted solution is discolored or contains visible particles. Dilute the EBANGA solution immediately upon reconstitution. If needed, the reconstituted solution may be stored refrigerated at 2°C to 8°C (36°F to 46°F), protected from light, for up to 4 hours.
This 4-hour window includes time required for further dilution and EBANGA solution should be infused immediately upon further dilution. Dilution Instructions Following reconstitution, EBANGA must be further diluted prior to IV infusion. Use an 18-20 gauge, 1-1.5" needle with an appropriately sized syringe up to 60 mL to perform the dilution steps.
Prepare the EBANGA IV dosing solution using an appropriately sized syringe up to 60 mL. For patients weighing ≥ 2 kg, prepare the diluent using either a latex-free, di-ethylhexylphthalate (DEHP)-free 0.9% Sodium Chloride Injection USP infusion bag, or latex-free, DEHP-free 5% Dextrose Injection USP infusion bag. For patients weighing 0.5 to < 2 kg use a pump-compatible syringe (Table 1).
For adult and pediatric patients, either 0.9% Sodium Chloride Injection, USP or 5% Dextrose Injection, USP can be used as the diluent. The total volume of the infusion solution to be administered is based on the patient's body weight and is specified in Table 1. For patients weighing 0.5 to < 2 kg: Use a 10 mL syringe compatible with the IV infusion pump.
Fill the 10 mL syringe with the appropriate amount of diluent (Table 1). Add the calculated volume of EBANGA to the 10 mL syringe (Table 1). Mix the diluted solution by gentle inversion (3 to 5 times) until admixed.
Do not shake.…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS For injection: 400 mg of ansuvimab-zykl, available as an off-white to white lyophilized powder in single-dose vial for reconstitution and further dilution. For injection: 400 mg lyophilized powder in a single-dose vial for reconstitution and further dilution. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None . None.
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hypersensitivity Reactions Including Infusion-Associated Events: Hypersensitivity reactions including infusion-associated events have been reported with EBANGA. These may include acute, life-threatening reactions during and after the infusion. Monitor patients and in the case of severe or life-threatening hypersensitivity reactions, discontinue the administration of EBANGA immediately and administer appropriate emergency care.
( 5.1 )
5.1Hypersensitivity Reactions Including Infusion-Associated Events Hypersensitivity reactions including infusion-associated events have been reported with EBANGA. These may include acute, life-threatening reactions during and after the infusion. Monitor all patients for signs and symptoms including, but not limited to, hypotension, chills and elevation of fever, during and following EBANGA infusion.
In the case of severe or life-threatening hypersensitivity reactions, discontinue the administration of EBANGA immediately and administer appropriate emergency care [see Adverse Reactions (6.1) ]. Infusion could not be completed in 1% of subjects who received EBANGA due to infusion-associated adverse events. The rate of infusion of EBANGA may be slowed or interrupted if the patient develops any signs of infusion-associated events or other adverse events [see Adverse Reactions (6.1) ].
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: Hypersensitivity Reactions Including Infusion-Associated Events [see Warnings and Precautions (5.1) ] The most frequently reported adverse events (≥ 5%) after administration of EBANGA were pyrexia, tachycardia, diarrhea, vomiting, hypotension, tachypnea, and chills. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Ridgeback Biotherapeutics, LP at 1-833-846-3789 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice. Overall, 424 adult and pediatric subjects with Zaire ebolavirus infection received EBANGA in one clinical trial and as part of an expanded access program during the 2018 Zaire ebolavirus outbreak in the Democratic Republic of Congo (DRC). In the PALM trial, the safety of EBANGA was evaluated in a multi-center, open-label, randomized controlled trial, in which 173 subjects (119 adults and 54 pediatric subjects) with confirmed Zaire ebolavirus infection received EBANGA as a single 50 mg/kg IV infusion and 168 subjects received an investigational control [see Clinical Studies (14) ] .
All subjects received optimized standard of care treatment (oSOC). The median age of the study population that received EBANGA was 26 years (range: 1 day to 85 years). Fifty-five percent (55%) of enrolled subjects were female and 45% were male.
During the same outbreak, 251 subjects (173 adults and 78 pediatric subjects) with laboratory-confirmed Zaire ebolavirus infection received EBANGA under an expanded access program; 57% of whom were female and 43% of whom were male. Ages ranged from 6 days to 80 years, with a median age of 25 years. Common Adverse Events Table 2 summarizes the adverse events that were reported in the PALM trial from a pre-defined list of signs and symptoms that occurred during EBANGA infusion.
The evaluation of adverse events in subjects who received EBANGA may have been confounded by the signs and symptoms of the underlying Zaire ebolavirus infection. Twenty nine percent (n=51) of subjects who received EBANGA in the PALM Trial experienced a pre-specified infusion-related adverse event. The most common pre-specified infusion-related adverse event reported in at least 10% of subjects who received EBANGA was fever (Table 2).
The adverse event profile in adult and pediatric subjects treated with EBANGA was similar. Table 2: Adverse Events That Occurred During Infusion in >10% of Adult and Pediatric Subjects in the PALM Trial Adverse Event Adverse events in this table were reported on the day of infusion, and included signs and symptoms that occurred during or immediately after infusion EBANGA (N=173) % Control Investigational therapy administered as three separate infusions (N=168) % Pyrexia 17 58 Tachycardia 9 32 Diarrhea Adverse events that occurred during infusion but were not pre-specified.
9 18 Vomiting 8 23 Hypotension 8 31 Tachypnea 6 28 Chills The term chills includes other similar adverse events including rigors and tremors 5 33 Hypoxia , 3 11 The following pre-specified symptoms, which were assessed on a daily basis during admission while admitted to the treatment unit, were reported in ≥40% of subjects who received EBANGA: diarrhea, pyrexia, abdominal pain, and vomiting. Evaluation of these symptoms may have been confounded by the underlying Zaire ebolavirus infection. Discontinuation and Infusion Rate Adjustments Approximately 99% of subjects who received EBANGA in the PALM trial were able to complete their dose within one hour.
Two subjects who received EBANGA (1%) did not receive their complete infusion. In eight subjects (5%) the EBANGA infusion rate was decreased due to an AE [see Warnings and Precautions (5.1) ] . Selected Laboratory Abnormalities in the PALM Trial Table 3 presents sele…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Interaction with live vaccine indicated for prevention of Zaire ebolavirus infection: No vaccine interaction studies have been performed. EBANGA may reduce the efficacy of the live vaccine. The interval between administration of EBANGA therapy and live vaccination should be in accordance with current vaccination guidelines. ( 7.1 )
7.1Vaccine Interactions No vaccine-therapeutic interaction studies have been performed in human subjects using EBANGA. However, because of the potential for EBANGA to inhibit replication of a live vaccine virus indicated for prevention of Zaire ebolavirus infection and possibly reduce the efficacy of the vaccine, avoid the concurrent administration of a live vaccine during treatment with EBANGA. The interval between administration of EBANGA therapy and live vaccination should be in accordance with current vaccination guidelines.
The efficacy of EBANGA among subjects who reported receipt of a recombinant live vaccine prior to their enrollment in the PALM trial was similar to subjects who did not report receiving a vaccine prior to enrollment.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Patients infected with Zaire ebolavirus should be instructed not to breastfed due to the potential for Zaire ebolavirus transmission. ( 8.2 )
8.1Pregnancy Risk Summary Zaire ebolavirus infection is life-threatening for both the mother and fetus and treatment should not be withheld due to pregnancy (see Clinical Considerations ) . Available data from the PALM trial in which pregnant women with Zaire ebolavirus infection were treated with EBANGA demonstrate the high rate of maternal and fetal/neonatal morbidity consistent with published literature regarding the risk associated with underlying maternal Zaire ebolavirus infection. These data are insufficient to evaluate for a drug associated risk of major birth defects, miscarriage, or adverse maternal/fetal outcome.
Animal reproduction studies with ansuvimab-zykl have not been conducted. Monoclonal antibodies, such as EBANGA, are transported across the placenta; therefore, EBANGA has the potential to be transferred from the mother to the developing fetus. Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Maternal, fetal and neonatal outcomes are poor among pregnant women infected with Zaire ebolavirus .
The majority of such pregnancies result in maternal death with miscarriage, stillbirth, or neonatal death. Treatment should not be withheld due to pregnancy.
8.2Lactation Risk Summary The Centers for Disease Control and Prevention recommend that mothers with confirmed Zaire ebolavirus not breastfeed their infants to reduce the risk of postnatal transmission of Zaire ebolavirus infection. There are no data on the presence of ansuvimab-zykl in human or animal milk, the effects on the breastfed infant, or the effects on milk production. Maternal IgG is known to be present in human milk.
The effects of local gastrointestinal exposure and limited systemic exposure in the breastfed infant to ansuvimab-zykl are unknown.
8.4Pediatric Use The safety and effectiveness of EBANGA for the treatment of infection caused by Zaire ebolavirus have been established in pediatric patients from birth to less than 18 years of age. Use of EBANGA for this indication is supported by evidence from a multi-center, open label, randomized controlled trial of EBANGA in adults and pediatric subjects that included 54 pediatric subjects birth to less than 18 years of age, including neonates born to a mother who is RT-PCR positive for Zaire ebolavirus infection.
Of the total number of subjects administered EBANGA in the PALM trial, pediatric subjects (1 day to 17 years) accounted for 31% (n=54) of the study population in the PALM trial. The 28-day mortality and safety in adult and pediatric subjects treated with EBANGA were similar [see Adverse Reactions (6.1) , and Clinical Studies (14) ]. An additional 78 (31%) pediatric subjects from birth to less than 18 years of age received EBANGA in an expanded access program.
8.5Geriatric Use Clinical trials of EBANGA did not include sufficient numbers of subjects aged 65 and over to determine whether the safety profile of EBANGA is different in this population compared to younger subjects. Of the total number of subjects administered EBANGA in the PALM trial, 6 subjects (3%) were 65 years or older. The limited clinical experience has not identified differences in responses between the elderly and younger subjects.
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Zaire ebolavirus infection is life-threatening for both the mother and fetus and treatment should not be withheld due to pregnancy (see Clinical Considerations ) . Available data from the PALM trial in which pregnant women with Zaire ebolavirus infection were treated with EBANGA demonstrate the high rate of maternal and fetal/neonatal morbidity consistent with published literature regarding the risk associated with underlying maternal Zaire ebolavirus infection. These data are insufficient to evaluate for a drug associated risk of major birth defects, miscarriage, or adverse maternal/fetal outcome.
Animal reproduction studies with ansuvimab-zykl have not been conducted. Monoclonal antibodies, such as EBANGA, are transported across the placenta; therefore, EBANGA has the potential to be transferred from the mother to the developing fetus. Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Maternal, fetal and neonatal outcomes are poor among pregnant women infected with Zaire ebolavirus .
The majority of such pregnancies result in maternal death with miscarriage, stillbirth, or neonatal death. Treatment should not be withheld due to pregnancy.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of EBANGA for the treatment of infection caused by Zaire ebolavirus have been established in pediatric patients from birth to less than 18 years of age. Use of EBANGA for this indication is supported by evidence from a multi-center, open label, randomized controlled trial of EBANGA in adults and pediatric subjects that included 54 pediatric subjects birth to less than 18 years of age, including neonates born to a mother who is RT-PCR positive for Zaire ebolavirus infection.
Of the total number of subjects administered EBANGA in the PALM trial, pediatric subjects (1 day to 17 years) accounted for 31% (n=54) of the study population in the PALM trial. The 28-day mortality and safety in adult and pediatric subjects treated with EBANGA were similar [see Adverse Reactions (6.1) , and Clinical Studies (14) ]. An additional 78 (31%) pediatric subjects from birth to less than 18 years of age received EBANGA in an expanded access program.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical trials of EBANGA did not include sufficient numbers of subjects aged 65 and over to determine whether the safety profile of EBANGA is different in this population compared to younger subjects. Of the total number of subjects administered EBANGA in the PALM trial, 6 subjects (3%) were 65 years or older. The limited clinical experience has not identified differences in responses between the elderly and younger subjects.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Ansuvimab-zykl is a recombinant human monoclonal antibody with antiviral activity against Zaire ebolavirus [see Microbiology (12.4) ].
12.2Pharmacodynamics Ansuvimab-zykl exposure-response relationship and the time course of pharmacodynamic response is unknown.
12.3Pharmacokinetics Limited data from 18 healthy subjects 22 to 56 years of age suggests that the pharmacokinetic profile of ansuvimab-zykl is consistent with the profile of other IgG1 monoclonal antibodies. Pharmacokinetic data are not available for Zaire ebolavirus infected patients. Specific Populations The effect of age, renal impairment or hepatic impairment on the pharmacokinetics of ansuvimab-zykl is unknown.
12.4Microbiology Mechanism of Action EBANGA (ansuvimab-zykl) is a recombinant, human IgG1κ monoclonal antibody that binds to the glycan cap and inner chalice of the EBOV GP1 subunit. The epitope to which it binds is located within the receptor binding domain of EBOV consisting of amino acids LEIKKPDGS (GP residues 111–119). Ansuvimab-zykl binds EBOV GP without the mucin domain with a K D of 0.2 nM at pH 7.4 and 0.6 nM at pH 5.3 as measured by biolayer interferometry.
Ansuvimab-zykl blocks binding of EBOV GP1 to the Neiman Pick cell receptor 1 in host cells (IC 50 value of 0.09 μg/mL), inhibiting virus entry into the host cell. Ansuvimab-zykl exhibited Fc-mediated Antibody Dependent Cellular Cytotoxicity (ADCC) activity against cells expressing EBOV GP when effector cells were added. Antiviral Activity In a live virus plaque-reduction neutralization assay performed in Vero E6 cells, ansuvimab-zykl neutralized Zaire ebolavirus Mayinga with an EC 50 value of 0.06 µg/mL.
In an EBOV GP lentivirus infectivity assay using HEK293 cells, ansuvimab-zykl inhibited Zaire ebolavirus Mayinga with an EC 50 value of 0.09 μg/mL and Zaire ebolavirus Makona with an EC 50 value of 0.15 μg/mL. The ADCC activity of ansuvimab-zykl was assessed in EBOV GP-transduced and non-transduced HEK293T target cells in the presence of antibody with effector cells added at an effector-to-target cell ratio 1:50 and analyzed via flow cytometry. Ansuvimab-zykl mediated ADCC, with maximal activity observed at a mAb concentration of 0.03 μg/mL.
Treatment of Zaire ebolavirus infected rhesus macaques with a single IV dose of ansuvimab-zykl (50 mg per kg) generally protected infected animals from Zaire ebolavirus mediated death when drug was administered 5 days post-infection. Resistance No nonclinical or clinical studies evaluating resistance to ansuvimab-zykl have been conducted. The possibility of resistance to ansuvimab-zykl should be considered in patients who either fail to respond to therapy or who develop relapse of disease after an initial period of responsiveness.
Immune Response Interaction studies with recombinant live EBOV vaccines and EBANGA have not been conducted [see Drug Interactions (7.1) ] .
🧬 Mechanism of Action ▾
12.1Mechanism of Action Ansuvimab-zykl is a recombinant human monoclonal antibody with antiviral activity against Zaire ebolavirus [see Microbiology (12.4) ].
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED / STORAGE AND HANDLING How Supplied EBANGA (ansuvimab-zykl) for injection is supplied as a sterile, preservative-free, off-white to white lyophilized powder in a single-dose vial (NDC 80673-001-01) for reconstitution and further dilution. One primary carton (NDC 80673-001-36) contains thirty-six 400 mg vials packaged in a box containing either one primary carton (NDC 80673-777-01), four primary cartons (NDC 80673-777-04), or eight primary cartons (NDC 80673-777-08). Storage and Handling Store refrigerated at 2ºC to 8ºC (36ºF to 46ºF) in the original carton to protect from light.
Do not freeze. Do not shake. Prior to reconstitution, allow EBANGA vial(s) to reach ambient temperature (15°C to 27°C [59°F to 81°F]) for approximately 20 minutes.
If for any reason reconstitution cannot proceed immediately upon reaching ambient temperature, vials that have NOT been reconstituted may be kept at ambient temperature, protected from light, for no more than 24 hours. After reconstitution, if storage is needed, the entire storage time for the reconstituted solution in the vial and the diluted solution in the IV bag should be protected from light and limited to 4 hours refrigerated at 2°C to 8°C (36°F to 46°F) [see Dosage and Administration (2.2) ] . The expiration date for the product is available via a product-specific website with frequent update.
The Quick Response (QR) Code at the end of this leaflet is scannable via mobile phone and will direct the user to the EBANGA website. Users will be asked to register for authorized access to lot- specific information via the Lot No. printed on the box containing one, four, or eight 36-vial carton(s). Please access the website using the QR code provided.
Alternatively, please go to: www.EBANGA.com . Do not use EBANGA beyond the expiration date available via this website.
📦 Storage and Handling ▾
Storage and Handling Store refrigerated at 2ºC to 8ºC (36ºF to 46ºF) in the original carton to protect from light. Do not freeze. Do not shake.
Prior to reconstitution, allow EBANGA vial(s) to reach ambient temperature (15°C to 27°C [59°F to 81°F]) for approximately 20 minutes. If for any reason reconstitution cannot proceed immediately upon reaching ambient temperature, vials that have NOT been reconstituted may be kept at ambient temperature, protected from light, for no more than 24 hours. After reconstitution, if storage is needed, the entire storage time for the reconstituted solution in the vial and the diluted solution in the IV bag should be protected from light and limited to 4 hours refrigerated at 2°C to 8°C (36°F to 46°F) [see Dosage and Administration (2.2) ] .
The expiration date for the product is available via a product-specific website with frequent update. The Quick Response (QR) Code at the end of this leaflet is scannable via mobile phone and will direct the user to the EBANGA website. Users will be asked to register for authorized access to lot- specific information via the Lot No. printed on the box containing one, four, or eight 36-vial carton(s).
Please access the website using the QR code provided. Alternatively, please go to: www.EBANGA.com . Do not use EBANGA beyond the expiration date available via this website.
📋 Description ▾
11 DESCRIPTION Ansuvimab-zykl is a Zaire ebolavirus (EBOV) glycoprotein 1 (GP1)-directed recombinant, human IgG1 monoclonal antibody. Ansuvimab-zykl is produced in Chinese Hamster Ovary (CHO) cells by recombinant DNA technology and has an approximate molecular weight of 147 kDa. EBANGA (ansuvimab-zykl) for injection is a sterile, preservative-free, off-white to white lyophilized powder in a single-dose vial for IV use after reconstitution and dilution.
Each single-dose vial delivers 400 mg of ansuvimab-zykl, and L-histidine (12.4 mg), L-histidine HCl (16.8 mg), polysorbate 80 (1.6 mg), and sucrose (657 mg). After reconstitution with 7.7 mL of Sterile Water for Injection, USP, each vial delivers 8 mL of a clear and colorless to slightly yellow solution containing 50 mg/mL of ansuvimab-zykl, with an approximate pH of 6.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Hypersensitivity Reactions Including Infusion-Associated Events Inform patients that hypersensitivity reactions including infusion-associated events have been reported during and post-infusion with EBANGA and to immediately report if they experience any symptoms of systemic hypersensitivity reactions [see Warnings and Precautions (5.1) ]. Lactation Instruct patients with Zaire ebolavirus not to breastfeed because of the risk of passing Zaire ebolavirus to the baby [see Use in Specific Populations (8.2) ].